Costs of Rumination

Reading a recent study (A Alioto et al. J Pediatr 2017; 185: 155-9) reminded me of “My Cousin Vinny.”  In a crucial scene, Mona Lisa Vito (Marisa Tomei) proves that the accused killers were not the killers by identifying tire tread marks that were inconsistent with the defendants’ car simply by looking a photograph.

Similarly, the authors of this retrospective report highlight the extensive cost of that children undergo for evaluation of rumination when simple observation might suffice.

Key findings:

  • Consecutive patients (n=68, 2009-2015) admitted to their inpatient rumination treatment program had undergone an average of 8.8 tests at a cost of $19,795.
  • Few tests were beneficial. Most common tests were esophagogastroduodenoscopy, upper gastrointestinal series, and abdominal ultrasound scan.

Limitations:

  • The cohort is derived from a quaternary center
  • The number of tests may be underestimated as the tests were done by the referring center; thus, the authors were reliant on data provided to them

Other comments:

  • A good clinical history can suffice to establish the diagnosis. “Observing the patient eat and/or drink and then ruminate is perhaps even more useful.”
  • “We strongly suggest that if a patient meets the symptom-based criteria for rumination syndrome, no further diagnostic testing is warranted. That said, …various phenotypes of the syndrome may make the diagnosis less clear-cut” and some testing could be needed.
  • Rumination may be “symptomatic for over 2 years before the diagnosis is established” (Pediatrics 2003; 111: 158-62)

My take: Not every doctor is as good at doctoring as Vinny Gambini is at lawyering. That being said, the authors note “for patients who present with repeated effortless regurgitation and vomiting of food that begins soon after they eat or drink, is not preceded by retching, and does not occur during sleep, there are very few other diagnoses to be considered.”

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Omaha Beach 2017

Surgery for Reflux Works Best in Those Who Need it the Least

In a recent retrospective study (JT Krill et al. Clin Gastroenterol Hepatol 2017; 15: 675-81), the authors reinforce the notion that surgery works best for reflux patients whose symptoms respond best to medical therapy.

Background: In this study, 196 patients with normal anatomy were identified, though 81 had inadequate follow-up at 1 year.  This left 115 patients (median age ~52).  This study examined patients with typical reflux symptoms (regurgitation, heartburn) (n=79 of 115, 68.7%) and extraesophageal symptoms, like cough, hoarseness, and throat clearing (n=36 of 115, 31.3%).  It is noted that 2/3rds of those with extraesophageal symptoms had coexisting typical GERD symptoms.  Most patients had a Nissen fundoplication but some underwent a Toupet fundoplication.

Key findings:

  • 91.5% of those with typical reflux symptoms (who  had responded to medical therapy) were in remission at 1 year; in comparison, only 33.3% (P <.01) of those with extraesophageal symptoms along with poor response to acid suppression therapy exhibited remission following fundoplication.
  • “The severity of acid reflux on pH monitoring and larger hiatal hernia size were associated with a more favorable outcome at 12 months.”  All patients had either abnormal pH monitoring or endoscopic esophagitis prior to surgery.  Only those with severe reflux had increased likelihood of response to surgery.

Limitations: retrospective study, 81 of 196 patients were excluded due to lack of followup

My take: This study is consistent with other studies in suggesting that reflux surgery is less effective in those who do not respond to medical therapies and who have atypical symptoms.

Related blog post:

From Pitts Street Bridge, Mt Pleasant

Dilatation for Eosinophilic Esophagitis -Pediatric Data

The most recent data in adults has indicated that dilatation for eosinophilic esophagitis (EoE) likely does not have increased risk compare to esophageal dilatation for other causes.  A recent pediatric retrospective study (C Menard-Katcher et al. JPGN 2017; 64: 701-6) reaches a similar conclusion.

In this study over a 5-year period, there were 68 dilatations among 40 patients with EoE.

Dilatation was considered complete if a diameter of 15 mm (45 French) was reached or if a deep rent in the mucosa was evident; small (<0.5 cm) shallow rents were “not considered criteria for cessation of dilations.”

Methods:

  • In their institution, areas of narrowing >5 cm in length were typically treated with Maloney dilators and shorter narrowings were managed with balloon dilators (through the scope).
  • For Maloney bougie dilators, often dilations started at 24 French; typically 30 French if scope could traverse narrowing.
  • For balloon, often dilations started at 10 mm.  Fluoroscopy was often used at initial dilation (12 of 19).
  • 17 of 40 required more than one dilation in the study period

Some of the key findings:

  • Approximately 5% of their EoE patients needed dilations.
  • Patients with EoE who needed dilations were older than EoE patients who did not need this: 13.8 vs 8.2 years
  • Postoperative chest pain was most common adverse event, affecting 15% of dilations. In this small series, there were no perforations.
  • At this institution, half of the patients had dilation at their diagnostic endoscopy before starting EoE-specific therapy. However, as noted in their commentary, medical management may obviate the need for dilations.
  • Medical management consisted of “swallowed steroids (62%), dietary therapy (12%) or both (24%).”

My take: Overall, this study indicates that dilations are fairly safe in the EoE population. That being said, in my view, all dilations carry a small but significant risk.

Related blog posts:

Musee d’Orsay, Naissance de Venus, Alexandre Cabanel, 1863


Surgical Reset for Anti-TNF Therapy with Crohn’s Disease

A recent study (A Assa et al. Inflamm Bowel Dis 2017; 23: 791-97) indicates that after surgery, anti-TNFα treatment is worth another try.

In this retrospective study with 53 children, 18 had “pharmacodynamic failure” with anti-TNFα medications (PK group) and 35 were controls. “Phamacocynamic failure is characterized by either a lack of improvement of CD symptoms or  loss of response after initial improvement in the setting of adequate serum drug levels without ADAs” [antidrug antibodies].

Key findings:

  • Mean age at time of intestinal resection was 14.8 years
  • Median time from resection to anti-TNF initiation was 8 months
  • Compared to the control group, the PK group had similar response to anti-TNF therapy.   “Similar proportions of patients from both groups were in clinical remission on anti-TNF treatment after 12 months and at the end of follow-up (1.8 years)”
  • At 12 months, remission rates were 89% (PK) versus 88.5% (control)

The authors propose an explanation: “A plausible explanation for this finding is that in severely inflamed tissue with high inflammatory burden, local high levels of TNFα serves as a sink for anti-TNFα antibodies and that tissue injury and local hypoxia might further limit drug penetrance to its target.”

My take: This information is useful.  Many patients who have surgery may respond to anti-TNFα therapy subsequently.  The unanswered question: Could more frequent dosing of anti-TNFα therapy have averted surgery in some patients by overcoming areas of intense disease?


Pediatric Endoscopic Quality Metrics

A recent study (J Sheu et al. JPGN 2017; 64: 671-8 Full Text link (courtesy of JPGNonline twitter feed): Outcomes from Pediatric GI MOC Modules) examined outcomes associated with NASPGHAN sponsored web-based quality improvement activities. This study showed that these modules, designed for Maintenance of Certification (MOC) for American Board of Pediatrics, improved quality care outcomes. What I found most interesting were some of the quality metrics that were targeted.  Here are some of them:

  • Performance of time out
  • Documentation of duodenal biopsies (eg. location/number)
  • Documentation of prep quality
  • Communication of endoscopy report to primary care providers
  • Documentation of biopsy results to family within 1 week
  • % of procedures that resulted in change in management
  • % successful terminal ileum intubation

My take: While this study showed the potential utility of these MOC modules, the larger point is that if you set specific measurable goals, you have a good chance of improving performance.  This article is a good place to start when thinking about improving pediatric endoscopy quality.

Related blog posts:

I really don’t get modern art. This art (a collection of newspapers)  is from Centre Pompidou. Robert Gober “Newspaper” 1992


Celiac Disease Epidemic?

A recent prospective study (E Liu et al. Gastroenterol 2017; 152: 1329-36) reports a very high rate of celiac disease in Denver.

The authors collected data on HAL-DR, DQ genotypes in 31,766 infants.  Among the various genotypes, a total of 1339 were followed .for 20 years (starting in 1993). The key outcomes were development of celiac disease autoimmunity (CDA) indicated by persistence of anti-TTG IgA antibody for at least 3 months or development of celiac disease (CD) with biopsies showing at least Marsh 2 histologic lesions.  The authors weighted the genotypes based on their frequency in the population to develop estimates for the entire Denver population.

Key findings:

  • 66 (of 1339) developed both CD and CDA. Another 46 developed only CDA. In this group of 46, seropositivity reverted to normal in 21 (46%).
  • Cumulative incidence for CDA at 5, 10 and 15 yrs of age: 2.4%, 4.3%, and 5.1% respectively
  • Cumulative incidence for CD at 5, 10 and 15 yrs of age: 1.6%, 2.8%, and 3.1% respectively

In their discussion, the authors note that “the 3.1% cumulative incidence of CD in Denver by age 15 is the highest to date in North America and is consistent with the 3% prevalence reported in Sweden for 12 year olds born during an ‘epidemic’ thought to be the result of early introduction…of gluten.” This theory about the epidemic is has been discounted: “timing of gluten introduction is not likely a factor” though the quantity could be a factor.

My take: These rates of CD and CDA are very high; ongoing data to determine the frequency in other parts of the country are needed.  This high rate of CD is clearly bad news for a lot of people, excepting those with commercial interests in gluten free products.


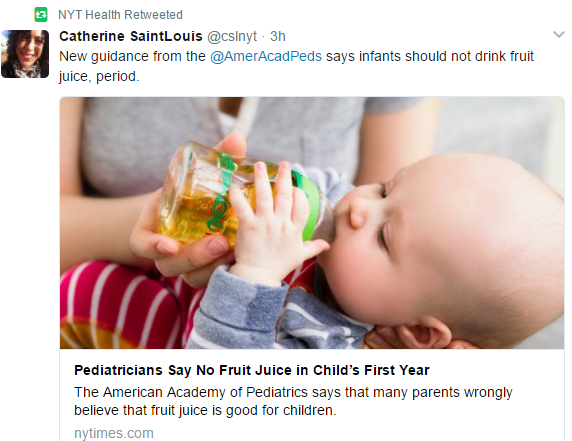
For 1-3 year old, AAP recommendation for maximum of 4 oz./day of 100% juice, and for 4-6 year olds a maximum of 6 oz/day.  For 7 years and older, AAP recommends a maximum of 8 oz/day

Brain-Gut Axis in 2017

“Brain–gut interactions and maintenance factors in pediatric gastroenterological disorders. Recommendations for clinical care.” B Reed-Knight et al. Clinical Practice in Pediatric Psychology, 2017; 5: 93-105.

A summary of this review article by Sharon Berry, PhD, ABPP, Past President, Society of Pediatric Psychology:

This review article describes the brain–gut axis as a means to increase understanding of how biological mechanisms implicated in a range of pediatric GI disorders interact with psychological and contextual factors to maintain GI symptoms and (b) provide practical ways for pediatricians and other healthcare providers to  incorporate a discussion of the brain–gut axis into patient education for pediatric GI disorders.

Biological mechanisms of the brain–gut axis including alterations in pain processing, the stress response system, and gut microbiome activity are reviewed. Psychosocial factors that contribute to or maintain disturbances in the brain–gut axis are discussed with implications for clinical assessment and intervention. The authors assert that a mutual understanding by patients, families, and providers alike of the relevant brain–gut interactions and the biopsychosocial model, in general, will serve as a foundation for successful delivery of and adherence to medical and psychological interventions. Important clinical conclusions include:

  • Early discussion of the brain-gut axis may reduce resistance to integrated behavioral or psychological treatment for pediatric gastroenterological disorders.
  • Sample visual aids and descriptive scripts are available within this review to guide discussions of the brain-gut axis with patients and families for a range of pediatric GI disorders.

My take: This article serves is a useful resource for pediatric psychologists to better understand the ideas of visceral hypersensitivity, stress response, and biological triggers (eg. gut microbiome, infections) for gastrointestinal disorders. Its discussion of biopsychosocial assessment and psychological interventions are helpful for pediatric gastroenterologists to understand the psychological approaches toward treatment.

Related blog posts:

NPR: Banana Diet for Celiac Disease

A recent report from NPR highlights a previous diet for celiac disease -the banana diet. While celiac disease had been discovered in the 1890s by Dr. Samuel Gee, the role of gluten was not understood until WWII.

NPR: Doctors Once Thought Bananas Cured Celiac Disease

Here’s an excerpt:

a high-calorie, banana-based diet [was] invented by Dr. Sidney Haas in 1924. The diet forbade starches but included numerous daily bananas, along with milk, cottage cheese, meat and vegetables…

Haas arrived at his banana diet through an honest error — one that, unfortunately, had serious repercussions for people with celiac disease. In his 1924 paper, he wrote of a town in Puerto Rico where “dwellers who eat much bread suffer from [celiac] sprue while the farmers who live largely on bananas never.”

Haas skipped over the role of wheat and focused instead on the exotic bananas, which he thought held curative powers…

But Haas’ honest error led to serious consequences. As the children recovered, wheat was reintroduced.

It was a Dutch pediatrician, Willem Karel Dicke, who first realized that wheat might be linked to celiac disease. He noticed that in the last few years of World War II, when bread was unavailable in the Netherlands, the mortality rate from celiac disease dropped to zero. In 1952, Dicke and his colleagues identified gluten as the trigger for celiac disease, and the gluten-free diet was born.


Vaccine for Celiac Disease

A recent study (KM Kemppainen et al. Clin Gastroenterol Hepatol 2017; 15: 694-702, editorial 703-5) showed that gastrointestinal infections can trigger celiac disease (CD) and that immunization with the rotavirus vaccine was protective against developing CD.

This study is part of the TEDDY study: The Environmental Determinants of Diabetes in the Young.  The TEDDY cohort involves more than 8000 children who are part of an international prospective cohort who carry genes (HLA-DR-DQ genotypes) with increased risk for diabetes and CD. In this particular group, the authors identified 6327 children who were 4 yrs old by March 2015.

Key Definition: CD autoimmunity (CDA) -children who tested positive for tTG IgA at their annual visit and remained persistently positive 3 months later

Key Findings:

  • Gastointestinal infections (n=13,881) but not respiratory infections (n=79,816) were associated with an increased risk of CDA.  CDA risk was increased within the 3 months of the GI infection.
  • 732 of 6327 (11.6%) developed CDA.  In this cohort, 318 underwent duodenal biopsy and 283 (90%) had biopsy indicative of CD (Marsh score >1). Thus, in their cohort, there is variability in the onset of CD from the onset of CDA.
  • Risk of CDA was reduced in children vaccinated against rotavirus and introduced to gluten before age 6 months (HR =0.57).
  • The exact risk depending on interaction with multiple factors including breastfeeding, HLA genotype, seasonality of birth, and timing of gluten introduction. Timing of infection plays a role as well, as earlier exposure to GI infections earlier in life was associated with a decreased risk of celiac disease.

This reference should be kept handy for vaccine advocates.  Not only can vaccines prevent infections, but they have now been shown to prevent an autoimmune disease (CD).  In addition, previous studies have shown that vaccines can prevent cancers, including hepatocellular carcinoma and cervical cancer.

My take (modified from editorial): This study “demonstrates the power of rigorously conducted prospective studies to reveal complex interactions among genetic and environmental factors.” In addition, this study shows that preventing rotavirus infection with vaccination lowers the risk of celiac disease.

Related blog posts:

SuperPoopers CCFA Team 2017

IBD Resources for Clinicians/IBD Tweets

Another website with a few useful resources:

  • Steroid taper calendar -helps develop a calendar (can use to print out or take a picture)
  • Imaging risk calculator -this is not that great.  In essence if you have a patient present to ER with a CRP of 1 mg/dL and ESR of 20, it states that risk of a complication like a perforation is “NOT LOW” and to consider imaging
  • IBD School Video collection -links to UM website

Note -therapeutic drug monitoring may be more useful in children due to their changing size.

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.