Nonsteroidal Analgesics and Risk of Empyema

A recent study (M Le Bourgeois et al. J Pediatr 2016; 175: 47-53) from 15 medical centers in France showed an association between nonsteroidal anti-inflammatory drugs (NSAIDs) and the development of empyema.

Methods: a case-control design with 83 cases of children with empyema and recent acute viral infection (w/in 15 days) and 83 controls who had recent acute viral infection but no emyema. Age range: 3 months-15 years.  To ascertain the underlying initial viral etiology, the investigators utilized molecular techniques and identified respiratory viruses in about half of both groups of children.

Key finding: Exposure to NSAIDs was associated with a modest increase in the rate of empyema (aOR 2.79).  The risk of empyema associated with NSAIDs was diminished if the  child had been prescribed an antibiotic.

My take: This study, by minimizing confounding factors, suggests that the casual use of NSAIDs during acute viral illnesses increases the chance of developing empyema.


Grinnell Glacier, Glacier Nat'l Park

Grinnell Glacier, Glacier Nat’l Park

 

World Congress 2016 Postgraduate Course

I’ve attached (with permission) the syllabus from the World Congress 2016 Postgraduate Course: 2016-world-congress-postgraduate-course-syllabus

screen-shot-2016-10-14-at-11-45-54-am

screen-shot-2016-10-14-at-11-46-04-am

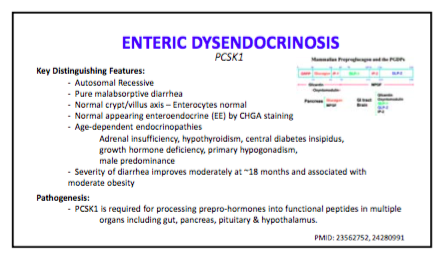
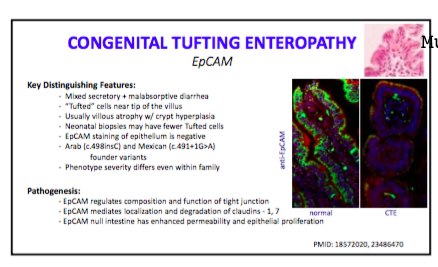
One lecture that I will highlight with a few slides is from Dr. Martin Martin (pg 53-62) which emphasizes a new model for evaluating neonatal intestinal failure/congenital diarrhea by using whole exome sequencing –see slides below.

Other pointers:

  • Pg 82.  Breastmilk associated with shorter duration of TPN dependence in short bowel syndrome
  • Pg 137. Look for vasculopathy (MRI/MRA) and renal disease in Alagille syndrome
  • Pg 152. Lactated ringer’s likely better in acute pancreatitis than normal saline.
  • Pg 171. If constipation at less than 1 year is untreated, >60% have issues with constipation at age 3.

screen-shot-2016-10-14-at-11-37-07-am screen-shot-2016-10-14-at-11-37-00-am screen-shot-2016-10-14-at-11-36-44-am screen-shot-2016-10-14-at-11-36-34-am screen-shot-2016-10-14-at-11-35-40-am


Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Total Pancreatectomy with Islet Autotransplantation for Refractory Recurrent Pancreatitis

A recent study (MD Bellin et al. Clin Gastroenterol Hepatol 2016; 14: 1317-23) describes the use of Total Pancreatectomy with Islet Autotransplantation (TPIAT) in 49 patients (mean age 32.8 years).  This study included 6 children.

All of these patients met strict criteria for recurrent acute pancreatitis and lacked imaging or functional evidence for chronic pancreatitis.  All 49 required narcotics for pain management prior to TPIAT.

The surgical technique for TPIAT is well-described in the report.  Patients underwent total pancreatectomy, splenectomy, cholecystectomy and partial duodenectomy with continuity restored via doudenoduodenostomy or Roux-en-Y duodenojejunostomy.  The islets were isolated and then infused intraportally.

Key findings:

  • At 1 year following TPIAT, 22 (46%) reported no use of narcotic pain medications.
  • Health-related quality of life scores improved (see Figure 3)
  • Diabetes is a common post-op concern.  Approximately half were insulin-independent at 1 and 2 years out from surgery, with one-third remaining so at 5 years.
  • Histopathology was consistent with chronic pancreatitis in 37 (76%) indicating that current imaging/functional features do not reliably identify chronic pancreatitis with adequate sensitivity.

In the discussion, the authors note the selected patients, due to having normal caliber pancreatitis ducts, were not candidates for surgical drainage procedures like the Puestow procedure.  They also note that the Puestow procedure can compromise later islet cell isolation.

My take: TPIAT is an important option in those with severe recurrent or persistent pancreatitis disease.

Related blog posts:

Quiet spot on Univ Virginia Grounds

Quiet spot on Univ Virginia Grounds

Smart Doctors Still Better Than Smartphones

The LA Times has reviewed a recent study: JAMA Intern Med. Published online October 10, 2016. doi:10.1001/jamainternmed.2016.6001

LA Times: Your phone may be smart, but your doctor still know more than an app

An excerpt:

In a head-to-head comparison, real human physicians outperformed a collection of 23 symptom-checker apps and websites by a margin of more than 2 to 1, according to a report published Monday in the journal JAMA Internal Medicine.

Even when the contestants got three chances to figure out what ailed a hypothetical patient, the diagnostic software lagged far behind actual doctors. Indeed, the apps and websites suggested the right diagnosis only slightly more than half of the time, the report says…

Though the humans trounced the computers across the board, there were situations in which doctors did a particularly good job of naming the correct diagnosis first. For instance, their margin in cases with common conditions was 70% to 38%. In cases with uncommon conditions, it grew to 76% to 28%.

My take:  According to the study, doctors still beat computer symptom algorithms.  But, there may be bias: “three of the study authors are doctors, and none are apps.”  At the same time, there is a likelihood of increased collaboration between physicians and computers.

NPR: Computerized Assistant for Cancer

screen-shot-2016-10-12-at-9-57-44-pm

Briefly Noted: Inflammatory Bowel Disease Updates

Gut Microbial Diversity is Reduced in Smokers with Crohn’s Disease. JL Opstelten et al. Inflamm Bowel Dis 2016; 22: 2070-77.  This study compared stools from 21 nonsmoking patients with Crohn’s disease (CD) with 21 smokers with CD.  Smoking was accompanied by a reduced relative abundance of multiple genera.  My take: It is unclear whether smoking’s effect on the microbiome directly contributes to worsened outcomes or whether the changes in the microbiome are only an epiphenomenon.  Regardless, smoking increases the likelihood of worse outcomes in CD.

A Systematic Review on Infliximab and Adalimumab Drug Monitoring Levels, Clinical Outcomes and Assay. F Silva-Ferreira et al. Inflamm Bowel Dis 2016; 22: 2289-2301. This review selected 20 studies from an initial query of 1654 articles. Key points:

  • Different studies are difficult to compare due to distinct assays with different limitations. Thus, specific cutoffs are based on the specific assay used.
  • The authors state that proactive monitoring may be helpful at week 6, 14, 30 and 54 for infliximab.  They recommend checking infliximab level and antidrug antibodies in those with loss of response, mucosal ulceration or elevated biomarkers (eg. CRP, Fecal calprotectin).

Molecular Panels for Identifying Etiology with Acute GI Symptoms

A recent study (MR Nicholson et al. J Pediatr 2016; 176; 50-6) examined the use of multiplex molecular testing to determine the etiology of acute gastroenteritis in children.  It is interesting that little has been published about this increasingly common practice of sending a 12 to 15 panel PCR assay when faced with acute GI symptoms, mainly diarrhea.

This study was a prospective population-based study of children <6 years with acute gastroenteritis (2008-2011).

Findings:

  • 70.4 % (152/216) samples tested positive for a pathogen, with norovirus the most frequent (n=78, 36.1%). Clostridium difficile was next at 16.2% (n=35).
  • 22.7% (n=49) tested positive for more than 1 pathogen including 25 with a C difficile detection
  • In this study, the authors noted C difficile colonization in 8% of healthy children aged 0-51 months and in 14% of children <12 months

Implications of this study and this technology:

  • Prior to this technology, traditional approaches typically identified less than 15% of the cases of acute gastroenteritis.  Thus, this new technology increases the likelihood of a definitive diagnosis.
  • Multiple pathogens, particularly with C difficile, illustrate how this new technology will present some difficulties with interpretation.  C difficile has very high rates of colonization in infants (anywhere from 25-80%) without AGE symptoms and lower rates of colonization in toddlers.  High colonization/detection has been noted in inflammatory bowel disease patients (17%) and pediatric oncology patients (30-55%).
  • For C difficile, molecular testing is much less likely to correlate with clinical disease than toxin-based assays. “A recent study in adults found that virtually all CDI-related complications occurred in patients with a positive toxin immunoassay.” (JAMA Intern Med 2015; 175: 1792-801)

My take: These panels are helpful in identifying infectious etiologies of AGE and may help prevent unnecessary endoscopic procedures.  Due to their limitations, careful selection of which patients to test and cautious interpretation of the results are needed.

Related blog posts:

Sunset from Bar Harbor, ME

Sunset from Bar Harbor, ME