DA Patel et al. Gastroenterol 2022; 162: 1617-1634. Open Access: Esophageal Motility Disorders: Current Approach to Diagnostics and Therapeutics
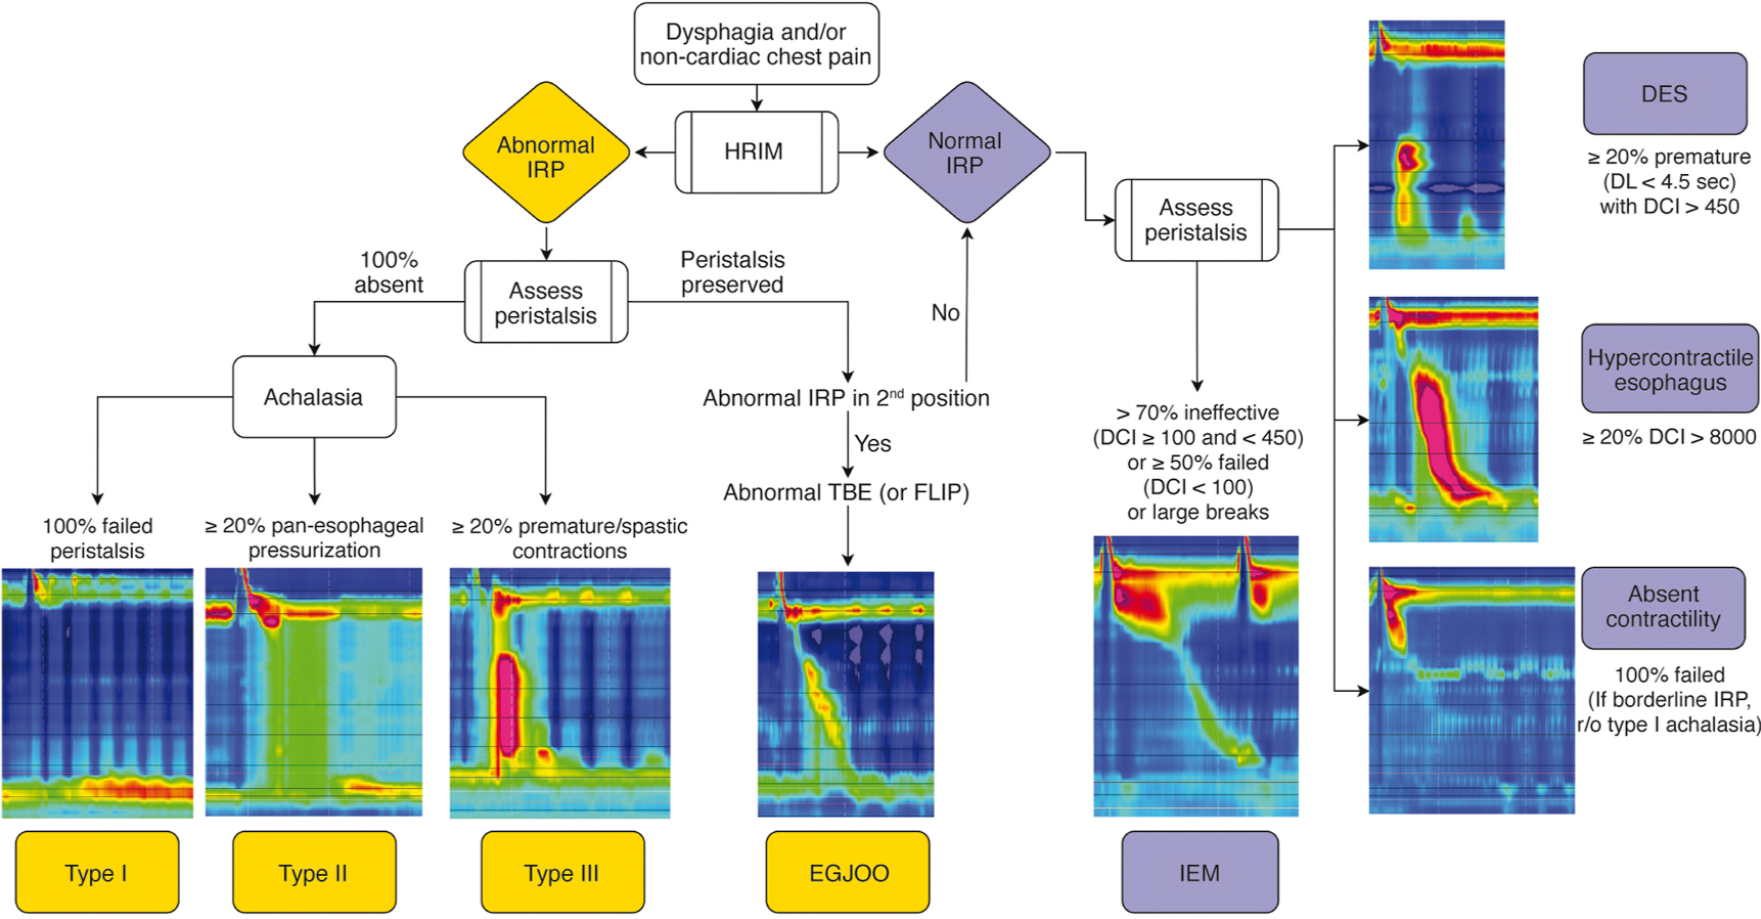
based on CC v4.0. HRIM, high-resolution impedance manometry
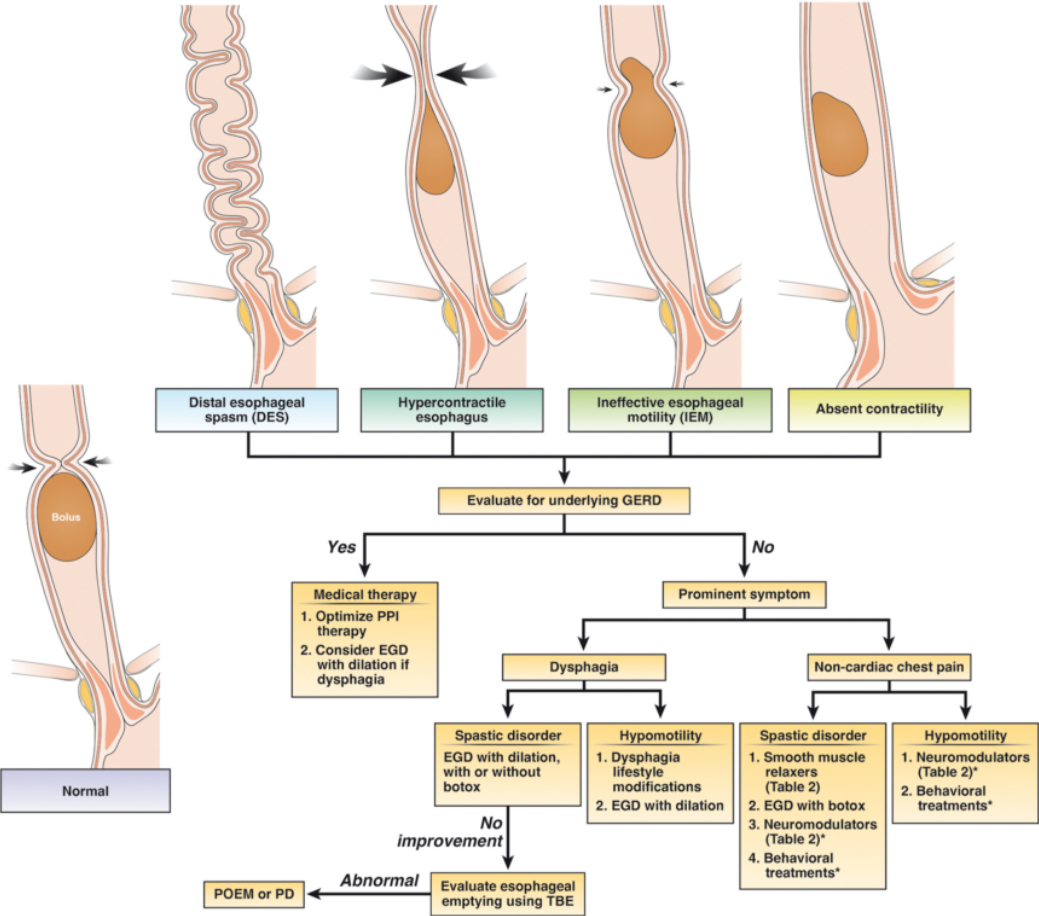
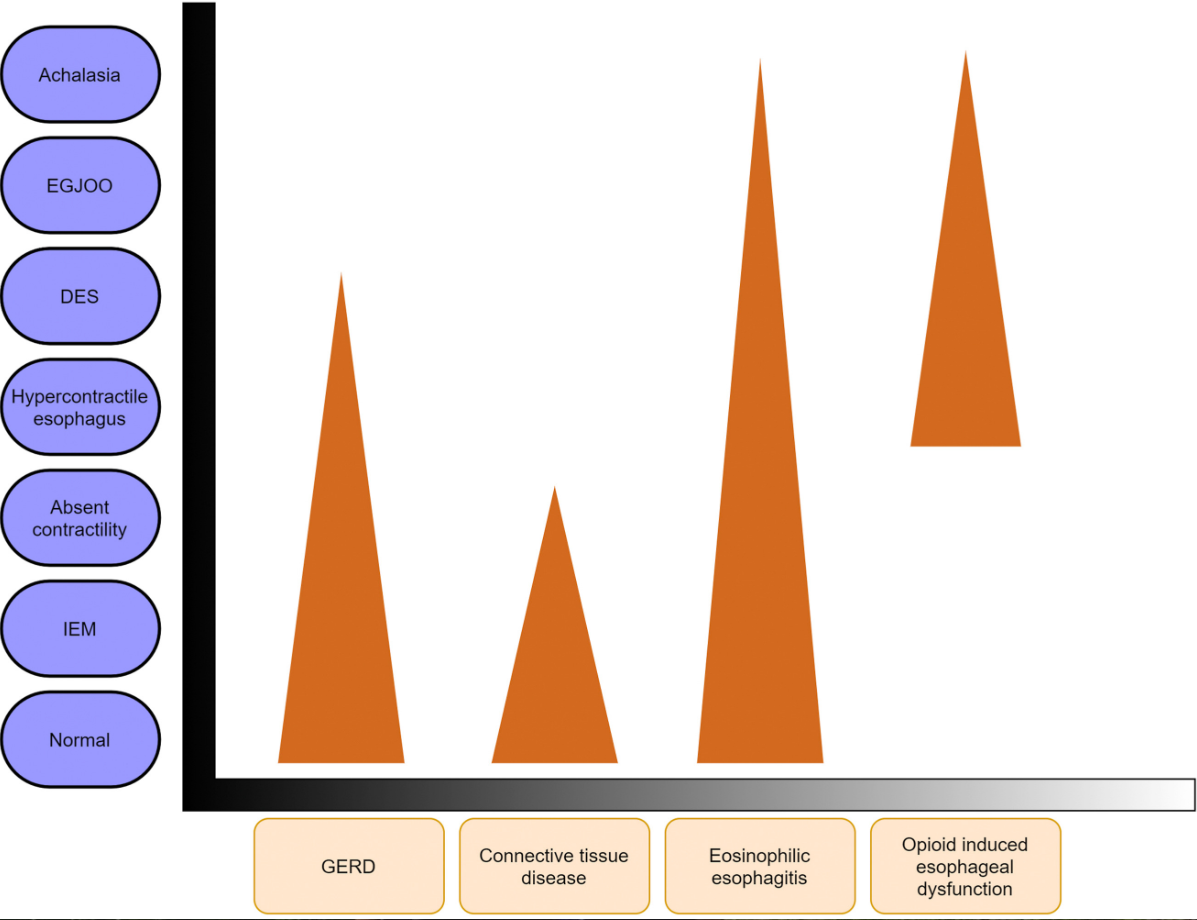

DA Patel et al. Gastroenterol 2022; 162: 1617-1634. Open Access: Esophageal Motility Disorders: Current Approach to Diagnostics and Therapeutics
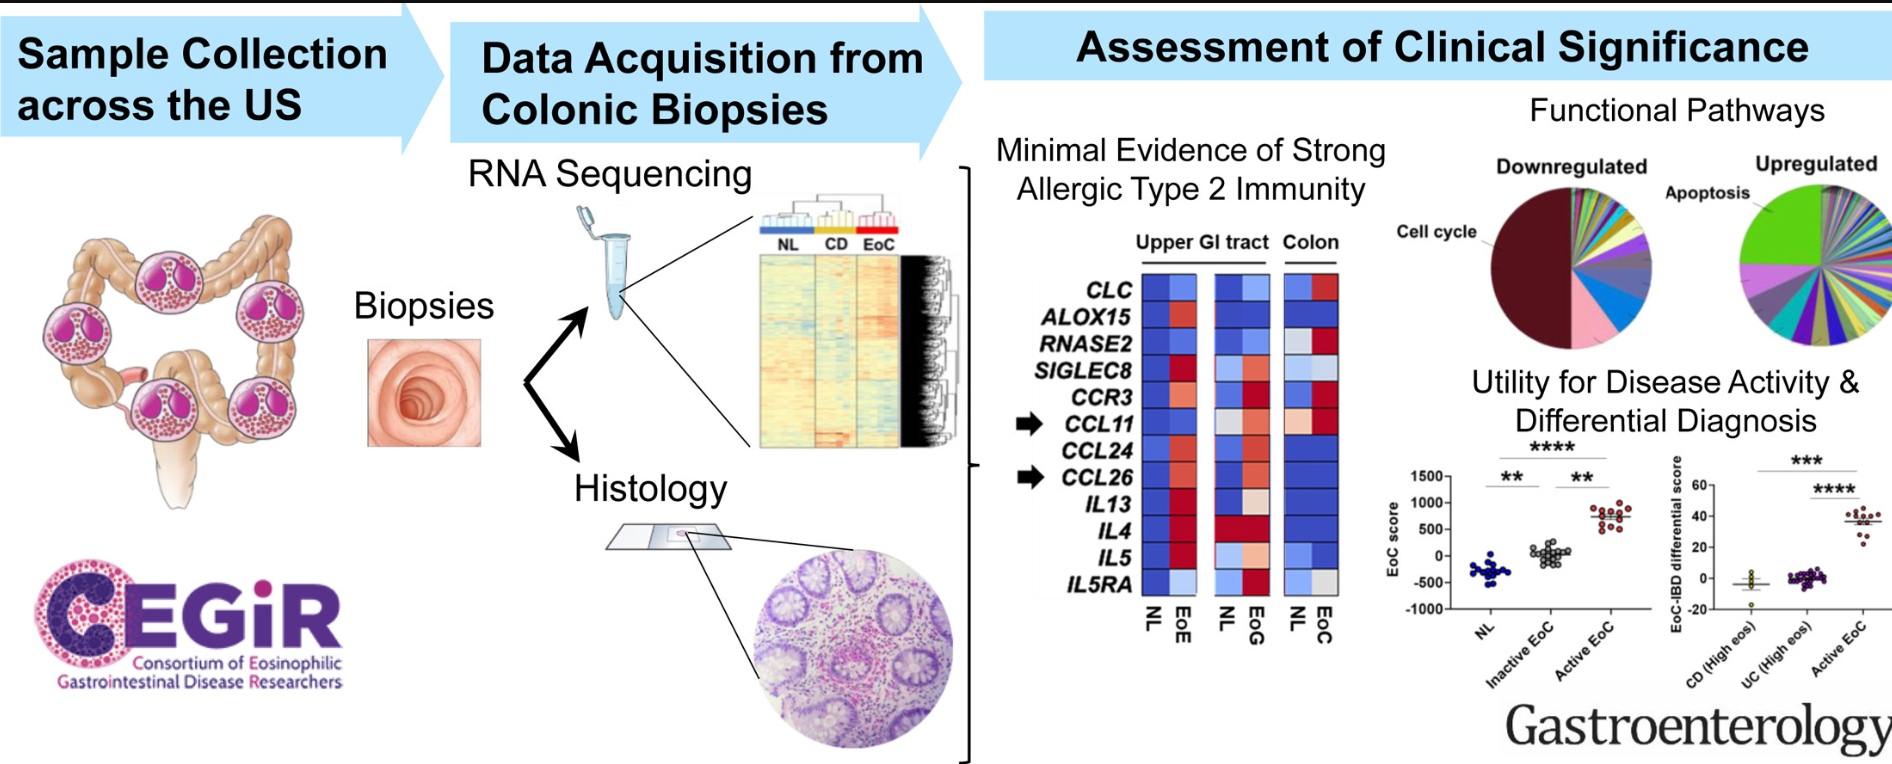
T Shoda et al. Gastroenterol 2022; 162: 1635-1642. Open Access: Evaluating Eosinophilic Colitis as a Unique Disease Using Colonic Molecular Profiles: A Multi-Site Study
Methods: Subjects with EoC (n = 27) and controls (normal [NL, n = 20], Crohn’s disease [CD, n = 14]) were enrolled across sites associated with the Consortium of Eosinophilic Gastrointestinal Disease Researchers. EoC was diagnosed as colonic eosinophilia (ascending ≥100, descending ≥85, sigmoid ≥65 eosinophils/high-power field) with related symptoms. Colon biopsies were subjected to RNA sequencing.
Key findings:
My take: The study indicates that eosinophilic colitis is likely unrelated to other eosinophilic GI disease and is likely unrelated to inflammatory bowel disease.
Related blog posts:
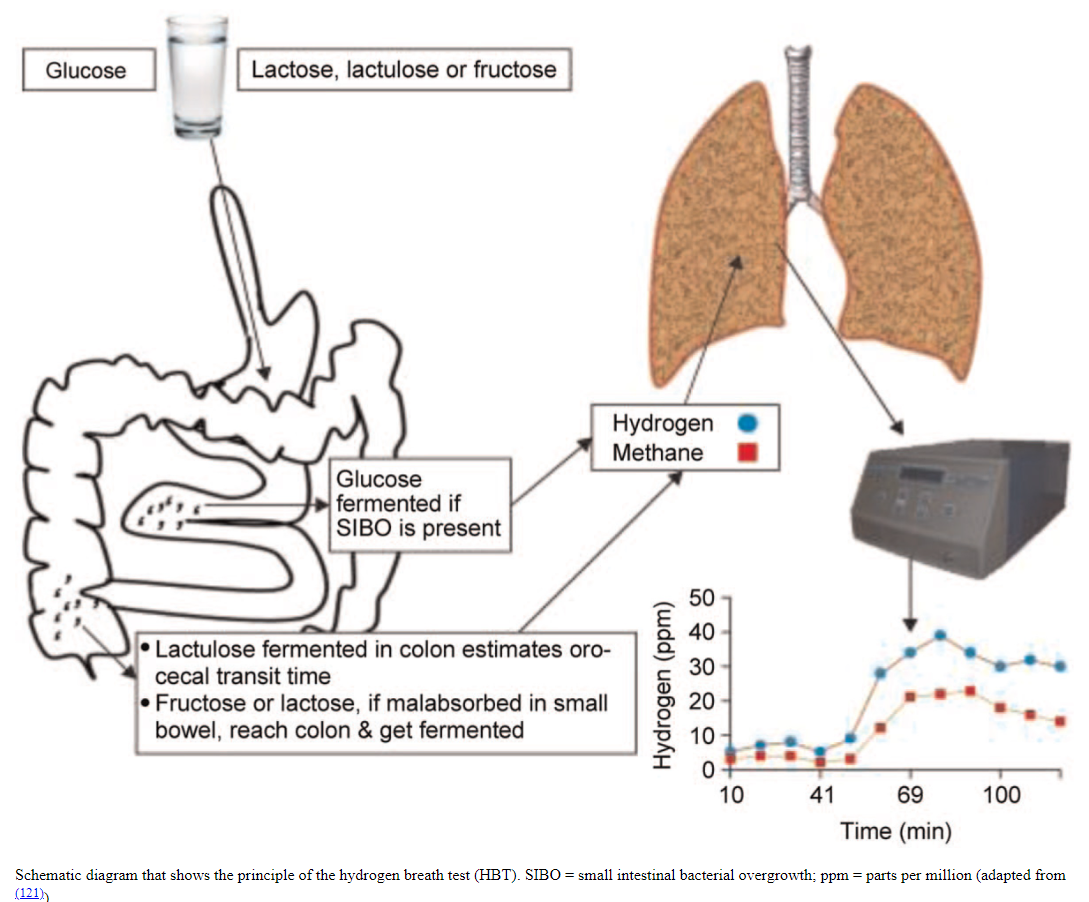
IJ Broekaert et al. JPGN 2022; 74: 123-127. Open access: An ESPGHAN Position Paper on the Use of Breath Testing in Paediatric Gastroenterology
This is a good article which provides pediatric dosing of breath testing agents and important considerations in methodology and interpretation. In addition, there are 22 graded recommendations (see below) –some may be surprising. For example, the breath testing is NOT recommended for diagnosis of H pylori but is recommended for determination of eradication therapy.







Related blog posts:
U.S. FDA (5/20/22): FDA Approves First Treatment for Eosinophilic Esophagitis, a Chronic Immune Disorder
“Today, the U.S. Food and Drug Administration approved Dupixent (dupilumab) to treat eosinophilic esophagitis (EoE) in adults and pediatric patients 12 years and older weighing at least 40 kilograms (which is about 88 pounds). Today’s action marks the first FDA approval of a treatment for EoE…”
“The efficacy and safety of Dupixent in EoE was studied in a randomized, double-blind, parallel-group, multicenter, placebo-controlled trial, that included two 24-week treatment periods (Part A and Part B)…In Part A of the trial, 60% of the 42 patients who received Dupixent achieved the pre-determined level of reduced eosinophils in the esophagus compared to 5% of the 39 patients who received a placebo…. In Part B, 59% of the 80 patients who received Dupixent achieved the pre-determined level of reduced eosinophils in the esophagus compared to 6% of the 79 patients who received a placebo”
My take: We will need to revise our patient handout and decide how best to position this very expensive therapy. Without insurance, Dupixent (2 pens of 300 mg/2 mL) costs $3,649.97 on GoodRx. For those with insurance, Dupixent has a manufacturer’s coupon (Dupixent MyWay).
Related blog posts:

DA Schwartz et al. Clin Gastroenterol Hepatol 2022; 20: 1059-1067. Open Access: Efficacy and Safety of 2 Vedolizumab Intravenous Regimens for Perianal Fistulizing Crohn’s Disease: ENTERPRISE Study
Methods: “Patients with moderately to severely active CD and 1–3 active perianal fistulae (identified on magnetic resonance imaging [MRI]) received vedolizumab 300 mg intravenously at weeks 0, 2, 6, 14, and 22 (VDZ) or the same regimen plus an additional vedolizumab dose at week 10 (VDZ + wk10)… Enrollment was stopped prematurely because of recruitment challenges”
Key findings:
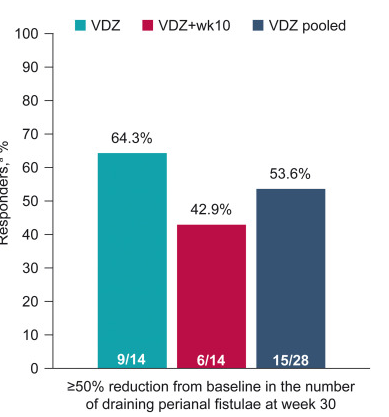
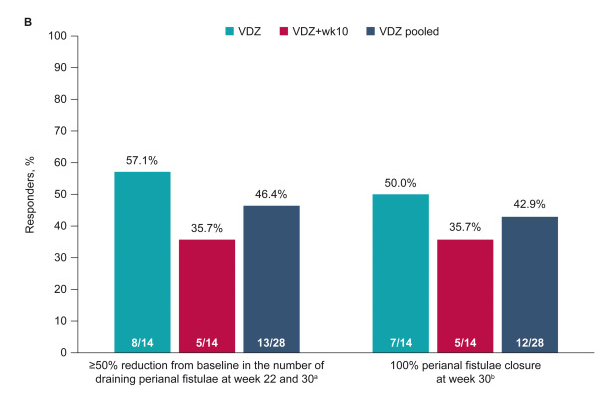
The study findings are limited by relatively small size and lack of control group (eg. placebo or seton/antibiotic group). However, the rate of response in this study is significantly higher than placebo studies which have shown “~1 in 6” who experienced fistula closure.
My take: Vedolizumab is another option for treating Crohn’s disease with perianal fistula. Both regimens in this study were associated with response, though the additional 10-week dose (in one group) did not improve outcomes.
Related blog posts:
Most patients that I see with celiac disease (CD) do very well after diagnosis/implementation of dietary therapy. A recent study indicates a subset of patients have significant work disability as adults.
SR Bozorg et al. Clin Gastroenterol Hepatol 2022; 20: 1068-1076. Open Access: Work Loss in Patients With Celiac Disease: A Population-based Longitudinal Study
In this large-scale nationwide study (part of the ESPRESSO study) from Sweden, the authors used prospectively recorded register data to estimate work loss in patients with CD in comparison to the general population, including the temporal relationship of work loss before and after diagnosis. This study included more than 16,000 patients with CD.
Key findings:
In the discussion, the authors speculate about whether the work loss could be due to inadequate response to a gluten free diet; however, in this study, the authors found similar work loss between patients with CD with or without mucosal healing (only 25% underwent f/u biopsy).
My take: It would be interesting to see the pediatric corollary of work loss, namely school absenteeism and whether this is increased in a small subset as well. My suspicion is that the subset with increased work loss likely has a higher rate of functional disorders, in addition to CD, than the comparator group and probably accounts for a significant amount of the work disability.
Related blog posts:

RC Ungaro et al. Inflamm Bowel Dis 2022; 28: 649-651. Impact of Thiopurine Exposure on Immunogenicity to Infliximab Is Negligible in the Setting of Elevated Infliximab Concentrations
Background: Whether proactive therapeutic drug monitoring (pTDM) is superior to reactive TDM (rTDM) is not entirely clear, though some studies have shown better outcomes with pTDM. Additionally, Colombel et al (Clin Gastroenterol Hepatol 2019; 17: 1525-32) showed that antidrug antibodies during combination therapy were detected only in those with the lowest quartile of infliximab trough levels; this suggests that optimized monotherapy should be similarly effective to combination therapy.
Methods: The authors retrospectively analyzed a commercial laboratory database (Prometheus) with 3970 patients and paired 6-thioguanine (6-TGN) levels with infliximab (IFX) and antibodies to infliximab (ATIs)
Key findings:
My take: In patients with IFX levels >5 mcg/mL, there does not appear to be much benefit for most patients from the addition of a thiopurine; this may not be true for those who are switching to a 2nd anti-TNF agent due to antidrug antibodies. This study supports pTDM to assure adequate IFX levels.
Related blog posts:
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

R Yadiatpati et al. Clin Gastroenterol Hepatol 2022; 20: 984-994. AGA Clinical Practice Update on the Personalized Approach to the Evaluation and Management of GERD: Expert Review
The general approach, outlined in Figure 1, is to empirically treat patients with typical GERD symptoms for 4-8 weeks with single-dose PPI. In those with response, the goal is to use the lowest effective dose and consider reflux testing (“offer endoscopy with prolonged wireless reflux monitoring”) if needing prolonged treatment (>1 yr). In those without a response, adjusting treatment (possibly change medication or change to twice a day) should be considered and reflux testing (off treatment) is recommended as well in those lacking response to treatment.
Some of the recommendations/best practice advice:
Related blog posts:

Yesterday, this blog discussed what is needed to achieve high cure rates for H pylori. One of my microbiology colleagues informed me that until recently there have only been susceptibility standards for clarithromycin from the Clinical Laboratory Standards. Now, the European Committee on Antimicrobial Susceptibility Testing has criteria for clarithromycin, tetracycline, amoxicillin, levofloxacin, metronidazole, and rifampin. Given the difficulty culturing H pylori, his view is that stool testing is the most promising avenue for susceptibility testing because we now have the genes that determine resistance delineated for all of these drugs.
A related issue is antimicrobial stewardship: DY Graham. J-M Liou. Clin Gastroenterol Hepatol 2022; 20: 973-983. Open Access: Primer for Development of Guidelines for Helicobacter pylori Therapy Using Antimicrobial Stewardship
Key points:
H pylori is difficult to eradicate:
My take: The lack of action on H pylori susceptibility despite the current tools is a bad look for the GI community. Would this still be the case if the treatment were relegated to our infectious disease colleagues? Antibiotic stewardship is coming for H pylori -children and adults with this infection should have higher cure rates and easier treatment regimens.
Related blog posts:

Related to yesterday’s blog, here is an SNL commercial for the “Koohl” toilet (also with Benedict Cumberbatch) in 2016: SNL Koohl Toilet
————————————
DY Graham, SF Moss. Am J Gastroenterol 2022. 117: 524-528. Antimicrobial Susceptibility Testing for Helicobacter pylori Is Now Widely Available: When, How, Why
Key points:
Susceptibility Testing Labs (see Table 1):
A treatment algorithm is listed:
My take: Perhaps H pylori susceptibility testing availability needs to be a quality metric for hospitals and endoscopy centers.

Related blog posts:

