Colonic Transit Radiomarker Studies (aka Sitz markers)
Colonic Scintigraphy
Colonic Manometry
Wireless Motility Capsule (aka SmartPill)
Electromagnetic Capsule Tracking System
CINE Motility MRI
The article provides useful information for indications and for interpreting these studies along with some terrific figures.
For colonic transit radiomarkers:
Fecal impaction should be addressed prior to study
Figure 1 algorithm: If >80% of markers remain in colon on day 4 or 5, this is an abnormal study. “Children are considered as having slow transit constipation when there is a delay in transit, with the pellets spread throughout the colon. When the delay occurs and over 50% of the markers are held up in the rectosigmoid colon, children are labeled as having rectal outlet obstruction”
Many times, treatment decisions are like on “Let’s Make a Deal.” That is, should I stick with what I’ve got or should I try for something better & sometimes wind up with a goat. In this referenced article, patients were under maintenance therapy with adalimumab (ADA) monotherapy (40 mg every 14 days) and had experienced a secondary loss of response (LOR) despite trough levels > 4.9 μg/mL. In this nonrandomized prospective study, patients were either swapped to vedolizumab (VDZ) or optimized on adalimumab (ADA) treatment.
Key findings:
At 24 months, 11 out of 70 patients (16%) in the swap group discontinued treatment compared with 36 out of 61 (59%) patients in the optimization group (P < 0.001)
In the optimization group, treatment discontinuation was positively associated with baseline fecal calprotectin >500 μg/g (HR, 3.5)
In patients selected for optimization, 56% (34/61) remained on ADA at 1 year and 41% (25/61) at 2 years
In their discussion, the authors state “current guidelines recommend switching to another class of biologics in case of LOR to ADA with therapeutic drug levels.” However, the authors note that their therapeutic level cut-off of >4.9 mcg/mL is lower than the latest recommendations. In addition, in their conclusion, they note that due to limited biologic options, “ADA optimization strategy might be considered” in a subgroup.
My take: Despite better results in the patients that swapped to VDZ in this study, I think it is important to assure adequate drug levels before choosing a new drug class. For ADA, expert recommendations have suggested a level of 8-12 as therapeutic and to avoid discontinuation if ADA level is less than 10. In this study, more than 40% remained on ADA two years after LOR in those with dosing optimization.
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
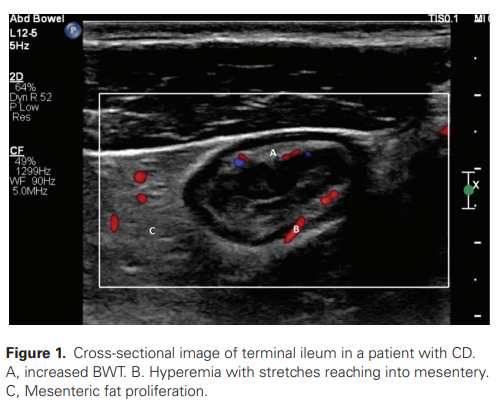
Research has shown that IUS has the potential to be a valuable additional point-of-care tool to guide treatment choice and to monitor and predict treatment response, although evidence of its accuracy and value in clinical practice is still limited
The utility may be operator-dependent as well
My take: Due to low upfront costs, IUS would be appealing adjunct to current monitoring. However, one could envision IUS leading to more downstream studies (& costs), especially if its sensitivity and specificity are not very high.
In this internet-based cohort of 9-17 yr olds (n=159, 96% white), the authors found no association between baseline PROMIS Pediatric anxiety score and subsequent sCDAI (change in sCDAI for 3-point change in PROMIS Pediatric −0.89; 95% CI −4.81 to 3.03). This study is in contrast to studies in adults which have shown a bidirectional relationship between anxiety/depression and IBD activity.
My take: It is difficult to know with certainty whether anxiety/depression may trigger IBD activity; more studies are needed. Treatment of mental health is important regardless of its effects on IBD activity.
An excerpt: “The Crohn’s & Colitis Foundation…launched the We Can’t Wait app, which provides an interactive map that allows users to find a restroom near them across the U.S. Driven by crowd-sourced submissions and major retail and restaurant partners that contributed their restroom location data, the app empowers IBD patients – and all users – with a tool to find restrooms more easily, both in emergency and everyday situations. The app is free and available for download now.
Background: Free treatments for HCV infection with direct-acting antivirals (DAAs) became widespread in Spain in April 2015
Key findings:
After the intervention, there was a great acceleration of the downward mortality trend from HCV, whose annual percent change (APC) went from −3.2% (95% CI, −3.6% to −2.8%) to −18.4% (95% CI, −20.6% to −16.3%). There were also significant accelerations in the downward trends in mortality from HCC.
This is a case series of six pediatric patients and young adults who developed hypersensitivity reactions during intravenous infusion with ustekinumab (UST).
Key findings:
Hypersensitivity reactions during intravenous (IV) induction dose of UST, ranging from mild allergic reactions to anaphylaxis, with no antibodies detected in the two who had testing
Reactions occurred 0-30 minutes after start of infusion
Management was with methylprednisolone in 5 of 6 patients, diphendyramine in 3 of 6, and epinephrine in 1. One patient was managed with IV diphenhydramine alone.
Four of six continued with UST subcutaneously without reactions. ***Change of formulation of UST from IV to subcutaneous was done in a controlled hospital-based setting. The other two 33% were switched to another biologic due to physician preference and were never exposed to the subcutaneous formulation
Although the exact pathogenesis of this infusion reaction remains unknown, it has been attributed to EDTA
My take: It appears that patients with UST hypersensitivity reactions can be changed to SC formulation. The authors recommend to trial a subcutaneous dose of UST in a controlled setting; in addition, they suggest testing with skin prick testing or specific IgE levels to EDTA done by allergy and immunology.
Everyday I see families and these terms create more work –not less.
DD Sherry (JAMA Pediatrics 2022; 176: 10-11. Amplified Pain—A Helpful Diagnosis) shares his views on chronic pain terminology with regard to rheumatology, but some of the same lessons should be applied to pediatric gastroenterology:
“The primary purpose of any diagnosis is to serve the patient. They want to know what they have, even if we, as scientists, do not know the cause or mechanism. For example, we have no idea why children have juvenile idiopathic arthritis and, even though it has the word idiopathic in it, giving the child and family this diagnosis is reassuring, allows them to stop looking for other reasons for their symptoms, lets them tell others what they have, and allows for therapy to begin.”
“Amplified pain, in essence, is when the body takes a signal and amplifies it to become symptomatic. The pain is disproportional, as is, frequently the degree of disability”
“Telling patients with amplified pain that their pain is chronic pain,… functional pain…is no help. Many of these children have already been told they are malingering”
“Using the term amplified pain is useful, understandable, and rational. These children are not exaggerating their pain complaint.”
My take: A term like amplified gut pain would be an improvement from what we have now. It could be introduced as another term for visceral hyperalgesia or as a childhood variant of IBS or FAP since it is not currently used in the literature.
Methods: Endoscopic features were prospectively recorded (n=65) using a system specifically developed for EG, the EG Endoscopic Reference System (EG-REFS)
Key findings:
The most common endoscopic findings were erythema (72%), raised lesions (49%), erosions (46%), and granularity (35%); only 8% of patients with active histology (≥30 eosinophils/high-power field) exhibited no endoscopic findings
A strong correlation between EG-REFS scores and physician global assessment of endoscopy severity was demonstrated (Spearman r = 0.84, P < 0.0001)
EG-REFS severity was significantly correlated with active histology, defined by a threshold of ≥30 eosinophils/high-power field (P = 0.0002).
My take: This reference has a ton of terrific pictures (48 for Figure 1) which showcase the wide variety of endoscopic findings (unfortunately these are behind a paywall). Overall, the study lays the groundwork for scoring the severity of EG and for serial assessments.
Related blog posts:
NASPGHAN Toolbox App -includes link to image atlas and many other useful features
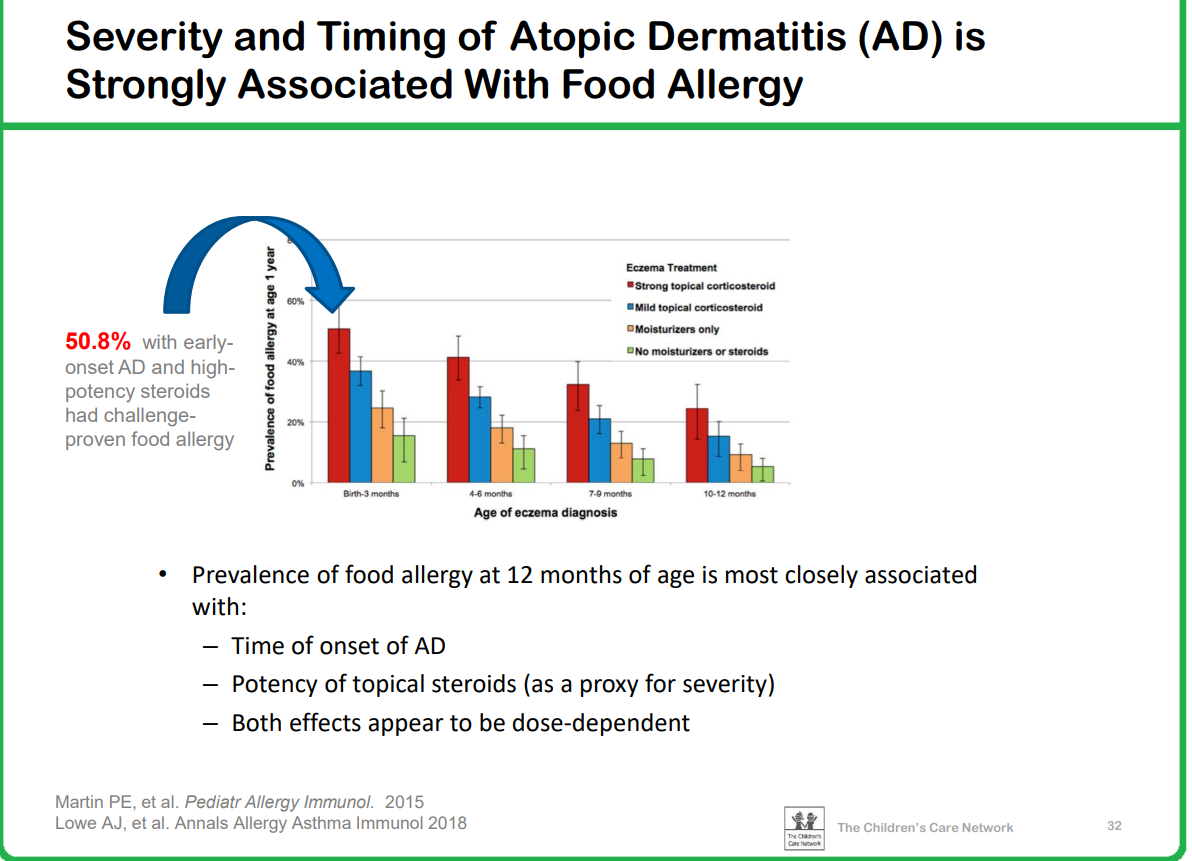
The Children’s Care Network (in Atlanta) has recently shared its Spring 2022 Clinical Quality Forum. Following is the link to the video recording. The poll during the live presentation is not active for the recording.
Some of the slides that I think are most helpful are shown below (used with permission). This 2nd part of content is from Dr. Brian Vickery which describes the relationship of atopic dermatitis to food allergy and best practices for prevention of food allergy:
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition
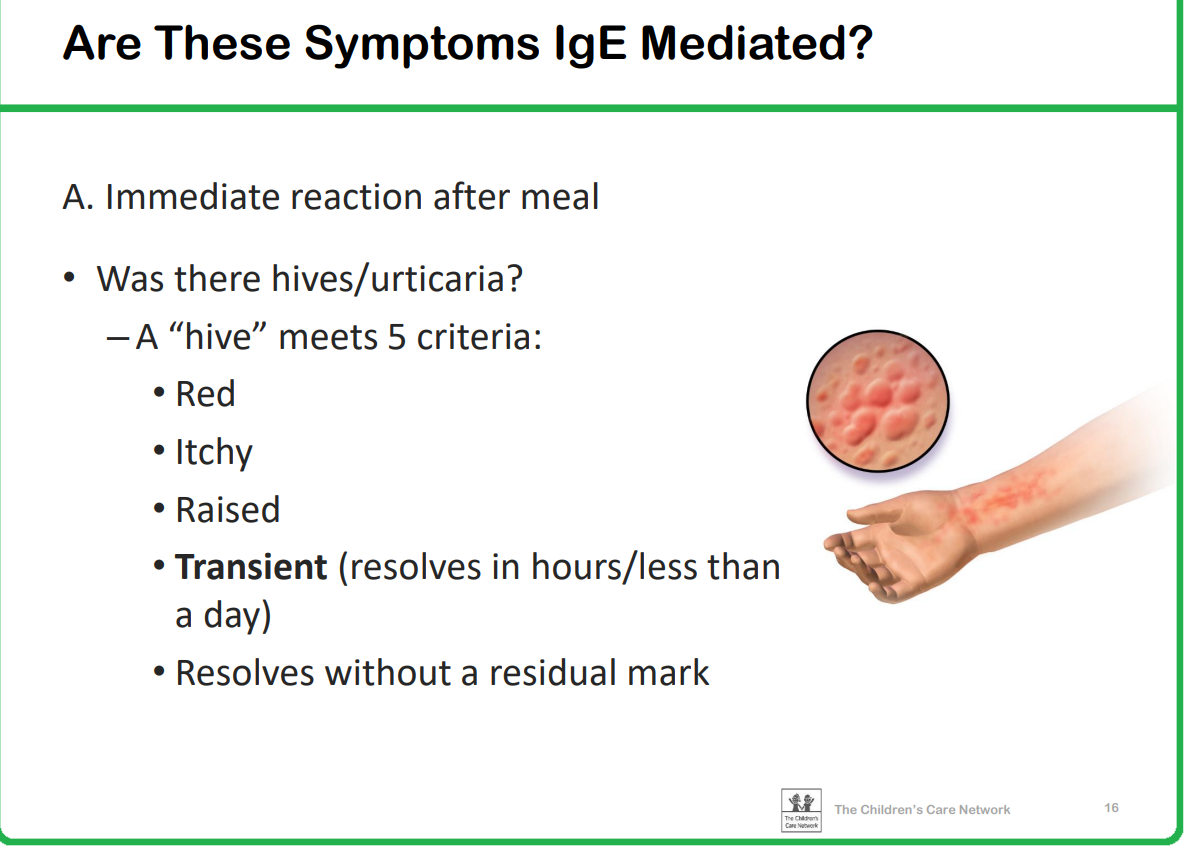
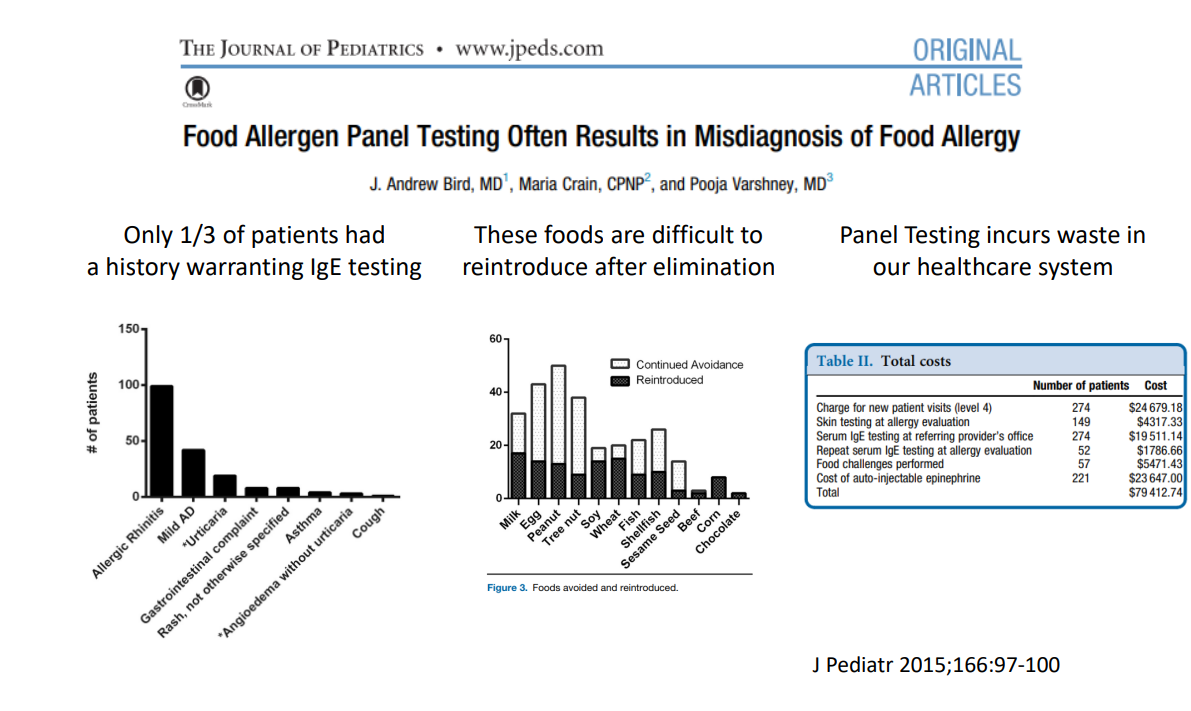
The Children’s Care Network (in Atlanta) has recently shared its Spring 2022 Clinical Quality Forum. Following is the link to the video recording. The poll during the live presentation is not active for the recording.
Some of the slides that I think are most helpful are shown below (used with permission). The first part of content is from Dr. Gerry Lee which describes best practices for selecting patients for Food Allergen IgE testing:
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition