Mitigation Efforts for Button Batteries

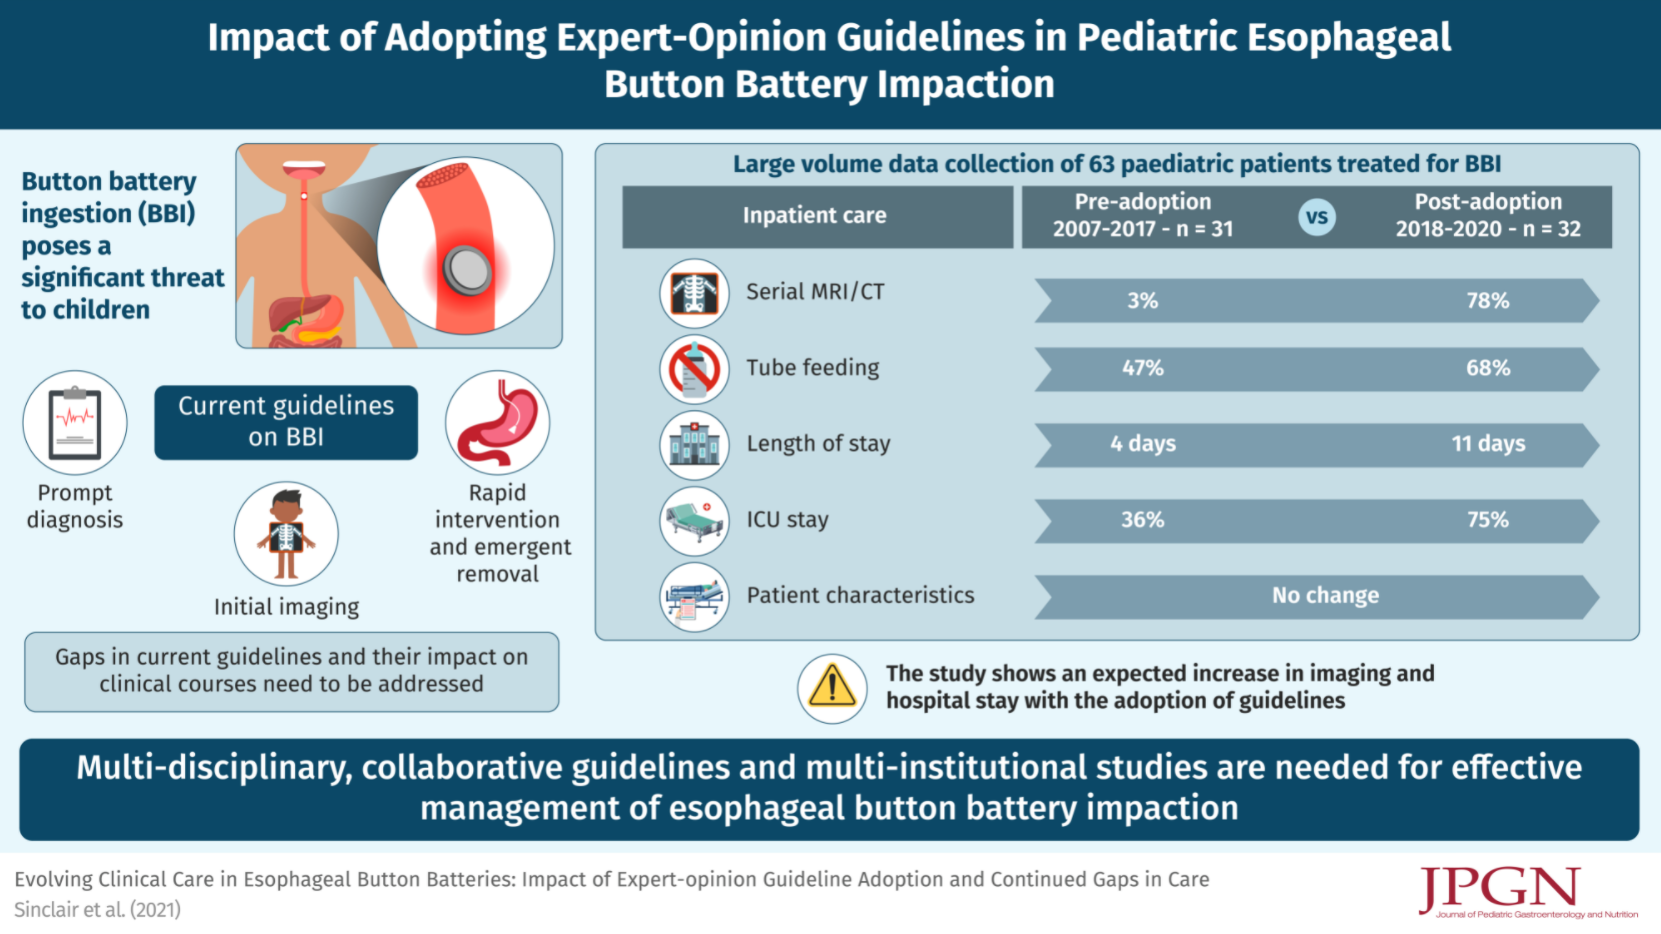
EM Sinclair et al. JPGN 2022; 74: 236-243. This retrospective study (n=63) describes the increased utilization of cross-sectional imaging, adoption of acetic acid irrigations, increased intensive care/hospitalizations after the implementation of consensus institutional guidelines for button battery management (see visual abstract below). An estimate in the increase in costs would have been a good addition to this study.

One of the references (EM Sinclair et al. J Pediatr Surg Case Rep 2021; 66: 101782. doi: 10.1016/j.epsc.2021.101782. Open Access: Development and repair of aorto-esophageal fistula following esophageal button battery impaction: A case report) describes one of the goals of prolonged hospitalization, namely preventing catastrophic bleeding. In this case report, though, the 6 yo had been discharged 12 days after presentation and represented on day 25 with hematemesis from a new aorto-esophageal fistula, requiring emergent cardiac catheterization with successful, life-saving aortic stent placement; “however a multidisciplinary approach to procedure planning is necessary with availability of surgical support for open repair if necessary.” This report has a lot of good images. The discussion notes that the National Capital Poison Center (NCPC) database reports a total 64 deaths in children following button battery ingestion worldwide since 1977; 61% (39/64) of which were due to documented arterio-esophageal fistulae (the actual numbers of deaths is likely much higher). This report also highlights the fact that serial MRIs “may not predict the development of severe complications.”

Related blog posts:

Trends in Pediatric IBD Epidemiology & More on Formula Recall

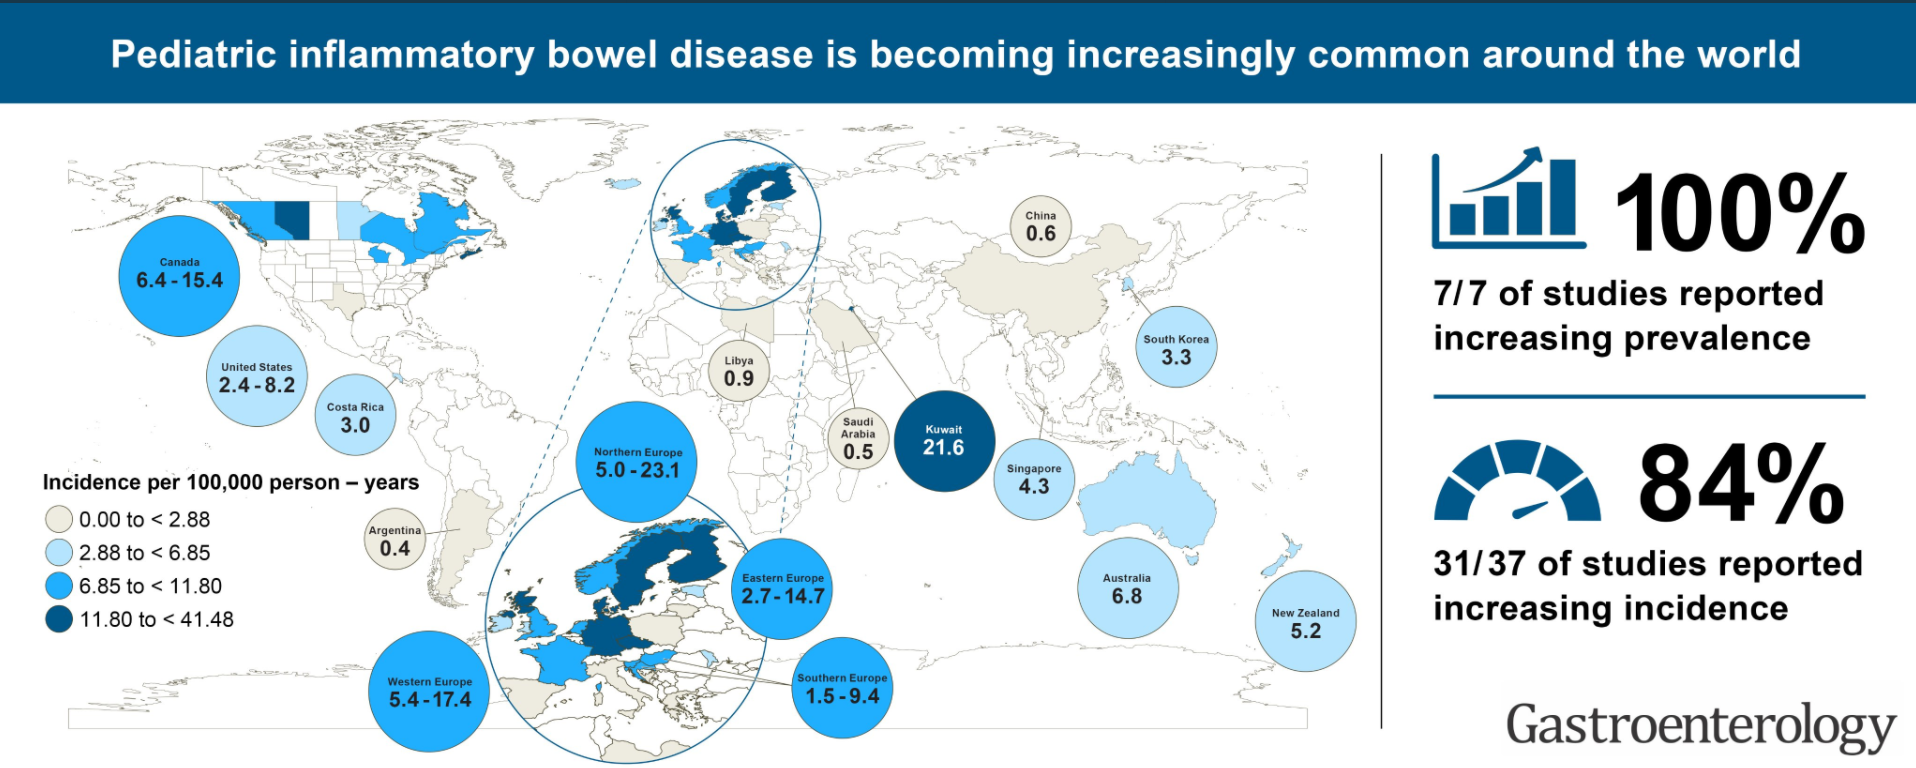
E Kuenzig et al. Gastroenterology 2022; DOI:https://doi.org/10.1053/j.gastro.2021.12.282. Open Access: Twenty-first Century Trends in the Global Epidemiology of Pediatric-Onset Inflammatory Bowel Disease: Systematic Review

Key finding:  Among studies evaluating trends over time, most (31 of 37, 84%) studies reported significant increases in incidence and all (7 of 7) reported significant increases in prevalence

App Website: The Global Epidemiology of Pediatric Inflammatory Bowel Disease

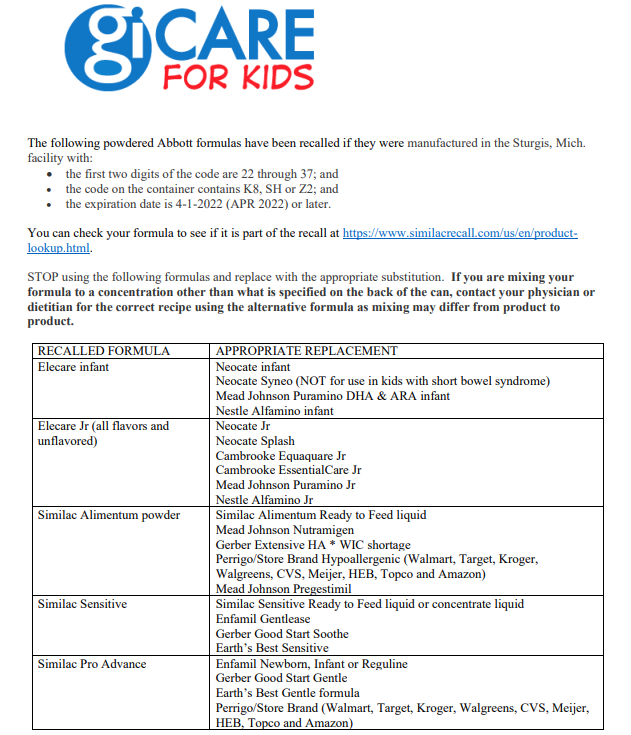
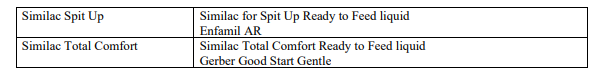
Yesterday, this blog noted the recall of several formulas (FDA Warns Consumers Not to Use Certain Powdered Infant Formula Produced in Abbott Nutrition’s Facility in Sturgis, Michigan). Our office has made a substitution table for the Abbott formulas:

Maintenance Topical Steroid Dosing for Eosinophilic Esophagitis

T Greuter et al. Clin Gastroenterol Hepatol 2021; 19: 2514-2523. Open Access: Effectiveness and Safety of High- vs Low-Dose Swallowed Topical Steroids for Maintenance Treatment of Eosinophilic Esophagitis: A Multicenter Observational Study

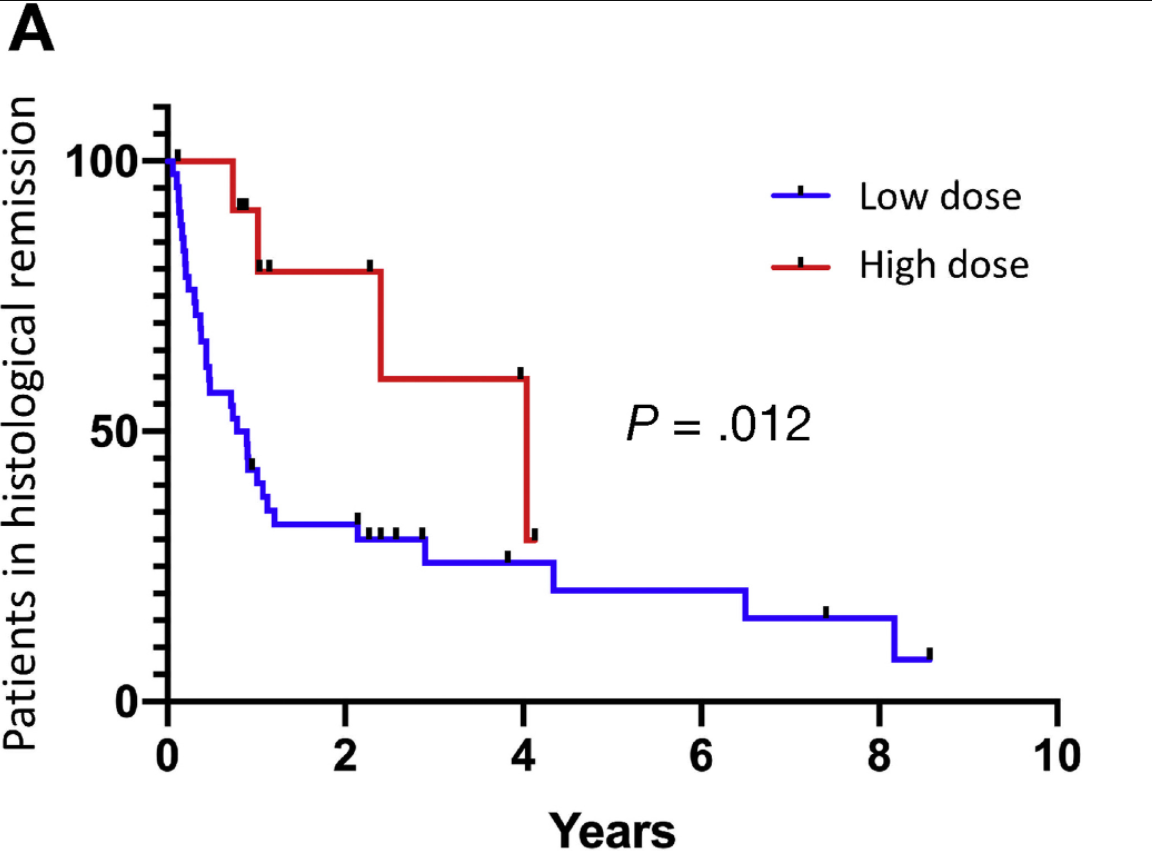
In this multicenter, retrospective study with 82 participants (mean age 37 years), the authors examined swallowed topical corticosteroids (STC) for maintenance of histologic remission (<15 eos/hpf). Low dose STC (22 budesonide, 60 fluticasone) was considered 0.5 mg/day or less. Key findings:

  • Histological relapse occurred in 67% of patients. This rate was comparable in patients treated with low-dose (72%) and high-dose (54%) STCs.
  • Histological relapse occurred significantly earlier with low dose STC (1.0 vs 1.8 years, P = .030)
  • Esophageal candidiasis was identified in 6% of subjects

The authors conclude that most of the histological relapse that occurred was due to true steroid failure since “low adherence and treatment cessation during follow-up were exclusion criteria.” Also, they note that “the recently finished but not yet fully published Maintenance of Remission With Budesonide Orodispersible Tablets vs Placebo in Eosinophilic Eosphagitis (EOS2 trial) (NCT02493335) comparing budesonide maintenance doses of 2 mg/d vs 1 mg/d suggest that there is no additional benefit of daily doses higher than 1 mg (1-year remission rates of 75.0% and 73.5%, respectively).

My take: Low dose STCs do not appear to be as effective in maintaining histologic remission; however, there is a high rate of relapse even in those with higher doses.

Related blog posts:

Kaplan Meier curve for time to histological relapse in patients with deep
histological remission at baseline stratified by steroid dose groups

Alcohol Burden in Hepatology

As an outside observer, I wonder how practitioners in the field of adult hepatology feel about the changing epidemiology of severe liver disease.

Case (article) in point: G Cholankeril et al. Hepatology 2021; 74: 3316-3329. Open Access: Impact of COVID-19 Pandemic on Liver Transplantation and Alcohol-Associated Liver Disease in the USA

This retrospective study utilized UNOS adult data from 6/1/19 to 3/1/21. This included 9528 in the pre-COVID era and 9259 in the COVID era.

Key findings:

  • There was “a significant reduction in the monthly listing rates for HCV (−21.69%, P < 0.001) and NASH (−13.18%; P < 0.001).” However, there “was a significant increase in ALD [alcohol-associated liver disease] listing (+7.26%; P < 0.001) and LT (10.67%; P < 0.001) during the pandemic.”
  • “In the COVID era, ALD (40.1%) accounted for more listings than those due to HCV (12.4%) and NASH (23.4%) combined. The greatest increase in ALD occurred in young adults (+33%) and patients with severe alcohol-associated hepatitis (+50%).”
  • Interestingly, “patients with ALD had a 50% higher probability rate of LT [liver transplantation] than patients with other liver disease.”

The authors note that patients with alcohol use disorder (AUD) and ALD, during the pandemic, “may no longer have structured non-alcohol-related activities and in-person behavioral counseling…coupled with the delay in routine health care…Few patients with ALD receive recommended care for AUD.”

My take: Due to the cumulative effects of ALD, there is likely to continued (worsening) high rates of liver failure due to ALD. Given the difficulties in managing ALD, aside from managing liver complications, this must be a huge emotional burden for many healthcare providers watching this tragedy play out on a continual basis.

Cumulative incidence rates for LT among patients listed for ALD and non-ALD
in the pre-COVID and COVID eras.

Related blog posts:

Epidemiology of Gastroparesis in Adults

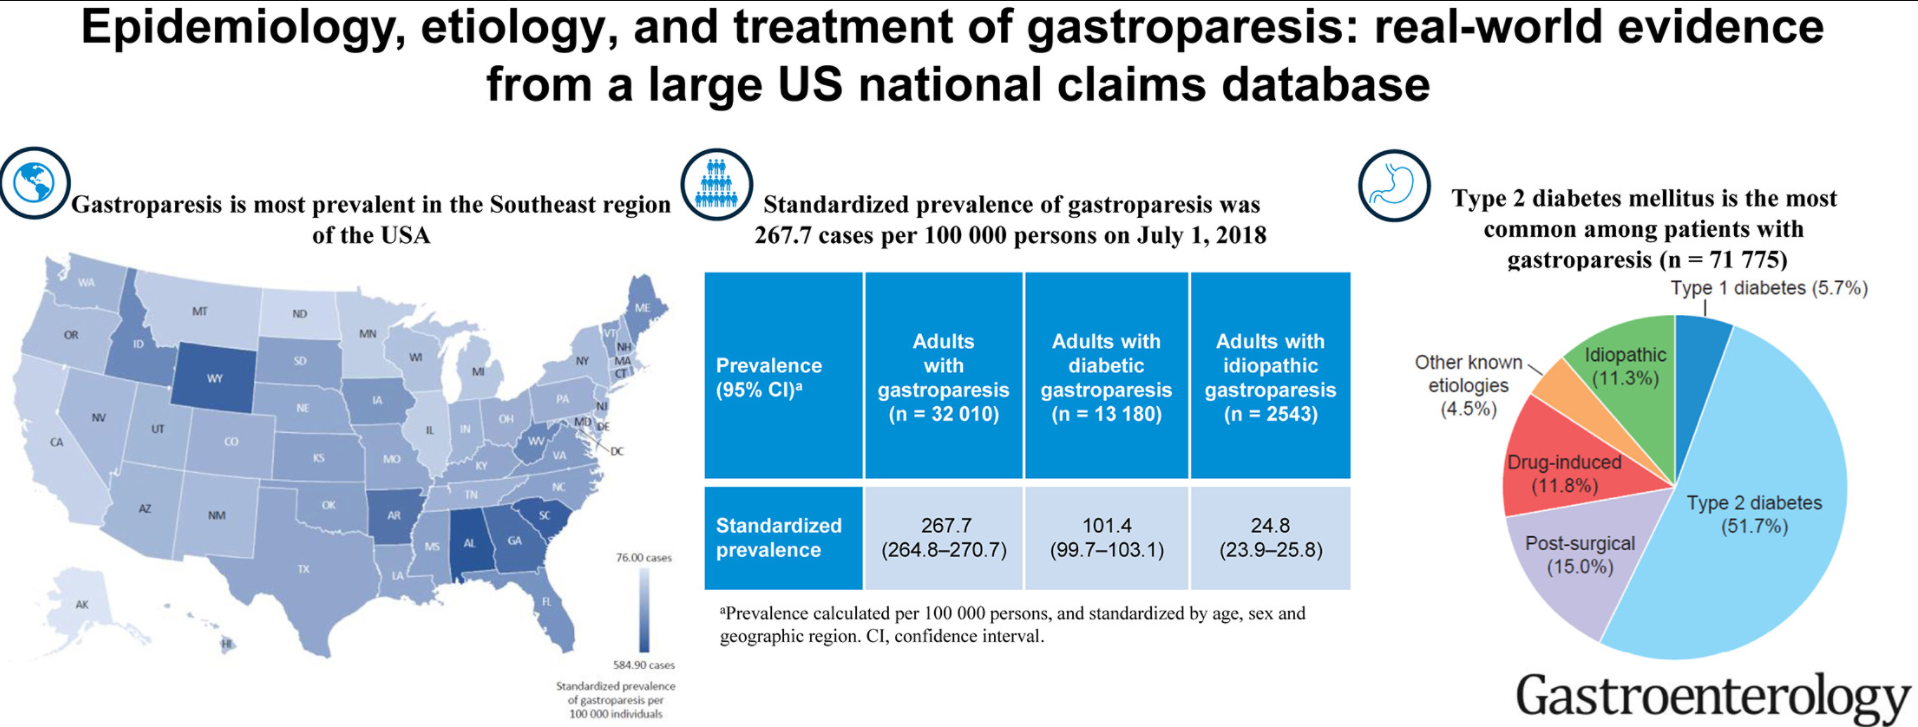
Briefly noted: Y Ye et al. Gastroenterol 2022; 162: 109-121. Open Access: Epidemiology, Etiology, and Treatment of Gastroparesis: Real-World Evidence From a Large US National Claims Database

Key findings:

  • The overall standardized prevalence of gastroparesis was 267.7 per 100,000 US adults, whereas prevalence of “definite” gastroparesis (individuals diagnosed within 3 months of gastric emptying scintigraphy testing with persistent symptoms for more than 3 months) was 21.5 per 100,000
  • Etiology was most commonly due to diabetes (57.4%; type 1, 5.7% and type 2, 51.7%), followed by postsurgical (15.0%), drug-induced (11.8%), and idiopathic (11.3%) etiologies

Related blog posts:

PSC in IBD

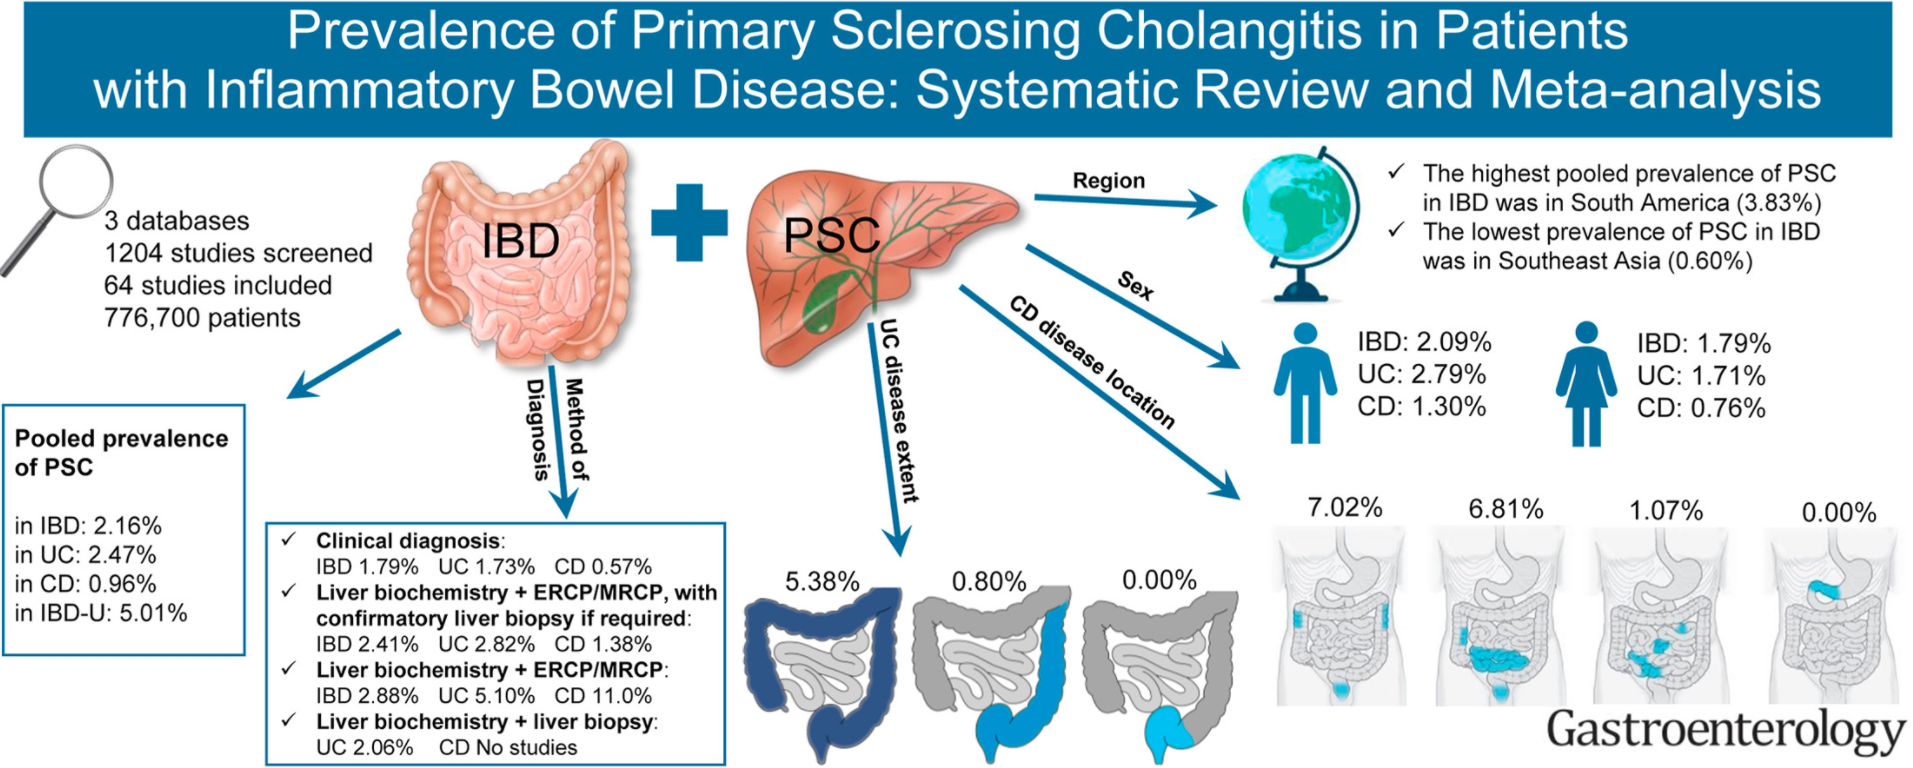
Briefly noted: B Barberio et al. Gastroenterol 2021; 161: 186-1877. Prevalence of Primary Sclerosing Cholangitis in Patients With Inflammatory Bowel Disease: A Systematic Review and Meta-analysis

Key findings: Overall, pooled prevalence of PSC in IBD was 2.16%; the pooled prevalence was significantly higher in UC versus CD (OR 1.69)

Related blog posts:

Microbiome Therapy (SER-109) for Recurrent Clostrioides Difficile

P Feuerstadt et al. N Engl J Med 2022; 386:220-229. DOI: 10.1056/NEJMoa210651. SER-109, an Oral Microbiome Therapy for Recurrent Clostridioides difficile Infection

Background: “SER-109, an investigational oral microbiome therapeutic composed of live purified Firmicutes bacterial spores, was developed to reduce the risk of C. difficile infection recurrence.14 We hypothesized that these spore-forming bacteria would compete metabolically with C. difficile for essential nutrients, modulate bile-acid profiles to reestablish resistance to colonization, or have both of these effects. Here, we report the 8-week efficacy and safety results from a phase 3 [double-blind, randomized, placebo-controlled] trial involving patients with recurrent C. difficile infection, along with supportive microbiome engraftment and metabolomic analyses.”

Methods: N=182 enrolled in the “ECOSPOR III” trial; all patients had at least 3 infections in past year and positive toxin test. After standard-of-care antibiotic treatment, patients received SER-109 or placebo (four capsules daily for 3 days). The primary efficacy objective was to show superiority of SER-109 as compared with placebo in reducing the risk of C. difficile infection recurrence up to 8 weeks after treatment.

Key findings:

  • The percentage of patients with recurrence of C. difficile infection was 12% in the SER-109 group and 40% in the placebo group (relative risk, 0.32)
  • The recurrence risk following SER-109 was even lower after fidaxomicin than vancomycin: relative risk, 0.09 [95% CI, 0.01 to 0.63] with fidaxomicin and 0.41 [95% CI, 0.22 to 0.79] with vancomycin
  • SER-109 dose species were detected as early as week 1 and were associated with bile-acid profiles that are known to inhibit C. difficile spore germination.

My take: This study shows that clinical outcomes with C difficile may be improved by the addition of this microbiome therapeutic after standard therapy. Engraftment of Firmicutes bacteria as a dominant component of the microbiome is generally associated with a healthy state. This opens the door for treatment of other conditions that may benefit from microbiome modulation.

Related blog posts:

NASPGHAN 2021 Nutrition Highlights

Thanks to Kipp Ellsworth for forwarding this link:

Nutrition for IBD website: NASPGHAN 2021 Nutritional Highlights

On this website: “Four presentations/lectures were released at the Nutritional Therapy for IBD Virtual Booth that provide a comprehensive review and update of the latest information regarding the use of EEN and therapeutic diets in the management of IBD”

Why Do We Need Dietary Therapies for IBD

Presenter: Lindsey Albenberg, DO

Dr. Lindsey Albenberg, a clinician and researcher from Children’s Hospital of Philadelphia, describes the rapidly increasing incidence of IBD and its relationship to diet, microbiome and the immune system. She reviews the rationale and science supporting the use of dietary therapy to compliment drug therapy as an avenue to potentially achieve higher, more sustainable and possibly safer levels of remission long term in pediatric patients.

The Crohn’s Disease Exclusion Diet Updates: December 2021

Presenter: Rotem Sigall Boneh, RD. Rotem Sigall Boneh, RD, a primary researcher and developer of CDED, provides an overview of the accumulating data with CDED in combination with PEN, including the newly published results of adult data with important endoscopic findings and further shares real world experience and application of nutritional therapy.

IBD Anti-inflammatory Diet or IBD-AID: Proof of Concept

Presenter Ana Maldonado-Contreras, MSc, PhD. Dr. Ana Maldonado-Contreras, a lead researcher in IBD-AID explains the relationship between diet, microbiome and immune function with the design and rational of IBD-AID to manipulate the microbiome. She shares the recently published data of the impact of IBD-AID on the microbiome and cytokine levels specific to food components.

Nutritional Therapy: Perioperative + Complicated Crohn’s Disease

Presenter Andrew S. Day, MB, ChB, MD, FRACP, AGAF

At the NTforIBD Nutritional Symposium prepared for NASPGHAN2021, Professor Day provides insight into the important role of EEN, an underutilized option to both induce remission and improve outcomes in complicated and peri-operative patients.

Austin Bradford Hill, PPIs and IBD

KH Allin, P Moayyedi. Gastroenterol 2021; 161: 1789-191 (editorial). Open Access: Proton Pump Inhibitor Use: A Risk Factor for Inflammatory Bowel Disease or an Innocent Bystander?

This editorial helps provide needed context on the associated observational study by Xia et al (B Xia, M Yang et al. Gastroenterol 2021; 161: 1842-1852. Open Access. Regular use of proton pump inhibitor and the risk of inflammatory bowel disease: pooled analysis of 3 prospective cohorts) which showed a mild increase risk of IBD among PPI users. While the PPI users were at 42% increased risk of IBD compared to nonusers, if correct, “the absolute risk associated with PPI use is modest. Number needed to harm is 3770, meaning that when 3770 individuals are treated with PPIs for 1 year, 1 additional case of IBD is observed.”

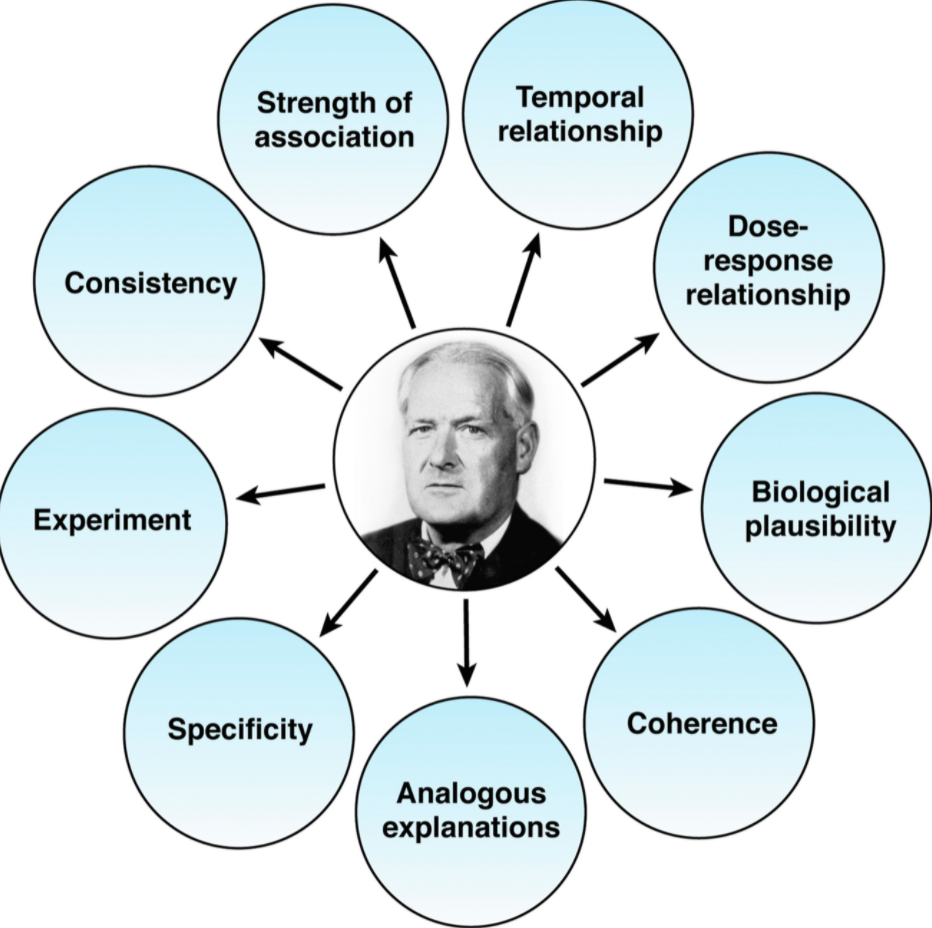
Despite the efforts of the study authors to minimize confounders, the editorial focuses on the work of Austin Bradford Hill (Proc R Soc Med. 1965; 58: 295-300. The environment and disease: association or causation?) who “realized making causal inferences on observational data was challenging and outlined a list of factors that would make this interpretation more or less likely….strength of association, dose response, and consistency are important and often not commented on in observational studies.”

In a previous “a double-blind, randomized clinical trial comparing pantoprazole with placebo over 3 years with more than 53,000 patient years follow-up found there was no association” with IBD identified…Interestingly, this trial reported a slightly higher risk of enteric infections, and this is the underlying mechanism proposed for how PPI therapy may increase the risk of IBD.”

My take (borrowed from editorial): “Most associations for PPI and harm are likely to be residual or unmeasured confounding, whether this is also true for IBD will only be determined by further study.”

Related blog posts:

IBD Updates: Fatigue Trajectory, Risk of IBD with Derm Findings

NZ Borren et al. Inflamm Bowel Dis 2021; 27: 1740-1746. Open Access: Longitudinal Trajectory of Fatigue in Patients With Inflammatory Bowel Disease: A Prospective Study

In this prospective study using the CCFA IBD Partners cohort, the authors examined fatigue symptoms with questionnaires (FACIT-F and MDI) at 3 timepoints over a 1 year period. There was likely a strong selection bias among participants (mean disease duration was 18 years) who chose to complete theses questionnaires. Key findings:

  • Persistent fatigue (at baseline and at 6 months) was the most common pattern, affecting two-thirds (65.8%) of patients
  • The strongest predictor of incident fatigue was sleep disturbance at baseline (odds ratio, 2.91.
  • Only 12.3% of those with fatigue at baseline had symptom resolution by 6 months. Resolution was more likely in patients with a diagnosis of ulcerative colitis, quiescent disease, and an absence of significant psychological comorbidity

My take: In those with fatigue, it is often persistent.

Related blog post: #MondayNightIBD and Fatigue

D King et al. Inflamm Bowel Dis 2021; 27: 1731-1739. The Risk of Later Diagnosis of Inflammatory Bowel Disease in Patients With Dermatological Disorders Associated With Inflammatory Bowel Disease

The authors retrospectively studied 7447 patients with dermatological conditions such as erythema nodosum (EN), pyoderma gangrenosum, Sweet’s syndrome, and aphthous stomatitis which can occur with inflammatory bowel disease (IBD) and are considered dermatological extraintestinal manifestations (D-EIMs).

Key findings:

  • 131 (1.8%) subsequent IBD diagnoses in patients with D-EIMs compared with 65 (0.2%) in those without D-EIMs
  • Median time to IBD diagnosis was 205 days (IQR, 44-661 days) in those with D-EIMs

My take: The absolute risk if IBD is low in patients with D-EIMs but still increased 6-fold. This would probably be a good population to screen for IBD with a biomarker (eg. calprotectin)

Related blog post: Review of Pyoderma Gangrenosum

J Shah et al. Inflamm Bowel Dis 2021; 27: 1832-1838. Ocular Manifestations of Inflammatory Bowel Disease Nice review: “ocular manifestations of IBD include keratopathy, episcleritis, scleritis, and uveitis and are among the most common extraintestinal manifestations.” Urgent referral to ophthalmology needed if deep eye pain that can awaken from sleep (?scleritis), if photosensitivity/blurry vision/headache (?anterior uveitis), or if floaters/decreased vision (?posterior uveitis)