Jump in Knowledge Regarding Gut-Brain Axis

Eric Topol has summarized some of the recent advances in the understanding of the Gut-Brain Axis. Open Access Link: The Gut-Brain Axis Takes Center Stage (6/22/25)

Here’s a lengthy excerpt:

We’ve known about the gut-brain axis for decades but there has recently been an unprecedented jump in our knowledge base that has transformed our expectations for its preeminence.
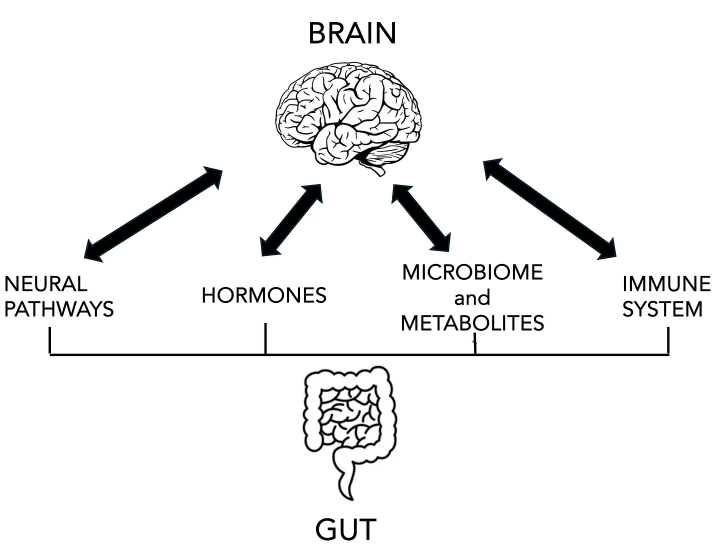
There are 2 types of neural pathways, the “second brain” referring to the enteric (gut) nervous system from the cells that line the intestine and communicate to the vagus nerve to the brain (and in the opposite direction, too). There are also connections via the sympathetic, parasympathetic nervous system (autonomic nervous system, ANS) branches and spinal cord innervation to the gut primarily through the ANS.

Cells in the gut produce hormones (enteroendocrine cells) such as glucagon-like peptide (GLP-1), gastric inhibitory peptide (GIP), peptide YY, secretin, gherlin, gastrin, and many others. Some of these regulate pancreatic hormones such as insulin, glucagon and amylin, which can be considered as gut hormones but derived from pancreatic cells rather than intestinal lining cells. The hormonal interaction between gut and brain also goes through the hypothalamus-pituitary-adrenal (HPA) axis.

The abundant and diverse bacteria in the gut microbiome of tens of trillion of cells of more than 3,000 species. These gut bacteria and their metabolites have an outsized impact by producing or stimulating different neurotransmitters (5HT, GABA) and metabolites (e.g. short chain fatty acids, SCFAs) that communicate with the brain and the immune system. For example, see my previous Ground Truths on how a gut bacteria and its metabolites can drive sugar cravings.

The interaction with the immune system is critical to maintain integrity of the gut lining (avoiding “leaky gut syndrome”) and the blood-brain-barrier…

The precise way by which the gut can induce inflammation in the brain has remained unclear. In the journal Nature this week it was shown that inflamed gut-derived CD4+ T cells can infiltrate the brain, leading to neuroinflammation and neurological damage in the experimental model…bacteria derived proteins (antigens) looking like host derived proteins, inciting an immune response.
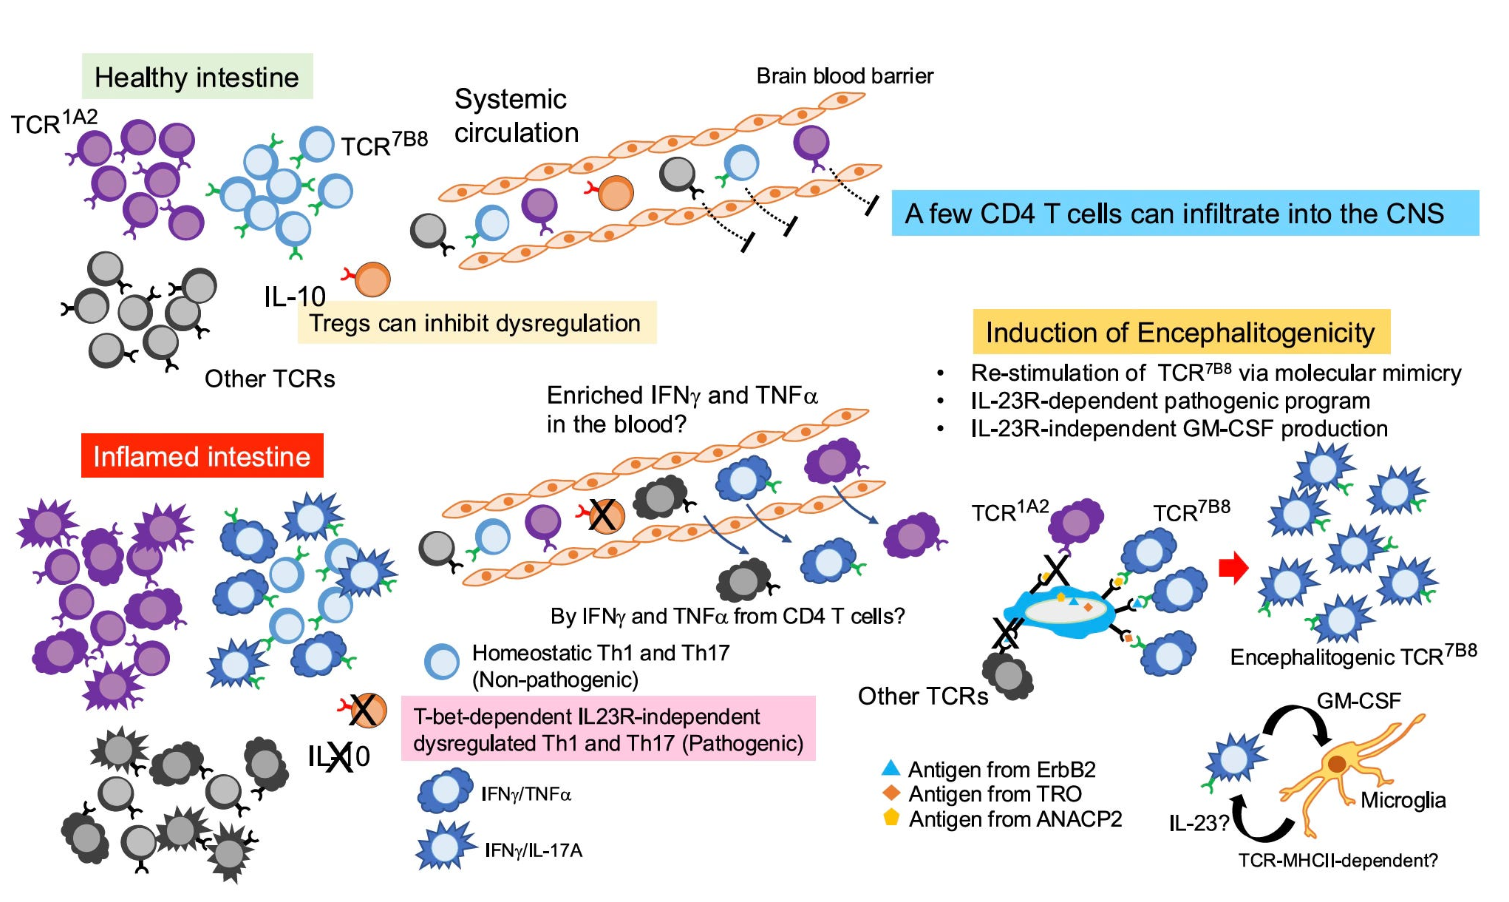
This was the second of 2 recent discoveries centered around gut-derived immune cells that get into the brain. Newly identified specialized CD4+ T cells from the gut and white adipose tissue establish residence in the brain’s subfornical organ and regulate feeding behavior…

It turns out the H. pylori can do good things too! As in blocking the formation of amyloid protein formation. This week in Science Advances it was demonstrated that H. pylori releases the protein CagA (cytotoxin-associated gene A) which potently inhibits pathogenic amyloid assemblies..for formation in Alzheimer’s disease, Parkinson’s disease and type 2 diabetes…

Several new gut hormone clinical trials, beyond the ones that are widely used—semaglutide (Ozempic) and tirzepatide (Zepbound, Mounjaro), were unveiled…Through randomized trials, their broad impact has been unequivocally proven for diabetes, obesity, and for treating related conditions of heart failure (with preserved ejection fraction), kidney disease, liver disease, sleep apnea, along with unexpected suppression of addiction to alcohol, cigarette smoking, nail biting and gambling. Add a surprising impact that we’re starting to see for autoimmune diseases. Even before there is weight loss with these drugs, there is evidence from experimental models of reduced systemic (body-wide) and brain inflammation. What is surprising is that drugs like semaglutide have little direct penetrance to the brain, but exert their effect chiefly through the gut-brain axis. New molecules in this class will have enhanced brain penetrance…

Will They Work For Alzheimer’s Disease?

[In a Liraglutide trial with 200 participants with Alzheimer’s,] after 1 year of treatment there was a reported 18% less cognitive decline and 50% reduced brain shrinkage compared to placebo…[There are also two studies] pending EVOKE and EVOKE Plus trials of daily oral semaglutide participants aged 55–85 years with mild cognitive impairment or mild dementia due to Alzheimer’s…About 12% of American adults are already taking GLP-1 drugs


Sulfasalazine vs 5-ASA: Treatment Outcomes in Pediatric UC

I Mansuri et al. J Pediatr Gastroenterol Nutr. 2025;80:988–997. Clinical outcomes of maintenance therapy with sulfasalazine compared to 5-aminosalicylates in children with ulcerative colitis

Methods: This was a retrospective review of children diagnosed with UC between June 1999 and December 2019 at Boston Children’s Hospital. 124 started on sulfasalazine (SZ) and 309 on 5-aminosalicylates (5-ASA). Most patients had mild to moderate disease based on PUCAI score; ~12% had severe disease.

Key findings:

  • At 1 year, 54%, 44.3%, and 36.6% of patients on SZ, 5-ASA, and those who switched, respectively, were in steroid-free remission (p = 0.13)
  • All medication switches due to adverse reactions (24) were from SZ to 5-ASA. No patient was switched from 5-ASA to SZ because of adverse reactions. The non-severe adverse reactions noted were nausea, vomiting, abdominal pain, non-severe skin rash, headache, mild leucopenia, and lymphadenitis. Three patients had serious skin reactions, and one had pancreatitis.
  • SZ tended to have more minor adverse reactions. Except for countering adverse reactions, switching between SZ and 5-ASA did not offer therapeutic benefits. Disease severity at diagnosis predicted early treatment escalation

Discussion Points:

  • SZ offers advantages such as lower cost and availability in suspension form; the suspension form is particularly beneficial for young children and those unable to swallow the solid form of medication.
  • 5-ASA formulations can be almost 10–50 times more expensive than SZ. For example, the wholesale acquisition cost of monthly generic SZ is $30 compared to $274 for generic Lialda, $1131 for generic Pentasa, and $1890 for generic Asacol HD

My take: About 20% of patients had to switch from Sz to 5-ASA due to adverse reactions; though, Sz had a mildly higher response rate (not statistically-significant). Switching between SZ and 5-ASA or vice versa is unlikely to provide much therapeutic benefit; patients who switched agents for medical reasons (rather than reactions) were more likely to require escalation to either a biologic or immune modulator.

Related blog posts:

Chatttahoochee River (Sandy Springs)

Retrospective Study on Botulinum Toxin for Refractory Constipation in Children

D Patel et al. J Pediatr Gastroenterol Nutr. 2025;80:956–962. Efficacy of anal botulinum toxin injection in children with functional constipation

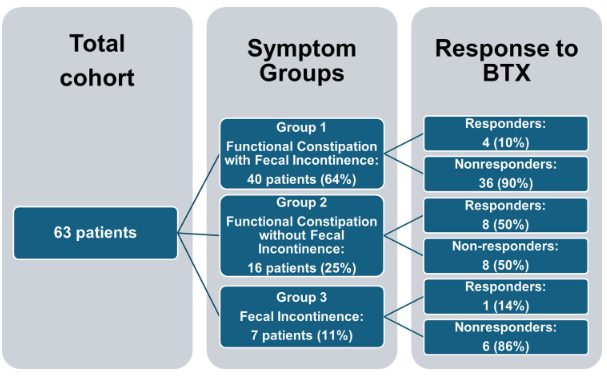
Methods: This was a retrospective, multicenter study including pediatric patients (n=63) who received anal botulinum toxin (BTX) for functional constipation (FC) refractory to medical therapy.  Response to therapy was assessed based on improvement in weekly frequency of BM (bowel movements) to 3 or more per week and/or resolution of functional incontinence (FI)

Key findings:

  • There was a a response rate of 10% in group 1 (FC +FI), 50% in group 2 (only FC) and 14% in group 3 (only FI); the an overall symptom resolution in 21% of patients
  • Fecal incontinence was the most common side effect, reported in 11% of all patients 

My take: In this highly-selected refractory population, there was a poor response to BTX in those with fecal incontinence (groups 1 and 3). The results should be interpreted with caution due to the retrospective nature of the study and the a lack of a control group.

Related blog posts:


Disclaimer
: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Liver Transplantation for PSC: Long-term Outcomes and Complications

M Mouchli et al. Liver Transplantation 2025; 31: 781-792. Long-term (15 y) complications and outcomes after liver transplantation for primary sclerosing cholangitis: Impact of donor and recipient factors

Methods: Using Mayo clinic prospectively maintained transplant database, 293 adult patients (>18 y, mean age 47 yrs) with PSC who underwent LT from 1984-2012 were identified. Patients with cholangiocarcinoma were excluded. One hundred and thirty-four patients received LT before 1995, and 159 were transplanted after 1995.

Key findings:

  • The 1-, 5-, 10-, and 15-year cumulative incidence of recurrent PSC was 1.0%, 8.0%, 23.5%, and 34.3%, respectively.
  • Vascular and biliary complications are frequent: hepatic artery thrombosis (N = 30), portal vein stenosis/thrombosis (N = 48), biliary leak (N = 47), biliary strictures (N = 87)
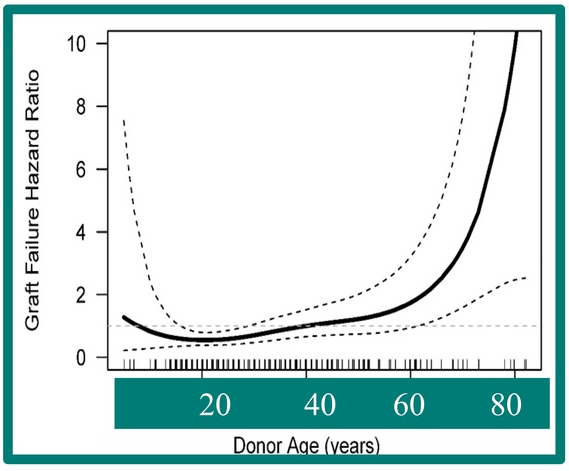
  • Graft failure occurred in 70 patients
  • Donor age >60 years was associated with an increased risk of recurrent PSC. 

My take: Overall, there was a good survival rate despite the increased frequency of vascular and biliary complications. Also, 2/3rds of patients did NOT have recurrent PSC. Older donor age was associated with higher graft failure in this cohort.

Related blog posts:

The VEO-IBD Foundation -Developing Resource for Families

Link: Family reflections: research gives back childhood: a family’s experience with very early onset inflammatory bowel disease Pediatric Research; https://doi.org/10.1038/s41390-024-03506-8

An excerpt:

Very Early Onset Inflammatory Bowel Disease is so rare and individualized that no standard of care yet exists, and almost none of the interventions are approved for infants. After eliminating all dairy, prematurely ending breastfeeding, and moving exclusively to a prescription formula, we tried and failed multiple classes of medications, hoping each time that this medication would be the one that would ease our son’s suffering. Doctors are only now building a history of successful interventions to draw from, so treatment options come from very small studies from Very Early Onset Inflammatory Bowel Disease researchers and educated guesses. Treatment options generally ramp up in aggressiveness, which is hard enough for parents of a miserably sick infant to process and decide. Once these interventions fail, drug costs and insurance approval become major hurdles. This process of trial-and-error in treating Very Early Onset Inflammatory Bowel Disease patients is a nightmare. On a weekly or monthly basis, parents must make life-altering decisions with very little data for a patient too young to advocate for themselves.

Link: The VEO-IBD Foundation This foundation is still in its early stages, but anticipate it will be a resource for families with VEO-IBD.

Related blog posts:

Navigating Celiac Disease: Tips for Pediatric to Adult Transition

L Kievela et al. Clinical Gastroenterology and Hepatology,2025; 23: 908 – 911. Transition of Care in Celiac Disease: A Chance to Advance

This clinical practice article offers some useful advice in transitioning patients with Celiac disease into adult provider care. Some of their recommendations for adult provider care:

  • Regular visits
  • Assessment of gluten-free diet adherence with low thresholf for dietician referral
  • Checking serum tissue transglutaminase antibody levels
  • Screening for other autoimmune conditions
  • Consider additional lab tests (eg. CMP, CBC, Ferritin, ALT, Albumin, Folate, Zinc, Vit D, Vit B12, and TSH) and DEXA scan based on clinical situation
  • Recommend screening family members
  • Check vaccination status
Figure 1 provides suggestions for a transition report

Related information that is not in the article:

College/school resources:

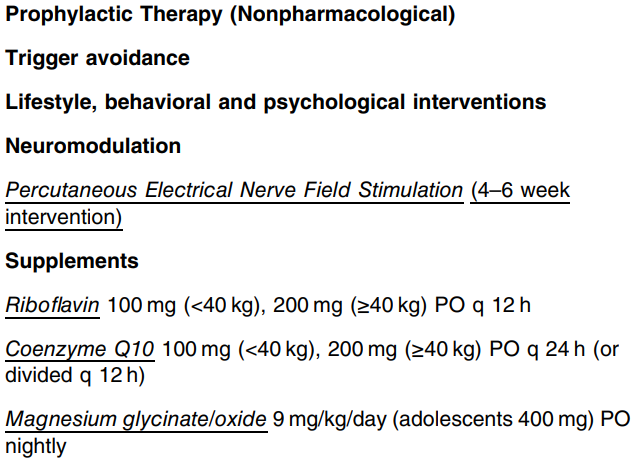
2025 Pediatric Cyclic Vomiting Syndrome Guidelines

K Karrento et al. J Pediatr Gastroenterol Nutr. 2025;80:1028–1061. Open Access! North American Society for Pediatric Gastroenterology, Hepatology, and Nutrition 2025 guidelines for management of cyclic vomiting syndrome in children

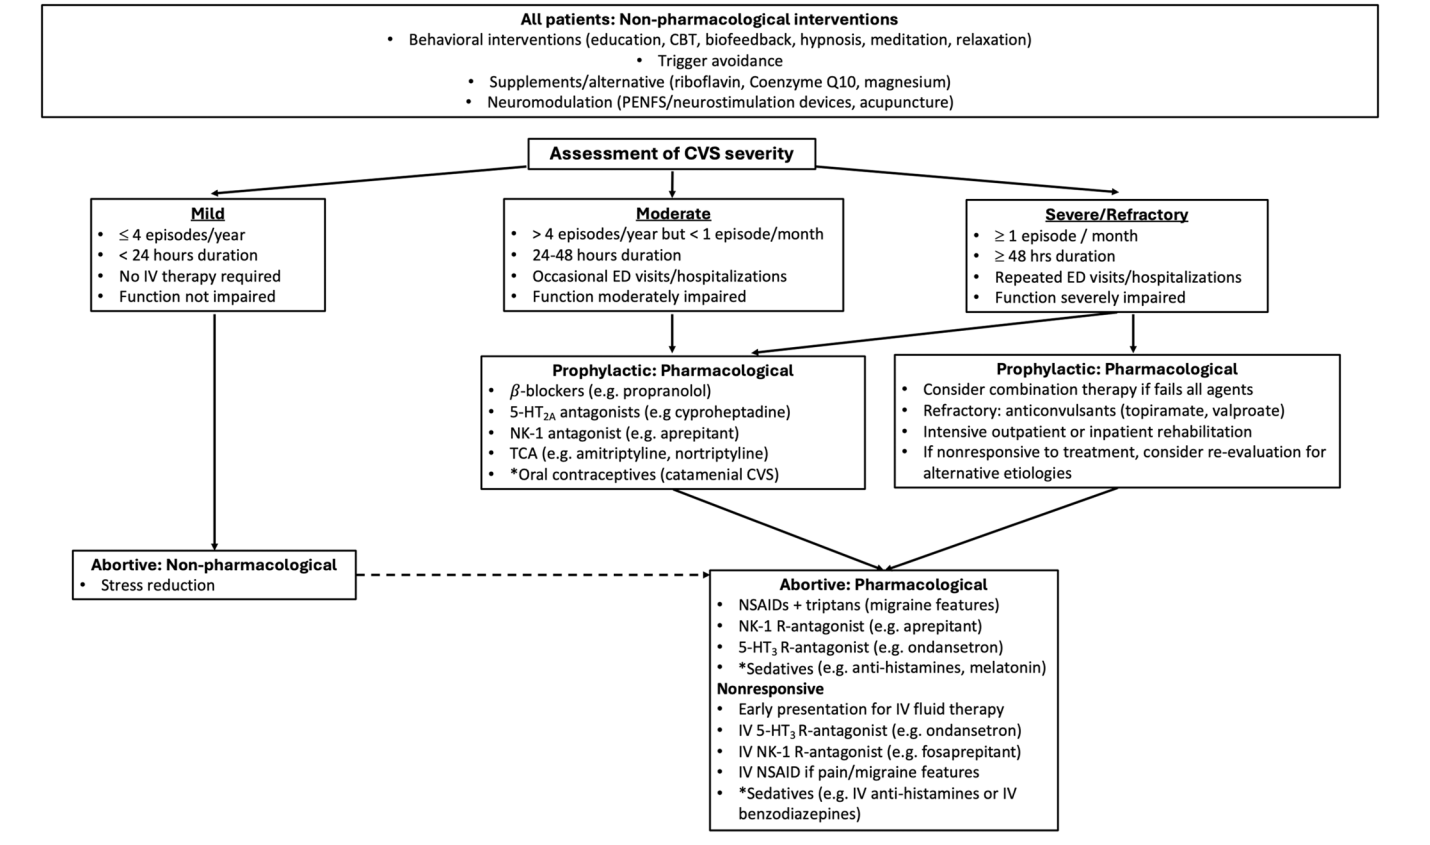
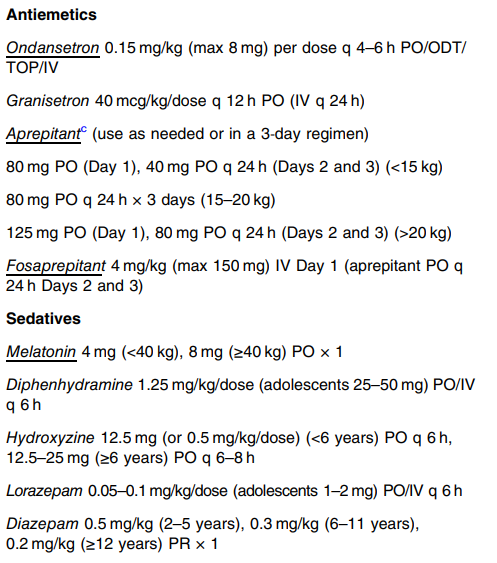
This is an excellent CVS guideline (36 pages). There is a lot of information and advice that is not easily summarized. Some important points:

  • Epidemiology: “The prevalence of pediatric CVS is estimated between 1.9% and 2.3% with an incidence of 3.2 per 100,000 children/year.1316 CVS peaks among school-aged children and often evolves into migraine headaches in adolescent years…17 56% of children experience resolution of CVS during a median follow-up of 29 months (range 6 months to 7 years)…A long-term follow-up study demonstrated progression to migraine in 26% of those with pediatric CVS.1
  • Autonomic dysfunction: “An underlying autonomic dysregulation is also supported by clinical features during attacks (diaphoresis, listlessness, palpitations, and peripheral vasoconstriction), and a study shows that 40% of pediatric patients with CVS develop chronic dysautonomia during adolescence.18
  • Cannabinoid hyperemesis syndrome: “CHS is considered a probable subtype of CVS that presents after prolonged and excessive cannabis use…26 Topical capsaicin, benzodiazepines, and droperidol or haloperidol have all been proposed as possible treatments for acute CHS episodes…50 Adult guidelines recommend that CHS patients be offered the same therapies as CVS patients…Complete cannabis cessation is the only known effective long-term treatment for CHS.”
  • Sato-variant: “This subtype manifests elevated levels of adrenocorticotropin hormone, cortisol, antidiuretic hormone, catecholamines, and prostaglandin E2, consequently presenting with hypertension and profound lethargy.25 While there is no published data for guidance, electrolyte monitoring is warranted, and episodic hypertension is generally managed by short-acting agents such as lisinopril or labetalol.”
  • L-carnitine: “The panel did not find evidence of efficacy other than when used in combination with coenzyme Q10 and cautioned against use based on concerns for atherosclerosis in animals.”
  • Propranolol: “The panel cautioned for use in patients with reactive airway disease…Retrospective studies showed high long-term efficacy of propranolol (57%–81%) when used as a first-line agent for pediatric CVS.155156 Two prospective, observational studies in pediatric CVS showed a high response rate to propranolol (77%–93%).157158 A larger (n = 81) randomized (uncontrolled and unblinded) trial demonstrated long-term effects of propranolol 1 mg/kg/day on both frequency and severity of CVS attacks with a 92% response rate and superiority over amitriptyline (53% response rate).159
  • Cyproheptadine: “Using criteria of ≥50% improvement in outcomes of interest (episode frequency and duration), 55%–75% (retrospective to randomized) met this threshold. In pediatric migraine, 83% had a positive response.”
  • Aprepitant: “The use of aprepitant two or three times per week for prophylaxis resulted in significant improvement in several essential outcomes, including episode frequency, duration, intensity, symptom-free periods, hospitalization rates, and school attendance.69169 At the 12-month follow-up, 82% of children [n=95] achieved either partial or complete treatment response.”
  • Tricyclic Antidepressants (TCAs): “The panel suggests that this medication be reserved for those with more frequent and severe disease who have not responded to therapies with more favorable side effect profiles. Caution for possible behavioral changes, including suicidality, is indicated in all children and adolescents….Using the common criteria of ≥50% improvement as definition of response (complete or partial), 57% of pediatric and 81% of adult CVS patients responded.”
  • Anticonvulsants: “The guideline panel suggests not using anticonvulsants (e.g., topiramate or valproate) for preventing CVS episodes in children and adolescents, except for refractory CVS.”

My take: While data for CVS remains limited, these guidelines are likely to influence how CVS is managed in children.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Dr. William Balistreri: Whatever Happened to Neonatal Hepatitis (Part 2)

Recently Dr. Balistreri gave our group an excellent lecture. I have taken some notes and shared some slides. There may be inadvertent omissions and mistakes in my notes.

Key Points:

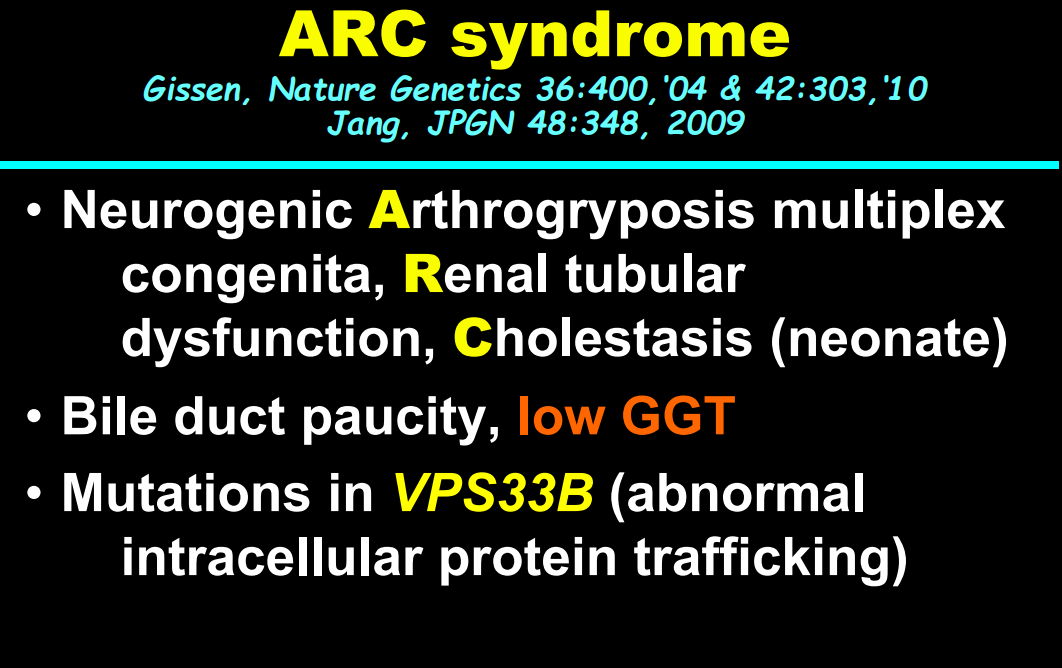
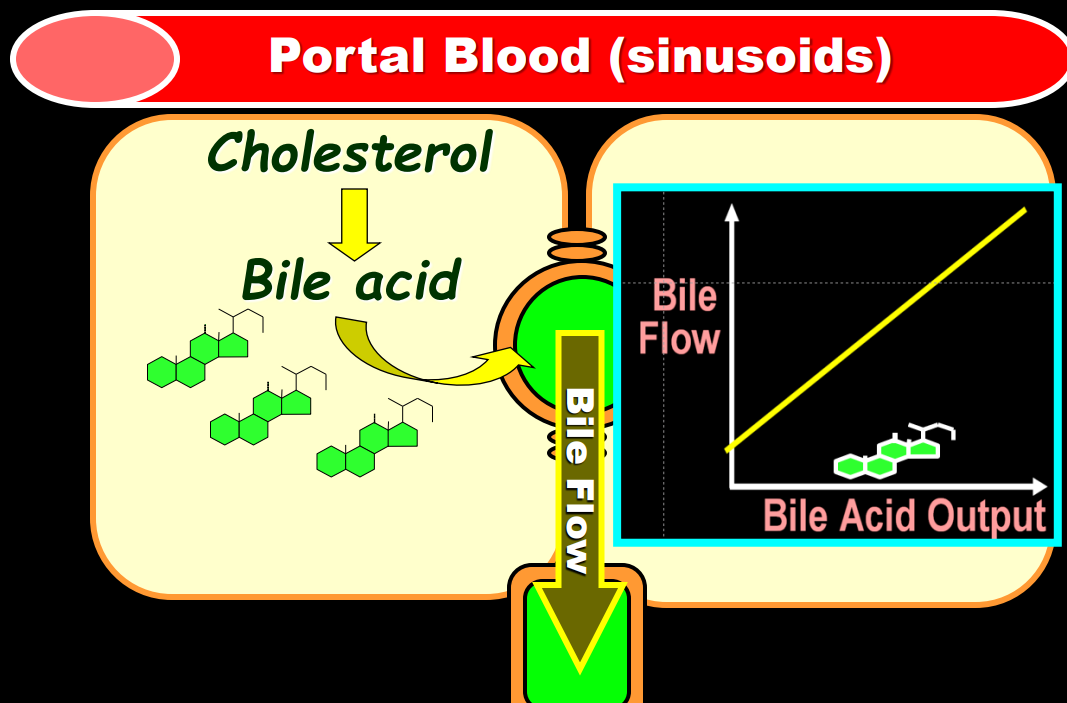
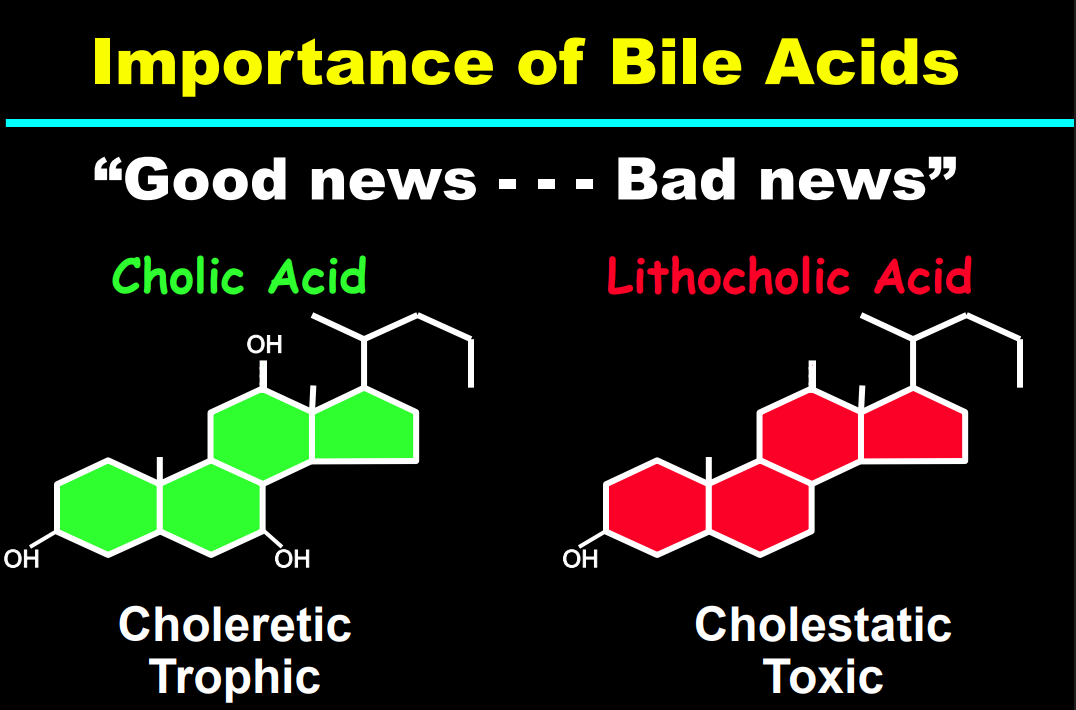
  • Producing enough bile acids and recycling bile acids in enterohepatic circulation is crucial for bile acid flow. In addition, there are ‘good’ bile acids like cholic acid that have trophic properties and ‘bad’ bile acids like lithocholic acid that cause liver toxicity
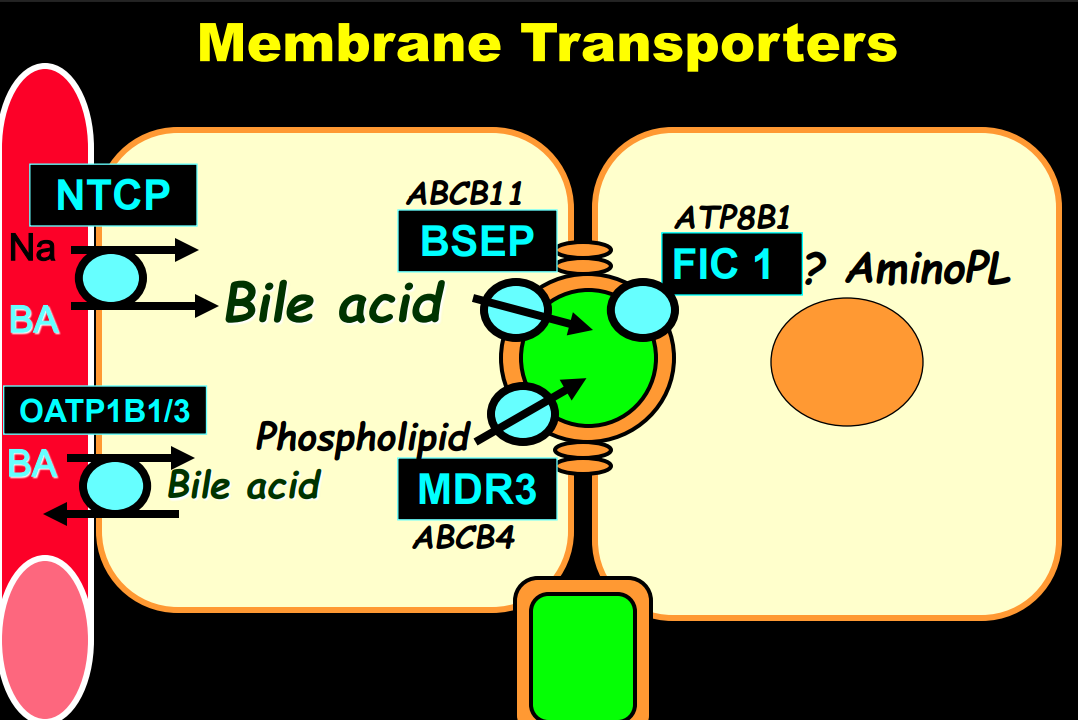
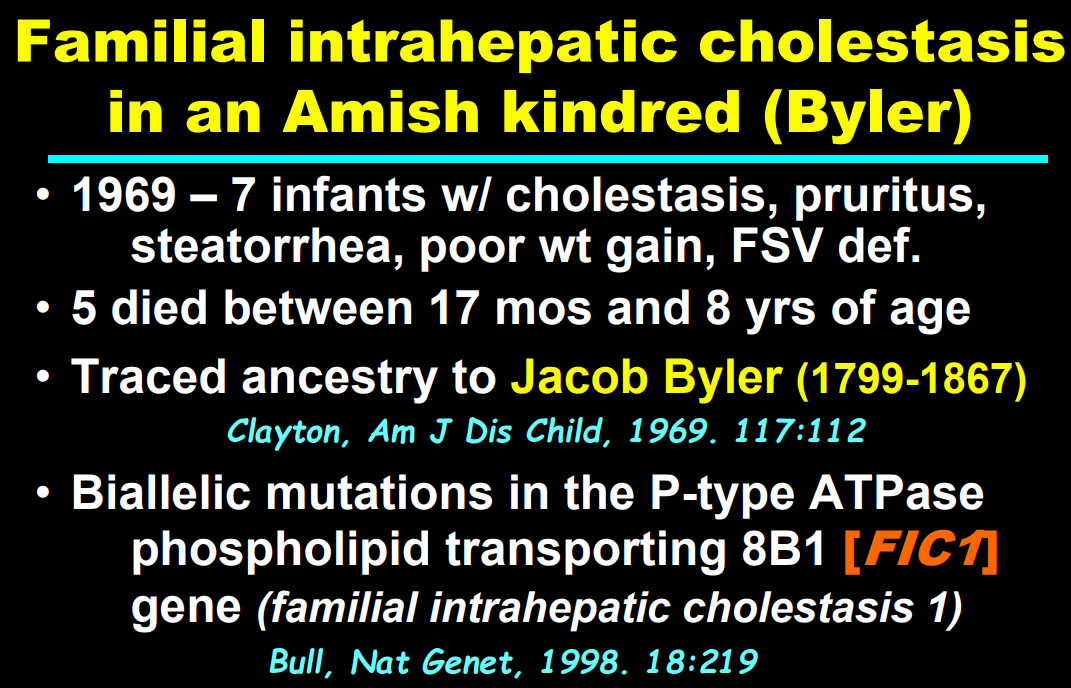
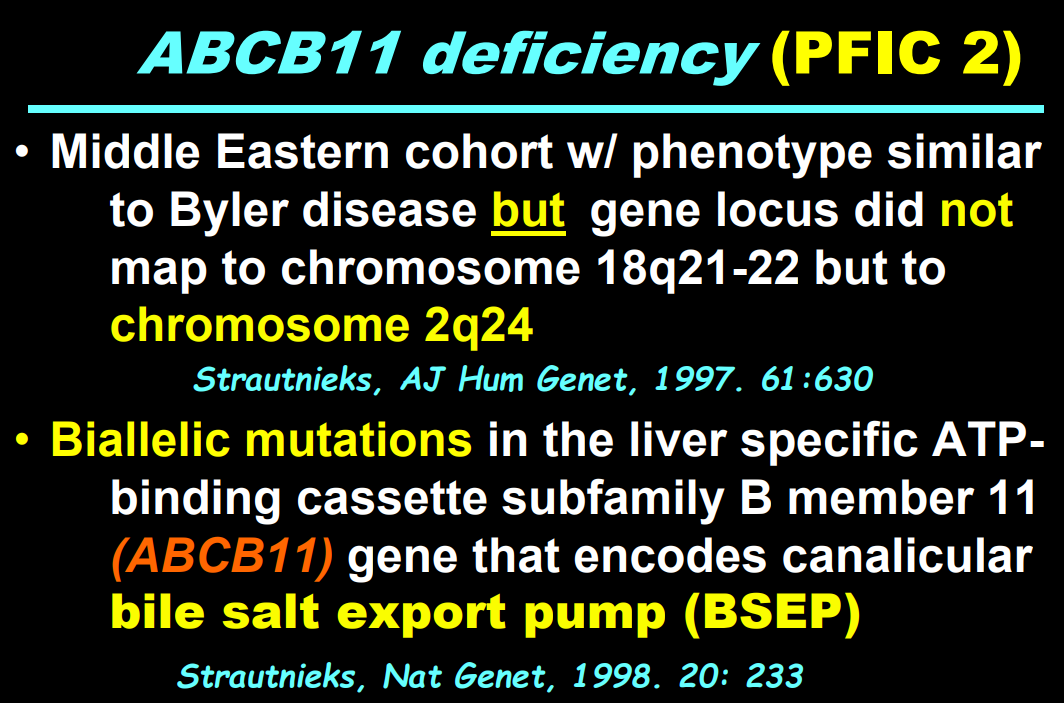
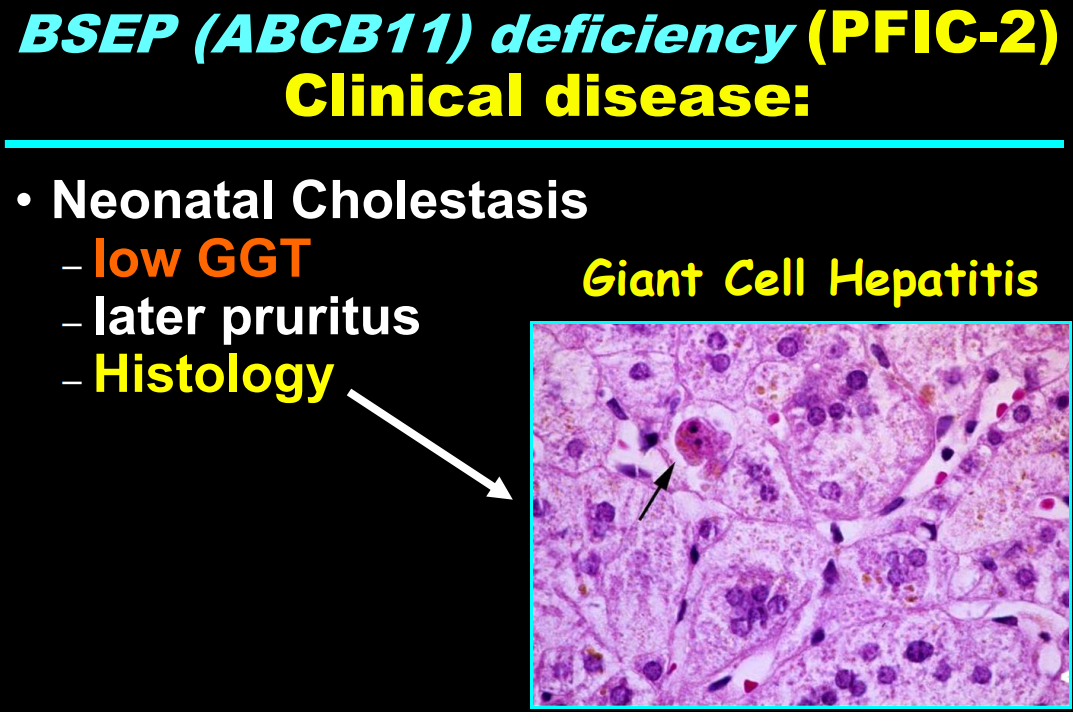
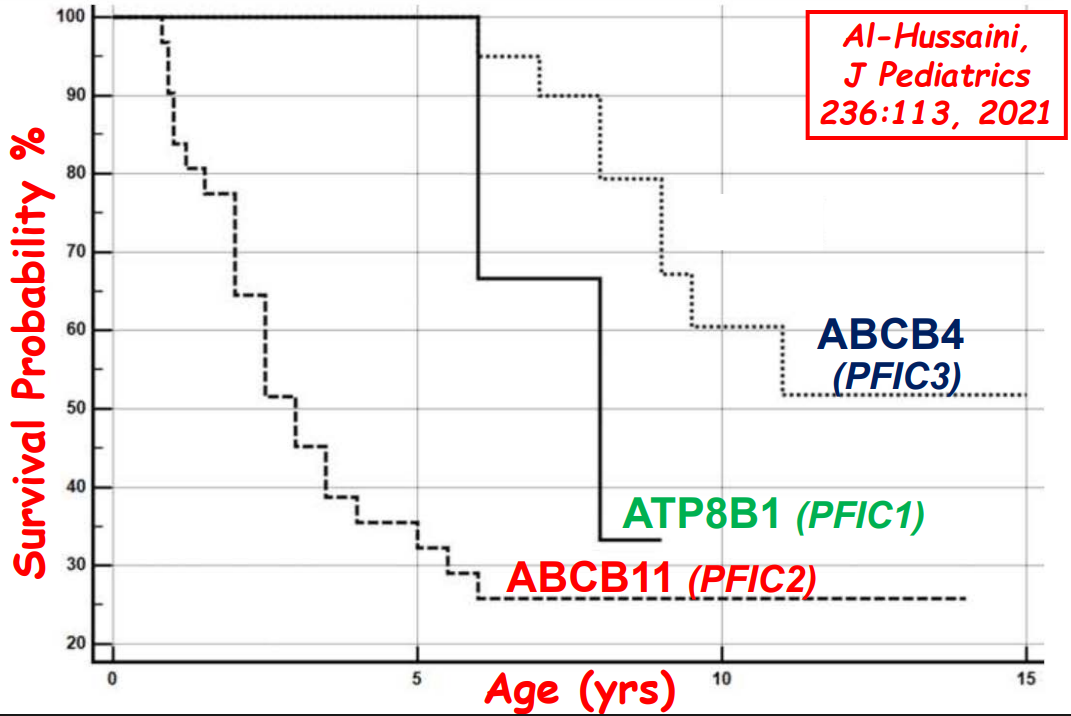
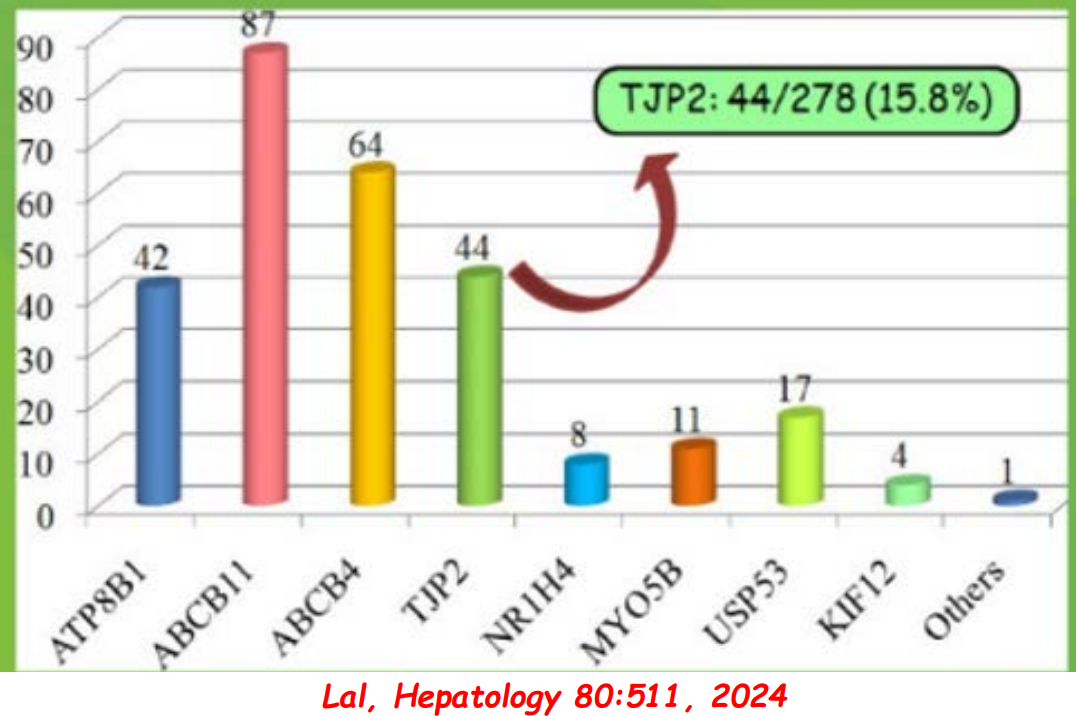
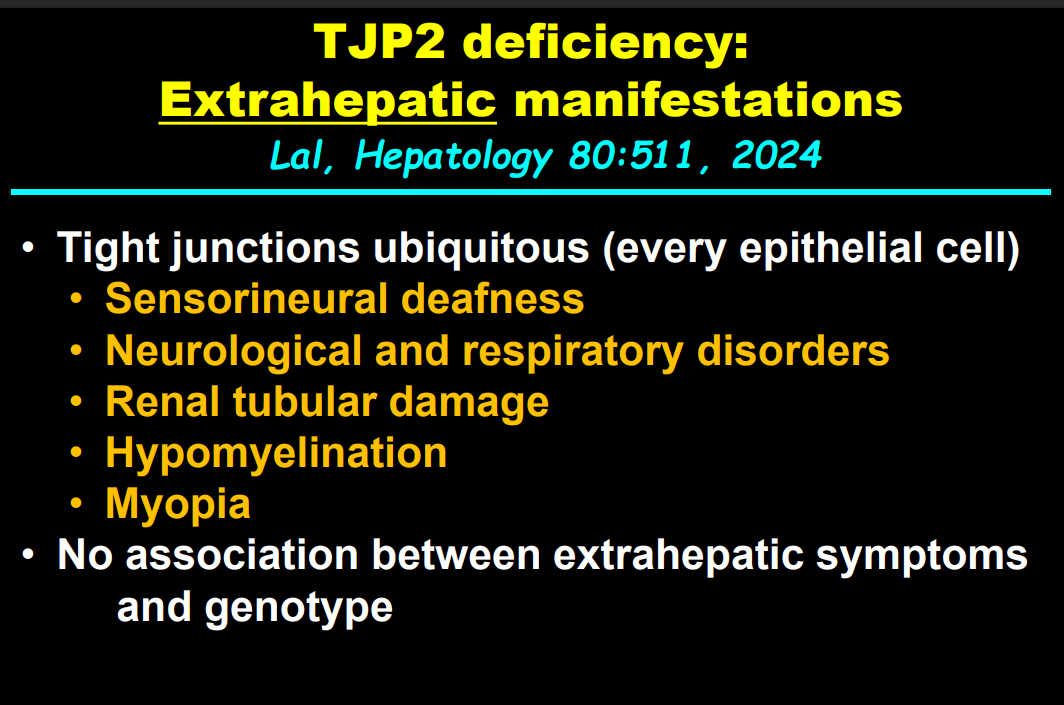
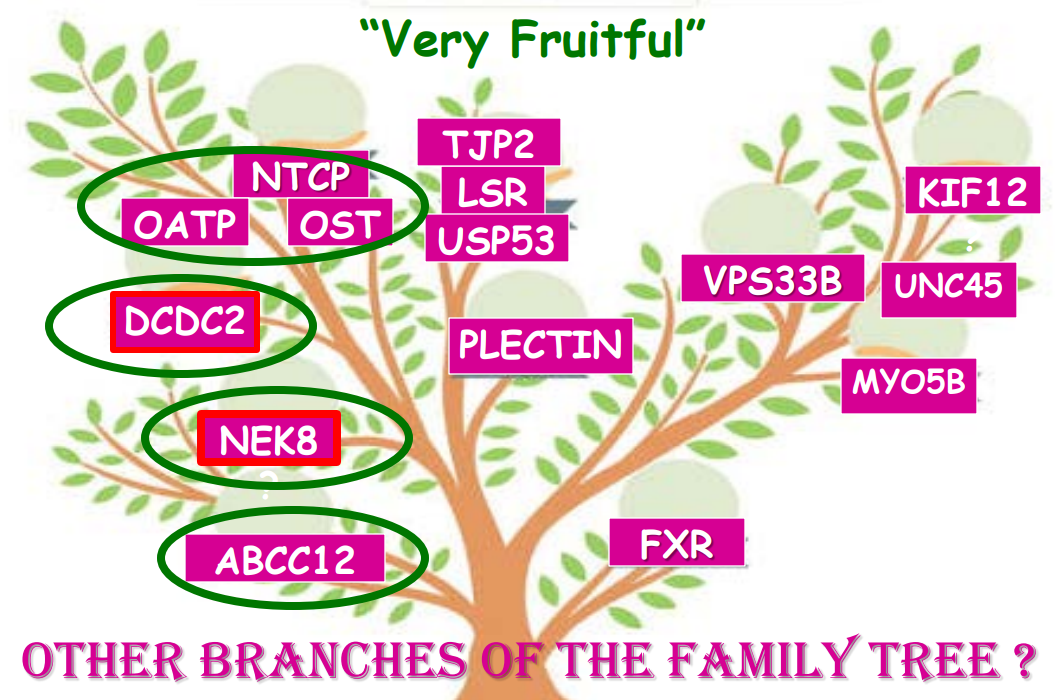
  • In addition to defects in the metabolic pathway of bile acids, discoveries identified defects in the membrane transporters (eg. FIC1, BSEP, MDR3), trafficking proteins (eg. MYO5B, VPS33B), nuclear control receptors (eg. FXR), and tight junction proteins (eg. TJP2). Tight junction protein defects are associated with bile leakage from bile canaliculus
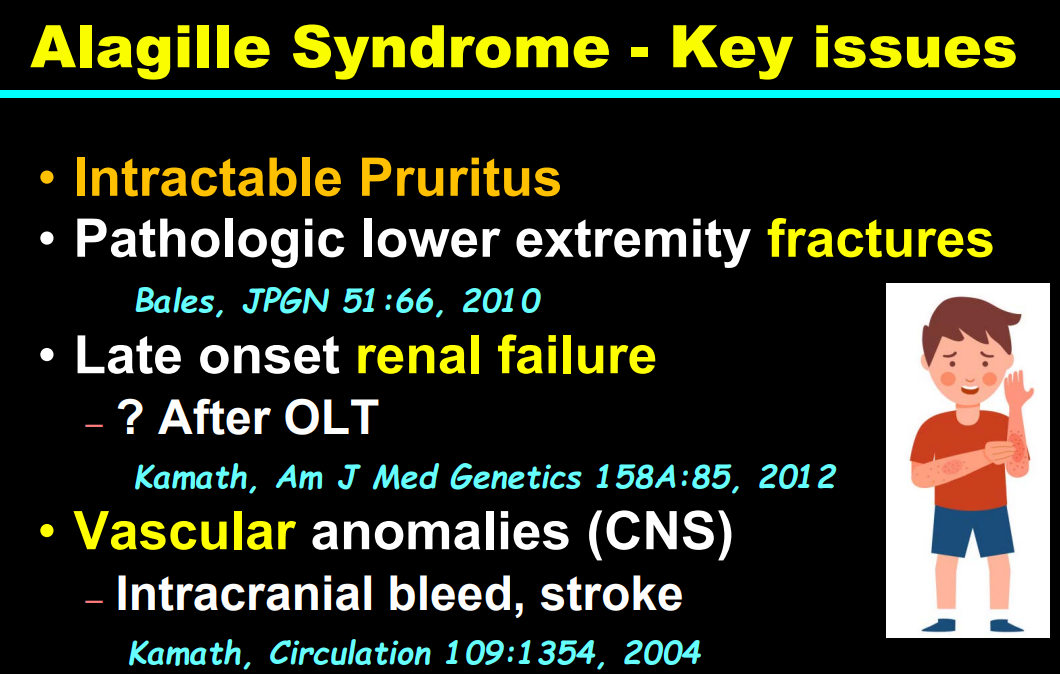
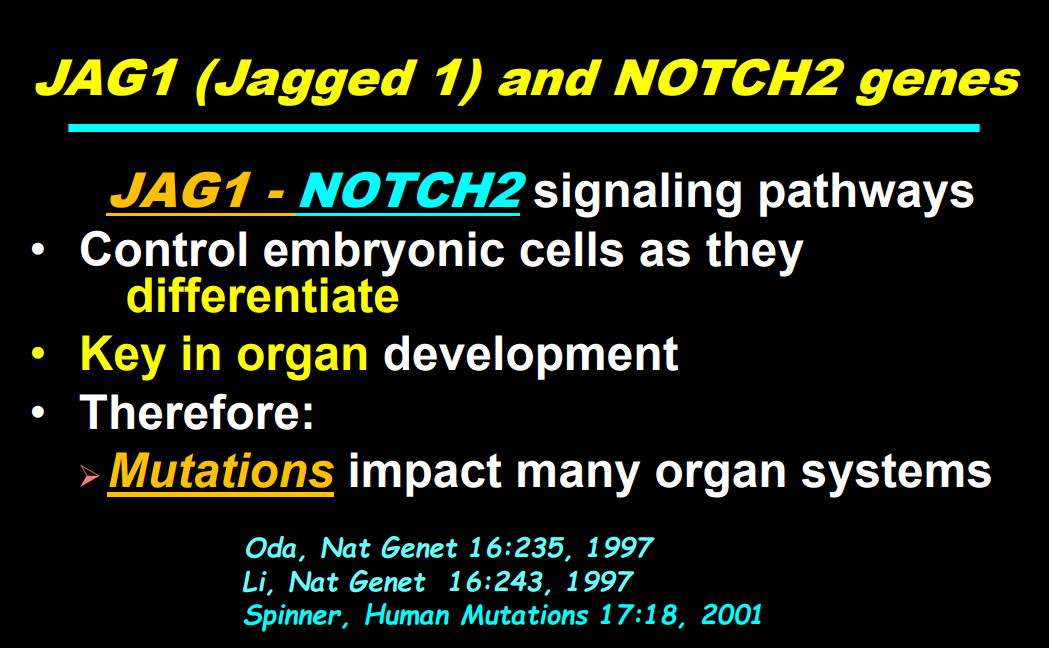
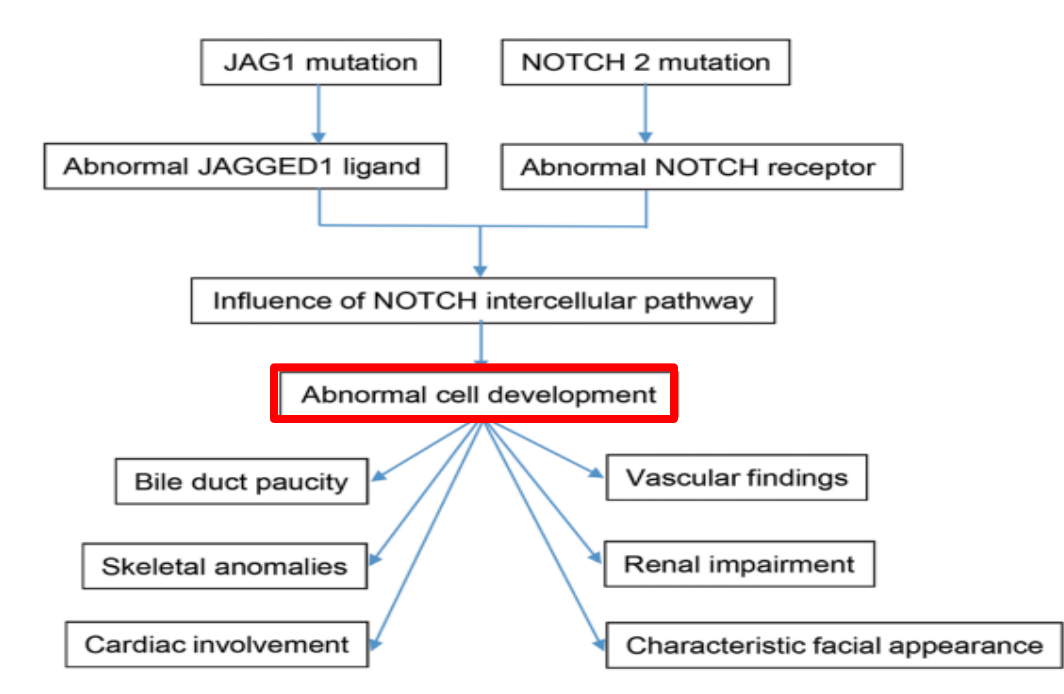
  • Alagille syndrome, a disorder of embryogenesis, related to JAG1-NOTCH2 signaling pathways affects organs throughout the body
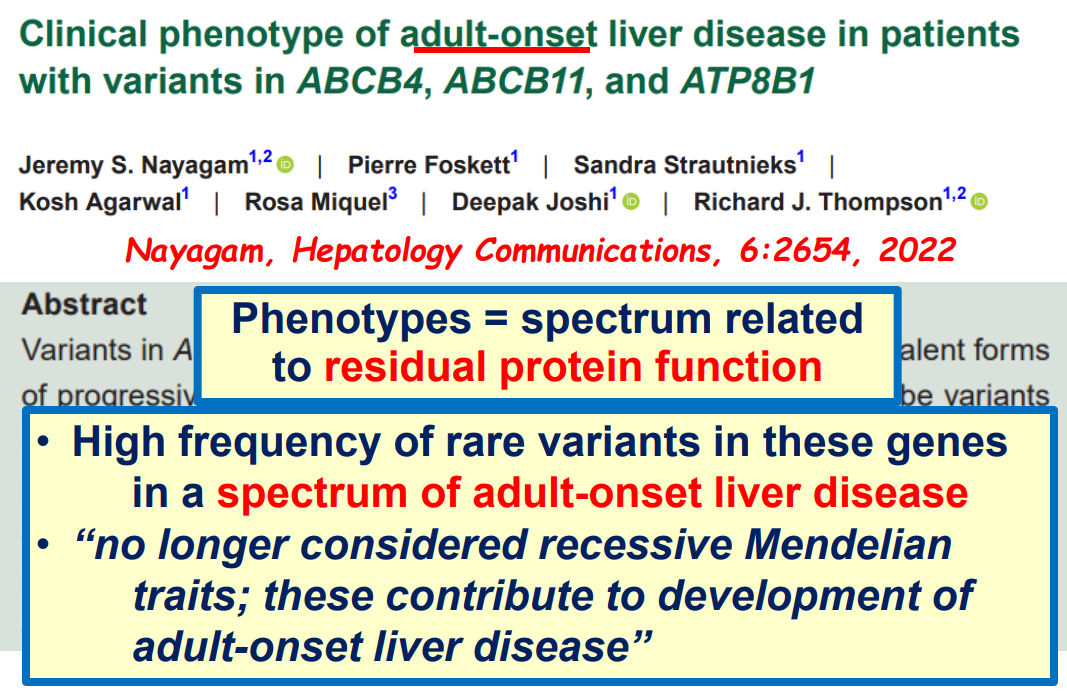
  • Many of these genetic mutations are now being identified in adults with unexplained liver diseases (eg. intrahepatic cholestasis of pregnancy and cryptogenic cirrhosis)
  • Cholestasis panels and whole exome sequencing are important tools
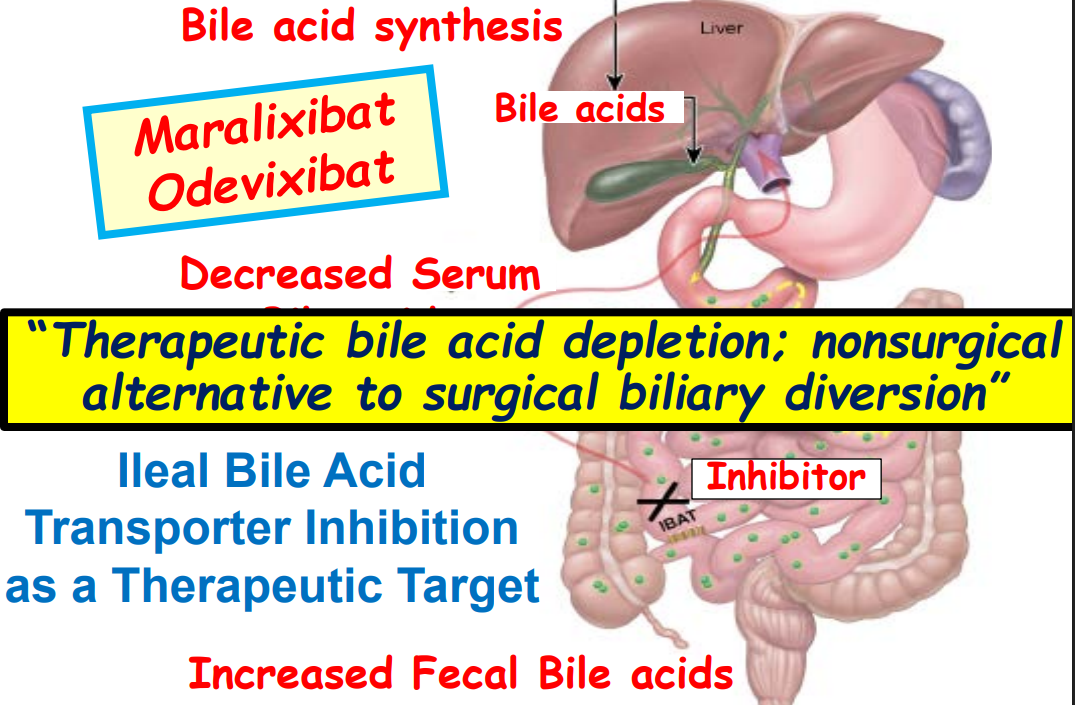
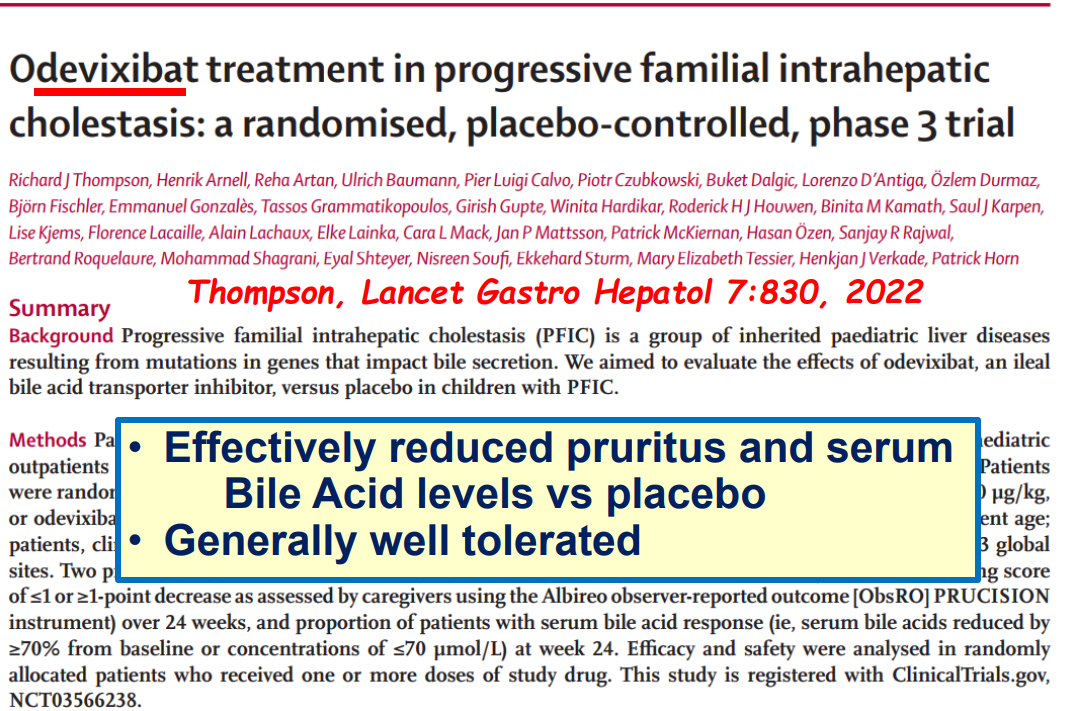
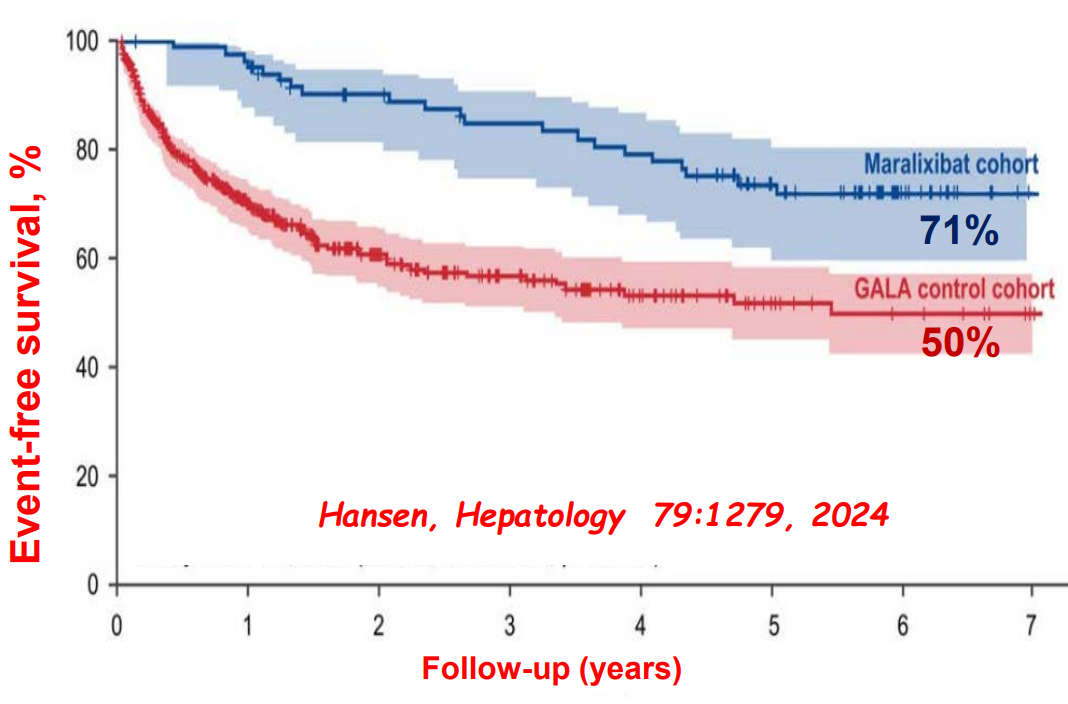
  • Ileal bile acid transporter (IBAT) inhibitors have emerged as important therapies for conditions like Alagille which were previously treated with biliary diversion

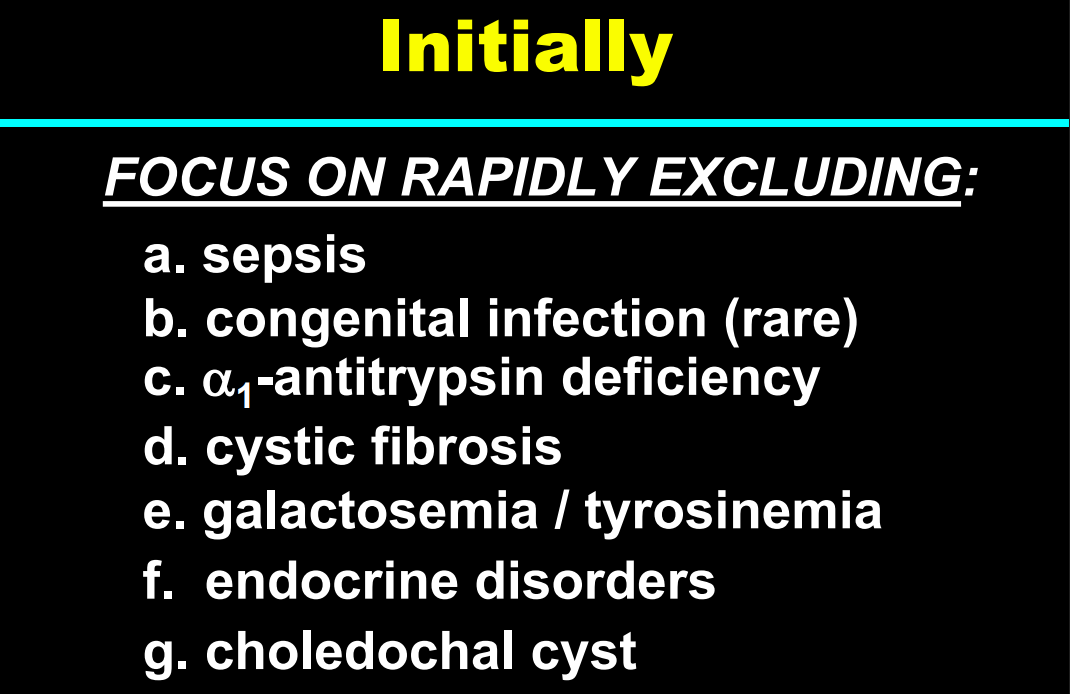
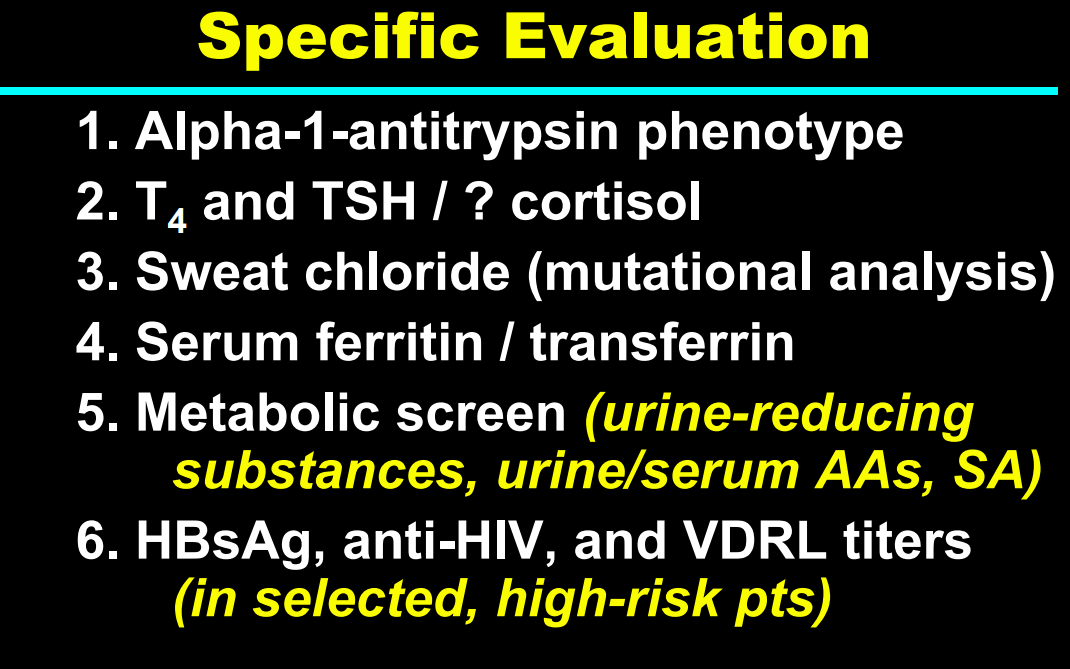
Cholestasis Evaluation:

See blog post: Identifying Biliary Atresia in Infants: New Guidelines

Baby with Carbamoyl-phosphate synthetase 1 (CPS1) deficiency (urea cycle defect)

My take: This lecture really shows how the field of pediatric liver disease has been a puzzle. Now one can see how almost all of the pieces of the puzzle work together.

Related blog posts:

Dr. William Balistreri: Whatever Happened to Neonatal Hepatitis (Part 1)

Recently Dr. Balistreri gave our group an excellent lecture. I have taken some notes and shared some slides. There may be inadvertent omissions and mistakes in my notes.

In my view, Dr.Balistreri’s contributions to our field of pediatric gastroenterology, hepatology and nutrition are unsurpassed by any other individual. This is due to his leadership roles (division director, president of AASLD and NASPGHAN), his editor roles (Journal of Pediatrics, and JPGN), his extensive publications/research including sentinel discoveries in bile acid pathophysiology and treatment, and through education (lectures and mentorship).

Key points:

  • Fifty years ago, ~65% of neonatal cholestasis cases were poorly understood and lumped together under the heading of “Idiopathic Neonatal Hepatitis” (INH). The discovery of Alpha-One Antitrypsin (A1AT) Deficiency was instrumental, indicating that there were specific medical diseases mislabeled as INH
  • A1AT deficiency proved that many cases were NOT “idiopathic,” NOT necessarily “neonatal,” and NOT “hepatitis”
  • Currently, less than 10% of infants with neonatal cholestasis are unspecified. Dr. Balistreri’s goal has been to make sure every patient receives a precise diagnosis
  • Now more than 90 genetic conditions have been recognized as causing neonatal cholestasis
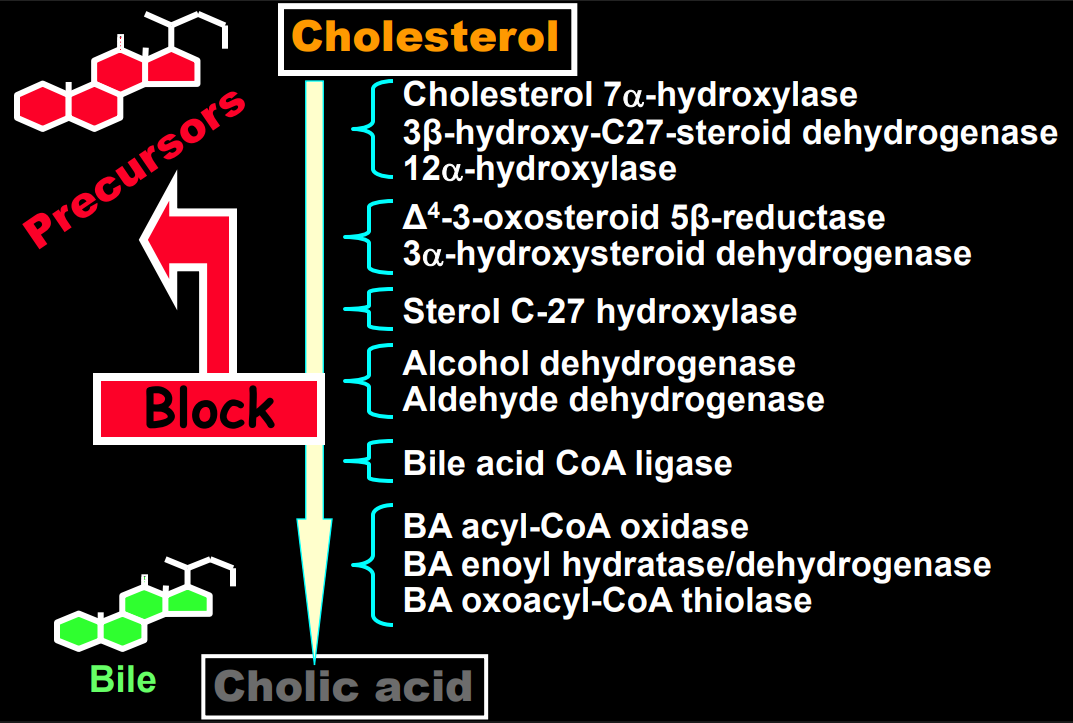
  • The journey of unraveling the reasons for neonatal cholestasis includes the referral of two infants from Atlanta by Dr. Saripkin to Cincinnati. These infants who had an older sibling who had died at 4 months of age were determined to have an inborn error of bile acid metabolism. Subsequently, they were treated successfully with cholic acid which suppressed production of toxic precursors via feedback inhibition
  • There are 11 steps in the conversion of cholesterol to bile acids; thus, it was hypothesized and later proven that there would be many other inborn errors of bile acid metabolism

Related blog posts:

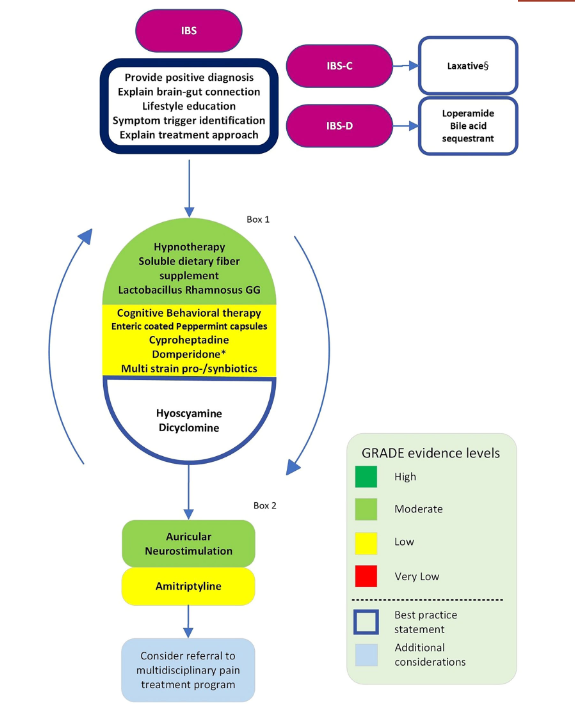
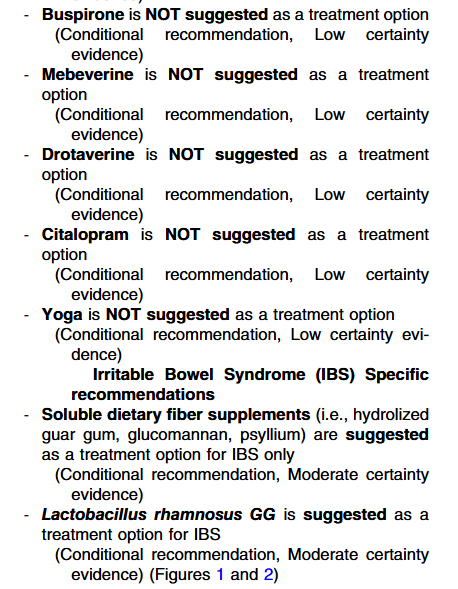
Treatment Guidelines for Pediatric Irritable Bowel Syndrome

J Green et al. JPGN 2025; Open Access! ESPGHAN/NASPGHAN guidelines for treatment of irritable bowel syndrome and functional abdominal pain-not otherwise specified in children aged 4–18 years

Overall, this article notes that the evidence based for most treatments for pediatric irritable bowel (IBS) is often lacking.

Specific recommendations:

Executive summary of Best Practice Statements‐ The Guideline Development Group (GDG) notes that a crucial emphasis should be placed on education regarding the abdominal pain‐related disorders of gut–brain interaction.

My take: This is a helpful guideline and likely to influence practice.

Related blog posts: