Understanding the Prevalence and Burden of Pediatric Inflammatory Bowel Disease in U.S.
 From editorial (which is more expansive than the study):

Kappelman et al4 report the US prevalence of pediatric-onset IBD (diagnosed before the age of 20 years by a physician) as well as rates of disease based on race and ethnic background. To ensure that a representative population was captured, they combined multiple health administrative databases…

The authors report that the US currently has a pediatric IBD prevalence of 125 per 100,000 population, increased from 110 per 100,000 in 2011. This is higher than previously reported in Canada (82 per 100,000 in 2023)6 and Sweden (75 per 100,000 in 2010).7 These differences may be due to the older age cutoff used in the US data, <20 years vs <18 years in the Canadian and Swedish studies. However, misclassification bias may also play a role...

Nevertheless, understanding the approximate prevalence of pediatric IBD in the US allows for adequate human and financial resource planning for this important population of children with an impactful chronic disease. The high prevalence should raise concerns among health care practitioners and policy makers that we have under-resourced IBD care in children, especially considering the high rate of use of biologics and the growing direct health costs incurred in the treatment of this population.11

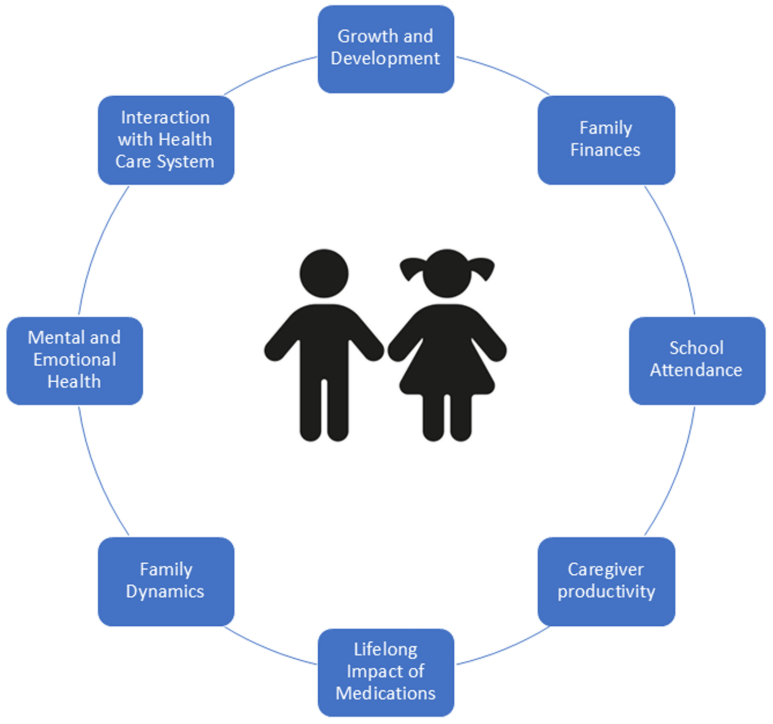
The burden of IBD in pediatrics goes beyond that of the child. Compared with adult IBD, it disproportionately affects caregivers and families (owing to missed work for appointments, hospitalizations, and home care), mental health of both the patient and the parents, and the health system...

They report that pediatric IBD is more frequent among White children and adolescents (145 per 100,000) compared with Black (91 per 100,000) and Hispanic (88 per 100,000) children, whereas children of Asian origin have markedly lower rates (52 per 100,000).

My take: The updated prevalence data helps understand the increasing frequency of pediatric IBD. The associated commentary reminds us of the broader burden the disease has for families and for our communities.

Related blog posts:

Constipation Preceding a New Diagnosis of Inflammatory Bowel Disease

S Cenni et al. J Pediatr Gastroenterol Nutr. 2025;80:799–806. The prevalence of constipation in children with new diagnosis of inflammatory bowel disease: A retrospective study

This was a cross-sectional observational study in pediatric IBD-patients (n=238) with 104 (43.6%) with Crohn disease (CD), 130 (54.6%) with ulcerative colitis (UC) and 4 (1.6%). Only patients who filled out the Rome IV questionnaire for FC, through dedicated symptom recall at the next clinic appointment or telephone recall, were finally enrolled in the study for subsequent analysis.

Key findings:

  • Forty-seven out of 238 (19.7%) had a functional constipation history before the IBD diagnosis. In the CD children the prevalence of constipation before the IBD diagnosis was 19/104 (18.2%) and in the UC patients was 28/130 (21.5%).
  • The difference in terms of endoscopic localization was statistically significant in UC patients presenting FC (p = 0.026) with a prevalence of proctitis and left side colitis (30% and 15%, respectively)
  • There was a delay in the diagnosis of patients with preceding constipation

Discussion Points:

  • The main limitations of the present study are certainly related to the retrospective nature and, therefore, the possibility of recall biases must be taken into account.
  • Rectal bleeding that persists despite stool softener therapy should be investigated

My take: While this study shows that constipation is fairly common prior to a diagnosis of IBD, many times a parent is told that their child is constipated on the basis of an xray or simply because the child complained of stomach pain. This likely increases the risk of recall bias. My guess is that a prospective study involving careful questioning at the time of the initial colonoscopy would yield a lower number of children who had constipation at the time of diagnosis.

Related blog posts:

Set of Shucked! at The Fox Theater. Really enjoyed this ‘corny’ musical.

Excellent Review of H Pylori in Children Plus One on Healthy Aging

Congratulations to my partner Ben Gold and coauthors on their recent publication –an excellent review of H pylori infection in children:

DL Mebuge, RJ Noel, BD Gold. Current Treatment Options in Pediatrics 2025; 11:13. doi.org/10/1007/s40746-025-00328-6. Open Access: Helicobacter pylori in Children: An Individualized Approach to a Worldwide Disease

Related blog posts:

For those interested in healthy aging/healthspan, Eric Topol had a recent interview with Katie Couric (54 minutes): On the State of US Life Science and Extending Healthspan

MMR Vaccination Safety in Immunocompromised Kids with IBD and Liver Transplant

A Keutler et al. Vaccine 2025; 59: 127288. Open Access! Safety and immunogenicity of the measles-mumps-rubella vaccine in immunocompromised children with inflammatory bowel disease, or after liver transplantation: An observational study

Background: “Measles is a highly contagious disease and, despite the availability of a safe and effective vaccine, remains still an important cause of childhood death worldwide [1,2]. The risk of severe illness in measles-naive individuals is particularly high in immunocompromised patients with inflammatory bowel disease (IBD) or after liver transplantation (LT) [3]…Ideally, vaccination with live attenuated vaccines (LAVVs) should be completed four weeks before organ transplantation or the initiation of immunosuppressive therapy (IST) to allow for the live vaccine’s incubation period and minimize the risk of vaccine-associated disease…LAVVs are considered contraindicated during IST due to safety concerns and limited experience.”

Methods: “In this prospective multicenter observational study (DRKS00014569) 22 children and adolescents with incomplete MMR vaccination status were identified… with stable immunosuppressive therapy in the last three months with no evidence of underlying disease activity…Sixteen patients were vaccinated against MMR, eleven after liver transplantation and five with inflammatory bowel disease. At the time of vaccination, four patients were receiving moderate (e.g., tacrolimus drug level below 5 ng/ml), eleven were receiving high-intensity immunosuppression (e.g. anti-tumor-necrosis factor agents, mycophenolate mofetil) and one child had previously discontinued immunosuppressive treatment.”

Immediately prior to the references, the authors provide a downloadable document detailing how they chose to categorize the degree of immunosuppression and their precise protocol, including immunologic pretesting and drug contraindications as noted below.

Key findings:

  • There were no serious adverse events or complications related to the vaccination
  • In children receiving immunosuppressive medications, the seroconversion rate for measles after the first MMR vaccination was 73.3 % (11/15) and after the second vaccination 80 % (12/15)

My take: In carefully-selected immunocompromised pediatric patients, the MMR vaccine may be safe. However, given the small numbers receiving vaccination in this study, the absolute safety is unclear. Even infrequent adverse effects would be problematic. This study’s protocol could be helpful for those considering vaccination in immunocompromised populations with a measles epidemic. For now, the most important approach is improving vaccination rates in those (especially family members) without contraindications.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Personal Quest Update: The Beginning of the End for the Penny & World Button Battery Day

As I noted in a blog in 2012, I had advocated for removal of the penny due to frequent ingestions (starting more than 20 years ago) (link: “Watch for change in the stools”). Now it appears I will finally get my wish.

RP Jones, Reuters, 5/22/25: US Treasury unveils plan to end production of penny coin

An excerpt:

In recent weeks, Republican and Democratic lawmakers introduced separate bills in the House of Representatives and the Senate calling for an end to penny production. The change means that businesses will have to start rounding the prices of cash transactions up or down to the nearest five-cent nickel as the number of pennies in circulation dwindles.

The Treasury’s penny phase-out plan was first reported by the Wall Street Journal…The cost of producing the penny has risen from 1.3 cents per coin to 3.69 cents over the past 10 years, according to the Treasury. It said stopping production will lead to immediate annual savings of $56 million. The penny was first issued by the government in 1793

Related article:

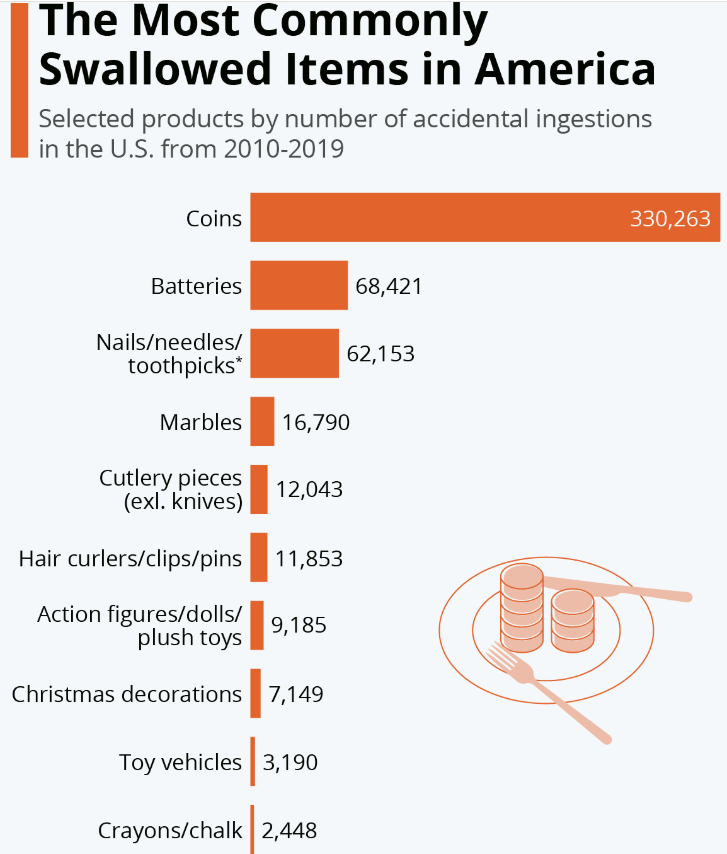
K Bucholtz, Statista 6/11/20: The Most Commonly Swallowed Objects in America

The following statistic will delight fans of obscure facts and overbearing bureaucracy: According to the U.S. Consumer Product Safety Commission, more than 850,000 accidental ingestions of everyday objects were recorded in the U.S. between 2010 and 2019. ..Coins topped the list of accidental ingestions, with around 33,000 being recorded each year (more might go unreported).

*According to the U.S. Consumer Product Safety Commission, 

My take: While this is a step in the right direction, there are still 114 billion pennies currently in circulation in the U.S. according to the Reuters article. Perhaps, other coins will be ingested less in the coming years too as so many business transactions are via smartphones and credit cards.


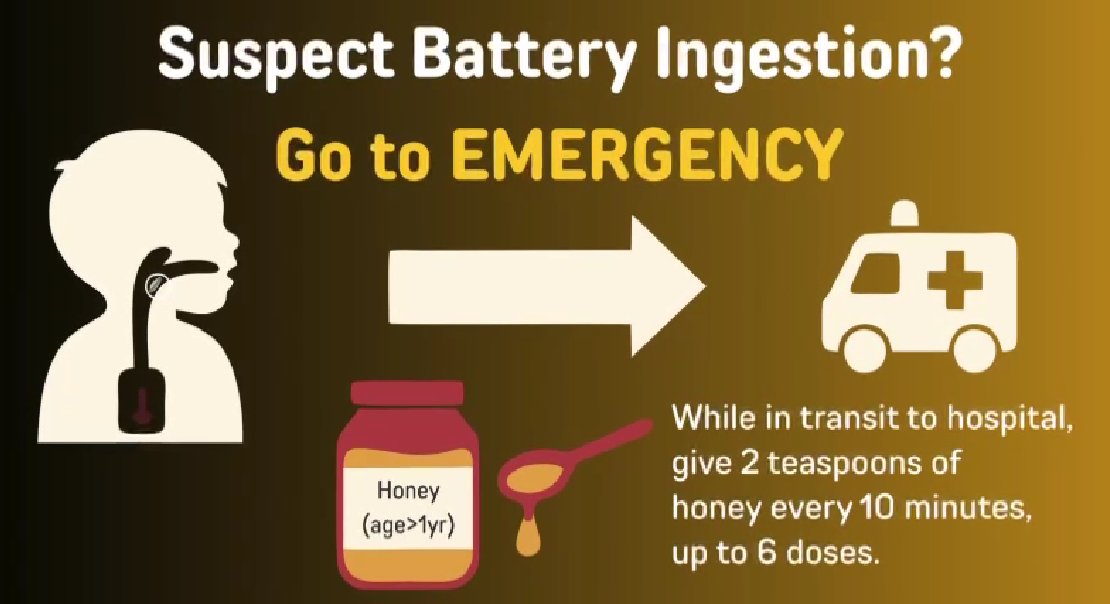
Button batteries are a much more serious ingestion than a coin. For World Button Battery Day, here’s a link to a 3 minute video from FISPGHAN. FISPGHAN Button Battery Video

The video provides a simple explanation of the problem though at times it is not certain who the target audience is. Particularly the first part feels like a video for kids rather than for parents. Thanks to Ben Gold for sharing this link.

Aso, Link: FISPGHAN Button Battery Website

Related blog posts:

Eosinophilic Esophagitis: Once vs Twice Daily Steroid Treatment

CC Reed et al. Clin Gastroenterol Hepatol 2025; 23: 946-953. Open Access! Daily or Twice Daily Treatment With Topical Steroids Results in Similar Responses in Eosinophilic Esophagitis

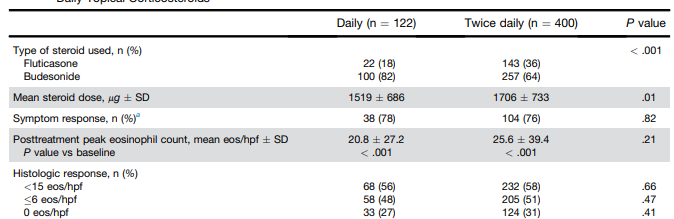
Methods: This was a retrospective cohort study using the UNC EoE Clinicopathologic Database of newly diagnosed patients with EoE treated with a tCS who had a follow-up endoscopy with biopsy. In total, there were 522 patients, including 195 pediatric patients (<18 yr). 122 patients received once daily dosing and 400 patients received twice daily dosing.

At our center, patients are typically treated on a clinical basis with either oral viscous budesonide or fluticasone from a multidose inhaler, with daily doses ranging from 1–2 mg for budesonide and 440–1760 μg for fluticasone based on patient size and at the discretion of the provider.

Key findings:

  • Global symptomatic response (78% vs 76%; P = .82), posttreatment eosinophil count (20.8 vs 25.6; P = .21), posttreatment EoE Endoscopic Reference Score (2.2 vs 2.2; P = .92), and histologic response (<15 eos/hpf; 56% vs 58%; P = .66) did not differ by dosing frequency
  • Candida was less frequent with daily dosing (2% vs 8%; P = .04)

My take: This study suggests that once daily dosing can be as effective as twice daily dosing. It may be that the total dose administered may be more important than the frequency. More studies are needed to confirm these results.

Related blog posts:

How HLA DQA1*05 and Combination Therapy Modulate Treatment Outcomes in Children with Crohn’s Disease
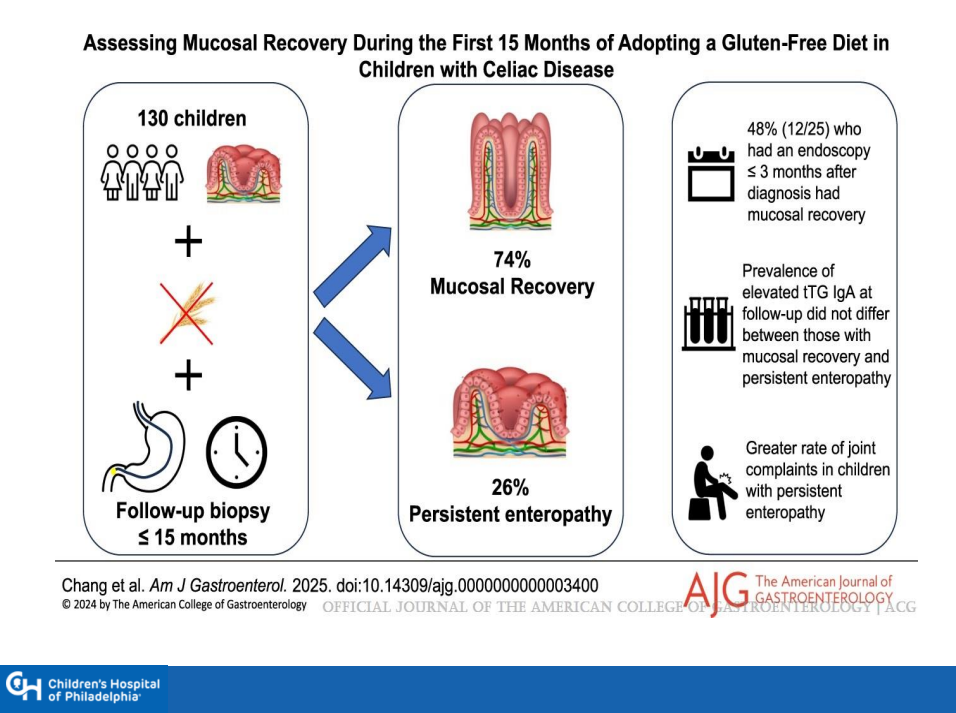
J Adler et al. Am J Gastroenterol 2025; 120: 1076-1086. HLA DQA1*05 and Risk of Antitumor Necrosis Factor Treatment Failure and Anti-Drug Antibody Development in Children’s with Crohn’s Disease.

This was a prospective, double-blind, placebo-controlled trial with 204 patients examining the clinical outcomes of anti-TNF with or without methotrexate (COMBINE).

Key findings:

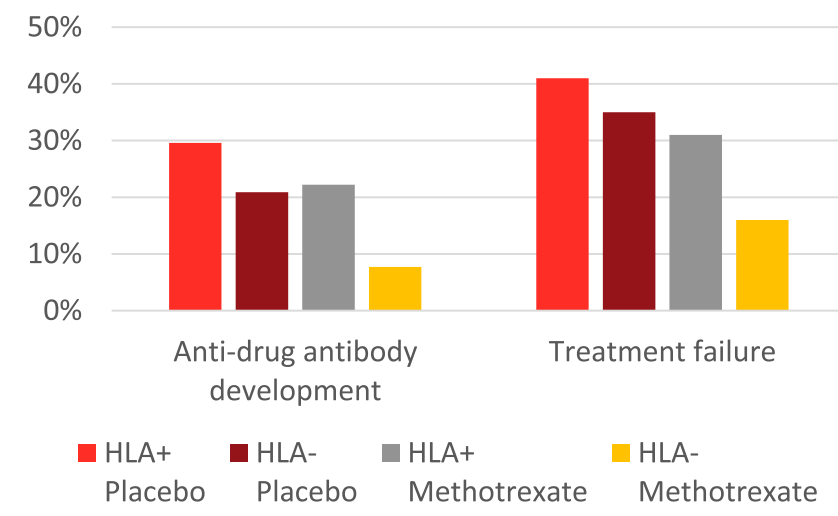
  • Treatment failure in HLA DQA1*O5: A trend toward increased treatment failure among HLA DQA1*05-positive participants was not statistically-significant (hazard ratio 1.58; P = 0.08).
  • HLA DQA1*05 and Treatment Failure Rate: During the followup period, HLA DQA1*05-positive patients had a 35% failure rate compared to 26% for those who were HLA DQA1*05-negative (P=0.098). The overall failure rate was 30%
  • Methotrexate Combined with HLA DQA1*05 Effect: Patients who were HLA DQA1*05 negative and assigned to methotrexate experienced less treatment failures than HLA DQA1*05-positive patients on placebo (hazard ratio 0.31, 95% CI 0.13-0.70; P = 0.005).
  • Anti-TNF Medication Comparison: Treatment failure was similar between infliximab and adalimumab, 29% and 33% respectively
  • Antidrug antibodies (ADA): A trend toward increased ADA development among HLA DQA1*05-positive participants was not significant (odds ratio 1.96, P = 0.09). The addition of methotrexate to the treatment regimen mitigated the risk of treatment failure among individuals positive for HLA DQA1*05 and reduced the odds of developing ADA by 90%.
  • Rate of ADA: “After further stratification, HLA DQA1*05-negative participants assigned to methotrexate were less likely to develop ADA relative to HLA DQA1*05-positive patients on placebo (odds ratio 0.12; P = 0.008).”

Discussion Points:

  • “A retrospective by Fuentes-Valenzuela et al …found that if patients underwent proactive TDM, there was no increase in the rate of treatment discontinuation among those who were HLA DQ-A105 positive compared with HLA DQ-A105 negative”
  • “The totality of evidence suggests that HLA DQ-A1*05 seems to confer a risk of both immunogenicity and treatment failure, particularly among infliximab-treated patients. Furthermore, this risk may be mitigated by the use of proactive TDM and/or concomitant immunomodulators.”

My take (borrowed in part from authors):  “40% of patients were HLA DQ-A1*05 positive, which was associated with a trend toward increased risk of both treatment failure and ADA. These risks were mitigated, but not eliminated, by adding oral methotrexate.” The use of combination therapy (methotrexate with anti-TNF) was associated with the lowest failure rates.

Also, unrelated article: DA Carlson et al. Gastroenterology 2025; 168: 1114-1127. A Standardized Approach to Performing and Interpreting Functional Lumen Imaging Probe Panometry for Esophageal Motility Disorders: The Dallas Consensus. Congratulations to Dr. Garza from our group who was one of the authors

Related blog posts:

Dr. Arun Singh: Tips and Tricks to Managing Celiac Disease
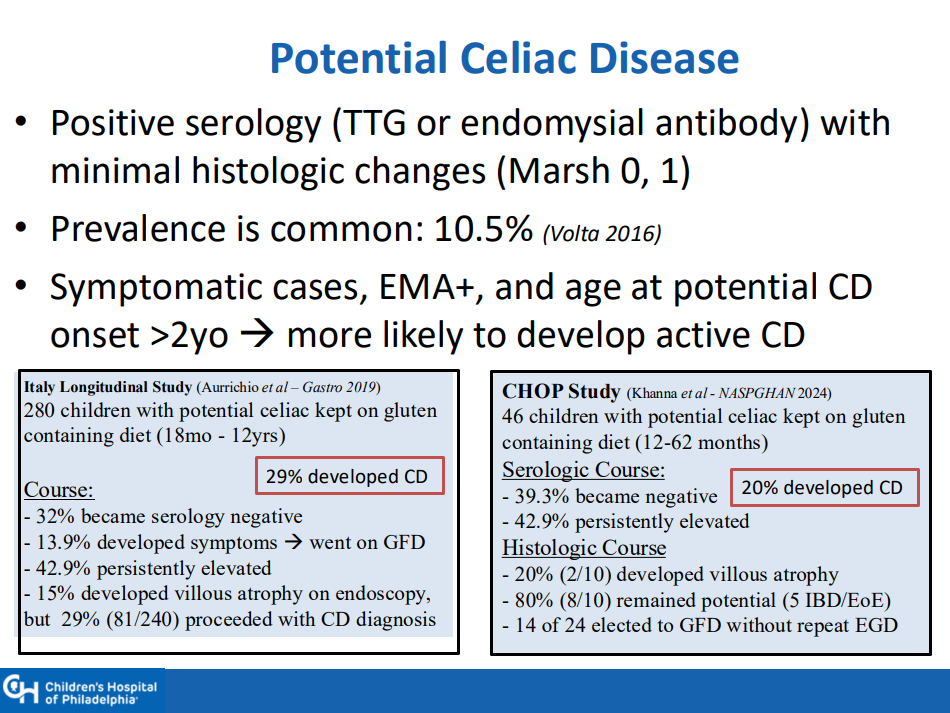
Recently Dr. Arun Singh gave our group a terrific update on Celiac Disease. I have taken some notes and shared some slides. There may be inadvertent omissions and mistakes in my notes.

Key points:

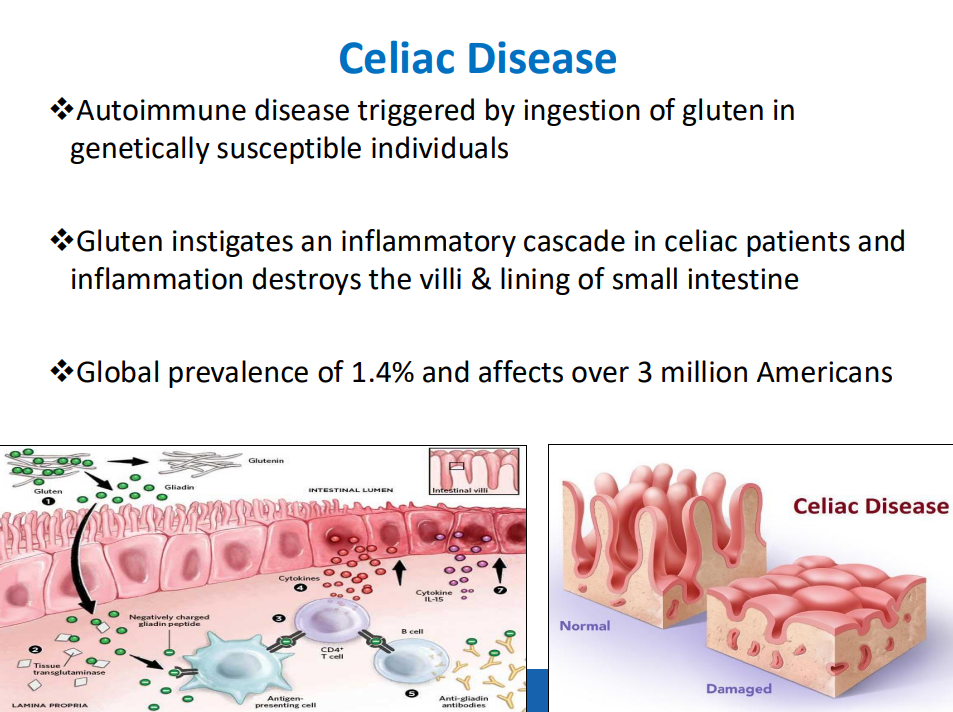
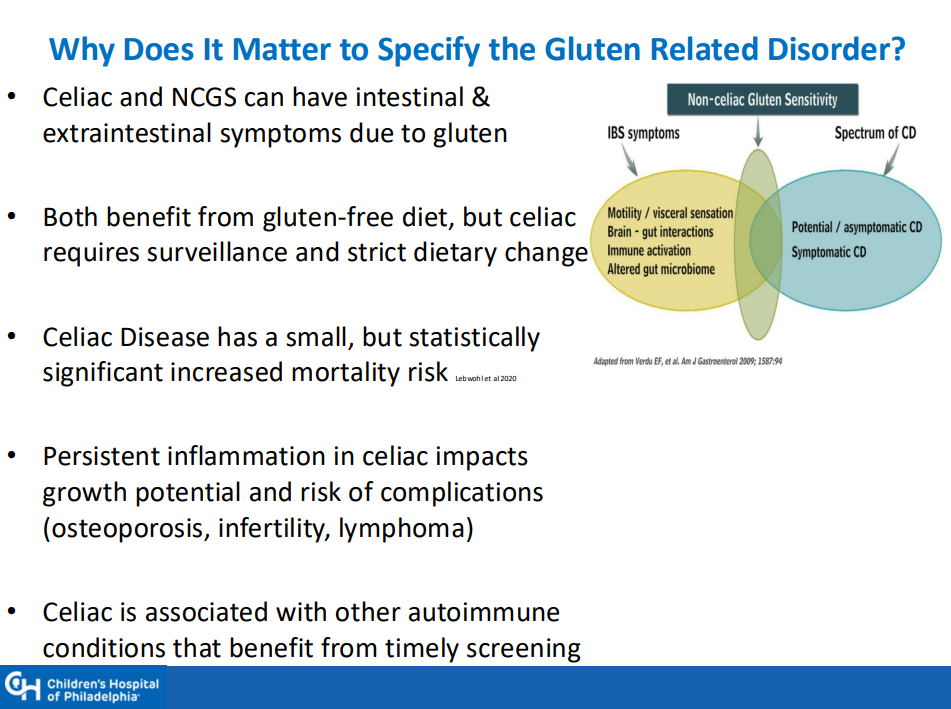
  • Celiac disease (CD) global prevalence is about 1.4%, though there are ‘pockets’ with much higher rates (~3% prevalence in Colorado). This equates to more than 3 million Americans with CD
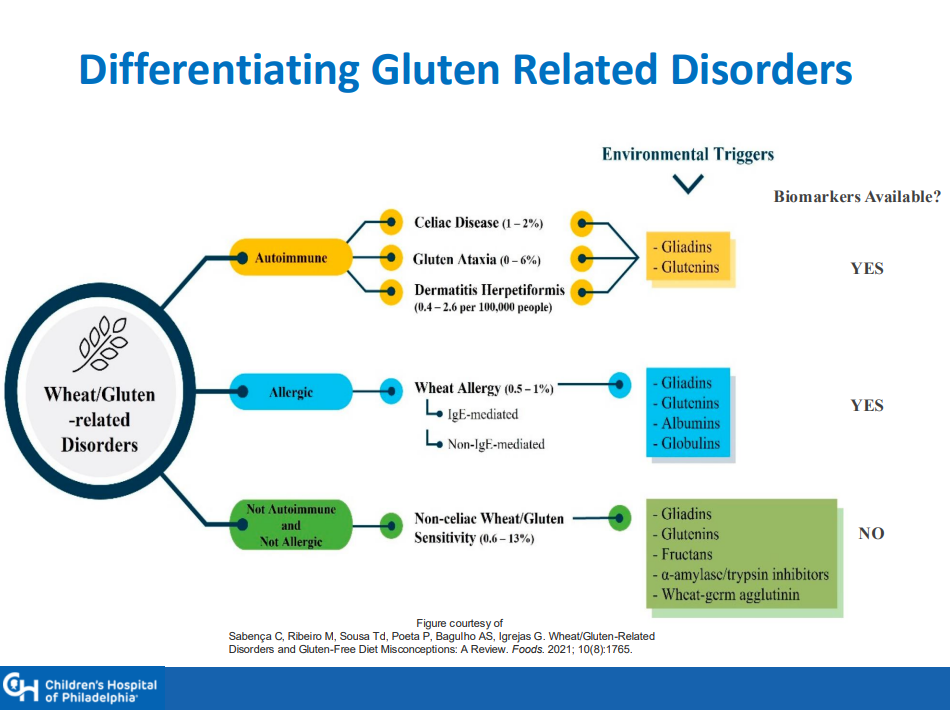
  • There is a huge gluten free diet market of ~$7 billion. This market includes CD, nonceliac gluten sensitivity (NCGS) and those with wheat allergies
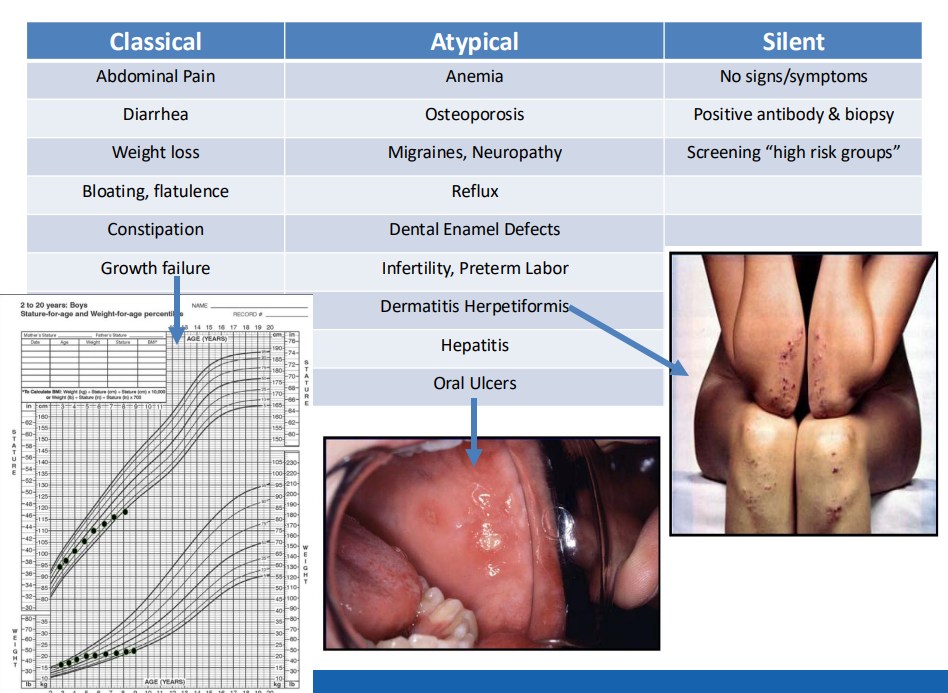
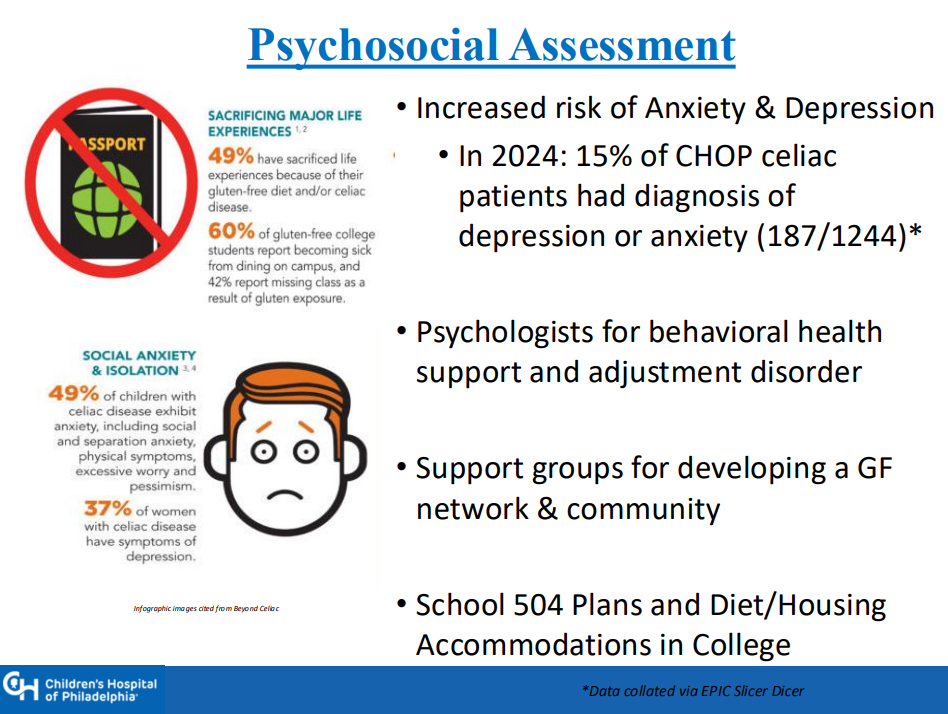
  • Many patients have atypical symptoms which can include ADHD, brain fog, headaches, and elevated LFTs. Many have silent CD with no symptoms
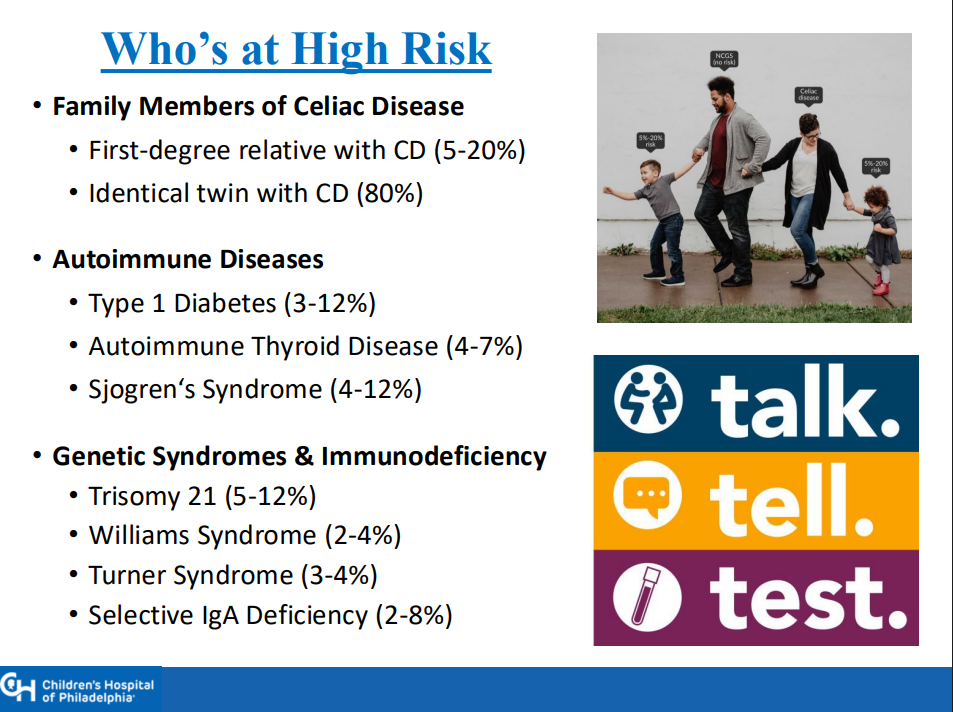
  • Higher risk groups include family members (~10% risk for 1st degree, ~80% risk for identical twin), autoimmune diseases (thyroid, diabetes, others), and genetic disorders (Down syndrome, Williams syndrome, Turner syndrome)
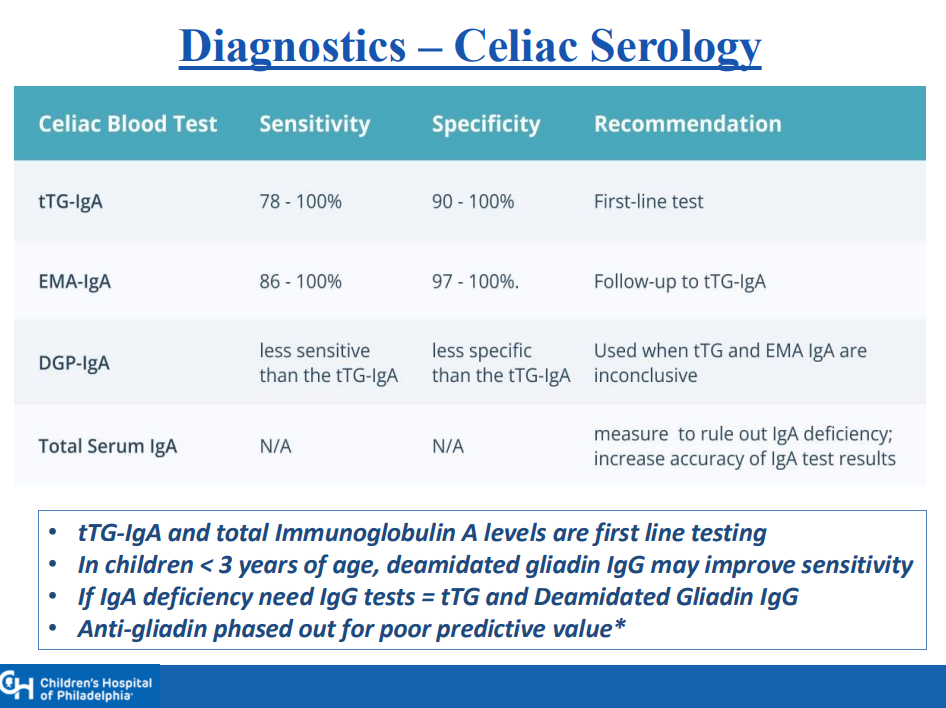
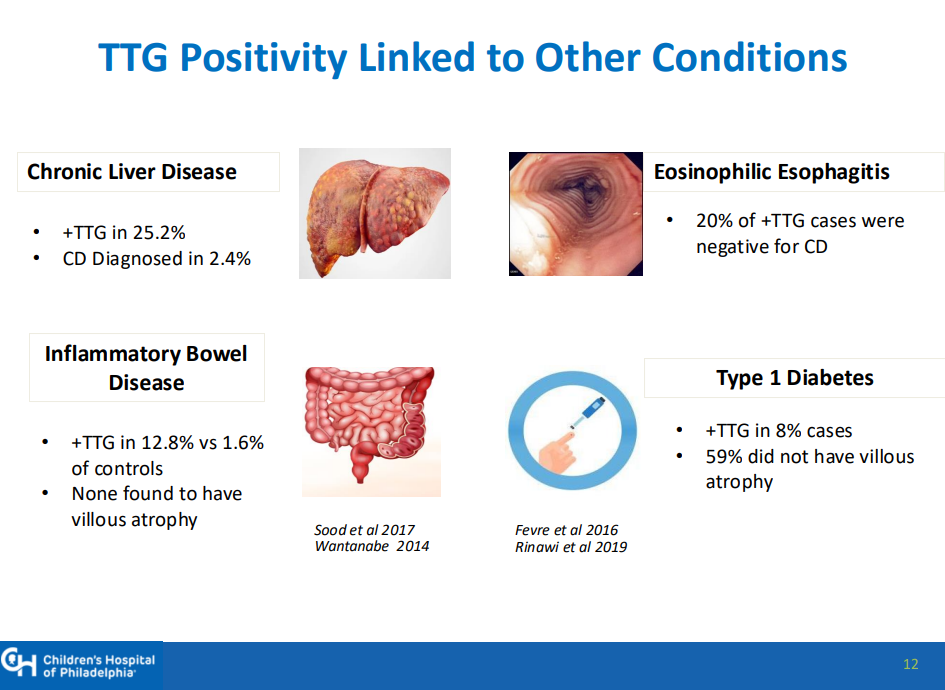
  • Transient elevation of TTG IgA is common. In TEDDY study, 19% had TTG IgA spontaneously normalize. Thus, a single abnormal lab is not reliable
  • Genetic testing can be a useful adjunct in a few specific situations, including prior to instituting a gluten challenge
  • 1-3% of those with celiac disease may be negative for HLA-DQ2 and HLA-DQ8
  • If a gluten challenge is needed, 12 weeks is ideal. However, if poorly tolerated, then consider endoscopy earlier and Dr. Singh recommends checking in with family 4-6 weeks into the challenge
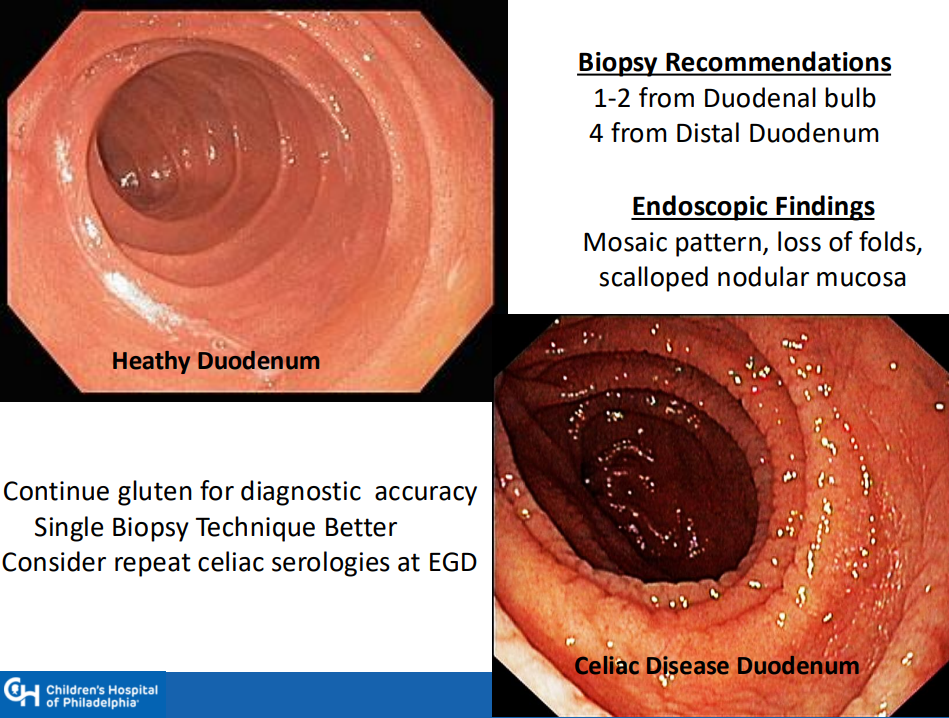
  • Endoscopy recommendations: Taking a single biopsy per pass can improve orientation when obtaining duodenal biopsies (bulb and distal portion, 5-6 in total)
  • NASPGHAN has not updated comprehensive guidelines for CD in 20 years
  • A survey of NASPGHAN members indicated that ~40% utilize a “no-biopsy” approach in patients. Dr. Singh noted that the accuracy of this approach, based on data from North America, may be about 96%
  • Drug trials for CD require a biopsy-confirmed diagnosis
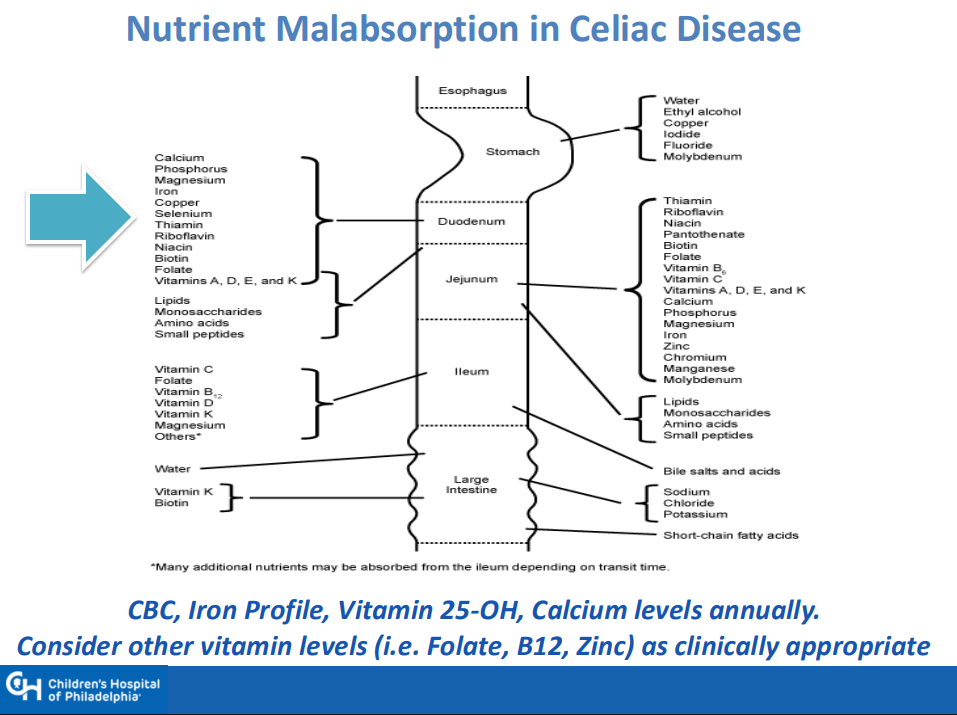
  • Surveillance practice is quite variable. Important to follow growth and serology. CHOP approach includes surveillance for type 1 DM
  • Followup endoscopy to assess mucosal healing is not the current standard of care but could be helpful in some patients
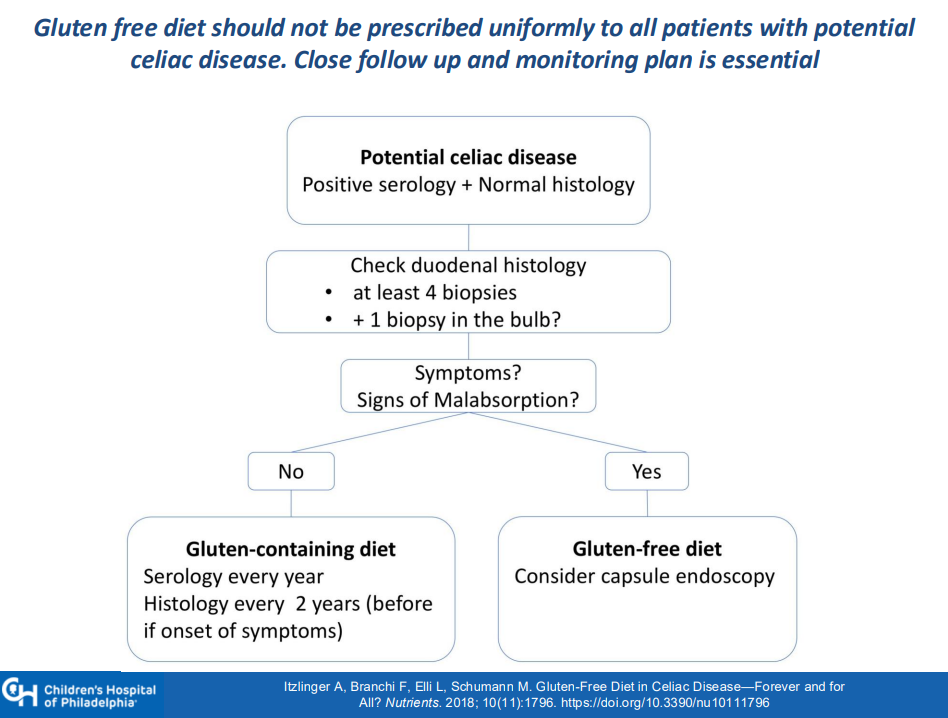
  • Among patients with potential CD, about 30% develop CD over time. Thus, these patients should be monitored (yearly labs, f/u scope after 2 years)
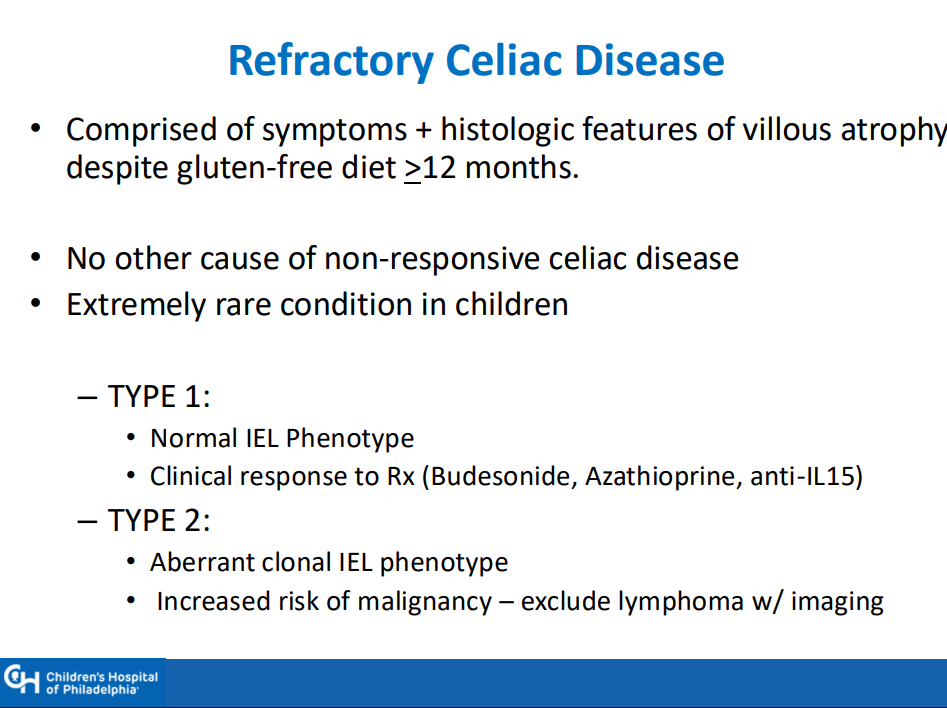
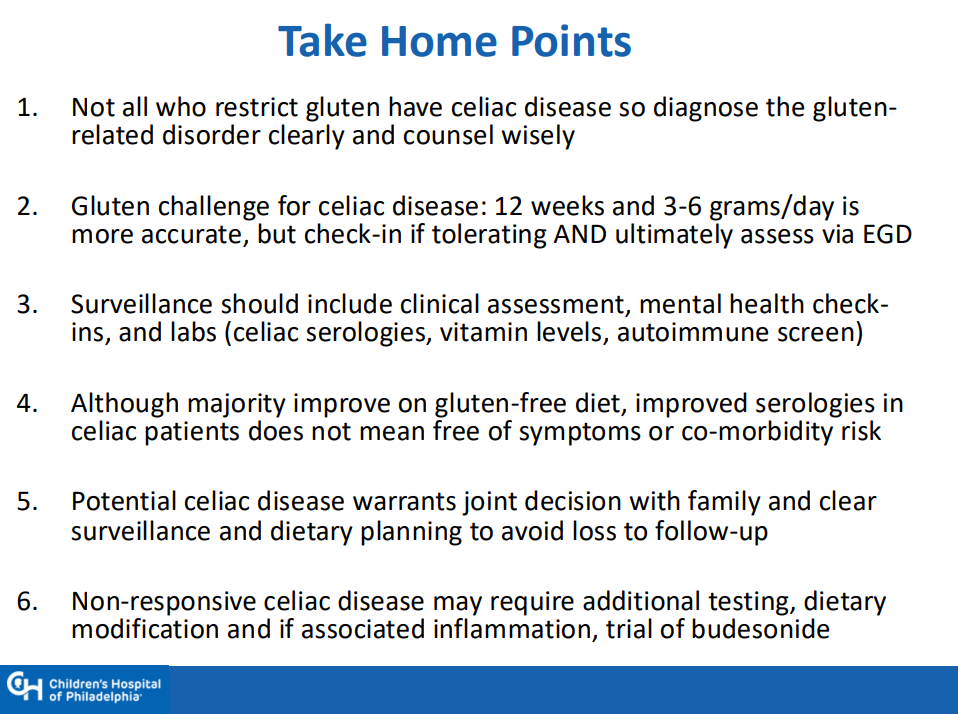
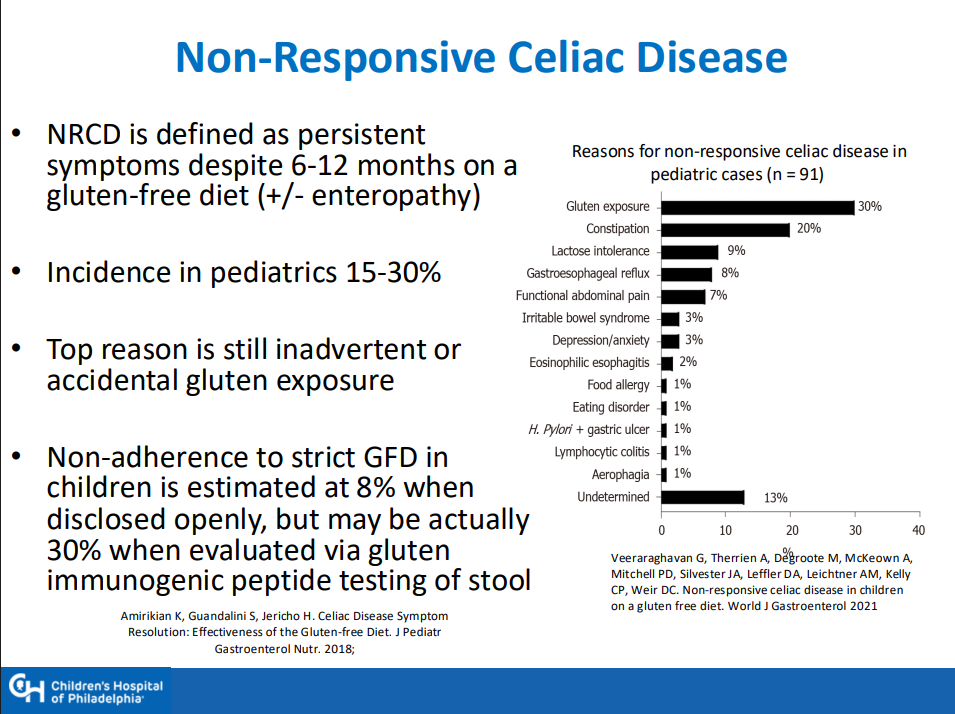
  • Nonresponsive/refractory CD: start with nutrition assessment, often needs a f/u scope before consideration of budesonide therapy (9 mg x 12 weeks) or gluten contamination elimination diet

Related blog posts:

The Guardian: UnitedHealth Secretly Paid Nursing Homes to Reduce Hospital Transfers

The Guardian 5/21/25:
Revealed: UnitedHealth secretly paid nursing homes to reduce hospital transfers

An excerpt:

UnitedHealth Group, the nation’s largest healthcare conglomerate, has secretly paid nursing homes thousands in bonuses to help slash hospital transfers for ailing residents – part of a series of cost-cutting tactics that has saved the company millions, but at times risked residents’ health, a Guardian investigation has found…

Those secret bonuses have been paid out as part of a UnitedHealth program that stations the company’s own medical teams in nursing homes and pushes them to cut care expenses for residents covered by the insurance giant.

In several cases identified by the Guardian, nursing home residents who needed immediate hospital care under the program failed to receive it, after interventions from UnitedHealth staffer…UnitedHealth said the suggestion that its employees have prevented hospital transfers “is verifiably false”. It said its bonus payments to nursing homes help prevent unnecessary hospitalizations that are costly and dangerous to patients and that its partnerships with nursing homes improve health outcomes…

To reduce residents’ hospital visits, UnitedHealth has offered nursing homes an array of financial sweeteners…

Two current and three former UnitedHealth nurse practitioners told the Guardian that UnitedHealth managers pressed nurse practitioners to persuade Medicare Advantage members to change their “code status” to DNR even when patients had clearly expressed a desire that all available treatments be used to keep them alive...

UnitedHealth’s insurance arm covers millions more Medicare Advantage seniors than any of its rivals

Commentary from Dr. Glaucomflecken account on X: https://x.com/i/status/1925348490680340979

My take: Healthcare insurance companies are incentivized to act as financial institutions and gatekeepers/third party administrators. This often compromises and delays patient care.

Related blog posts: