In this report, the authors describe nine patients with refractory microscopic colitis (median age 55 years) who were treated with vedolizumab.
Key findings:
Clinical response with induction in 9 (100%); time to >50% response ranged from 1 to 7 weeks with 5 patients responding within 2 weeks.
Sustained response with maintenance therapy in 6 (67%); duration of follow-up ranged from 1 month to 15 months. The three patients without response had symptom duration of 10 yrs, 12 yrs, and 25 yrs prior to institution of vedolizumab.
Only two patients had histologic follow-up. While both had clinical response, the patient with lymphocytic colitis had histologic resolution whereas a patient with collagenous colitis had histologic persistent.
My take: Given vedolizumab’s favorable safety profile, further studies (with endoscopic endpoints) of vedolizumab are needed to define its efficacy for microscopic colitis.
Key finding: The risk of serious infections was not different between vedolizumab and anti-TNF in the overall IBD cohort (HR, 0.95; 95% CI, 0·79-1.13), while the risk was decreased for vedolizumab users in patients with UC (HR, 0.68; 95% CI, 0.50-0.93), but not CD (HR, 1.10; 95% CI, 0.87-1.38)
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
“The risk of fatal anaphylaxis is about 1 in 10 million (about equivalent to being struck by lightning)..and fatality on first ingestion of an allergen in infancy has never been described”
Food allergy causes considerable morbidity/worsens quality of life (QOL): bullying, meal preparation, stress, social activities, and school attendance (with 10% choosing home schooling because of a food allergy). Some of this detriment on QOL is due to fear “that accidental exposure could result in fatal anaphylaxis”
“The impact of peanut allergy on QoL has been noted to be significantly worse than the impact of other chronic childhood diseases such as rheumatologic disease and type 1 diabetes mellitus”
Uriticaria does not equal allergy. “Although urticaria is commonly equated with a food allergy, food allergy accounts for less than 10% of the causes of all acute urticaria and is not a cause of chronic urticaria.” Urticaria can be triggered by an acute infection (most common etiology)
“Food proteins are digested within several hours; therefore, urticaria associated with a food ingestion will occur within minutes to 2 hours of ingestion, but typically last no more than a few hours (and less with treatment)” (an exception is meat anaphylaxis owing to galactose-α-1,3-galactose allergy)
Other common symptoms that are often incorrectly attributed to food allergy include headaches, chronic behavioral symptoms, or chronic nonspecific abdominal pain
Allergy testing: “the presence of a food-specific IgE is not itself indicative of an allergy…Although both skin prick testing and food-specific IgE testing are highly sensitive (>90% for skin prick tests, 70%-90% for sIgE), the specificity and positive predictive values of testing are often very low. The rate of false-positive tests is up to 40%.”
Broad “panel testing” (eg, to a panel of “common” foods), or any food allergy diagnostic testing in the absence of a convincing clinical history has high potential to overdiagnose food allergy and result in unnecessary food avoidances
Don’t do IgG testing. “There is no evidence that IgG testing marks food sensitivity; in fact, the presence of IgG is both expected and is a potential indicator of ongoing tolerance”
For first-line management anaphylaxis, (intramuscular) epinephrine is the “only life-saving intervention available.” Antihistamines are useful only in the treatment of cutaneous symptoms/urticaria.
“Although oral corticosteroids are often administered in the setting of anaphylaxis, there is no convincing evidence that their use prevents a biphasic reaction…their routine use is not recommended” (for anaphylaxis)
In this prospective study, the authors compared Eosinophil-Derived Neurotoxin (EDN) levels in pediatric patients with eosinophilic esophagitis (EoE) who responded PPIs (n=15) to those who did not respond to PPIs (n=21). The publication states that EDN levels of 10 mcg/mL or greater are diagnostic for EoE (sensitivity 97%, specificity 89%) but EDN levels have not previously been studied as a marker for PPI responsiveness.
Key finding: EDN concentration was significantly higher in the PPI-nonresponsive group than in the PPI-responsive group (219.1 ± 229 mcg/mL vs 75.7 ± 60 mcg/mL, respectively, P = 0.036).
However, Figures 1 (see below) and 2 show that EDN levels while generally higher in those who did not respond to PPIs are not likely to help much at all in predicting who will respond to PPIs, mainly due to a lot of overlap in the levels. While very elevated levels (above ~300 mcg/mL) all occurred in PPI non-responders, this only accounted for 5 patients out of 36 in the entire cohort.
My take: This article’s title is quite misleading. EDN levels are generally higher in PPI-nonresponders but they do not predict response.
This case report examined the effect of benralizumab, a monoclonal antibody against the interleukin-5 receptor (IL5Rα) on eosinophils in 20 year old with asthma and EoE. Histology was notable for resolution of esophageal eosinophilia but demonstrated marked basal zone hyperplasia (BZH) in association with high numbers of CD3+ T cells and tryptase+ mast cells. Subsequently, she improved with the institution of dupilumab with resolution of BZH and mast cell inflammation with significant reduction in T cells.
My take: Even with resolution of eosinophilia, mast cells and T cells appear to be capable of coordinating mucosal inflammation and symptoms of EoE (at least in some patients). This study mirrors my limited experience, in which patients receiving benralizumab had a grossly abnormal-appearing esophagus but resolution of the eosinophils.
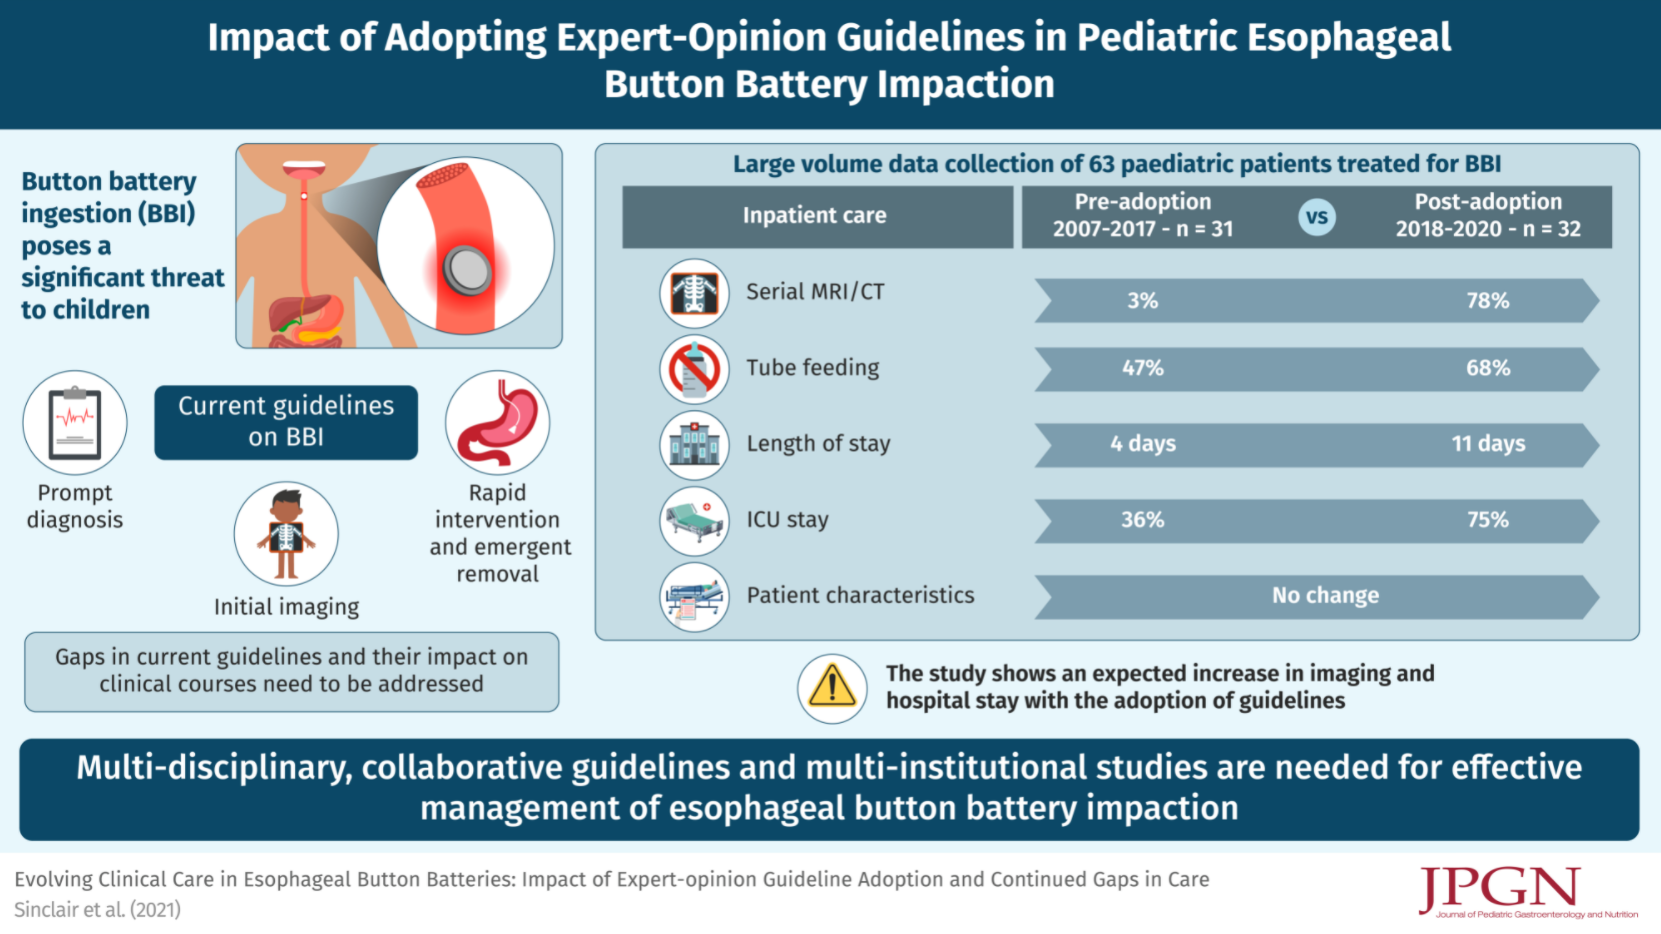
EM Sinclair et al. JPGN 2022; 74: 236-243. This retrospective study (n=63) describes the increased utilization of cross-sectional imaging, adoption of acetic acid irrigations, increased intensive care/hospitalizations after the implementation of consensus institutional guidelines for button battery management (see visual abstract below). An estimate in the increase in costs would have been a good addition to this study.
One of the references (EM Sinclair et al. J Pediatr Surg Case Rep 2021; 66: 101782. doi: 10.1016/j.epsc.2021.101782. Open Access: Development and repair of aorto-esophageal fistula following esophageal button battery impaction: A case report) describes one of the goals of prolonged hospitalization, namely preventing catastrophic bleeding. In this case report, though, the 6 yo had been discharged 12 days after presentation and represented on day 25 with hematemesis from a new aorto-esophageal fistula, requiring emergent cardiac catheterization with successful, life-saving aortic stent placement; “however a multidisciplinary approach to procedure planning is necessary with availability of surgical support for open repair if necessary.” This report has a lot of good images. The discussion notes that the National Capital Poison Center (NCPC) database reports a total 64 deaths in children following button battery ingestion worldwide since 1977; 61% (39/64) of which were due to documented arterio-esophageal fistulae (the actual numbers of deaths is likely much higher). This report also highlights the fact that serial MRIs “may not predict the development of severe complications.”
Related blog posts:
Foreign Bodies in Children -Expert Guidance Even with “spent” batteries, there is enough residual charge to cause injury and all ingestions (even if asymptomatic) into the esophagus require emergent removal. If these batteries are in the stomach & asymptomatic, urgent removal is recommended if age < 5 years and BB ≥20 mm.
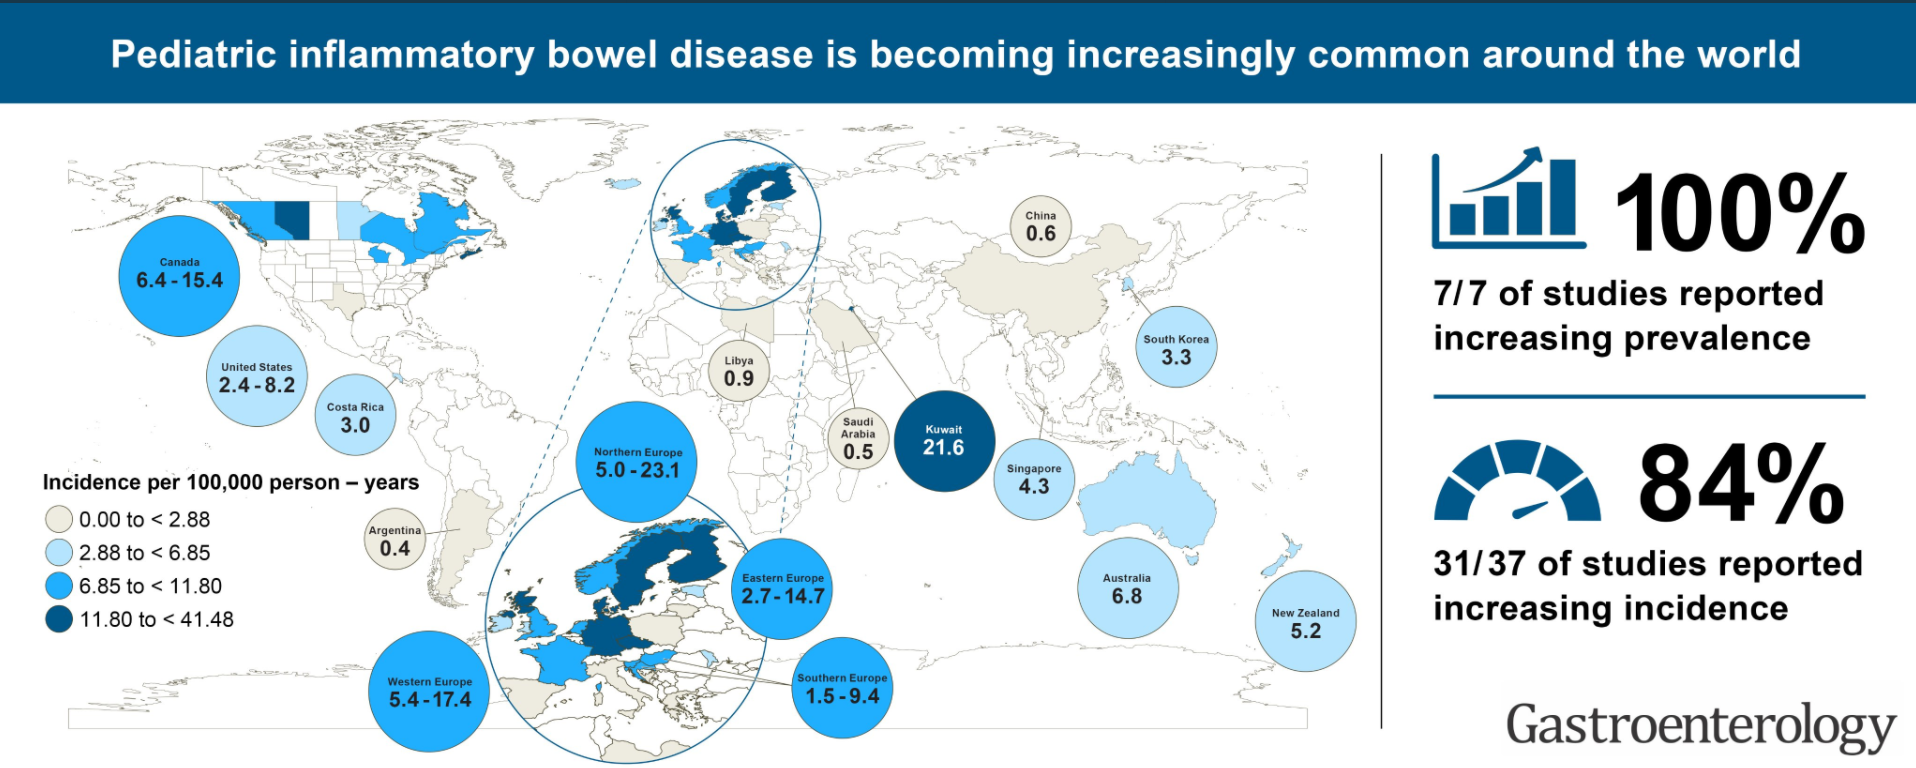
Key finding: Among studies evaluating trends over time, most (31 of 37, 84%) studies reported significant increases in incidence and all (7 of 7) reported significant increases in prevalence
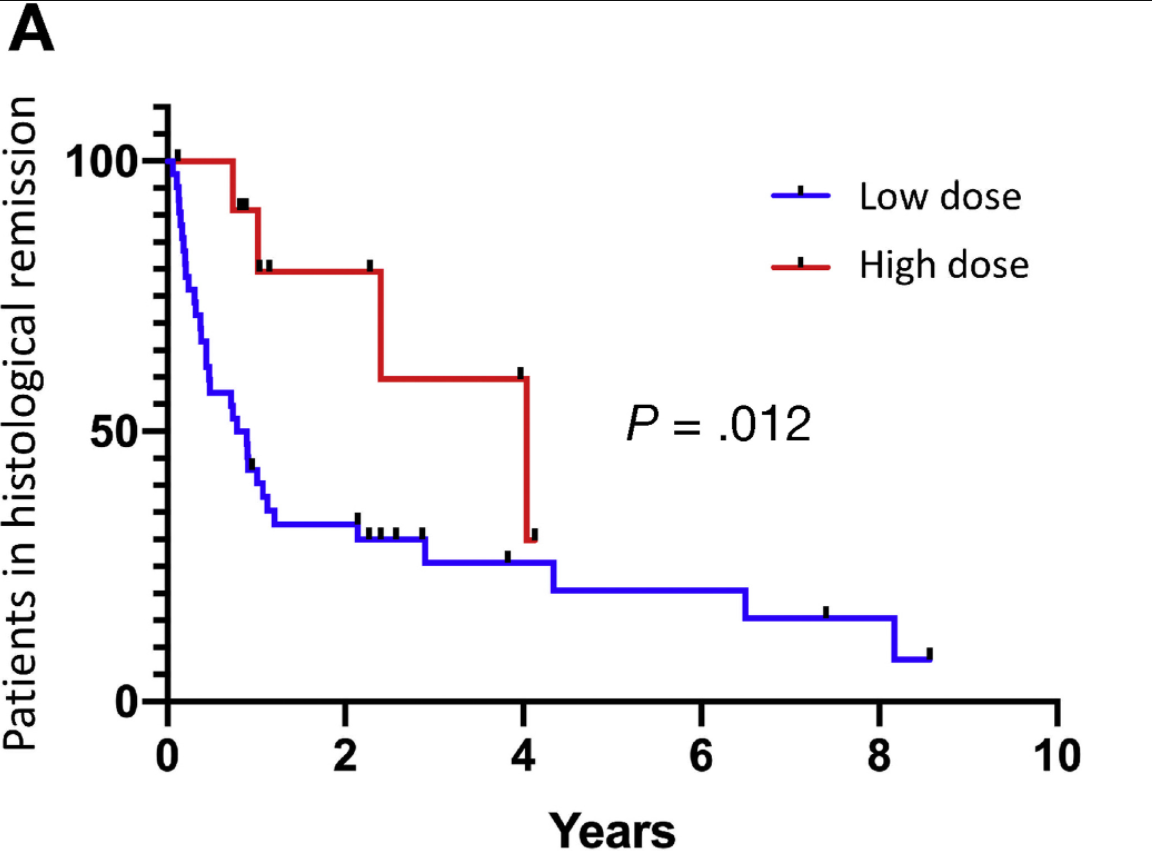
In this multicenter, retrospective study with 82 participants (mean age 37 years), the authors examined swallowed topical corticosteroids (STC) for maintenance of histologic remission (<15 eos/hpf). Low dose STC (22 budesonide, 60 fluticasone) was considered 0.5 mg/day or less. Key findings:
Histological relapse occurred in 67% of patients. This rate was comparable in patients treated with low-dose (72%) and high-dose (54%) STCs.
Histological relapse occurred significantly earlier with low dose STC (1.0 vs 1.8 years, P = .030)
Esophageal candidiasis was identified in 6% of subjects
The authors conclude that most of the histological relapse that occurred was due to true steroid failure since “low adherence and treatment cessation during follow-up were exclusion criteria.” Also, they note that “the recently finished but not yet fully published Maintenance of Remission With Budesonide Orodispersible Tablets vs Placebo in Eosinophilic Eosphagitis (EOS2 trial) (NCT02493335) comparing budesonide maintenance doses of 2 mg/d vs 1 mg/d suggest that there is no additional benefit of daily doses higher than 1 mg (1-year remission rates of 75.0% and 73.5%, respectively).
My take: Low dose STCs do not appear to be as effective in maintaining histologic remission; however, there is a high rate of relapse even in those with higher doses.
This retrospective study utilized UNOS adult data from 6/1/19 to 3/1/21. This included 9528 in the pre-COVID era and 9259 in the COVID era.
Key findings:
There was “a significant reduction in the monthly listing rates for HCV (−21.69%, P < 0.001) and NASH (−13.18%; P < 0.001).” However, there “was a significant increase in ALD [alcohol-associated liver disease] listing (+7.26%; P < 0.001) and LT (10.67%; P < 0.001) during the pandemic.”
“In the COVID era, ALD (40.1%) accounted for more listings than those due to HCV (12.4%) and NASH (23.4%) combined. The greatest increase in ALD occurred in young adults (+33%) and patients with severe alcohol-associated hepatitis (+50%).”
Interestingly, “patients with ALD had a 50% higher probability rate of LT [liver transplantation] than patients with other liver disease.”
The authors note that patients with alcohol use disorder (AUD) and ALD, during the pandemic, “may no longer have structured non-alcohol-related activities and in-person behavioral counseling…coupled with the delay in routine health care…Few patients with ALD receive recommended care for AUD.”
My take: Due to the cumulative effects of ALD, there is likely to continued (worsening) high rates of liver failure due to ALD. Given the difficulties in managing ALD, aside from managing liver complications, this must be a huge emotional burden for many healthcare providers watching this tragedy play out on a continual basis.
Cumulative incidence rates for LT among patients listed for ALD and non-ALD in the pre-COVID and COVID eras.
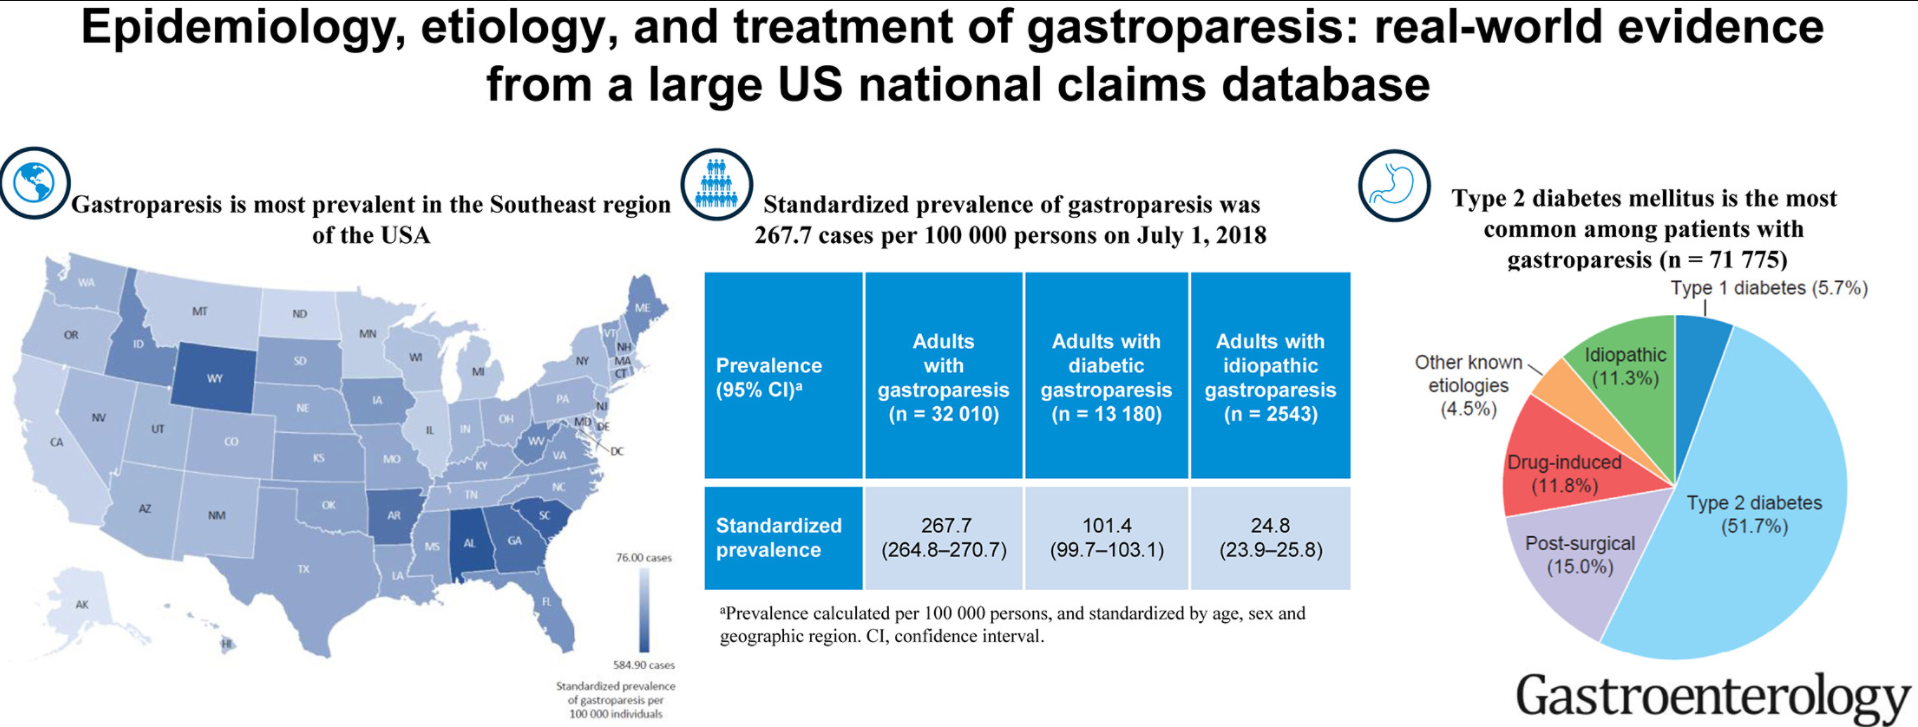
The overall standardized prevalence of gastroparesis was 267.7 per 100,000 US adults, whereas prevalence of “definite” gastroparesis (individuals diagnosed within 3 months of gastric emptying scintigraphy testing with persistent symptoms for more than 3 months) was 21.5 per 100,000
Etiology was most commonly due to diabetes (57.4%; type 1, 5.7% and type 2, 51.7%), followed by postsurgical (15.0%), drug-induced (11.8%), and idiopathic (11.3%) etiologies
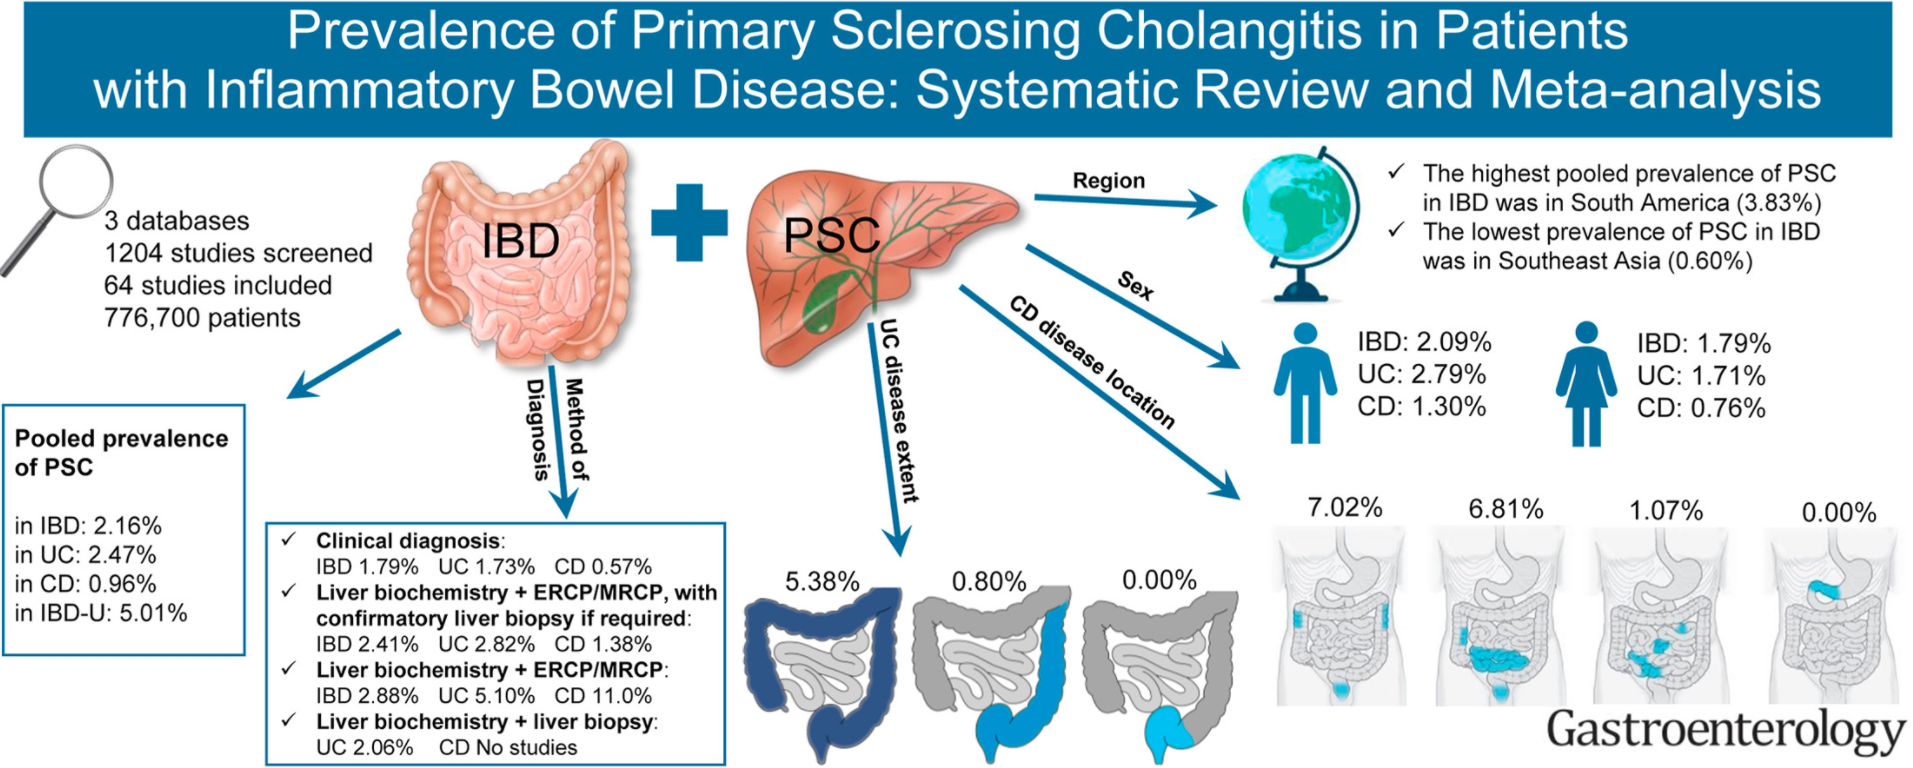
Key findings: Overall, pooled prevalence of PSC in IBD was 2.16%; the pooled prevalence was significantly higher in UC versus CD (OR 1.69)
Related blog posts:
Aspen Webinar 2021 Part 5 -Autoimmune Liver Disease & PSC This lecture highlights studies show lack of efficacy with vancomycin, ursodeoxycholic acid and vedolizumab. Also, there is potential utility of MMP-7 for distinguishing between PSC and AIH