2/17/22: Today, the U.S. Food and Drug Administration announced it is investigating consumer complaints of Cronobacter sakazakii and Salmonella Newport infections. All of the cases are reported to have consumed powdered infant formula produced from Abbott Nutrition’s Sturgis, Michigan facility ..The FDA is investigating complaints of four infant illnesses from three states.
The FDA is advising consumers not to use Similac, Alimentum, or EleCare powdered infant formulas if:
the first two digits of the code are 22 through 37; and
the code on the container contains K8, SH or Z2; and
the expiration date is 4-1-2022 (APR 2022) or later.
Products that do not contain the information listed above are not impacted. The FDA advisory does not include liquid formula products or any metabolic deficiency nutrition formulas. Consumers should continue to use all products not covered by the advisory.
Background: “Processed foods often include many non-natural ingredients and additives such as artificial flavours, sugars, stabilisers, emulsifiers, and preservatives. Detergents and emulsifiers that are added to foods might have a detrimental effect on the gut barrier. Carboxymethylcellulose has been shown to increase bacterial adherence to intestinal epithelium and might lead to bacterial overgrowth and infiltration of bacteria into the spaces between intestinal villi. Polysorbate 80, an emulsifier commonly used in processed foods, increases translocation of bacteria such as Escherichia coli across M cells and Peyer’s patches in people with Crohn’s disease.”
Methods: Using food questionnaires, the authors prospectively followed 116 087 adults aged 35-70 years from 21 low, middle, and high income countries from 2003 to 2016 (median follow-up of 9.7 years).
Key findings:
After adjustment for potential confounding factors, higher intake of ultra-processed food was associated with a higher risk of incident IBD with a hazard ratio of 1.82 for ≥5 servings/day and 1.67 for 1-4 servings/day (compared to <1 serving/day)
Since this is an observational study, this does not prove a causal association between these foods and inflammatory bowel disease. Nevertheless, limiting the consumption of ultraprocessed foods is a good idea as these foods may increase the risk of other health problems as well, including cardiometabolic disease and cancer (Gastroenterol 2022; 162: 652-54). This will be difficult, though, as in the U.S. more than half of calories consumed are from ultraprocessed foods.
My take: This study supports the notion that more fresh foods in our diets is beneficial.
This is a super cool article documenting a new human model for studying biliary atresia. The authors “generated biliary organoids from liver biopsies of infants with biliary atresia and normal and diseased controls…Organoids from biliary atresia are viable and have evidence of halted epithelial development. The induction of developmental markers, improved cell-cell junction, and decreased epithelial permeability by EGF and FGF2 identifies potential strategies to promote epithelial maturation and function.”
The authors note that delayed development of cholangiocytes impair barrier function and leave the liver susceptible to various insults which can trigger an inflammatory response with potential progression to obliteration of the bile ducts.
Among 18,595,345 pregnancies, 935 (<0.001%) had AIH (60 with cirrhosis) and 120,100 (0.006%) had other CLD (845 with cirrhosis). Key findings:
AIH was not associated with postpartum hemorrhage, maternal, or perinatal death
AIH was associated with preterm births when compared with women without CLD (OR: 2.0)
The odds of gestational diabetes (GDM) and hypertensive complications (pre-eclampsia, eclampsia, or hemolysis, elevated liver enzymes, low platelets) were significantly higher in AIH compared to other CLD (GDM: OR 2.2 and hypertensive complications: OR: 1.8) and also compared to no CLD in pregnancy (GDM: OR: 2.4 and hypertensive complications: OR: 2.4)
In this brief report, the authors identified 7.8% of children from a cross-sectional California cohort (n=12,945) with ALT >44 U/L and BMI in the 95% or higher (2012-2014). Males were twice as likely to have elevated ALT. Ethnicity rates were higher in hispanics, asians than white and black children (in males: 12%, 10.4%, 7.3% and 3.1%, respectively)
Key findings: Polyreactive IgGs (pIgGs) are a common finding in untreated AIH and have “the highest overall accuracy for the distinction between AIH and non-AIH LD compared to the most common conventional autoantibodies.” In addition, in this study with 1568 adutls, pIgGs were present in “up to 88% of patients with seronegative AIH and in up to 71% of AIH patients with normal IgG levels. Under therapy, pIgG returns to background levels of non-AIH-LD.”
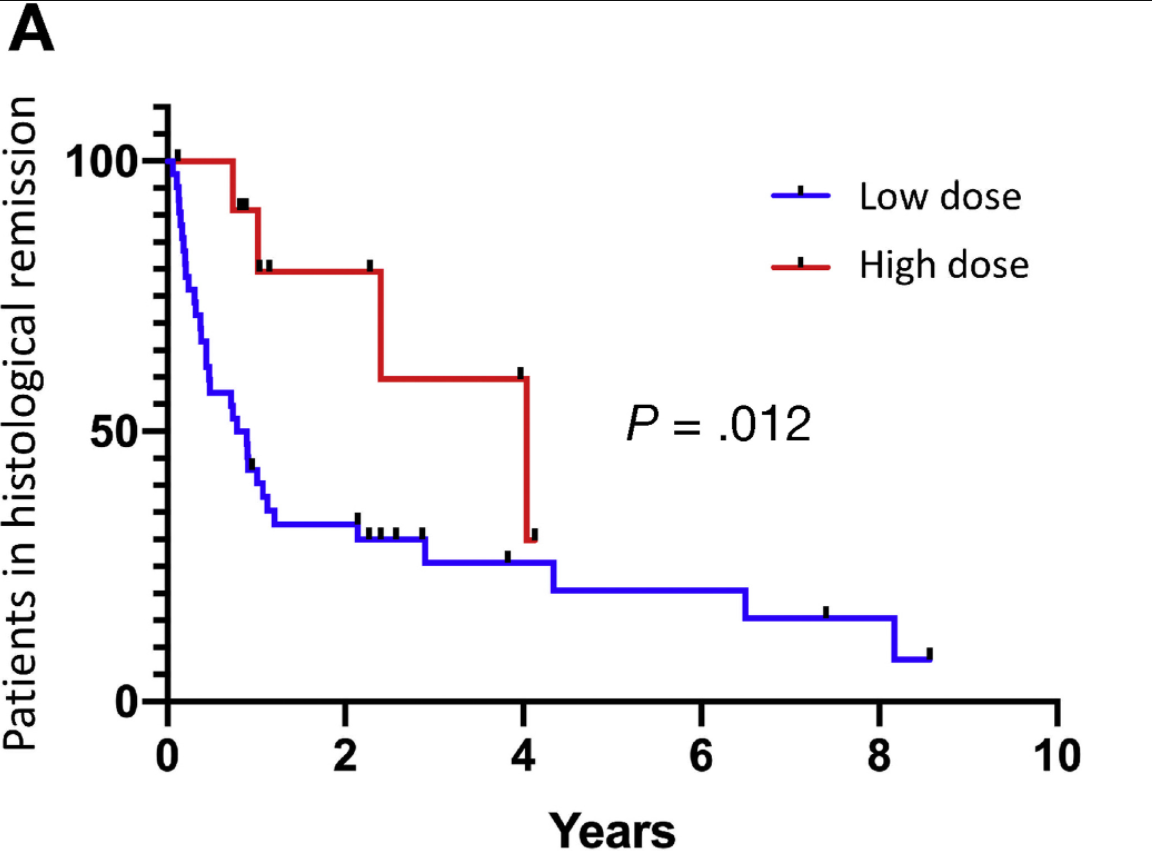
In this multicenter, retrospective study with 82 participants (mean age 37 years), the authors examined swallowed topical corticosteroids (STC) for maintenance of histologic remission (<15 eos/hpf). Low dose STC (22 budesonide, 60 fluticasone) was considered 0.5 mg/day or less. Key findings:
Histological relapse occurred in 67% of patients. This rate was comparable in patients treated with low-dose (72%) and high-dose (54%) STCs.
Histological relapse occurred significantly earlier with low dose STC (1.0 vs 1.8 years, P = .030)
Esophageal candidiasis was identified in 6% of subjects
The authors conclude that most of the histological relapse that occurred was due to true steroid failure since “low adherence and treatment cessation during follow-up were exclusion criteria.” Also, they note that “the recently finished but not yet fully published Maintenance of Remission With Budesonide Orodispersible Tablets vs Placebo in Eosinophilic Eosphagitis (EOS2 trial) (NCT02493335) comparing budesonide maintenance doses of 2 mg/d vs 1 mg/d suggest that there is no additional benefit of daily doses higher than 1 mg (1-year remission rates of 75.0% and 73.5%, respectively).
My take: Low dose STCs do not appear to be as effective in maintaining histologic remission; however, there is a high rate of relapse even in those with higher doses.
This retrospective study utilized UNOS adult data from 6/1/19 to 3/1/21. This included 9528 in the pre-COVID era and 9259 in the COVID era.
Key findings:
There was “a significant reduction in the monthly listing rates for HCV (−21.69%, P < 0.001) and NASH (−13.18%; P < 0.001).” However, there “was a significant increase in ALD [alcohol-associated liver disease] listing (+7.26%; P < 0.001) and LT (10.67%; P < 0.001) during the pandemic.”
“In the COVID era, ALD (40.1%) accounted for more listings than those due to HCV (12.4%) and NASH (23.4%) combined. The greatest increase in ALD occurred in young adults (+33%) and patients with severe alcohol-associated hepatitis (+50%).”
Interestingly, “patients with ALD had a 50% higher probability rate of LT [liver transplantation] than patients with other liver disease.”
The authors note that patients with alcohol use disorder (AUD) and ALD, during the pandemic, “may no longer have structured non-alcohol-related activities and in-person behavioral counseling…coupled with the delay in routine health care…Few patients with ALD receive recommended care for AUD.”
My take: Due to the cumulative effects of ALD, there is likely to continued (worsening) high rates of liver failure due to ALD. Given the difficulties in managing ALD, aside from managing liver complications, this must be a huge emotional burden for many healthcare providers watching this tragedy play out on a continual basis.
Cumulative incidence rates for LT among patients listed for ALD and non-ALD in the pre-COVID and COVID eras.
Methods: Secondary analysis of US children in the National Survey of Children’s Health combined 2016–2019 dataset who had continuous and adequate health insurance
Key findings:
The proportion of US children experiencing underinsurance rose from 30.6% to 34.0% (+3.4%; 95% CI, +1.9% to +4.9%), an additional 2.4 million children
The estimate of children lacking continuous insurance coverage rose from 8.1% to 8.7%
My take: The U.S. healthcare system is messed up. Economic incentives nudge/force families to neglect high value care frequently (& getting worse). At the same, the U.S. expends a ton of resources on low value care.
Key finding: Improvements in ESLD mortality and LDRs (listing-to-death ratios) were associated with both Medicaid expansion and leniency of HCV coverage under Medicaid. In patients living in states with nonexpansion/restrictive cohort, deaths continued to increase throughout study period.
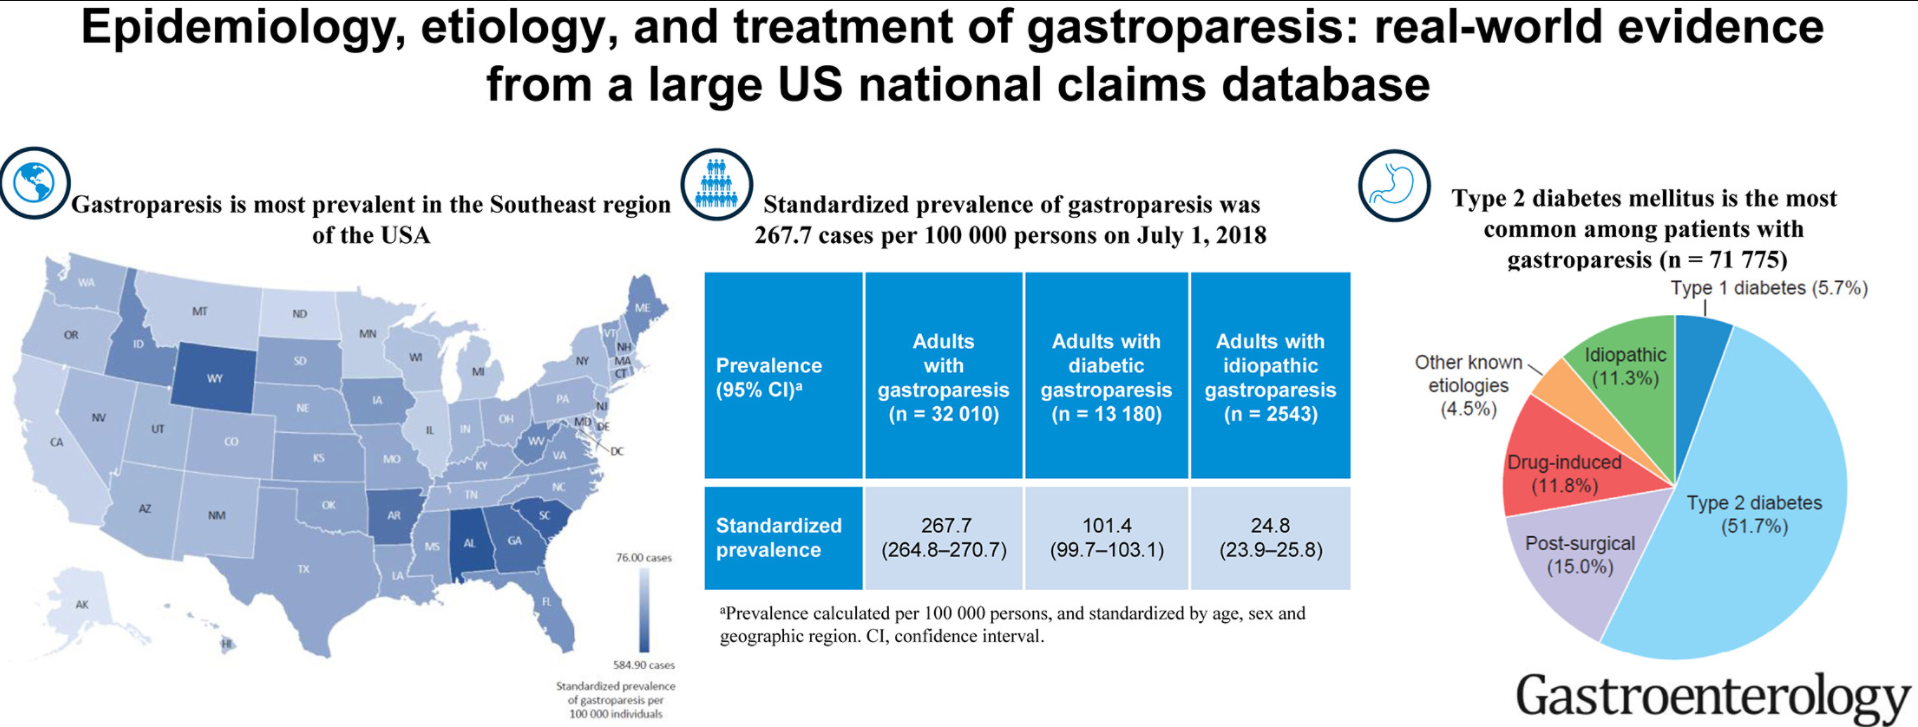
The overall standardized prevalence of gastroparesis was 267.7 per 100,000 US adults, whereas prevalence of “definite” gastroparesis (individuals diagnosed within 3 months of gastric emptying scintigraphy testing with persistent symptoms for more than 3 months) was 21.5 per 100,000
Etiology was most commonly due to diabetes (57.4%; type 1, 5.7% and type 2, 51.7%), followed by postsurgical (15.0%), drug-induced (11.8%), and idiopathic (11.3%) etiologies
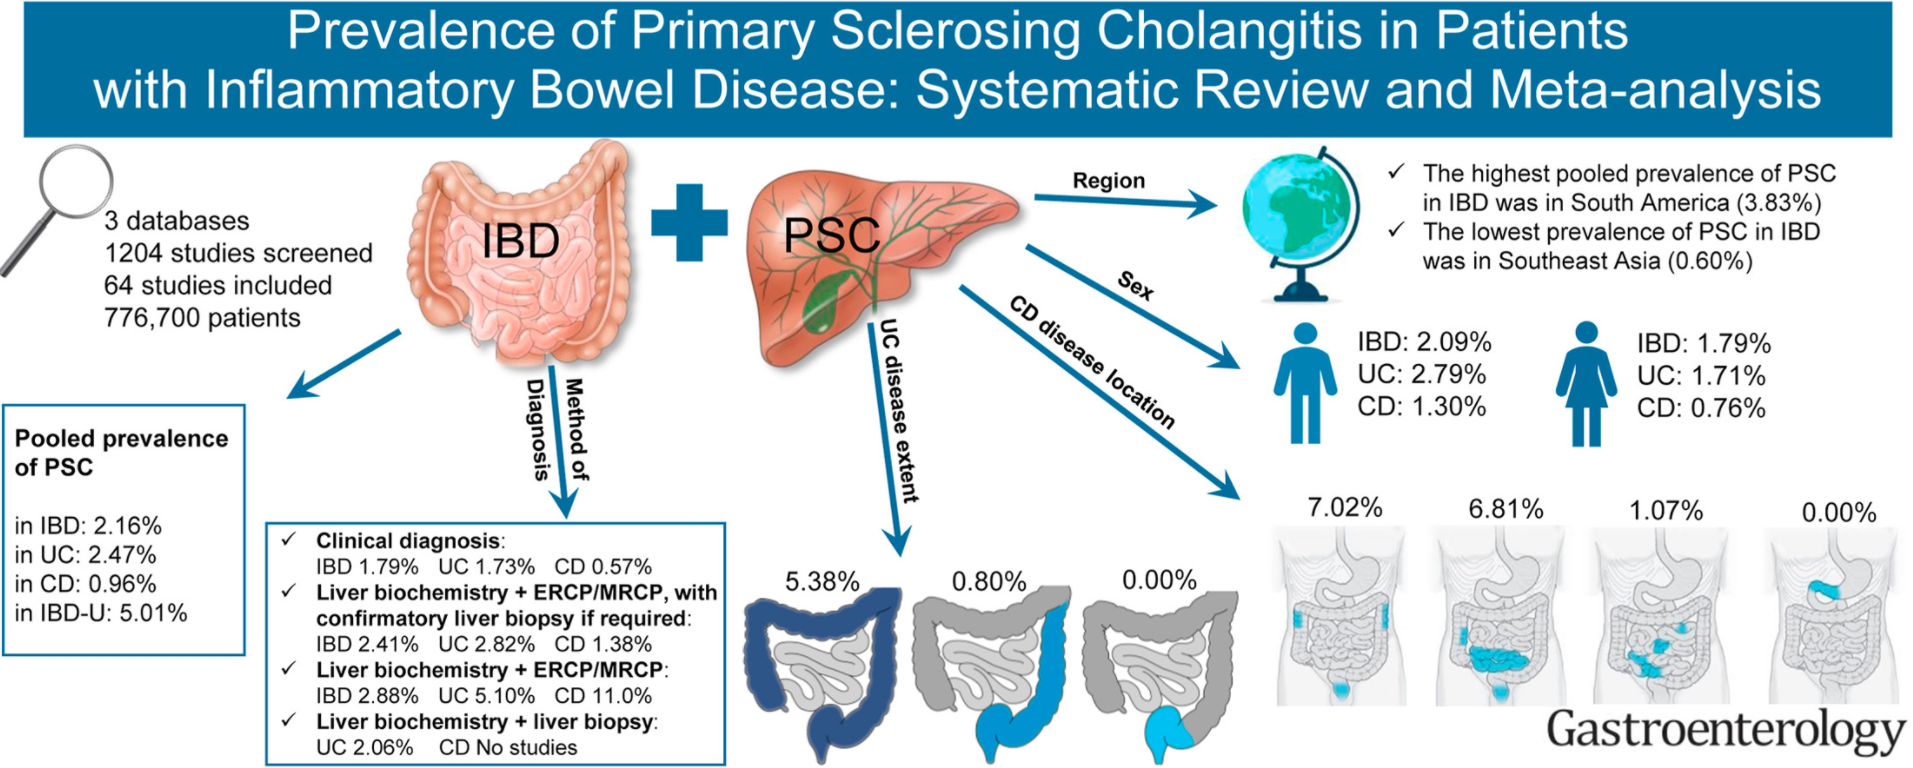
Key findings: Overall, pooled prevalence of PSC in IBD was 2.16%; the pooled prevalence was significantly higher in UC versus CD (OR 1.69)
Related blog posts:
Aspen Webinar 2021 Part 5 -Autoimmune Liver Disease & PSC This lecture highlights studies show lack of efficacy with vancomycin, ursodeoxycholic acid and vedolizumab. Also, there is potential utility of MMP-7 for distinguishing between PSC and AIH
I would urge colleagues when they see infants in the first few months of life to always discuss safe sleep which is the number one cause of mortality in infants. A simple message can be added to standard ‘Smartphrases’ for every infant seen with reflux, colic and formula intolerance.
A terrific website that focuses on this crucial issue: Charlieskids.org; it has videos, do’s and don’ts as well as a link to Cribs for Kids (discounted safe crib website). In addition,this website has a book called “Sleep Baby Safe and Snug” which incorporates updated recommendations on safe sleep practices.
Here are some screenshots from CHOA’s twitter feed on this topic.
Related blog posts:
The High Toll of Sudden Infant Death From 2013-2015, there was an average of 3523 US infants each year who died from SUID (sudden unexpected infant death), peaking at 1-2 months of life. More black infants died of SUID in the first year than black children who died from firearm homicides in all of childhood through age 19 years. SUID deaths from 2013-2015 (10,568) was similar to the total number of motor vehicle-traffic deaths in all of childhood (10,714) and greater than the total number of any of the other causes.