After I Passed The Test

After I passed my maintenance exam (American Board of Pediatrics -Pediatric Gastroenterology Subspecialty), I thought I would publish a few criticisms.

1. The test has not kept up with the digital age. In daily practice, it is a good idea to look up information and research difficult cases.  Knowing how to use these resources is more important than memorizing a lot of rare facts for an exam.

2. Why should any of the questions ask me to interpret radiographs or histology slides?  In daily practice, I would rely on my colleagues in radiology and pathology.  One of my surgical colleagues years ago used to say, “when I order a CT it should be like ordering a pizza.  Don’t ask me why I want it.  Ask me what I want on it.”  In the case of the maintenance exam, ask which test I want.  There are excellent radiologists and pathologists who are the experts at interpreting the results.

3. How is the MOC evidence-based? The popular buzz word of quality care is “evidence-based.”  Where is the data that taking the test & keeping up with the MOC (maintenance of certification) process improves physician performance?   From my discussions, it is apparent that physicians do not believe that the test “weeds” out underperforming physicians.

4. If the MOC process is so important, how come there are so many physicians who were “grandfathered” out of the requirements?  While the official line to this question is that the “diplomates” at that time who were board-certified were not time-limited, an honest answer is that it was the only politically feasible way to get enough physician support.

As a whole, these criticisms indicate the difficulty in designing a test to assess whether a physician has the necessary competencies.  As alluded to in a previous post (Training Not Meeting Procedure Thresholds for Fellows …), it is crucial that physicians gain the necessary experience/knnowledge in their training.

The MOC has lofty goals of assuring that physicians acquire and maintain their skills.  Yet, the current approach does not meet these goals.  Ultimately, the burden on a physician, like in other career pathways, on keeping up his knowledge and clinical skills relies mainly on the conscientious individual.  Those interested in taking shortcuts will do this and the current system is merely a nuisance.
Superiority of Anti-TNF Therapy (Part 2)

A recent blog (Superiority of Anti-TNF Therapy in Children | gutsandgrowth) described a recent article showing that kids treated with anti-TNF therapy at the time of diagnosis had improved outcomes compared to children who were treated with other medications.  In this day of multimedia, there is a video explaining the study which may be helpful for families and clinicians alike –here’s the link:  Dr. Michael Stephens discusses the research findings: .

An excerpt from the explanation with the video:

The current research study looks at outcomes and compares three different types of treatments. The first group receives anti-TNF therapy. The second group received immune modulating therapy. The third group received no treatment within the first three months. This study was an observational study and the choice of treatment was at the discretion of the physician. In order to correct for this factor, a statistical technique was used. Patients with similar characteristics were paired within the three groups . The results showed that patients who received the anti-TNF therapy had an improved outcome, such as a higher remission rate and some indications of improved growth, at one year. All three groups had improvements in weight and body mass index but only the anti-TNF group had improvements in linear growth.

Just the Beginning: Mutations in Very Early Onset Inflammatory Bowel Disease

A recent study (Gastroenterol 2014; 146: 1028-39) indicates that mutations in tetratricopeptide repeat domain 7A (TTC7A) can result in a severe form of very early onset inflammatory bowel disease (VEOIBD).

After identifying a TTC7A heterozygote mutation in an infant by using whole exome sequencing of DNA, the authors subsequently identified 4 additional patients (2 siblings from 2 families) who also had loss of function mutations in VEOIBD.  Thus far, four of the five identified infants have died.

The manuscript has some terrific figures describing endoscopic/histologic characteristics, TTC7A genetic analysis, functional TTC7A enterocyte studies with immunofluorescence, impaired cell adhesion figure, tandem mass spectrometry, and a summary mechanistic figure (figure 6).  Hematopoietic stem cell transplantation has not been effective and might not work due to the enterocyte defect.

This study adds another VEOIBD gene mutation.  Previous mutations have involved in VEOIBD have included IL10RA/B, XIAP, ADAM17, NCF4, and NCF2/RAC2. The specific subtype matters as some defects may respond to stem cell transplantation.

Take-home message: there are a diverse number of pathways that can lead to VEOIBD.  Given the recent availability of whole exome sequencing, more mutations are sure to be identified soon.

Related blog post/link:

IL-10 and early onset IBD | gutsandgrowth In addition to the Toronto group (noted in this blog), a group in Boston with Harland Winter/CJ Moran is also interested in whole exome sequencing for VEOIBD patients.

Causes and Treatment of Very-Early Onset IBD -this link is to the AGA Journals blog post on the same subject.

How Long Will Infliximab Work?

Given the limited therapeutic options, the question of infliximab (IFX) durability in pediatrics is quite important.  One center has published its 10-year retrospective experience (Inflamm Bowel Dis 2014; 20: 606-13).

Inclusion criteria for the 188 patients included initiating IFX prior to age 21 years and patients who had a minimum of 1-year followup.

Demographics: Median age at diagnosis was 11 years for Crohn’s disease (CD) and 12 years for ulcerative colitis (UC). Indication for IFX due to steroid refractory disease was present in 42% of UC patients compared with 14% of CD patients.  Monotherapy was more common in UC patients, 65%, compared to 35% of CD patients.

Methotrexate was administered in 69 (44%) of CD patients at time of IFX with the majority (n=56) as oral treatment (low-dose <10 mg every week).  In addition, MTX was initiated after IFX induction in another 38 (24%).  Only 36 (23%) remained on IFX mono therapy throughout the duration of treatment in CD patients.

Key findings:

  • 88% of CD patients remained on IFX at 1 year, 80% at 2 years, and 72% at 5 years.
  • Only 7 of 157 CD patients were primary nonresponders.
  • 65 of 89 CD patients who did not achieve a sustained durable remission underwent dose escalation. 40 of 65 responded to dose escalation.
  • Of those who lost response to IFX, the majority were transitioned to adalimumab (ADA) and among this group, 82% remained on ADA treatment at last followup.
  • Among UC patients (n=31), 9 were primary nonresponders. At last followup, 41% (9) remained in a durable sustained response at last followup.
  • While the authors used MTX due to favorable effects on IFX pharmacokinetics (Arthritis Rheum 1998; 41: 1552-63), there was “not a significant difference in IFX durability or efficacy between this group and patients with CD on IFX monotherapy”
  • Availability of antibodies to infliximab (ATIs) and IFX trough levels were only assessed in a subset.  However, “we did see a significant difference in those that responded to dose intensification when ATIs were undetectable.”

Bottomline: The majority of CD patients can remain on IFX for >5 years.  Among those who lose response, adalimumab was a durable alternative.  A much lower durable response was evident with the subset of patients with UC.

Related blog post:

Also noted:

Inflamm Bowel Dis 2014; 20: 614-21. In this study of 78 youth with IBD, depressive symptoms warranting additional evaluation were present in 13% which was lower than in the community comparison group.  Disease severity was noted to be inactive in 63% and mild in another 18%.

Inflamm Bowel Dis 2014; 20: 495-501. This study showed that 25 children exposed to anti-TNFs prenatally for maternal IBD seemed to show good safety.  Immunologic investigation undertaken in 17 of the children was normal.  No control group limited the ability to determine if increased infections were present.

And, here’s a link to Mar-April Circle Newsletter from ImproveCareNow -topics include group medical appointments, parent working group, dieting with IBD, and includes link to self management handbook.


Imaging in NAFLD -Don’t Rely on Ultrasound

A recent article (Clin Gastroenterol Hepatol 2014; 12: 765-73) notes that ultrasound is not accurate for diagnosing NAFLD:

The link to the article: http://goo.gl/R1GdAG, video abstract: http://youtu.be/spnlSPTS-SE (from Jeff Schwimmer’s twitter feed) ,and an excerpt from the article’s abstract:

Results

We analyzed 9 studies comprising 610 children; 4 studies assessed ultrasonography and 5 studies assessed magnetic resonance imaging (MRI). Ultrasonography was used in the diagnosis of fatty liver with positive predictive values of 47% to 62%. There was not a consistent relationship between ultrasound steatosis score and the reference measurement of hepatic steatosis. Liver fat as measurements by MRI or by spectroscopy varied with the methodologies used. Liver fat measurements by MRI correlated with results from histologic analyses, but sample size did not allow for an assessment of diagnostic accuracy.

Conclusions

Available evidence does not support the use of ultrasonography for the diagnosis or grading of fatty liver in children. Although MRI is a promising approach, the data are insufficient to make evidence-based recommendations regarding its use in children for the assessment of hepatic steatosis.

Related blog posts:

“Low quality of evidence; strong recommendation” for Probiotics in Gastroenteritis

Recently a position paper on “Use of probiotics for management of acute gastroenteritis: a position paper by the ESPGHAN working group for probiotics and prebiotics” was published (JPGN 2014; 58: 531-39).

Two specific probiotics were recommended “strongly” but the working group describes the evidence for both as “low quality.”  This strikes me as odd.  The authors extensively reviewed previous studies and used the “GRADE” system to classify the quality of evidence and the category of recommendation.  There were 4 categories of quality of evidence: high, moderate, low and very low.  There were 2 possible recommendation categories: strong or weak.

The summary recommendations included the following:

  • Rehydration is the key treatment for AGE
  • Probiotics, overall, reduce diarrhea by approximately 1 day
  • However, probiotic effects are strain specific; findings from one probiotic cannot be extrapolated to another
  • The group recommends choosing probiotics with efficacy confirmed in well-conducted RCTs from a reputable manufacturer
  • Two specific recommended probiotics: Lactobacillus GG and Saccromyces boulardii

Take-home message: This article summarizes the available evidence for the use of probiotics in acute gastroenteritis.  Despite their classification as  “low quality of evidence,” the authors provide a strong recommendation for two probiotics (Lactobacillus GG and Saccromyces boulardii) as adjunctive therapy.

Related blog posts:


Why Rich Kids Get Measles More Often in the U.S.

Most of the time, having more wealth and education translates into better health care outcomes.  One exception has been with some vaccine-preventable illnesses like the measles, according to a recent article in USA Today which reported on the CDC’s efforts to counter anti-vaccination misinformation.

Here’s an excerpt:

Vaccines given to infants and young children over the past two decades will prevent 322 million illnesses, 21 million hospitalizations and 732,000 deaths over the course of their lifetimes, according to a new report from the Centers for Disease Control and Prevention.

Vaccines also will have saved $295 billion in direct costs, such as medical expenses, and a total of more than $1.3 trillion in societal costs over that time, because children who were spared from sometimes-devastating illnesses will be able to contribute to society, the report shows. These calculations may underestimate the full impact of vaccines, the study notes, because authors considered only the early 14 routine childhood immunizations typically required for school entry. Authors didn’t include flu shots or adolescent vaccines given at ages 11 or 12…

Before the measles vaccine became available in 1963, the virus infected about 500,000 Americans a year, causing 500 deaths and 48,000 hospitalizations. In recent years, the number of diagnoses fell to around 60 to 65, mostly in isolated travelers arriving in the USA.

Doubts about vaccines safety – and fading memories of vaccine-preventable diseases — have contributed to a resurgence of nearly forgotten diseases such as measles, which was officially declared eradicated in the USA in 2000. Numerous studies have debunked the notion that vaccines cause autism or other chronic diseases, says William Schaffner , an infectious disease specialist and professor at the Vanderbilt University School of Medicine in Nashville….

Congress created the entitlement program in 1994, responding to a measles outbreak in 1989 to 1991 that sickened 55,000 people and killed more than 100. At the time, measles outbreaks were fueled by viruses circulating among low-income, inner-city residents.

The picture has completely changed today, Schaffner says. The federal program has eliminated racial and ethnic disparities among vaccines. Today, the bulk of the unvaccinated children come from wealthy, educated families where parents intentionally choose not to immunize them, due to concerns about vaccine safety. These relatively wealthy children can then spread measles after returning from vacations in Europe, which has had large outbreaks for several years, Schaffner says.

“Borders can’t stop measles, but vaccination can,” says CDC Director Tom Frieden.

START Study: Steroids Not Effective For Biliary Atresia (After Kasai)

A recent multicenter study has shown that steroids are not helpful after hepatoportoenterostomy for Bilairy Atresia (BA) (Bezerra JA et al. Hepatoportoenterostomy for Bile Drainage in Infants With Biliary Atresia. JAMA. 2014 May 7;311(17):1750).  Thanks to Saul Karpen for the reference.  I want to congratulate all of the authors, but particularly Jorge Bezerra, Saul Karpen, and Rene Romero for collaborating on this important study.

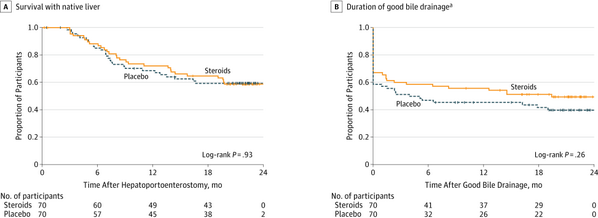
The randomized, double-blind, placebo-controlled START trial from the NIH-supported ChiLDren study enrolled 140 patients (257 were screened) from 2005-2011.  High-dose steroids, starting with methylprednisolone 4 mg/kg/day for 2 weeks and then tapered was compared with placebo.  No statistically significant improvement was noted.  Ultimately, the steroid intervention did not affect transplant-free survival which was 58.7% in the steroid group and 59.4% in the placebo group at 24 months of age.  Figure 2 (see below -from @JAMA twitter feed) shows Kaplan-Meier analysis plots with regard to transplant-free survival and bile drainage; the latter was slightly better in steroid group, but not statistically significant. In addition, steroids were associated with an earlier onset of first serious adverse events, 37% in steroid group compared with 19% in the placebo group within 30 days of Kasai.

Embedded image permalink

With regard to safety, the authors note that both groups were “found to have a high incidence of adverse events, indicating that they were most likely the direct consequences of the severe liver disease typical of biliary atresia. However, steroid therapy was associated with…complications at the sites of surgical anastomoses and intestinal perforation.”

Take-home message: Avoid steroids after Kasai procedure.

Related blog posts:

Something You Probably Have Not Seen with Celiac Disease and Headaches

An “image of the month” in the NEJM shows the association between celiac disease and occipital calcifications in a 24 year-old with a 10 year history of headaches, here’s the link: 

The course and explanation: Treatment with a gluten-free diet, folic acid supplementation, and carbamazepine was initiated, and the patient’s condition improved, with remission of all symptoms. The combination of celiac disease, epilepsy, and cerebral calcification is a rare condition known as the CEC syndrome. Folate malabsorption is a suggested mechanism

——

Also, there is a useful patient celiac education page from JAMA Pediatrics & University of Chicago: http://dlvr.it/55h6Rd 

Considering Cost in Treatment Choices

A recent article indicates a growing trend in medicine –considering the cost of therapy not just the effectiveness.  Physicians, by and large, view the patient sitting in front of them as their top priority, not “bedside rationing.”  On the other hand, policy makers often avoid engaging in cost issues and argue that physicians are best-suited to make decisions for their patients.

Here’s an excerpt:

Some doctors see a potential conflict in trying to be both providers of patient care and financial overseers.

“There should be forces in society who should be concerned about the budget, about how many M.R.I.s we do, but they shouldn’t be functioning simultaneously as doctors,” said Dr. Martin A. Samuels, the chairman of the neurology department at Brigham and Women’s Hospital in Boston. He said doctors risked losing the trust of patients if they told patients, “I’m not going to do what I think is best for you because I think it’s bad for the health care budget in Massachusetts.”

Doctors can face some stark trade-offs. Studies have shown, for example, that two drugs are about equally effective in treating an eye disease, macular degeneration. But one costs $50 a dose and the other close to $2,000. Medicare could save hundreds of millions of dollars a year if everyone used the cheaper drug, Avastin, instead of the costlier one, Lucentis.

But the Food and Drug Administration has not approved Avastin for use in the eye, and using it rather than the alternative, Lucentis, might carry an additional, albeit slight, safety risk. Should doctors consider Medicare’s budget in deciding what to use?

…Generally, Medicare is not supposed to consider cost effectiveness in coverage decisions, and other government attempts to do so are susceptible to criticism as rationing. Insurers do perform cost analyses, but they also risk ire from patients and doctors…

Also, in recent years, as part of a campaign called Choosing Wisely, many medical societies have submitted lists of the top five procedures, tests or products to be questioned because they are considered wasteful…

Dr. Steven D. Pearson, a visiting scientist in the ethics department at the National Institutes of Health, said the move by some societies to incorporate economic analysis “heralds an important shift in the way doctors in America are talking about cost and value.”

He said that having societies do such evaluations was better than having a doctor make such trade-offs while treating an individual patient, which is sometimes called bedside rationing…

Related blog postDo you know about the “Choosing Wisely Campaign …