I am a pediatric gastroenterologist at GI Care for Kids (previously called CCDHC) in Atlanta, Georgia. The goal of my blog is to share some of my reading in my field more broadly. In addition, I wanted to provide my voice to a wide range of topics that often have inaccurate or incomplete information.
Before starting this blog in 2011, I would tear out articles from journals and/or keep notes in a palm pilot. This blog helps provide an updated source of information that is easy to access and search, along with links to useful multimedia sources.
I was born and raised in Chattanooga. After graduating from the University of Virginia, I attended Baylor College of Medicine. I completed residency and fellowship training at the University of Cincinnati at the Children’s Hospital Medical Center. I received funding from the National Institutes of Health for molecular biology research of the gastrointestinal tract.
During my fellowship, I had the opportunity to work with some of the most amazing pediatric gastroenterologists and mentors. Some of these individuals included Mitchell Cohen, William Balistreri, James Heubi, Jorge Bezerra, Colin Rudolph, John Bucuvalas, and Michael Farrell. I am grateful for their teaching and their friendship. During my training with their help, I received a nationwide award for the best research by a GI fellow.
I have authored numerous publications/presentations including original research, case reports, review articles, and textbook chapters on various pediatric gastrointestinal problems. In addition, I have been recognized by Atlanta Magazine as a "Top Doctor" in my field multiple times.
Currently, I am the vice chair of the section of nutrition for the Georgia Chapter of the American Academy of Pediatrics. In addition, I am an adjunct Associate Clinical Professor of Pediatrics at Emory University School of Medicine. Other society memberships have included the North American Society for Pediatric Gastroenterology Hepatology and Nutrition (NASPGHAN), American Academy of Pediatrics, the Food Allergy Network, the American Gastroenterology Association, the American Association for the Study of Liver Diseases, and the Crohn’s and Colitis Foundation.
As part of a national pediatric GI organization called NASPGHAN (and its affiliated website GIKids), I have helped develop educational materials on a wide-range of gastrointestinal and liver diseases which are used across the country. Also, I have been an invited speaker for national campaigns to improve the evaluation and treatment of gastroesophageal reflux disease, celiac disease, eosinophilic esophagitis, hepatitis C, and inflammatory bowel disease (IBD). Some information on these topics has been posted at my work website, www.gicareforkids.com, which has links to multiple other useful resources.
I am fortunate to work at GI Care For Kids. Our group has 17 terrific physicians with a wide range of subspecialization, including liver diseases, feeding disorders, eosinophilic diseases, inflammatory bowel disease, cystic fibrosis, DiGeorge/22q, celiac disease, and motility disorders. Many of our physicians are recognized nationally for their achievements. Our group of physicians have worked closely together for many years. None of the physicians in our group have ever left to join other groups. I have also worked with the same nurse (Bernadette) since I moved to Atlanta in 1997.
For many families, more practical matters about our office include the following:
– 14 office/satellite locations
– physicians who speak Spanish
– cutting edge research
– on-site nutritionists
– on-site psychology support for abdominal pain and feeding disorders
– participation in ImproveCareNow to better the outcomes for children with inflammatory bowel disease
– office endoscopy suite (lower costs and easier scheduling)
– office infusion center (lower costs and easier for families)
– easy access to nursing advice (each physician has at least one nurse)
I am married and have two sons (both adults). I like to read, walk/hike, bike, swim, and play tennis with my free time.
I do not have any financial relationships with pharmaceutical companies or other financial relationships to disclose. I have helped enroll patients in industry-sponsored research studies.
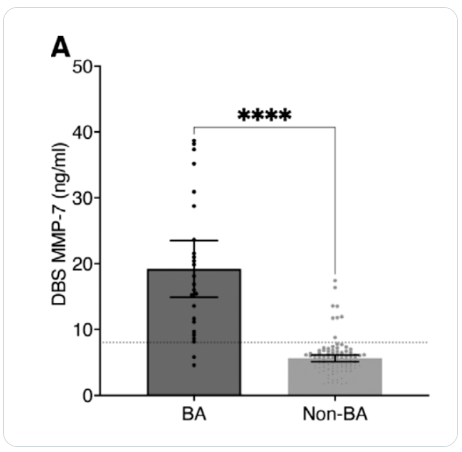
Methods: The study used stored DBS samples collected from 48 to 72 hours of life were retrieved from newborn screening centers in Taiwan (n=25 biliary atresia (BA), 107 non-BA)
Key findings:
MMP-7 levels of BA patients on the DBS were significantly higher than those of non-BA patients (19.2 ± 10.4 vs 5.6 ± 2.7 ng/mL, P value < 0.0001).
BA patients in this cohort underwent Kasai operation at a mean of 43 days. 32% (n=8) had surgery before 30 days of life, and 24% (n=6) had surgery after 60 days.
In this cohort, at time of publication, 9 (36%) of BA patients had received a liver transplantation at a mean of 2.4 years. Patients with their native liver tended to have had an earlier Kasai (38 days vs 54 days, P=0.057).
In their discussion, the authors note that BA starts very early in life. Increase in MMP-7 within 3 days of birth, supports “speculation that most BA ” may start before birth (JPGN 2019; 69: 396-403, What Is The Evidence That Biliary Atresia Starts in Utero?).
My take: Incorporating MMP-7 testing with newborn screening needs to be looked at in a bigger study. Efforts to identify BA cases earlier have largely been unsuccessful over the past several decades despite the knowledge that delayed diagnosis leads to worse outcomes.
S Travis et al. NEJM 2023; 388: 1191-1200. Vedolizumab for the Treatment of Chronic Pouchitis
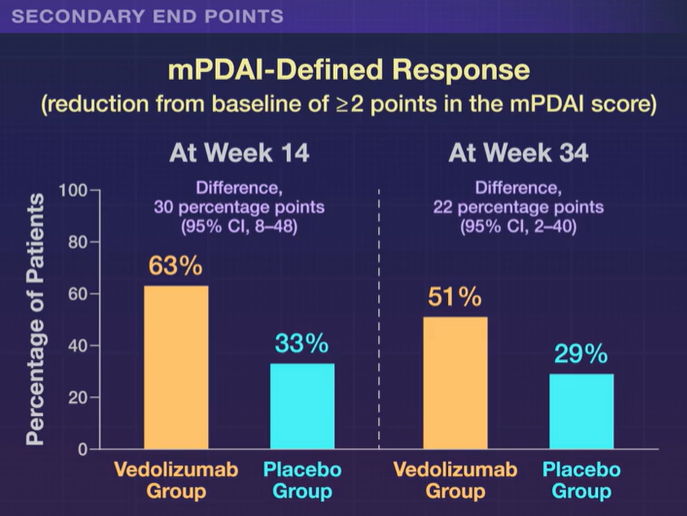
Methods: This was a a phase 4, double-blind, randomized trial (n=102 adults,EARNEST trial) to evaluate vedolizumab in adult patients in whom chronic pouchitis had developed after undergoing IPAA for ulcerative colitis.All patients received 4 weeks of ciprofloxacin and the treatment group received standard vedolizumab dosing. The primary end point was modified Pouchitis Disease Activity Index (mPDAI)–defined remission (an mPDAI score of ≤4 and a reduction from baseline of ≥2 points in the mPDAI total score; scores range from 0 to 12, with higher scores indicating more severe pouchitis) at week 14. The mPDAI is based on clinical symptoms and endoscopic findings.
Key findings:
The incidence of mPDAI-defined remission at week 14 was 31% (16 of 51 patients) with vedolizumab and 10% (5 of 51 patients) with placebo
Differences in favor of vedolizumab over placebo were also seen with respect to mPDAI-defined remission at week 34 (difference, 17 percentage points, 35% vs 18%)
My take: Vedolizumab is an effective treatment for chronic pouchitis.
Methods: This study analyzed postresection pediatric (≤18 years) CD patients (n=434) identified in the 2007–2018 IQVIA Legacy PharMetrics administrative claims database
Key findings:
Risk of surgical recurrence was 3.5%, 4.6%, and 5.3% at 1, 3, and 5 years, respectively
Postoperatively, patients were most commonly prescribed an immune modulator (33%), anti-tumor necrosis factor agent (32%), or antibiotic (27%)
My take: Current recommendations include postoperative endoscopic surveillance 6-12 months after surgery. Would the surgical recurrence rate have been lower if there had been higher postoperatively endoscopic evaluation?
This single center retrospective study reviewed 640 colonoscopies in symptomatic children.
Key findings:
Thirty-three children had isolated histologically-defined terminal ileitis. Seventeen children were diagnosed with CD and 18 children had idiopathic terminal ileitis (3 lost to followup)
Children with CD had higher prevalence of abnormal C-reactive protein levels, severe inflammation, and radiological evidence of bowel wall thickening compared with children with idiopathic ileitis.
Two children with idiopathic ileitis were later diagnosed with CD; the remaining 13 did not develop CD over a follow-up period of 83 months.
From the data presented, it appeared that the center had a low rate of ileal intubation (316 colonoscopies were excluded for this reason)
75% of those with histologic ileitis had normal endoscopic appearance
When our group looked at colonoscopies (n=374) in our outpatient endoscopy center, we identified isolated ileitis in 10% (6% grossly abnormal, 4% with only histologically abnormal) (related blog post: Our Study: Provider Level Variability in Colonoscopy Yield). Higher rates of ileal intubation (90% in our study) should be considered a quality metric given that 5-10% of children may have disease isolated in ileum.
My take: This study provides reassurance that most children with histologic ileitis will not progress to CD if the ileum is visually-normal (in the absence of abnormal blood tests and/or imaging).
Cigna, one of the country’s largest insurers…has built a system that allows its doctors to instantly reject a claim on medical grounds without opening the patient file, leaving people with unexpected bills…Over a period of two months last year, Cigna doctors denied over 300,000 requests for payments using this method, spending an average of 1.2 seconds on each case, the documents show.
Before health insurers reject claims for medical reasons, company doctors must review them, according to insurance laws and regulations in many states…This process helps avoid unfair denials…Cigna adopted its review system more than a decade ago, but insurance executives say similar systems have existed in various forms throughout the industry…At UnitedHealthcare….built a similar system to let its doctors quickly deny claims in bulk.
Cigna eventually designated the list “PXDX” — corporate shorthand for procedure-to-diagnosis. The list saved money in two ways. It allowed Cigna to begin turning down claims that it had once paid. And it made it cheaper to turn down claims, because the company’s doctors never had to open a file or conduct any in-depth review. They simply denied the claims in bulk with an electronic signature.
Cigna knows that many patients will pay such bills rather than deal with the hassle of appealing a rejection [for lower cost denials]…In one corporate document, Cigna estimated that only 5% of people would appeal a denial resulting from a PXDX review.
My take: It is a hassle to appeal denials. It is not surprising to me to hear about this reporting; it confirms the fact that insurance companies are focused primarily on cost and not patient care.
JS King. NEJM 388: 1057-60. On Consolidation and Competition — The Trials and Triumphs of Health Care Antitrust Law
Key points:
“Historically, the United States has relied nearly entirely on market competition to control prices and promote quality in health care. Yet health care markets haven’t been healthy for some time. Over the past 30 years, health care consolidation has gone largely unchecked by federal and state antitrust enforcers, which has resulted in higher prices, stagnant quality of care, and limited access to care for patients.”
Consolidation has been both horizontal (eg. two competitors merge), vertical (eg. hospital acquiring physician groups. or insurance acquiring pharmacy benefit manager) or cross-market (eg. merger of hospital in two separate regions)
“Private-equity firms have recently invested heavily in health care providers, purchasing hospitals, emergency services and staffing companies, and specialist-physician groups, such as anesthesiology groups…Studies have found that acquisitions by private-equity firms have led to consolidation and increases in hospital charges and net income.”
“Mergers are often justified with promises of improved quality or patient access, evidence supporting these claims is lacking.”
“Antitrust law aims to protect consumers and competitive markets from anticompetitive practices and the harms described above. Three federal laws — the Clayton Act, the Sherman Act, and the Federal Trade Commission Act — along with legislation in nearly all states form the foundation of antitrust law.”
“Despite these enforcement options, the U.S. health care industry is the most consolidated it’s ever been… In the 1990s and early 2000s, the FTC lost six consecutive horizontal hospital-merger cases…[subsequently] federal agencies didn’t challenge another hospital merger for nearly a decade.”
My take: Consolidation is happening in all components of health care, including hospitals, insurance companies, pharmaceutical companies and physician groups. This leads to higher costs, fewer choices and possibly staff shortages. At the same time, each segment of health care is incentivized to consolidate, in part for financial gain and in part to negotiate with other consolidated segments.
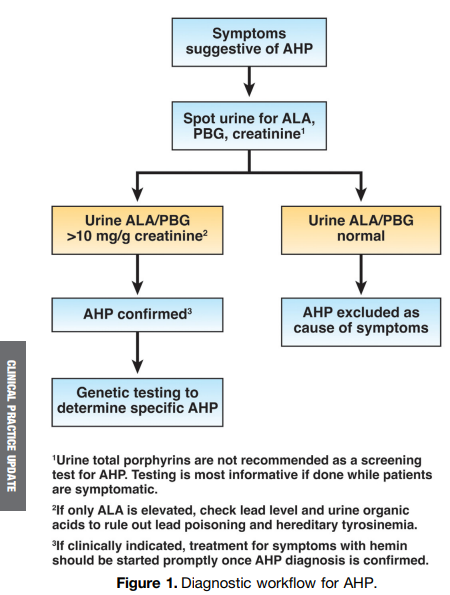
Overall, acute hepatic porphyrias (AHP) are rare disorders. “Acute intermittent porphyria is the most common type of AHP, with an estimated prevalence of patients with symptoms of approximately 1 in 100,000. The major clinical presentation involves attacks of severe pain, usually abdominal and generalized, without peritoneal signs or abnormalities on cross-sectional imaging…The screening tests of choice include random urine porphobilinogen and d-aminolevulinic acid corrected to creatinine.”
“All patients with elevations in urinary porphobilinogen and/or d-aminolevulinic acid should initially be presumed to have AHP. The cornerstones of management include discontinuation of porphyrinogenic drugs and chemicals, administration of oral or intravenous dextrose and intravenous hemin, and use of analgesics and antiemetics. Diagnosis of AHP type can be confirmed after initial treatment by genetic testing for pathogenic variants in HMBS, CPOX, PPOX, and ALAD genes.”
Some of the best practice advice:
Women aged 15–50 years with unexplained, recurrent severe abdominal pain without a clear etiology after an initial workup should be considered for screening for an AHP.
Initial diagnosis of AHP should be made by biochemical testing measuring d-aminolevulinic acid, porphobilinogen, and creatinine on a random urine sample.
Genetic testing should be used to confirm the diagnosis of AHP in patients with positive biochemical testing.
Acute attacks of AHP that are severe enough to require hospital admission should be treated with intravenous hemin, given daily, preferably into a high-flow central vein
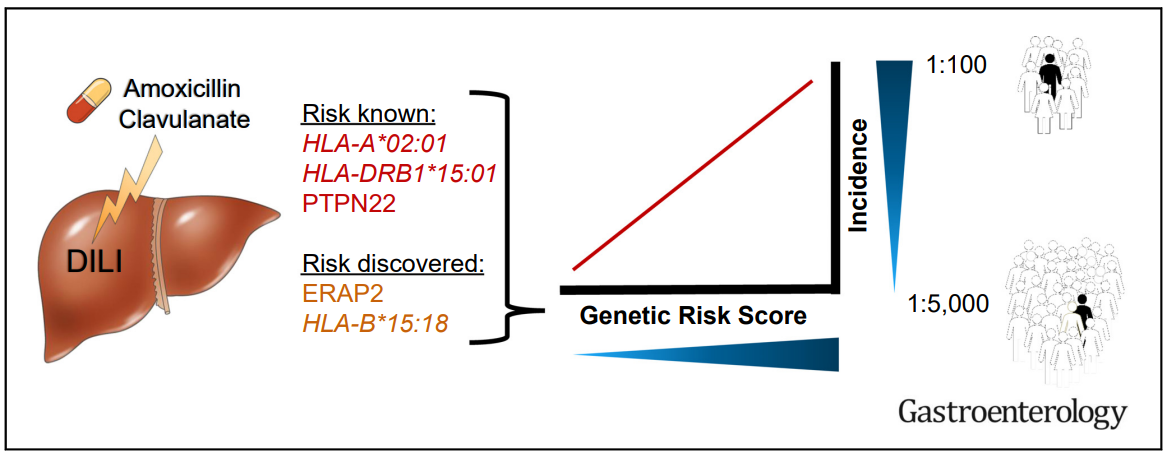
Transcriptome-wide association study revealed a significant association of AC-DILI risk with reduced liver expression of ERAP2 (P = 3.7 × 10⁻⁷), coding for an aminopeptidase involved in antigen presentation
“We also identified HLA-B∗15:18 as a novel AC-DILI risk factor in both discovery (OR, 4.19) and validation (OR, 7.78) cohorts”
A genetic risk score incorporating rs1363907, rs2476601, HLA-B∗15:18, HLA-A∗02:01, and HLA-DRB1∗15:01, was highly predictive of AC-DILI risk when cases were analyzed against both general population and non–AC-DILI control cohorts.
This genetic risk score does not apply to amoxicillin. “Clavulanate has long been considered the main component causing Amoxicillin-Clavulanate-DILI (LiverTox https://www.ncbi.nlm.nih.gov/books/NBK548517/).”
While the genetic risk score has high specificity, it is not highly sensitive. “Our multimarker model based on the 5 risk alleles predicted approximately 13% of the total risk for AC-DILI, which is approximately one-third of the total DILI risk that has previously been attributed to common genetic variants (approximately 40%)”
My take: In cases of suspected AC-DILI, identifying an abnormal genetic risk could help confirm the diagnosis. However, due to low sensitivity it is not likely to gain widespread clinical use.
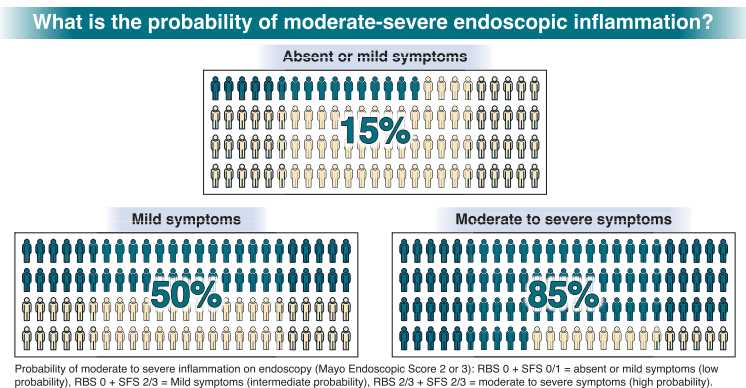
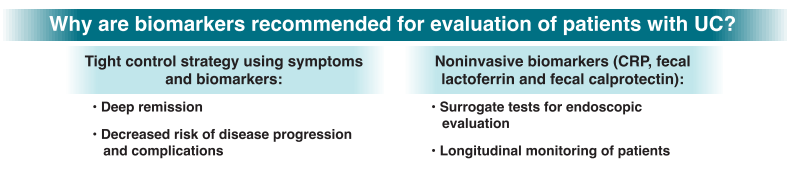
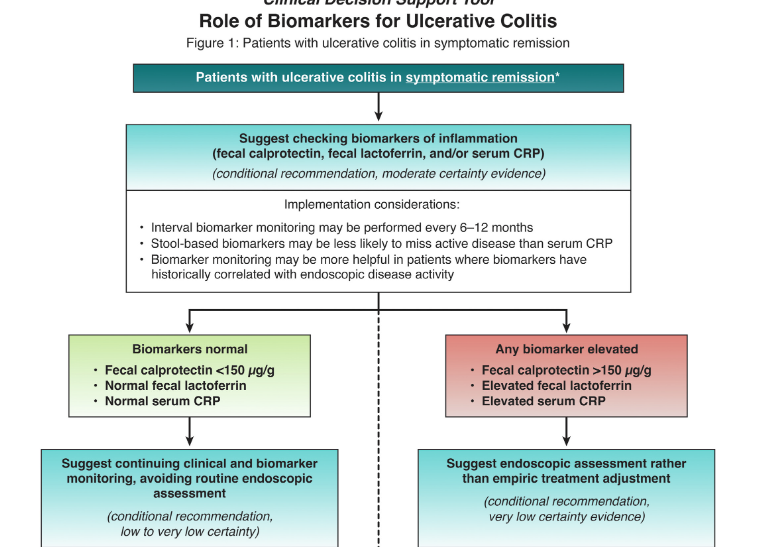
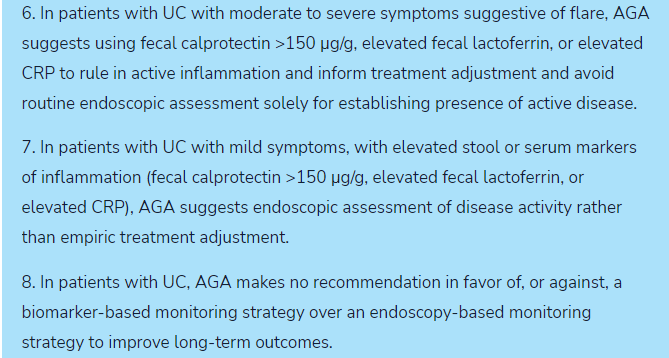
The full access links to the article and related articles provide extensive information and rationale for AGA’s biomarker recommendations in ulcerative colitis (UC). For me, the recommendations highlight the important role of biomarkers (especially fecal calprotectin (FC)) when things are going very well or very poorly. Key points:
In asymptomatic patients with normal biomarkers (FC <150, normal lactoferrin, normal CRP), the recommendations suggest continued monitoring without endoscopic assessment.
In patients with moderate-to-severe symptoms and with elevated biomarkers, the authors, likewise, advocate for treatment adjustment without endoscopic assessment.
For asymptomatic patients with elevated biomarkers and symptomatic patients with normal biomarkers, the authors recommend endoscopic assessment.
From Spotlight MaterialFrom Spotlight Material
My take: By combining biomarkers with symptoms, this improves utility of more invasive testing.
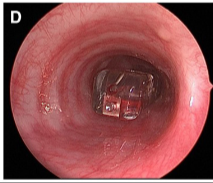
This case report describes placement of a Bravo pH capsule into the bronchus rather than in the esophagus. The complication was quickly recognized and managed by having ENT remove the capsule during the same anesthetic. It is noted that the esophageal mucosal findings included “longitudinal furrows, edema, and mucosal friability.” Biopsies “demonstrated esophagitis consistent with GER.”
Key point:
The authors note that this has led to a change in their practice: “before suction attachment, the endoscope is reintroduced into the hypopharynx to ensure the delivery system enters the cricopharyngeus. This ensures esophageal probe placement before deployment.”
My take: It has been my practice since the Bravo catheter’s inception to assure the deployment catheter is in the esophagus before releasing the Bravo capsule. However, I am impressed with this report. It is very helpful for practitioners to relay difficult experiences to help others avoid complications. This case report should be a reminder also to carefully consider whether a pH study is needed in those with erosive esophagitis.