The first several slides are from David Rubin. The last two slides were shared by my colleague, Seth Marcus. I think the speaker was Gary Lichtenstein.

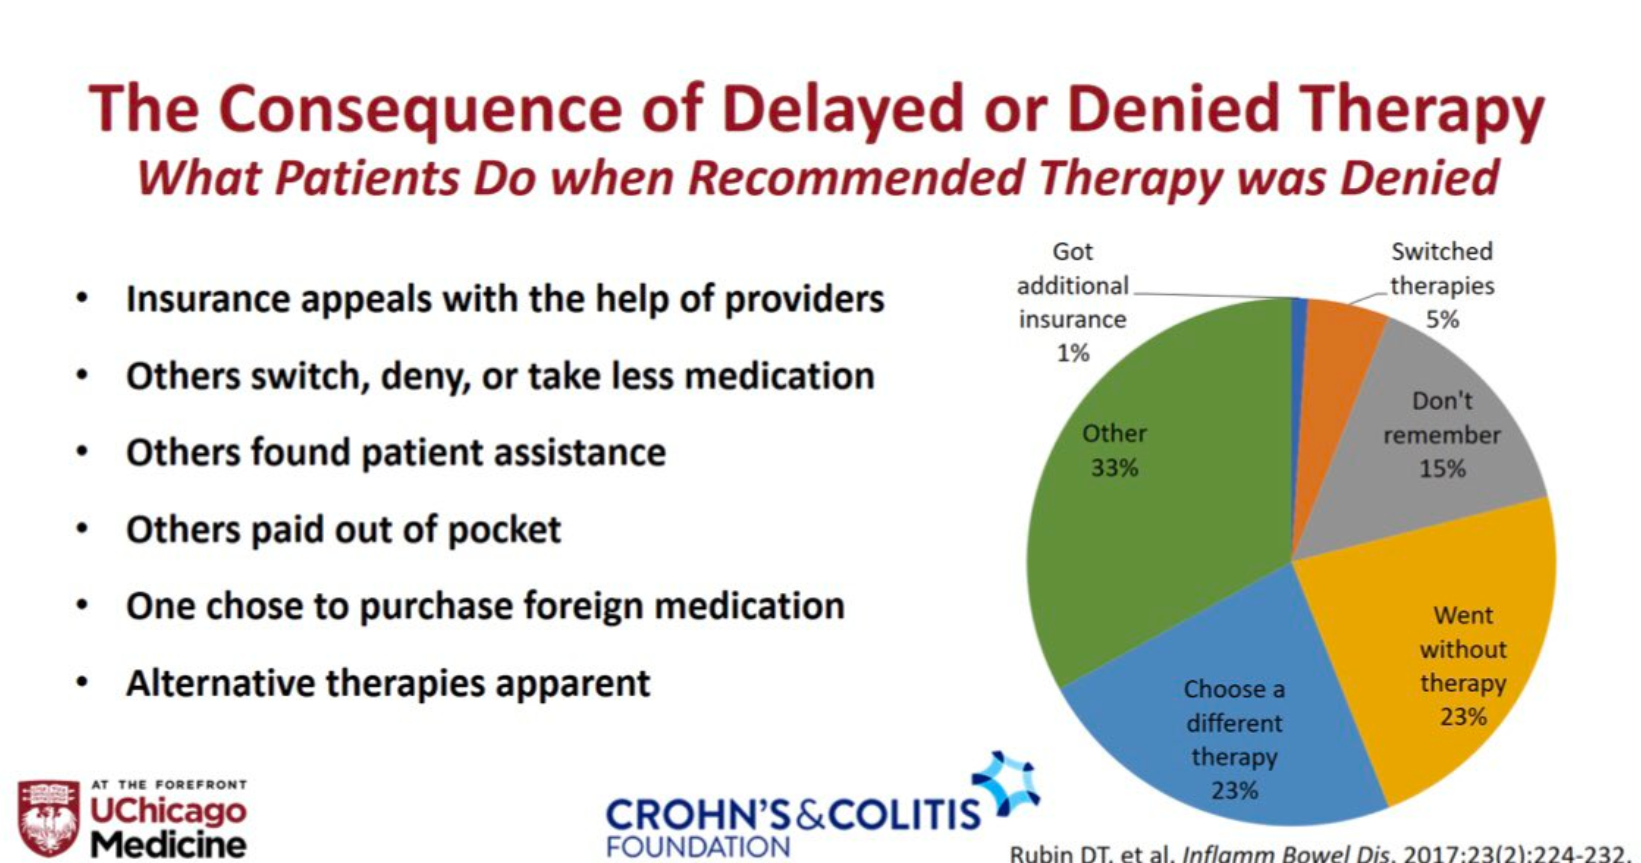
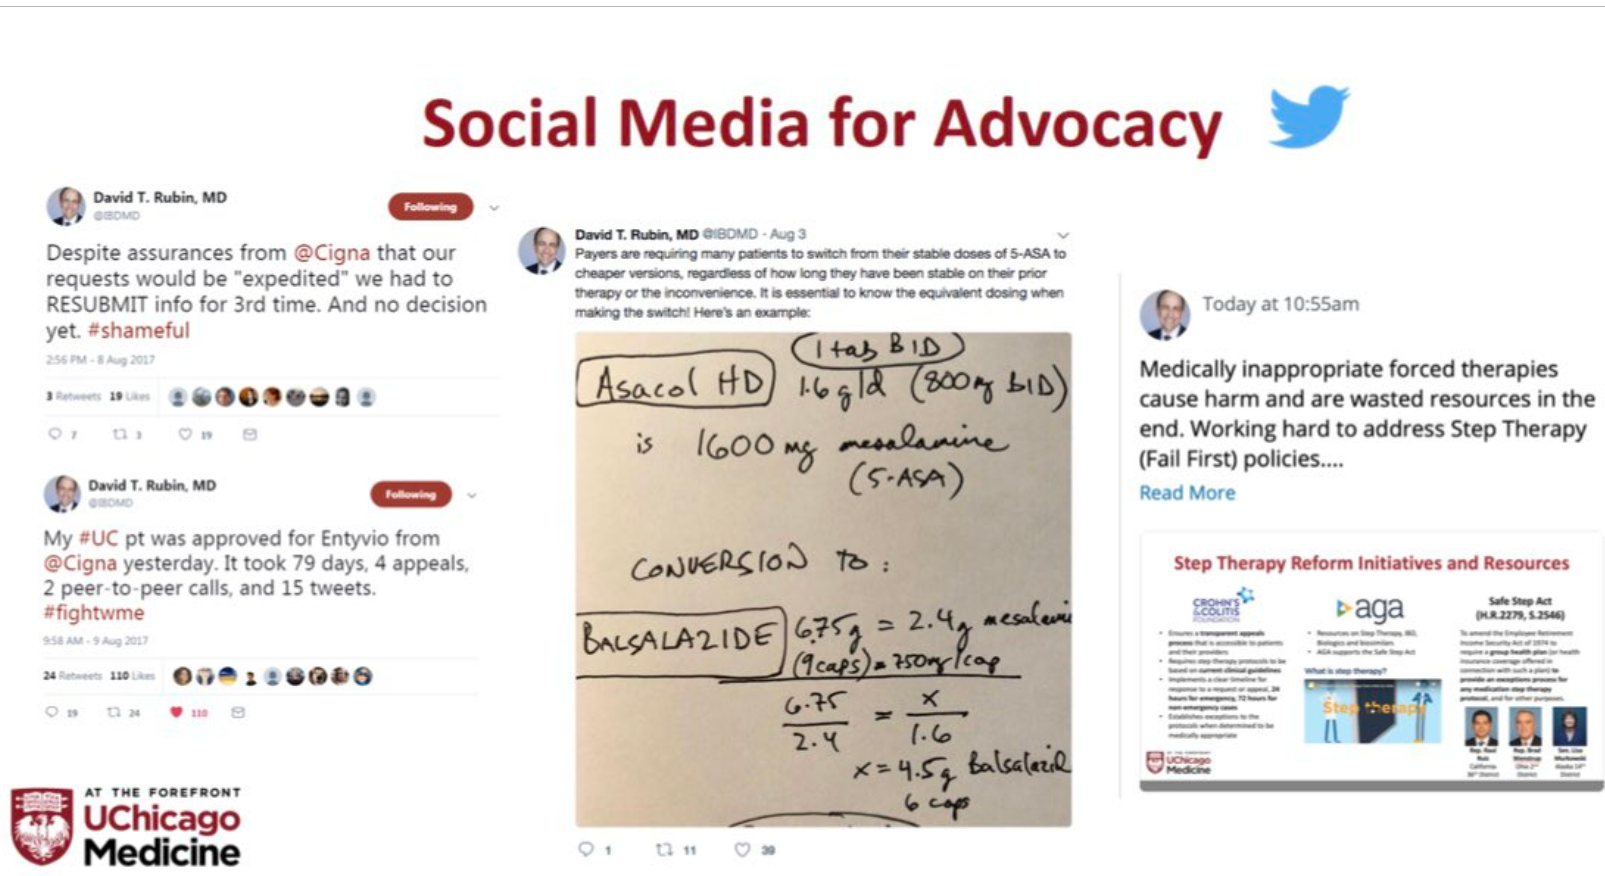




The first several slides are from David Rubin. The last two slides were shared by my colleague, Seth Marcus. I think the speaker was Gary Lichtenstein.
A recent article (J Bourke et al. .J Pediatr 2019; 215: 90-7) made me wonder if my outlook on disability-free survival of preterm infants has been skewed by the population that I encounter. That is, the outcomes from this large Australia study were better than I would have guessed.
This retrospective cohort study identified 720.091 live births from 1983-2010; in this group, 12,083 were diagnosed with a disability and 5,662 died. The authors sought to determine rates of intellectual disability or autism as identified by the IDEA (Intellectual Disability Exploring Answers) database. Because this is a retrospective study, it did not capture milder and more common neurodevelopmental disorders like attention deficit hyperactivity disorder.
Key findings:
The probability of disability-free survival to 25 years was the following:
Risk factors for lower rates of disability-free survival:
My take: This data shows the marked improvement in outcomes with longer gestation age.
Some Newsworthy Tweets:


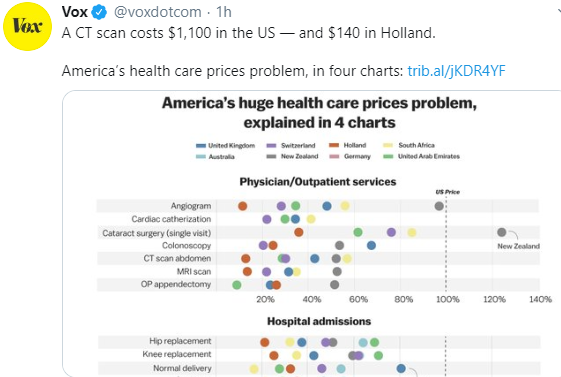
From Vox: A CT scan costs $1,100 in the US — and $140 in Holland
An excerpt:
The Health Care Cost Institute put out a new report Tuesday showing how the prices paid for medical services by private insurance in the United States stack up against prices in other countries. As expected, American prices are collectively higher than the rest.
But four charts, based on the report, show just how thoroughly the United States is outspending other countries for almost every medical service or prescription drug.

Image Available on Twitter and Can be Found in Article
Related blog posts:
A recent small study (SR Cox et al. Gastroenterology 2019: doi: 10.1053/j.gastro.2019.09.024. [Epub ahead of print]) examined the use of a low-FODMAP diet to reduce symptoms in inflammatory bowel disease.
A summary of the study in GI & Hepatology News: Low-FODMAP diet eases gut symptoms in IBD
An excerpt:
While previous research has shown that a low-FODMAP diet can relieve gut symptoms such as swelling and flatulence in people with irritable bowel syndrome, the diet has been little studied in IBD patients, for whom gut symptoms often persist even in the absence of gastrointestinal inflammation.
In a study published in Gastroenterology, Selina Cox, MD, of King’s College, London, and colleagues randomized 52 people with ulcerative colitis or Crohn’s disease with persistent gut symptoms but without active inflammation to 4 weeks on a low-FODMAP diet (n = 27) or a control diet comprising sham dietary advice (n = 25).
At 4 weeks, Dr. Cox and her colleagues reported more patients on the low-FODMAP diet reported “adequate” relief of gut symptoms (52% vs. 16%, P = .007), and saw slight improvements in health-related quality of life scores, compared with the control group. Patient-reported flatulence and bloating were significantly lower in the treatment group, while few other symptom-specific differences were seen between groups…
There were no significant between-group differences in bacterial diversity or in biomarkers of inflammation.
My take: A low-FODMAP diet may help reduce symptoms but there is no indication that this diet is an effective treatment to reduce complications or reduce inflammation for patients with Crohn’s disease or ulcerative colitis. In addition, assistance from a dietician is recommended when implementing a low-FODMAP diet.
Related Blog Posts:
AGA website for patient information: Low FODMAPs diet

Quebec City
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition
Yesterday, I listed the posts with the most views. The posts below were the ones I like the most.
General/General Health:
Nutrition:
Liver:
Endoscopy:
Intestinal Disorders:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
The following are the most viewed posts from the past year:
Wishing friends, family and colleagues a healthy and happy New Year.

Morning in Sandy Springs, GA
A recent randomized clinical study (M Urashima et al. indicates that avoiding cow’s milk formula in the first 3 days of life may prevent the development of cow’s milk allergy. Thanks to Ben Gold for this reference.
Link to full Abstract (article behind paywall): Primary Prevention of Cow’s Milk Sensitization and Food Allergy by Avoiding Supplementation With Cow’s Milk Formula at Birth
The Atopy Induced by Breastfeeding or Cow’s Milk Formula (ABC) trial, a randomized, nonblinded clinical trial, began enrollment October 1, 2013, and completed follow-up May 31, 2018, at a single university hospital in Japan. The primary outcome was sensitization to cow’s milk (IgE level, ≥0.35 allergen units [UA]/mL) at the infant’s second birthday.
Immediately after birth, newborns were randomized (1:1 ratio) to BF with or without amino acid–based elemental formula (EF) for at least the first 3 days of life (BF/EF group) or BF supplemented with CMF (≥5 mL/d) from the first day of life to 5 months of age (BF plus CMF group).
If the mother, allocated to the BF/EF group, added more than 150 mL/d of EF to BF for 3 consecutive days, EF was switched to CMF after the fourth day. Thus, offspring allocated to BF/EF could avoid CMF for at least the first 3 days of life.
Key Finding:
This study is interesting in that it suggests that exposure to cow’s milk in the first three days of life potentially increases the risk of CMA, whereas a previous study (*see below) showed showed that early exposure to CMF within 14 days after birth reduces the risk of CMA. In this previous study, exposure to small quantities of CMF for the first 3 days of life was not monitored. “Thus, the results of that observational study are not necessarily in contrast to those of the present trial.”
My take: This type of study is difficult to complete. It is difficult to understand why exposure to cow’s milk in the first two weeks of life is helpful and why exposure in the first three days of life is detrimental with regard to the development of cow’s milk allergy.
*Katz Y, Rajuan N, Goldberg MR, et al. Early exposure to cow’s milk protein is protective against IgE-mediated cow’s milk protein allergy. J Allergy Clin Immunol. 2010;126(1):77-82.e1. doi:10.1016/j.jaci.2010.04.020)
Related blog posts:

Quebec City
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
An interesting commentary (SA Santen et al. NEJM 2019; 381: 2287-9): “Kicking the Can Down the Road –When Medical Schools Fail to Self-Regulate”
Key points:
My take: This concern of advancing the medical careers of problematic individuals is limited to a small number. However, it is NOT limited to medical school but applies as well to residency & fellowship programs. In addition, of course, promoting suboptimal individuals is not limited to the field of medicine.
Related blog posts:

C Dong et al. AP&T 2019 https://doi.org/10.1111/apt.15592
Link: Systematic review with meta‐analysis: mortality in acute severe ulcerative colitis
Key point:
Related blog posts:

Quebec City

