Should Younger Transplant Patients Receive Better Organs?

Many physicians are unhappy with the current liver transplantation allocation system.  A recent article (A Cucchetti et al. Liver Transl 2015; 21: 1241-49, editorial  LB Vanwagner, AI Skaro. Liver Transpl 2015; 21: 1235-37) suggests that there should be adjustments to consider age in liver organ allocation. While this issue is not new, the article does suggest the idea of “age-mapping” which is a different twist on this subject.

The editorial notes that the current MELD system as been a poor predictor of post transplant outcomes and “does little to promote utility in organ allocation.”  Because age is not a factor in MELD, “there is a subsequent loss of equity in the current system because younger recipients receive fewer opportunities to achieve a full lifespan compared with older recipients.” However, age matching is prohibited by discrimination laws.

“Age mapping differs from age matching.” With age mapping, all candidates would have an “equal chance of getting a liver” but the probability of receiving a ‘better organ’ (donor ≤35 years) would be more likely for younger recipients.

My take: The scarcity of organ availability compounded with the possible decline in organ quality leads to these discussions.  Who really can balance unfair against unfortunate?


Related blog posts:

Brooklyn Bridge

Portopulmonary Hypertension -A Little More Data

A recent study (E Echocahrd-Dugelay et al. JPGN 2015; 61: 346-54, editorial 268-9) provides a little more data on the rare condition of portopulmonary hypertension (POPH). Untreated POPH can lead to right-sided heart failure and death; a prompt diagnosis improves the chance for responding to treatment.

In brief, the authors reviewed their experience with 14 patients that were diagnosed with POPH between 1983-2009. The authors also reviewed the literature for a total of 98 patients.

Findings:

  • 0.5% of children with portal hypertension had POPH
  • 0.9% of children with end-stage liver disease awaiting liver transplantation had POPH
  • Congenital portosystemic shunts (CPSS) appeared to be a risk factor for POPH and were noted in 3 of their 14 cases as well as 22 of 98 cases overall.
  • In treated patients (n=42), five-year survival was noted to be 80%. Treatment included vasodilator therapy, closure of CPSS, or liver transplantation.
  • Hepatopulmonary syndrome (with hypoxemia) may precede POPH; this was reported in 6 of the 98 patients in this report

Dr. Ronald Sokol’s commentary noted that guidelines for timing/frequency of pulse oximetry testing and formal echocardiographic screening are needed but “challenging given the present body of evidence.”  He recommends screening all pediatric liver transplantation candidates who have cirrhosis and portal hypertension with pulse oximetry and echocardiography as well as those with clinical features of POPH (eg. syncope, shortness of breath, dyspnea).  For other patient populations, it remains unclear.

Bottomline (from the authors): “Detection of POPH at an early stage requires systematic screening at regular intervals by echocardiography in children with all causes of portal hypertension.” Unanswered questions:

  • how much portal hypertension is needed to merit screening?
  • how often should screening take place?

Related blog posts:


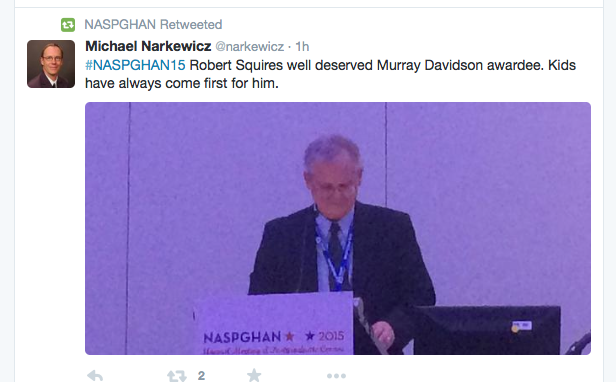
Best Tweets Two #NASPGHAN15

One clarification -I do not think that Dr. Narkewicz is calling Dr. Balistreri a panda:

Dr B

Screen Shot 2015-10-09 at 6.19.24 PM

Screen Shot 2015-10-09 at 6.16.32 PM

Screen Shot 2015-10-09 at 6.16.04 PM

Screen Shot 2015-10-09 at 6.07.49 PM

Screen Shot 2015-10-09 at 6.06.43 PM

Screen Shot 2015-10-09 at 6.05.27 PM

Dr. H

Screen Shot 2015-10-09 at 5.56.32 PM

Related blog posts:


Medical Progress for Intestinal Failure Associated Liver Disease

A recent review (WS Lee, RJ Sokol. J Pediatr 2015; 167: 519-26) provides a good explanation of the role of various intralipids and intestinal microbial dysbiosis in the setting of intestinal failure-associated lipid disease (IFALD).

The review discusses criteria for IFALD (e.g. conjugated bilirubin ≥2 mg/dL & parenteral nutrition ≥14 days), the epidemiology, and the pathogenesis. Potential risk factors and level of evidence for these risk factors is noted in Table 1.

Table 2 describes the evidence supporting suggested strategies for the prevention of IFALD. The effectiveness and recommendation levels for these strategies are generally very low and weak based on reviews by ASPEN and the American Pediatric Surgical Association.  Among the strategies, reduction of lipid emulsion to ≤ 1 g/kg/day has some of the strongest support in this table but is still regarded as level III evidence and described as “probably effective.” Other strategies reviewed included ethanol locks, multidisciplinary team management, use of ursodeoxycholic acid/bile acid supplementation, cycling of parenteral nutrition, use of prokinetics, removal of manganese and copper from parenteral nutrition, and antibiotic use to prevent bacterial overgrowth.

With regard to alternative intravenous lipids (eg. fish oil, or SMOF mixture):

  • “Although a properly powered randomized controlled trial has not been conducted, current evidence suggests that the use of FO-ILE [fish oil -intravenous lipid emulsion] is effective in reversing the established cholestasis associated with IFALD, but there is insufficient evidence for a preventative effect in neonates.”
  • “Most studies have been retrospective, used a historical comparison group, used different doses of lipid, and were conducted in patients with quite advanced IFALD.”
  • Use of FO-ILE improves biochemical parameters, but has not been shown to “improve other important long-term clinical outcomes, such as severity of hepatic fibrosis.”
  • In addition, reduced ILE and FO-ILE may result in other sequelae such as cognitive developmental delay. “Recently, lower brain weight and alterations of brain PUFA content were demonstrated in newborn piglets receiving total PN with reduced dose SO-ILE or FO-ILE compared with normal dose SO-ILE.”

My take: This review underscores how little is known about the approaches often recommended for management of IFALD.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Empty Road

Phase 3 Trial of Sebelipase Alfa for Lysosomal Acid Lipase Deficiency

A recent report (BK Burton et al. NEJM 2015; 373: 1010-20, editorial 1071-1) provides preliminary evidence of efficacy of Sebeliplase Alfa for lysosomal acid lipase deficiency.

In this multicenter, randomized, double-blind, placebo-controlled study of 66 patients, enzyme replacement therapy with Sebelipase alfa was examined (1 mg intravenously every other week).  After 20 weeks, all patients were treated by open-label. Of the 32 patients who had had liver biopsies, 10 (31%) were noted to have cirrhosis.

Findings:

  • Alanine aminotransferase normalized in 11 (36%) of treated patients compared with 2 (7%) of controls
  • Improvement in lipid levels and reduction in hepatic fat content were evident in treated patients (P<0.001 for all comparisons, except P-0.04 for triglycerides

The editorial provides a schematic explaining how sebelipase alfa targets the hepatocyte (Figure 1).  The authors note that “longer-term follow-up in a larger number of patients will be required for confirmation.”

Related blog post:

Antivirals Reduce Vertical Transmission of Hepatitis B

Chelsea Market, NYC

Chelsea Market, NYC

The latest study that shows antivirals interrupt hepatitis B viral (HBV) transmission from mother-to-infant: H-L Chen et al. Hepatology 2015; 62: 375-86.

In this open-label, non-randomized controlled study from Taiwan, the researchers recruited women to receive tenofovir (TDF) at a dose of 300 mg once a day (n=62), initiated from gestational age 30-32 weeks until 1 month following delivery, and compared them to a control group (n=56).  There were high levels of viremia with HBV DNA ≥7.5 log10 IU/mL. All infants received HBV vaccination and HBIG within 24 hours of birth.

Key findings:

  • Infant transmission of HBV was reduced: at 6 months of age, infant HBsAg positivity was 1.54% versus 10.71%, P=0.0481).  At delivery, HBV DNA positivity was noted in 6.15% compared with 31.48% of the control group.
  • Maternal ALT was improved in the TDF group. ALT elevation more than two times the upper limit of normal for ≥3 months occurred in 3.23% compared with 14.29% of controls.
  • Adverse effects: only mild to moderate (self-limited) gastrointestinal and skin symptoms were noted. No fetal abnormalities were identified.

Bottomline: Antivirals, including both tenofovir and telbivudine, reduce vertical HBV transmission with a favorable safety profile.  The use of antivirals is complementary to standard prevention which consists of providing Hepatitis B immune globulin and Hepatitis B vaccine to infants of HBV-infected pregnant women within 12 hours of birth.

Related blog posts:

Pediatric Entecavir Data

While entecavir and tenofovir have been in use for many years in adult hepatology for hepatitis B virus (HBV) infection, a well-designed study supporting their use in pediatrics has been lacking until now.  Recently, a study (M Jonas et al. Hepatology 2015; DOI: 10.1002/hep.28015)  has shown that entecavir is effective for pediatric HBV

Link to full study. Randomized Controlled Trial of Entecavir Versus Placebo in Children with HBeAg-positive Chronic Hepatitis B

Here’s the abstract:

This ongoing, randomized phase III study assesses the safety and efficacy of entecavir versus placebo in nucleos(t)ide-naive children (2 to <18 years) with HBeAg-positive chronic hepatitis B (CHB). Blinded treatment was administered for a minimum of 48 weeks. After Week 48, patients with HBeAg seroconversion continued blinded treatment; those without, switched to open-label entecavir. The primary endpoint was HBeAg seroconversion and HBV DNA <50 IU/mL at Week 48. A total of 180 patients were randomized (2:1) and treated. Baseline median age was 12 years, with approximately 50% of children aged >12 to <18, and 25% each aged ≥2 to ≤6 and >6 to ≤12. Rates for the primary endpoint at Week 48 were significantly higher with entecavir than placebo (24.2% [29/120] versus 3.3% [2/60]; P=0.0008). Furthermore, higher response rates were observed with entecavir compared with placebo for the key Week 48 secondary endpoints: HBV DNA <50 IU/mL (49.2% [59/120] versus 3.3% [2/60]; P < 0.0001), alanine aminotransferase normalization (67.5% [81/120] versus 23.3% [14/60]; P < 0.0001), and HBeAg seroconversion (24.2% [29/120] versus 10.0% [6/60]; P = 0.0210). Among entecavir-randomized patients there was an increase in all efficacy endpoints between Weeks 48 and 96, including an increase from 49% to 64% in virologic suppression. The cumulative probability of emergent entecavir resistance through Years 1 and 2 of entecavir was 0.6 and 2.6%, respectively. Entecavir was well tolerated with no observed differences in adverse events or changes in growth compared with placebo. Conclusion: In childhood CHB, entecavir demonstrated superior antiviral efficacy to placebo with a favorable safety profile. These results support the use of entecavir as a therapeutic option in children and adolescents with CHB.

Related blog posts:

From Brooklyn Bridge

From Brooklyn Bridge


Helpful Review on Biliary Atresia

Biliary atresia (BA) remains the leading cause of pediatric liver transplantation and a frequent cause of cholestasis in newborns.  A recent review (AG Feldman, CL Mack. JPGN 2015; 61: 167-75) provides a helpful update. The article begins with a review on pathogenesis, though this remains unknown and continues to be an area of speculation.

The section on evaluation includes a suggested diagnostic algorithm for neonatal cholestasis.  In short, for a 2 week old with jaundice , the authors recommend (STEP 1) fractionating the bilirubin.  The infant is considered cholestasis if the direct bilirubin is ≥1 mg/dL (if total bilirubin is <5 mg/dL) or if direct bilirubin ≥20% of total bilirubin (if total bilirubin is >5 mg/dL).

Among cholestatic infants, the authors recommend (STEP 2) next checking ultrasound and alpha-one antitrypsin (A1AT) (level & phenotype).  The text implies that the authors would check a GGTP.  While this is not in their algorithm, many would suggest checking urine reducing substances, coags, serum glucose, and consideration of sepsis evaluation; these tests can identify issues that are more urgent than identifying biliary atresia.

STEP 3: If U/S and A1AT, are not diagnostic, consider urine culture, urine reducing substances, urine succinylacetone, and additional infectious studies.

STEP 4: Proceed with liver biopsy. If findings of biliary atresia (eg. bile plugs, bile duct proliferation, portal fibrosis), proceed with intraoperative cholangiogram.

Other points:

  • “It is rare for an infant with BA to have a GGTP level <200 U/L.” If low GGTP, consider PFIC, inborn error of bile acid metabolism, and panhypopituitarism.
  • Extensive differential diagnosis table given ((Table 1)
  • “Late diagnosis of BA remains a problem in the United States. The average age of HPE [hepatoportoenterostomy] is 61 days and 44% of patients still undergo HPE after 60 days of life.”  The authors indicate a goal for HPE of taking place  at <45 days of life.
  • Successful HPE can occur even with late diagnosis. 10% to 20% of children who undergo HPE after 100 to 120 days of life still have success in restoring bile flow.”
  • Early/successful HPE is helpful in increasing 10-year transplant-free rate.  Early on, 3 months after HPE, those with a total bilirubin <2 mg/dL compared with those with a total bilirubin of >6 mg/dL have a much lower likelihood of liver transplantation by 2 years of age: 84% vs. 16%.
  • Recommends checking a pulse oximetry at routine followup visits following HPE to look for the possibility of hepatopulmonary syndrome.
  • The article reviews complications including ascites, portal hypertension/GI bleeding, cholangitis, malignancy, and hepatopulmonary syndrome/portopulmonary hypertension.
  • Outcomes: With HPE, “up to two-thirds of patients with BA have short-term clearance of jaundice.” Yet, “80% of patients with biliary atresia will require liver transplantation during childhood.”

Also noted:

“Biliary Atresia is Associated with Hypertension” JPGN 2015; 61: 182-86.

“Pathogenesis of biliary atresia: defining biology to understand clinical phenotypes” A Asai, A Miethke, JA Bezerra. Nat Rev Gastroenterol Hepatol 2015; 12: 343-52.  This review provides in-depth review examines more precise phenotyping, influencing factors (eg. cytomegalovirus), and potential mechanisms.

Related blog posts:

From Mt Washburn, Yellowstone

From Mt Washburn, Yellowstone

Impact of Kasai Portoenterostomy on Liver Transplantation

Briefly noted: JS Neto, et al. Liver Transpl 2015; 21: 922-7.

This retrospective cohort study of 347 biliary atresia patients who underwent liver transplantation )LT) (1995-2013) divided patients into eraly Kasai failures (K-EF) (27%), late Kasai failures (K-LF) (33%), and no Kasai portenterostomy (No-K) (40%). K-EF was defined by patients who underwent LT before 12 months of age.

Key findings:

  • After adjustment of confounding factors, the K-LF group had an 84% less probability of dying and 55% less chance to undergo retransplantation.
  • Having a K-EF did not have an effect on patient or graft survival compared to No-K.
  • Both the K-LF and K-EF had more post-LT biliary complications.

Bottomline: This retrospective study suggests that if a Kasai portoenterostomy helps postpone LT then this results in improved outcomes; whereas if it is ineffective, it does not impact survival compared to those who did not undergo a Kasai.

Related blog posts:

From Cascade Canyon, Grand Tetons

From Cascade Canyon, Grand Tetons

What HBV Testing is Needed Before Tumor Necrosis Factor Inhibitor Therapy

As noted in a previous blog post (What’s Going on with Hepatitis A and Hepatitis B?):

Hepatitis B Reactivation risk & recommendation: (For all of the specifics — Full text article link)

  • High risk of reactivation (>10%): B cell depleting agents (eg. rituximab, ofatumumab), anthracycline derivatives (eg. doxorubicin, epirubicin), and daily moderate to high dose steroids (>10 mg) for at least 4 weeks. Recommendation: Use HBV prophylaxis
  • Moderate risk of reactivation (1-10%): anti-TNF therapy, integrin inhibitors (eg. ustekinimab, vedolizumab), tyrosine kinase inhibitors, low-dose steroids daily (<10 mg/day) for at least 4 weeks.  Recommendation: Use HBV prophylaxis if HBsAg-positive but not if only anti-HBc-positive
  • Low risk of reactivation (<1%): azathiopurine, 6-mercaptopurine, methotrexate. Recommendation: No antiviral prophylaxis required.

For those interested in a more detailed summary of the recommendations: AGA Website HBV Reactivation Recommendations

In line with the reactivation risk, a new study (and editorial) (M Barone et al. Hepatology 2015; 62: 40-6; editorial BP Perillo. Hepatology 2105; 62: 16-8) indicates that for those receiving tumor necrosis inhibitor (anti-TNF) monotherapy, hepatitis B screening requires only checking HBsAg. The study examined a total of 1218 Caucasian rheumatologic patients (receiving biologic agents) between 2001-12. In this cohort, the authors identified 179 patients who had a previously resolved HBV infection; 146 treated with anti-TNF, 14 with rituximab, and 19 with other biologic therapy. Key finding: HBV reactivation was not seen in these patients.

Bottomline: For most pediatric patients receiving anti-TNF monotherapy (eg. infliximab, adalimumab), screening with HBsAg alone should suffice.

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Grand Tetons from Jackson Lodge

Grand Tetons from Jackson Lodge