How to Do a Colonoscopic Polypectomy & U.S. COVID-19 Tracker

NPR’s website has a good tracker of what is going in each state.  Here’s the link:

NPR: Map: Tracking The Spread Of The Coronavirus In The U.S  One example: on this tracher, in Georgia, March 27, 8:30 am: 1642 reported cases, 56 deaths. (However, Georgia has conducted less than 10,000 tests in a population of more than 10 million).

——————–

A recent review (M Kay, R Wyllie. JPGN 2020; 70: 280-4) provides some practical tips for improving polypectomy technique.

Key points:

The optimal position for the polyp is in the 5-7 o’clock position.

  • Snaring juvenile polyps close to the head rather than close to the colonic wall “allows for easier therapeutic intervention if polypectomy bleeding occurs” (eg. hemoclip) and may lower the risk of complications like perforation
  • Epinephrine volume reduction (for larger polyps) (use 1:10,000 dilution) and saline-assisted polypectomy may facilitate procedure.  Large polyps (>2 cm) could require piecemeal resection; epinephrine reduction may result in a decreased size as well.
  • “Cold snare technique has replaced use of hot biopsy forceps in adults for removal of small sessile polyps”
  • Electrosurgical units (ESUs) -settings are specific to each unit.  Newer ‘smart’ ESUs have suggested default settings, typically lower settings for right colon. “Most endoscopists use pure coagulation current or a combination of coagulation and cutting settings (blended current) for snare polypectomy. Use of pure cutting current without coagulation will result in bleeding.”

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition
Pipeline Medications for Ulcerative Colitis (Part 2)

To continue with topic of new medications for ulcerative colitis started yesterday -two more articles:

  • WJ Sandborn et al. Gastroenterol 2020; 158: 537-49
  • S Danese. Gastroenterol 2020; 158: 467-70 (commentary)

The first reference describes a randomized phase 2 study of mirikizumab with 249 patients.  Mirikizumab is a monoclonal antibody to the p19 subunit of IL23. A similar agent, ustekinumab is a monoclonal antibody directed at the p40 subunit of IL23 and IL12; thus mirikuzumab is more selective targeting of IL23. the authors examined response to the study drug at 3 doses: 50 mg, 200 mg, and 600 mg and compared to intravenous placebo.  All patients received dosing at weeks 0, 4, and 8. A subset of patients continued with subcutaneous treatment starting at week 12, with 47 receiving 200 mg every 4 weeks and 46 receiving 200 mg every 12 weeks. 63% of patients in this trial had previous exposure to biologics.

Key findings:

  • At week 12, 15.9% (50 mg), 22.6% (200 mg), and 11.5 % (600 mg) in the treatment groups achieved clinical remission compared to 4.8% of the placebo group
  • Clinical responses occurred in 41.3%, 59.7%, and 49.2% in the respective treatment groups compared to 20.6% in placebo group
  • At week 52, clinical remission was achieved in 46.8% of SC every 4 weeks and 37.0% every 12 weeks.

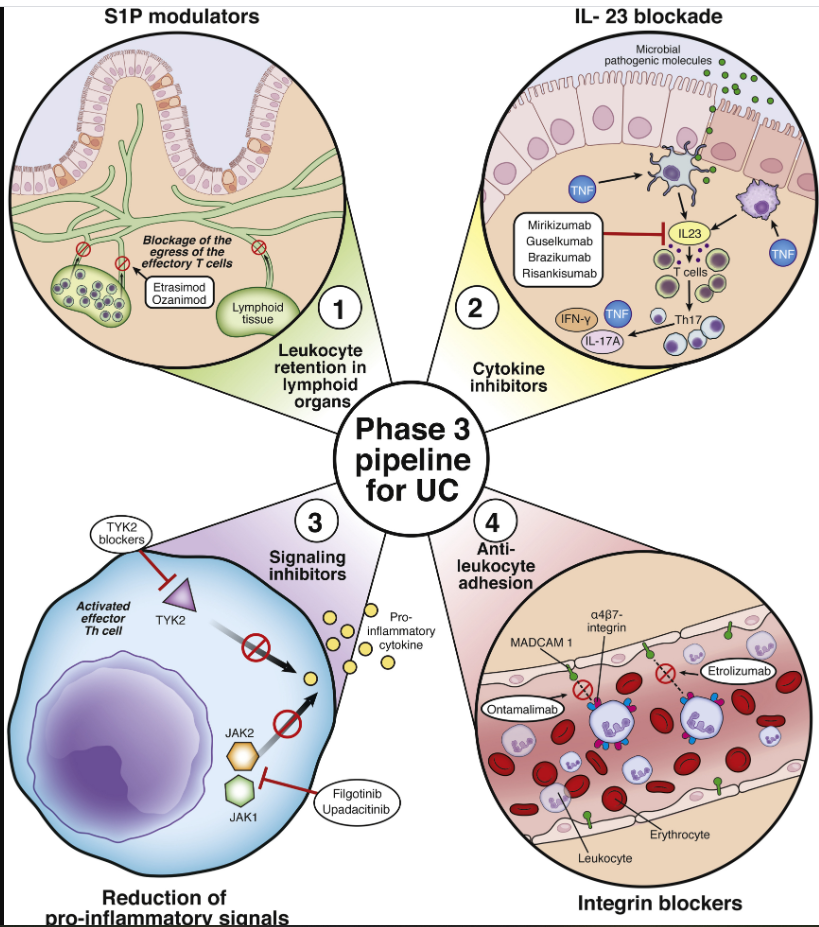
In the commentary, Danese reviews the pipeline of new drugs emerging for ulcerative colitis.  Full Text Link: New Drugs in the Ulcerative Colitis Pipeline: Prometheus Unbound

A couple of key points:

  • “Like Prometheus, who gave fire to humans and paid with the price of eternal torment, so the gift of new drugs in ulcerative colitis brings the consequence of patients with heterogeneous disease being cycled indiscriminately through similarly modestly effective agents.”
  • “Predictive biomarkers are needed” to optimize treatment and avoid ineffective and potentially harmful treatments

My take: The emergence of new treatments is welcome given the frequent loss of response or lack of response to current therapies.  Two questions: How will we decide which agent(s) is the best one to use? When will pediatric studies be available?


Pipeline Medications for Ulcerative Colitis (Part 1) & Face Mask Shortages

Before getting to today’s post, I wanted to provide a link on why we are desperately short of face masks in the midst of this crisis: NY Times: How the World’s Richest Country Ran Out of a 75-Cent Face Mask

An excerpt:

The answer to why we’re running out of protective gear involves a very American set of capitalist pathologies — the rise and inevitable lure of low-cost overseas manufacturing, and a strategic failure, at the national level and in the health care industry, to consider seriously the cascading vulnerabilities that flowed from the incentives to reduce costs…

Given the vast global need for masks — in the United States alone, fighting the coronavirus will consume 3.5 billion face masks, according to an estimate by the Department of Health and Human Services — corporate generosity will fall short. People in the mask business say it will take a few months, at a minimum, to significantly expand production…

Hospitals began to run out of masks for the same reason that supermarkets ran out of toilet paper — because their “just-in-time” supply chains, which call for holding as little inventory as possible to meet demand, are built to optimize efficiency, not resiliency.

My take: Conserve, conserve, conserve PPE -supply chains meeting the need is NOT imminent.

—————

Several articles from Gastroenterology highlight emerging medications for ulcerative colitis (UC).

Two of the studies:

  • WJ Sandborn et al. Gastroenterol 2020; 158: 550-61.
  • WJ Sandborn et al. Gastroenterol 2020; 158: 562-72.

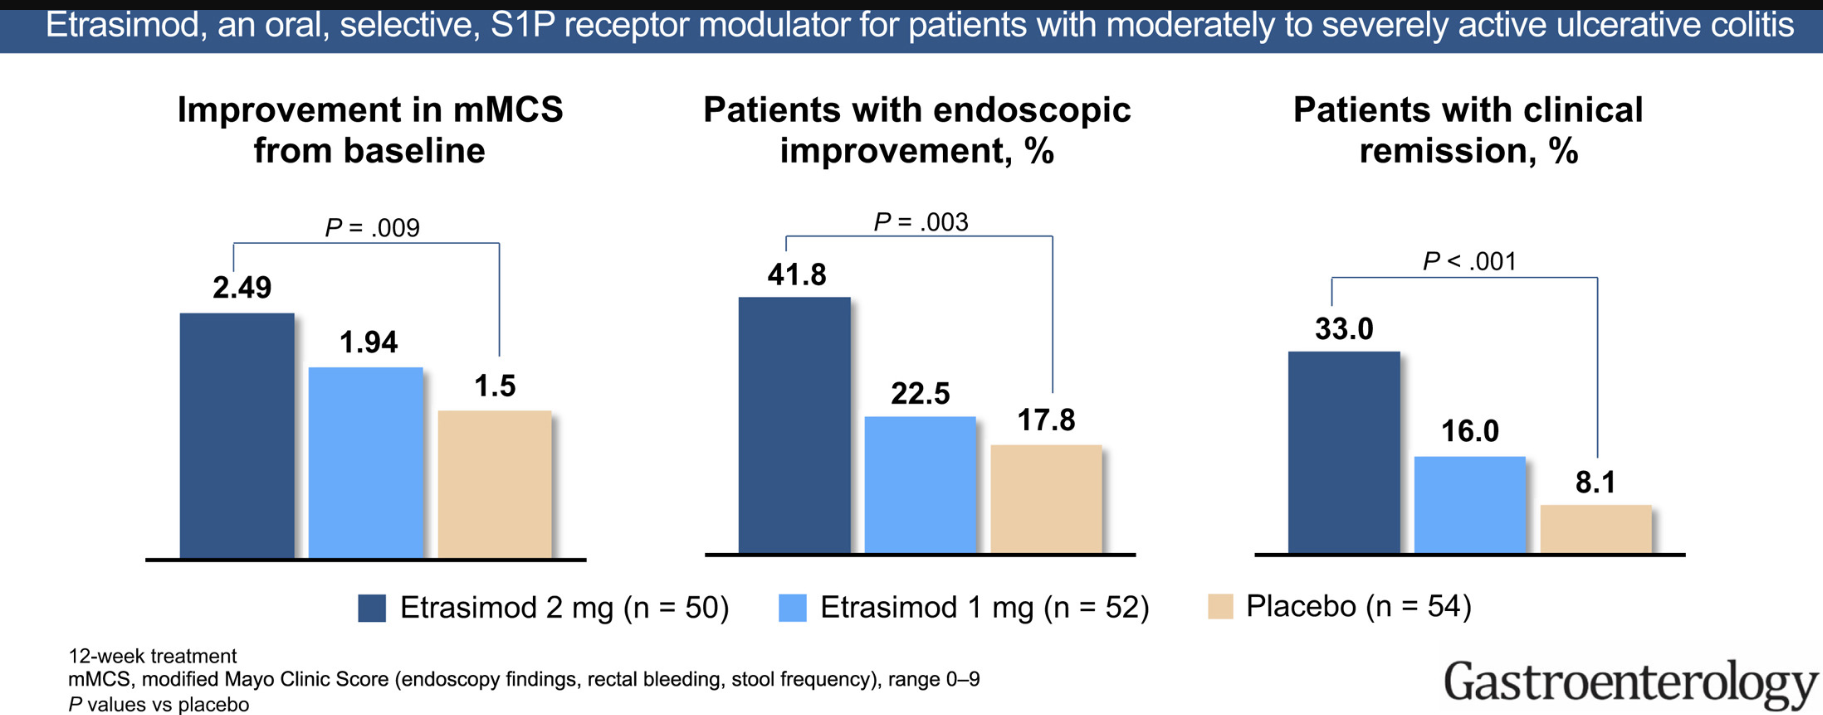
The first study was a phase 2 randomized trial of etrasimod which is an oral selective sphingosine 1-phosphate receptor modulator.  A total of 156 patients were randomized into 3 groups: placebo, 1 mg etrasimod, and 2 mg etrasimod.

Key findings (graphical abstract):

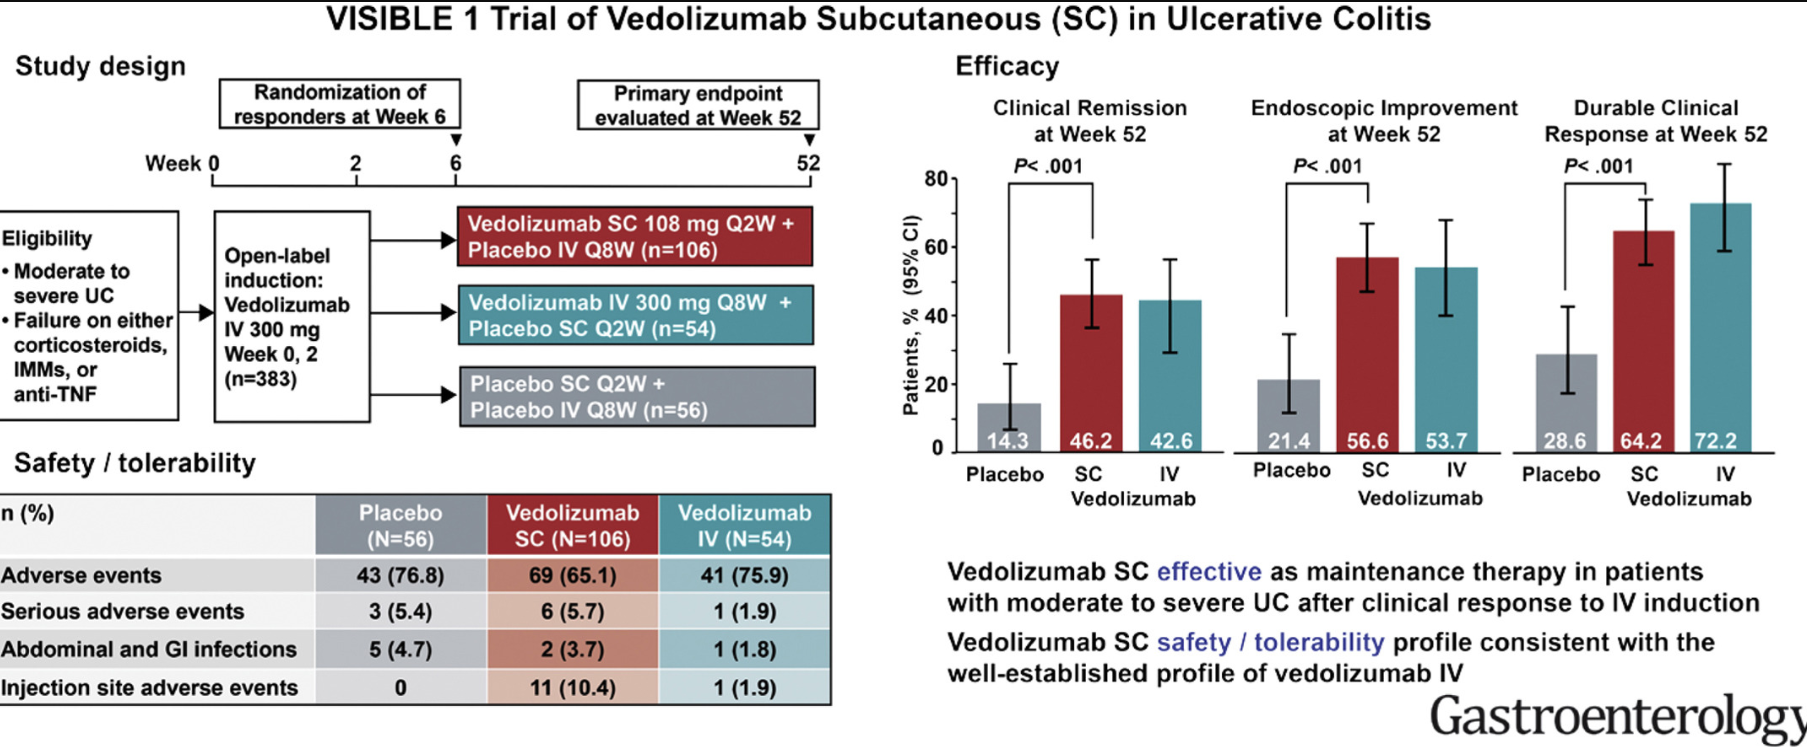
In the second phase 3, double-blind, double-dummy study, Sandborn et al show that, after the initial 2 intravenous doses,  among patients with an initial response subcutaneous vedolizumab (108 mg every 2 weeks) had similar effectiveness to intravenous vedolizumab (300 mg every 8 weeks); both SC and IV vedolizumab resulted in higher clinical remission rates compared to placebo at 52 weeks in the 216 patients: 46.2%, 42.6%, and 14.3% respectively.

Full text link: Efficacy and Safety of Vedolizumab Subcutaneous Formulation in a Randomized Trial of Patients With Ulcerative Colitis

Iron Injectables

At bottom of post, more information on COVID-19.

——————————————————-

At a recent Pharmacy, Nutrition, and Therapeutics (PNT) meeting, one of the topics that we reviewed was injectable iron agents, primarily iron sucrose (Venofer ®) and ferric carboxymaltose (Injectafer®).  Iron dextran is mainly used as a supplement in parenteral nutrition in our patient population.

Also, this topic is reviewed in Practical Gastroenterology Jan 2020 (M Auerbach et al. January 2020 • Volume XLIV, Issue 1: Treatment of Iron Deficiency in Gastroenterology: A New Paradigm

Key points:

  • Venofer® is much less expensive and currently has an FDA indication for children. To provide 1500 mg, Venofer®, 5 doses of 300 mg (~$75/dose)~$375. Injectafer®, 2 doses of 750 mg (~$600/dose) ~1200.  This does not include potential travel and other ancillary costs.
  • Dosing: Injectafer® can give large amounts of iron; in adults, typical dose is 750 mg given 7 days apart (in children 15 mg/kg/dose with 750 mg max).  FDA approved method is to administer over 15 minutes. Venofer® in children is 5-7 mg/kg/dose with 300 mg max per dose.
  • Injectafer® has been associated with hypophosphatemia (in 27%, <2 mg/dL); Hypophosphatemia has also been reported with iron sucrose.  The reported incidence of hypophosphatemia is higher with ferric carboxymaltose vs iron sucrose.
  • Other Adverse Effects: 
Iron Sucrose (Venofer®) Ferric Carboxy (Injectafer®)
Nausea 8.6% 7.2%
Vomiting 5% 1.7%
Diarrhea 7.2% <1%
Dizziness 6.5% 2%
Hypertension 6.5% 3.8%

Oral vs IV Iron for IBD: Auerbach et al recommends that “iron should only be given orally to IBD patients with inactive disease, mild anemia, and good tolerance of oral iron; in patients with active IBD oral iron should be avoided.”  They state that “oral iron has been shown to exacerbate intestinal inflammation of IBD independent of anemia, and cause luminal changes in microbiota and bacterial metabolism, which may negatively alter the microbiome.” (Has IV iron’s effect on the microbiome been studied/compared to oral iron?)

Safety of intravenous iron: “In a recent meta-analysis, the results of more than 10,000 patients who were treated with intravenous iron were reported. Compared to oral iron, placebo, and even intramuscular iron (which should never be given), while minor infusion reactions were observed with IV iron, there was no increase in serious adverse events compared to any comparator including placebo.”

My take: Injectafer® is likely preferable to Venofer® in the outpatient setting as adequate dosing can be given in 1 or 2 infusions.

Related blog posts:

Trail on Blood Mountain

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition
————————————

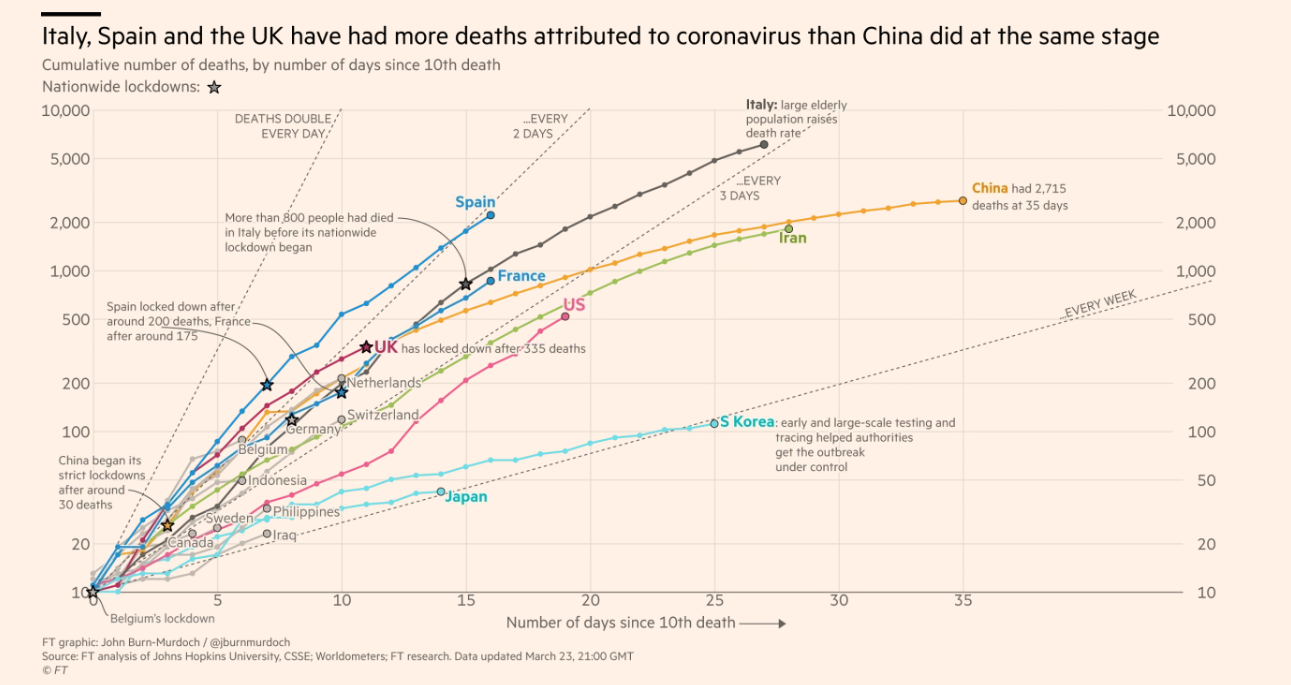
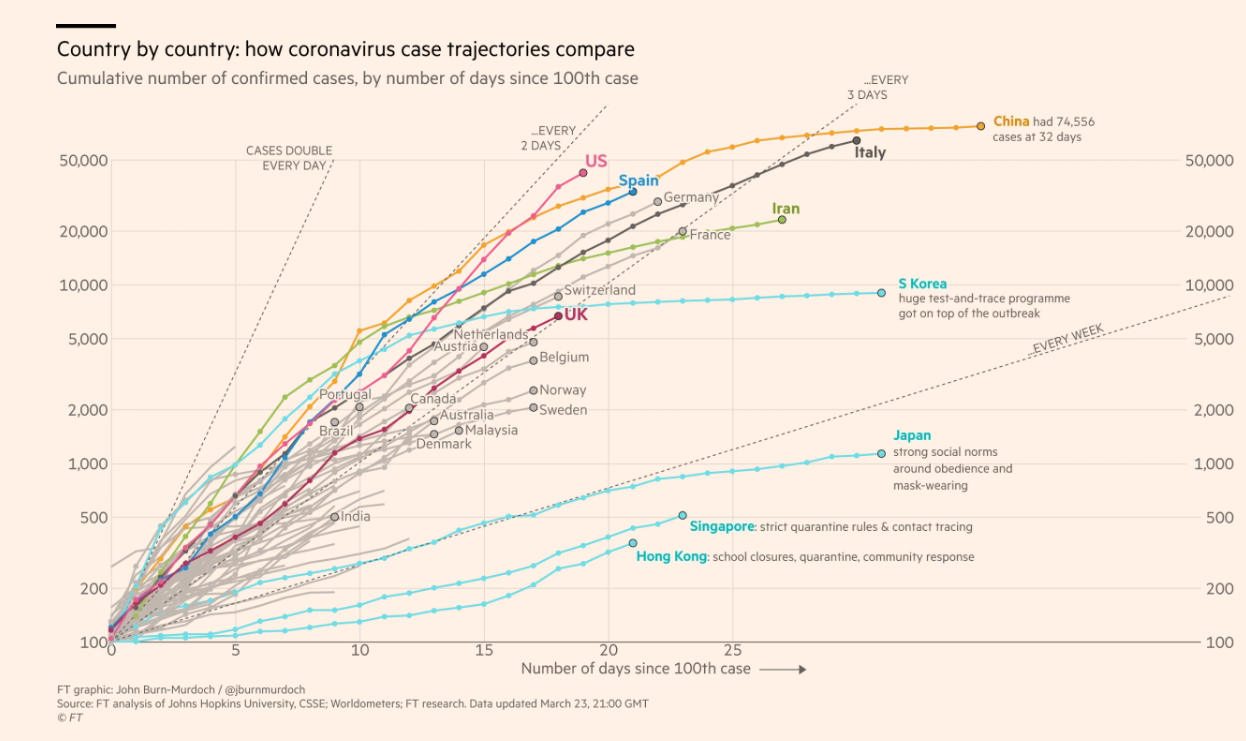
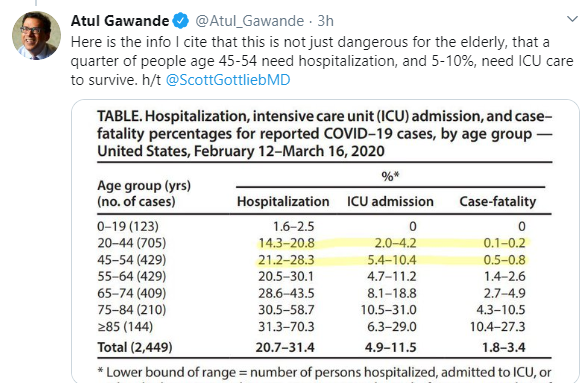
Here’s a link to Financial Times COVID-19 Tracker –includes logrithmic charts plotting the rates of reported infection and deaths and allows quick comparison between countries and high-volume locations (eg. Madrid, Lombardia, NY City).  Some figures from March 23, 2100 GMT noted below; unfortunately, the U.S is likely to the world leader in number of reported cases quite soon.

Other relevant tweets:


Esophagus! & Nutritional/GI Outcomes with Esophageal Atresia

In 8th grade, our English teacher would say ‘Esophagus, recite that poem.’  He would say this to everybody.  It is possible that the flask that he carried could have influenced his word choice.

That anecdote came to mind as reading a recent article (K Birketvedt et al. J Pediatr 2020; 218: 130-7) which showed that a large number of adolescents with history of esophageal disease (esophageal atresia [EA]) had a high likelihood of suboptimal nutritional parameters. In this study with 68 pediatric subjects, extensive investigations including 4-day diet records, blood tests, pH measuring, EAT (eating assessment test) questionnaire, and interviews. Median age at follow-up was 16 years.

Key findings:

  • Median height-for-age Z score was -0.6. 10 patients (15%) were considered stunted (height-for-age Z score <-2).
  • More than two-thirds reported symptoms of dysphagia (EAT score ≥3) and avoided specific foods.
  • 48 (71%) had suboptimal energy intake on diet records –intake below age-appropriate recommendations.  Many had low vitamin D and iron intake.
  • 13 of 68 patients had VACTERL association and 17 (25%) had congenital heart disease

My take: If your esophagus is not working right, it definitely can impair one’s nutritional status.  Some patients have other reasons (other comorbidities) that could influence these reported results.

As for the anecdote, I still remember some of the poems we had to recite.  The one I remember best:

To An Athlete Dying Young  A. E. Housman – 1859-1936 

The time you won your town the race
We chaired you through the market-place; 
Man and boy stood cheering by, 
And home we brought you shoulder-high.  

To-day, the road all runners come,    
Shoulder-high we bring you home,  
And set you at your threshold down,  
Townsman of a stiller town.  

Smart lad, to slip betimes away  
From fields where glory does not stay, 
And early though the laurel grows  
It withers quicker than the rose.  

Eyes the shady night has shut  
Cannot see the record cut,  
And silence sounds no worse than cheers 
After earth has stopped the ears:  

Now you will not swell the rout  
Of lads that wore their honours out,  
Runners whom renown outran  
And the name died before the man. 

So set, before its echoes fade,  
The fleet foot on the sill of shade,  
And hold to the low lintel up  
The still-defended challenge-cup.  

And round that early-laurelled head
Will flock to gaze the strengthless dead,  
And find unwithered on its curls  
The garland briefer than a girl’s.

Related blog posts:


Ethical Dilemmas and Digestive Symptoms –Common with COVID-19

Ethical Dilemmas:

Full link: NEJM: Facing Covid-19 in Italy — Ethics, Logistics, and Therapeutics on the Epidemic’s Front Line

That truth is rather grim. Though Italy’s health system is highly regarded and has 3.2 hospital beds per 1000 people (as compared with 2.8 in the United States), it has been impossible to meet the needs of so many critically ill patients simultaneously…

If protecting patients is difficult, so is protecting health care workers, including nurses, respiratory therapists, and those tasked to clean the rooms between patients…

Though approaches vary even within a single hospital, I sensed that age was often given the most weight.

In the midst of the outbreak’s peak in northern Italy, as physicians struggled to wean patients off ventilators while others developed severe respiratory decompensation, hospitals had to lower the age cutoff — from 80 to 75 at one hospital, for instance…

The first and most important is to separate clinicians providing care from those making triage decisions. The “triage officer,” backed by a team with expertise in nursing and respiratory therapy, would make resource-allocation decisions and communicate them to the clinical team, the patient, and the family.

Digestive Symptoms:

From ACG: Full Link: ACG Media Statement

Excerpt:  (March 18, 2020) – Digestive symptoms are common in COVID19, occurring as the chief complaint in nearly half of patients presenting to hospital according to a new
descriptive, cross-sectional multicenter study from China by investigators from the Wuhan Medical Treatment Expert Group for COVID-19 published today in The American Journal of Gastroenterology

Key findings:

  • Compared to COVID-19 patients without digestive symptoms, those with digestive symptoms have a longer time from onset to admission and a worse clinical outcome according to this analysis by investigators from several hospitals and research centers in China who gathered data on 204 patients with COVID-19 presenting to three
    hospitals in Hubei province from January 18, 2020 to February 28, 2020.
  • Patients with digestive symptoms had a variety of manifestations, such as anorexia (83 [83.8%] cases), diarrhea (29 [29.3%] cases), vomiting (8 [0.8%] cases), and abdominal pain (4 [0.4%] cases)
  • As the severity of the disease increased, digestive symptoms became more pronounced.
  • Link to study: Pan L, et al., Clinical characteristics of COVID-19 patients with digestive symptoms in Hubei, China: a descriptive, cross-sectional, multicenter study, Am J Gastroenterol 


More Advice on Coronavirus for Pediatric GIs: NASPGHAN and CCFA

For Georgia:

NASPGHAN statement regarding Coronavirus (SARS-CoV-2) Associated Infectious Disease (COVID -19) and Pediatric GI Patient Care and Providers.

Dear Members,

In view of the COVID -19 pandemic, care of our pediatric GI patients and at the same time our pediatric GI providers (i.e. physicians and other members of the healthcare team) is an utmost priority at NASPGHAN. NASPGHAN is working on several initiatives concurrently, and we are writing at this time to make you aware.

1. The Endoscopy Committee and the Clinical Practice Committee are working on a statement regarding elective procedures for pediatric GI patients with respect to this highly contagious pathogen, COVID to both preserve Personal Protective Equipment (PPE) as well as limit potential exposure.

2. A task force of leaders from NASPGHAN, ESPGHAN, LASPGHAN, and Asia (Hangzhou, China) will be writing a commentary to be published in the JPGN, our journal, with what COVID-19 means to the pediatric gastroenterologist.

3. Mike Kappleman of UNC, ICN, NASPGHAN and in particular the IBD Committee, are launching a prospective, real-time monitoring study of COVID-19 in IBD patients. The study is IRB and HIPAA approved and will link its data with that collected by the European Porto group’s study of coronavirus in IBD patients in Europe and Asia, thereby allowing an operational real-time active surveillance network for children and adolescents with IBD (our patients).

4. Jason Silverman, Jennifer Lee, and Peter Lu are putting together a special episode of the Bowel Sounds Podcast™ including relevant up-to-date guidelines and information about COVID-19 as it relates to our members and our patients.

5. The Endoscopy Committee and Clinical Practice Committee are working on information and options for telemedicine and virtual health, given the more recent announcement by CMS and the White House/President Trump in terms of changes in reimbursement given the coronavirus pandemic.

6. Within the next 24 hours, the NASPGHAN Website, as well as GIKids.org will house resources and links to the Centers for Disease Control and Prevention (CDC), the American Academy of Pediatrics (AAP), Crohn’s and Colitis Foundation (CCF), the Canadian Association of Gastroenterology (CAG) and the Joint GI Societies Statement (adult-based), including ASGE, ACG, AGA on Endoscopic procedures in the face of COVID-19.

7. Finally, please feel free to send us suggestions that would help our pediatric GI community work towards creative solutions during this time.

Sincerely,

Karen F. Murray MD
President, NASPGHAN

James Heubi MD
Past President, NASPGHAN

Benjamin Gold MD
President Elect, NASPGHAN

Jeannie S. Huang MD
Secretary Treasurer, NASPGHAN

Rina Sanghavi MD

Underlying Genetic Disease in Pediatric Inflammatory Bowel Disease

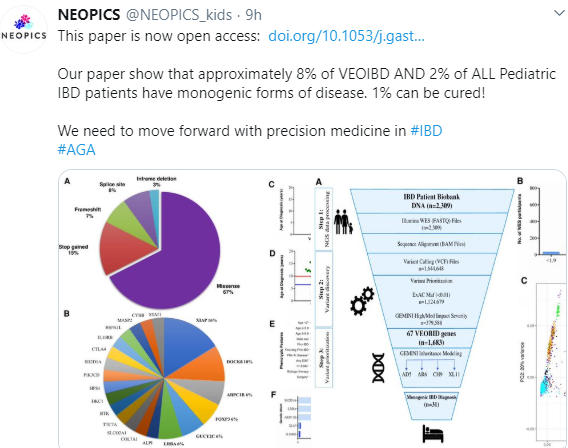
Link to text of accepted study (Gastroenterology, ahead of publication): Prevalence and Clinical Features of Inflammatory Bowel Diseases Associated with Monogenic Variants, Identified by Whole-exome Sequencing in 1000 Children at a Single Center 

Abstract:

Background & Aims: A proportion of infants and young children with inflammatory bowel diseases (IBD) have subtypes associated with a single gene variant (monogenic IBD). We aimed to determine the prevalence of monogenic disease in a cohort of pediatric patients with IBD.

Methods: We performed whole-exome sequencing analyses of blood samples from an
unselected cohort of 1005 children with IBD, 0–18 y old (median age at diagnosis, 11.96 y) at a single center in Canada and their family members (2305 samples total). Variants believed to cause IBD were validated using Sanger sequencing. Biopsies from patients were analyzed by immunofluorescence and histochemical analyses.

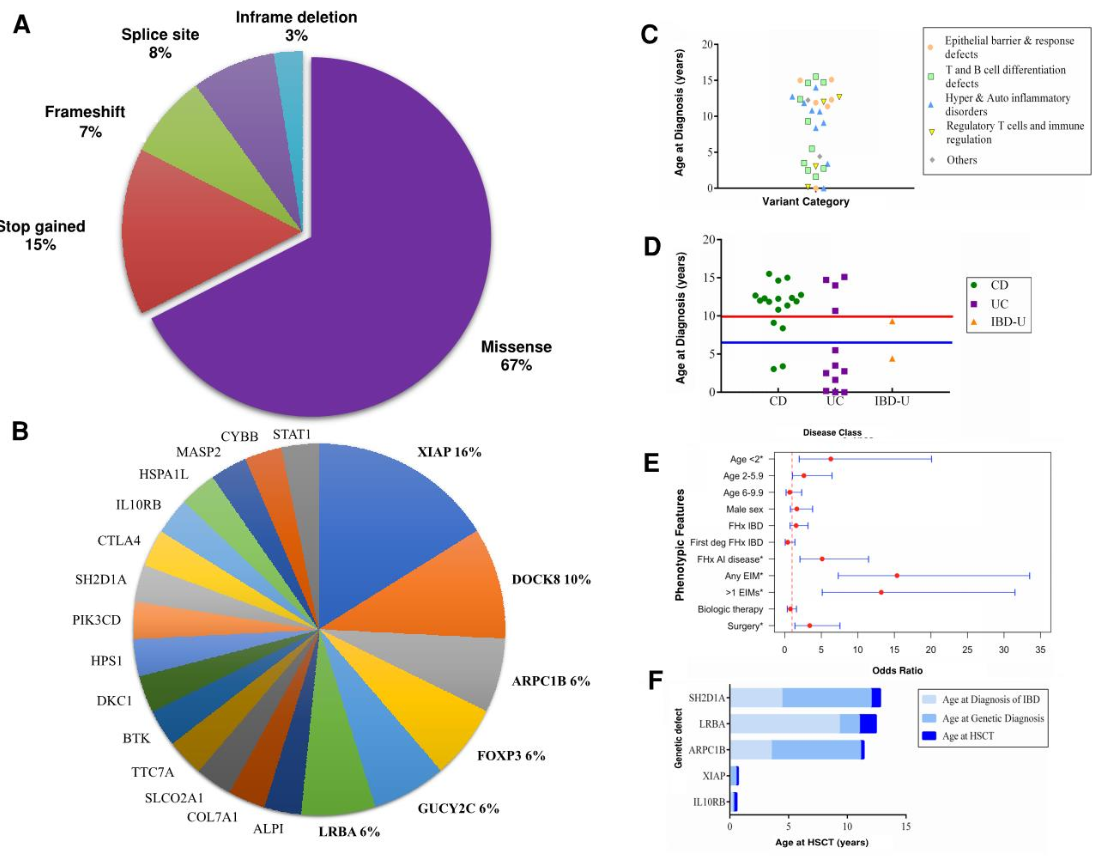
Results: We identified 40 rare variants associated with 21 monogenic genes among 31 of the 1005 children with IBD (including 5 variants in XIAP, 3 in DOCK8, and 2 each in FOXP3, GUCY2C, and LRBA). These variants occurred in 7.8% of children younger than 6 y and 2.3% of children 6–18 y old. Of the 17 patients with monogenic Crohn’s disease, 35% had abdominal pain, 24% had non-bloody loose stool, 18% had vomiting, 18% had weight loss, and 5% had intermittent bloody loose stool. The 14 patients with monogenic ulcerative colitis or IBD unclassified received their diagnosis at a younger age, and their most predominant feature was bloody loose stool (78%). Features associated with monogenic IBD, compared to cases of IBD not associated with a single variant, were age of onset younger than 2 y (odds ratio [OR], 6.30; P=.020), family history of autoimmune disease (OR, 5.12; P=.002), extraintestinal manifestations (OR, 15.36; P<.0001), and surgery (OR, 3.42; P=.042). Seventeen patients had variants in genes that could be corrected with allogeneic hematopoietic stem cell transplantation.

Conclusions: In whole-exome sequencing analyses of more than 1000 children with IBD at a single center, we found that 3% had rare variants in genes previously associated with pediatric IBD. These were associated with different IBD phenotypes, and 1% of the patients had variants that could be potentially corrected with allogeneic hematopoietic stem cell transplantation. Monogenic IBD is rare but should be considered in analysis of all patients with pediatric onset of IBD.
KEY WORDS: HSCT, genetics, risk factor, prevalence


VEO-IBD -Useful “Position” Paper is Really a Review

A recent publication (Full text: NASPGHAN Position Paper on the Evaluation and Management for Patients with Very Early-onset Inflammatory Bowel Disease. JR Kelsen et al. JPGN 2020; 70: 389-403) is more of a review than a true position paper. A related upcoming study (highlighted tomorrow) indicates that ~8% of VEO-IBD patients have underlying monogenetic forms of IBD.

While the article makes numerous useful points, explicit recommendations are not clearly stated.

Key Points:

  • Epidemiology: 6-15% of pediatric IBD population presents at <6 years of age
  • Children with VEO-IBD need careful immunologic evaluation.  Some of the specific disorders that need to be considered include Chronic Granulomatous Disease (can check DHR) and XIAP (can check a flow cytometry-based assay).
  • Besides panendoscopy, the article recommends close collaboration with the pathologist to identify specific features of the numerous VEO-IBD disorders (most listed/described in Table 1)
  • Identification of VEO-IBD disorders with genetic testing (either whole exome or targeted gene panel) helps determine specific medical therapies and/or stem cell transplantation for disorders like CTLA4B deficiency, LRBA defects, IL-10 deficiency, XIAP, STXBP2, and FOXP3 deficiency.
  • Infliximab does not work as well in VEO-IBD patients.  A recent study found only 12% remained on infliximab 3 years after initiation.
  • VEO-IBD were much more likely to need surgery with rates of 50% for those with onset before 1 year and ~30% for those after 1 year of age.  Colectomy should be considered with caution due to the overlapping presentation of Crohn’s disease and ulcerative colitis in this age group.

One topic that was not discussed was the potential role for dietary therapy in this age group.

Related blog posts:

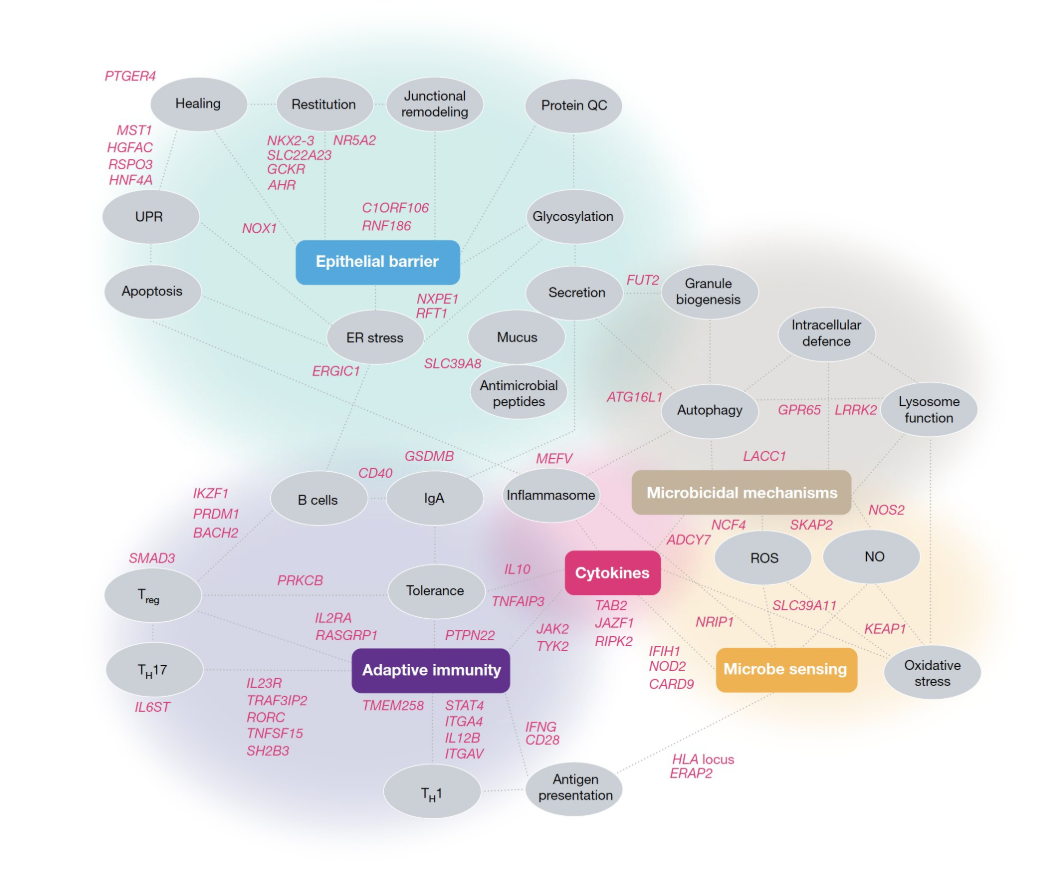
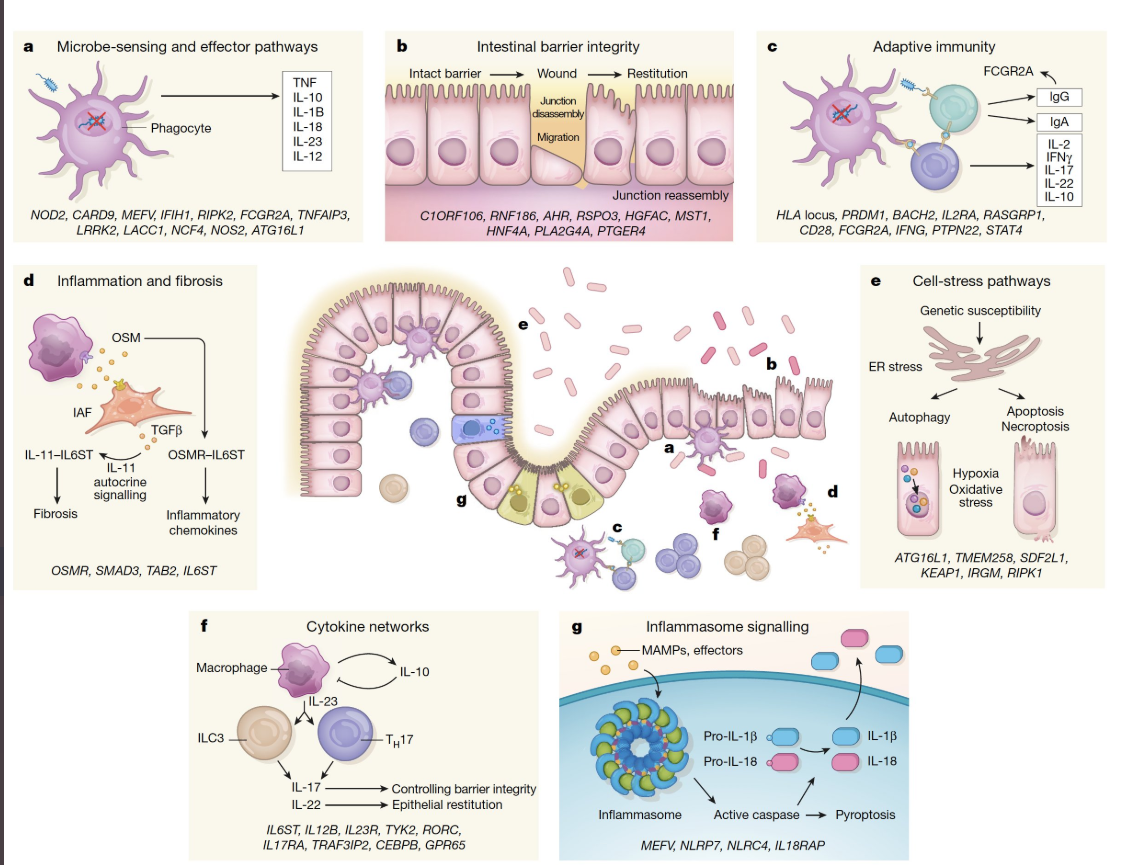
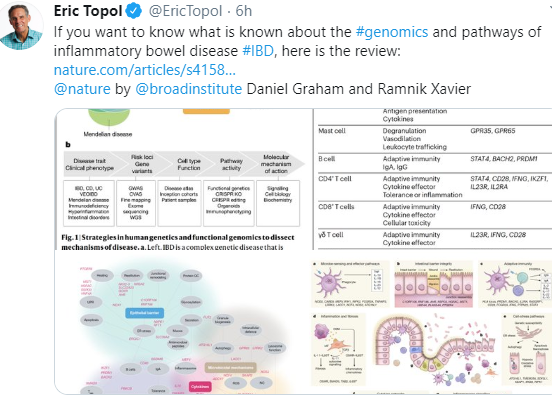
The following related images are from Eric Topol’s twitter feed and share figures from a Nature review.

Seen on Eric Benchimol’s twitter feed

Briefly Noted: Parent Preference: MiniONE over MIC-KEY

In a prospective, randomized cross-over trial (RA Abdelhad et al. JPGN 2020; 70: 386-8) that compared two low profile gastrostomy buttons, caregiver preference favored AMT’s MiniONE over Avanos Medical’s MIC-KEY.  It is worth noting that the authors reported no conflict of interests.

Among 185 patients, 65 with MIC-KEY and 43 with MiniONE completed crossover study; GT buttons were placed laparoscopically.

  • In this group, 69% preferred MiniONE.
  • There were no differences in objective outcomes: adverse effects, emergency room/clinic visits, leavage, granulation tissue or dislodgements.
  • Caregiver preference was based on smaller size of external bolster and its ability to glow in the dark.

Some limitations of this study included a lack of long-term followup and an imbalance in the crossover groups completing the study.  Lack of blinding of the investigators and caregivers could have allowed bias to affect evaluations as well.

UNC Campus Pic (Chapel Hill)