Prospective Study n=365 adult patients with post-operative Crohn’s disease. Findings: At first colonoscopy, 109 [29.9%] had recurrence. Male gender (odds ratio [OR] = 1.95), non-White ethnicity [OR = 2.48], and postoperative smoking [OR = 2.78] were associated with recurrence, while prophylactic anti-TNF reduced the risk [OR = 0.28]. Postoperative anti-TNF prophylaxis had a protective effect on anti-TNF experienced patients but not on anti-TNF naïve patients. Among patients without recurrence at first colonoscopy, Rutgeerts score i1 was associated with subsequent recurrence [OR = 4.43]
A Lecoutour et al JPGN 2024; 78:1116–1125. Efficacy of infliximab after loss of response of/intolerance to adalimumab in pediatric Crohn’s disease: A retrospective multicenter cohort study of the “GETAID pédiatrique”
Key findings: In this retrospective study, 27 of 32 patients (84.4%) were still on IFX at 12 months of the switch. Among them, 13 had discontinued ADA because of a LOR, 12 for insufficient response and 2 due to primary nonresponse. At 1 year, 22 patients were in corticosteroid free clinical remission (68.7%).
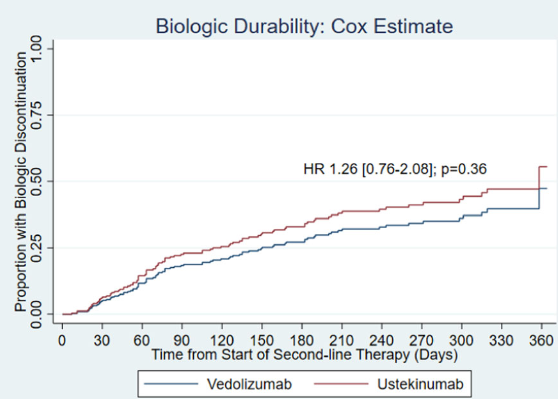
PV Patel et al. JPGN 2024; 78:1126–1134. Real‐world effectiveness of ustekinumab and vedolizumab in TNF‐exposed pediatric patients with ulcerative colitis
Using the ICN registry, this observational study had 262 anti-TNF refractory patients receiving VDZ and 74 patients receiving UST. Key finding: At 6 months, 28.3% of patients on VDZ and 25.8% of those on UST achieved CFCR (p= 0.76)
In medical school, I distinctly remember my anatomy professor discussing how a test’s accuracy was affected by the underlying population tested. He said, ‘Well if you do an RPR test for syphilis among prostitutes and it is abnormal, then it is likely accurate as the test performs better in a population with a higher risk of the condition. Whereas if you run the same test on the faculty, the test would perform with much less accuracy. Well, actually, may be the faculty here are not the best example…’
This discussion comes to mind with the recent publication regarding the No-Biopsy Approach for Celiac disease in adults:
In this systematic review and meta-analysis with 12,103 adult patients from 18 studies, the key findings:
The pooled prevalence of biopsy-proven celiac disease in the included studies was 62%.The proportion of patients with IgA-tTG ≥10×ULN was 32%.
The summary sensitivity of IgA-tTG ≥10×ULN was 51%, and the summary specificity was 100%
However, the positive predictive value of the no-biopsy approach to identify patients with celiac disease was 65%, 88%, 95%, and 99% if celiac disease prevalence was 1%, 4%, 10%, and 40%, respectively in hypothetical cohorts.
The duodenal biopsy, long the cornerstone of a celiac disease diagnosis, has lost some of its luster in recent years. As data emerged that the specificity of tissue transglutaminase (TTG) IgA for duodenal villus atrophy increases in accordance with the degree of antibody elevation in children, in 2012 the European Society for Pediatric Gastroenterology and Nutrition adopted a biopsy-free pathway for the diagnosis of celiac disease in symptomatic children who met stringent criteria, including a ≥10-fold TTG IgA elevation and an elevated endomysial antibody on a separate blood draw.1 With further data supporting the positive predictive value of a highly elevated TTG IgA2 these guidelines were modified in 2020 to now include asymptomatic children.3
..the specificity of an elevated TTG IgA seems to be lower in people with type 1 diabetes.8
Studies employing a serial serology strategy, such as a ≥10-fold TTG IgA elevation that persists over a number of months, might yield specificities that are so high that that they are impervious to decreases in positive predictive values wrought by low underlying prevalences…
Most patients with celiac disease do not mount a sufficiently high TTG IgA to rely exclusively on a serological diagnosis. And the minority who do meet the stringent criteria of a biopsy-free diagnosis might wisely choose to confirm their life-long diagnosis with a biopsy.
My take: Ironically, this study, which showed that a TTG IgA ≥10 x ULN was highly indicative of celiac disease in adult patients with a 100% specificity and a positive predictive value of 98%, makes an argument for ongoing duodenal biopsies in those at lower risk for celiac disease. However, the lower positive predictive values (in some groups) are based on hypothetical cohorts. Shared decision-making is important and relying on a single elevated lab test is particularly problematic.
JM Sharfstein, LO Gostin. NEJM 2024; 390: 1637-1639: The Public Good on the Docket — The Supreme Court’s Evolving Approach to Public Health
This article provides a great summary of how the current Supreme Court has undermined the ability of Congress, federal agencies and states in their efforts to safeguard public health.
Some excerpts:
The preamble to the U.S. Constitution states that a central aim of government in U.S. democracy is to “promote the general Welfare… From the earliest days of the republic, U.S. courts have upheld public health laws and regulations in large part on the basis of their importance for protecting the well-being of communities…
Under the Constitution, states have the primary responsibility and authority to protect the public’s health and safety — often termed “police powers.” In Gibbons v. Ogden (1824), Chief Justice John Marshall observed that states have a long tradition of enacting “inspection laws, quarantine laws, [and] health laws of every description.” In the landmark Slaughter-House Cases (1873), the Court affirmed the states’ power to safeguard health, even when doing so requires restricting liberties. The foundational 20th-century case is Jacobson v. Massachusetts (1905), which upheld the authority of states to mandate smallpox vaccinations…a social compact that recognizes not only the rights of the individual but also the needs of a community “to protect itself against an epidemic of disease which threatens the safety of its members.”
In recent years, however, the Supreme Court’s majority has increasingly blocked states from using public health evidence to protect community safety. During the Covid-19 pandemic, the Court struck down public health orders in California on the basis of religious-liberty concerns…
For most of our country’s history, the Court consistently upheld a wide variety of firearm-safety laws. But in New York State Rifle & Pistol Association v. Bruen (2022), it struck down a New York law requiring applications for concealed carry permits by demanding that laws regulating firearms be “analogous” to laws enacted in the 18th and 19th centuries — even though current high-capacity, powerful firearms bear little resemblance to guns that existed early in U.S. history…
For more than 200 years, courts have accepted that Congress has the power to charge federal agencies with carrying out laws to protect the country’s health and safety and the environment…Yet today’s Supreme Court is significantly constraining the authority of Congress to provide broad direction to agencies. In West Virginia v. Environmental Protection Agency (EPA) (2022), the Court announced a new “major questions doctrine,” holding that Congress must, in advance, spell out specific hazards and the actions that an agency may take to address them…
This term, the Court appears to be poised to…invalidate the long-standing Chevron doctrine, whereby judges give deference to expert agencies in resolving ambiguities in the laws they enforce. Absent Chevron deference, judges will be able to substitute their judgment more readily for that of agency scientists…
In FDA v. Alliance for Hippocratic Medicine, the Court will determine whether the FDA can set science-based policies governing access to mifepristone, a medication used for abortion…The case comes in the shadow of the Court’s decision in Dobbs v. Jackson Women’s Health Organization (2022), in which the majority not only abandoned the right to abortion established in Roe v. Wade after nearly 50 years but also criticized the Roe Court for considering evidence about abortion’s relevance to women’s health.
My take: This court’s rulings have already resulted in profound consequences for public health and individual freedoms. In addition for trying to claim “historical” precedents to establish rulings (when it conveniently the interpretation conveniently aligns with their predetermined views), the court is undermining the role of expertise at every turn.
This commentary starts with a sad anecdote about a physician trying to navigate a difficult end of life decision and transitions to a discussion of public trust in medicine.
A few excerpts:
We are at a crossroads in medicine when it comes to public trust. After a pandemic that twisted science for political gain, it is not surprising that confidence in medicine is eroding. In fact, trust in medical scientists has fallen to its lowest levels since January 2019...
But our medical system relies on trust — in face-to-face meetings as well as public health bulletins. Distrust can lead doctors to burnout and can encourage avoidable negative outcomes for our patients. This is partly what is driving increasing rates of measles among unvaccinated children, failure to follow recommended cancer screening and refusal to take lifesaving preventive medications. There are no easy solutions here. But if we do not find ways to restore and strengthen trust with our patients, more lives will be lost.…
When that skepticism shifts into abject and irreparable disbelief, we see some patients make dangerous decisions…Trust can sometimes be repaired by clearly presenting facts and figures, but it is about more than explaining numbers…
Many of our patients started their medical journeys wanting to believe in their doctors. But then the medical system that they wanted to trust failed them, in small ways and large, from haphazardly rescheduled appointments to real medical error…
For her patient and family facing an end of life decision, “they left without a word, carrying with them his bags of belongings and —I can only hope — faith that we had done the best we could.”
My take: Trying to understand distrust and navigate hostility is one of the most difficult challenges that physicians face. It is difficult to witness patients and families make decisions or omissions in care that lead to worsened outcomes.
37 potential SI gene variants, including the four most common variants seen in genetic sucrase-isomaltase deficiency (GSID). Some variants have isomaltase activity and individuals with these variants can tolerate/digest starch
Children with disorders of gut–brain interaction (DGBI) with a primary complaint of loose stools were found to have a higher prevalence of SI pathologic variants, the vast majority heterozygous, compared with those in a reference consortium database (4.5% vs. 1.3%, respectively).28 Children with DGBI who had primarily abdominal pain did not have a higher prevalence of SI pathologic variants
Disaccharidase testing: Disaccharidase assay on duodenal mucosal tissue homogenates is currently the gold standard for diagnosing overall SID…One in five cases with pan-disaccharidase deficiency of all four or all five evaluated enzymes may be associated with heterozygous SI mutations and sucrase deficiency.39 A ratio of sucrase to lactase at 1.0 or less has been proposed as a guide to CSID, but may miss cases
Genetic testing: Genetic tests for four common mutations up to the entire SI gene are commercially available.9, 39 The test is typically performed using genomic DNA extracted from buccal/cheek swab and blood samples. One specialty laboratory also accepts formalin-fixed paraffin-embedded biopsy tissues and other biopsy samples.
Diet: Good dietary advice is provided in Table 3 (see below).
Sacrosidase Treatment: Dosing of sacrosidase is weight-based, with a recommendation of 1 mL for patients weighing less than 15 kg and 2 mL for patients weighing more than 15 kg. The enzyme should be taken with each meal or snack, mixed into 2–4 ounces of room temperature liquid, and divided with half taken before the meal and half taken midway through
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
In this article, their machine learning algorithm was trained on 187,571 informative patches from rectal hematoxylin and eosin biopsy samples from 292 treatment-naive pediatric patients with UC in a multicenter inception cohort (PROTECT) 2) study.
Key findings (summarized by editorial):
The authors first trained the machine learning models on 250 histomic features at the patch level and achieved an area under the receiver operating characteristic curve (AUROC) of 0.87 (95% confidence interval [CI], 0.73–1.00) and an accuracy of 0.90 (95% CI, 0.80–1.00) at the WSI (whole slide images) level in predicting treatment response.
A subset of 18 histomic features exhibited comparable performance with an AUROC of 0.89 (95% CI, 0.71–0.96) and accuracy of 0.90 (95% CI, 0.80–1.00) to model using the full set of 250 features, indicating the potential for standardized practical application in clinical settings.
The authors confirmed that the set of 18 histomic features demonstrated comparable performance on the real-world independent SickKids cohort7 (University of Toronto) with an AUROC of 0.85 (95% CI, 0.75–0.95) and accuracy of 0.85 (95% CI, 0.75–0.95) at the WSI level.
An important limitation on this study was that the population was 83% white, indicating that it may have less applicability in other cohorts.
My take (borrowed from editorial): Although this study focused solely on the therapeutic outcomes of mesalamine on treatment-naïve patients, it is anticipated thata comparable methodology (based on the fusion of machine learning and digital histopathology) could be applied in subsequent research to elucidate the necessity for colectomy, evaluate responses to biological agents, andoptimize drug selectionfrom the current armamentarium. In other words, this approach utilizing routine biopsy specimens may offer a pathway toward a precision personalized approach to managing pediatric-onset UC (and possibly IBD more broadly).
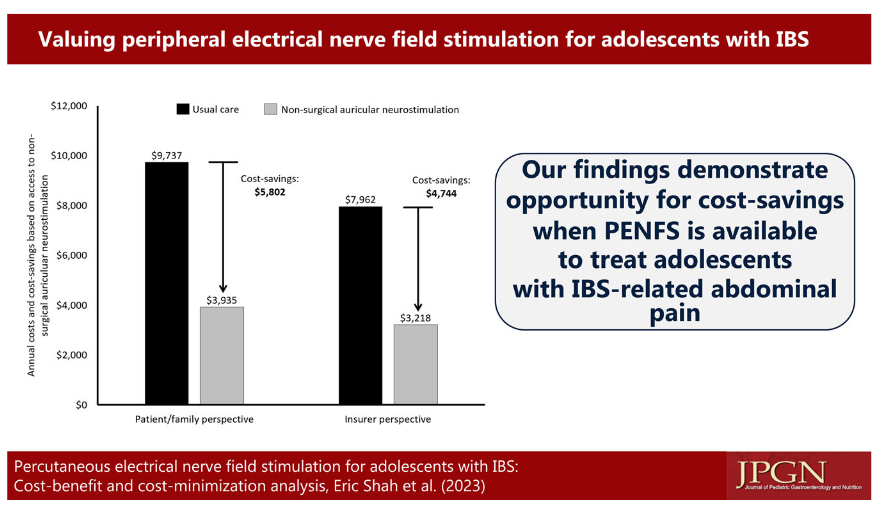
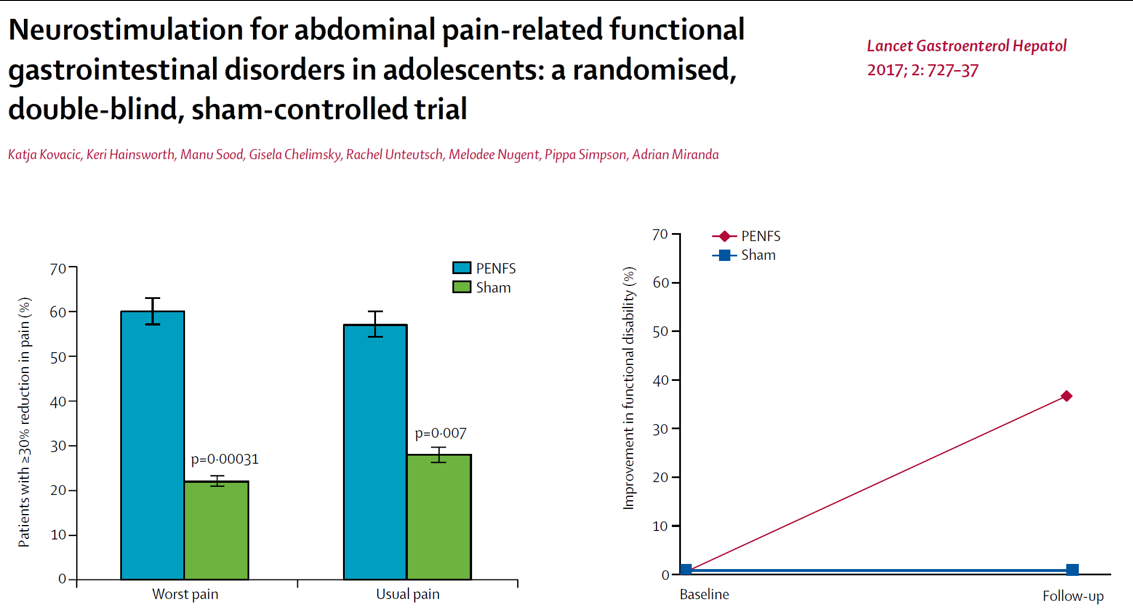
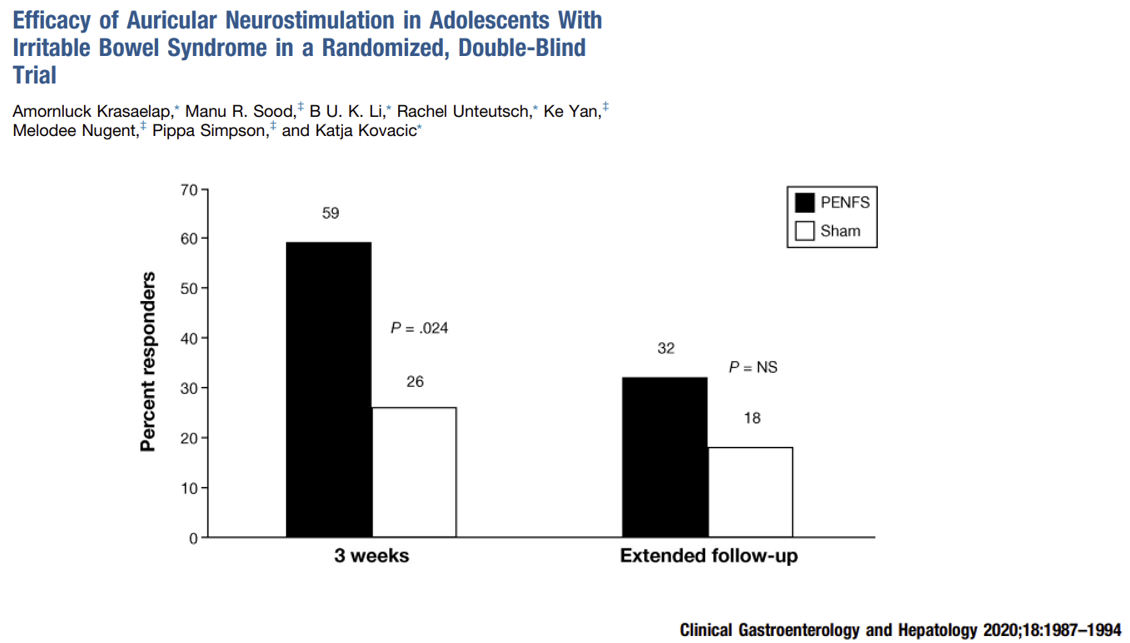
E Shah et al. JPGN 2024; 78: 608–613. Percutaneous electrical nerve field stimulation for adolescents with irritable bowel syndrome: Cost‐benefit and cost‐minimization analysis
Background: “Despite its favorable efficacy and safety profile, access to PENFS and other modalities in IBS can be limited by insurance coverage.”
Methods: The authors performed an economic analysis to estimate cost‐savings for patients’ families and healthcare insurance, and health outcomes, based on abdominal pain improvement with percutaneous electrical nerve field stimulation (PENFS) with IB‐Stim® (Neuraxis). The authors created a a Markov model.
Key findings:
PENFS was associated with 18 added healthy days over 1 year of follow‐up, increased annual parental wages of $5,802 due to fewer missed work days to care for the child, and $4744 in cost‐savings to insurance
Important Limitation: The economic benefits that derive from the clinical improvements used in this analysis are based on a small prospective cohort study of 20 patients with up to 1 year of follow‐up
My take: It appears that auricular stimulation should be positioned earlier in treatment algorithms for adolescents with IBS based on safety, and efficacy, especially if cost is not prohibitive.
Dr. Jose Garza joined our group in 2013 and has been providing excellent care for children throughout the South with suspected motility disorders. Recently, he gave our group a fabulous update on what’s new in motility. My notes below may contain errors in transcription and in omission. Along with my notes, I have included many of his slides.
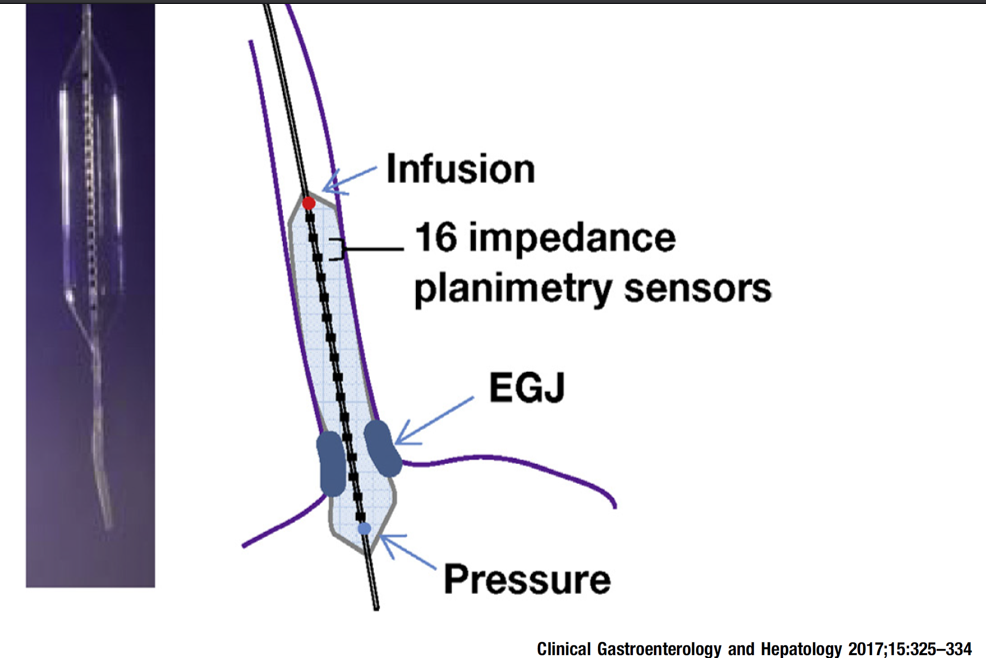
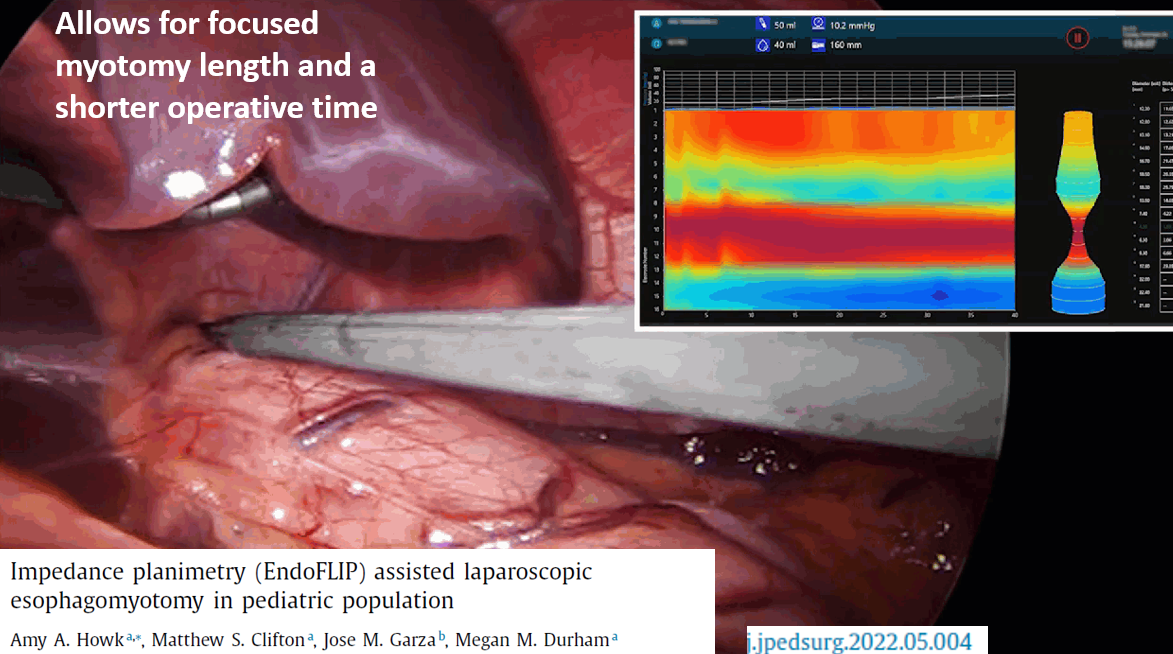
FLIP -How Distensible is the Esophagus
Distensibility index less than 2 mm2/mmHg is considered abnormal.
Normal FLIP (presence of RACs and normal Distensibility Index) can obviate need for high resolution esophageal manometry (HREM)
FLIP during anesthesia can only be done with certain medications: versed, fentanyl and propofol (no gas)
FLIP is useful in evaluating if symptoms after achalasia treatment, during achalasia treatment (dilatation or Heller), if symptoms after fundoplication, and if manometry uncertain
IB-Stim
Good results in improving pain, sleep, nausea and function
Could be a 1st line treatment though cost can be an issue
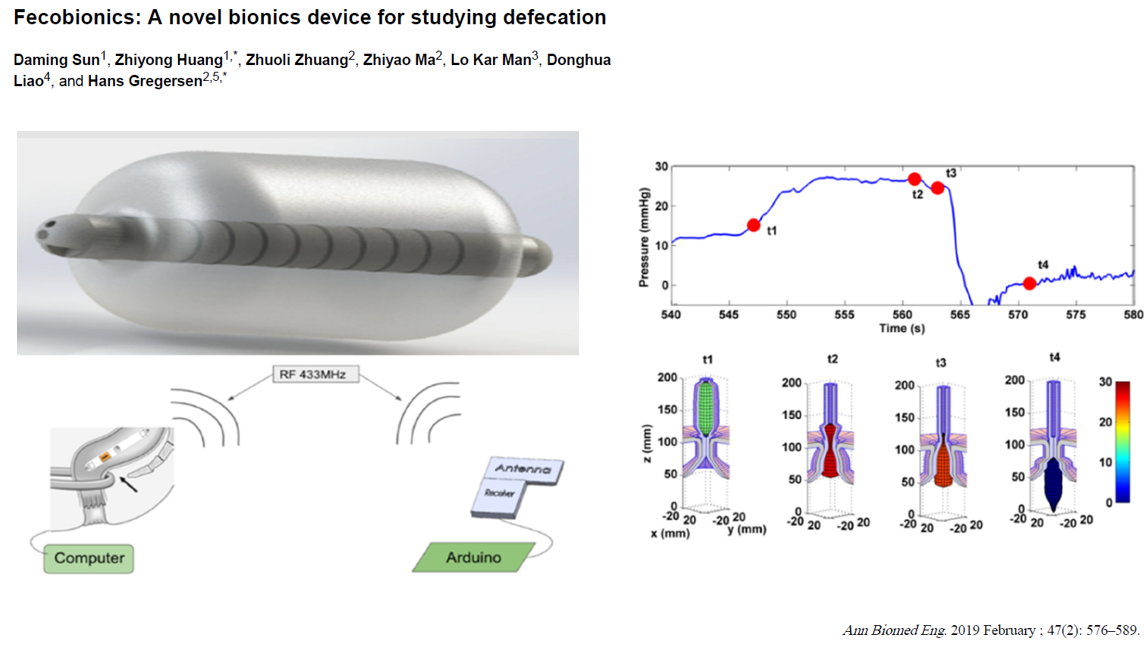
Emerging technology to help provide more data on defecation dysfunction
Medications:
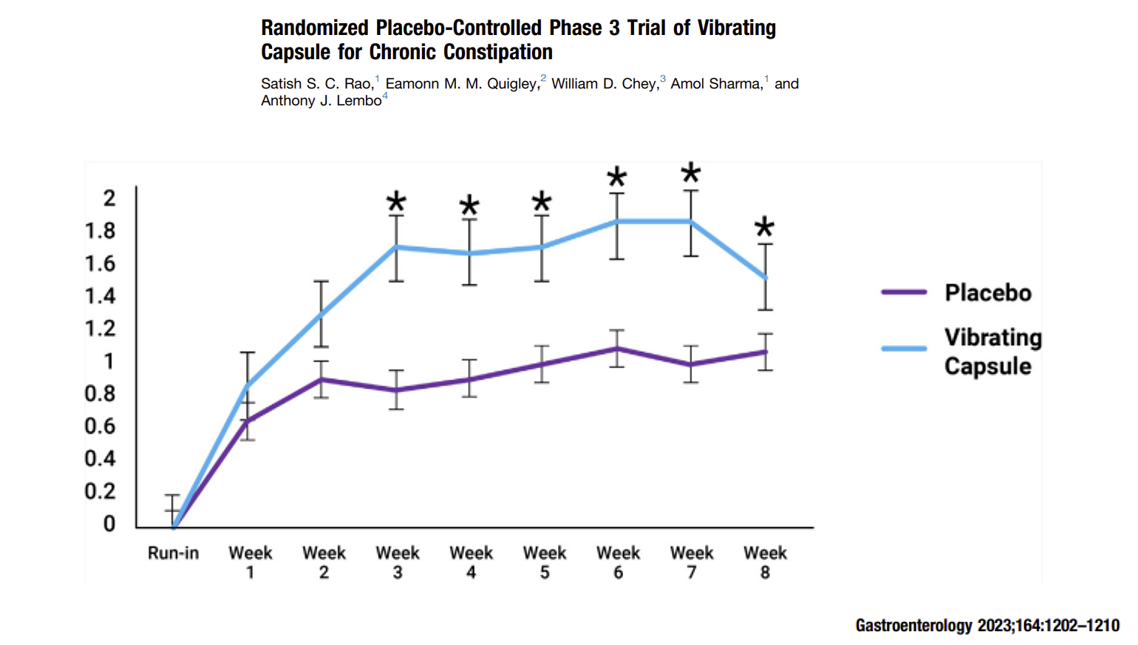
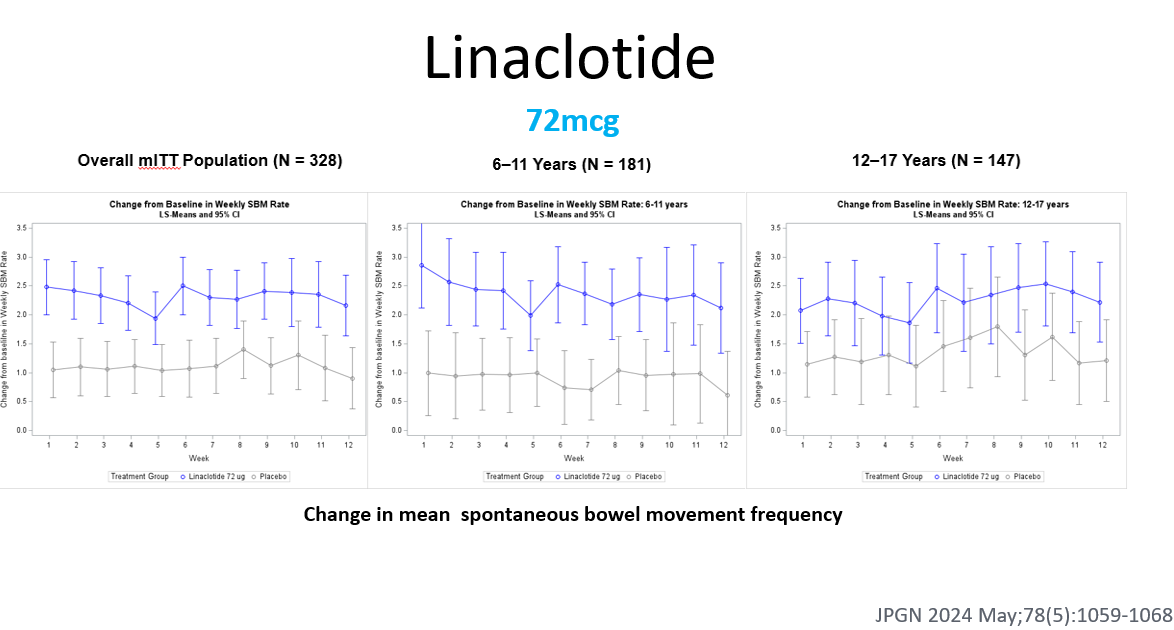
Linaclotide effective in randomized controlled-trial of children (dose 72 mcg). In this study, 6-11 yr olds had better response and it is possible that a higher dosage would be more effective in adolescents. Safe profile -can cause diarrhea. Related post: Linaclotide -Now FDA-Approved for Children
Gabapentin shown to have similar effectiveness as baclofen for chronic cough.
Prucalopride helps with esophageal peristalsis, upper GI symptoms and with constipation. There was a negative pediatric study for treatment of constipation but the study enrolled a lot of younger patients (not likely helpful in overcoming withholding). Insurance coverage often precludes use in younger age group. Related post: Prucalopride -Not Better Than Placebo for Children with Constipation
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
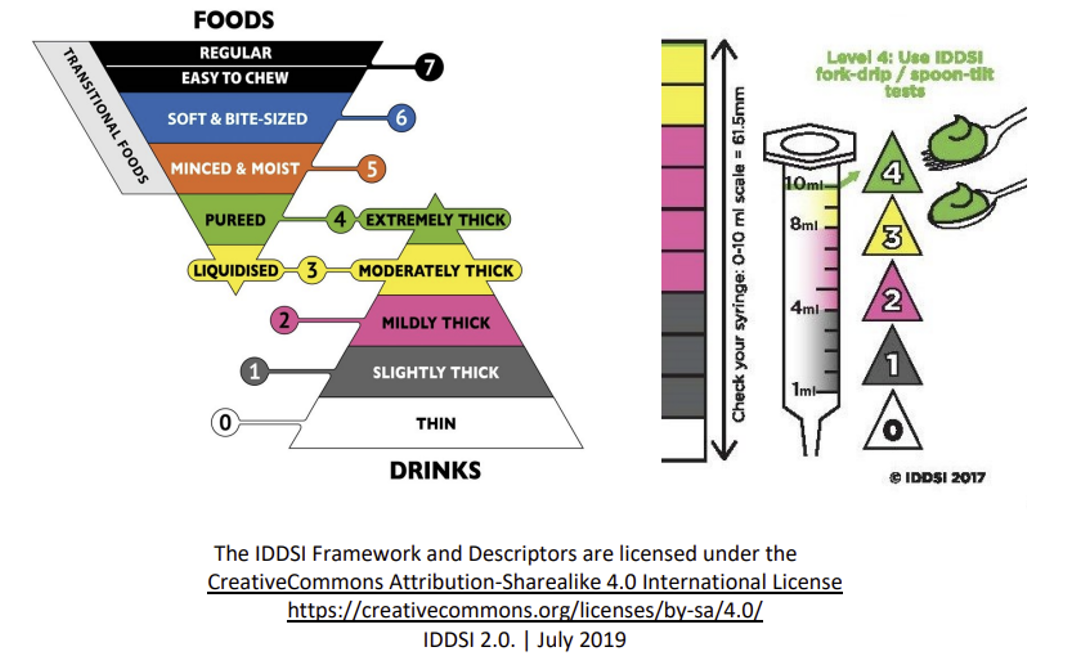
Dr. Jose Garza joined our group in 2013 and has been providing excellent care for children throughout the South with suspected motility disorders. Recently, he gave our group a fabulous update on what’s new in motility. My notes below may contain errors in transcription and in omission. Along with my notes, I have included some of his slides. His talk had 123 slides; true motilists would be appalled that I haven’t included more of the high resolution tracing slides (though there are a few tomorrow).
Colic may be a biorhythm disorder. Infants with colic sleep less and have family history with much higher rates of maternal migraines (related post: Is Infantile Colic a Biorhythm Disorder?)
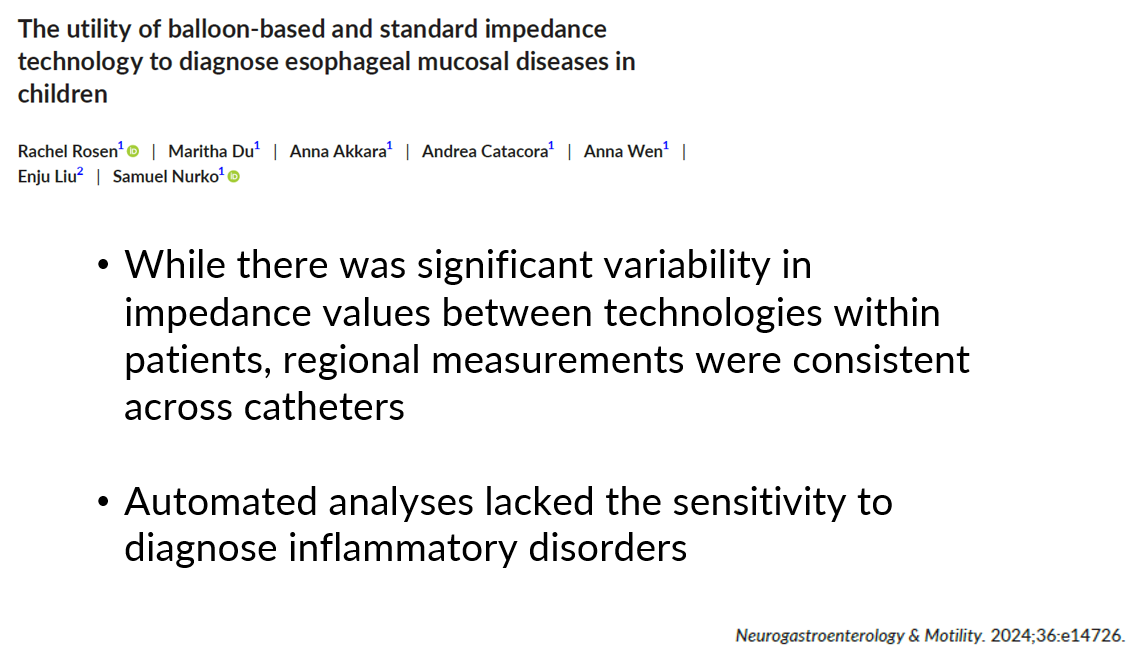
In adults, but not pediatrics, balloon-based impedance technology has been useful in distinguishing GERD, EoE from normal mucosa
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
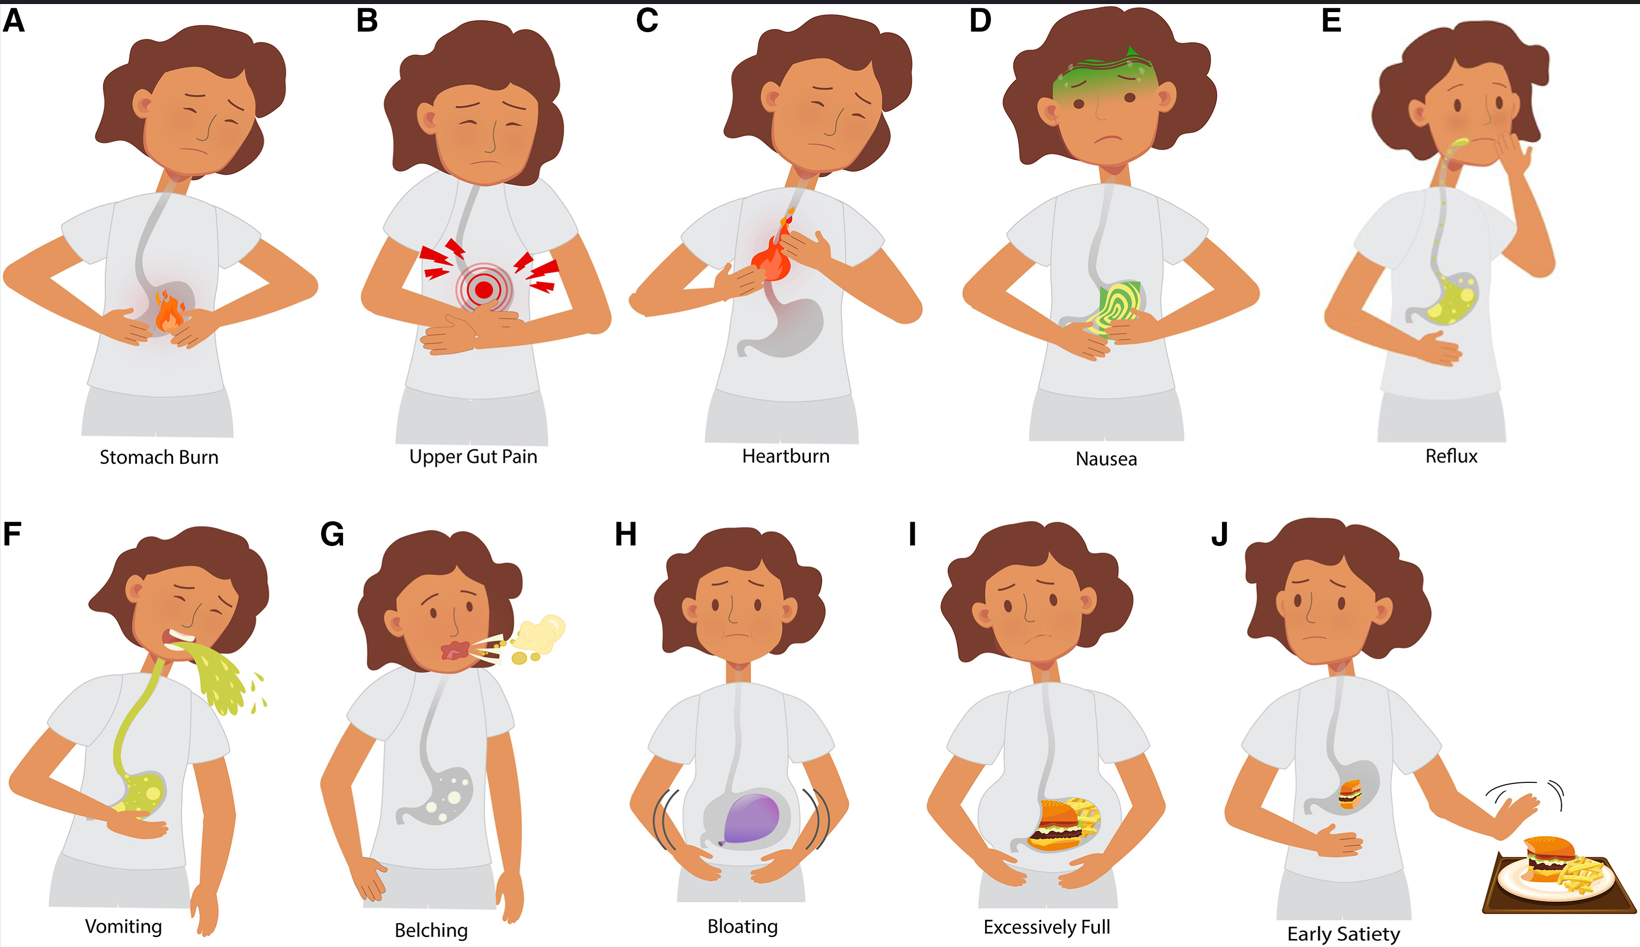
The authors attempted to develop useful pictograms to help enable standardization of symptom reporting in children with gastroduodenal disorders.
Figure 2: Pediatric gastroduodenal symptom pictograms. A, stomach burn; B, upper gut pain; C, heartburn; D, nausea; E, reflux; F, vomiting; G, belching; H, bloating; I, excessively full; and J, early satiety. (The same images were used to create the animated set).
Key findings:
Face and content validity were higher for the pediatric static and animated pictogram sets compared with pre-existing adult pictograms (78% vs 78% vs 61%).
Participants with worse gastric symptoms had superior comprehension of the pediatric pictograms (χ2 [8, N = 118] P < .001)
“Little significant comprehension was gained by having the animated pictograms.”
My take: Some research while worthwhile does not pan out. This is what I was thinking when I read this study. Upper GI symptoms are difficult to convey in pictures; in addition, some patients will have multiple overlapping symptoms. This is why the validity percentages are not higher. I don’t foresee using these pictograms in clinical practice.