Expert Guidance on Current Management of IBD (Part 1)

A recent issue of Clinical Gastroenterology and Hepatology focused solely on the clinical features and management of inflammatory bowel disease. Even for those with expertise in IBD, there is a lot of useful information and concise reviews of what is known.

Here are some of my notes from this issue:

AN Ananthakrishnan et al. Clin Gastroenterol Hepatol 2020; 18: 1252-60. Changing Global Epidemiology of Inflammatory Bowel Diseases: Sustaining Health Care Delivery Into the 21st Century

Reviews risk factors and recommends the following as ways to lower risk of developing IBD for at-risk individuals:

  • Breastfeeding in infancy
  • Do not start smoking
  • Avoid vitamin D deficiency
  • Minimize non-steroidal anti-inflammatory drug use
  • Minimize antibiotic use especially for young children and during pregnancy
  • Encourage moderate physical activity, healthy weight, low stress and regular sleep
  • Diet high in fruit, vegetables, fiber, and fish

Reviews the epidemiology and notes that there has been a evidence of a decline in incidence in IBD in (at least) the Western world; however, because of compounding prevalence, it is expected that the number of individuals with IBD will continue to rise.  In Canada, for example, it is expected that the prevalence will rise from 0.7% in 2018 to 1% by 2030.

In newly industrialized countries, it is expected that rising incidence is going to substantially increase the global disease burden. The authors note the following as areas needed in research and clinical care to meet global IBD care burden:

  • tools for early diagnosis
  • early effective intervention to prevent irreversible bowel damage
  • precision medicine to select the right treatment for the right patient
  • need for less costly and more safe therapies
  • simple tools to monitor disease activity
  • primary disease prevention strategies, especially for those at high risk

CA Siegel, CN Bernstein. Clin Gastroenterol Hepatol 2020; 18: 1261-7. Identifying Patients With Inflammatory Bowel Diseases at High vs Low Risk of Complications

This article’s disease-stratification information overlaps with subsequent articles which detail the positioning of therapies for Crohn’s disease (CD) and ulcerative colitis (UC) respectively.

NH Nguyen, S Singh, WJ Sandborn. Clin Gastroenterol Hepatol 2020; 18: 1267-79. Positioning Therapies in the Management of Crohn’s Disease.

Some of the information summarized in this article:

Table 2 -Comparative Efficacy of Biologics for Moderate to Severe Active Crohn’s Disease (CD):

  • Infliximab: For induction: OR compared to placebo for remission: 5.90 (2.78-12.51); probability of remission 60%. For maintenance in those with clinical response: probability of remission SUCRA ranking: 48%; 0.68
  • Adalimumab: For induction: OR compared to placebo for remission: 3.80 (1.76-8.18); probability of remission 49%. For maintenance in those with clinical response: probability of remission SUCRA ranking: 58%; 0.97
  • Ustekinumab: For induction: OR compared to placebo for remission: 2.75 (1.76-4.32); probability of remission 41%.  For maintenance in those with clinical response: probability of remission SUCRA ranking: 39%; 0.36
  • Vedolizumab: For induction: OR compared to placebo for remission: 2.69 (1.36-5.32); probability of remission 40%.  For maintenance in those with clinical response: probability of remission SUCRA ranking: 42%; 0.52
  • Certolizumab pegol: For induction:  OR compared to placebo for remission: 1.36 (0.89-2.08); probability of remission 25%.  For maintenance in those with clinical response: probability of remission SUCRA ranking: 42%; 0.48

In deciding therapy, the authors specify factors that help classify as high-risk CD Table1):

  • Structural damage: large or deep mucosal lesions, fistula or perianal abscess, prior resections (especially if >40 cm)
  • Inflammatory burden: extensive disease involvement (ileal disease >40 cm or pancolitis), increased C-reactive protein, low albumin
  • Impact on quality of life: presence of stoma, >10 loose stools/week, lack of symptomatic improvement with prior biologics and/or immunomodulators, presence of anorectal symptoms, anemia, daily abdominal pain
  • Emerging predictors: antimicrobial antibody pattern, antimicrobial genetic peptide signature

Though the authors note a lack of adequate head-to-head comparative studies, they make some recommendations for treatment:

  • For severe disease, they suggest first-line therapy for CD would be infliximab or adalimumab in combination therapy regimen (with infliximab favored for higher disease severity)
  • For second-line therapy, they suggest ustekinumab for most patients in combination therapy or 2nd anti-TNF in those with loss or response due to immunogenicity or intolerance
  • For those with higher risk factors for adverse events (or preference) and moderate disease severity, the authors recommend vedolizumab as 1st line and ustekinumab as 2nd line.  For this same group with higher disease severity, they suggest ustekinumab as 1st line treatment.

Other key points:

  • In terms of risk of malignancy, the authors note that in a comprehensive systematic review of 23 RCTs of TNF-alpha antagonists in IBD, there was NO significant increase in the risk of malignancy with TNF-alpha antagonists.
  • In terms of combination therapy, the authors note that their has been an observed benefit which is “at least partly attributed to achieving a higher biologic trough concentration….no differences in efficacy of combination therapy vs infliximab were observed when evaluating patients by quartiles of infliximab trough concentration; however, currently this represents association rather than causation, and it is possible that superior remission rates drove higher trough concentrations, rather than vice versa.”

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.


AGA Practice Guidelines: Probiotics NOT Helpful for Most GI Conditions

Here is a link to the EPUB draft of AGA clinical report (G Su et al. Gastroenterology DOI: https://doi.org/10.1053/j.gastro.2020.05.059): AGA Clinical Practice Guidelines on the Role of Probiotics in the Management of Gastrointestinal Disorders

Here is a link to the pre-draft technical review by GA Preidis et al. Gastroenterology DOI: https://doi.org/10.1053/j.gastro.2020.05.060 AGA Technical Review on the Role of Probiotics in the Management of Gastrointestinal Disorders

  • The report recommends NOT using probiotics outside of clinical trials for irritable bowel syndrome, Clostridium difficile infection treatment, Crohn’s disease, and gastroenteritis.
  • It recommends a specific probiotic for pouchitis and for prevention of necrotizing enterocolitis in preterm infants <37 weeks and 3 probiotics for patients who are receiving antibiotics (to prevent Clostridium difficile infection)

CNN summary: Probiotics don’t do much for most people’s gut health despite the hype, review finds

“While our guideline does highlight a few use cases for probiotics, it more importantly underscores that the public’s assumptions about the benefits of probiotics are not well-founded,” said Dr. Grace L. Su, a professor of medicine and chief of gastroenterology at the University of Michigan, Ann Arbor, in a news statement. She was the chair of the panel that issued the new guidance….

“The industry is largely unregulated and marketing of product is often geared directly at consumers without providing direct and consistent proof of effectiveness,” said the new guidelines. “This has led to widespread use of probiotics with confusing evidence for clinical efficacy,” it said…

“Not all probiotics are created equal. Some probiotic strains and mixtures are very effective for some types of diseases and should not be overlooked due to studies that lump all probiotics together as one”

My take: Probiotics are overhyped and underperform for most conditions. This report suggests that most people should NOT be taking probiotics.

Related blog posts:

Briefly Noted: Bleeding in Noonan Syndrome, Pets Help Children’s Emotional Health

B Briggs et al. J Pediatr 2020; 220: 154-8.  This study confirmed a high rate of bleeding problems in infants with Noonan syndrome.  9/70 (12.8%) had bleeding complications in those without comprehensive preoperative testing and undergoing major or dental surgery. Hematology evaluation is indicated in these children.

H Christian et al. J Pediatr 2020; 220: 200-6. Using data from the Longitudinal Study of Australian Children with data points at ages 5 (n=4242) and at ages 7 (n=4431).  Key finding: Owning pets was associate with improved emotional health for children: odds of abnormal emotional scores on SDQ questionnaire was OR 0.81, peer problems OR 0.71, and prosocial behavior OR 0.70 compared with non-pet owners. Prosocial behavior was most improved for children without any siblings with OR 0.21.

Updated Outcome Data for Necrotizing Enterocolitis

A recent systematic review (IH Jones, NJ Hall. J Pediatr 2020; 220: 86-92) provides contemporary outcomes for infants with necrotizing enterocolitis (NEC). The authors analyzed from 38 articles (from 1375 abstracts); the authors excluded data from developing countries. This review included 21,349 infants with any stage of NEC and 7540 with Bell stage 2a+.

Key findings:

  • Overall mortality was 23.5% in all neonates with confirmed NEC (Bell stage 2a+), 34.5% for infants who underwent surgery
  • Mortality rates were higher for extremely low birthweight infants (<1000 g) at 40.5%; the rate was 50.9% for surgical NEC in this cohort
  • Neurodevelopmental disability was reported in only 4 studies and ranged between 24.8% and 61.1% (n=1209)
  • Intestinal failure was reported with an incidence of 15.2% to 35.0% (n=1370)

A limitation with this study is the lack of agreement on definitions/diagnosis for necrotizing enterocolitis and intestinal failure.

My take: This study shows that NEC still carries a high mortality.

Related blog posts:

Sandy Springs

One More Problem with HIDA Scans

A recent case study (A Adeyemi et al. J Pediatr 2020; 220: 245-8) provides information on 6 infants with a subsequent diagnosis of biliary atresia who had HIDA scans which reported excretion.

Methods: HIDA scans from 1992-2012 were reviewed from CHOP, this included 223 infants up to 4 months of age.

Key findings:

  • While there were six cases with HIDA scans that showed excretion into the bowel, none of these infants had truly normal HIDA scans.
  • 4 of the 6 patients had excretion qualified as slight, mild, or subtle and faint.
  • 5 of the 6 patients did not have the gallbladder visualized on HIDA.

Commentary:

  • HIDA scans are well-known to have a high sensitivity but a low specificity for biliary atresia (even with pretreatment choleretic agents). Liver biopsies have a higher diagnostic accuracy.
  • Since biliary atresia is a progressive disease, some excretion on HIDA does not exclude the diagnosis.  Though, age at HIDA was not a significant variable in this small series.

My takes:

  • Don’t rely too much on any test, including HIDA scans.  Equivocal findings need to be reported as such.
  • Fortunately, MMP-7 has emerged as another quick way with good (not perfect) specificity for biliary atresia.
  • Another related caveat is to look carefully at ultrasounds in this age group.  Often a small or retracted gallbladder is overlooked and could be an important clue to the diagnosis of biliary atresia.

Related blog posts:

Rhododendron Flowers (Spring 2020)

Does Stopping Cannabis Improve Cyclic Vomiting Syndrome?

Cannabis use has been linked to hyperemesis. However, a recent cross-sectional study (T Venkatesan et al. Clin Gastroenterol Hepatol 2020; 18: 1082-90) that stopping cannabis rarely results in improvement in cyclic vomiting syndrome (CVS).

This study enrolled 140 patients who had CVS with a mean age of 37 years, all seen at a specialized clinic; 41% were current cannabis users and were classified as regular users (≥4/wk, n=30) or occasional users (<4/wk, n=26).

Key findings:

  • Only 1 of 56 (2%) reported that cannabis abstinence (for a month) resolved their CVS symptoms and 1 of 56 (2%) noted improvement with cannabis abstinence.
  • 27 of 56 (56%) reported that cannabis abstinence worsened their CVS symptoms; 19 (40%) reported no change with cannabis abstinence
  • Only 1 patient taking cannabis met Rome IV criteria for cannabinoid hyperemesis syndrome (CHS). This patient subsequently resumed cannabis with a higher proportion of CBD (less THC) without recurrence of CVS symptoms.  This provides some support to the idea that THC in cannabis is responsible for CHS.

My take: (borrowed from authors) “If a patient with CVS and chronic regular cannabis use is refractory to standard therapy, we recommend a period of abstinence of at least 6 months or a duration of time that exceeds at least 3 consecutive cycles.”

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition


How to Get Rid of the Placebo Effect in Inflammatory Bowel Disease Trials

A recent study (M Duijvestein et al. Clin Gastroenterol Hepatol 2020; 18: 1121-32, editorial 1030-32) analyzed data from recent randomized, double-blind, placebo-controlled trials for Crohn’s disease (CD).  In these induction trials fro eldelumab, filgotinib, risankizumab, and ustekinumab, the authors found very low rates of placebo response (n=188 in placebo arms).

Key findings:

  • Based on endoscopic assessment of CD activity, response rate to placebo was 16.2%; response indicated >50% reduction in the simple endoscopic score for CD.
  • The rate of remission was 5.2%
  • Even lower rates of response were noted in those with elevated CRP at baseline (OR 0.93) and those with history of anti-TNF therapy (OR 0.31)

Commentary:

  • The key to lowering the placebo response are to use objective biologic markers rather than relying exclusively on clinical symptoms.
  • Central reading of endoscopic endpoints also is thought to minimize placebo effect
  • The editorial notes that the use of placebo in clinical trials “must be justified by the importance of the additional scientific value gained, and placebo should be used in trials only if there is genuine equipoise between the active treatment and placebo.”
  • “Because of ethical questions concerning placebo and the emergence of head-to-head trials, placebo arms may disappear from future IBD trials.”

My take: In reality, very few individuals with CD improve without adequate treatment.  Use of objective criteria is crucial to finding out what really works, both in clinical trials and in clinical practice.

Related blog posts:

Is It Safe for Me to Go to Work?

Just for fun —YouTube (~3 minute video): The Swish Machine: 70 Step Basketball Trickshot (Rube Goldberg Machine)


Full text —MR Larochelle. DOI: 10.1056/NEJMp2013413. NEJM: Is It Safe for Me to Go to Work?

An excerpt:

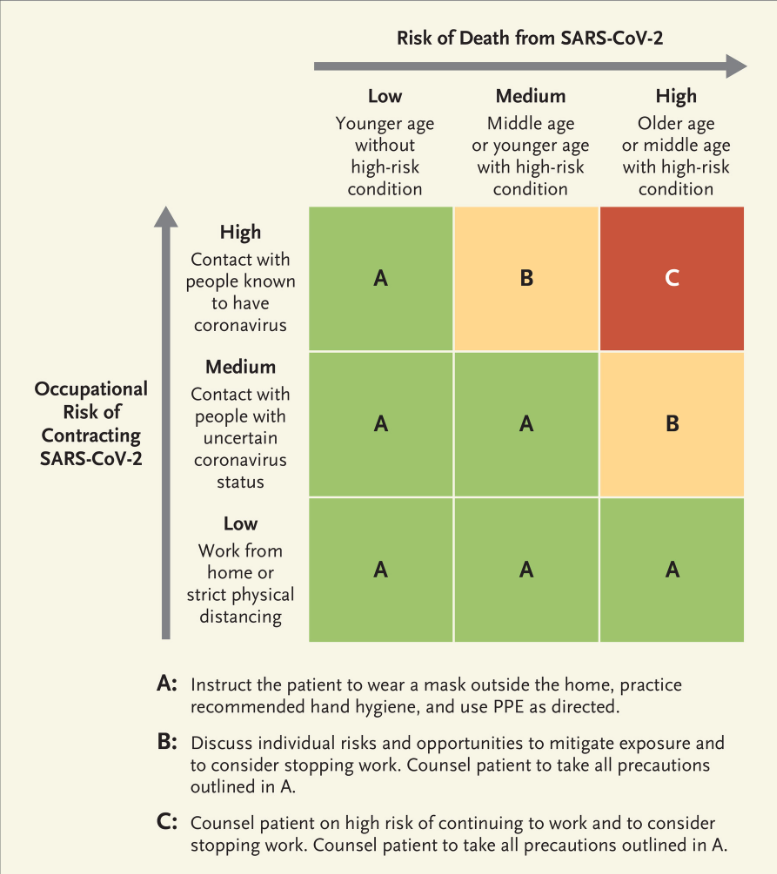
I believe that a strategy to protect at-risk workers needs at least three components: a framework for counseling patients about the risks posed by continuing to work, urgent policy changes to ensure financial protections for people who are kept out of work, and a data-driven plan for safe reentry into the workforce…

The Occupational Safety and Health Administration has published guidance and proposed a scheme for classifying the risk of SARS-CoV-2 infection as high, medium, or low based on potential contact with persons who may or do have the virus (www.osha.gov/Publications/OSHA3990.pdf. opens in new tab). Low-, medium-, and high-risk categories of individual risk of death from Covid-19 are based on age and the presence of high-risk chronic conditions identified by the CDC…

As states move to reopen their economies, millions of nonessential employees will join essential employees in putting themselves at risk for contracting SARS-CoV-2 at work. Physicians should engage patients in individualized risk assessments. Our society has the moral imperative and means to provide vulnerable employees a financial safety net until we can better ensure their workplace safety.

Related blog post: @Atul_Gawande: How to Reopen

Prevalence of Rome IV Functional Bowel Disorders in Adults (US, UK, Canada) & Largest Study to Date on Hydroxychloroquine for COVId-19

OS Palsson et al. Gastoenterol 2020; 158: 1262-73.  The authors note that the switch from Rome III to Rome IV criteria reduces the prevalence of IBS by half, but increases the prevalence of functional constipation and functional diarrhea.

Full text PDF: Prevalence of Rome IV Functional Bowel Disorders Among Adults in the United States, Canada, and the United Kingdom

Abstract

BACKGROUND & AIMS:

Little is known about the population prevalence or demographic distributions of Rome IV functional bowel disorders (FBDs) or their effects on quality of life. We examined these in a multinational survey.

METHODS:

We analyzed data from a population-based [online] survey of adults in the United States, Canada, and United Kingdom (5931 valid responders; 49.2% female; mean age, 47.4 years; range, 18-92 years). The survey included the Rome IV Diagnostic Questionnaire, Rome III irritable bowel syndrome (IBS) and constipation questions, and the SF-8 quality of life questionnaire.

RESULTS:

The prevalence values of census-adjusted Rome IV FBDs were similar among the 3 countries; ranges were: 4.4%-4.8% for IBS, 7.9%-8.6% for functional constipation, 3.6%-5.3% for functional diarrhea, 2.0%-3.9% for functional bloating or distention, 1.1%-1.9% for opioid-induced constipation, 7.5%-10.0% for unspecified FBDs, and 28.6%-31.7% for any Rome IV FBD. FBDs were less common in older individuals, and all except functional diarrhea were more common in women. IBS was only half as prevalent by Rome IV as by Rome III criteria (4.6% vs 9.0% overall), primarily due to higher Rome IV minimum pain frequency. Functional diarrhea and functional constipation were more prevalent by Rome IV than Rome III criteria. Subjects with FBD had significant reductions in quality of life and reported more gastrointestinal doctor consultations than other subjects.

CONCLUSIONS:

More than 1 in 4 adults in the general population meet the Rome IV criteria for FBDs. These disorders affect quality of life and increase use of gastrointestinal health care. The switch from Rome III to Rome IV criteria reduces the prevalence of IBS by half, but increases the prevalence of functional constipation and functional diarrhea.

Related blog posts:


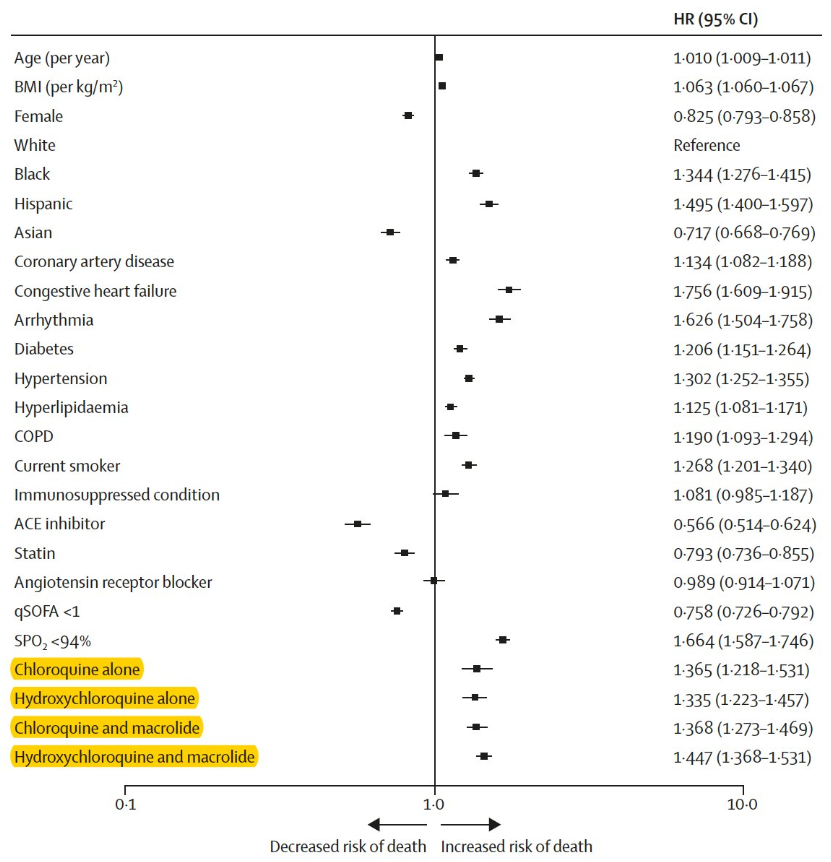
From @EricTopol: Just published @TheLancet The largest study of hydroxychloroquine shows a significant increase in death (~35%) and >2-fold increase of serious heart arrhythmias. ~96,000 patients, ~15,000 on HCQ or CQ from 671 hospitals, 6 continents.


More Jokes: