I recently had the opportunity to hear a terrific lecture by Kathleen Hoff regarding efforts to achieve continence for children, especially those with anorectal malformations. This blog entry has abbreviated/summarized the presentation. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.
Key points (my notes followed by screenshots of some of the slides):
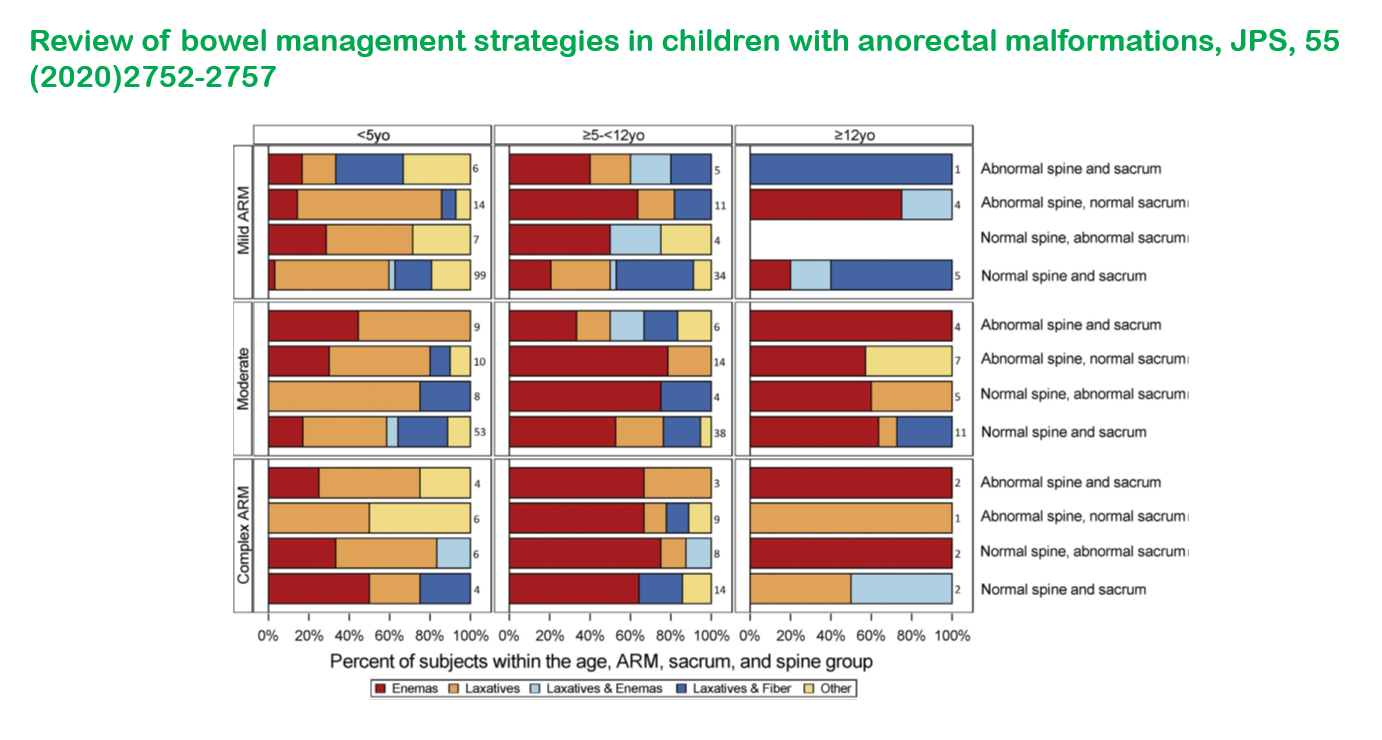
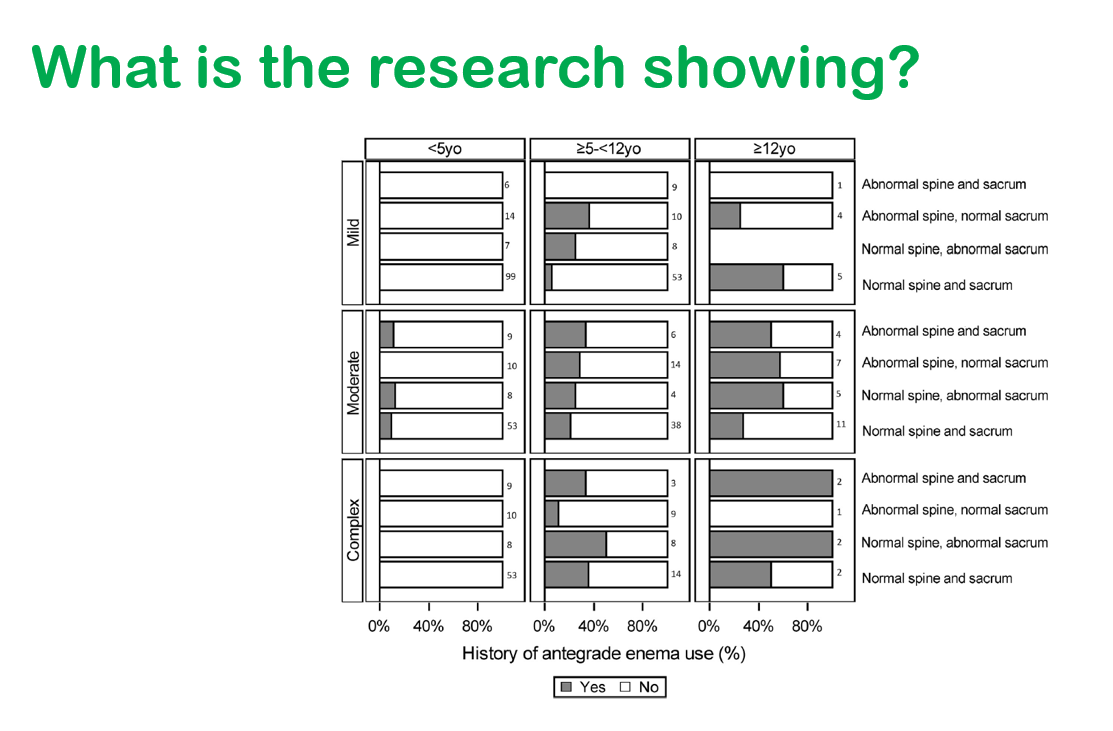
Data from PARC: Red color indicates use of enemas, light brown indicates use of laxativesProducts for enemasData showing increasing use of antegrade enemas in older children and those with moderate and complex malformations
A recent clinical problem-solving case (TW Fredrick et al. NEJM 2021; 385; 549-554. Turning Purple with Pain) is a good review on episodic pain and acute intermittent porphyria (AIP).
The case presentation regarded a 32 yo with episodic severe pain for 10 years (associated with constipation) that required morphine. Episodes occurred every month or two and lasted for several days. Some clues in this case included the development of hyponatremia, purple urine, and an episode in which she was “out of it.” This episode was attributed to opioid use and providers were concerned about opioid-seeking behavior and a conversion disorder.
She had extensive evaluations including imaging, panendoscopy, and labs. Atypical labs included serum tryptase, cortisol, and C1 esterase inhibitor level. Ultimately, her constellation of findings led to a urine porphyrin levels which disclosed elevated porphobilinogen (PBG) and delta-aminolevulinic acid. The diagnosis of AIP was confirmed with genetic testing.
Key points:
AIP results from mutations in HMBS, the gene encoding hydroxymethylbilane synthase which plays an integral role in heme synthesis
AIP is rare, affecting about 5 people per million; age of onset is typically 18-45 years of age
In a case series, 18% of patients with AIP reported nearly constant abdominal pain symptoms, 73% had nausea/vomiting, 60% have constipation, and 55% had anxiety/depression.
Flares of AIP may be triggered by alcohol, infections, low caloric intake, and medications (especially seizure medications and hormonal contraceptives)
The urine can appear red or brown and darkens on exposure to oxygen, light or heat. Purple urine reflects very high urinary PBG levels
My take: This article provides a useful overview. AIP needs to be considered in adolescents with severe abdominal pain that results in hospitalization (especially if episodic).
Factoring in new infections in unvaccinated people, we can conservatively expect more than 15 million cases of long Covid resulting from this pandemic. And though data are still emerging, the average age of patients with long Covid is about 40, which means that the majority are in their prime working years.
Long Covid is not a condition for which there are currently accepted objective diagnostic tests or biomarkers…The health care community, the media, and most people with long Covid have treated this syndrome as an unexpected new phenomenon. But given the long arc and enigmatic history of “new” postinfection syndromes, the emergence of long Covid should not be surprising.
Equally unsurprising has been the medical community’s ambivalence about recognizing long Covid as a legitimate disease or syndrome…If the past is any guide, they will be disbelieved, marginalized, and shunned by many members of the medical community…Some of the disregard can be attributed to the fact that long Covid has disproportionately affected women.
The ultimate success of the research-and-development and clinical management agendas in ameliorating the impending catastrophe is critically dependent on health care providers’ believing and providing supportive care to their patients. These beleaguered patients deserve to be afforded legitimacy, clinical scrutiny, and empathy.
My take: It is unfortunate that many cases of long-haul Covid that will develop could be prevented with vaccination
Causeway Trail in Burlington VT (adjacent to Lake Champlain)
GI Care For Kids is seeking multiple experienced Pediatric Gastroenterologists to join our group of 15 pediatric gastroenterologists and 5 advanced practice providers. Our highly-regarded and busy private practice provides state-of-the art, comprehensive care in our offices and at Children’s Healthcare of Atlanta at Scottish Rite, located across the street from our main office.
Our group includes general pediatric gastroenterologists as well as physicians with a wide range of subspecialization, including inflammatory bowel disease, short bowel syndrome, eosinophilic diseases, motility disorders, feeding disorders, aerodigestive disorders, and celiac disease. Many of our physicians are recognized nationally for their achievements. With our clinical colleagues at Children’s Healthcare of Atlanta, we are rated as the #8 pediatric gastroenterology program in the country by U.S. News.
Important features of our practice include the following:
13 office/satellite locations. All physicians help cover satellite locations.
opportunity for cutting edge clinical research
currently >12 pharmaceutical trials for IBD, EoE, IBS, and Clostridium difficile
fully-accredited office-based pediatric endoscopy center
office infusion centers
multi-lingual physicians
EPIC electronic health record system
We are looking for candidates with prior clinical experience (prefer 2 or more years after fellowship) and excellent communication skills. Additional expertise in advanced endoscopy or pancreatic specialization would be ideal but not a requirement for consideration. All candidates should be board-certified in pediatric gastroenterology.
The Atlanta area is a thriving city (except during a snowstorm) with excellent schools and recreational opportunities. Our office offers competitive salary, benefits, vacation time (20 work days including CME time), and partnership opportunity. Compensation package includes family health insurance, profit sharing, and CME allowance. Hospital coverage averages 1 week/1 weekend per month. Night call is shared and averages about 2 nights per month. Our group is committed to fostering a diverse, equitable, inclusive, and family-friendly environment in which all physicians and staff can excel and achieve work/life balance.
Please send letter of interest and curriculum vitae to: Katrin Herzog. Email address: kherzog@gicareforkids.com
In this retrospective study with 98 patients, the authors examined the sensitivity and specificity of fecal calprotectin (FC) at a cutoff of 150 mcg/g in comparison to findings of ileocolonoscopy and MRE in those with isolated ileal CD (L1, n=14), colonic CD (L2, n=10) and ilecolonic CD (L3, n=74) . Note: the abstract erroneously states the cutoff as 50 mcg/g.
Key findings:
The sensitivity and specificity of FC for L1 CD were 36% and 91%, respectively, compared to 93% and 75% for L2 and 70% and 95% for L3.
An FC of 95 mg/kg was identified as the best cut off for identification of active isolated ileal disease, with a sensitivity of 77% and a specificity of 56%
My take: Though this study had only 14 patients with isolated ileal disease, it is likely that a calprotectin level is less reliable as a biomarker in these patients.
Related article: Jukic A, Bakiri L, Wagner EF, et al Calprotectin: from biomarker to biological functionGut Published Online First: 18 June 2021. doi: 10.1136/gutjnl-2021-324855. Thanks to KT Park for this reference. Open Access- Full text: Calprotectin: from biomarker to biological function
This was a retrospective study with 61 children, median age, 14.4 years; overall, 42 (69%) achieved clinical remission based on weighted PCDAI. The study compared a modified Crohn’s disease exclusion diet (CDED) (modified as 80% in this group had 1–2 weeks of EEN initially) to EEN; PEN accounted for ~50% of calories CDED/PEN group received mainly modulen whereas EEN received a number of standard polymeric isocaloric formulas (eg. pediasure, osmolite, ensure plus). Concomitant medical therapy was used in ~80% of patients (most often azathioprine).
Key finding: Clinical remission was similar in both groups: 27 of 41 (65.9%) received EEN and 15 of 20 (75.0%) received CDED + PEN after 6-8 weeks of treatment. In addition, both groups had improvement in CRP and Hemoglobin.
*Several authors grants/payments from formula manufacturers.
My take: This study while favorable towards a combination of CDED/PEN is limited by small numbers, retrospective design, limited followup and absence of data on mucosal healing.
K Lambert et al. AP&T 2021; https://doi.org/10.1111/apt.16549. Systematic review with meta-analysis: dietary intake in adults with inflammatory bowel disease. Thanks to Ben Gold for this reference.
This meta-analysis included 19 studies of adults with IBD involving dietary intake. Results “show inadequate energy for all subgroups of adults with IBD (mean intake in adults with IBD 1980 ± 130 kcal), as well as fiber (14 ± 4 g), folate (246 ± 33 mg) and calcium (529 ± 114 mg) per day.” Further, “In comparison to the healthy control groups, IBD patients consumed significantly less dietary fiber (SMD −0.59; 95% CI, −0.73 to −0.46).”
The Smart Toilet was able to determine the stool consistency and if the stool had blood 85% and 75% accuracy, respectively, in agreement with a gastroenterologist.
An excerpt:
“At the 2021 virtual Digestive Disease Week, Duke University gastroenterologist Deborah Fisher, MD, and engineering professor Sonia Grego, PhD, showed that toilets enabled with artificial intelligence can analyze stool samples for signs of acute or chronic gastrointestinal disease, such as bleeding, infections or even inflammatory bowel disease.”
My take: I definitely do NOT want my toilet to be too smart. It would not be hard to imagine the toilet berating me for what I ate for dinner the night before.
Citation: Gorelik Y, Freilich S, Gerassy-Vainberg S, et al Antibiotic use differentially affects the risk of anti-drug antibody formation during anti-TNFα therapy in inflammatory bowel disease patients: a report from the epi-IIRNGut Published Online First: 03 August 2021. doi: 10.1136/gutjnl-2021-325185
This study reviewed data from 1946 patients with 363 who developed anti-drug antibodies (ADA). Then, specific pathogen and germ-free C57BL mice were treated with respective antibiotics and challenged with infliximab. ADA were assessed after 14 days.
Key findings:
Cox proportional hazard model demonstrated an increased risk of ADA development in patients who used cephalosporins (HR=1.97, 95% CI 1.58 to 2.44), or penicillins with β-lactamase inhibitors (penicillin-BLI, HR=1.4, 95% CI 1.13 to 1.74), whereas a reduced risk was noted in patients treated with macrolides (HR=0.38, 95% CI 0.16 to 0.86) or fluoroquinolones (HR=0.20, 95% CI 0.12 to 0.35).
In mice exposed to infliximab, significantly increased ADA production was observed in cephalosporin as compared with macrolide pretreated mice. Germ-free mice produced no ADA.
My take: The combination of retrospective data and mouse studies suggests that taking some antibiotics (mainly penicillins and cephalosporins) could increase the risk of immunogenicity to infliximab and increase the risk of anti-drug antibodies.
Background: The authors of this position paper are trying to modulate the treatment recommendations based on the PEPaNIC trial. This “large randomized trial, the Early versus Late Parenteral Nutrition in the Pediatric Intensive Care Unit (PEPaNIC) trial, showed that withholding parenteral nutrition (PN) during the first week of acute illness improved early outcomes as compared to PN initiated during the first 24 hours after admission in children [Fivez T, Kerklaan D, Mesotten D, et al. Early versus late parenteral nutrition in critically ill children. N Engl J Med 2016; 374:1111–1122] (71). Effects were similar in the subgroup of 209 term-born neonates recruited to the trial (72). Despite this finding, many clinicians appear reluctant to limit early nutritional support due to (1) concerns about possible harm by not providing adequate nutrients during the first week of critical illness, particularly in neonates and undernourished children (73), and (2) the belief that exogenous dietary protein provision is essential during critical illness (73).”
Key recommendations:
In preterm infants, available evidence does not support any significant changes to current guidelines, which recommend that critically ill preterm infants should receive nutritional support started at (or reduced to) the minimal amount needed to cover basal metabolic rate and basic macronutrient needs during the early acute phase (26,27,129,149). For many preterm infants, this means that they will need PN.
In critically ill term neonates, initiation of PN within 24 hours is not routinely recommended; however, considering the limitations of the PEPaNIC trial and the observed low risk of long-term harm from early PN in critically ill neonates, the ESPGHAN-CoN does NOT support a change towards withholding parenteral nutritional support for 7 days as standard nutritional care. This position paper suggests considering careful initiation of nutritional support, including micronutrients, just below or at predicted REE after 48–72 hours… when adequate enteral nutrition is not feasible
My take: Particularly in preterm infants, adequate nutrition should not be withheld due to their very limited reserves. In term critical infants, these guidelines offer a logical approach until more studies are available.
This retrospective study with 250 patients determined that clinicians at this large center (Boston Children’s) have a low rate of adherence to the NASPGHAN/ESPGHAN H pylori guidelines (JPGN 2017; 64: 991-1003).
Key findings:
Patient outcomes: 107/186 (58%) had resolution of symptoms after treatment; abdominal pain was the most common presenting symptom (67%)
131 (62%) had documented followup visit and an eradication test
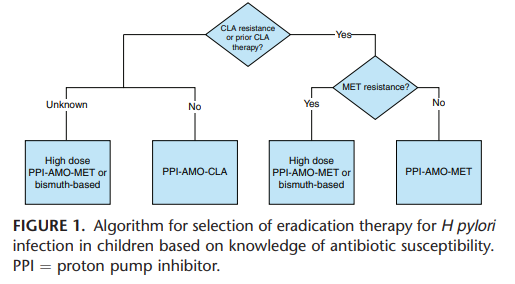
First-line treatment was most commonly amoxicillin, clarithromycin, and PPI (69%) (in those without sensitivity information, amoxicillin, metronidazole, and PPI are recommended in the guidelines)
Biopsy culture was sent in 3% of patients
In their discussion, the authors make a number of points:
Both pediatricians and gastroenterologists “are utilizing a ‘test and treat’ strategy rather than endoscopy-based diagnostic testing.” This along with low followup and low biopsy culture deviate from NASPGHAN guideline.
77 of 256 patients had non-invasive testing prior to referral and in this subset, more than two-thirds of patients received a clarithromycin-based triple therapy before being referred; “this has a high likelihood of failure.”
The authors advocate endoscopy over empiric treatment but acknowledge some reasons why families may want to avoid endoscopy (interestingly the authors do not mention the cost of the procedure). They also note that H pylori culture is not widely available.
Treatment recommendations for initial triple therapy does not align with adult guidelines for quadruple therapy. Even the “rescue” therapies (Table 5), these pediatric guidelines do not recommend quadruple therapy. Yet, there is no indication that H pylori is more susceptible to treatment in children.
Recommendations for susceptibility/antibiotic resistance testing (Table 1, #11) makes no sense if susceptibility testing is not available. Fortunately, PCR-based assays are making this easier recently.
The absence of susceptibility testing and cost would favor empiric treatment over endoscopy as a first-line approach in those who have a reliable non-invasive test indicating infection along with symptoms suggestive of H pylori infection.