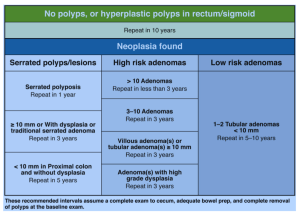
Polyps: Clinical Decision Tool

The best approach to polyps from the U.S. Multi-Society Task Force: Gastroenterology 2014; 146: 305-306.  This paper’s simple chart on page 306 could help reduce many follow-up colonoscopies that are performed at shorter than recommended intervals.

Polyp Guideline

Related blog post:  Consensus guidelines after polypectomy | gutsandgrowth)

“Fill er up”

A few years ago my wife took a bunch of kids to a local frozen yogurt place.  The kids take their bowl and choose their frozen yogurt flavor and toppings; the cost is determined at the end of the line based on how much you took.  One of our guests filled her bowl (at a sizable expense) but only ate a small portion.  My wife told her, ‘if you lived in our household, I would insist that you eat what you took.’  And even though we both hate waste, it seems like human nature to have ‘eyes that are bigger than your stomach.’

An interesting publication (J Pediatr 2014; 164: 323-6) on bowl size and cereal consumption did not make the coveted list of articles reviewed by the editors.  But, I think a lot of pediatric providers and anyone who goes to frozen yogurt establishments would find the information useful.

The article consisted of two studies.  In the first, 69 preschool-age children were randomized to either an 8 oz bowl or a 16 oz bowl and asked to tell researchers how much cereal they wanted for a morning snack; the amount consumed was not measured.  In the second study, 18 school-age children at a summer camp were given an 8 oz bowl on one day and a 16 oz bowl on another day.  Each day, they were asked by the cafeteria server how much cereal and milk they wanted for breakfast.  Hidden scales measured how much was served, consumed, and discarded.

Who thinks they can guess the results?

  • In study 1, children with the larger bowl requested 87% more.
  • In study 2, the older children also consumed more (52%) when given a larger bowl; in addition, they wasted 26% more.

The article notes that some studies (eg. J Consumer Res 2012; 39: 215-28) but not all (Appetite 2007; 49: 652-60) have indicated that “when adults serve themselves, they select an amount of food proportional to the size of the plate;” some have suggested this is due to a visual illusion effect —Delboeuf illusion – Wikipedia, the free encyclopedia.

Screen Shot 2014-02-07 at 4.23.54 PM


Take-home message: If kids (and probably adults) have a bigger bowl, they will want to “fill er up.”  This will certainly lead to more waste but it may increase their waists too.

Clostridium difficile: Colonization vs. Symptomatic Infection

A recent study provides another way to distinguish individuals colonized with Clostridium difficile from those with symptomatic infection (J Pediatr 2013; 163: 1697-704).

Methods: This study comprised two designs. “The first is a case-control study comparing children with a positive C difficile test (cases), children with diarrhea but no C difficile (symptomatic controls), and asymptomatic controls, some of whom were colonized with C difficile.  The second is a prospective-cohort study where we followed our cases for the duration of their illness.”

Results: Fecal cytokines (CXCL-5 and IL-8 mRNA) were elevated in samples from symptomatic children, whether cases or controls.

Bottomline: Inflammatory cytokines can help distinguish C difficile colonization from disease.  Of course, this may have limited utility in patients with underlying inflammatory bowel disease.

Recent posts regarding C difficile:

Teaching an Old Drug New Tricks

A couple recent articles focused on the new uses of methotrexate (MTX) and how to handle potential hepatotoxicity:

  1. J Pediatr 2014; 164: 231-36
  2. Inflamm Bowel Dis 2014; 20: 47-59

In the first medical review article, the authors note the efficacy of MTX for the following:

  • Juvenile idiopathic arthritis
  • Uveitis
  • Psoriasis
  • Crohn disease
  • Juvenile dermatomyositis
  • Localized scleroderma
  • Vasculitis

This review article discusses mechanism of action which is poorly understood along with pharmacogenomics and practical issues in usage.  The latter includes the need for supplemental folic acid.  Other points:

  • “The long-term safety of MTX is remarkable”
  • “The issue of nausea and vomiting…can be especially disturbing.”  They note that one study demonstrated that ondansetron 1 hour prior to MTX from the first injection prevented nausea, which was often difficult to treat once developed.
  • “Liver enzyme abnormalities occur frequently (up to 30% of patients) but are usually of minimal clinical significance.”  Best to draw blood tests 1-2 days before MTX dosing.
  • “In children, unlike adults, MTX-related pulmonary adverse events are very rare.”
  • “In recent years it was shown that live vaccine boosters are effective and safe during MTX use (caution may be needed if MTX is used with other immunosuppression medications)” Ref: JAMA 2013; 309: 2449–56.
  • “Use during pregnancy or within 3 months of planning pregnancy is contraindicated”

The second article was a systemic review which identified 12 high-quality studies which focused on MTX hepatotoxicity in children.  Key findings:

  • 57 of 457 developed some degree of abnormal liver biochemistries.
  • Due to hepatotoxicity, dose reductions were undertaken in 6.4% and 4.5% discontinued MTX.

The authors note that studies of MTX in adults with IBD have not demonstrated cumulative liver toxicity from MTX.  In addition, many of the patients with hepatotoxicity may have had  other reasons for abnormal liver biochemistries including other medications (eg. glucocorticoids).  “Confirmation of MTX hepatotoxicity with a liver biopsy is seldom performed in children;” as a consequence, the exact rate of MTX hepatotoxicity is unknown.

The authors propose that liver biochemistry monitoring occur at baseline, biweekly x 2, then every 2-3 months.  Also, the authors recommend:

  • If ALT < 2 times upper limit of normal (ULN), check liver biochemistries every 2 weeks
  • If persistent abnormalities, the authors recommend an ultrasound
  • If ALT ≥ 2 times ULN, repeat testing should be obtained and consider consultation with a hepatologist

Bottomline: Methotrexate is an important medication for Crohn disease –there are not very many available.  If there are persistent liver enzyme elevations, dose reduction of MTX (or cessation) may be necessary.  As a practical matter, it is advisable to obtain blood draws 1-2 days prior to MTX rather than afterwards. Nausea can be minimized with ondansetron and weekend dosing.

Related blog posts:

“Can you identify the six saltiest foods in American diets?”

From the American Heart Association Twitter Feed: http://bit.ly/SVnguk 

  1. Breads and rolls. We all know breads add carbohydrates and calories, but salt, too? It may not seem like it because a lot of bread doesn’t even taste salty, but one piece can have as much as 230 milligrams of sodium. That’s 15 percent of the recommended amount from only one slice, and it adds up quickly. Have a sandwich and muffin in one day? The bread alone could put you at about 1,000 milligrams of salt – or two-thirds of the American Heart Association’s recommended daily sodium limit of 1,500 milligrams.  Be sure to check the nutrition label as different brands of the same foods may have differing sodium levels.
     
  2. Cold cuts and cured meats. Even foods that would otherwise be considered healthy may have high levels of sodium. Deli or pre-packaged turkey can contain as much as 1,050 milligrams of sodium.  They have so much because most cooked meats would spoil in only a few days without the added sodium solution. Look for lower sodium varieties.
     
  3. Pizza. OK, everybody knows pizza’s not exactly a health food. But you’re probably thinking the big concerns are cholesterol,fat and calories. But pizza’s plenty salty, too. One slice can contain up to 760 milligrams of sodium. It doesn’t take a whole lot of math to realize two or three slices alone can send you way over the daily sodium recommendation. You may want to have fewer slices of pizza topped with vegetables and less cheese.
     
  4. Poultry. Surely chicken can’t be bad for you, right? Well, it depends on how the chicken is prepared. Reasonable portions of lean, skinless grilled chicken are great. But when you start serving up the chicken nuggets or poultry injected with added sodium solutions/marinades, the sodium starts adding up. Just 3 ounces of frozen and breaded nuggets can add nearly 600 milligrams of sodium. (And most kids probably aren’t stopping at 3 ounces.)  Check labels to be sure you are selecting the lower sodium version and that there are no added sodium solutions.
     
  5. Soup. This is another one of those foods that seems perfectly healthy. It can’t be bad if Mom gave it to you for the sniffles, right? But when you take a look at the nutrition label for some products, though, it’s easy to see how too much soup can quickly turn into a sodium overload. One cup of canned chicken noodle soup can have up to 940 milligrams of sodium.  Look for lower sodium options that taste just as great!
     
  6. Sandwiches. This covers everything from grilled cheese to hamburgers. We already know that breads and cured meats are heavy on the sodium. Add them together, and you can pretty easily surpass 1,500 milligrams of sodium in one sitting.   Top sandwiches with plenty of vegetables, such as lettuce, tomato and cucumbers.

Nice graphic: The-Salty-Six-Infographic_UCM_446591_SubHomePage.jsp

Related blog link:

Will salt intake make you fat? | gutsandgrowth

What and When for ERCP with Gallstone Pancreatitis

A recent case vignette highlights several key points regarding use and timing of ERCP (endoscopic retrograde cholangiopancreatography) for gallstone pancreatitis (NEJM 2014; 370: 150-7). Figure 1 provides a nice illustration of ERCP.

Indications:  Suspected bile-duct stones as the cause of pancreatitis AND one of the following:

  • cholangitis (fever, jaundice, sepsis)
  • persistent biliary obstruction (conjugated bilirubine level >5 mg/dL)
  • clinical deterioration (worsening pain, increasing white cell count, worsening vital signs)
  • stone evident in the common bile duct on imaging

AGA position paper (2007):

  • Urgent ERCP (within 24 hours of admission) was recommended in those with cholangitis
  • Early ERCP (within 72 hours of admission) was recommended if suspicion of persistent bile-duct stones remained high

Patient information/animated videos for pancreatic diseases from the National Pancreas Foundation: http://ow.ly/sF9vb 

Related post:

Indomethacin to prevent post-ERCP pancreatitis | gutsandgrowth

Why Doctors Don’t Want Unvaccinated Children in Their Practice

This is a good read by Russell Sanders from The Daily Beast. Here’s the link along with an excerpt:

http://thebea.st/1lpV5Wl  (link from Atul Gawande’s twitter feed)

No contemporary phenomenon confounds and confuses me more than seemingly sensible people turning down one of the most unambiguously helpful interventions in the history of modern medicine.

There are few questions I can think of that have been asked and answered more thoroughly than the one about the safety and effectiveness of vaccines.

The measles-mumps-rubella vaccine does not cause autism.

The HPV vaccine is safe.

There is no threat to public health from thimerosal.

I often wonder why a parent who believes vaccines are harmful would want to bring their children to a medical doctor at all…

If vaccines caused the harms Jenny McCarthy and her ilk claim they do, then my persistence in giving them must say something horrifying about me. Why would you then want to bring your children to me when you’re worried about their illnesses? As a parent myself, I wouldn’t trust my children’s care to someone I secretly thought was a fool or a monster.

It’s not merely that I don’t want to have to worry that the two-week-old infant in my waiting room is getting exposed to a potentially-fatal case of pertussis if these parents bring their children in with a bad cough. It’s not just that I don’t want their kid to be the first case of epiglottitis I’ve ever seen in my career. Those are reasons enough, to be sure. But they’re not all.

What breaks the deal is that I would never truly believe that these parents trust me. Giving kids vaccines is the absolute, unambiguous standard of care, as easy an answer as I will ever be able to offer.

If they don’t trust me about that, how can I hope they would if the questions ever got harder?

Related blog entries:

Unrelated link: Medical app (from Kipp Ellsworth twitter feed): http://goo.gl/pV4vJC :BabyGrow App Enables Parents to Track Children’s CDC/WHO Growth Curves.


Superiority of Anti-TNF Therapy in Children

This study’s conclusion comes as no surprise:

“In children newly diagnosed with comparably severe CD, early monotherapy with anti-TNFα produced better overall clinical and growth outcomes at 1 year than early monotherapy with an immunomodulator. Further data will be required to best identify children most likely to benefit from early treatment with anti-TNFα therapy.”

Here’s the reference:

Gastroenterology Volume 146, Issue 2 , Pages 383-391, February 2014

Here’s a link to the full text article:  Increased Effectiveness of Early Therapy with Anti-Tumor Necrosis Factor-α Versus an Immunomodulator in Children with Crohn’s Disease

Methods: “From 2008 through 2012 at 28 pediatric gastroenterology centers in North America. Patients were managed by physician dictate. From 552 children (median age, 11.8 y; 61% male; 63% with pediatric CD activity index scores >30; and median C-reactive protein level 5.6-fold the upper limit of normal), we used propensity score methodology to identify 68 triads of patients matched for baseline characteristics who were treated with early anti-TNFα therapy, early immunomodulator, or no early immunotherapy.”

Another reference/link from same issue:

Accuracy of Magnetic Resonance Enterography in Assessing Response to Therapy and Mucosal Healing in Patients with Crohn’s Disease

Does Sun Exposure Lower the Risk of Crohn Disease?

An intriguing recent study suggests that individuals who spend more time outside are less likely to develop Crohn disease (CD) (Inflamm Bowel Dis 2014; 20: 75-81).

In this prospective cohort study from France, 123 cases of inflammatory bowel disease (45 CD, 71 ulcerative colitis, and 7 indeterminant colitis)  developed among the 91,870 women in the study.  The study period had a mean followup of 13.1 years and followed women between 40 and 65 years. The authors estimated residential sun exposure by utilizing a database (derived from satellite collection) containing the mean daily ultraviolet radiation dose for each French county.

Key findings:

  • Higher levels of sun exposure were associated with a decreased risk of Crohn disease with a Hazard Ratio (HR) of 0.49.
  • Sun exposure did not affect the likelihood of developing UC (HR 1.21).
  • In women with information about dietary vitamin D intake, higher sun exposure had a HR of 0.29 for developing CD.  That being said, the authors note a low dietary vitamin D intake in their population.

Despite the large cohort, this study has a number of limitations. The absolute number of IBD patients can lead to a Type 1 error (false-positive conclusion).  In addition, the age of the study population and the lack of data regarding individual sun exposure limit the conclusions as well.  Besides these factors, there may be confounders such as changes in diet and soil exposure which are not accounted for.

At the same time, there have been other studies which have shown a latitude effect.  As with this study, those living in sunny areas had a lower incidence of CD.

Bottomline: This study suggests that additional sun exposure is associated with a lower risk of developing Crohn disease.  Whether this lower risk is directly through better vitamin D levels or simply an epiphenomenon is unclear.

Other recent unrelated studies:

Gut 2013; 62: 1122-30.  A randomized phase 1 study of etrolizumab (rhuMAb β-7) in moderate to severe ulcerative colitis.  Etrolizumab is an adhesion cell molecular blocker.

Inflamm Bowel Dis 2014; 20: 21-35.  Meta-analysis of 23 randomized controlled trials of probiotics for UC, Pouchitis, and CD.  Probiotics, in particular VSL#3, increased UC remission rates and helped maintain remission in patients with pouchitis.

Inflamm Bowel Dis 2014; 20: 213-27. Review article of cutaneous manifestations of inflammatory bowel disease.  Good pictures of multiple problems including metastatic Crohn disease, erythema nodosum, pyoderma gangrenosum, Sweet’s syndrome, aseptic abscess syndrome, and epidermolysis bullosa acquisita.

Inflamm Bowel Dis 2013; 19: 1753-63.  Review on hair loss associated with inflammatory bowel disease. Remember telogen effluvium?

Related posts:

For those who read from the top to the very bottom, here’s a tangential question: Do you know what a “sun dog” is?   Sun dog – Wikipedia, the free encyclopedia

What to Make of Dr. Oz and his Detox? Not much

Although my exposure to Dr. Oz has been limited, he is not one of my favorite TV doctors. He often offers opinions in areas where he clearly is not an expert.  By presenting himself as a doctor who is knowledgeable in so many areas, he has the potential of undermining the credibility of physicians more broadly.  A recent report provides some welcome pushback and at the same time indicates that “detox” treatments are unlikely to be helpful.

Here’s the link: Detox treatments by DrOz and others lack evidence, benefit  – CBC

An excerpt:

Despite bold promises that the treatments would purify, detoxify and boost energy and optimize organ function, the cleanses lacked any scientific evidence of efficacy, or clear idea of what toxins they would actually diminish…

“In looking at the medical literature on these things, there has never been a properly conducted scientific investigation of any of these treatments that I’ve been able to find,” Dr. George Dresser, a toxicologist, pharmacologist and an internal medicine specialist at London Health Sciences Centre, told Marketplace co-host Tom Harrington. “It’s an intensely popular topic. And it’s popular because people are interested in a quick fix to health ”

A group of sorority sisters from Western University volunteered to help Marketplace test the cleanse. Half of the group participated in the Dr. Oz cleanse, which required that the students observe a strict diet and refrain from alcohol and caffeine, and not eat any food after 7 p.m. They also drank detoxifying teas and took soothing baths as prescribed by the diet, while the other students ate and drank normally.

To test the efficacy of the cleanse, all students had their liver and kidney functions tested both before and after the 48-hour period. At the end of the 48-hour period, however, Dr. Dresser was unable to detect any physiological benefit at all, or even tell which students had participated in the cleanse.

Despite a CV that boasts degrees from Harvard and the University of Pennsylvania medical school, Dr. Oz has been the target of growing criticism from fellow medical and science professionals for his promotion of products and methods that lack evidence.

Bottomline: “Given his education and influence,” wrote Erin May on the Harvard University science research blog Policylab, “there’s no excuse for the unsubstantiated claims and sensational language that is so pervasive on his show.”

Perhaps Dr. Oz can garner additional publicity by placing his detox on the following website:  Quackwatch (He’s already frequently cited on this website.)