#NASPGHAN19 Annual Meeting -Plenary Session

Here are some notes and a few slides from NASPGHAN’s plenary session.  There could be errors of transcription in my notes.

Benjamin Gold, NASPGHAN president and part of our GI group, GI Care For Kids, welcomed everyone to the meeting.

Link to NASPGHAN_Annual_Meeting_Program 2019

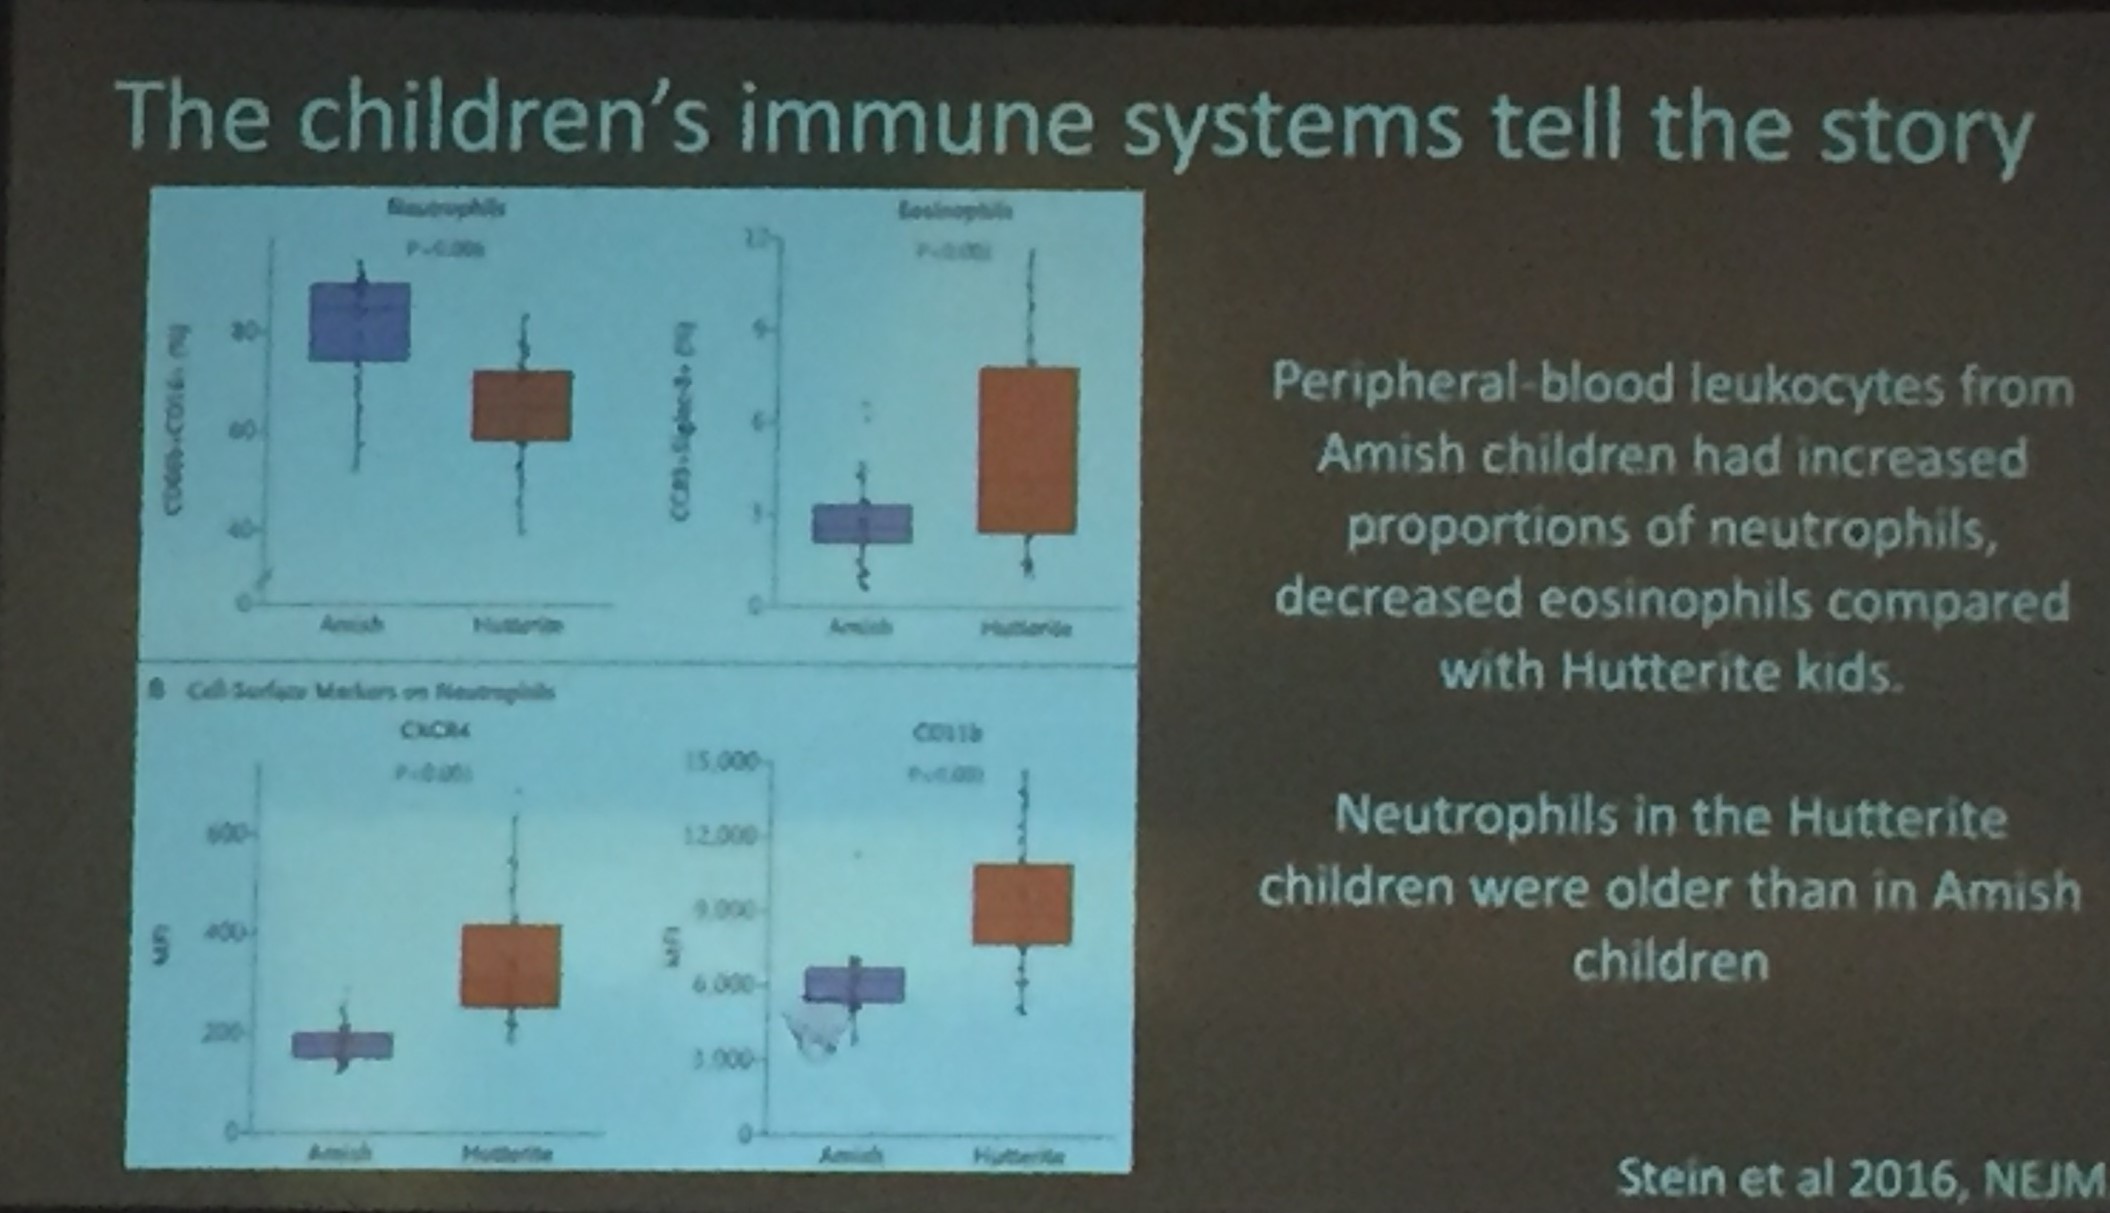
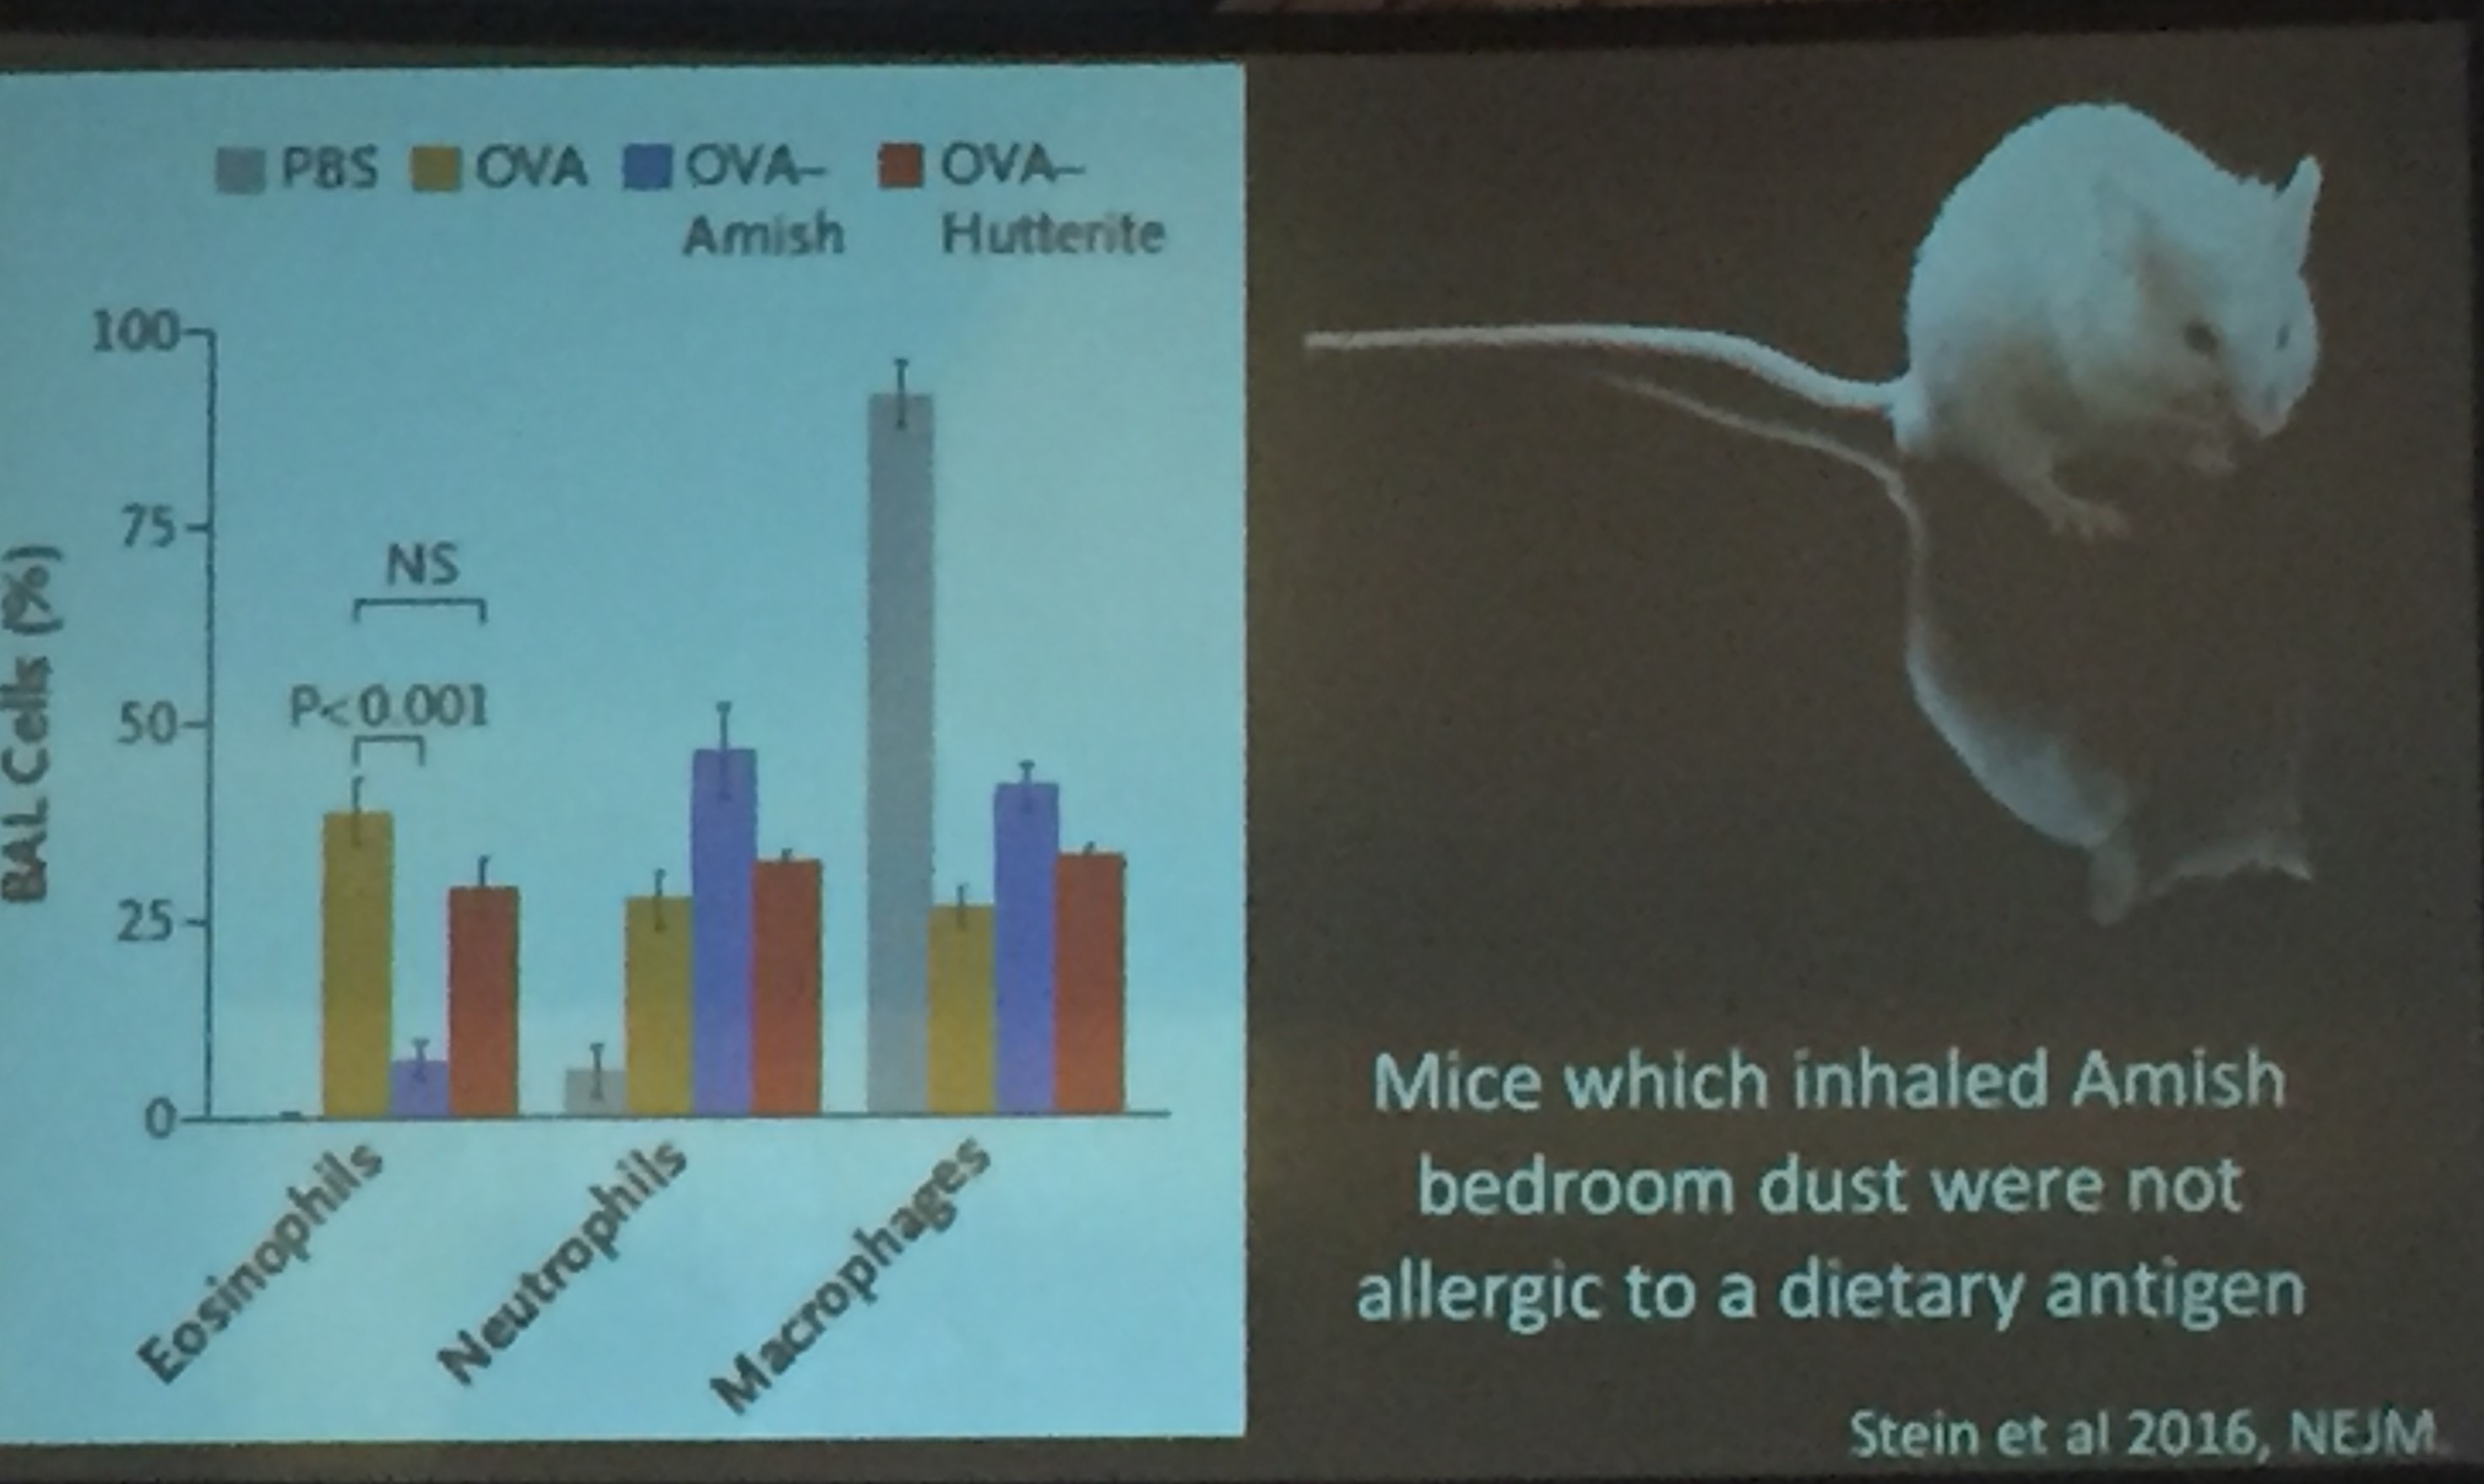
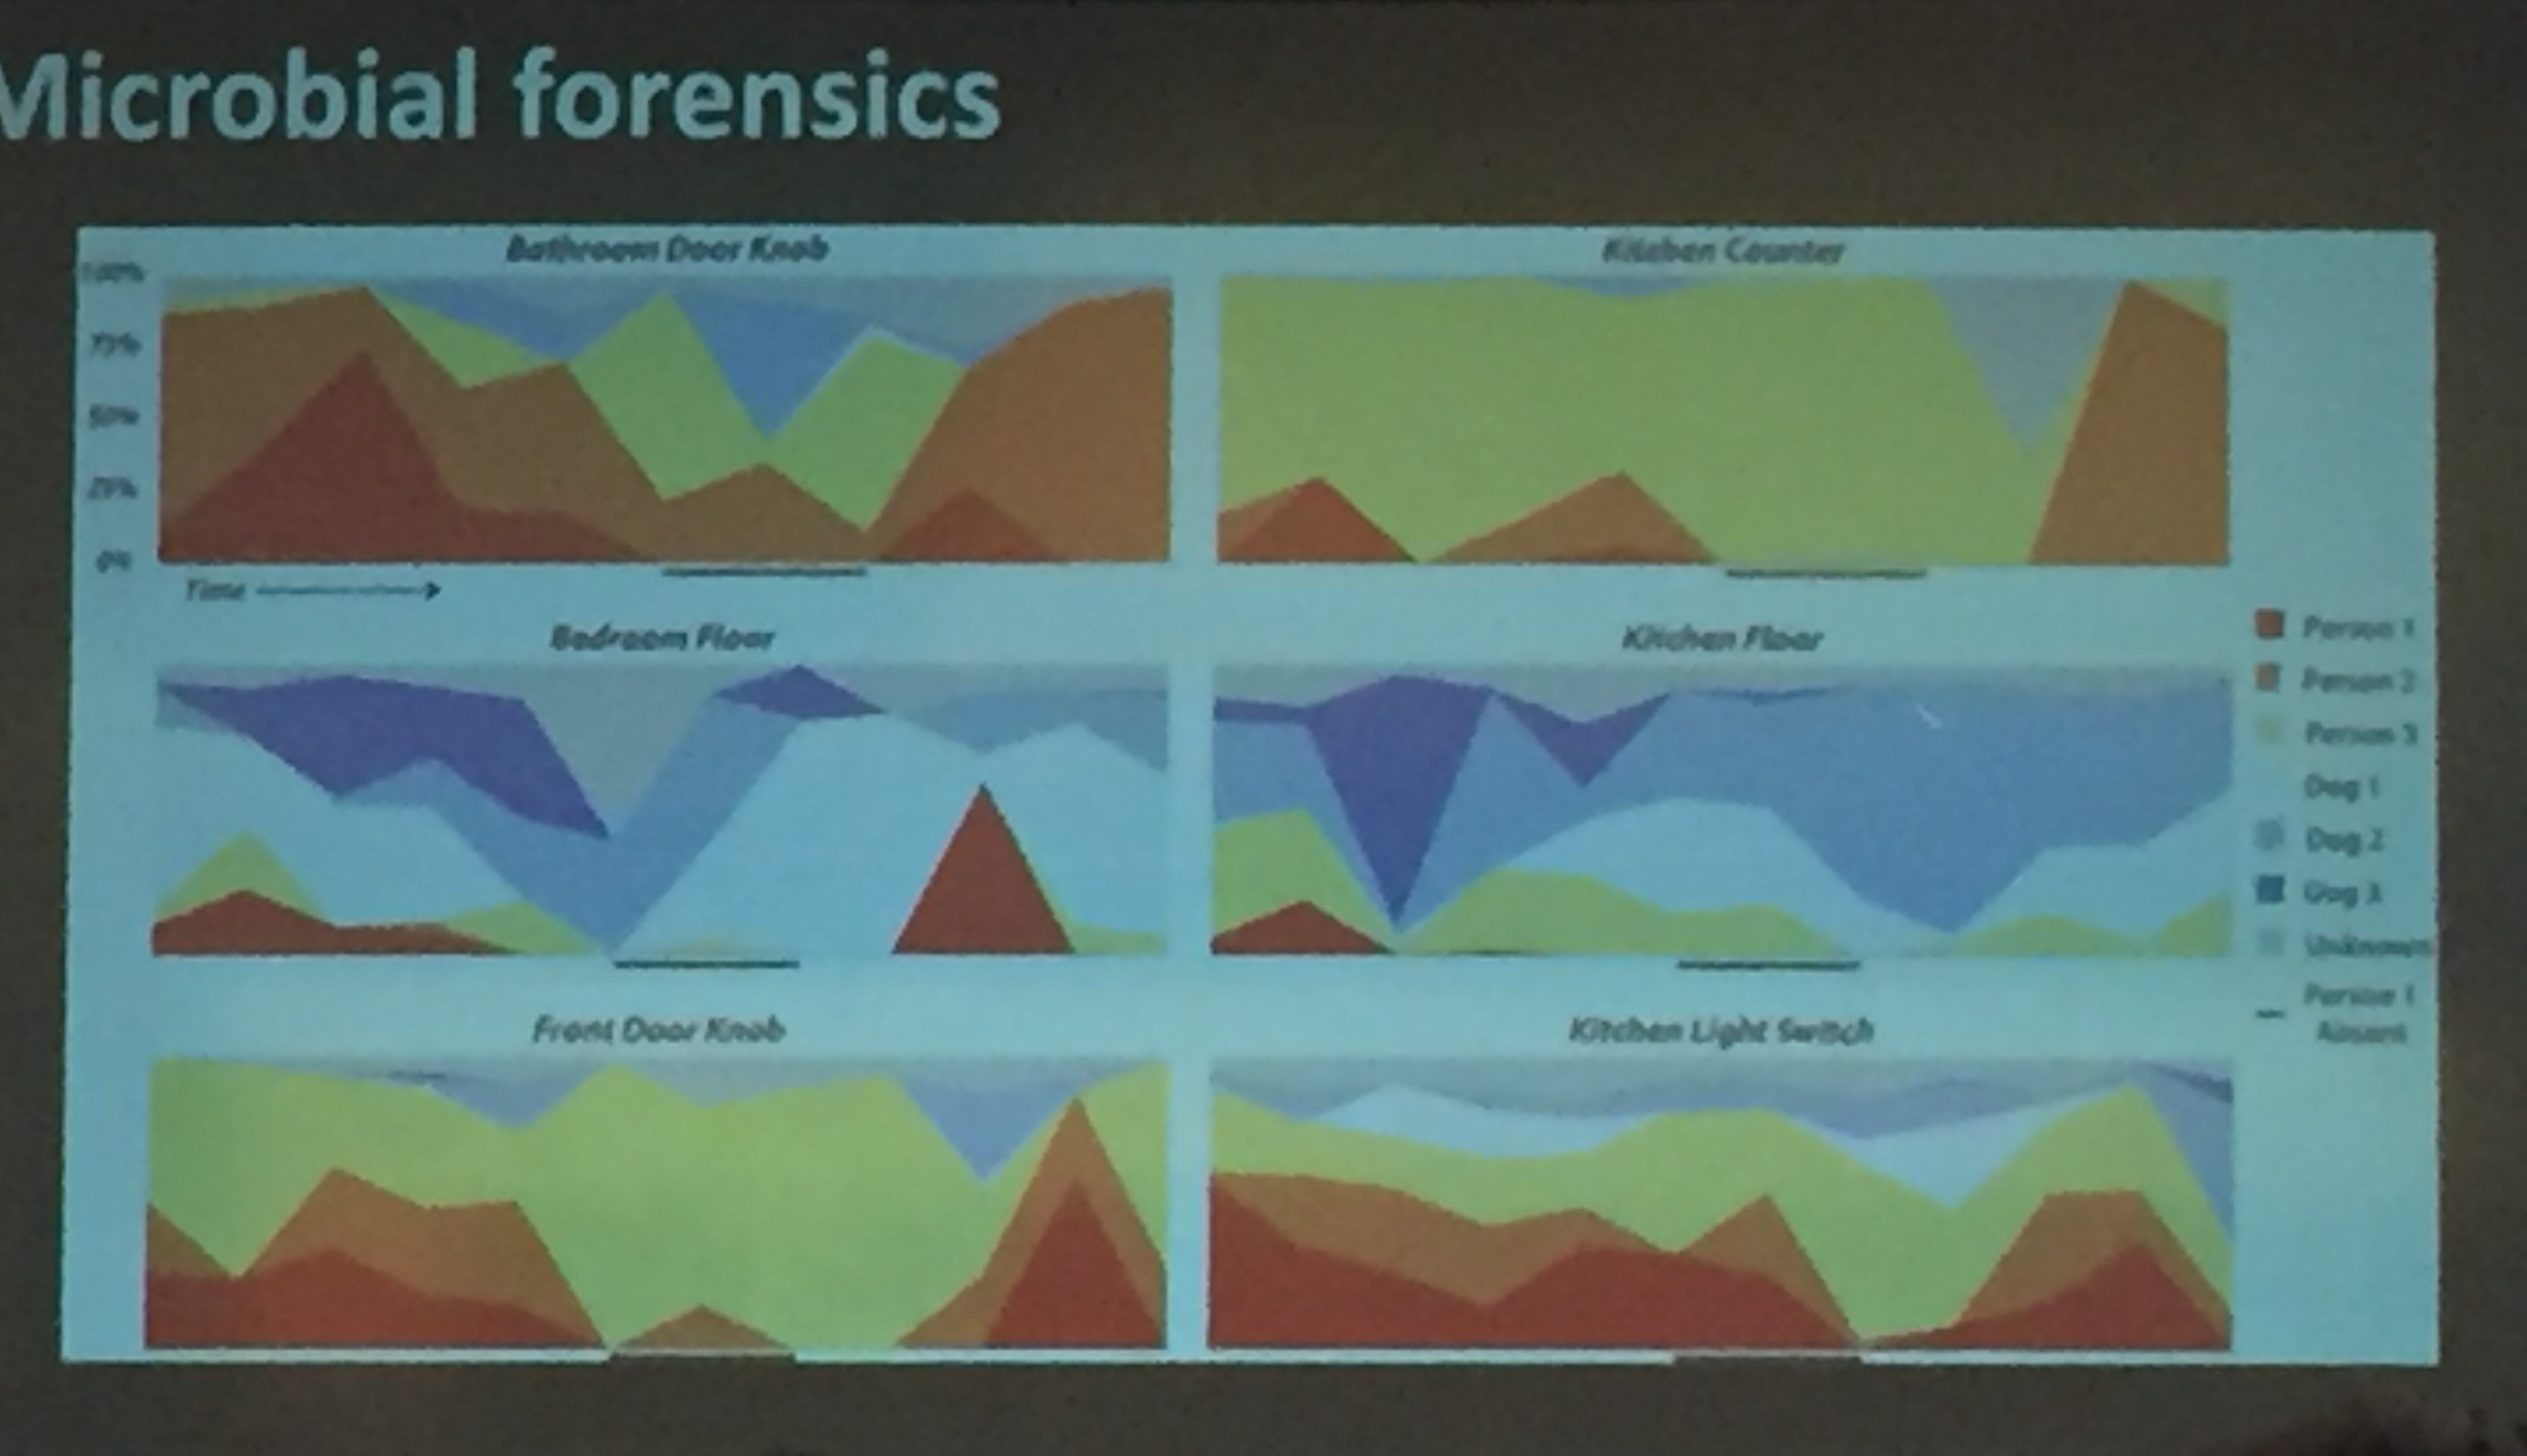
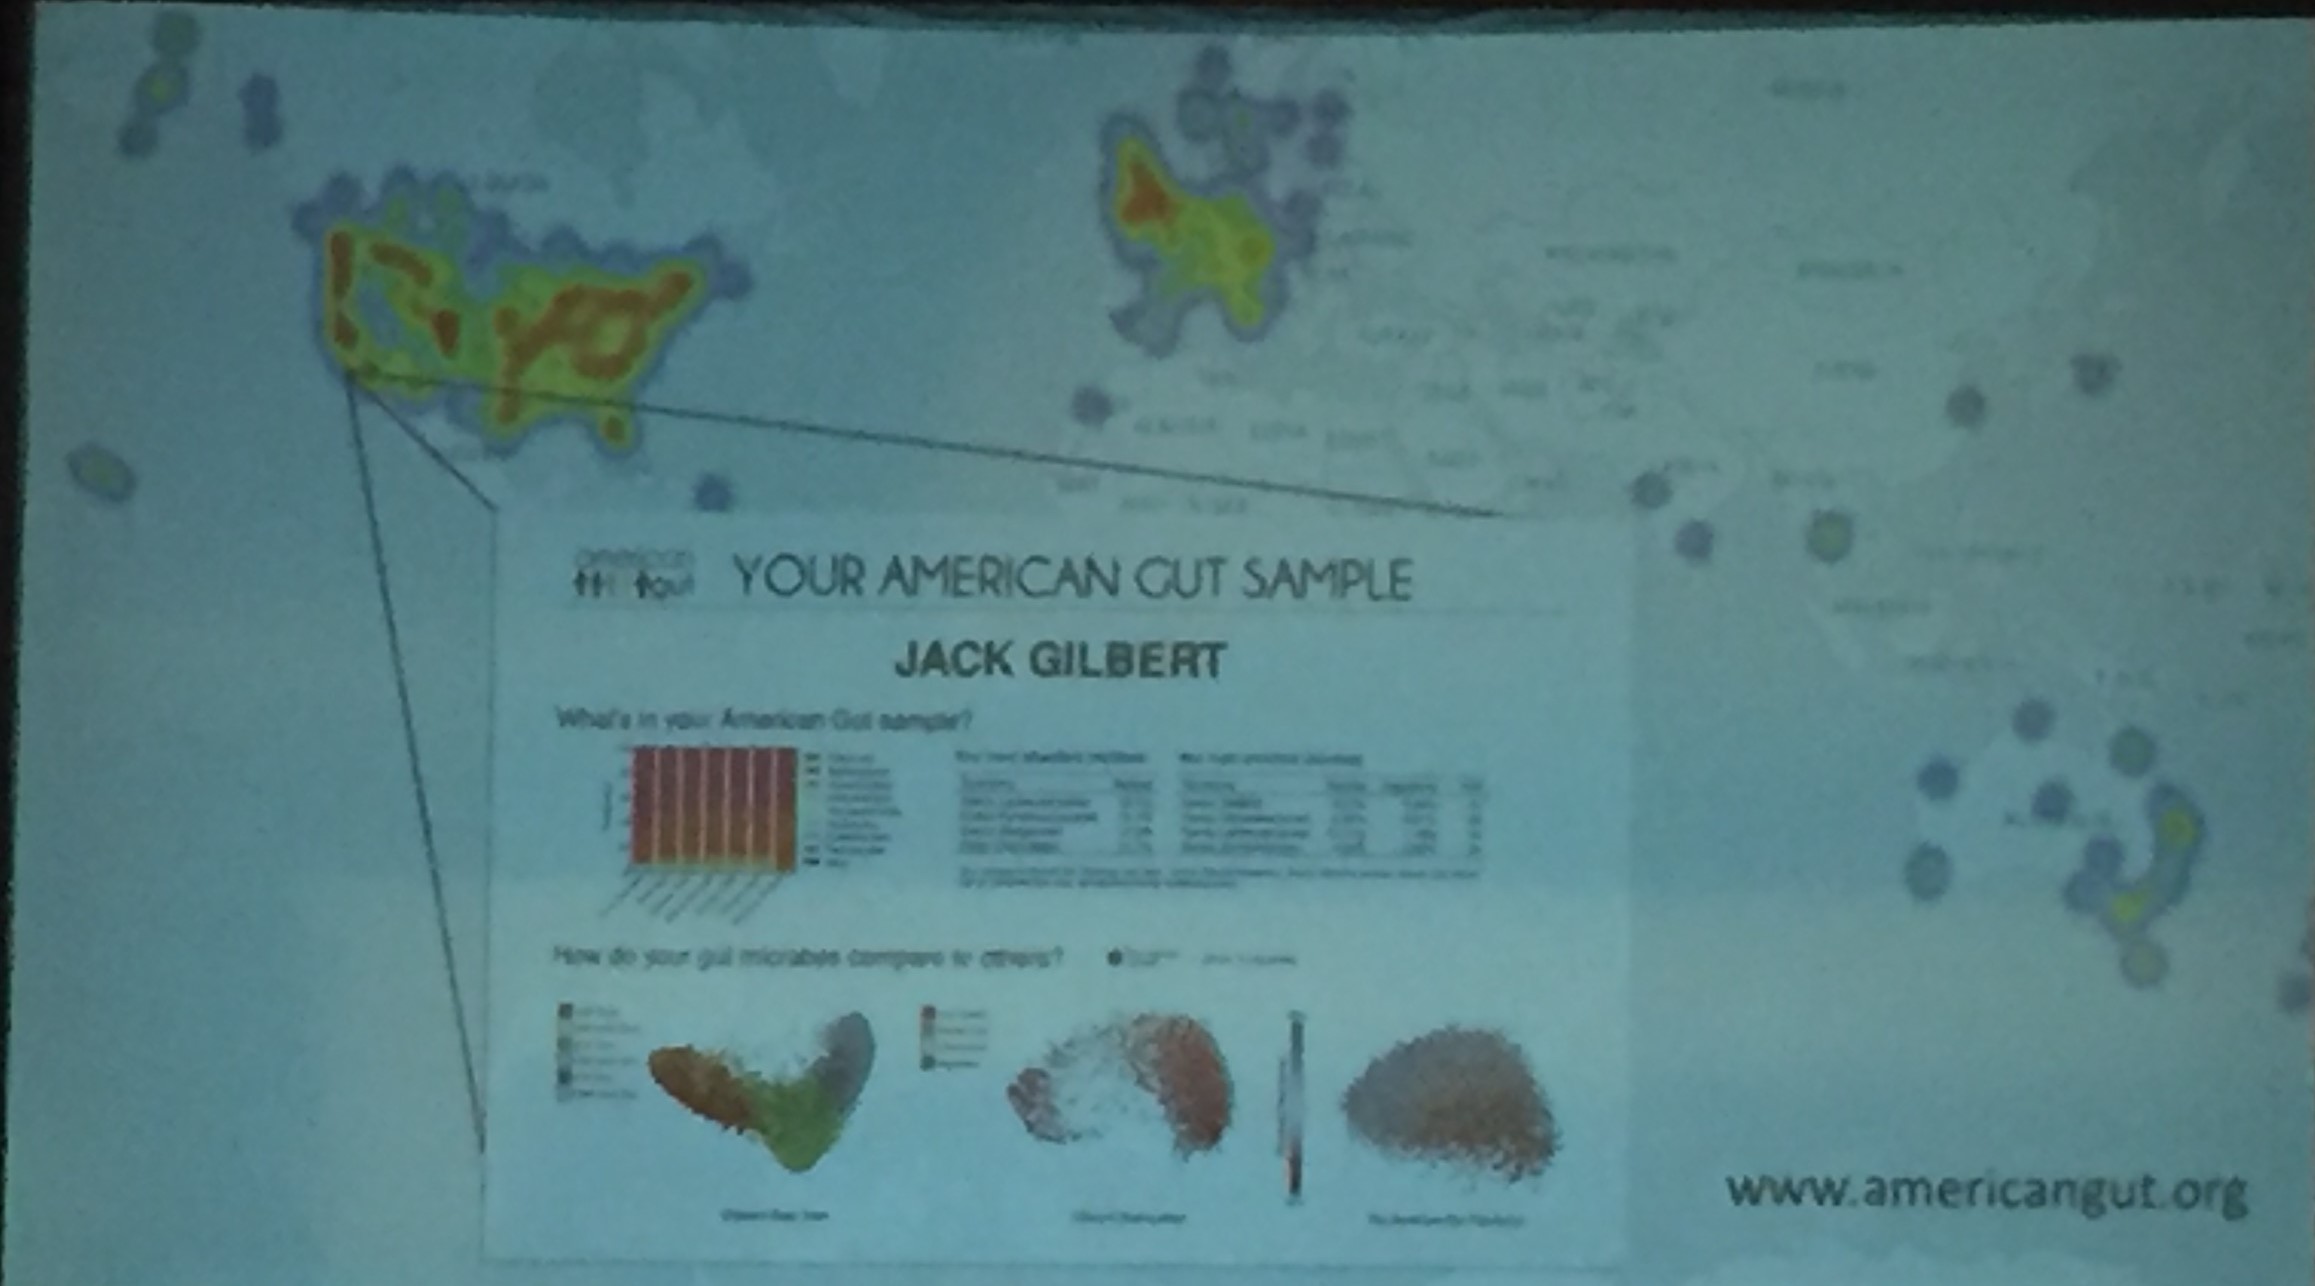
The first speaker, Jack Gilbert, gave the William F Balistreri lecture.  Dr. Gilbert has written a book on the topic of our ‘magnificent microbiome,’ Dirt is Good.  Here are a few slides:

Related study (not discussed in the talk): A recent study (R Vasapolli et al. Gastroenterology 2019; 157: 1081-91) provided data from 21 healthy adults. Using biopsies from panendoscopy and saliva/fecal samples, the authors found that the fecal microbiome is not representative of the mucosal microbiome.  In addition, each GI region had a different bacterial community.

Christopher Forrest gave the keynote lecture on pediatric learning health systems. By collating data from large pediatric health systems, the researchers can determine more quickly how effective treatments are in all pediatric specialties.

Melvin Heyman, editor of JPGN, provided a good year in review. I only capture a few images.

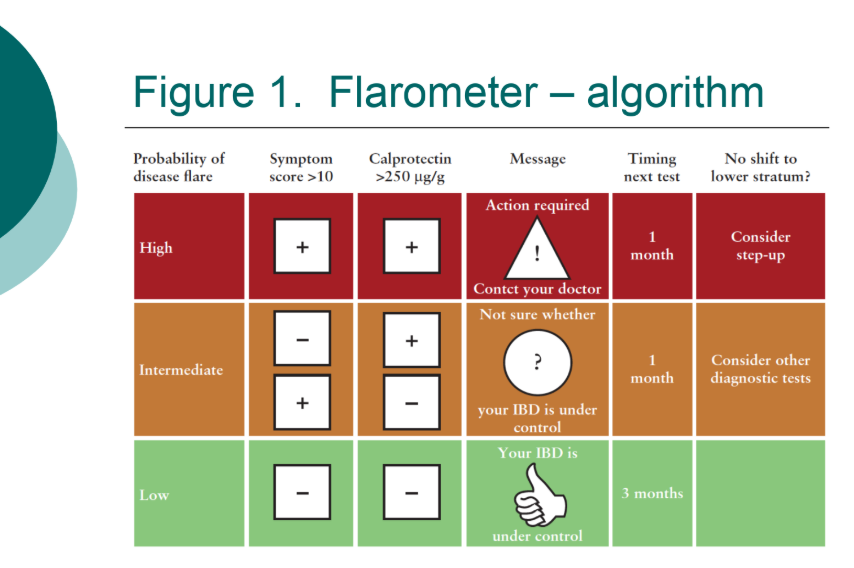
What is the Calprotectin Threshold for Disease Progression in Crohn’s Disease?

A recent retrospective study (NA Kennedy et al. Clin Gastroenterol Hepatol 2019; 17: 2269-76) with 918 patients with Crohn’s disease (CD) examined calprotectin levels and disease progression. Median followup was 50.6 months.

Key findings:

  • A calprotectin level cut-off of 115 mcg/g was identified as optimal for separation of those with and without disease disease progression.
  • The authors noted: “Several studies have identified a cut-off value of 250 mcg/g as being useful to distinguish active from inactive disease.  In the present study,…a lower threshold of 115 mcg/g (was identified) suggesting that lower levels of inflammatory activity still may be associated with an adverse outcome.”
  • The authors’ figure 2, as estimated by the empiric transition matrix method, shows disease progression over 30 years.  At that point,  the groups were nearly equally divide between stricturing disease, penetrating disease and inflammatory disease; in contrast at disease onset, ~80% had inflammatory disease behavior.

My take: As more effective therapies have become available, our goals for disease control have changed and focus on altering the disease course with more stringent endpoints.  For calprotectin, the lower number (115 compared to 250) indicates a much lower risk for disease progression.

Related blog posts:

Chicago

#NASPGHAN19 Impact of New Technologies on Patient Health

Along with Ragh Varier, I had the privilege of moderating a session on new technologies on patient health.  Below I’ve included a few slides and some notes; my notes may have errors of omission or transcription.

Chicago


Dr. Mehta’s lecture focused on wearable health technologies. Key points:

  • It is already in use in some areas (eg. continuous glucose monitoring for diabetes, ECG sensors).
  • She noted that wearable technology dates back to the 1600s with the abacus ring
  • Challenges: Accuracy, Actionability/outcome improvement, Reaching at-risk populations (not just the ‘worried well’ populations), regulation, sustainability (users may abandon quickly), and ethical/privacy concerns
  • Some families taking technology into their own hands, so to speak. #WeAreNotWaiting.  Example: artificial pancreas device system

Dr. Syed’s lecture focused on artificial intelligence in medical-decision making. Key points:

  • AI is already in use in areas like facial recognition
  • AI may be able to increase polyp detection rate in colonoscopy and improve histology reading
  • Her team has been working on using AI to help distinguishing enviromental enteropathy histology from other etiologies
  • Other potential uses: AI to help predict Crohn’s disease progression based on histology

Related study (not discussed in talk): Z Deng, H Shi et al. Gastroenterology 2019; 157: 1044-54. The authors collected more than 113 million images from 6970.  With a deep-learning algorithm, they found that video capsule endoscopy could have higher detection rates and improved reading time with a “CNN-based” reading system (CNN=convolutional neural network).  The mean reading time was reduced from 97 minutes with conventional reading to 6 minutes with CNN-based reading system.  The later had 99.88% sensitivity in per-patient analysis (vs. 74.57% with conventional reading).

The oral abstract presentation, by Sonja Swenson, detailed how machine learning was applied to try to improve transplantation selection/PELD scores.

  • The authors of this abstract (437) used data from 6273 patients with PELD scores and added additional variables to try to identify a more accurate model.
  • Link: All NASPGHAN 2019 Abstracts

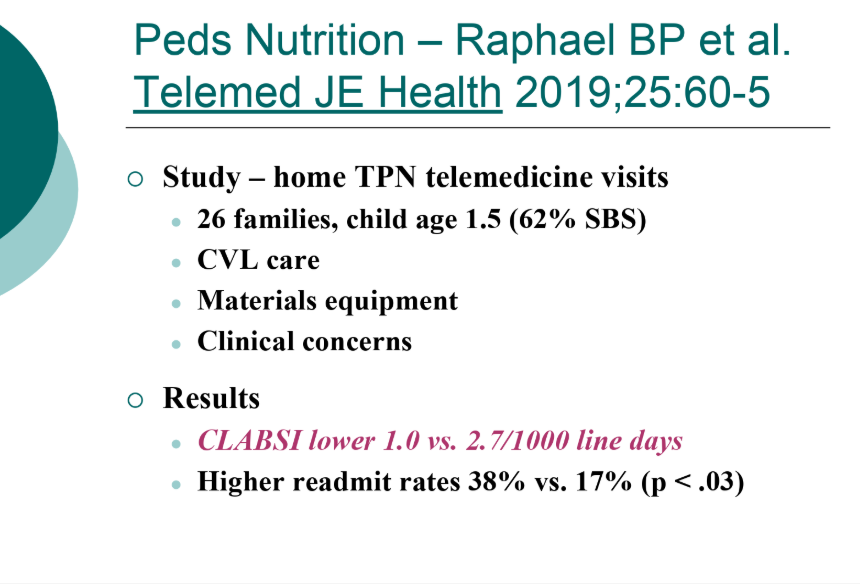
Dr. Li, known by some as the ’emperor of emesis,’ presented a lecture on telemedicine. His full slides: Telemedicine NASPGHAN Updated 2019 (B Li)

Key points:

  • When surveyed, patients/families prefer telemedicine over conventional medicine.  Key reason is convenience
  • Lots of issues from health care provider viewpoint: reimbursement, licensing (improving), increased time
  • Many examples of telemedicine/telemonitoring that are ongoing

Disclaimer: NASPGHAN/gutsandgrowth assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. The discussion, views, and recommendations as to medical procedures, choice of drugs and drug dosages herein are the sole responsibility of the authors. Because of rapid advances in the medical sciences, the Society cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. Some of the slides reproduced in this syllabus contain animation in the power point version. This cannot be seen in the printed version.


Here’s The Proof That Proactive Drug Monitoring Improves Outcomes in Children With Crohn’s Disease

A nonblinded randomized controlled trial (A Assa et al. Gastroenterology 2019; 157: 985-06) with 78 children who had Crohn’s disease provides some of the best evidence to date that proactive therapeutic drug monitoring (pTDM) is important for anti-TNF therapy. The trial was called the PAILOT =Paediatric Crohn’s disease Adalimumab-Level-based Optimisation Treatment.  This is the first RCT of pTDM that actually achieved its primary end point.

In this study, children were divided into a pTDM group (n=38) who received adalimumab levels at weeks 4 and 8 along with every 8 weeks unitl week 72.  The control group (n=31) had reactive monitoring.  The investigators aimed for a trough concentrations above 5 mcg/mL.

Key findings:

  • The primary endpoint of sustained corticosteroid-free clinical remission (CFCR) was achieved in 82% of the pTDM group compared to 48% in the reactive monitoring group (p-.002).
  • The pTMD also  had a higher rate of the composite outcome (CFCR, CRP ≤0.5 mg/dL, and calprotectin ≤150): 42% compared to 12% in the control group (p=.003)
  • 87% of pTDM had dose intensification compared to 60% in control group.

The editorial by Papamichael and Cheifetz (pg 922-4) highlights some additional observations:

  • “The study actually showed that a 10.0 mcg/mL threshold performed better than 7.5 and 5.0 mcg/mL” with respect to PCDAI and CRP levels.
  • “The recent prospective Personalized anti-TNF therapy in Crohn’s disease study (PANTS) showed that the optimal week 14 adalimumab concentration …at both week 14 and 54 was 12 mcg/mL”

My take: Most pediatric gastroenterologist understand the importance of pTDM, especially as conventional dosing of anti-TNF agents is often too low.  This study provides some needed proof and hopefully will aid our efforts to get adequate insurance coverage.  The optimal frequency and timing of pTDM still needs work.

Related blog posts:

I really enjoyed my recent trip to Chicago. Here’s a picture from Lincoln Park Zoo from my favorite photographer

#NASPGHAN19 Selected Abstracts (Part 2)

Link to full NASPGHAN 2019 Abstracts.

Here are some more abstracts/notes that I found interesting at this year’s NASPGHAN meeting.

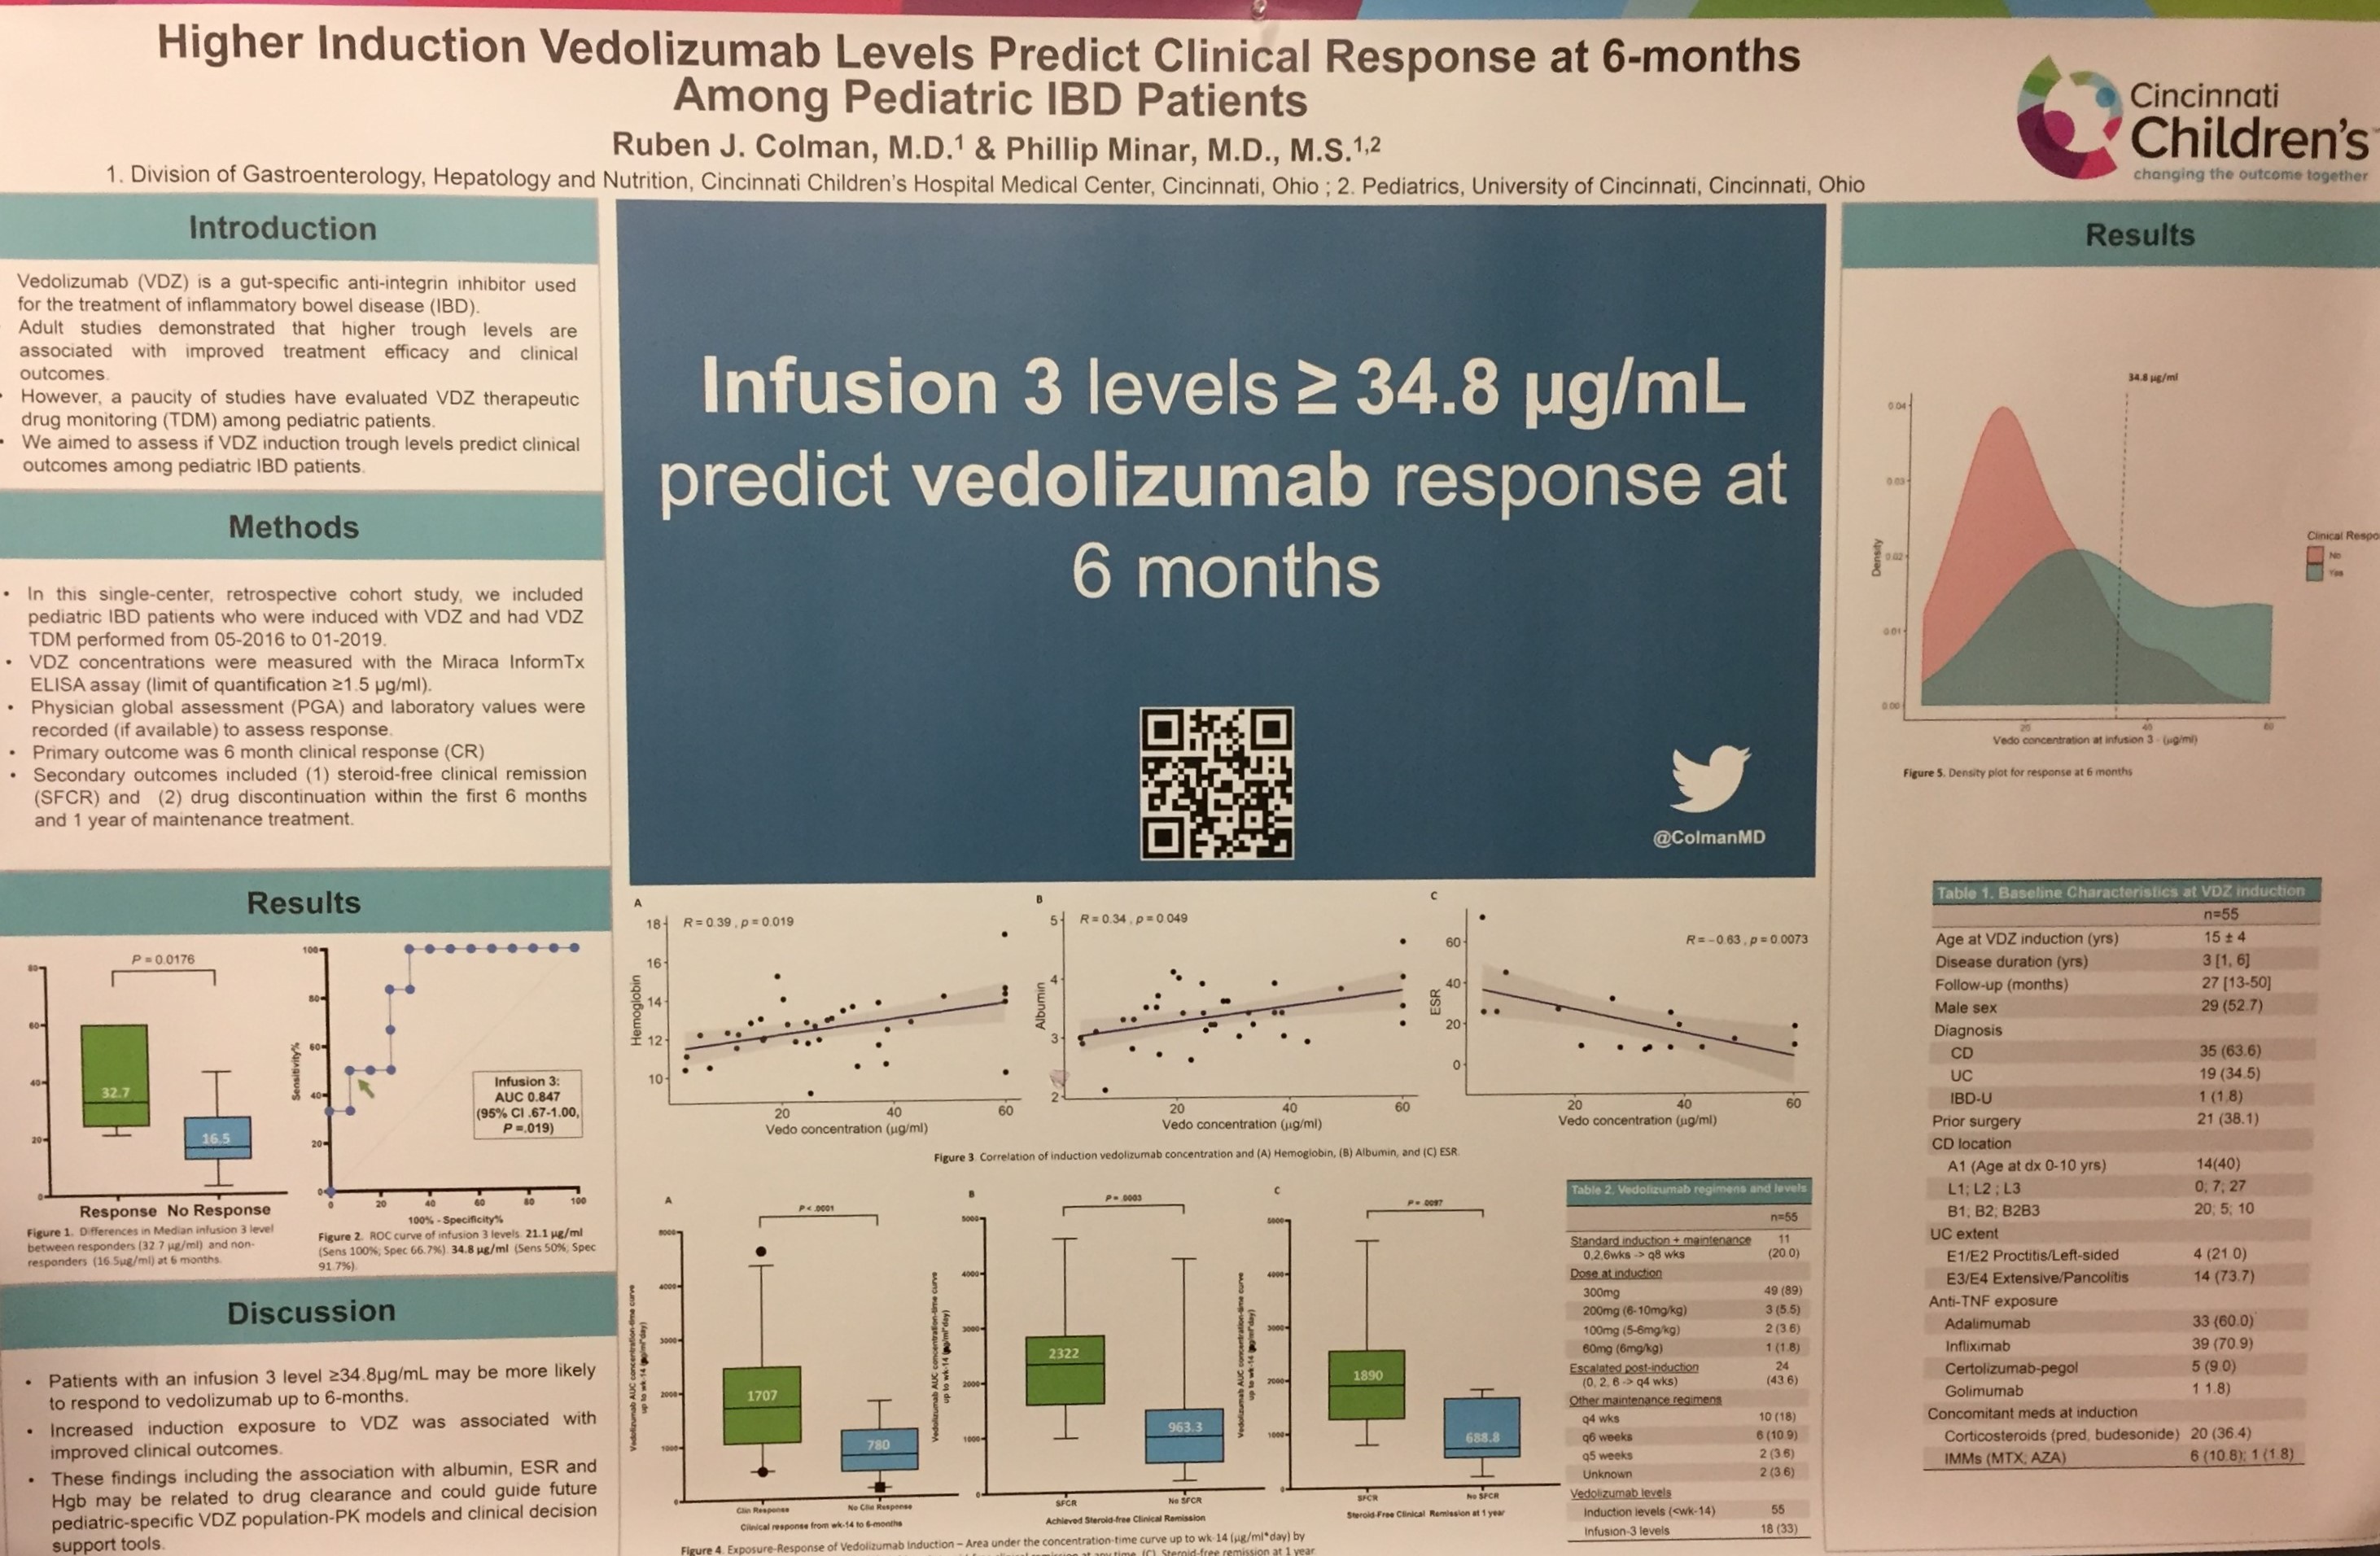
A study (poster below) from Cincinnati found that a vedolizumab level ≥34.8 mcg/mL at week 6 (prior to 3rd infusion) predicted clinical response at 6 months

Related blog posts:

The poster below reported a high frequency of eosinophilic disorders in children who have undergone intestinal transplantation. Related blog post: Eosinophilic disease in children with intestinal failure

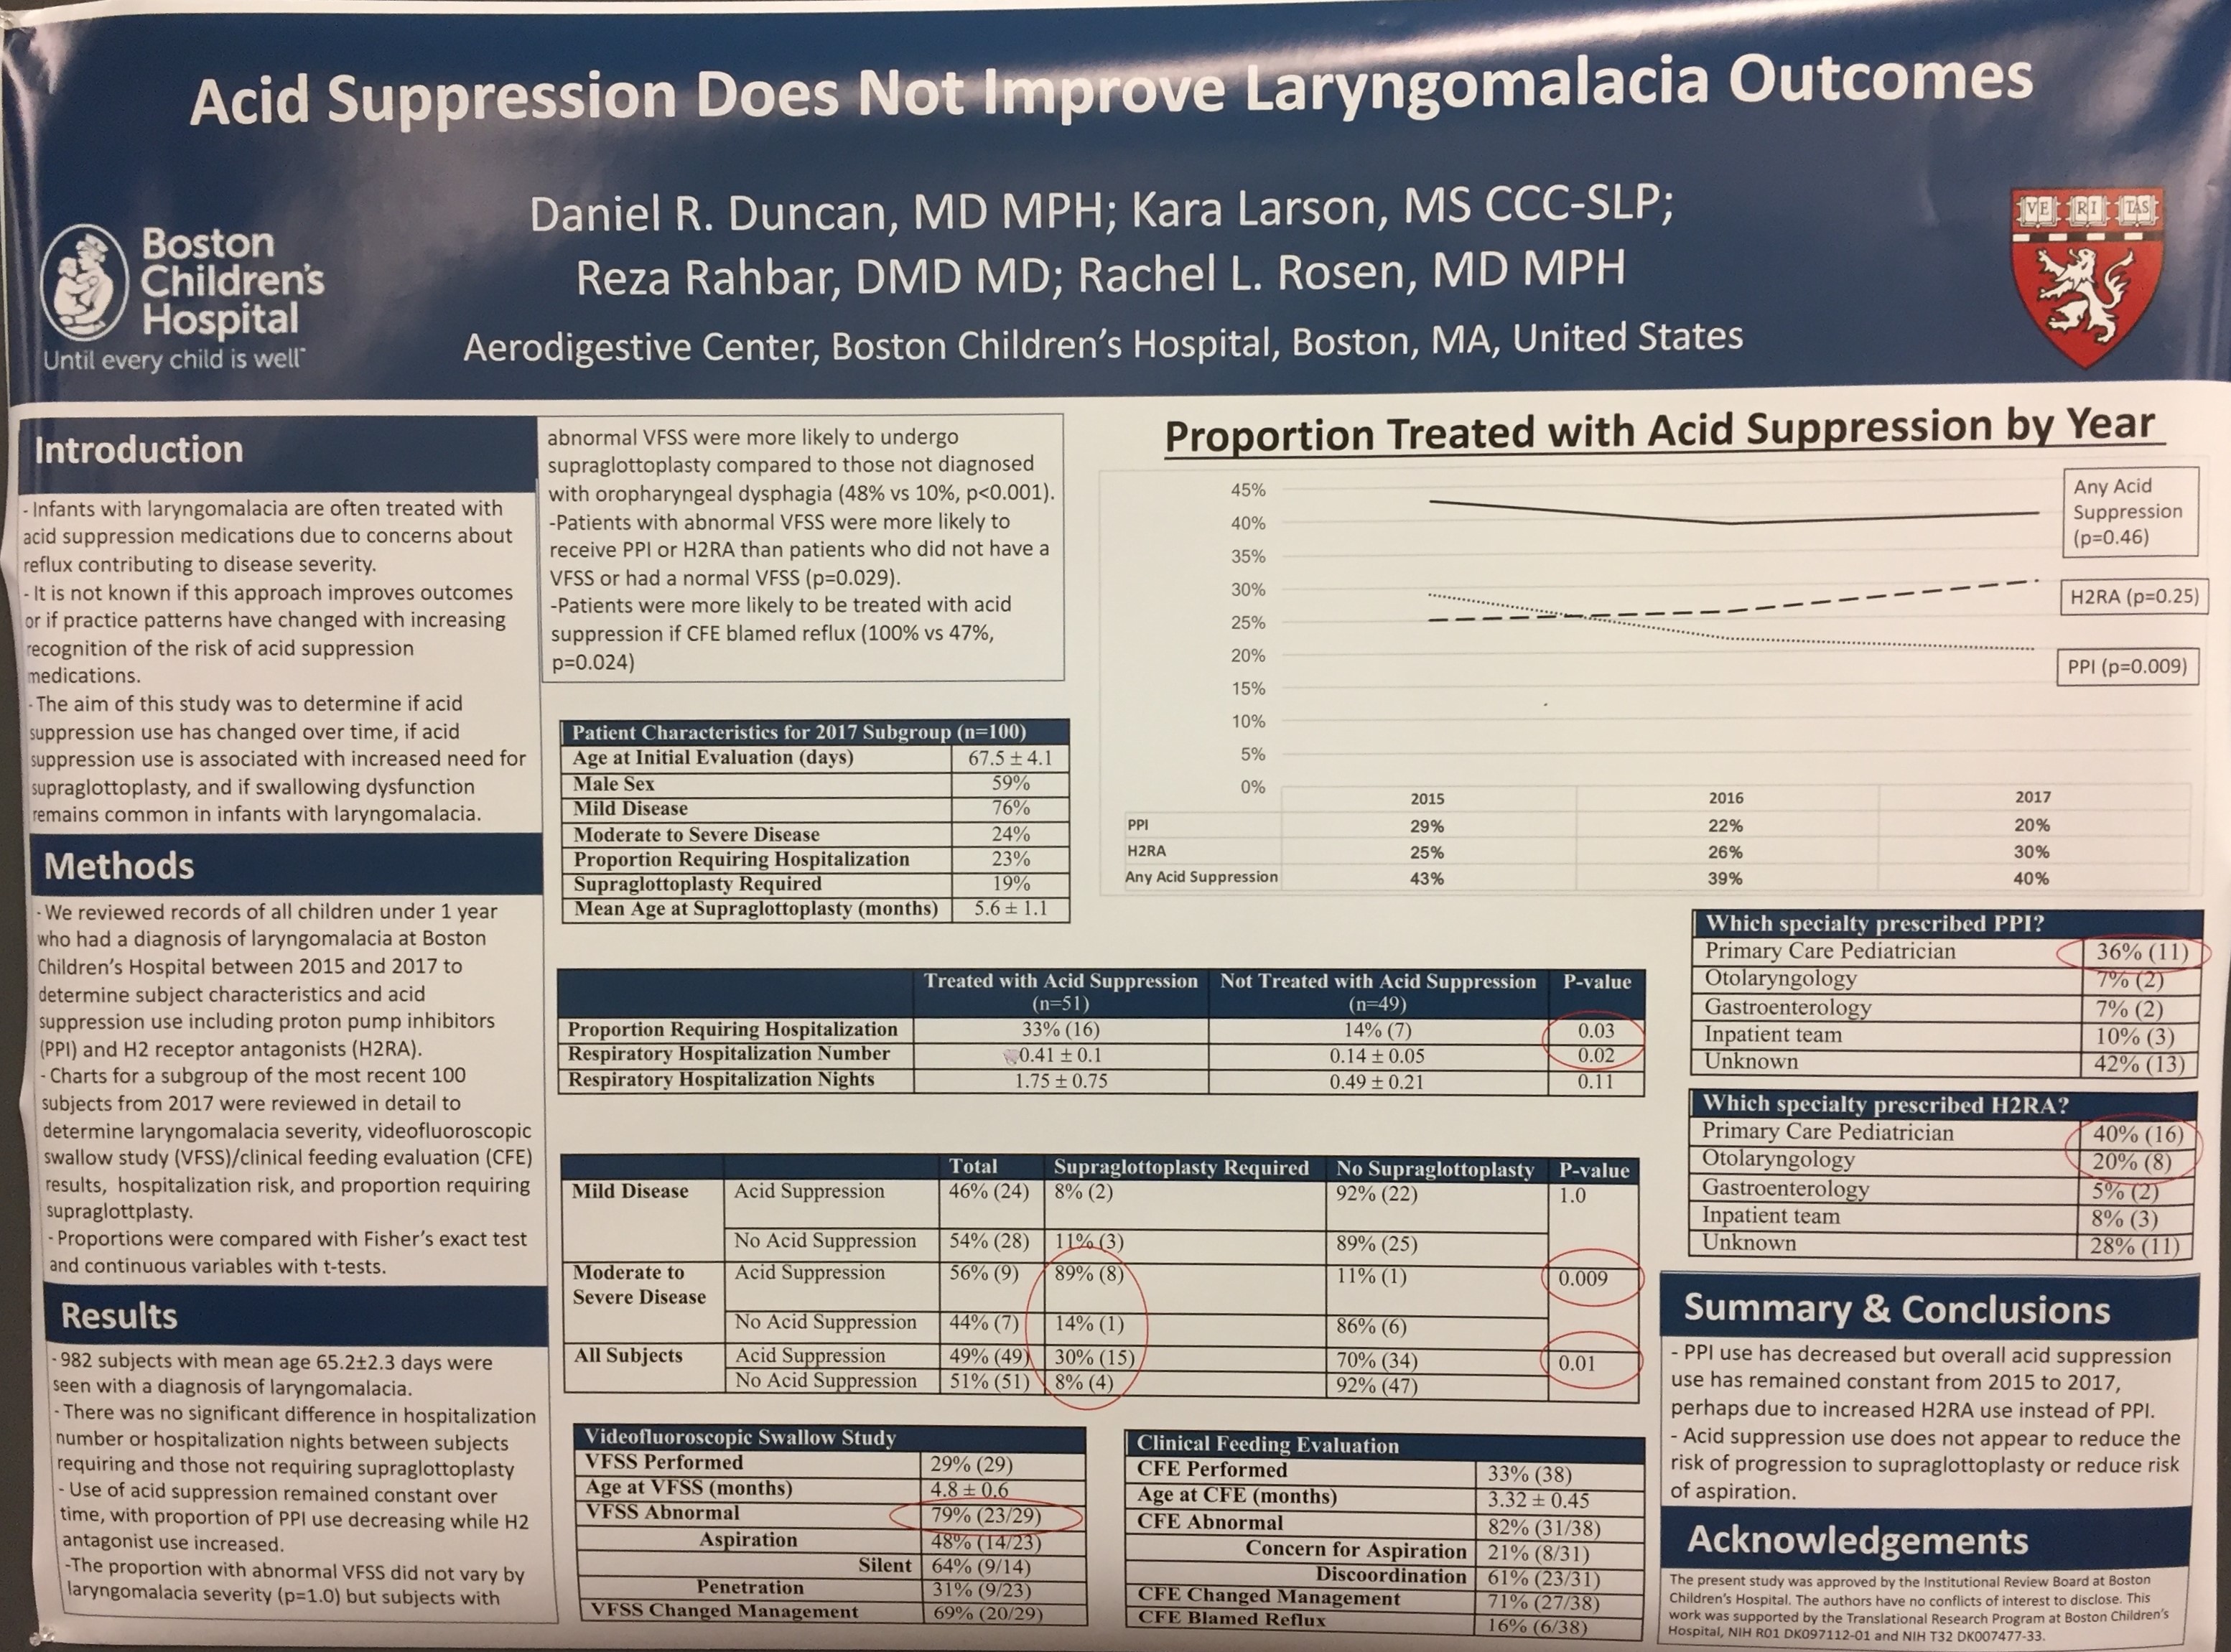
This study from Boston indicates that acid suppression was not associated with improved outcomes in infants with laryngomalacia (eg. lower supraglottoplasy rates or lower aspiration rates.

Related blog posts:

The study below showed that “less than half of children who started the low FODMAP diet were able to complete the elimination phase.” This indicates the need for careful dietary counseling when attempting this therapy.

Related blog posts:

The abstract below showed that the dietary intake of children with inflammatory bowel disease, who were not receiving enteral nutrition therapy, was similar to healthy control children.

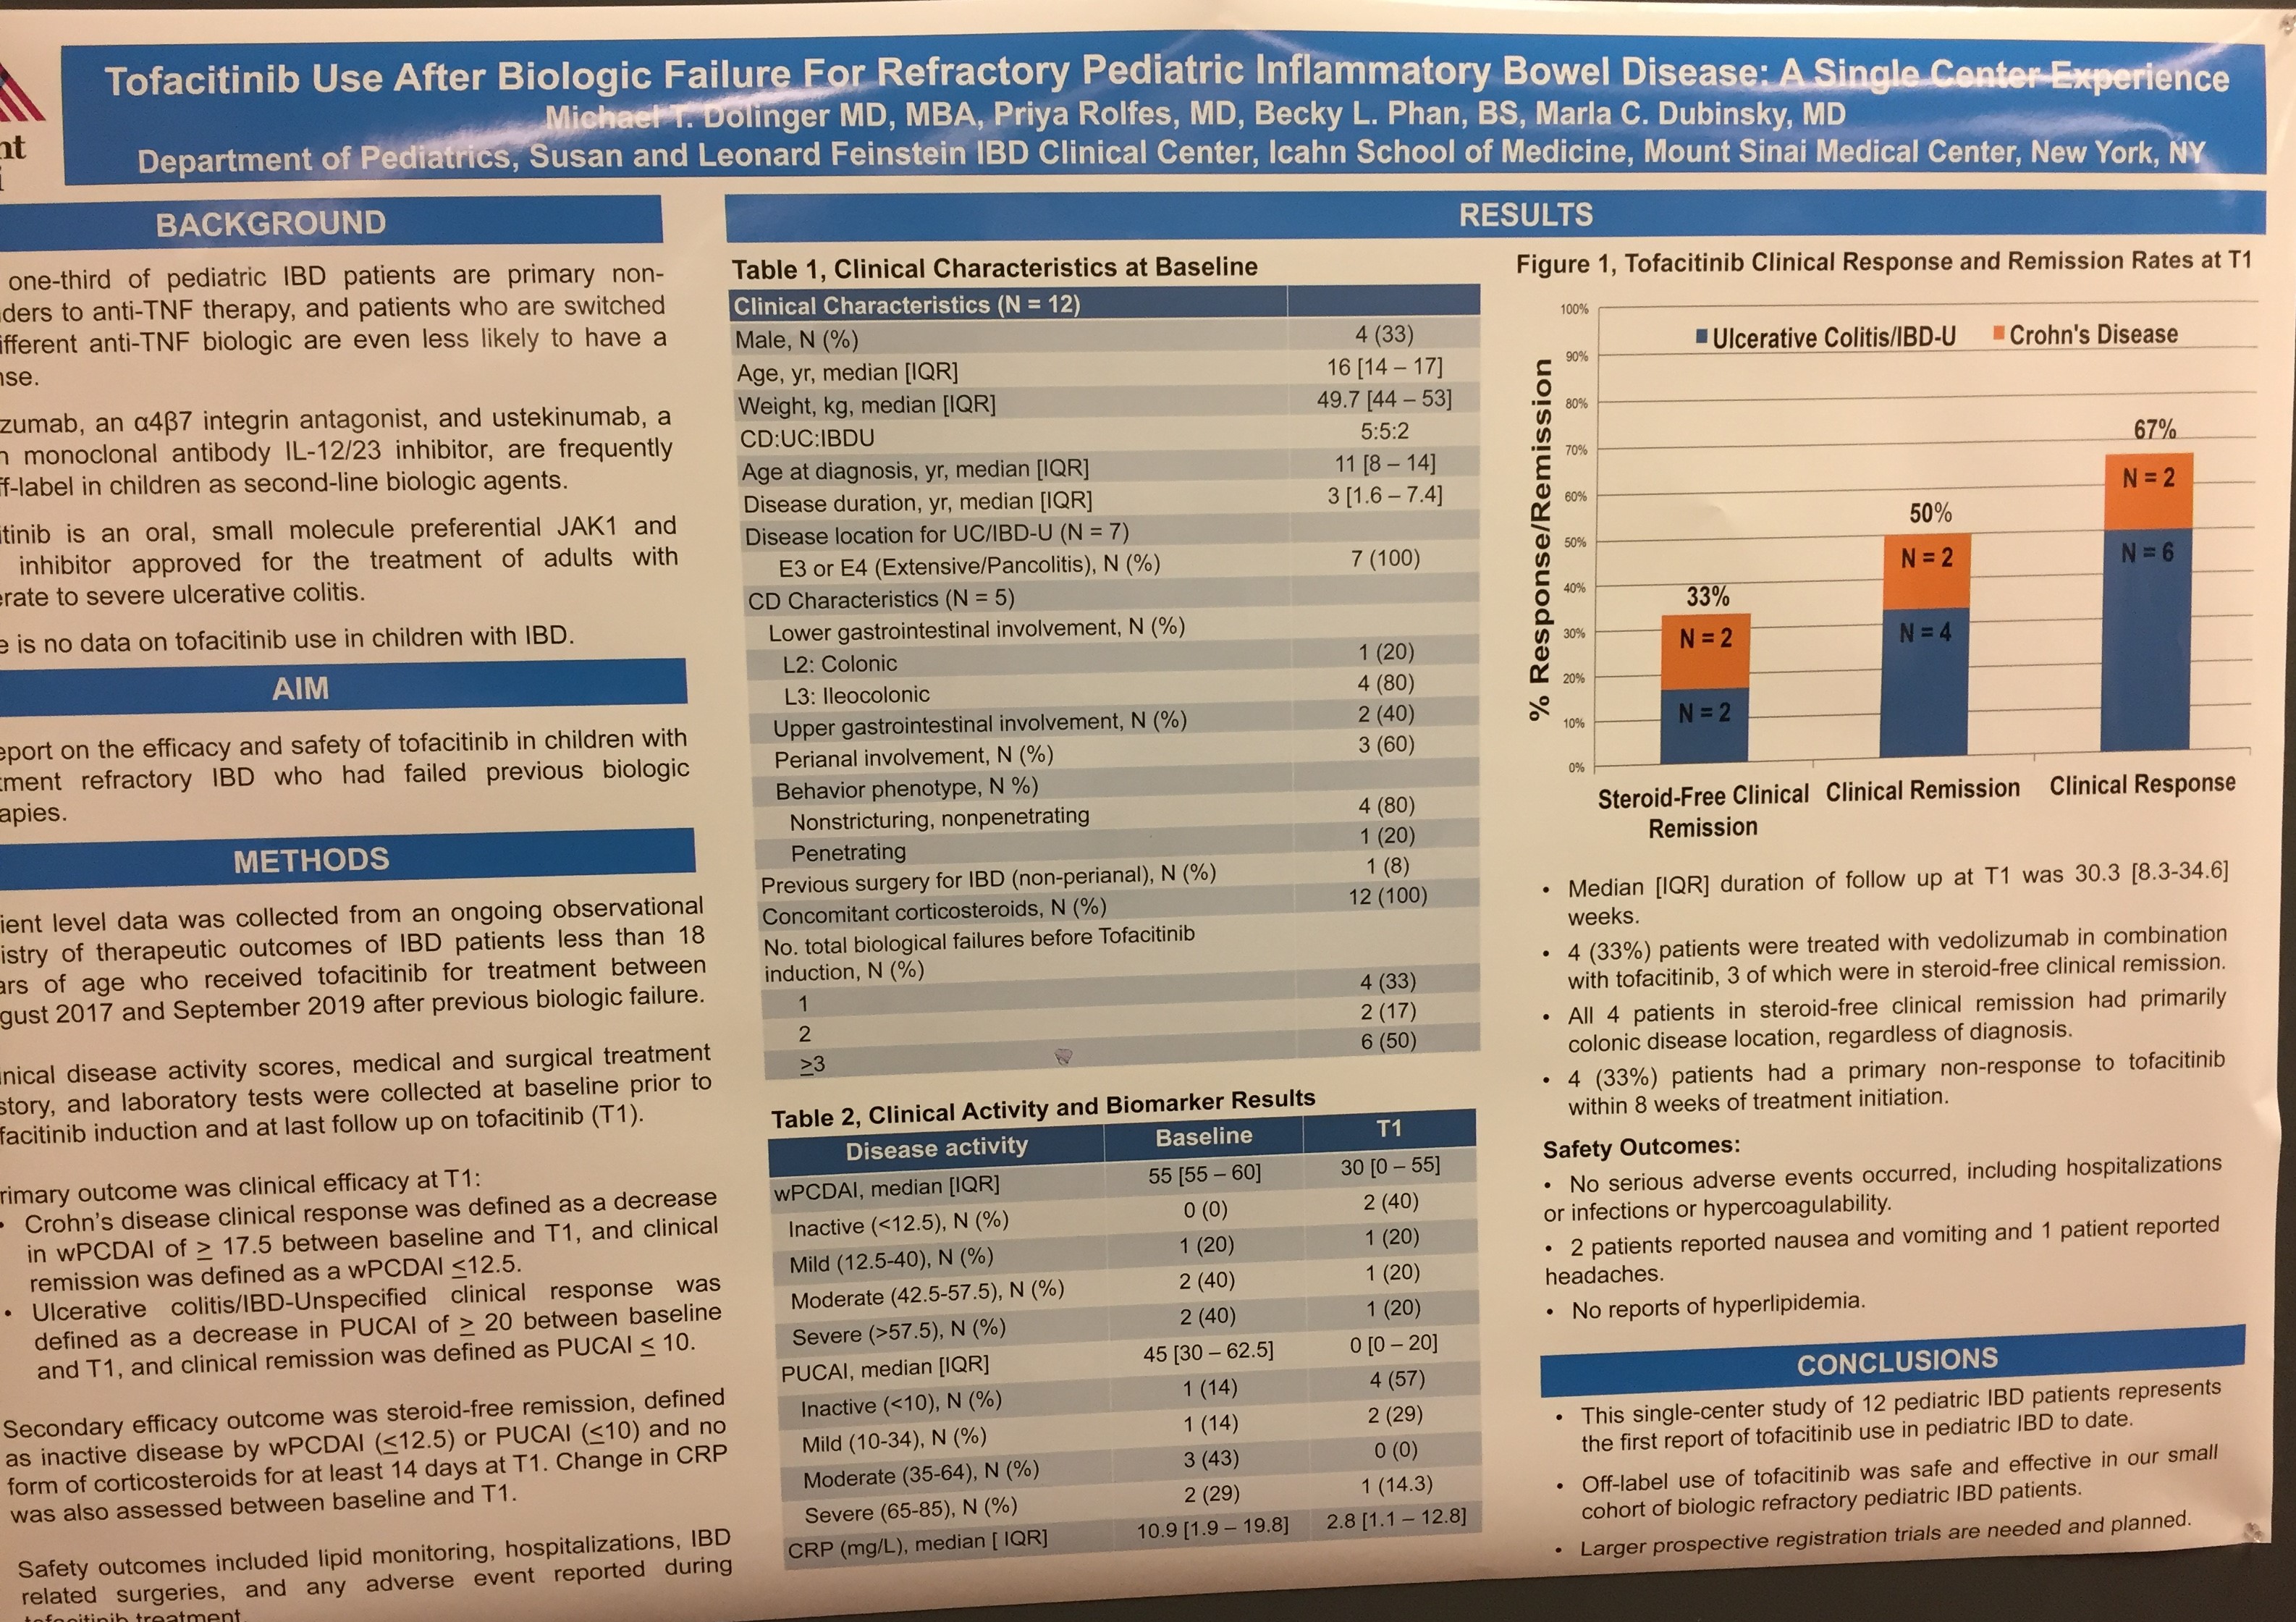
The next two studies provide some pediatric experience with tofacitinib in teenagers with inflammatory bowel disease (14-18 years of age).  The first poster had 12 children and reported a 67% clinical response rate (cohort with 5 with CD, 5 with UC, and 2 with IC).  The second poster had 4 of 6 with a clinical response and 3 in remission.

Related blog posts -Tofacitinib:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

#NASPGHAN19 Selected Abstracts (Part 1)

Link to full NASPGHAN 2019 Abstracts.

Here are some abstracts that I found interesting at this year’s NASPGHAN meeting:

NAFLD:

  1. Off-label use of topiramate may be helpful in stabilizing weight and improving NAFLD
  2. Socioeconomic barriers are frequent in NAFLD patients (the 2nd poster did not appear to show a control population):

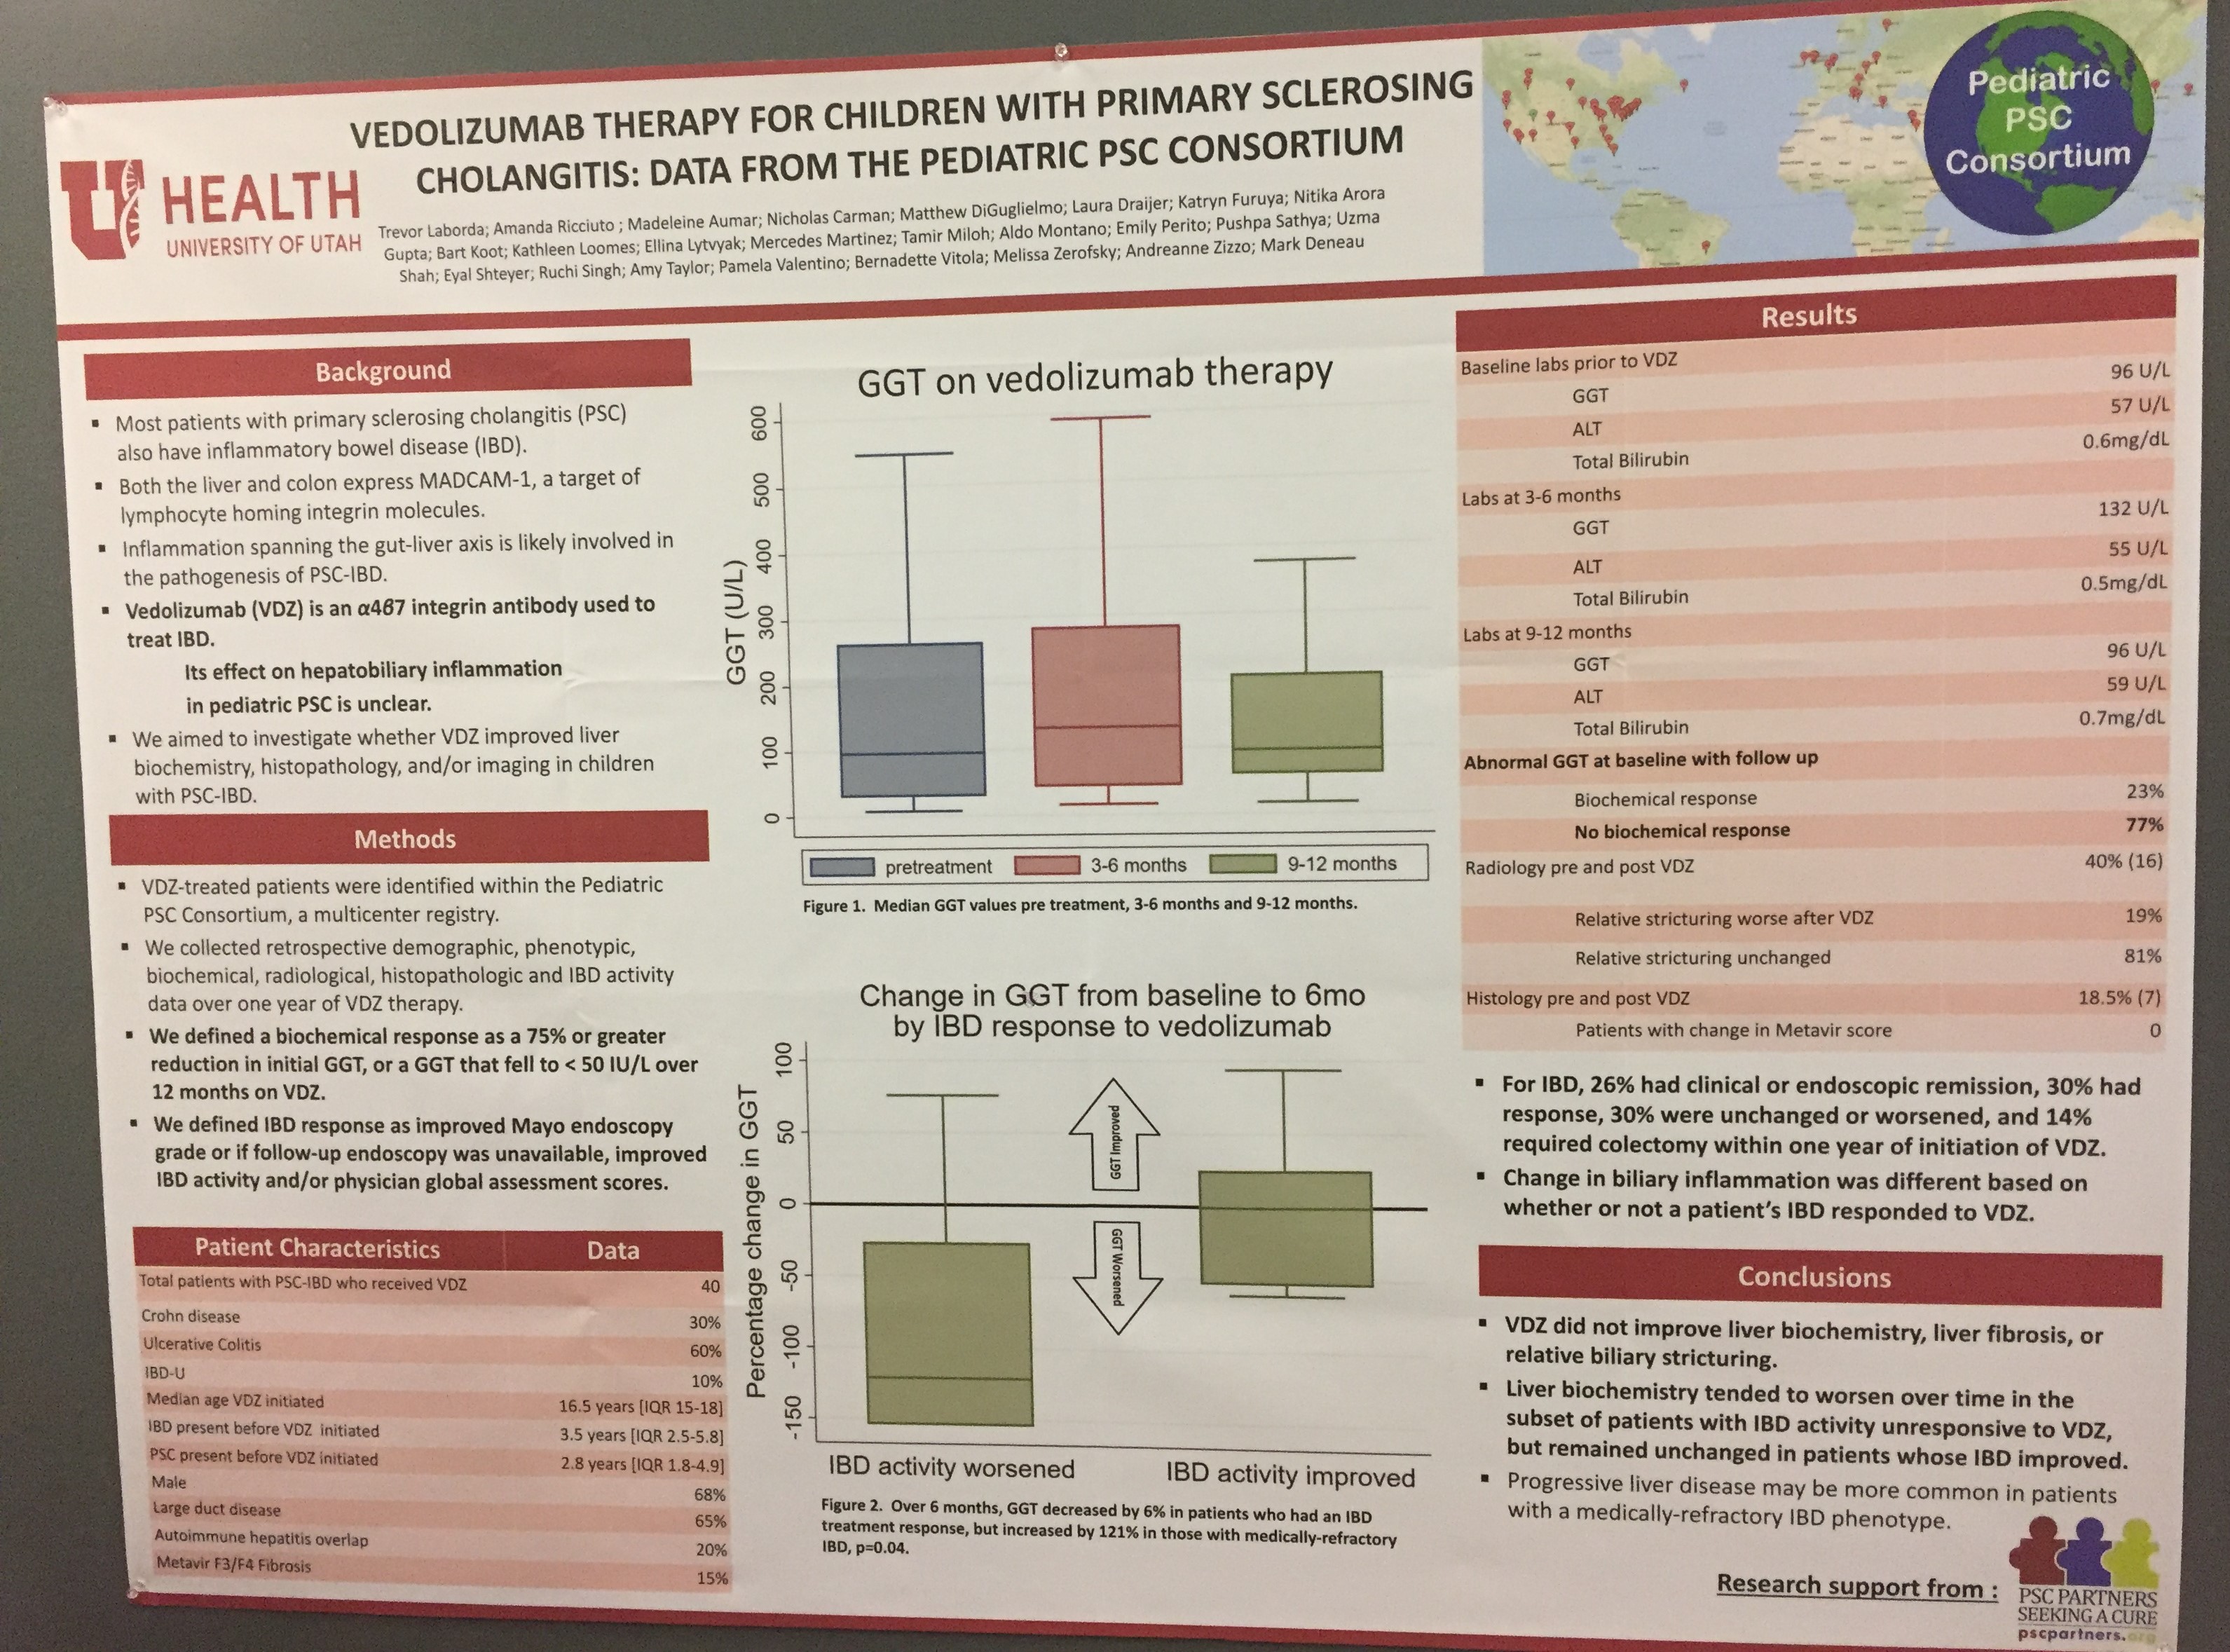
Primary Sclerosing Cholangitis -Use of Vedolizumab for PSC did not appear to help

Eosinophilic Esophagitis

  1. EoE is four times more likely in this cohort with inflammatory bowel disease
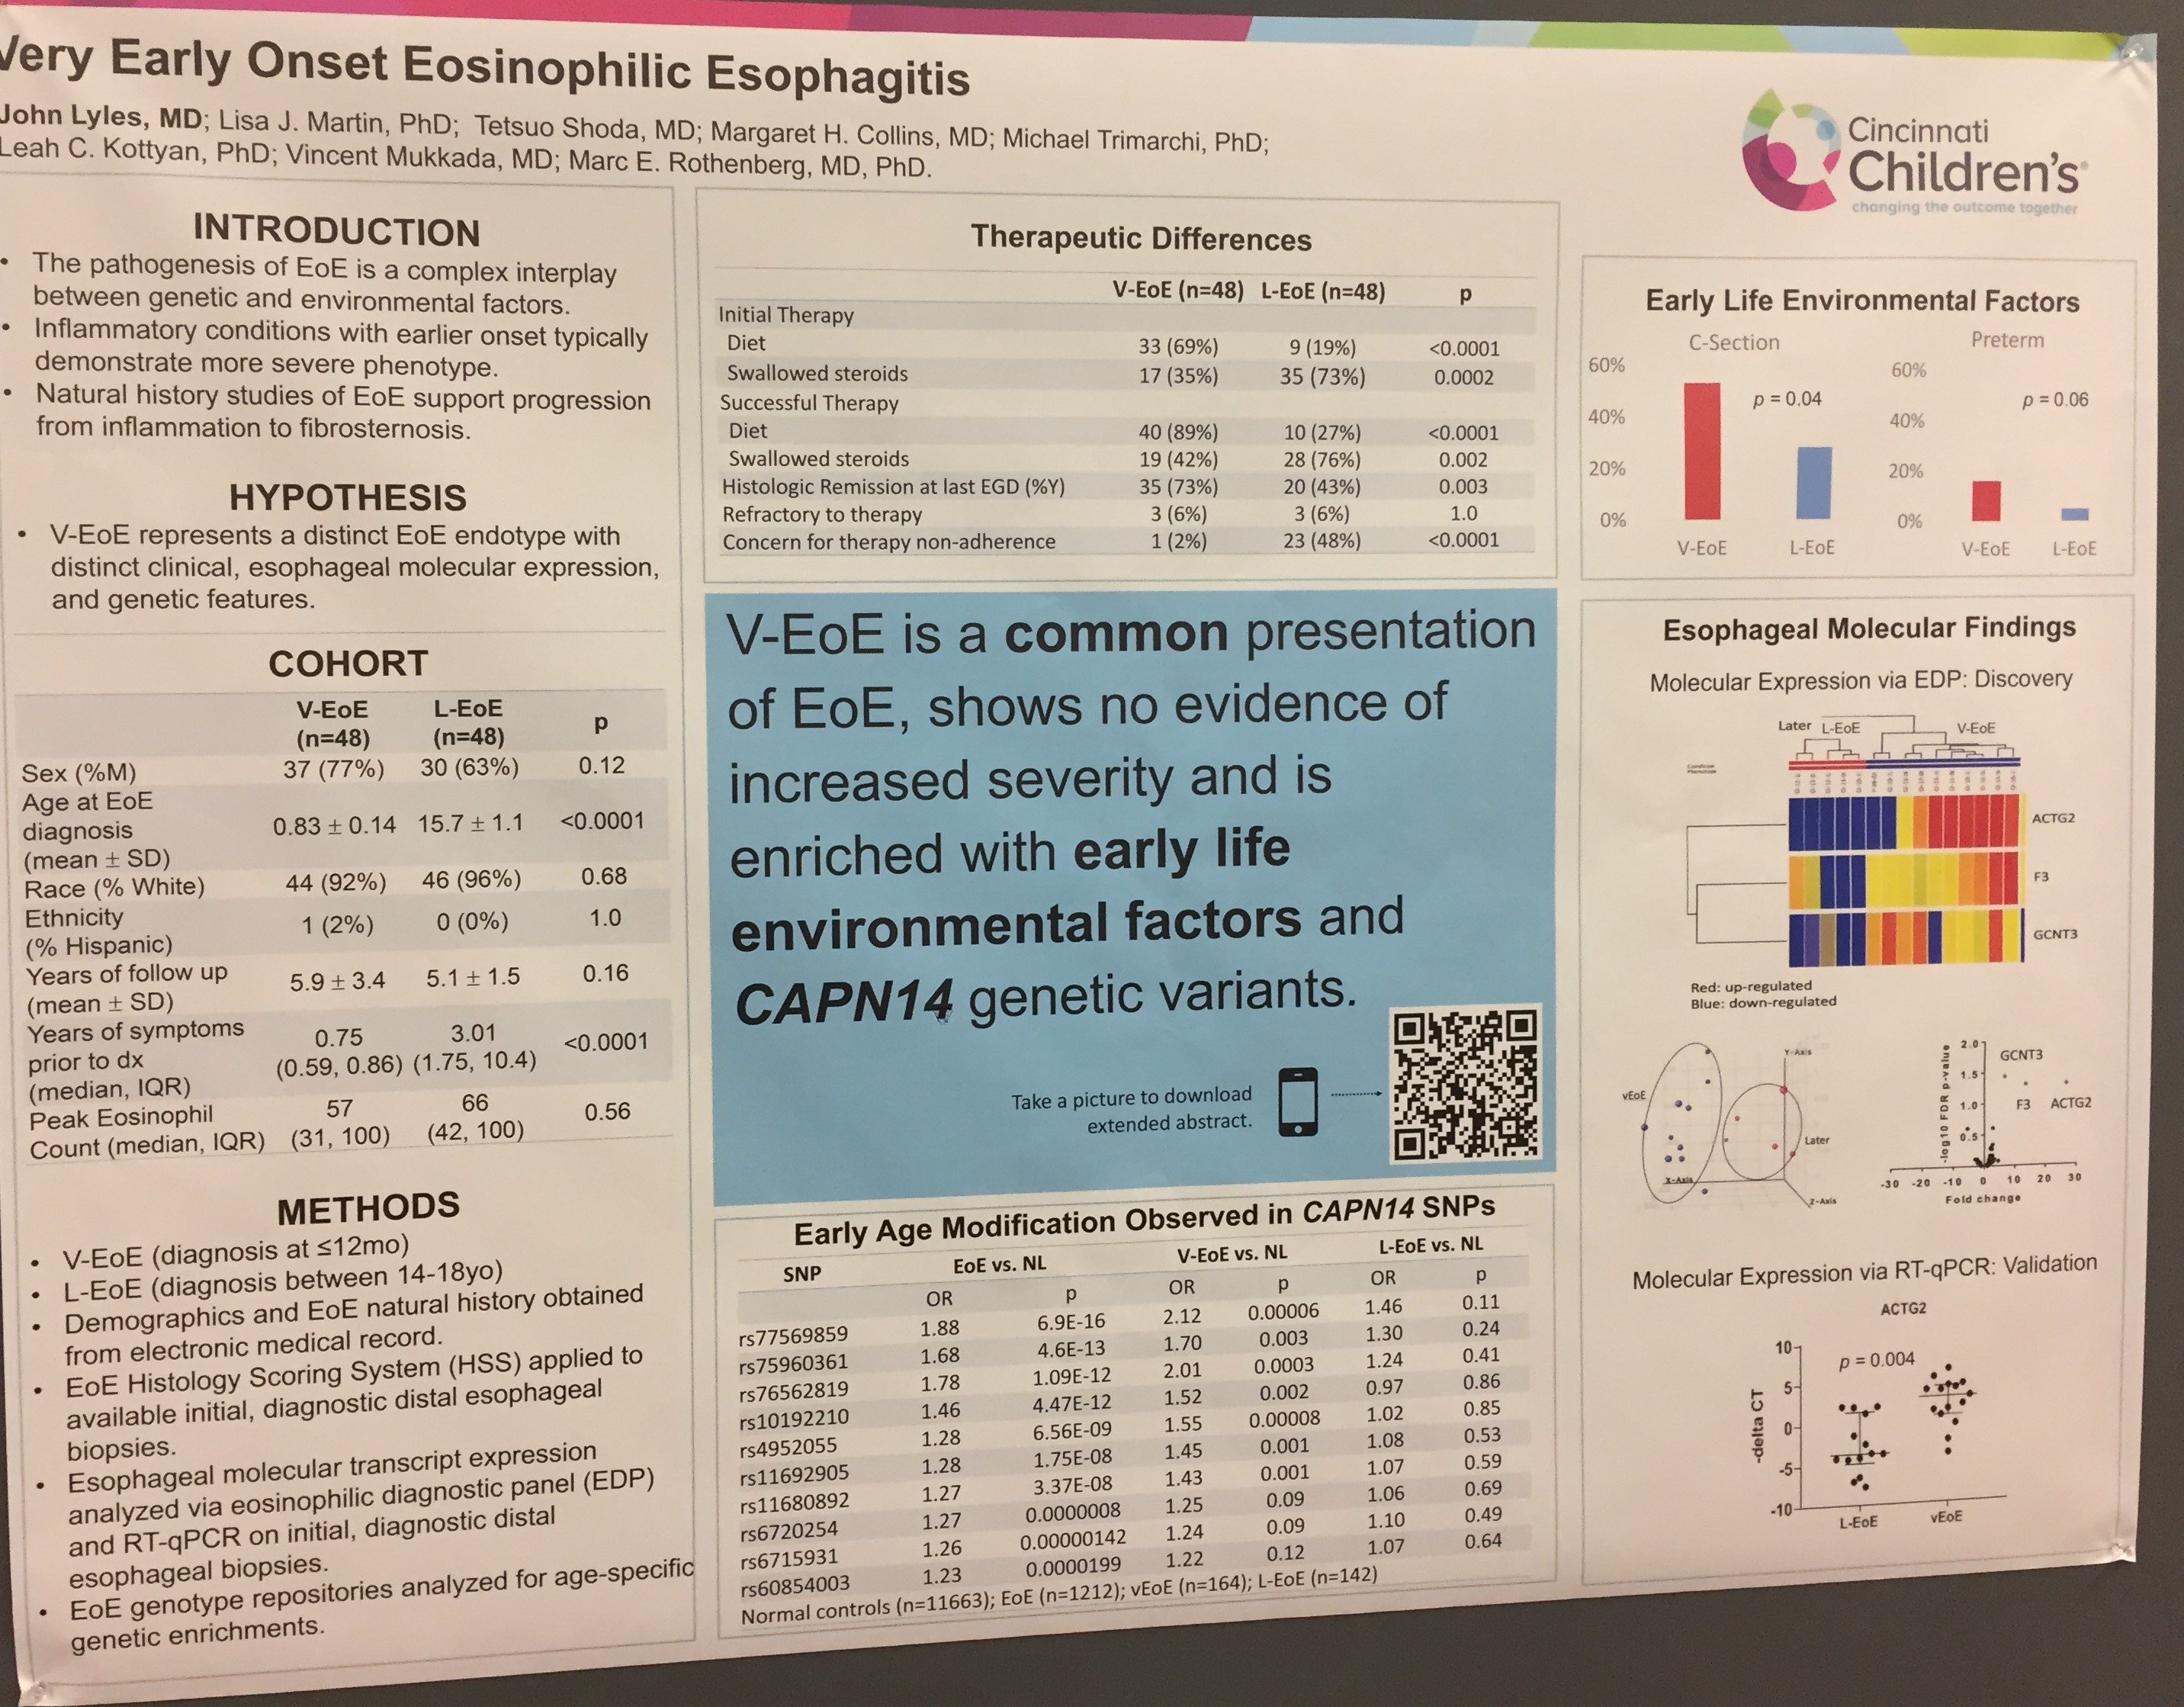
  2. 2nd poster describes very early-onset EoE

Inflammatory Bowel Disease:

  1. Use of infliximab in VEO IBD.  Used in 46/122 (38% of patients) and 50% had persistent use 3 years later

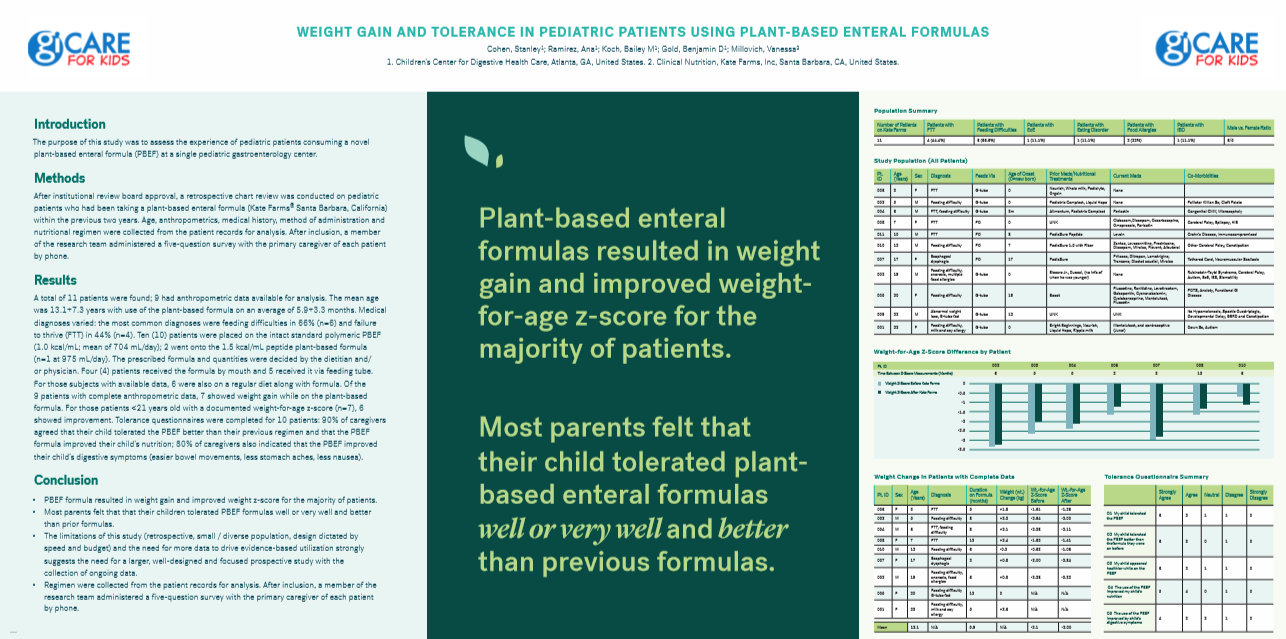
Enteral nutrition –poster from our group describing good tolerance of plant-based formula (with Ana Ramirez).

Celiac disease.  This poster indicates low yield of additional serology for celiac disease besides TTG IgA and serum IgA. This includes testing in young patients (< 2 years) with celiac disease.

Food-borne Outbreaks and Lack of FDA Transparency

A recent opinion piece from FoodSafetyNews highlights the lack of transparency from the FDA regarding food-borne outbreaks (several more listed below).

Bill Marler: Publisher’s Platform: A bit more about the FDA and lack of Transparency

Here’s an excerpt:

The Halloween disclosure of a multistate E. coli outbreak linked to romaine lettuce raises another concern about the FDA and transparency — the failure to disclose where consumers purchased the tainted product..

Under the Freedom of Information Act and Title 21 of the Code of Regulations, government agencies — and specifically, the FDA — are told to exempt trade secrets and commercial information from any of their releases…

Formulations, ingredients and how products are made are trade secrets.  Who supplied the tainted raw material, who made the tainted product and where the tainted product was sold are not a trade secrets – especially during an outbreak.  Simplicity, transparency and consistency allows for a visible supply chain and one that consumers can have confidence in. 

Recent outbreaks (thanks to colleague for these references):

Multistate Salmonella Outbreak Linked To Ground Beef Causes One Death, Eight Hospitalizations

  • Reuters (11/1, Maddipatla) reported, “A multistate outbreak of salmonella linked to ground beef has caused one death in California and eight hospitalizations, U.S. health officials said on Friday. A total of 10 people in six U.S. states were infected with a strain of the bacteria called Salmonella Dublin, according to the Centers for Disease Control and Prevention.”
  • TIME (11/2, Carlisle) reported, “Officials have not yet identified a single common source of the ground beef that is believed to be spreading the Salmonella Dublin based on epidemiological and laboratory evidence. According to the CDC, the sick individuals reported eating different brands of ground beef at different locations.”
  • CNN (11/1, Christensen) also reported the story.

Previously Undisclosed E. Coli Outbreak Linked To Romaine Lettuce Sickened Nearly Two Dozen People, FDA Says

  • The Washington Post (11/1, Brice-Saddler) reported, “A previously undisclosed E. coli outbreak linked to romaine lettuce sickened nearly two dozen people between July and early September, the Food and Drug Administration said Thursday – a delayed announcement one food safety lawyer called a ‘lie to the public in all respects.’” The piece added, “Illnesses associated with the outbreak infected 23 people across 12 states from July 12 to Sept. 8, according to the FDA. No patients died of their illnesses, and officials say there is no ongoing public health risk.”

Dozens more fresh vegetable products because of Listeria monocytogenes risk (11/4) (FoodSafetyNews.com)

  • A (Canadian) nationwide recall of freshcut vegetables continues to expand with dozens of products and multiple brands now on the list. Products potentially contaminated with Listeria monocytogenes are cole slaw, riced cauliflower, green beans, noodles, kale salads and more.  Some of the products do not expire for 10 days or more, so consumers and businesses are urged to check their supplies for the recalled products listed here by the Canadian government

My take: Food-borne illnesses cause 48 million cases in U.S. each year (CDC estimates) and 3000 deaths (MMWR 64:2, 2015). More transparency is needed.

Related blog post: Food Safety Lecture-It’s Still A Jungle Out There


In the News, New Cystic Fibrosis Study

More information related to today’s earlier post: In the News: Big Therapeutic Advance for Cystic Fibrosis

Abstract

BACKGROUND

Cystic fibrosis is caused by mutations in the gene encoding the cystic fibrosis transmembrane conductance regulator (CFTR) protein, and nearly 90% of patients have at least one copy of the Phe508del CFTR mutation. In a phase 2 trial involving patients who were heterozygous for the Phe508del CFTR mutation and a minimal-function mutation (Phe508del–minimal function genotype), the next-generation CFTR corrector elexacaftor, in combination with tezacaftor and ivacaftor, improved Phe508del CFTR function and clinical outcomes.

METHODS

We conducted a phase 3, randomized, double-blind, placebo-controlled trial to confirm the efficacy and safety of elexacaftor–tezacaftor–ivacaftor in patients 12 years of age or older with cystic fibrosis with Phe508del–minimal function genotypes. Patients were randomly assigned to receive elexacaftor–tezacaftor–ivacaftor or placebo for 24 weeks. The primary end point was absolute change from baseline in percentage of predicted forced expiratory volume in 1 second (FEV1) at week 4.

RESULTS

A total of 403 patients underwent randomization and received at least one dose of active treatment or placebo. Elexacaftor–tezacaftor–ivacaftor, relative to placebo, resulted in a percentage of predicted FEV1 that was 13.8 points higher at 4 weeks and 14.3 points higher through 24 weeks, a rate of pulmonary exacerbations that was 63% lower, a respiratory domain score on the Cystic Fibrosis Questionnaire–Revised (range, 0 to 100, with higher scores indicating a higher patient-reported quality of life with regard to respiratory symptoms; minimum clinically important difference, 4 points) that was 20.2 points higher, and a sweat chloride concentration that was 41.8 mmol per liter lower (P<0.001 for all comparisons). Elexacaftor–tezacaftor–ivacaftor was generally safe and had an acceptable side-effect profile. Most patients had adverse events that were mild or moderate. Adverse events leading to discontinuation of the trial regimen occurred in 1% of the patients in the elexacaftor–tezacaftor–ivacaftor group.

CONCLUSIONS

Elexacaftor–tezacaftor–ivacaftor was efficacious in patients with cystic fibrosis with Phe508del–minimal function genotypes, in whom previous CFTR modulator regimens were ineffective. (Funded by Vertex Pharmaceuticals; VX17-445-102 ClinicalTrials.gov number, NCT03525444. opens in new tab.)

In the News: Big Therapeutic Advance for Cystic Fibrosis

Washington Post: Long-Awaited Drug Could Turn Deadly Disease into Manageable Condition

An excerpt:

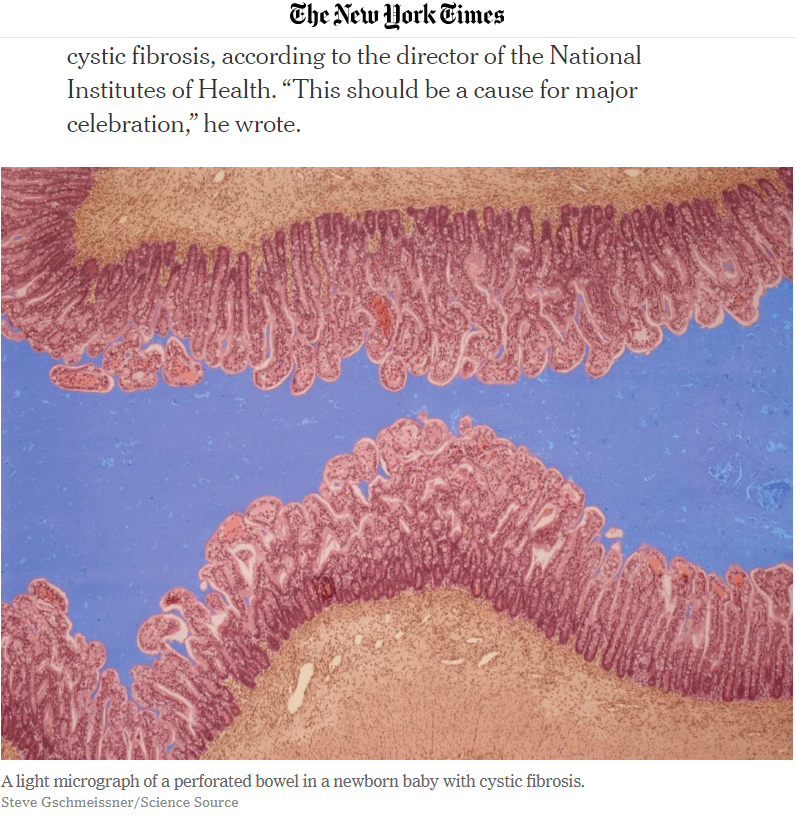
A new cystic fibrosis therapy dramatically improved patients’ lung function and showed clear signs of targeting the genetic root of the disease, instead of just alleviating symptoms — a breakthrough so long-sought that many doctors and patients are moved to tears when talking about it.

The data, being unveiled Thursday at a national conference in Tennessee and simultaneously published in two leading medical journals, was so persuasive that the Food and Drug Administration last week approved the three-drug combination, called Trikafta — five months ahead of the agency’s deadline. The drug could benefit 90 percent of patients with the disease, a major advance over previous drugs that worked in a tiny fraction of the people with the disease or had more modest effects…

Sarah Carollo, 28, a special needs teacher in Lee’s Summit, Mo., started Trikafta through a clinical trial in late 2018. Carollo… couldn’t walk down a hallway without stopping to rest and catch her breath…

A few days after she began taking the pill, her doctors tested her lung function and were so stunned at the improvement that they had to check whether they were really looking at the results from the right patient. Two weeks ago, Carollo ran a 5K race with another patient, Laurana Blackburn, who was also taking the drug through the clinical trial…

There are more than 1,700 gene mutations that can cause the protein to malfunction, but in the most common mutation, the protein is misfolded and can’t reach the right spot in the cell — and even if it does reach that spot, it doesn’t work properly. The new combination therapy includes one drug that corrects the misfolded protein and two that activate the correctly folded protein when it reaches the right spot in the cell.
In the largest trial, reported in the New England Journal of Medicine, 403 patients who had at least one copy of the most common gene mutation underlying cystic fibrosis received either Trikafta or a placebo. There were improvements in objective tests of lung function, decreases in lung problems and hospitalizations and an increase in people’s quality of life…

It also remains to be seen whether patients have an easy time gaining access to the drug, which will cost $311,000 a year. While that is a tremendous amount, orphan drugs for small patient populations typically carry very large price tags, and physicians are optimistic that insurers will cover the drug.
The NY Times reported on the FDA approval (October 2019), Studies Yield ‘Impressive’ Results in Fight Against Cystic Fibrosis, and noted that the “Institute for Clinical and Economic Review, which evaluates the cost-effectiveness of drugs, found that the cystic fibrosis drugs the company sells should cost as much as 77 percent less. ”