What happens when anti-TNF therapy is stopped

Another study (NA Kennedy et al. Aliment Pharmacol Ther 2016; 43: 910-23) has examined the issue of outcomes after anti-TNF therapy withdrawal among patients with inflammatory bowel disease.

This study included 166 UK patient cohort (117 with Crohn’s disease [median 31 yrs], 19 with ulcerative colitis [median 40 years]) as part of a retrospective observational study and a meta-analysis incorporating 11 further cohorts totalling 746 patients (624 with Crohn’s dissease, 122 with ulcerative colitis).

Key findings:

  • In the UK cohort, relapse rates were 36% at year and 56% at 2 years for Crohn’s disease
  • In the UK cohort, relapse rates were 42% at year and 47% at 2 years for ulcerative colitis
  • Increased relapse rates were noted for those with a diagnosis prior to age 22 years (hazard ratio (HR) 2.78), calprotectin >50 mcg/g (HR 2.95).
  • In meta-analysis, 1-year relapse rates were 39% for CD and 35% for UC/IBDU patients
  • Retreatment with anti-TNF was successful in 88% for CD and 76% of UC/IBDU patients

To understand this study, it is important to note some of the study criteria.  In the UK cohort, inclusion criteria required the patient to have had at least 12 months of ant-TNF therapy and be in corticosteroid-remission for at least 6 months.  In addition, the relapse rate is likely to be underestimated due to using a definition of relapse that required either commencement of steroids, immunomodulator or anti-TNF therapy.  The meta-anlaysis cohort studies also used clinical relapse rather than endoscopic or other objective markers.

My take: Relapse of clinical symptoms occur in about 40% after withdrawal in highly-selected groups who were doing well prior.  Significantly higher rates of endoscopic relapse are likely.  This study provides strong reasons for not interrupting therapy when it is working.

Related blog posts:

Cures Tshirt


How Likely is Reflux in Infants with “Reflux-like” Behaviors?

Another study (Funderburk et al. JPGN 2016; 62: 556-61) has shown that gastroesophageal reflux disease is infrequent in infants with a “strong clinical suspicion for reflux.”  This is a good to know since we also know that pharmacologic therapy for gastroesophageal reflux has not been proven to be effective in infancy either.

This retrospective study with 58 infants, including 40 preterm infants, evaluated for GERD with MII-pH studies.  Characteristics of cohort: median gestational age 31 weeks, median birth wt 1683 gm, and median age at study: 70 days. 10 patients were receiving acid suppression therapy.

Indications for testing:

  • Irritability 55%
  • Bradycardia  34%
  • Desaturation 31%
  • Cough 21%
  • Gagging 12%
  • Difficulty feeding 12%
  • Arching 10%
  • Apnea 5%

Key findings:

  • Only 6 infants (~10%) had abnormal MII-pH studies (defined as >95th percentile for reflux episodes/hours or >95th percentile for acid exposure time)
  • None of the symptom indices correlated with symptoms. SI, SSI, or SAP
  • The majority of reflux episodes did not correlate with clinical “reflux” behaviors
  • Small bore (5 Fr) NG tubes were not associated with increased reflux.

In the related commentary by Rachel Rosen (pgs 517-18), she noted that “there is little to no evidence to show that the 3 indices predict any meaningful clinical outcome…including response to fundoplication, or medications.” “The current literature fails to support the use of symptom indices to prove causality when resolution of symptoms with medical or surgical therapies is used as the criterion standard.”

My take: The vast majority of infants with “reflux behaviors” do not have reflux.  Even if they do, current pharmacologic therapies have not been shown to work.  So, there is little  value in reflux testing in most infants.  Finally, given the failure of symptom indices, does the addition of the impedance data to the pH data add any value?

Related blog posts:

Jerusalem Collage -Made from hundreds of postcards.  Vik Muniz

Jerusalem Collage -Made from hundreds of pictures/postcards. Look closely -it’s amazing.  by Vik Muniz

Another Rare Cause of Neonatal Diarrhea

A well-described case report (B Harter et al. JPGN 2016; 62: 577-80) provides a description of proprotein convertase 1/3 (PC1/3) deficiency. To date, only 21 cases have been reported.

Clinical features: congenital diarrhea and polyuria; normal endoscopy/histology. This patient required parenteral nutrition until 11 months of age. Her polyuria resolved at 13 months of age. Low serum levels of c-peptide and insulin along with elevated pro-insulin, combined with the polyuria, were suspicious for PC1/3 deficiency. This patient’s diagnosis was established with genetic analysis of the PCSK1 gene.

PC1/3 is responsible for peptide hormone processing in endocrine cells in the gut, and has targets in the hypothalamus and pancreas. Growth hormone deficiency, adrenal insufficiency, diabetes insipidus, and hypogonadism are commonly observed.

Related blog posts:

Gibbs Gardens

Gibbs Gardens

Should Medical Marijuana Get a Free Pass?

In many states, including Georgia, medical marijuana has bypassed the rigorous Food and Drug Administration (FDA) approval process via state laws permitting its usage.  A recent editorial (J Koliani-Pace, CA Siegel. Am J Gastroenterol 2016; 111: 161-62 -thx to Ben Gold for this reference) highlights the dilemma facing physicians with medical marijuana with regard to providing advice/approval for this treatment.

Key points:

  • 12% of people aged 12 years or older report using cannabis in the past year.
  • For gastrointestinal illnesses, there is scant evidence effectiveness.  There is some data indicating that it makes you feel better, but no data proving that there is objective improvement in conditions like Crohn’s disease.
  • Adverse effects require more research.  “Approximately 9% of people who experiment with marijuana will become addicted.”  Other concerns: increased car accidents, altered memory/judgment, hyperemesis syndrome, and respiratory effects.  With increasing availability and increasing THC concentrations, there have been in an increase in emergency department visits related to usage.
  • Lack of quality control: various concentrations of THC and cannabinoids, different administration routes, contaminants.

My take: At least with GI illnesses, more studies are needed to determine whether medical marijuana should be recommended.

Related blog posts:

Gibbs Gardens

Gibbs Gardens

Here’s Why Biologic Therapy for Crohn’s Helps Adolescents Grow

It is well-recognized that Crohn’s disease is associated with delays in the onset and progression of puberty with the potential for stunted growth, impaired bone accrual, and diminished quality of life.

Now, a study (MD DeBoer et al. J Pediatr 2016; 171: 146-52) shows that initiation of anti-tumor necrosis factor α (anti-TNFα) treatment results in a rapid increase in sex hormone and gonadotropin levels.

In 72 adolescents, this observational study followed levels of sex hormones, gonadotropin levels, dual-energy x-ray absorptiometry, along with cytokine/inflammatory markers at initiation of anti-TNFα therapy, at 10 weeks and at 12 months.

Key findings:

  • By week 10 , testosterone z scores in males increased from a median of -0.36 to 0.40 (P<0.05)
  • By week 10 , estradiol z scores in females increased from a median of -0.35 to -0.02 (P<0.01)

My take (from the authors): This study suggests that “systemic inflammation suppresses gonadotropin-stimulated production of sex hormones” and that treatment of this inflammation with anti-TNFα agents allows rapid resumption normal production.

Related blog posts:

Law Quad, Univeristy of Michigan

Law Quad, Univeristy of Michigan

Linking Reflux and Tooth Erosion

Every now and then a dentist sends a kid to our GI practice due to eroded teeth because of concerns about reflux damaging the enamel.  While it is recognized that reflux may damage teeth, the exact frequency is unclear.  Other questions:

  • Which asymptomatic kids with poor dentition require GI evaluation?
  • What is the best way to evaluate these children?
  • If reflux is identified, how long should they remain on treatment? Forever?
  • How effective is reflux treatment in reducing tooth damage?

While none of these questions have been definitely answered, Rosen et al (JPGN 2016; 62: 309-13) show that acid reflux rather than nonacid reflux is predictive of tooth erosion. In this study, the authors used a prospective cohort of 27 children (age ≥3 years)–ALL of them were ON acid suppression (for >1 year) at the time of pH-MII testing.  Key findings:

  • Prevalence of tooth erosion was 10 or 27 (37%)
  • There was correlation with acid reflux episodes (& time in reflux) and tooth erosion, r=0.44, P=0.02
  • There was correlation with reflux index as well, r=0.54, P=0.004,  In the tooth erosion group, the mean reflux index was 7.3% compared with 1.6% in no dental erosion group.
  • There was no correlation with nonacid reflux with tooth erosion

The authors’ discussion highlights many prior relevant studies and indicates that a pH-metry study alone (rather than pH-MII) “may be adequate.” They note some of the limitations of this study which included a small number of patients and potential referral bias, as these children had suspected GERD.  In the methods section, the authors state that their standard practice, at the time of the study, was to maintain patients on prior acid suppression medication.  It would be useful to acknowledge that many experts, at this time, recommend doing pH-MII studies as well as standard pH studies off all acid suppression due to improved sensitivity/accuracy.

My take: This study shows that in the 10 children with tooth erosion who had suspected GERD, there was correlation with acid reflux but not with nonacid reflux.

Related blog post: Notes from PPI Webinar GutsandGrowth

Unrelated but interesting: Are medical errors really the 3rd leading cause of death in U.S.? Here’s NPR’s summary of a recent BMJ article which makes that claim: Only Heart Disease and Cancer Exceed Medical Errors As Cause of U.S. Death

Gibbs Gardens

Gibbs Gardens


Here’s What I Really Want to Know about an MRE Study –What is the Correlation with PGA?

A nice pediatric study (CG Sauer et al. JPGN 2016; 62: 378-83) provides data on 101 children from a single center who underwent MRE to evaluate their Crohn’s disease.  This study was a retrospective chart review using a prospectively maintained MRE database.  All of the children in this study underwent MRE greater than 180 days after diagnosis.  MRE was ordered at the discretion of the treating gastroenterologist. Median followup was 2.8 years after MRE.

Key findings:

  • MRE correlated with meaningful clinical outcomes. Of the 65 with active inflammation on MRE, only 44.6% achieved clinical remission (another 30% progressed to mild disease activity). Of the 36 without active inflammation, 88.9% achieved clinical remission.
  • Children with active inflammation on MRE were more likely to undergo surgery (18.5% vs. 2.8%) and more likely to have medication changes (44.6% vs. 8.3%).

While this population may have had more disease than those who did not undergo MRE (since it was done at the discretion of gastroenterologist), what would interest me would be the correlation with the physician global assessment.  A rough calculation would suggest that only 40% of these patients achieved a clinical remission which is well below ImproveCareNow reported benchmarks, but not much different from previous studies using objective markers.  Furthermore, it would be of interest to look at whether individual clinicians incorporated their abnormal MREs into their assessment of PGA.  If the patient was doing well clinically but their MRE was markedly abnormal or even mildly abnormal, were these patients classified as in remission or otherwise.

My take: MRE is an excellent & expensive tool to assess for mucosal healing.  As our treatments continue to improve, MRE will be useful to monitor our progress.  How we incorporate our objective markers with our clinical markers needs further work.

Related blog posts:


ERAS -Enhanced Recovery After Surgery

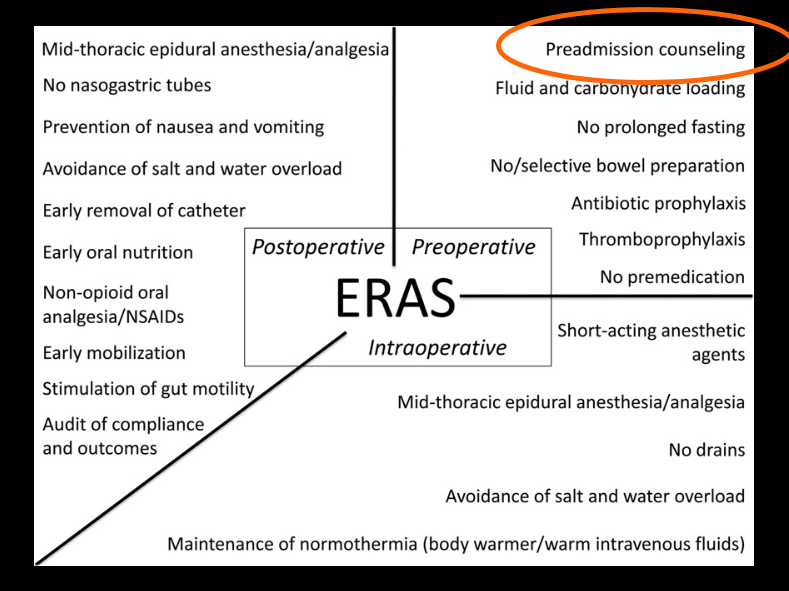
Fortunately, only a small number of children need colorectal surgery.  For those who do need this surgery, there are advancements which are helping to reduce length of stay and shorten recovery.  Some of the concepts with “Enhanced Recovery After Surgery” or ERAs have been around for more than 10 years.  One of our surgical colleagues, Dr. Kurt Heiss, described his experience in applying these techniques in the pediatric population and was kind enough to share his slides.  Slide 10 (see below) outlines the key points.

The immediate challenge in improving the quality of surgical care is not discovering new knowledge, but rather how to integrate what we already know into practice –Urbach DR, Baxter NN, BMJ 2005

Preoperative:

  • Counseling family
  • Avoid bowel prep –>can lead to bowel edema
  • Avoid prolonged fast prior to surgery.  Fluid/carbohydrate loading
  • Use of Neurontin preoperative
  • Antibiotic prophylaxis
  • Thromboprophylaxis

Intraoperative:

  • Short-acting anesthetics
  • Use of TAP and/or short-term epidural. Avoid narcotics
  • Avoid excessive fluid administration
  • No drains
  • Maintenance of normothermia

Postoperative:

  • Early feeding (same night)
  • No NG
  • Avoid/minimize narcotics
  • Early mobilization

ERAS: leads to shorter length of stay, reduced nonsurgical complications and no increase in readmission rates.

Resources:

My take: ERAS concept/team approach is leading to better outcomes.  GI surgery is likely to benefit more than other areas due to the often-slow recovery of the GI tract after operations.

Screen Shot 2016-04-25 at 5.00.40 PM

CCFA Conference Notes 2016 (part 5) -Emerging Therapies

This blog entry has abbreviated/summarized this terrific presentation; most of the material has been covered in this blog in prior entries (can use search function to find additional relevant material) but still this was a useful review. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.

Emerging Therapies in IBD –Dr. Gary Lichtenstein

Background: This lecture started with a review of current therapies. We have learned how to use our current therapies better. There still remain a large number of patients that face surgery with IBD; though there has been improvement (?50% reduction).

Issues with thiopurines were reviewed. May take 2-6 months to take effect, though monotherapy with thiopurines are fairly ineffective for Crohn’s disease as initial therapy.

Leukocyte Trafficking Agents:

  • Natalizumab
  • Vedolizumab
  • AJM300 –oral agent. Initial safety data were fine.
  • AMG 181
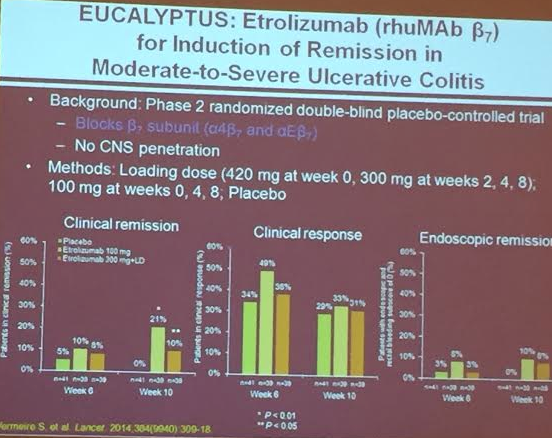
  • Etrolizumab (Vermeire S Lancet 2014) –low rates of endoscopic healing, but better than placebo

Screen Shot 2016-04-17 at 12.15.26 PM

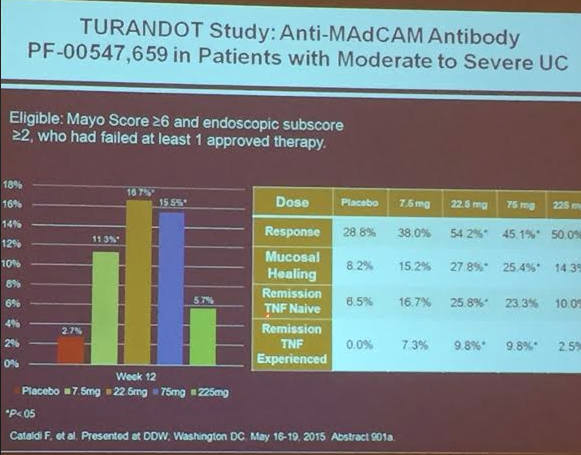
PF-00547,659

Screen Shot 2016-04-17 at 12.15.52 PM

S1P Modulators:

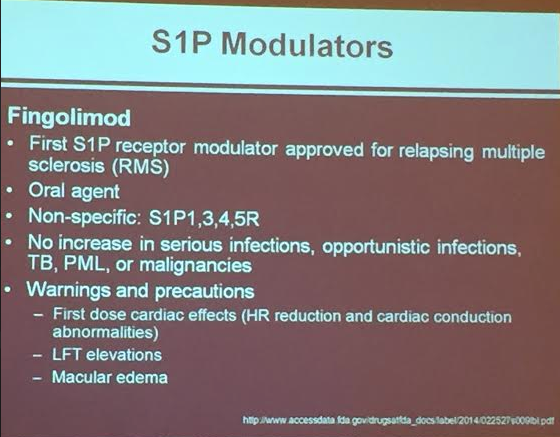
Fingolimod

Screen Shot 2016-04-17 at 12.16.26 PM

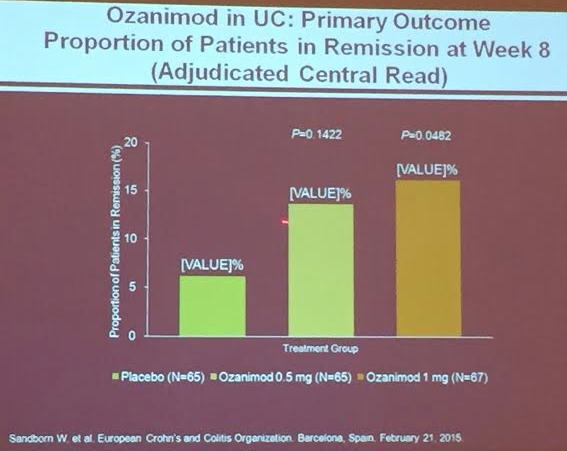
Ozanimod (RPC1063) (oral agent, fairly rapid onset) causes S1P-r on lymphocytes to be internalized –more selective than Fingolimod. Good safety has been noted thus far.  No notable cardiac problems. Infrequent elevations of transaminases; this issue will need to be followed.

Screen Shot 2016-04-17 at 12.16.38 PM

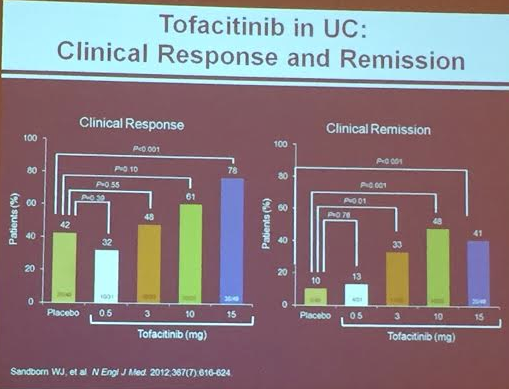
Tofacitinib oral Janus Kinus (JAK) Inhibitor (Sanborn WJ et al. NEJM 2012; 367: 616-24). Dr. Lichtenstein thinks 10 mg will be recommended dose. Follow lipids. For UC

Screen Shot 2016-04-17 at 12.17.11 PM

Mongerson related post: Mongerson -Phase II Data Available in NEJM | gutsandgrowth


Ustekinumab

Screen Shot 2016-04-17 at 12.18.05 PM

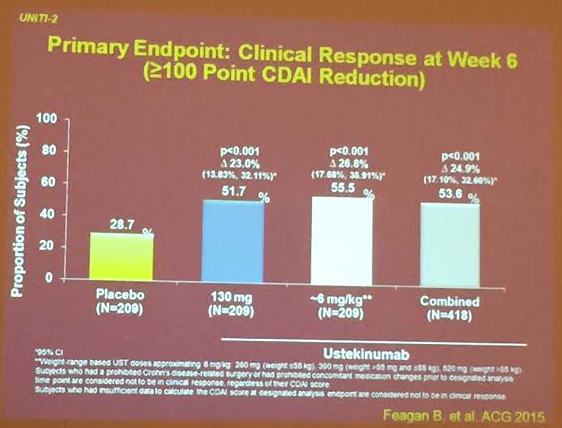
Related article from GI & Hep News: Ustekinumab for complex Crohn’s from ECCO conference/UNITI-1 Study (n=741)

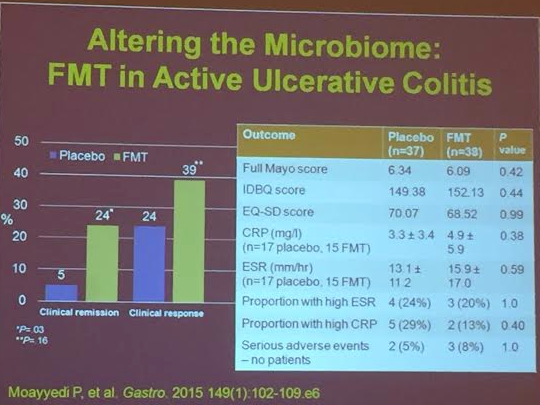
FMT.  Further studies are needed

Screen Shot 2016-04-17 at 12.18.17 PM

CCFA Conference Notes 2016 (part 3) -Malignancy and IBD

This blog entry has abbreviated/summarized this terrific presentation; most of the material has been covered in this blog in prior entries but still this was a useful review. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.

3rd Lecture: Prevention and management of malignancy in IBD –Dr. Thomas Ullman

Malignancy risk (colorectal cancer [CRC]) is present with prolonged ulcerative colitis, though more recent studies have shown lower risk than in the past –not much higher than the general population.

Screen Shot 2016-04-17 at 12.02.04 PM

  • CRC surveillance–colonoscopy monitoring after 8-10 years. Typically colonoscopy every other year for most patients, every year in higher risk patients (eg. PSC).

Screen Shot 2016-04-17 at 12.01.37 PM

  • Unclear if chemoprevention is effective (5-ASA, thiopurines, others).
  • Chromoendoscopy “has not been consensus on its use in our field (yet).” It is time consuming and expensive and unclear if it will improve outcome.

Does medical therapy for IBD predispose to developing cancer?

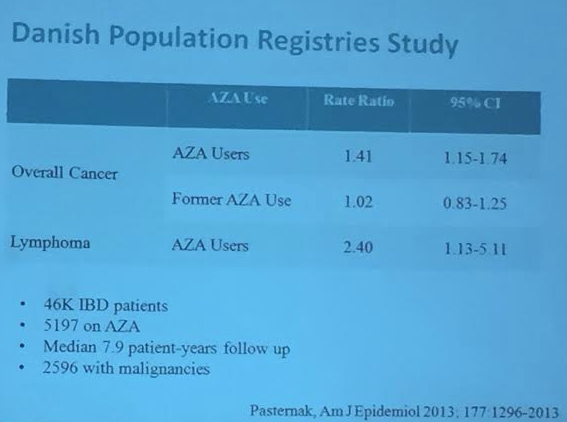
  • Thiopurines increase the risk of malignancy. (Pasternak et al) though the risk returns to near baseline when stopped according to study below.

Screen Shot 2016-04-17 at 12.03.27 PM

  • No overall increased risk with anti-TNF agents with RCTs (may not follow patients long enough) but also not seen in Danish registry either (JAMA study)
With Anti-TNFs

No increased risk of malignancy in this study with Anti-TNFs

  • Lymphoma risks: age, immunodeficiency, EBV
  • EBV negative are at risk for HLH with thiopurines
  • HTSCL ~200, >90% men and >90% <35 years. NOT EBV-related. Has not been identified in anti-TNF monotherapy.

Screen Shot 2016-04-17 at 12.02.55 PM

  • Skin cancer –main concern is in non-melanoma skin cancer (possibly melanoma too). Skin cancer increase has not been noted with methotrexate. Prevention: Skin care, and annual dermatology visits.
  • Cervical cancer—likely increased risk in IBD, probably due to thiopurine exposure and reduced immune surveillance. Prevention: HPV vaccination, Pap testing.
  • Urinary Tract cancers –especially in those >65 years with thiopurine exposure