Liver Shorts: Malnutrition in Biliary Atresia, Cholestasis with ECMO, Impaired Cognition After Pediatric Liver Transplantation

JM Boster et al. Liver Transplantation 2022; 28: 483-492. Malnutrition in Biliary Atresia: Assessment, Management, and Outcomes Good review article. Malnutrition and sarcopenia negatively impact pretransplant, peritransplant, and posttransplant outcomes and survival in children with BA.

E Alexander et al. JPGN 2022; 74: 333-337. Clinical Implications for Children Developing Direct Hyperbilirubinemia on Extracorporeal Membrane Oxygenation Key findings: 36/106 (34%) children developed direct hyperbilirubinemia (DHB) on ECMO. Illness acuity scores were significantly higher in the DHB group on ECMO day 2 (P = 0.046) and day 7 (P = 0.01). Mortality rate was higher in the DHB group 72%, versus 29% in the control group (P < 0.001).

A Ostensen et al. J Pediatr 2022; 243: 135-141. Open Access: Impaired Neurocognitive Performance in Children after Liver Transplantation In this study with 65 participants, key findings:

  • Compared with the patients who underwent transplantation a age >1 year (n = 35), those who did so at age <1 year (n = 30) had a lower FSIQ (87.1 ± 12.6 vs 96.6 ± 13.8; P = .005) and lower verbal comprehension index (87.3 ± 13.8 vs 95.4 ± 13.0; P = .020).
  • Transfusion of >80 mL/kg (P = .004; adjusted for age at transplantation: P = .046) was also associated with detrimental effects on FSIQ.
  • No difference in IQ between tests was found in those patients tested more than once, indicating no significant improvement with more time after transplantation (first testing was at median of 4.1 years after transplantation and the second testing was at a median age of 6.7 years after transplantation)
  • “Our findings indicate that transplantation at early age has a pronounced effect on later neurocognitive impairment, and that this effect is separate from and more pronounced than the effect of cholestasis before transplantation.”

Related blog posts:

Onion Headline:
Withdrawal of Chronic Hepatitis B Therapy

G Hirode et al. Gastroenterol 2022; 162: 757-771. Off-Therapy Response After Nucleos(t)ide Analogue Withdrawal in Patients With Chronic Hepatitis B: An International, Multicenter, Multiethnic Cohort (RETRACT-B Study)

Methods: This cohort study included patients (n=1552) with virally-suppressed chronic hepatitis B (CHB) who were hepatitis B e antigen (HBeAg)–negative (and without advanced liver disease) and stopped nucleos(t)ide analogue (NA) therapy

Key findings:

  • Cumulative probability of HBsAg loss was 3.2% at 12 months and 13.0% at 48 months of follow-up
  • HBsAg loss was higher among Whites (vs Asians: subdistribution hazard ratio, 6.8; P < .001) and among patients with HBsAg levels <100 IU/mL at end of therapy (vs ≥100 IU/mL: subdistribution hazard ratio, 22.5; P < .001)

My take: This study identifies subsets with HBeAg-negative CHB who may benefit from NA therapy cessation.

Related blog posts:

Endoscopic Assessment of Eosinophilic Gastritis

I Hirano et al. Am J Gastroenterol 2022; 117: 413-423. Prospective Endoscopic Activity Assessment for Eosinophilic Gastritis in a Multisite Cohort Thanks to Ben Gold for this reference.

Methods: Endoscopic features were prospectively recorded (n=65) using a system specifically developed for EG, the EG Endoscopic Reference System (EG-REFS)

Key findings:

  • The most common endoscopic findings were erythema (72%), raised lesions (49%), erosions (46%), and granularity (35%); only 8% of patients with active histology (≥30 eosinophils/high-power field) exhibited no endoscopic findings
  • A strong correlation between EG-REFS scores and physician global assessment of endoscopy severity was demonstrated (Spearman r = 0.84, P < 0.0001)
  • EG-REFS severity was significantly correlated with active histology, defined by a threshold of ≥30 eosinophils/high-power field (P = 0.0002).

My take: This reference has a ton of terrific pictures (48 for Figure 1) which showcase the wide variety of endoscopic findings (unfortunately these are behind a paywall). Overall, the study lays the groundwork for scoring the severity of EG and for serial assessments.

Related blog posts:

 Ristras are the strings of chile you see hanging along fences,
on patios and on portals all over New Mexico

Quality Forum: Understanding Food Allergy Testing (Part 2) & Atopic Dermatitis

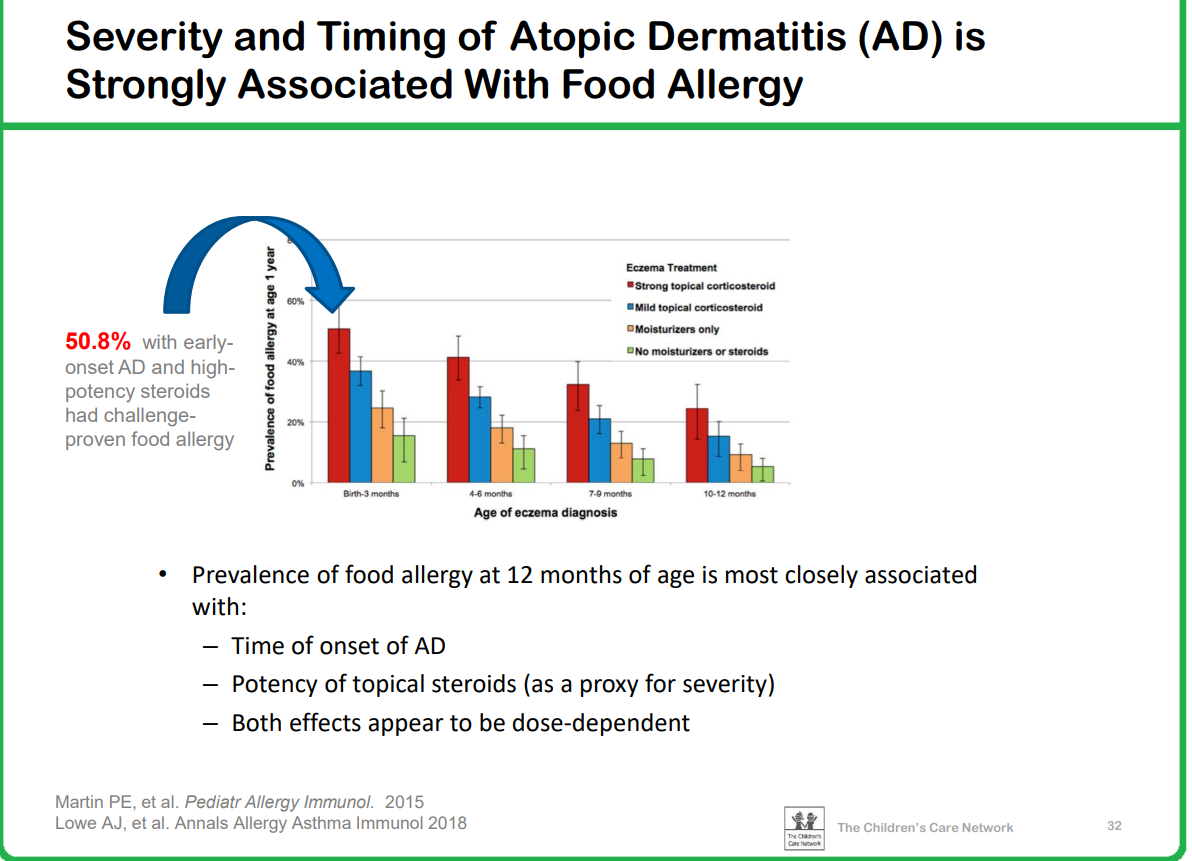
The Children’s Care Network (in Atlanta) has recently shared its Spring 2022 Clinical Quality Forum. Following is the link to the video recording. The poll during the live presentation is not active for the recording.

​Some of the slides that I think are most helpful ​are shown below (used with permission).  This 2nd part of content is from Dr. Brian Vickery which describes ​the relationship of atopic dermatitis to food allergy and best practices for prevention of food allergy:

ASCIA Handouts:

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Quality Forum: Understanding Food Allergy Testing (Part 1)

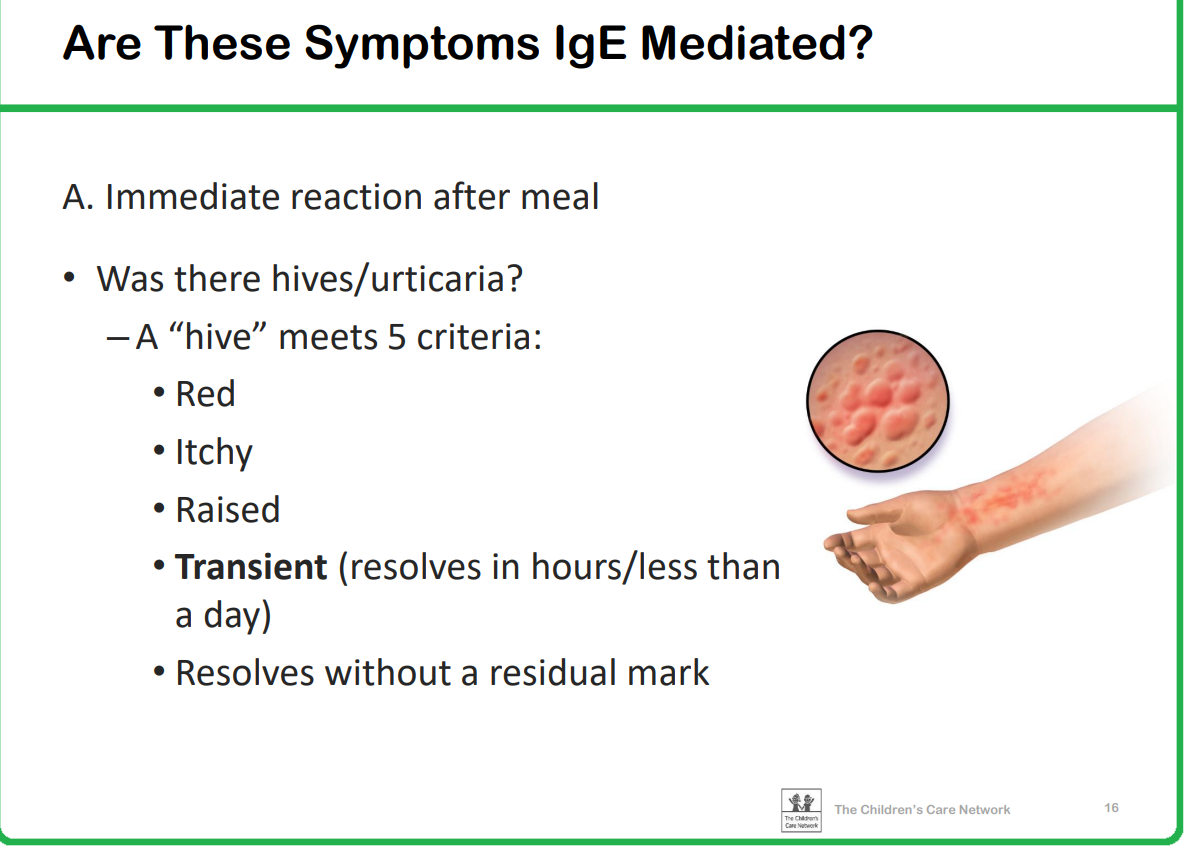
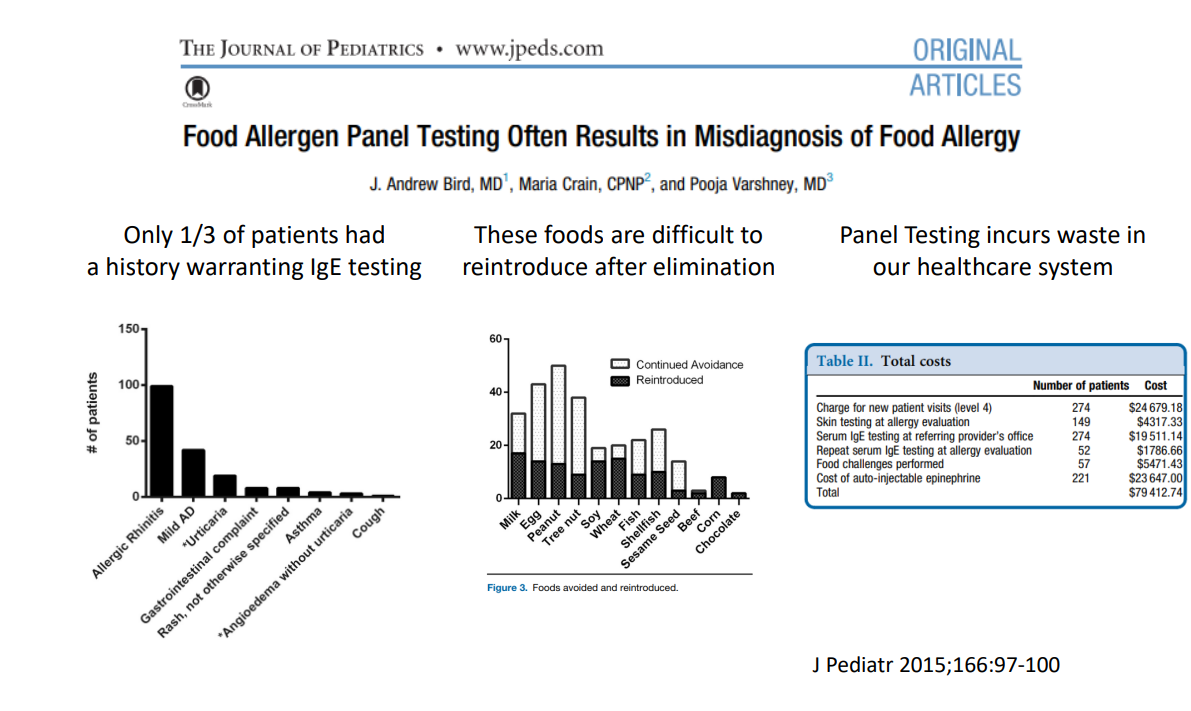
The Children’s Care Network (in Atlanta) has recently shared its Spring 2022 Clinical Quality Forum. Following is the link to the video recording. The poll during the live presentation is not active for the recording.

Some of the slides that I think are most helpful are shown below (used with permission). The first part of content is from Dr. Gerry Lee which describes best practices for selecting patients for Food Allergen IgE testing:

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Tired of Seeing This Headline

The Onion has used the same headline 21 times since 2014. The article was first published on May 27, 2014, following the Isla Vista killings.

Milwaukee, El Paso, Dayton,

Related blog posts:

Update on Esophageal Motility Disorders

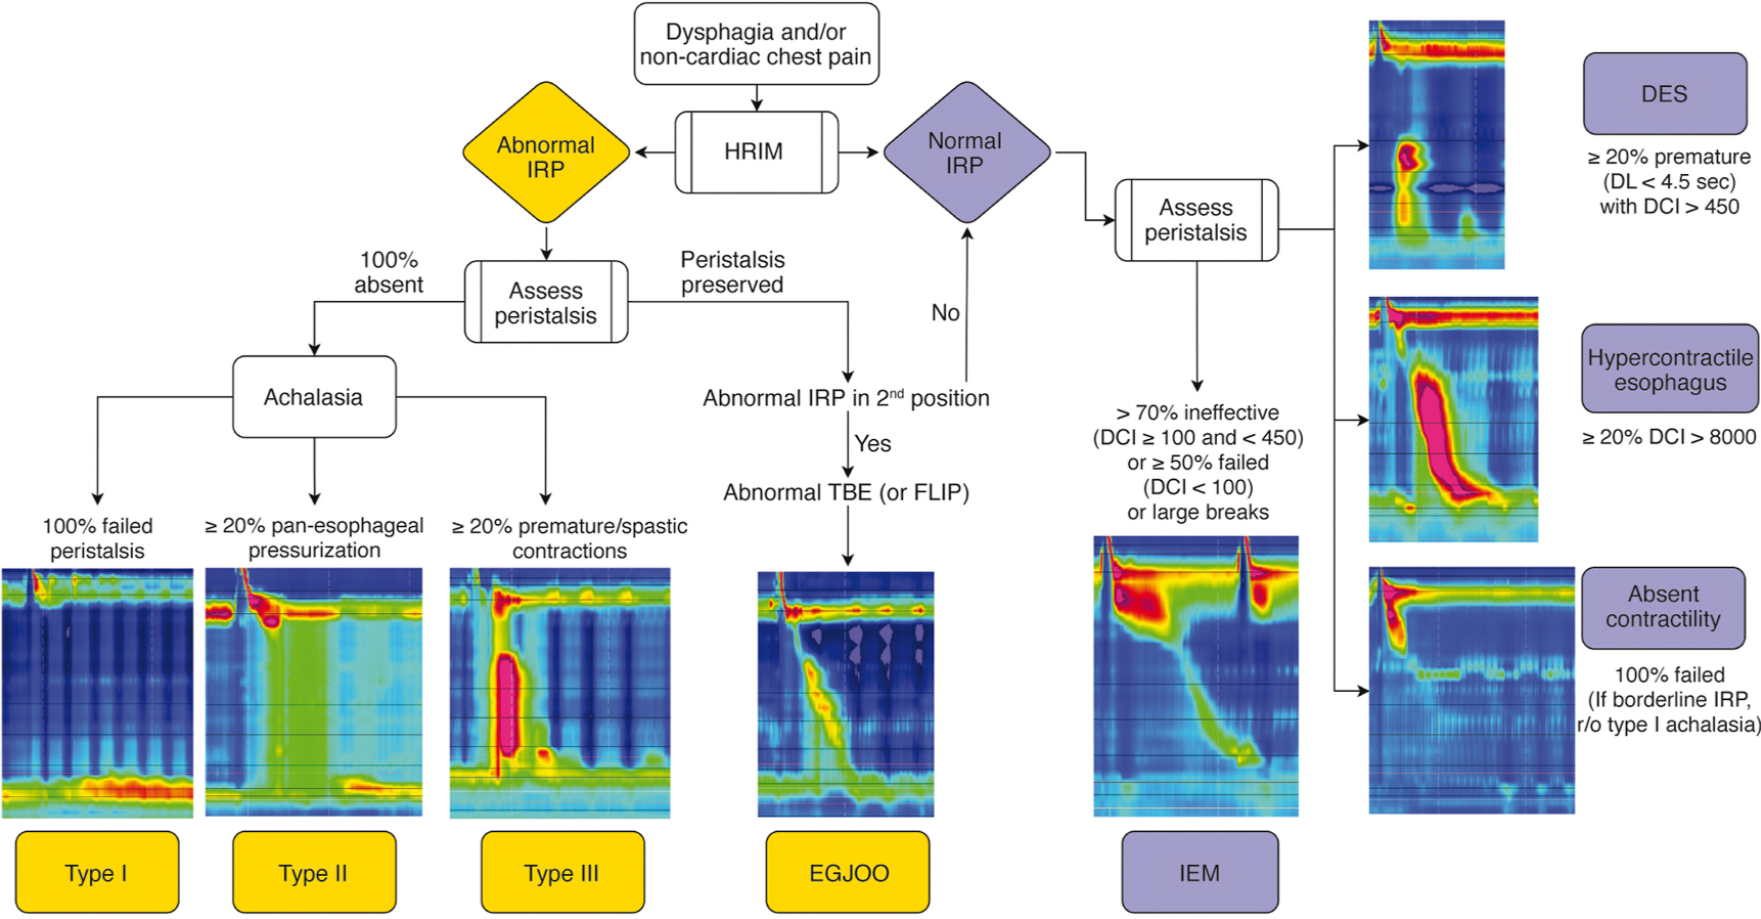
DA Patel et al. Gastroenterol 2022; 162: 1617-1634. Open Access: Esophageal Motility Disorders: Current Approach to Diagnostics and Therapeutics

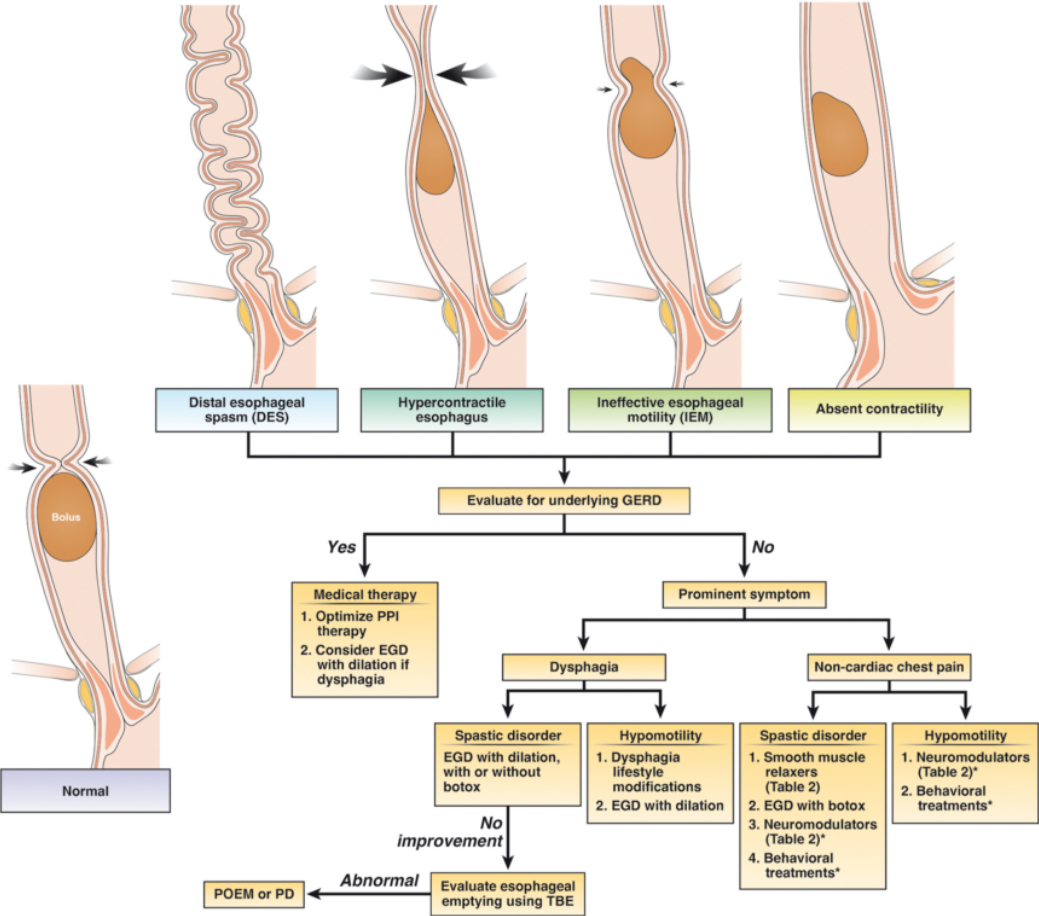
Manometric classification of various esophageal motility disorders
based on CC v4.0. HRIM, high-resolution impedance manometry
Treatment options in patients with disorders of esophageal peristalsis after a careful endoscopy is performed to rule out a mechanical or mucosal disease (such as eosinophilic esophagitis
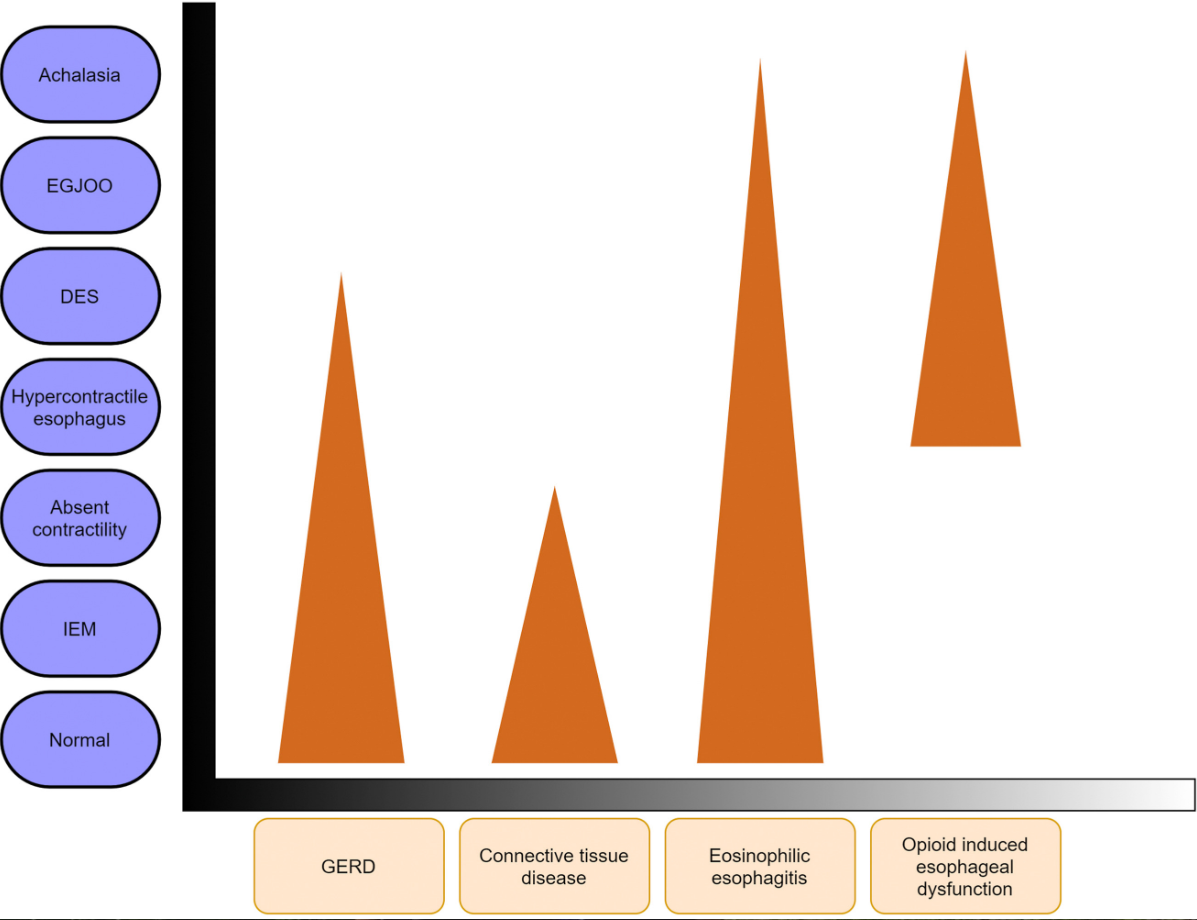
Impact of mucosal diseases, opioids, and connective tissue disease on esophageal motility. Figure shows presence of various secondary motility abnormalities, and the triangle indicates visual approximations of the prevalence of those motility abnormalities with each disease state. Most patients will have normal motility testing.

Eosinophilic Colitis Is Not a Typical EGID or IBD

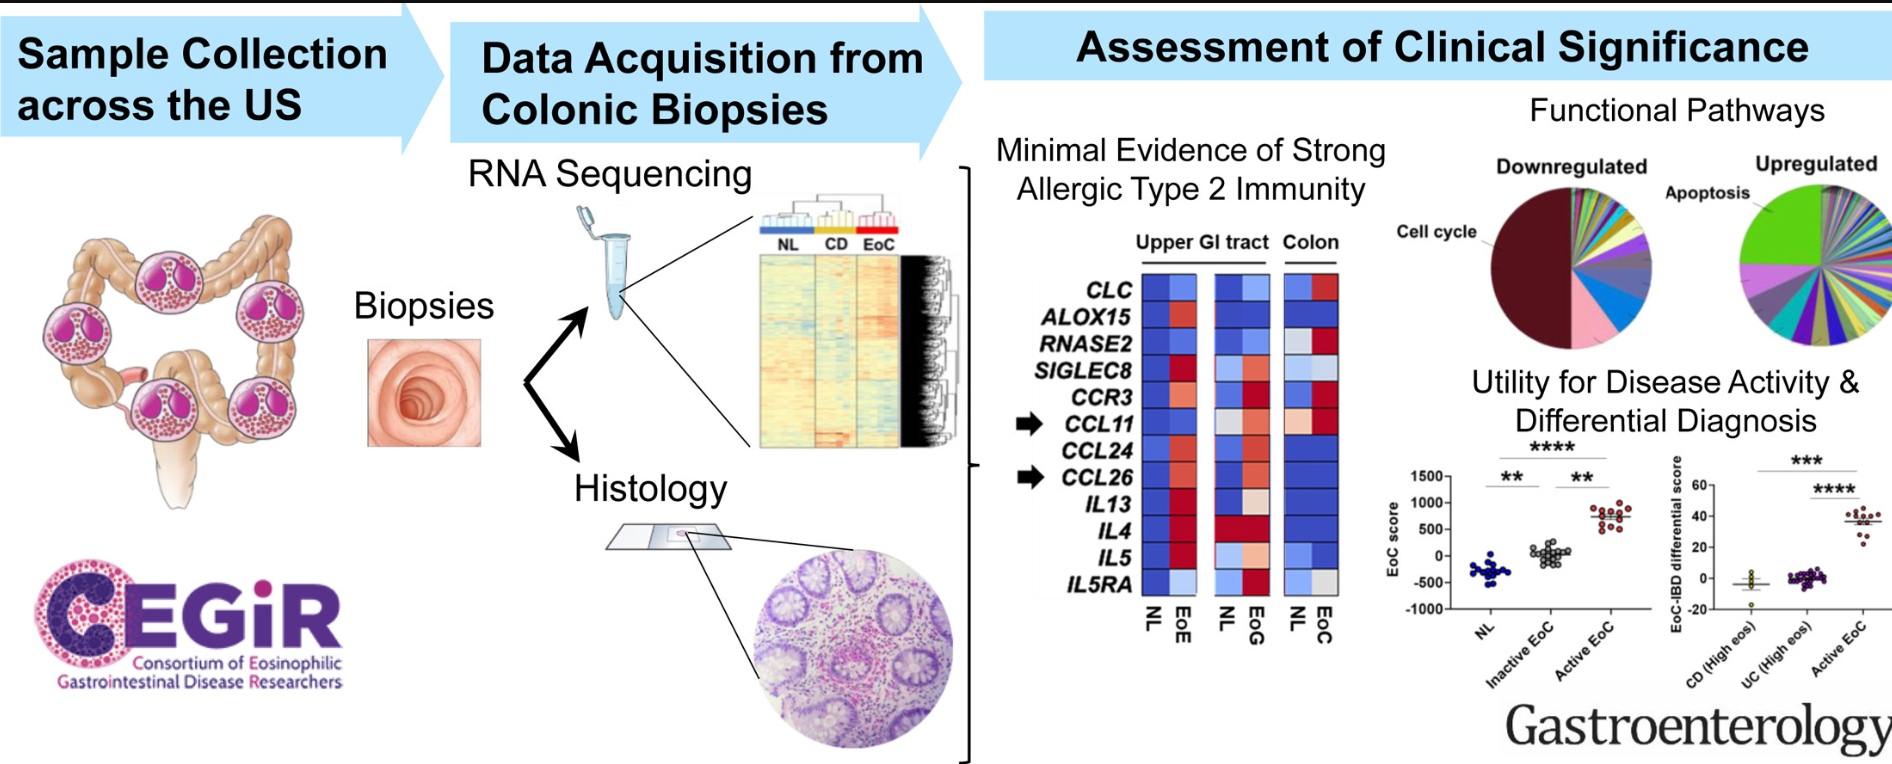
T Shoda et al. Gastroenterol 2022; 162: 1635-1642. Open Access: Evaluating Eosinophilic Colitis as a Unique Disease Using Colonic Molecular Profiles: A Multi-Site Study

Methods: Subjects with EoC (n = 27) and controls (normal [NL, n = 20], Crohn’s disease [CD, n = 14]) were enrolled across sites associated with the Consortium of Eosinophilic Gastrointestinal Disease Researchers. EoC was diagnosed as colonic eosinophilia (ascending ≥100, descending ≥85, sigmoid ≥65 eosinophils/high-power field) with related symptoms. Colon biopsies were subjected to RNA sequencing.

Key findings:

  • Among EoC and other EGIDs, there was minimal transcriptomic overlap and minimal evidence of a strong allergic type 2 immune response in EoC compared with other EGIDs
  • EoC transcriptome–based scores were reversible with disease remission and differentiated EoC from IBD, even after controlling for colonic eosinophil levels (P < .0001)

My take: The study indicates that eosinophilic colitis is likely unrelated to other eosinophilic GI disease and is likely unrelated to inflammatory bowel disease.

Related blog posts:

Position Paper for Pediatric Breath Testing

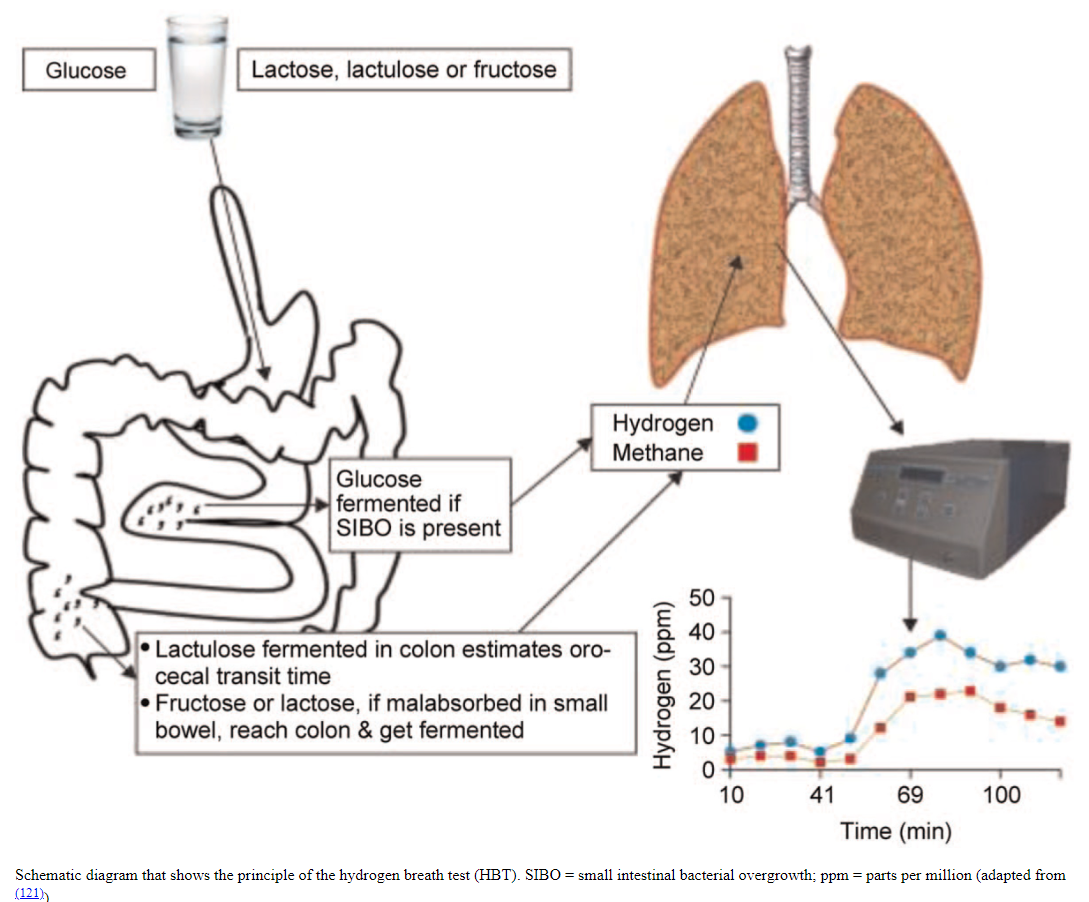
IJ Broekaert et al. JPGN 2022; 74: 123-127. Open access: An ESPGHAN Position Paper on the Use of Breath Testing in Paediatric Gastroenterology

This is a good article which provides pediatric dosing of breath testing agents and important considerations in methodology and interpretation. In addition, there are 22 graded recommendations (see below) –some may be surprising. For example, the breath testing is NOT recommended for diagnosis of H pylori but is recommended for determination of eradication therapy.

Related blog posts:

IBD Shorts: Pediatric Cost Savings with Biosimilars and Multiple Biosimilar Switch Data

GA Morris et al. Inflamm Bowel Dis 2022; 28: 531-538. Increasing Biosimilar Utilization at a Pediatric Inflammatory Bowel Disease Center and Associated Cost Savings: Show Me the Money

Key findings:

  • Biosimilar utilization initiation increased from a baseline of 1% in June 2019 to 96% by February 2021 among eligible patients; 20% of all patients (n-98) had insurance which preferred originator product
  • Estimated cost savings over the project duration were nearly $381,000 (average sales price) over the 20 month study

My take: The introduction of biosimilars have resulted in huge cost savings. In addition, for infliximab, the originator product price has also dropped substantially (more than 60% in some locations)

J Hanzel et al. Inflamm Bowel Dis 2022; 28: 495-501. Open Access: Multiple Switches From the Originator Infliximab to Biosimilars Is Effective and Safe in Inflammatory Bowel Disease: A Prospective Multicenter Cohort Study 

Methods: This was a prospective multicenter cohort study of adult IBD patients (n=176) who underwent 2 switches from the originator IFX to CT-P13 to SB2 (group 1), 1 switch from CT-P13 to SB2 (group 2), and 1 switch from the originator IFX to CT-P13 (group 3).

Key findings:

  • At 12 months after the most recent switch 76.9% (40 of 52, group 1), 65.7% (46 of 70, group 2) and 76.9% (20 of 26, group 3) of patients were in clinical remission. Treatment persistence at 12 months was 85.0%, 87.0%, and 70.1%, respectively.
  • There were no significant differences in the rate of clinical, CRP, FC remission, or treatment persistence at 12 months between the 3 groups.

My take: This study did not identify detrimental effects from multiple successive switching and switching between biosimilars of IFX. Longer followup and more clinical experience will be needed to confirm these findings.