For Policy Wonks: Bayh-Dole Act and Reducing Pharmaceutical Costs

AB Engelberg et al. NEJM 2022; 386: 1104-1106 (Commentary). A New Way to Contain Unaffordable Medication Costs — Exercising the Government’s Existing Rights

This commentary notes that the National Institutes of Health (NIH) spends more than $40 billion each year to fund biomedical research. “We believe that medicines discovered at public expense should be affordable.”

A Few Excerpts:

  • “Existing laws provide two paths for achieving this result. First, the Bayh–Dole Act of 1980 gives the government a royalty-free license to use patented inventions that were discovered using federal funding. The government has never exercised its Bayh–Dole license”
  • “Second, 28 U.S. Code §1498, which dates to 1910, gives the government immunity from being sued for patent infringement in federal courts, while giving patent owners the right to receive reasonable compensation when the government makes or uses a patent-protected product”
  • Case in point: “Recently, the government signed a contract with Merck to purchase molnupiravir (Lagevrio), an oral antiviral drug that reduces the severity of Covid-19. The contract price of $712 per treatment is estimated to be more than 35 times the cost of producing the drug at a reasonable profit. Molnupiravir was discovered at Emory University using government funding, and Emory’s patent applications acknowledge the government’s Bayh–Dole license.5 Molnupiravir payments for Medicare, Medicaid, and VHA patients could cost the government billions in 2022. This amount could be reduced by more than 90% if the government exercised its license and allowed a generic manufacturer to supply the drug for patients in government-supported programs.”

My take: U.S. taxpayers should get a return on their investment when new medications are developed with government funding rather than paying more for these medications than any other country.

Related blog posts:

Ravenel Bridge, Charleston SC (blue skies -no filter)

Digital Health Care Inclusion

JA Rodriguez, et al. NEJM 2022; 386: 1101-1103 (commentary). Digital Inclusion as Health Care — Supporting Health Care Equity with Digital-Infrastructure Initiatives

Key points:

  • “With digital health tools such as telehealth and patient portals becoming prominent components of care delivery, the barriers to digital inclusion have grown increasingly apparent.1 For example, more than 100 studies have revealed disparities in portal use based on age, race, socioeconomic status, English-language proficiency, and other factors”
  • Barriers: digital redlining (discrimination by internet providers), limited broadband infrastructure/access, costs, and knowledge
  • “The recently enacted Infrastructure Investment and Jobs Act (IIJA) makes investments that could foster sustainable digital inclusion”
  • “The IIJA takes much of the responsibility for building digital infrastructure away from individual health care organizations and makes digital inclusion a public concern. The law includes $65 billion for digital-inclusion initiatives. It earmarks $42.5 billion for investment in broadband infrastructure by means of state deployment grants, promotes broadband affordability by providing $14.2 billion for $30-per-month subsidies for Internet costs for underserved people, and allocates $2.8 billion for the creation of digital-literacy programs. It also includes funds to support connectivity in tribal communities and broadband deployment in rural areas”
  • “The law charges the FCC with adopting rules to prevent “digital discrimination of access based on income level, race, ethnicity, color, religion, or national origin.” These policies are an attempt to overcome structural barriers to digital inclusion, such as redlining”
  • “By capitalizing on new policies, health care organizations could become a critical part of an environment of community-based players working toward digital inclusion”

Issues Not Addressed by Infrastructure Investment and Jobs Act (IIJA):

  • “Law doesn’t address changes that are needed to the design of digital health platforms (e.g., language translation) or to make workflows more inclusive (e.g., integration of interpreters into telehealth visits)”
  • “Simplification of interstate licensing laws for clinicians would also enable digital tools to increase access to care for marginalized populations”
  • Assuring adequate reimbursement for digital care

My take: Digital health literacy/availability is needed to improve outcomes.

Related blog posts:

Island in Charleston Harbor with Ravenel Bridge in the distant (near Shem Creek)

Predicting Intestinal Failure After Gastroschisis Repair

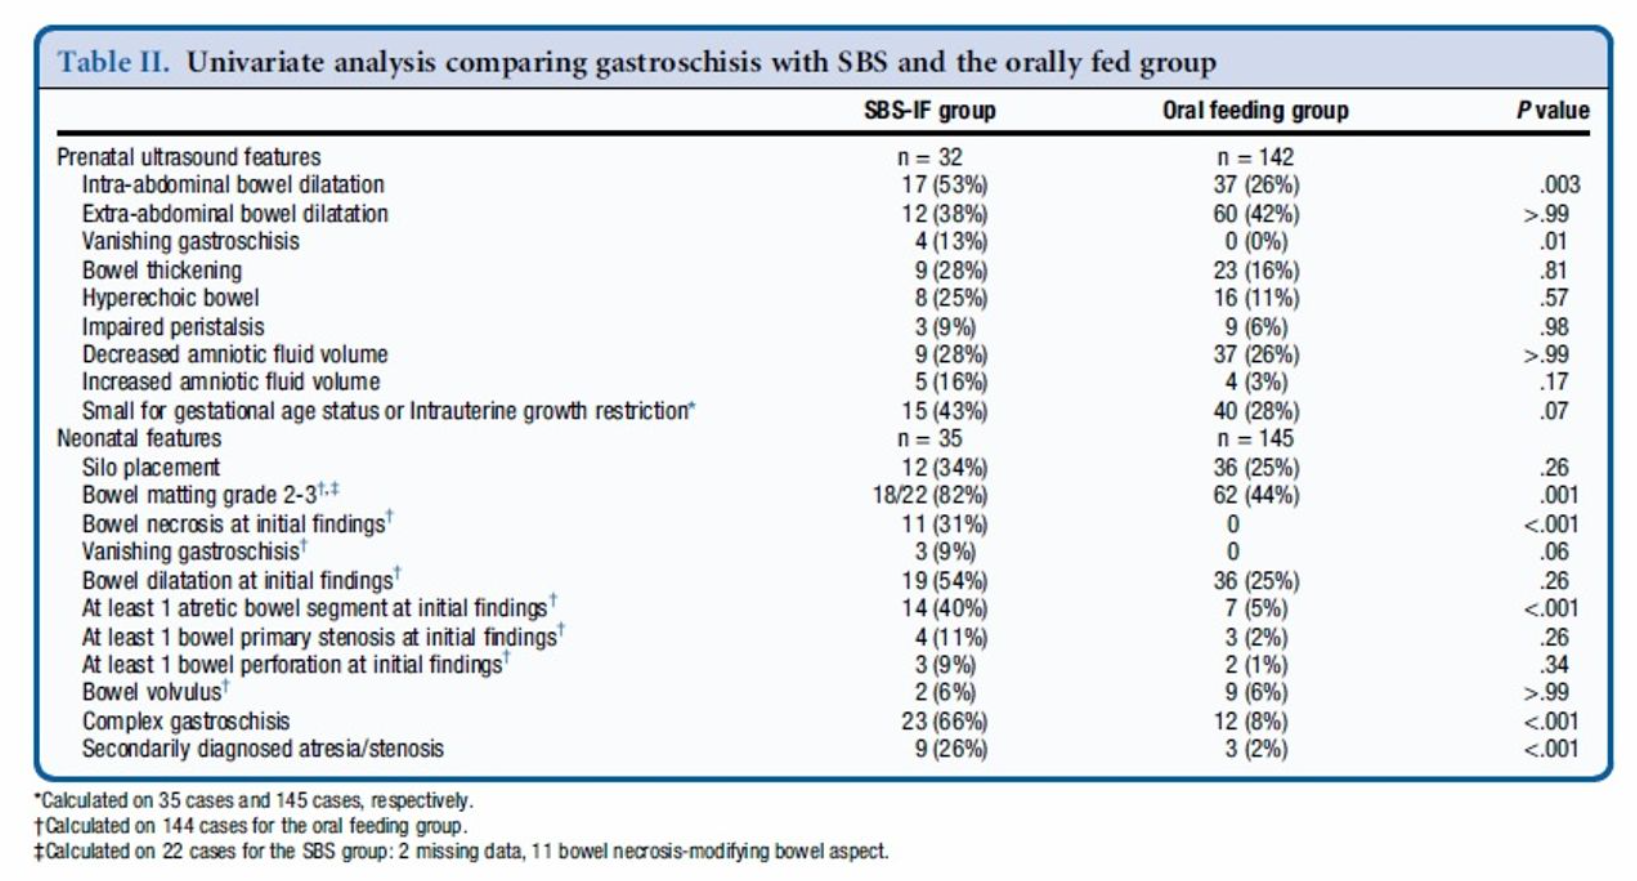
N Vinit et al. J Pediatr 2022; DOI:https://doi.org/10.1016/j.jpeds.2021.11.004 (Ahead of print) Predicting Factors of Protracted Intestinal Failure in Children with Gastroschisis

Methods: Retrospective study. Among 180 patients, 35 required long-term parenteral nutrition (SBS-IF group) and 145 acquired full oral feeding within 6 months (oral feeding group) over mean f/u of 7.9 years.

Key findings:

  • Both bowel matting (OR, 14.2, P = .039) and secondarily diagnosed atresia or stenosis (OR, 17.78, P = .001) were independent postnatal predictors of SBS-IF.
  • An initial residual small bowel length of more than 50 cm was the best predictive cut-off for nutritional autonomy, with a sensitivity of 67% and a specificity of 100%

My take: This study identifies bowel matting and atresia/stenosis as additional factors in predicting nutritional autonomy.

Related blog posts:

Tricky Article Title: IBD and Celiac

M Alkhayyat et al. Inflamm Bowel Dis 2022; 28: 385-392. Patients With Inflammatory Bowel Disease on Treatment Have Lower Rates of Celiac Disease

When I first saw this title, I mistakenly thought the title indicated that celiac disease (CD) occurred less often in those with inflammatory bowel disease (IBD). This would have been surprising given previous studies have found the opposite. In fact, this study confirms the bidirectional associated risk between patients with CD and in patients with IBD but with a twist. Most IBD treatments were associated with a lower risk of developing CD than those who were not treated.

Database study: Of the 72,965,940 individuals in the database (1999-2020), 133,400 had celiac disease (CD) (0.18%), 191,570 (0.26%) had ulcerative colitis (UC), and 230,670 (0.32%) had Crohn disease.

Key findings:

  • Patients with IBD were more likely to have a diagnosis of celiac disease (odds ratio [OR], 13.680), with a greater association with Crohn disease (OR 24.473).
  • Treated patients with IBD with UC and with Crohn disease, respectively, had a lower risk association with CD compared to those not undergoing IBD treatment, specifically corticosteroids (OR, 0.407 and 0.585), 5-aminosalicylates (OR, 0.124 and 0.127), immunomodulators (OR, 0.385 and 0.425), and anti-tumor necrosis factor drugs (OR, 0.215 and 0.242)
  • A new diagnosis of CD after 1 year of IBD diagnosis, was 1.59% for Crohn disease and 0.90% for UC compared to 0.16% in patients without IBD (P<0.0001)
  • A new diagnosis of IBD, Crohn disease and UC respectively, in patients with celiac disease was 2.75% and 1.11% compared to 0.29% and 0.25% in the non-celiac population (P<0.0001)
  • A new diagnosis of IBD and celiac disease among patients with microscopic colitis was 10.5% and 2.6% respectively; a new diagnosis of microscopic colitis among patients with celiac disease was 0.01%

My take: This study confirms the bidirectional associated risk between IBD and celiac disease. The risk of developing celiac disease in those with IBD may be lower in those receiving some treatments; however, this assertion is limited by the nature of a database study.

Related blog posts:

Pelicans at Shem Creek, SC (near Charleston)

Does Motivational Interviewing Help Long-Term Outcomes for Obesity?

M Michalopoulou et al. Annals Int Med 2022; https://doi.org/10.7326/M21-3128. Effectiveness of Motivational Interviewing in Managing Overweight and Obesity

This review and meta-analysis examined forty-six studies involving 11 077 participants.

Key findings:

  • At 6 months, behavior weight management programs (BWMPs) using motivational interviewing (MI) were more effective than no/minimal intervention (−0.88) but were not statistically significantly more effective than lower-intensity (−0.88 ) or similar-intensity (−1.36 ) BWMPs.
  • “At 1 year, data were too sparse to pool comparisons with no/minimal intervention, but MI did not produce statistically significantly greater weight change compared with lower-intensity”

My take: Several years ago our hospital system strongly encouraged practitioners to learn motivation interviewing techniques. However, based on this review, “there is no evidence that MI increases effectiveness of BWMPs in controlling weight.”

Related blog posts:

Isle of Palms, SC

How NOT To Do a Transit Time Study

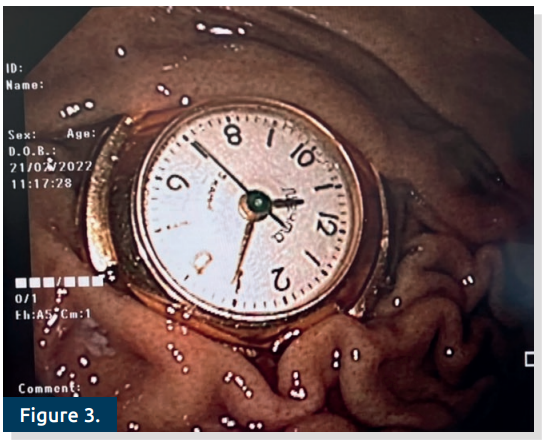
ESPGHAN’s Image of the Month: What time is it? A case of unusual foreign body ingestion

Perhaps this 4 yo child was interested in answering the question of whether the watch ‘takes a licking and keeps on ticking?”

Related blog posts:

Auricular Stimulation Associated with Less Pain, Less Disability, and Better Sleep

N Santucci et al. Neurogastroenterology & Motility. 2022;00:e14358. Effect of percutaneous electrical nerve field stimulation on mechanosensitivity, sleep, and psychological comorbidities in adolescents with functional abdominal pain disorders

This study evaluated the effects of IB-stim® (Innovative Health Solutions, Versailles, IN, USA) in 20 patients (11-19 years old) with functional pain. This external auricular device with a battery powered generator that creates percutaneous electrical nerve field stimulation (PENFS), targeting cranial nerves V, VII, IX, and X. This device which has been associated with improvement in functional abdominal pain previously was evaluated for its effects on resting and evoked pain and nausea, sleep and psychological functioning, and long-term outcomes.

Key Findings:

  • During pain evoked by Water Load Symptom Provocation Task (WL-SPT), visual analog scale (VAS) pain intensity and nausea were lower following PENFS compared with baseline (p = 0.004 and p = 0.02, respectively)
  • After PENFS, resting VAS pain unpleasantness (p = 0.03), abdominal pain (p < 0.0001), pain catastrophizing (p = 0.0004), somatic complaints (0.01), functional disability (p = 0.04), and anxiety (p = 0.02) exhibited significant improvements, and some were sustained long-term.
  • Self-reported sleep improved after PENFS (p’s < 0.05) as well as actigraphy-derived sleep onset latency (p = 0.03). The authors note that, paradoxically, patients receiving neuromodulators had more trouble with sleep at baseline. “It is hard to tease out if these differences are due to the medications themselves or if the patients on these medications have more severe symptoms that may have a bigger impact on their life”
  • In assessing predictors of response to PENFS therapy, those with higher pain catastrophizing and somatization had lesser reduction in VAS pain scores, while those with high anxiety had lesser improvements in functioning.
  • Study limitations: small sample size and lack of control/sham group

In this limited study, PENFS was associated with improvements in pain intensity and nausea through visual analog scales and validated questionnaires. Disability, pain catastrophizing, somatization, and anxiety reduced after four weeks of PENFS and effects were sustained at 6–12 months post-treatment.

My take: Auricular stimulation if feasible (in terms of cost) is a good alternative to pharmacologic therapy. It would be of interest to study outcomes of patients who received this treatment modality compared with those who were treated by well-qualified pain psychologists.

Related blog posts:

Osprey on The Hunley Bridge, Isle of Palms, SC

Image Only: Pneumatosis Intestinalis in Necrotizing Enterocolitis

L Tong, Y-T Chang. NEJM 2022; 386: 1070. Pneumatosis Intestinalis in Necrotizing Enterocolitis

This image below is from an 11 day-old born at 39 weeks gestational age. Sadly, he did not survive an emergency operation.

From NEJM Twitter Feed

Related blog posts:

COVID-19 Update: COVID.gov, Ivermectin Lack of Efficacy & Erectile Dysfunction Due to COVID-19

Link: COVID-19 Government website. This site has information on (free) masks, free tests (up to 2 sets of 4 kits), vaccines and treatments.

The website is available in English, Spanish and Chinese. The administration is also making all of these tools available over the phone through the national vaccine hotline at 1-800-232-0233 (TTY 1-888-720-7489), which supports over 150 languages.

Link to article: Open Access (3/30/22): Effect of Early Treatment with Ivermectin among Patients with Covid-19

Highlights from Eric Topol’s Twitter Feed

Abraham Lincoln’s Cyclic Vomiting Action Plan

PT Reeves et al. J Pediatr 2022; 242: 174-183. Development and Assessment of a Low Literacy, Pictographic Cyclic Vomiting Syndrome Action Plan

Similar to the constipation action plan (see blog link below), the authors have created a stepwise pictographic CVS action plan (CVSAP).

Image is from Pat Reeves twitter feed and corresponds to figure in study (pg 175)

Key points:

  • A composite readability score of 5.32 was consistent with a fifth-grade level.
  • Patients/caregivers (n = 70) judged the CVSAP to be of high quality with consumer information rating form rating of 84.2%
  • Six medical librarians rated the CVSAP to have 93% understandability and 100% actionability, and 33 clinicians completing the SAM generated a suitability rating of 87.5%

On the listed ED management, the authors note “consider fosaprepitant…and can give oral aprepitant on days 2 and 3.” It should be noted that oral dosing afterwards is generally not required as fosaprepitant can last 2-3 days after a single dose. In addition, many use a maximum dose of 150 mg rather than 115 mg. Also, the ED dosage of several agents need to be tailored to the individual based on weight and other medications. Lower doses of many of the medications in the protocol are often effective.

My take: Patients with cyclic vomiting syndrome, like those with constipation, are likely to benefit from clearly articulated plans for maintenance treatment, escalation approaches and for ED management. The need for ED management may lessen with more consistent treatment approaches.

Link to blank CVS PDF Action Plan form: The Uniformed Services Cyclic Vomiting Syndrome Action Plan

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition