The Elephant in the Transplant Room: Personhood

A recent study and related editorial discuss the ethics and utilization of transplantation for children with intellectual disability.

In the study by Wightman et al, the researchers performed a retrospective cohort analysis of children receiving a first kidney, liver, or heart-alone transplant in the United Network for Organ Sharing dataset from 2008 to 2017. Key findings:

  • Definite intellectual disability accounted for 594 of 6747 (9%) first pediatric kidney-alone, 318 of 4566 (7%) first pediatric liver-alone, and 324 of 3722 (9%) first pediatric heart-alone transplant recipients. 
  • Children with intellectual disability account for 7%-9% of pediatric transplant recipients with comparable long-term outcomes to other pediatric recipients.
  • The article had a number of limitations including a lack of a standardized assessment of cognitive development.

In the editorial, the author “opposes the absolute exclusion of patients with intellectual disability and end-stage organ disease from transplantation waitlists provided that the candidates are expected to gain a predefined minimum benefit threshold of life-years and quality-adjusted-life years. Intellectual disability is one of many factors that should be considered in determining transplant eligibility and each candidate should have an individualized interdisciplinary assessment.”

In this commentary, it is noted that “the vast majority (85%) of individuals classified as having intellectual disability are able to live independently with minimum levels of support.” While the author would exclude those in a persistent vegetative state and those who were minimally conscious, otherwise he advocates “the candidate with intellectual disability should be given equal priority for organ transplantation.”

My view: The suitability for transplantation of individuals with intellectual disability centers on the issue of personhood; those who meet the threshold of personhood should be eligible to receive organ transplants without discrimination.  Wikipedia-Personhood: “Defining personhood is a controversial topic in philosophy and law and is closely tied with legal and political concepts of citizenship, equality, and liberty.”

Related blog posts:

Transient Elastography in Pediatric Liver Disease

AM Banc-Husu, LM Bass. JPGN 2021; 73: 141-144. Transient Elastography in Pediatric Liver Disease

This useful review explains the techniques/technologies/limitations of transient elastography and provides pediatric values which correlate with liver fibrosis. Confounding factors, however, may affect elastography measurements, such as obesity, severe inflammation, nonfasting state, and hepatic congestion.

From Table 2 for Elastography (FibroScan technology) Cut-Off Values and Correlation with Outcomes :

  • Biliary Atresia: >15.5 kPa distinguishes METAVIR F4 fibrosis and >12.7 kPa predicts development of varices
  • Any Chronic Liver disease: >10.6 kPa distinguishes METAVIR F2 fibrosis
  • Non-alcoholic fatty liver disease: >9 kPa distinguishes advanced fibrosis
  • Portal hypertension: >9.7 kPa distinguishes presence of portal hypertension
  • Liver transplant graft: >5.6 kPa distinguishes advanced fibrosis

My take: Elastography is most useful when values are at the very low and very high end. Low values provide a lot of reassurance against significant fibrosis and high values indicate a high likelihood of significant liver fibrosis.

Related blog post:

From Shelburne Farms (https://shelburnefarms.org/) Vermont

Pelvic AnoRectal Care Program (PARC)

I recently had the opportunity to hear a terrific lecture by Kathleen Hoff regarding efforts to achieve continence for children, especially those with anorectal malformations. This blog entry has abbreviated/summarized the presentation. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.

Key points (my notes followed by screenshots of some of the slides):

How to reach PARC team:

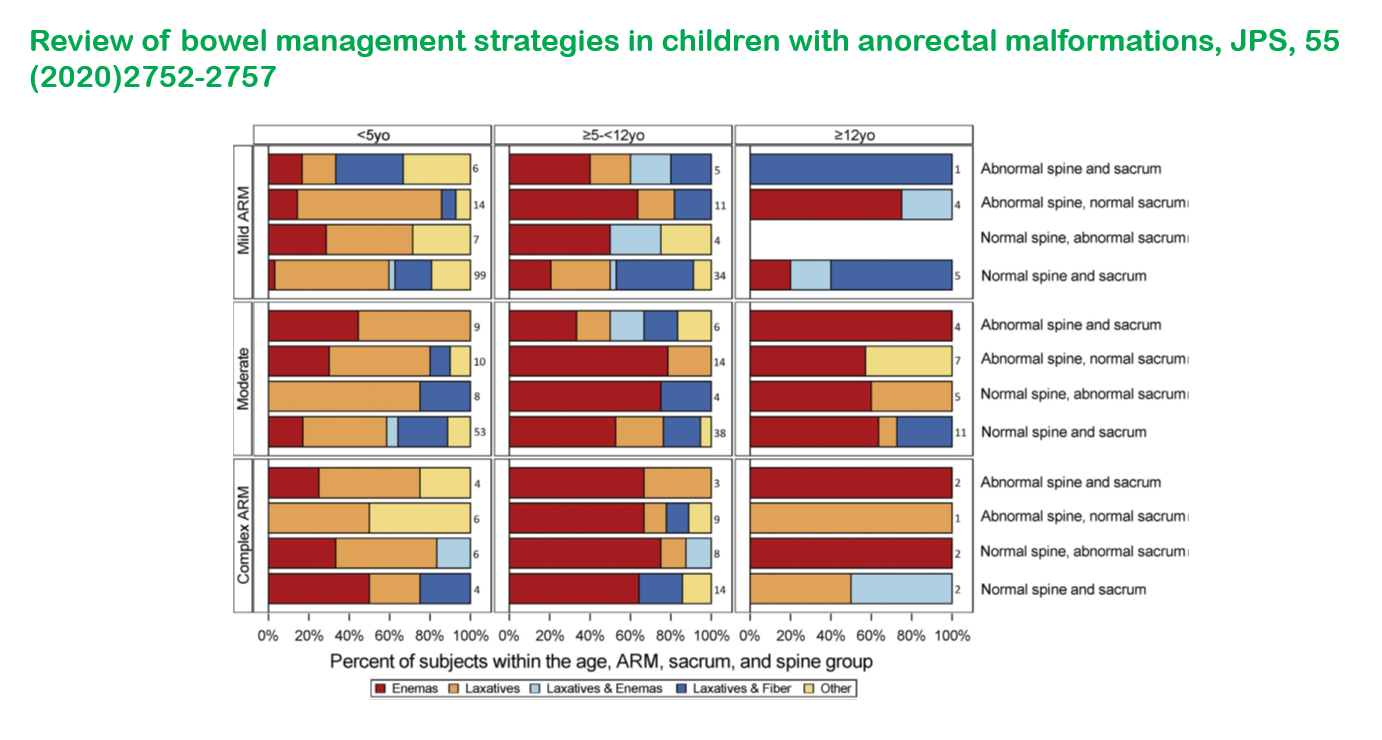
Data from PARC: Red color indicates use of enemas, light brown indicates use of laxatives
Products for enemas
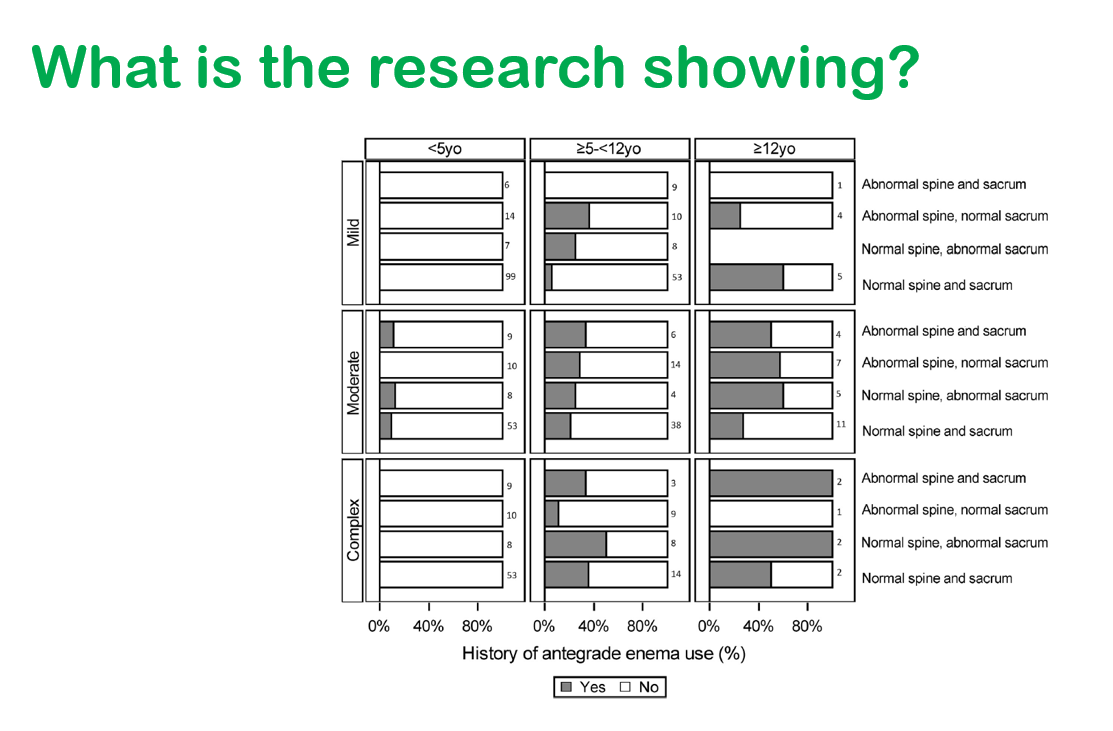
Data showing increasing use of antegrade enemas in older children
and those with moderate and complex malformations

Related blog posts:

“Turning Purple with Pain”

A recent clinical problem-solving case (TW Fredrick et al. NEJM 2021; 385; 549-554. Turning Purple with Pain) is a good review on episodic pain and acute intermittent porphyria (AIP).

The case presentation regarded a 32 yo with episodic severe pain for 10 years (associated with constipation) that required morphine. Episodes occurred every month or two and lasted for several days. Some clues in this case included the development of hyponatremia, purple urine, and an episode in which she was “out of it.” This episode was attributed to opioid use and providers were concerned about opioid-seeking behavior and a conversion disorder.

She had extensive evaluations including imaging, panendoscopy, and labs. Atypical labs included serum tryptase, cortisol, and C1 esterase inhibitor level. Ultimately, her constellation of findings led to a urine porphyrin levels which disclosed elevated porphobilinogen (PBG) and delta-aminolevulinic acid. The diagnosis of AIP was confirmed with genetic testing.

Key points:

  • AIP results from mutations in HMBS, the gene encoding hydroxymethylbilane synthase which plays an integral role in heme synthesis
  • AIP is rare, affecting about 5 people per million; age of onset is typically 18-45 years of age
  • In a case series, 18% of patients with AIP reported nearly constant abdominal pain symptoms, 73% had nausea/vomiting, 60% have constipation, and 55% had anxiety/depression.
  • Associated conditions included hypertension ((43%), peripheral neuropathy (43%), chronic kidney disease (29%), psychiatric disorders (22%), palpitations (19%), seizures (9%), cirrhosis (2%), and hepatocellular carcinoma (1%)
  • Flares of AIP may be triggered by alcohol, infections, low caloric intake, and medications (especially seizure medications and hormonal contraceptives)
  • The urine can appear red or brown and darkens on exposure to oxygen, light or heat. Purple urine reflects very high urinary PBG levels

My take: This article provides a useful overview. AIP needs to be considered in adolescents with severe abdominal pain that results in hospitalization (especially if episodic).

Related blog post: Liver Shorts -June 2020 (with AIP article)

Also, data supporting COVID-19 effectiveness in reducing the risk of hospitalization–CDC study shows unvaccinated people are 29 times more likely to be hospitalized with Covid (CNBC)

Sterling Pond. Jeffereson, VT

Long-Haul COVID: ‘Next Health Disaster’

S Phillips, MA Wiliams. NEJM 2021; 385: 577-579. Open Access: Confronting Our Next National Health Disaster — Long-Haul Covid

A few excerpts:

  • Factoring in new infections in unvaccinated people, we can conservatively expect more than 15 million cases of long Covid resulting from this pandemic. And though data are still emerging, the average age of patients with long Covid is about 40, which means that the majority are in their prime working years.
  • Long Covid is not a condition for which there are currently accepted objective diagnostic tests or biomarkers…The health care community, the media, and most people with long Covid have treated this syndrome as an unexpected new phenomenon. But given the long arc and enigmatic history of “new” postinfection syndromes, the emergence of long Covid should not be surprising.
  • Equally unsurprising has been the medical community’s ambivalence about recognizing long Covid as a legitimate disease or syndrome…If the past is any guide, they will be disbelieved, marginalized, and shunned by many members of the medical community…Some of the disregard can be attributed to the fact that long Covid has disproportionately affected women.
  • The ultimate success of the research-and-development and clinical management agendas in ameliorating the impending catastrophe is critically dependent on health care providers’ believing and providing supportive care to their patients. These beleaguered patients deserve to be afforded legitimacy, clinical scrutiny, and empathy.

My take: It is unfortunate that many cases of long-haul Covid that will develop could be prevented with vaccination

Causeway Trail in Burlington VT (adjacent to Lake Champlain)

Pediatric Gastroenterology Opportunities at GI Care For Kids

This image has an empty alt attribute; its file name is image-79.png

Job Openings: Pediatric Gastroenterologists

Description

GI Care For Kids is seeking multiple experienced Pediatric Gastroenterologists to join our group of 15 pediatric gastroenterologists and 5 advanced practice providers.  Our highly-regarded and busy private practice provides state-of-the art, comprehensive care in our offices and at Children’s Healthcare of Atlanta at Scottish Rite, located across the street from our main office. 

Our group includes general pediatric gastroenterologists as well as physicians with a wide range of subspecialization, including inflammatory bowel disease, short bowel syndrome, eosinophilic diseases, motility disorders, feeding disorders, aerodigestive disorders, and celiac disease.  Many of our physicians are recognized nationally for their achievements.  With our clinical colleagues at Children’s Healthcare of Atlanta, we are rated as the #8 pediatric gastroenterology program in the country by U.S. News.  

Important features of our practice include the following:


  • 13 office/satellite locations.  All physicians help cover satellite locations.
  • opportunity for cutting edge clinical research
  • currently >12 pharmaceutical trials for IBD, EoE, IBS, and Clostridium difficile
  • on-site nutritionists
  • on-site psychology support for patients
  • participation in ImproveCareNow
  • fully-accredited office-based pediatric endoscopy center
  • office infusion centers
  • multi-lingual physicians
  • EPIC electronic health record system

We are looking for candidates with prior clinical experience (prefer 2 or more years after fellowship) and excellent communication skills.  Additional expertise in advanced endoscopy or pancreatic specialization would be ideal but not a requirement for consideration.  All candidates should be board-certified in pediatric gastroenterology.

The Atlanta area is a thriving city (except during a snowstorm) with excellent schools and recreational opportunities.  Our office offers competitive salary, benefits, vacation time (20 work days including CME time), and partnership opportunity. Compensation package includes family health insurance, profit sharing, and CME allowance.  Hospital coverage averages 1 week/1 weekend per month. Night call is shared and averages about 2 nights per month.  Our group is committed to fostering a diverse, equitable, inclusive, and family-friendly environment in which all physicians and staff can excel and achieve work/life balance.

Please send letter of interest and curriculum vitae to: Katrin Herzog. Email address:  kherzog@gicareforkids.com

Calprotectin Less Accurate for Isolated Ileal Crohn’s Disease

G D’Arcangelo et al. JPGN 2021; 73: 242-246. Is Fecal Calprotectin a Useful Marker for Small Bowel Crohn Disease?

In this retrospective study with 98 patients, the authors examined the sensitivity and specificity of fecal calprotectin (FC) at a cutoff of 150 mcg/g in comparison to findings of ileocolonoscopy and MRE in those with isolated ileal CD (L1, n=14), colonic CD (L2, n=10) and ilecolonic CD (L3, n=74) . Note: the abstract erroneously states the cutoff as 50 mcg/g.

Key findings:

  • The sensitivity and specificity of FC for L1 CD were 36% and 91%, respectively, compared to 93% and 75% for L2 and 70% and 95% for L3.
  • An FC of 95 mg/kg was identified as the best cut off for identification of active isolated ileal disease, with a sensitivity of 77% and a specificity of 56%

My take: Though this study had only 14 patients with isolated ileal disease, it is likely that a calprotectin level is less reliable as a biomarker in these patients.

Related article: Jukic A, Bakiri L, Wagner EF, et al Calprotectin: from biomarker to biological functionGut Published Online First: 18 June 2021. doi: 10.1136/gutjnl-2021-324855. Thanks to KT Park for this reference. Open Access- Full text: Calprotectin: from biomarker to biological function

Related blog posts:

CDED + PEN: An Alternative Diet to Exclusive Enteral Nutrition?

T Niseteo et al Nutr Clin Pract 2021: 1-7. Modified Crohn’s disease exclusion diet is equally effective as exclusive enteral nutrition: Real-world data Thanks to Kipp Ellsworth for this reference.

This was a retrospective study with 61 children, median age, 14.4 years; overall, 42 (69%) achieved clinical remission based on weighted PCDAI. The study compared a modified Crohn’s disease exclusion diet (CDED) (modified as 80% in this group had 1–2 weeks of EEN initially) to EEN; PEN accounted for ~50% of calories CDED/PEN group received mainly modulen whereas EEN received a number of standard polymeric isocaloric formulas (eg. pediasure, osmolite, ensure plus). Concomitant medical therapy was used in ~80% of patients (most often azathioprine).

Key finding: Clinical remission was similar in both groups: 27 of 41 (65.9%) received EEN and 15 of 20 (75.0%) received CDED + PEN after 6-8 weeks of treatment. In addition, both groups had improvement in CRP and Hemoglobin.

*Several authors grants/payments from formula manufacturers.

My take: This study while favorable towards a combination of CDED/PEN is limited by small numbers, retrospective design, limited followup and absence of data on mucosal healing.

Related blog posts:

K Lambert et al. AP&T 2021; https://doi.org/10.1111/apt.16549. Systematic review with meta-analysis: dietary intake in adults with inflammatory bowel disease. Thanks to Ben Gold for this reference.

This meta-analysis included 19 studies of adults with IBD involving dietary intake. Results “show inadequate energy for all subgroups of adults with IBD (mean intake in adults with IBD 1980 ± 130 kcal), as well as fiber (14 ± 4 g), folate (246 ± 33 mg) and calcium (529 ± 114 mg) per day.” Further, “In comparison to the healthy control groups, IBD patients consumed significantly less dietary fiber (SMD −0.59; 95% CI, −0.73 to −0.46).” 

Would You Want a Smart Toilet?

Gastro & Endo News July 2021, Full Text: Disease Surveillance With Every Flush: Introducing the Smart Toilet

Key finding:

  • The Smart Toilet was able to determine the stool consistency and if the stool had blood 85% and 75% accuracy, respectively, in agreement with a gastroenterologist.

An excerpt:

“At the 2021 virtual Digestive Disease Week, Duke University gastroenterologist Deborah Fisher, MD, and engineering professor Sonia Grego, PhD, showed that toilets enabled with artificial intelligence can analyze stool samples for signs of acute or chronic gastrointestinal disease, such as bleeding, infections or even inflammatory bowel disease.”

My take: I definitely do NOT want my toilet to be too smart. It would not be hard to imagine the toilet berating me for what I ate for dinner the night before.