Facts, “Misfearing” and Women’s Health

A terrific short perspective article shows how “misfearing” affects health care (NEJM 2014; 370: 595-597).

The author quotes one of her patients who when asked what is the number-one killer of women, replies “I know the right answer is heart disease…but I’m still going to say ‘breast cancer.'”

Key points:

  • “Tornadoes. Terrorist attacks. Homicides.  The big, the dramatic, and the memorable occupy far more of our worry budget than the things that kill with far greater frequency.”
  • “Misfearing” is a term coined by Cass Sunstein “to describe the human tendency to fear instinctively rather than factually”  274. Cass R. Sunstein, “Misfearing: A Reply” – University of Chicago 
  • “When I read Angelina Jolie’s New York Times editorial…She’s beautiful and brave, I thought, and I want to be like her.  The cardiologist in me, however, said, ‘Oh no –will this make it even harder for us to help women believe they’re at risk for cardiovascular disease?'” My Medical Choice by Angelina Jolie – NYTimes.com

A graphic from this perspective article shows that mortality from cardiovascular disease is approximately ten times greater than mortality from breast cancer (if difficult to see, the graphic is available online http://www.nejm.org/doi/full/10.1056/NEJMp1314638?query=featured_home):
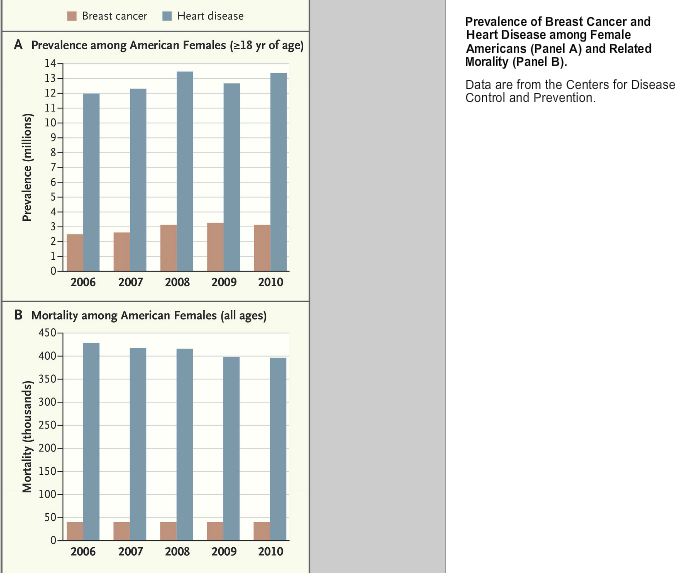
Cardiovascular vs. Breast Cancer Mortality in Women

Cardiovascular vs. Breast Cancer Mortality in Women

In pediatric GI, families are often more worried about the treatment than the disease (e.g.. inflammatory bowel disease), despite the fact that the disease is often far more dangerous.

Take home message: (quote from author) “If we want our facts to translate into better health, we may need to start talking more about our feelings.” This is true not just in cardiovascular disease, but in all aspects of medicine.

Related blog posts:
Eosinophilic Esophagitis and Psychosocial Dysfunction

There are many medical challenges in treating patients with eosinophilic esophagitis (EoE) and this has been discussed extensively in this blog (some links below).  What is striking in managing these patients and families is how often there are significant psychosocial problems.  Does this disorder serve as an excuse for other issues? Does the altered diet create enormous stress and isolation? Is the diagnosis of EoE an epiphenomenon for many of these patients?

While these questions are not answered, a recent retrospective study from a tertiary care center does provide some data on the frequency of psychosocial dysfunction in children and adolescents with EoE (JPGN 2013; 57: 500-05).

Psychosocial evaluation was offered as part of these patients’ clinical evaluation; this took place in 64 of 152 patients during the study timeframe.  Subsequently, a retrospective review of these patients, who had been offered a 1-hour behavioral health assessment by either a psychologist or social worker, were analyzed.

Key findings:

  • 69% had some psychosocial impairment
  • 64% had social difficulties
  • 41% had anxiety
  • 33% had sleep difficulties
  • 28% had depression
  • 26% had school problems
  • 44% had adjustment problems; this was more common in older children and in children with gastrostomy tubes

The main limitations of this study are its retrospective nature and the fact that only a minority of patients were analyzed; the latter indicates a high likelihood of a selection bias. The severity of EoE was not correlated with these problems, but could have been higher  at a tertiary center.

Take-home message: As with other chronic diseases, EoE patients have frequent psychosocial health problems –this study starts to define the extent of the problem.

The Genius of Breastmilk

While there has been a lot of talk about how breastmilk improves IQ/development (see links below), there are many other reasons why breastmilk is amazing.  For example, breastmilk reduces the risk of necrotizing enterocolitis (NEC).  A recent study on this effect: J Pediatr 2013; 163: 1592-5.

In this multicenter randomized controlled trial involving 7 NICUs, the authors studied extremely premature infants whose mothers did not provide their breastmilk.  Infants were fed either a cows-milk based preterm formula (COW, n=24) or pasteurized donor human milk (HUM, n=29). Birth weight and gestational age were similar in both groups, approximately 990 g and 27.5 weeks respectively.

Results:

  • HUM patients had fewer days of parenteral nutrition: 27 vs. 36, P=.04
  • HUM patients had fewer bouts of NEC: 1 (3%) vs. 5 (21%), P=.08; surgical NEC occurred 4 times in COW group compared with 0 in HUM patients (P=.04)

Take-home message: The data from this study are in line with recent American Academy of Pediatrics policy statement that recommends the following: “premature infants should receive only human milk from their mother and that, if it is not available, pasteurized donor human milk should be used.”

Another relevant study: J Pediatr 2010; 156: 562-7.

Related blog posts:

Benefits of Rotavirus Vaccine and Intussception

The latest information on rotavirus vaccines provide more information on the relative benefits (very high) compared to the risks (very low).

  • NEJM 2014; 370: 503-12
  • NEJM 2014; 370: 513-19
  • NEJM 2014; 370: 568-70 -editorial

While the initial marketing studies for Rotateq (Merck) and Rotarix (GlaxoSmithKiline) which each enrolled more than 60,000 infants did not show a significant risk of intussusception, these latest studies do indicate a very low risk for intussusception.

  • Risks of intussusception: “approximately 1 to 5 cases per 100,000 infants.” This equates to 45 to 213 cases of intussusception nationwide each year.
  • Benefits of these rotavirus vaccines in U.S.: “in the U.S. cohort of 4.5 million babies born each year, vaccination is estimated to prevent approximately 53,000 hospitalizations and 170,000 emergency department visits for diarrhea.”
  • In developing countries, the results for vaccination are even more impressive.  In Mexico which has implemented a vaccination program, there has been a 40% reduction in deaths due to diarrhea (NEJM 2010; 362: 299-305).

Related blog posts:

Polyps: Clinical Decision Tool

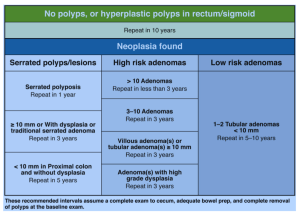
The best approach to polyps from the U.S. Multi-Society Task Force: Gastroenterology 2014; 146: 305-306.  This paper’s simple chart on page 306 could help reduce many follow-up colonoscopies that are performed at shorter than recommended intervals.

Polyp Guideline

Related blog post:  Consensus guidelines after polypectomy | gutsandgrowth)

“Fill er up”

A few years ago my wife took a bunch of kids to a local frozen yogurt place.  The kids take their bowl and choose their frozen yogurt flavor and toppings; the cost is determined at the end of the line based on how much you took.  One of our guests filled her bowl (at a sizable expense) but only ate a small portion.  My wife told her, ‘if you lived in our household, I would insist that you eat what you took.’  And even though we both hate waste, it seems like human nature to have ‘eyes that are bigger than your stomach.’

An interesting publication (J Pediatr 2014; 164: 323-6) on bowl size and cereal consumption did not make the coveted list of articles reviewed by the editors.  But, I think a lot of pediatric providers and anyone who goes to frozen yogurt establishments would find the information useful.

The article consisted of two studies.  In the first, 69 preschool-age children were randomized to either an 8 oz bowl or a 16 oz bowl and asked to tell researchers how much cereal they wanted for a morning snack; the amount consumed was not measured.  In the second study, 18 school-age children at a summer camp were given an 8 oz bowl on one day and a 16 oz bowl on another day.  Each day, they were asked by the cafeteria server how much cereal and milk they wanted for breakfast.  Hidden scales measured how much was served, consumed, and discarded.

Who thinks they can guess the results?

  • In study 1, children with the larger bowl requested 87% more.
  • In study 2, the older children also consumed more (52%) when given a larger bowl; in addition, they wasted 26% more.

The article notes that some studies (eg. J Consumer Res 2012; 39: 215-28) but not all (Appetite 2007; 49: 652-60) have indicated that “when adults serve themselves, they select an amount of food proportional to the size of the plate;” some have suggested this is due to a visual illusion effect —Delboeuf illusion – Wikipedia, the free encyclopedia.

Screen Shot 2014-02-07 at 4.23.54 PM


Take-home message: If kids (and probably adults) have a bigger bowl, they will want to “fill er up.”  This will certainly lead to more waste but it may increase their waists too.

Clostridium difficile: Colonization vs. Symptomatic Infection

A recent study provides another way to distinguish individuals colonized with Clostridium difficile from those with symptomatic infection (J Pediatr 2013; 163: 1697-704).

Methods: This study comprised two designs. “The first is a case-control study comparing children with a positive C difficile test (cases), children with diarrhea but no C difficile (symptomatic controls), and asymptomatic controls, some of whom were colonized with C difficile.  The second is a prospective-cohort study where we followed our cases for the duration of their illness.”

Results: Fecal cytokines (CXCL-5 and IL-8 mRNA) were elevated in samples from symptomatic children, whether cases or controls.

Bottomline: Inflammatory cytokines can help distinguish C difficile colonization from disease.  Of course, this may have limited utility in patients with underlying inflammatory bowel disease.

Recent posts regarding C difficile:

Teaching an Old Drug New Tricks

A couple recent articles focused on the new uses of methotrexate (MTX) and how to handle potential hepatotoxicity:

  1. J Pediatr 2014; 164: 231-36
  2. Inflamm Bowel Dis 2014; 20: 47-59

In the first medical review article, the authors note the efficacy of MTX for the following:

  • Juvenile idiopathic arthritis
  • Uveitis
  • Psoriasis
  • Crohn disease
  • Juvenile dermatomyositis
  • Localized scleroderma
  • Vasculitis

This review article discusses mechanism of action which is poorly understood along with pharmacogenomics and practical issues in usage.  The latter includes the need for supplemental folic acid.  Other points:

  • “The long-term safety of MTX is remarkable”
  • “The issue of nausea and vomiting…can be especially disturbing.”  They note that one study demonstrated that ondansetron 1 hour prior to MTX from the first injection prevented nausea, which was often difficult to treat once developed.
  • “Liver enzyme abnormalities occur frequently (up to 30% of patients) but are usually of minimal clinical significance.”  Best to draw blood tests 1-2 days before MTX dosing.
  • “In children, unlike adults, MTX-related pulmonary adverse events are very rare.”
  • “In recent years it was shown that live vaccine boosters are effective and safe during MTX use (caution may be needed if MTX is used with other immunosuppression medications)” Ref: JAMA 2013; 309: 2449–56.
  • “Use during pregnancy or within 3 months of planning pregnancy is contraindicated”

The second article was a systemic review which identified 12 high-quality studies which focused on MTX hepatotoxicity in children.  Key findings:

  • 57 of 457 developed some degree of abnormal liver biochemistries.
  • Due to hepatotoxicity, dose reductions were undertaken in 6.4% and 4.5% discontinued MTX.

The authors note that studies of MTX in adults with IBD have not demonstrated cumulative liver toxicity from MTX.  In addition, many of the patients with hepatotoxicity may have had  other reasons for abnormal liver biochemistries including other medications (eg. glucocorticoids).  “Confirmation of MTX hepatotoxicity with a liver biopsy is seldom performed in children;” as a consequence, the exact rate of MTX hepatotoxicity is unknown.

The authors propose that liver biochemistry monitoring occur at baseline, biweekly x 2, then every 2-3 months.  Also, the authors recommend:

  • If ALT < 2 times upper limit of normal (ULN), check liver biochemistries every 2 weeks
  • If persistent abnormalities, the authors recommend an ultrasound
  • If ALT ≥ 2 times ULN, repeat testing should be obtained and consider consultation with a hepatologist

Bottomline: Methotrexate is an important medication for Crohn disease –there are not very many available.  If there are persistent liver enzyme elevations, dose reduction of MTX (or cessation) may be necessary.  As a practical matter, it is advisable to obtain blood draws 1-2 days prior to MTX rather than afterwards. Nausea can be minimized with ondansetron and weekend dosing.

Related blog posts:

“Can you identify the six saltiest foods in American diets?”

From the American Heart Association Twitter Feed: http://bit.ly/SVnguk 

  1. Breads and rolls. We all know breads add carbohydrates and calories, but salt, too? It may not seem like it because a lot of bread doesn’t even taste salty, but one piece can have as much as 230 milligrams of sodium. That’s 15 percent of the recommended amount from only one slice, and it adds up quickly. Have a sandwich and muffin in one day? The bread alone could put you at about 1,000 milligrams of salt – or two-thirds of the American Heart Association’s recommended daily sodium limit of 1,500 milligrams.  Be sure to check the nutrition label as different brands of the same foods may have differing sodium levels.
     
  2. Cold cuts and cured meats. Even foods that would otherwise be considered healthy may have high levels of sodium. Deli or pre-packaged turkey can contain as much as 1,050 milligrams of sodium.  They have so much because most cooked meats would spoil in only a few days without the added sodium solution. Look for lower sodium varieties.
     
  3. Pizza. OK, everybody knows pizza’s not exactly a health food. But you’re probably thinking the big concerns are cholesterol,fat and calories. But pizza’s plenty salty, too. One slice can contain up to 760 milligrams of sodium. It doesn’t take a whole lot of math to realize two or three slices alone can send you way over the daily sodium recommendation. You may want to have fewer slices of pizza topped with vegetables and less cheese.
     
  4. Poultry. Surely chicken can’t be bad for you, right? Well, it depends on how the chicken is prepared. Reasonable portions of lean, skinless grilled chicken are great. But when you start serving up the chicken nuggets or poultry injected with added sodium solutions/marinades, the sodium starts adding up. Just 3 ounces of frozen and breaded nuggets can add nearly 600 milligrams of sodium. (And most kids probably aren’t stopping at 3 ounces.)  Check labels to be sure you are selecting the lower sodium version and that there are no added sodium solutions.
     
  5. Soup. This is another one of those foods that seems perfectly healthy. It can’t be bad if Mom gave it to you for the sniffles, right? But when you take a look at the nutrition label for some products, though, it’s easy to see how too much soup can quickly turn into a sodium overload. One cup of canned chicken noodle soup can have up to 940 milligrams of sodium.  Look for lower sodium options that taste just as great!
     
  6. Sandwiches. This covers everything from grilled cheese to hamburgers. We already know that breads and cured meats are heavy on the sodium. Add them together, and you can pretty easily surpass 1,500 milligrams of sodium in one sitting.   Top sandwiches with plenty of vegetables, such as lettuce, tomato and cucumbers.

Nice graphic: The-Salty-Six-Infographic_UCM_446591_SubHomePage.jsp

Related blog link:

Will salt intake make you fat? | gutsandgrowth

What and When for ERCP with Gallstone Pancreatitis

A recent case vignette highlights several key points regarding use and timing of ERCP (endoscopic retrograde cholangiopancreatography) for gallstone pancreatitis (NEJM 2014; 370: 150-7). Figure 1 provides a nice illustration of ERCP.

Indications:  Suspected bile-duct stones as the cause of pancreatitis AND one of the following:

  • cholangitis (fever, jaundice, sepsis)
  • persistent biliary obstruction (conjugated bilirubine level >5 mg/dL)
  • clinical deterioration (worsening pain, increasing white cell count, worsening vital signs)
  • stone evident in the common bile duct on imaging

AGA position paper (2007):

  • Urgent ERCP (within 24 hours of admission) was recommended in those with cholangitis
  • Early ERCP (within 72 hours of admission) was recommended if suspicion of persistent bile-duct stones remained high

Patient information/animated videos for pancreatic diseases from the National Pancreas Foundation: http://ow.ly/sF9vb 

Related post:

Indomethacin to prevent post-ERCP pancreatitis | gutsandgrowth
