ESPGHAN Position Paper: Management of Foreign Bodies (2026)

O Ledder et al. J Pediatr Gastroenterol Nutr. 2026;83:539–554. Open Access! Foreign body ingestions in children and adolescents: A position paper of the European Society for Pediatric Gastroenterology, Hepatology, and Nutrition (ESPGHAN) endoscopy special interest group

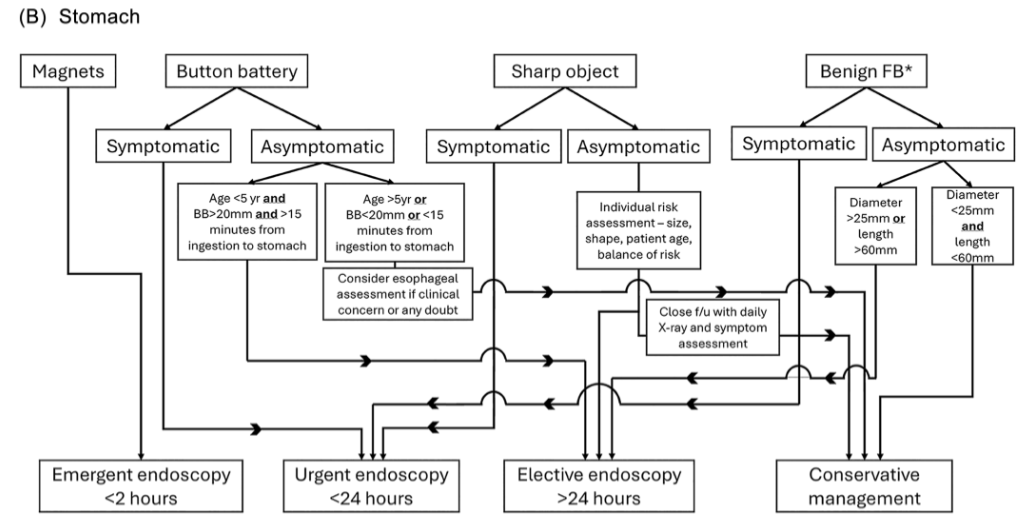
In 2015, NASPGHAN’s endoscopy committee published a report on the management of foreign bodies (see: Foreign Bodies in Children -Expert Guidance). This was quite helpful. This ESPGHAN position paper provides updated guidance though many of the recommendations are unchanged.

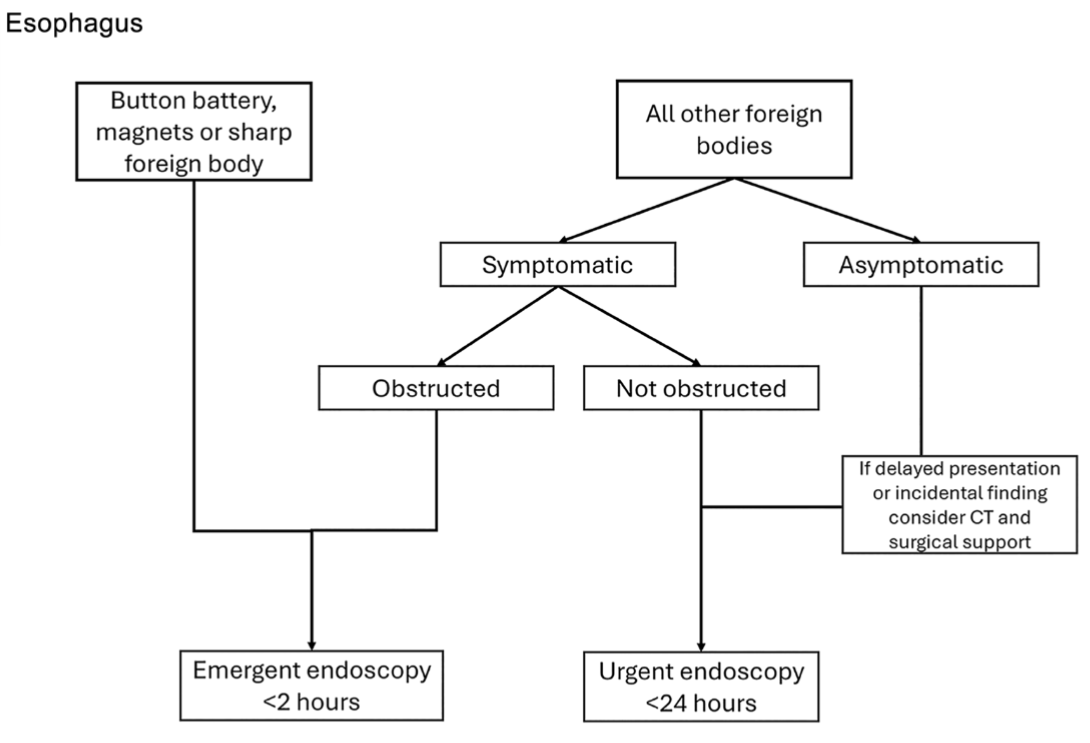
Overall Treatment Algorithm:
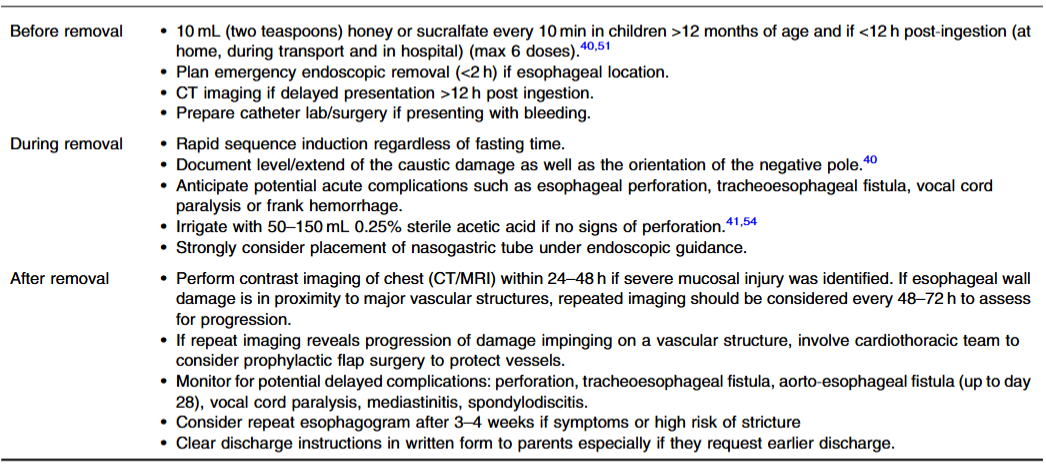
Button Batteries
Blunt Objects/Benign Foreign Bodies

  • Superabsorbent polymers (SAP) Since these items are translucent, imaging is useful only for identifying the sequelae of the ingestion, but not the SAP itself… In cases of witnessed or suspected ingestion of SAP, emergency endoscopy should be performed to attempt retrieval of the material. If this is unsuccessful, or not completely retrieved, the child should be admitted for close observation with surgical support.

Magnets:

  • On table fluoroscopy has been suggested to confirm removal of all magnets if there is doubt whether all have been retrieved. (My personal experience is that fluoroscopy is particularly helpful if a colonoscopy is needed.)

Sharp Objects

My take: These guidelines are similar the previous NASPGHAN endoscopy committee recommendations from 2015. They are still worth a read for more context and there are a lot of endoscopy pointers in this report.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

“Being a Doctor Will Never Be the Same After A.I.”

Rachael Bedard. NY Times 9/25/26: Being a Doctor Will Never Be the Same After A.I.

An excerpt:

“I have a confession: A.I. is making me a better doctor. And I worry that it’s making doctors-in-training worse…

I already use the technology in my practice all the time…This summer, I used an A.I. tool — a platform called OpenEvidence, accessible only to health care providers — to help me choose antibiotics for one patient and to interpret unusual bloodwork for another. A.I. reminded me to consider migraines when a woman presented with dizziness. ..

Almost every month, I’m confronted with a complaint or syndrome that I don’t recognize. I’m confident in my mastery over what doctors do — history-taking, reasoning, communicating. I’m less confident about my continued mastery of an ever-evolving universe of facts. Now, the chatbot in my pocket reassures me that I will always know enough, or have access to the cloud-based intelligence that generally does.

All of my students and residents also use OpenEvidence, however, and I worry about the consequences of introducing such a powerful decision aid so early in their careers. Not only have they memorized less than I’d like, but they can seem almost passive in their relationship to their machines…

OpenEvidence is trained exclusively on peer-reviewed evidence and guidelines, and includes citations for all its claims…To use the app well, you must stay skeptical as you scroll…

I’m surprised by how much I learn from, and enjoy, these interactions. More important, my patient care has improved as conversations with the agent push my thinking beyond its usual limits…

Adam Rodman, a physician and A.I. researcher at Harvard Medical School,… said he shared my concern that trainees aren’t benefiting from “productive struggles” as much as their predecessors. “In experienced hands, decision support might cause a little de-skilling, but a little de-skilling probably doesn’t matter much to you,” Dr. Rodman told me. “But if you do that to somebody who has much less skill, the cognitive offloading can cause never-skilling”…

Current doctors-to-be may be the most adversely affected generation when it comes to A.I. They’re training before we know enough about how to teach them well in this new paradigm.

My take: In all aspects of learning, not just medicine, using AI shortcuts may make learners increasingly dependent on their devices, undermine their judgment and hinder developing their own voice. How to best train individuals in this new era remains unclear.

Related blog posts:

Svörtuloft Lighthouse is located at the westernmost tip of the Snæfellsnes Peninsula in West Iceland. It is perched atop a 2.5-mile stretch of pitch-black volcanic lava cliffs.

Long-Term Effectiveness of Dupilumab for Eosinophilic Esophagitis

S Oliva et al. Clinical Gastroenterology and Hepatology; 2026 (Epub, 9/7/26). Open Access! Long-Term Effectiveness of Dupilumab in Eosinophilic Esophagitis: Results From the DUPEOETALY Study

Methods: This retrospective observational study included 167 patients, median age, 21.5 years, with EoE from 50 Italian centers, unresponsive or intolerant to conventional therapies. Given the real-world design of the study, no standardized protocol mandated patient re-evaluation at fixed follow-up timepoints. Histologic remission was considered having <15 eos/hpf. All patients, however, underwent at least 3 endoscopic assessments: at baseline, after the induction phase (performed between weeks 12 and 24), and at 1-year follow-up. At baseline, 76% had a personal history of atopy, 86.2% had used corticosteroids, and 94% had used proton pump inhibitors.

Key findings:

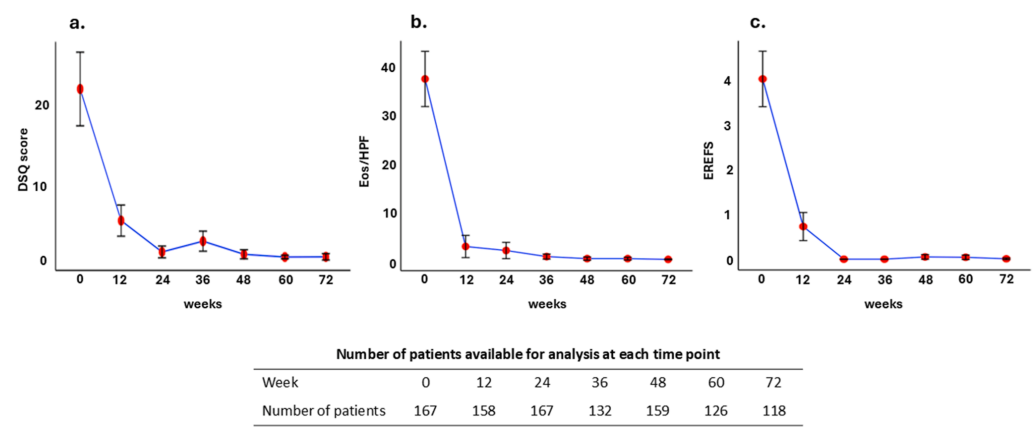
  • DSQ score decreased from 22.14 ± 26.63 to 0.21 ± 2.30, EREFS from 4.95 ± 3.43 to 0.07 ± 0.09, and Eos/HPF from 36.80 ± 31.75 to 0.06 ± 0.46.
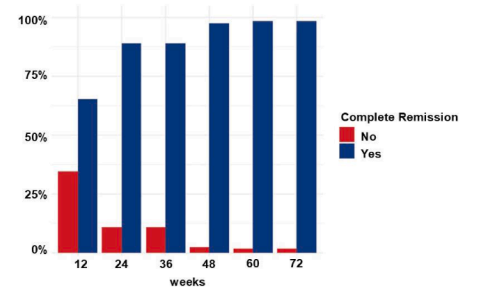
  • Improvements increased with treatment duration. By week 72, 98.3% of patients achieved remission criteria (DSQ ≤5, Eos/HPF ≤15, and EREFS ≤2). 
  • No serious or systemic adverse events were reported, and no patients discontinued treatment due to intolerance. 
Remission criteria were defined as DSQ ≤5, EREFS ≤2, and <15 eos/HPF,
with complete remission achieved when all 3 were met simultaneously.24

Discussion:

  • “Only a small proportion of patients in our cohort had a history of esophageal dilation (8.4%), which may suggest a relatively lower burden of advanced fibrostenotic disease…could partially influence remission rates and should be considered when interpreting the generalizability of our findings to populations with more severe structural disease.”

My take: This study supports the long-term effectiveness of dupilumab in pediatric and adult patients with EoE. It is not clear why there was such a high remission rate in this cohort compared to previous reports.

Related blog posts:

Some good brief YouTube EoE educational videos for families from GIKids.org (with pharmaceutical funding), links:

The Median Arcuate Ligament Syndrome (MALS) Study For Skeptics Like Me

MA Nassif et al. J Pediatr Gastroenterol Nutr. 2026;83:397–403. Outcomes of surgical versus conservative treatment inpediatric median arcuate ligament syndrome

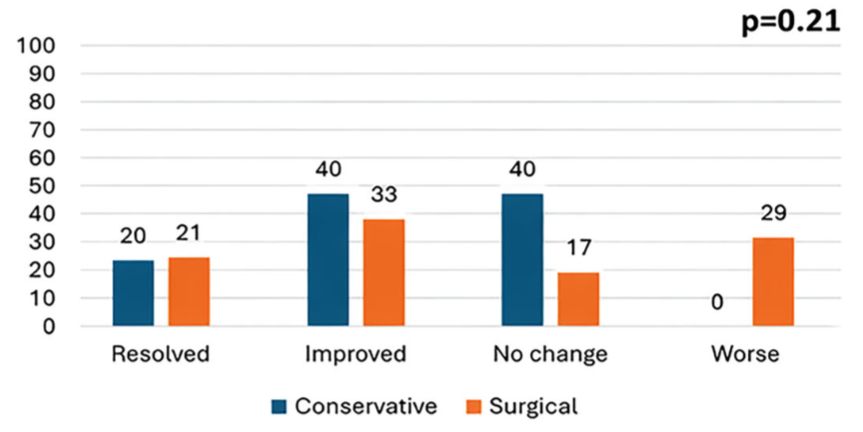
Methods: This was a retrospective pediatric study (n=34) evaluating surgical versus conservative management in pediatric MALS. Conservative therapy included the following: 100% pharmacologic, 80% behavioral, 30% botulinum toxin, 20% neurostimulation.

Key findings:

  • Conservative therapy outcomes (n=10): resolution (20%), improvement (40%), unchanged (40%), and none worsened.
  • Surgical therapy outcomes (n=24) resolution (21%), improvement (33%), unchanged (17%), worsened (29%); thus, these outcomes are not significantly different from the conservative group (p = 0.21). Median hospital stays: 4 days. Postoperative complications occurred in 21%. The one major complication was an intraoperative splenic artery injury in a patient with Ehlers-Danlos Syndrome.
  • Overall, 60% of children with MALS improved with conservative DGBI‐directed therapy and 54% improved with decompression surgery at long‐term follow‐up (at median 9.8 months), despite a robust short‐term postoperative response (87%). At 20 days postop: 52% reported resolution, 35% improved.
Recent follow‐up data show comparable rates of resolution and improvement between the two groups, with no statistically significant difference (p = 0.21).

Discussion points:

  • Other studies have reported higher response rates for MALS surgery: “The newest and largest‐scale review suggests a 70% symptom relief rate in three of six pediatric studies, with follow‐ups of 6–62 months after laparoscopic MALS release.[28]”
  • “A more recent study conducted in 2017 determined that only post‐exertional abdominal pain was a predictor of a good surgical outcome.[31]”
  • “The lack of universally accepted diagnostic criteria for MALS remains a challenge.”

My take: In this study, surgery for MALS did not seem to improve long-term outcome more than DGBI therapy. If one finds celiac artery compression which may be identified in many healthy individuals (10-24% of population), it is unclear to me if an MALS operation is indicated and how to determine when it is indicated.

Related blog posts:

Experts Doubt Benefits of Popular Supplements. Yet, In New Survey – Nearly 80% of Americans Taking Supplements

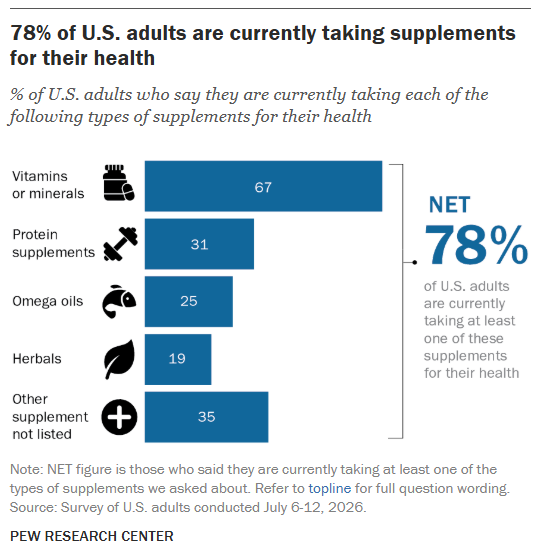
Alice Callahan, NY Times, 9/11/26: Americans Love Supplements, but Experts Doubt Their Benefits “A new survey found that 8 in 10 Americans were taking vitamins, protein powders or other supplements. But experts said there is little evidence for many of these products.”

This article was based on a Pew Research Study with 3,554 U.S. Adults: Emma Kikuchi, Brian Kennedy, Pew Research Center, 9/10/26. About 8 in 10 Americans take supplements, and many see them as important to their health “Supplements are a booming industry, with an estimated global value of $209.5 billion in 2025.”

While the PEW Research study indicated that the majority of individuals taking these supplements thought they were very important for their health, the NY Times article stated the following:

“I would guess that well over 80, 90 percent of supplement consumption doesn’t offer any proven benefit to the person who’s taking it,” said Dr. Pieter Cohen, an associate professor of medicine at Harvard Medical School…

There are good reasons to take dietary supplements, for example to treat a nutrient deficiency or to prevent birth defects, said Dr. Eric Topol, a cardiologist and the founder of the Scripps Research Translational Institute. “But that’s the minority,” he added.

People often take omega-3 supplements because they believe they will improve their heart or brain health, for instance, but most clinical trials have failed to find those benefits.

And most people probably don’t need protein supplements, Dr. Topol said…in reality, most people already consume enough protein from the foods they eat, Dr. Topol said…

Supplement use…has increased in recent decades, said Elizabeth Kantor, an epidemiologist at Memorial Sloan Kettering Cancer Center. In June, she and her colleagues published a study that included more than 63,000 U.S. adults, surveyed between 1999 and 2023. Over that time, the researchers found, supplement use climbed to 60 percent from 51 percent of adults.

The rise in supplement use may be driven in part by claims of their benefits on social media, many of which are unsubstantiated, Dr. Topol said.

My take: Most people do not need or benefit from supplements. In addition, some supplements result in adverse outcomes. Supplements are often needed in individuals who are pregnant and those with previous intestinal resections and restricted diets.

Related blog posts:

How Effective Is Treatment of Eosinophilic Esophagitis In Patients with Rumination Syndrome?

D Yang et al. J Pediatr Gastroenterol Nutr. 2026;83:374–380. Rumination syndrome and eosinophilic esophagitis in children: Defining the relationship

Methods: This was a retrospective cohort study of children with RS and EoE evaluated at our institution from 2016 to 2023.

Key findings:

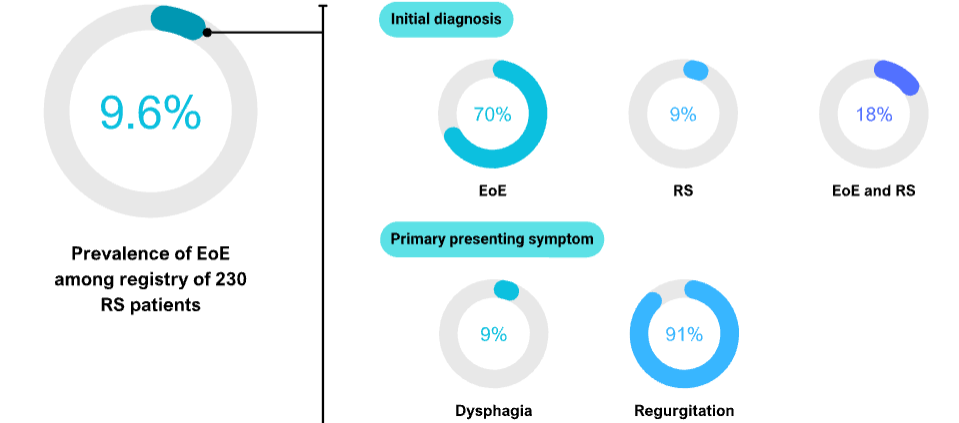
  • In this cohort with rumination syndrome, 22 of 230 had EoE. This is a significantly greater prevalence of EoE (10%) among children with RS than in the general population (0.1%).
  • Among those diagnosed with EoE first (70%), RS diagnosis occurred after a median of 15.4 months.
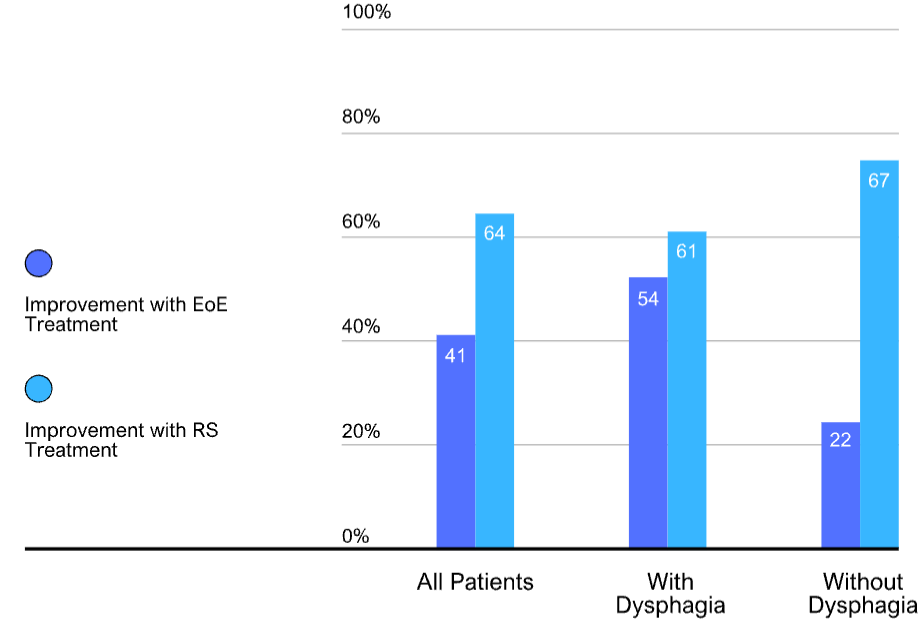
  • EoE treatment led to mucosal remission in 73% and improved dysphagia in 41%, but 86% continued to experience regurgitation.
  • RS treatment, including behavioral therapy and baclofen, improved or resolved regurgitation in 64%.
Improvement in Regurgitation to EoE vs RS ‐based treatments among patients with RS and EoE.
EoE, eosinophilic esophagitis;RS, rumination syndrome

Limitations: retrospective design and potential referral/selection bias in a tertiary care population (specialized center for rumination).

My take: In patients with both EoE and RS, regurgitation continued in 86% of patients who achieved EoE remission. Especially in those without dysphagia, most will need treatment of RS in additon to EoE. In addition, earlier treatment of RS may improve outcomes.

Related blog posts:

Balanced Fluid (like Lactated Ringer’s) vs Saline in Pediatric Sepsis

  • Balamuth F, Weiss SL, Long E, et al. N Engl J Med 2026;395:870-881. Balanced fluid or 0.9% saline in children treated for septic shock. 

Key finding: No significant difference was seen in the incidence of death, new renal-replacement therapy, or persistent kidney dysfunction when fluid resuscitation was administered with balanced fluid as compared with 0.9% saline.

  • MF O’Connor, J Bubeck-Wardenburg. N Engl J Med 2026;395:921-922. Commentary: Fluid Resuscitation in Patients with Sepsis — For Whom the Balance Tolls

From the commentary:

“Balamuth and colleagues report the findings of the Pragmatic Pediatric Trial of Balanced versus Normal Saline Fluid in Sepsis (PRoMPT BOLUS), a large, international, pediatric trial evaluating whether treatment with balanced crystalloid fluid (lactated Ringer’s solution, Plasma-Lyte, or Hartmann’s solution according to clinician discretion) is associated with better kidney-function outcomes than therapy with normal saline in patients with sepsis..

Evaluating more than 8000 children who were well matched with respect to the severity of sepsis at initial presentation, the current trial showed that the nature of fluid administered did not significantly affect patient outcomes…This finding contrasts with those of SMART and the SALT-ED trial as well as those of two other trials…6,7 

As appropriately recognized by Balamuth et al., less-severe illness in the participants in the present trial may have limited the ability of the trial to detect an influence of fluid composition on clinical outcome. Taken together, both adult and pediatric studies suggest that the clinical benefit of balanced-fluid administration correlates directly with the degree of cellular homeostatic disruption in patients with sepsis…

It is important to consider that harm has not been associated with the administration of balanced fluids in any clinical study. With the notable exception of patients with intracranial hypertension, the prudent approach may be to use balanced fluids as standard care in patients with sepsis.”

My take: For most children with sepsis, the outcomes are likely to be similar between those receiving balanced fluids and saline. However, sicker patients, which may be difficult to discern initially, may benefit from balanced fluids.

Related blog posts:

Congratulations to NASPGHAN’S NEWLY ELECTED LEADERS:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
Outcomes in a Large PSC-IBD Cohort

Methods: This population-based study, using an administrative database that covered >99% of 15 million residents, identified 476 incident patients with PSC-IBD. Patients were identified between 2002-2018 with followup through 2021. Median age at PSC diagnosis was 36 years and for IBD 34 years. 73% were diagnosed with IBD and had a median time to PSC diagnosis of 3.2 years. In the 27% with an initial diagnosis of PSC, the median time to IBD diagnosis was 0.9 years. The background comparator group consisted of 54,591 individuals diagnosed with IBD alone.

Key findings:

  • 54% probability of remaining event-free at 10 years. 
  • There were 98 (21%) deaths and 80 (17%) who underwent liver transplant.
  • There were 36 (7.5%) hepatopancreatobiliary cancers (HPBCa) in this cohort
  • A diagnosis of HPBCa was associated with higher progression rates to liver transplant (TIR 20.9) and mortality (TIR 75.0).
  • PSC–IBD patients had approximately 300-fold higher HPBCa and 4-fold higher CRC rates than IBD alone, underscoring their comparative substantial cancer burden.
  • Mortality occurred more frequently post-colectomy (TIR 3.08) and post-cholecystectomy (TIR 3.85) relative to event-free PSC–IBD, but there were no differences in post-surgery incidence of cancer or transplant.

My take: This provides more granular data on the likely outcomes in individuals with PSC-IBD. Identifying individuals who are likely to develop a complicated course is not currently feasible. Current strategies rely on ongoing surveillance.

Related blog posts:

This image captures Kirkjufell Mountain and the Kirkjufellsfoss waterfall in western Iceland. It was a filming location for Game of Thrones, where it was referred to as “Arrowhead Mountain”.

Survival Advantage of Living Donor Liver Transplantation in Large Pediatric Cohort

Yodoshi, T., Kuenzig, M. E., Tang, F., Kajiwara Saito, M., Zizzo, A., Ng, V. L., & Benchimol, E. I. Liver Transplantation 2026, 32(9), 1273–1284. Donor type, social deprivation, and long‑term outcomes in pediatric liver transplantation: A 30‑year population‑based cohort.

Background: Living donor liver transplantation (LDLT) reduces wait‑list mortality in children; this can be due to shorter waiting times, minimal cold ischemia, and healthier donor organs. However, its long‑term advantages over deceased donor liver transplantation (DDLT) and how socioeconomic context shapes outcomes in a universal healthcare system (Canada) remain uncertain. Families with socioeconomic disadvantages may have significant barriers to accessing living donor liver transplantation (LDLT). In additon, caregiver resources, neighborhood deprivation, and health literacy may negatively impact post-transplant outcomes.

Methods: From 1991 to 2021, clinical data was linked to provincial health administrative data, yielding 449 recipients who underwent their first transplant. There were 189 LDLT and 260 deceased donor liver transplantation (DDLT).

Key findings:

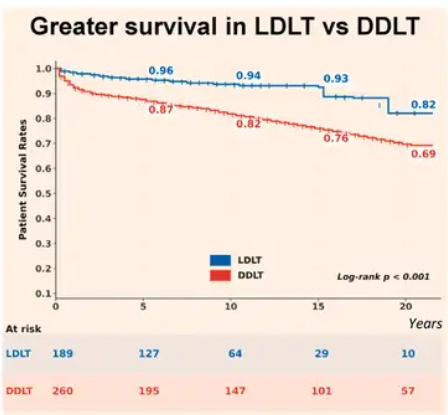
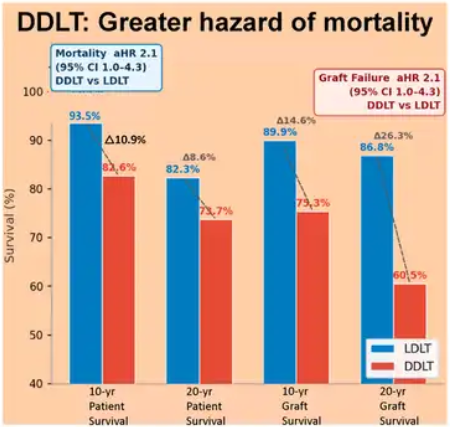
  •  LDLT recipients had superior patient and graft survival. DDLT was associated with a higher risk of mortality [adjusted hazard ratio (aHR) 2.1], graft failure (aHR 2.1), and chronic kidney disease (adjusted subdistribution HR 5.3), compared with LDLT.
  • The absolute survival advantage of 10-15% at 10 years persisted into the third decade.
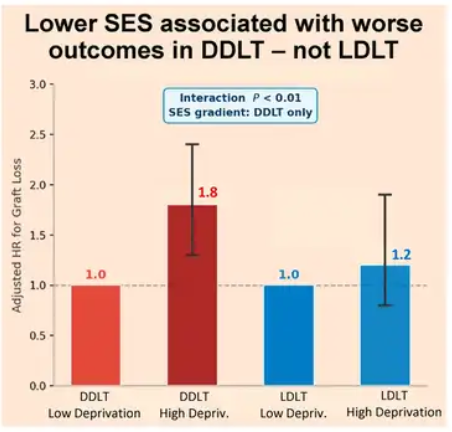
  • LDLT outcomes were less impacted by the socioeconomic disadvantages, with recipients showing comparable outcomes regardless of their SES.
  • The overall incidence of de novo cancer was low (2-3% at 10 years post-LT; most of these cancers were due to PTLD.
  • Limitations: The survival advantage could be in part due to selection bias. Patients with more urgent conditions like PALF were more likely to be DDLT recipients. In addiiton, this study did not adjust severity of illness at time of transplantation.

My take: LDLT is underutilized. More use of LDLT will result in better outcomes.

Related blog posts:

Neurocognitive Deficits in 30% of Short Bowel Cohort

RAL Duister, LE Vlug et al. J Pediatr Gastroenterol Nutr. 2026;83:404–411. Open Access! Cognitive assessment in children with intestinal failure on and weaned off parenteral nutrition

This multicenter international cross-sectional study of children with IF (n=50) examined neurocognitive outcomes (2019-2024); all children were currently receiving home PN or having a history of home PN-dependency.

Key findings:

  • The most common underlying condition was necrotizing enterocolitis (28%); other etiologies included intestinal atresia (20%), midgut volvulus (10%), and intestinal pseudo-obstruction (12%)
  • 21/50 children (42%) received home parenteral nutrition (PN); median PN-duration was 26.8 (7.5–66.5) months
  • Median IQ score was 92.0 (74.3–101.0); 15 children (30%) had very/extremely low IQ (</= 79), both significantly different from the normal population (p < 0.001)

My take: This study provides a good estimate of the percentage of children with intestinal failure/short bowel syndrome with significant neurocognitive impairment: about 30%. The likelihood would be higher in those with proven neurological insults.

Related blog posts:

Seljalandsfoss with a 200 foot watefall cascade. Iceland