Sharp Objects in GI Tract & Good Outcomes

P Quitadamo et al. JPGN 2023; 76: 213-217. Sharp-Pointed Foreign Body Ingestion in Pediatric Age

In this study with 580 children, consecutively recruited from 2016 to 2020, the authors examined outcomes after ingestion of sharp-pointed foreign bodies (FBs).

Key findings:

  • Mean age was 50 months.
  • Sharp/pointed FBs mainly included fragments of metal 270 of 580 (46.55%) and glass 180 of 580 (31%).
  • FBs were endoscopically removed in 79 of 580 (13.6%) children whereas the remaining FBs passed through the gastrointestinal tract over an overall mean time of 29 hours
  • No cases of intestinal perforation nor prolonged retention were observed.
  • The most common metal objects were earrings (n=72). Other objects: screws (n=20), dental works (n=20), nails (n=13), open safety pins (n=7), fish bones (n=65)

My take: I have not had a severe complication from sharp-pointed FBs (in nearly 30 yrs of pediatric GI practice); this article confirms the overall low risk that they pose.

Related blog posts:

Turtle at Chattahoochee Nature Center

Is It a ‘Waste’ to Do Colonic Manometry in Kids with Autism?

A Coe et al. JPGN 2023; 76: 154-159. Evaluation of Chronic Constipation in Children With Autism Spectrum Disorder

In this retrospective study with 56 patients with autism spectrum disorder (ASD) and 123 controls underwent colonic manometry (CM). Key findings:

  • The rate of abnormal CM findings between ASD and matched controls (24% vs 20%, P = 0.78) did not differ significantly
  • The authors noted that higher rates of abnormal CM with duration of constipation and with soiling in children with ASD. However, “even in the minority of cases with abnormal colonic motility, chronic stool retention due to functional constipation over time likely caused impaired motility in the majority of these cases. In 6 of the 8 ASD cases with abnormal CM finding, impaired motility was isolated to the distal colon while normal motility occurred in the proximal colon.”

My take: In this highly-selected group of patients with ASD from specialized motility centers, only 2 had abnormal colonic motility affecting the entire colon. Overall, patients with ASD did NOT have higher rates of abnormal CM studies. Hence, for most children with ASD, CM has little value.

Related blog posts:

Immune Dysregulation and Inflammatory Bowel Disease

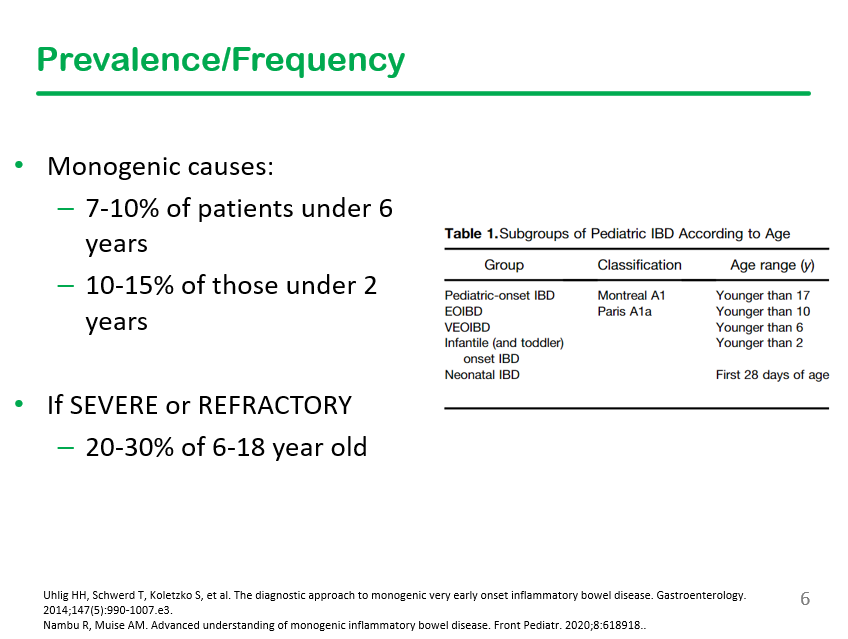
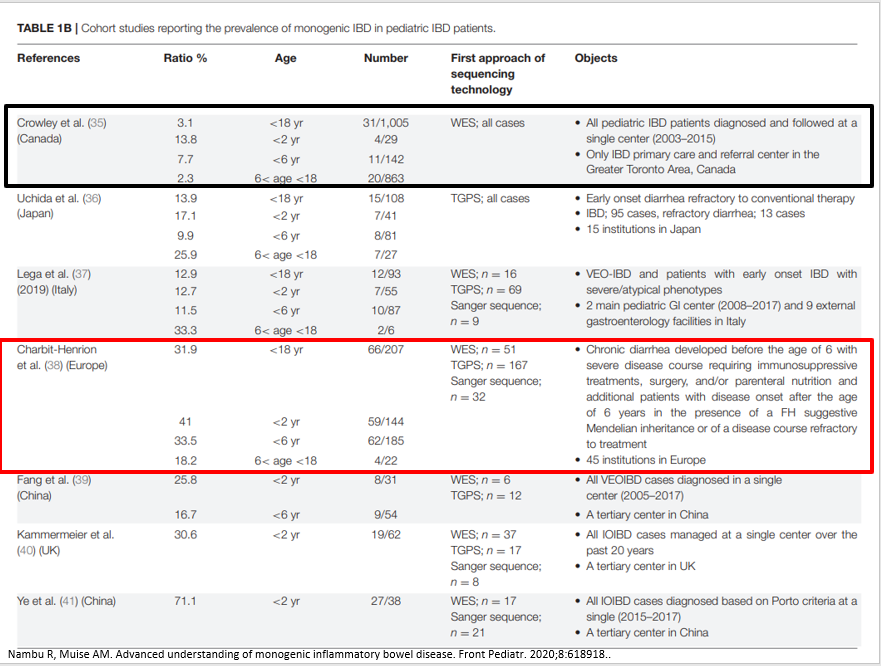
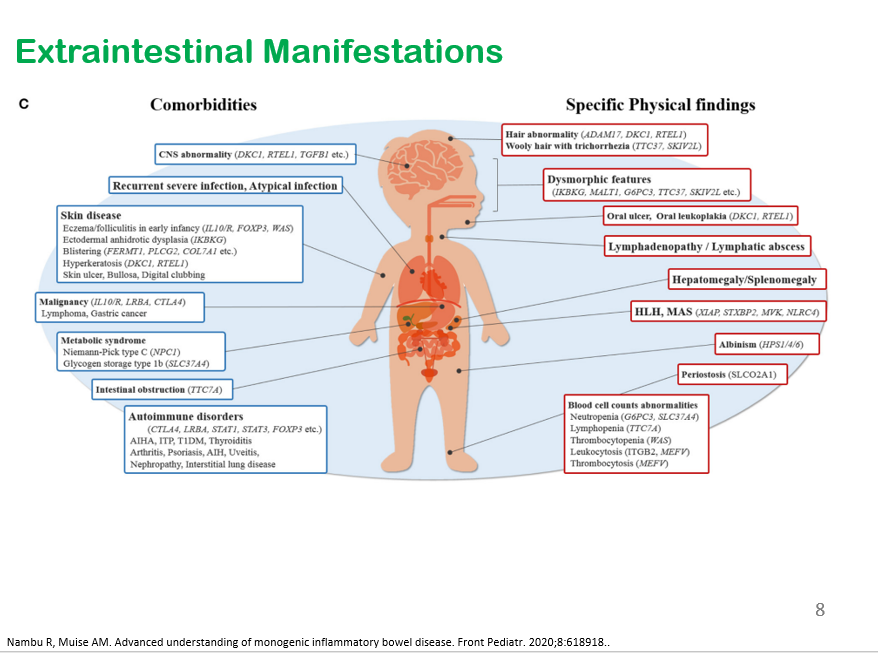
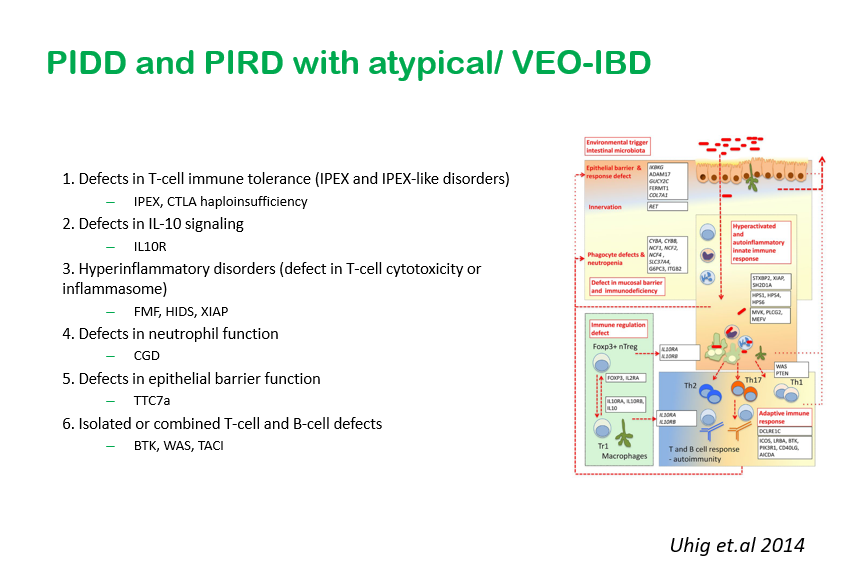
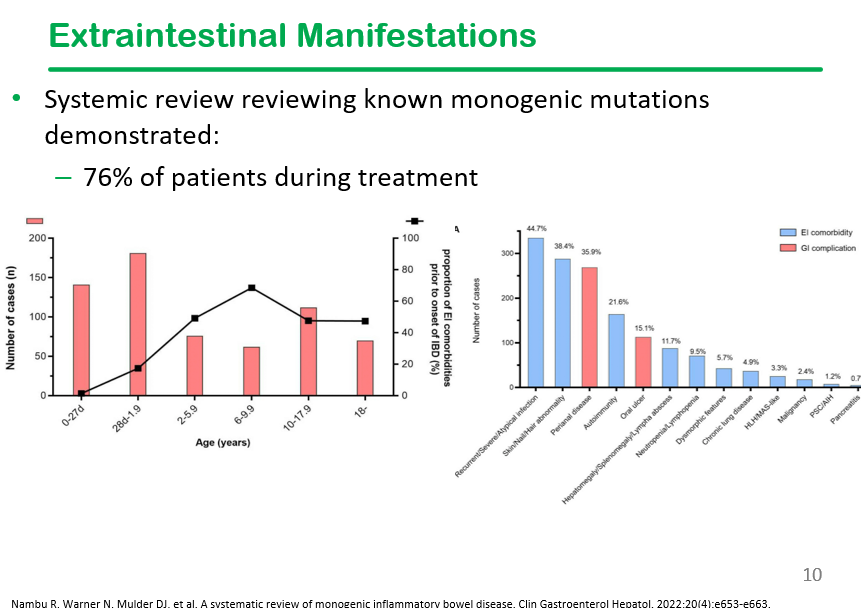
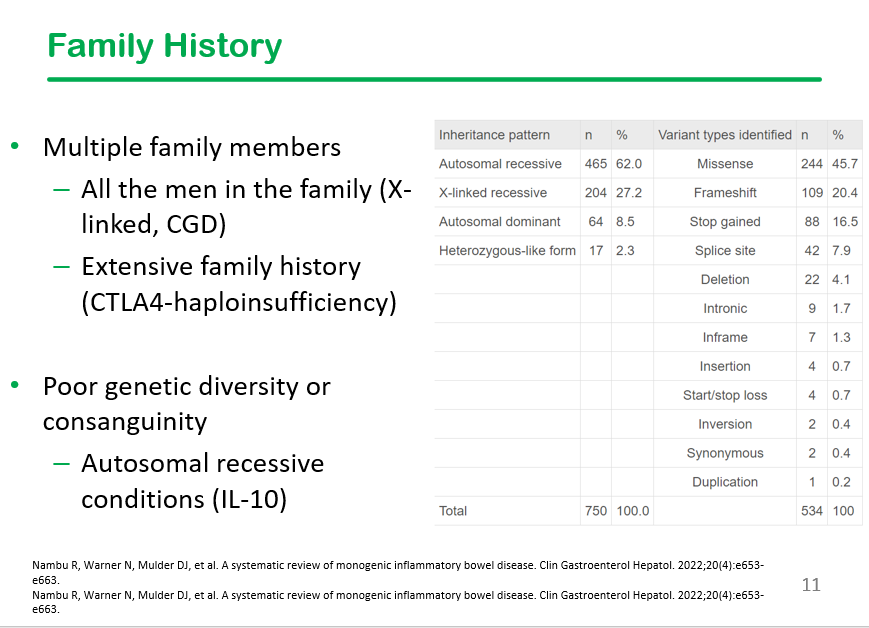
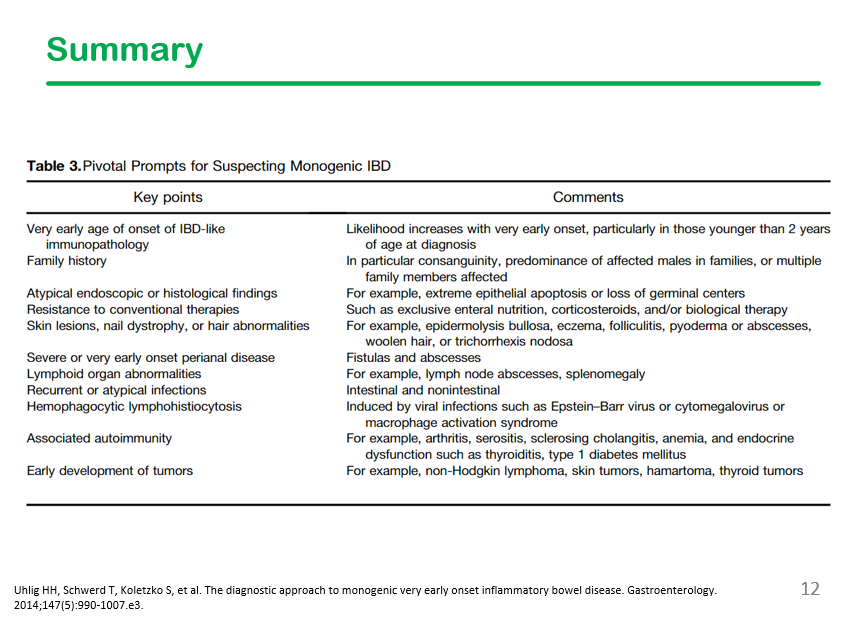
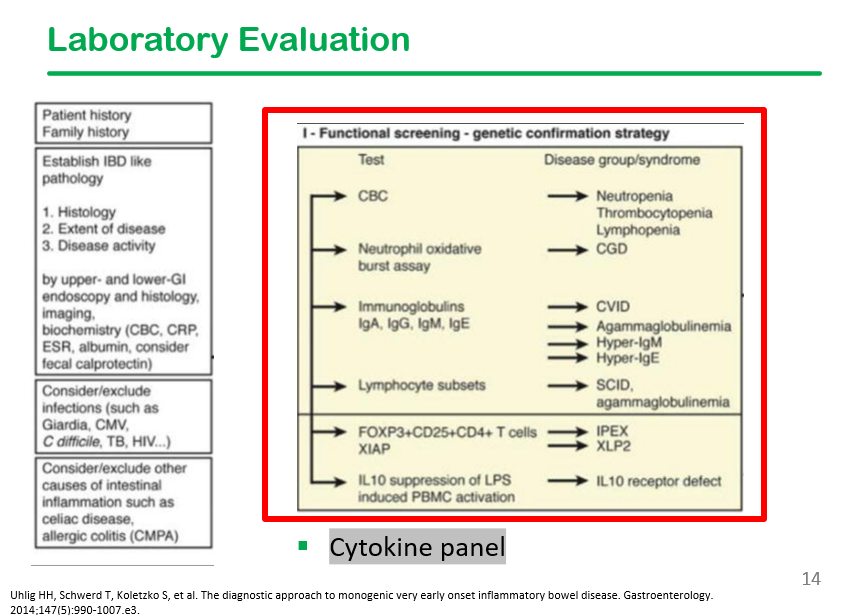
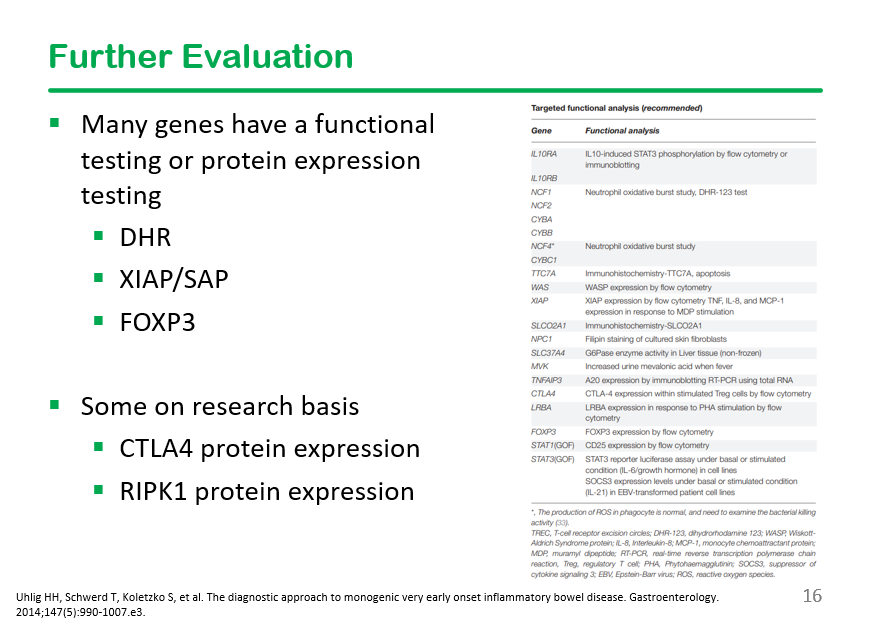
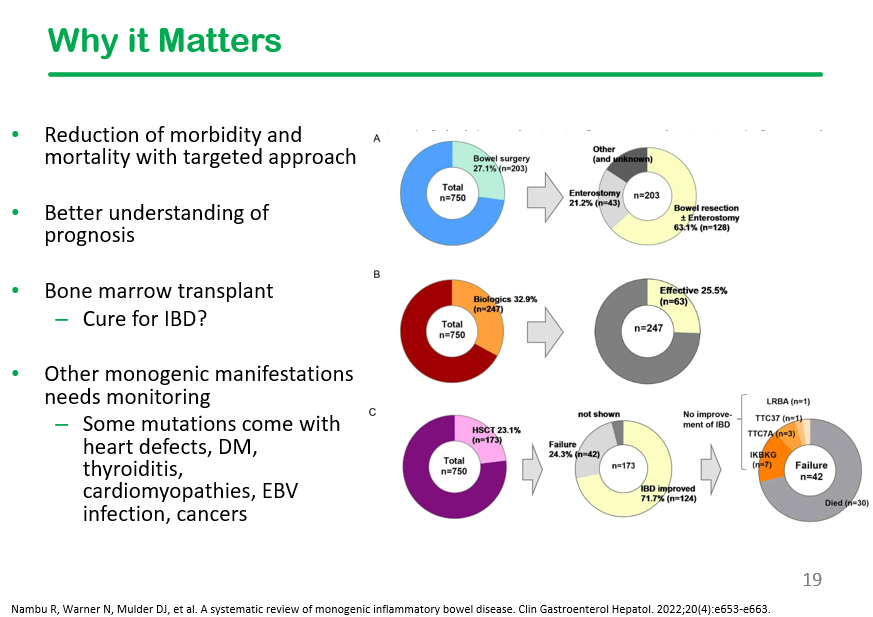
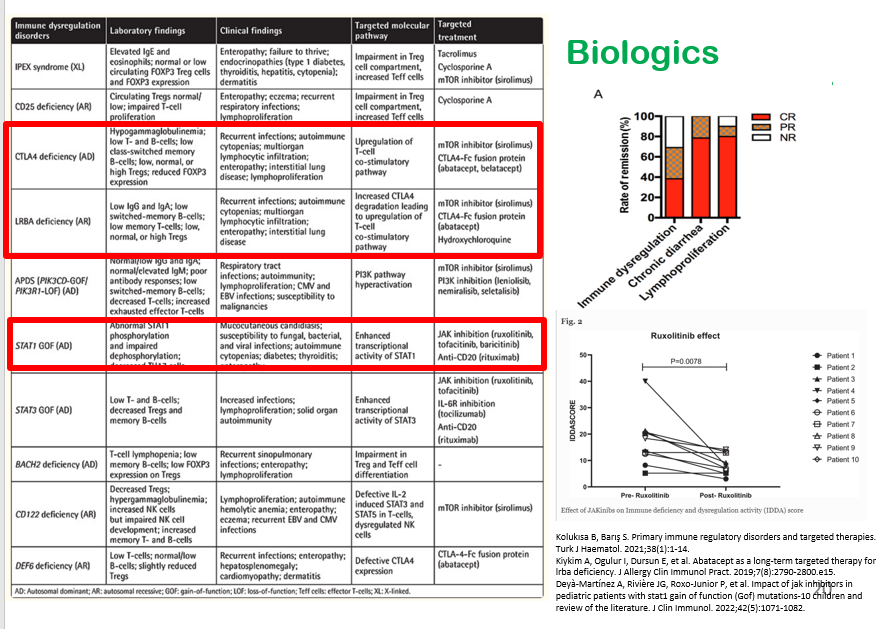
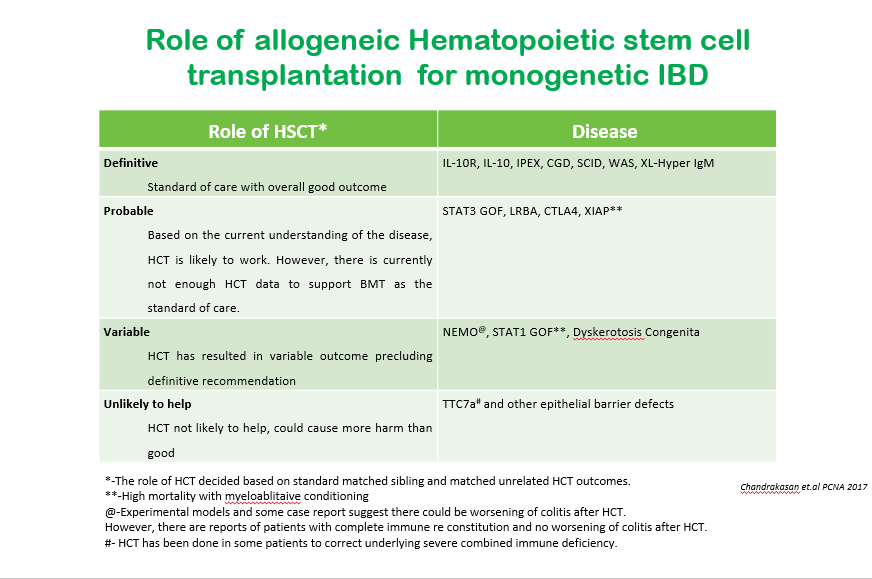
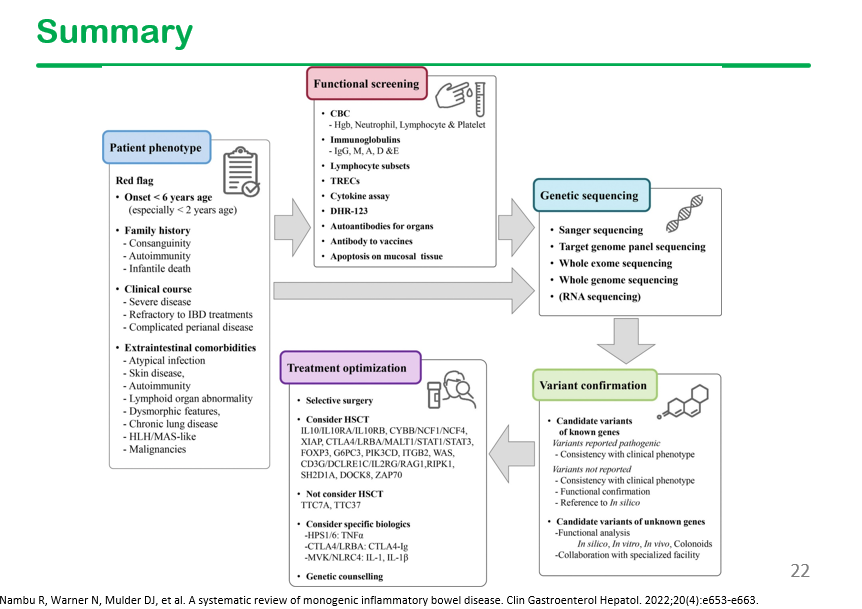
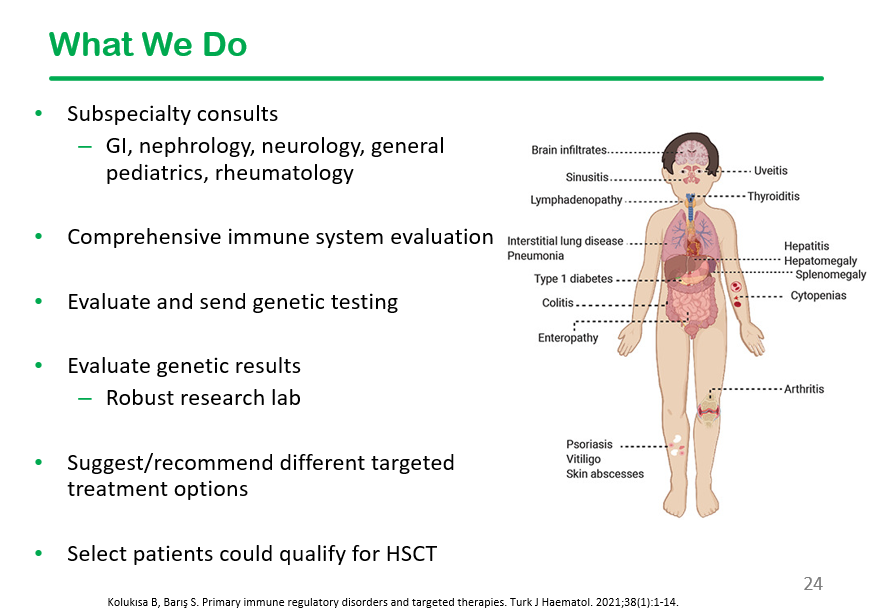
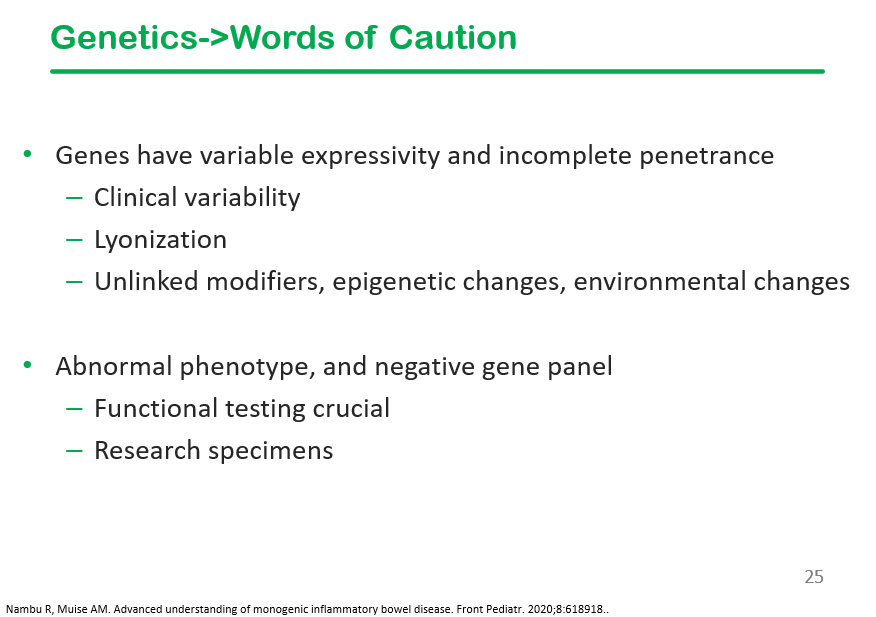
At our center, we are fortunate to work with an immune dysregulation clinic (Dr. Shanmuganathan Chandrakasan, Dr. Taylor Fitch) that helps sort out patients with inflammatory bowel disease with underlying monogenetic disorders. This is very important as specific treatments, including hematopoietic stem cell transplants (HCST), may be needed. The likelihood of an underlying monogenetic disorder is much more frequent in the VEO population. A recent talk on this topic by Taylor Fitch was given to our group. Here are some of the slides:

Generally, about 2% of those older than 6 years of age have monogenetic disorders, but it is much higher in those with severe or refractory disease.

This slide shows six major categories of immune defects.

This slide shows the high frequency of extraintestinal manifestations in patients with monogenetic disorders, particularly recurrent infections, skin/hair abnormalities, and autoimmunity. Perianal disease is also frequent in this population.

In the discussion, it was noted that DHR testing is often unreliable, especially if the specimen is not run promptly.

My take: I have had several patients with IBD/immune dysregulation, including a patient with CTLA4 and a patient with TTC7A. Making these diagnoses led to specific treatment recommendations. The patient with CTLA4 is doing well with abatacept therapy.

For those in Atlanta, a referral can be made via EPIC order and/or via contact with immune dysregulation team members. Epic order:

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

IBD Updates: Low Lymphoma Risk, Fewer Biopsies for Ulcerative Colitis, MRE Distinguishes Backwash Ileitis, Beta-Fructans and IBD Activity

M Egberg et al. AJC 2023: 118: 354-359. Low Risk of Lymphoma in Pediatric Patients Treated for Inflammatory Bowel Disease

Key finding:

  • Using a database with 10,777 pediatric patients (2007-2018) with more than 28,000 patient years, there were 5 lymphomas reported. 4 had received thiopurines and none received anti-TNF monotherapy.

My take: This is a very reassuring study for the safety of anti-TNF agents.

AE Mikolajczyk et al. Inflamm Bowel Dis 2023; 29: 222-227. Assessment of the Degree of Variation of Histologic Inflammation in Ulcerative Colitis

  • In this retrospective study with 92 patients (182 colonoscopies), the authors found “minimal variability between degree of inflammation among biopsy fragments within and among different colorectal segments in UC, suggesting that even a single biopsy would adequately reflect the inflammation of the entire colorectum.”

My take: This study suggests that taking biopsies from every segment of the colon (when it looks uniform) is usually not needed, unless the purpose is to look for dysplasia. Also, it is worth recognizing that individuals with primary sclerosing cholangitis often have greater histologic activity in the right colon.

References only:

Understanding the Laxative Effects of Coffee

V Mehta et al. JPGN 2023; 76: 20-24. Open Access! Effect of Caffeine on Colonic Manometry in Children

Methods: A prospective study of pediatric patients (N=16) undergoing standard colonic motility testing that were able to consume caffeinated coffee, decaffeinated coffee, and caffeine tablet during colonic manometry (with normal response to bisacodyl)

Key findings:

  • Caffeinated coffee resulted in a higher AUC, motility index (MI), and time to HAPC compared with decaffeinated coffee (P < 0.05).
  • Urge to defecate, or actual bowel movement in 100% (n = 16) of patients after intraluminal bisacodyl (IB), compared to 81% (n = 13) after caffeinated coffee (CC), 56% (n= 9) after caffeine tablet (CT), and 50% (n = 8) after decaffeinated coffee (DC)
  • Based on AUC between T = 1 and T = 60 minutes after each agent, the response of the colon to IB was more robust, relative to other agents (P < 0.05). Both CC and DC had resulted in a higher AUC compared to CT (P < 0.05), but no significant difference between CC and DC 
  • Caffeine is indeed a colonic stimulant; however, other components of caffeinated and non-caffeinated beverages likely induce colonic response as well
  • Limitation: Study population: patients required motility testing for refractory chronic constipation Therefore, they do not represent a normal population

My take: As with adult patients, coffee (both caffeinated and decaffeinated) acts as a colonic stimulant. Though, it is relatively weak compared to bisacodyl

Related blog posts:

What I Don’t Want to See: Catastrophic Antiphospholipid Syndrome

SA Kahn et al. NEJM 2023; 388: 358-368. Case 3-2023: A 16-Year-Old Girl with Abdominal Pain and Bloody Diarrhea

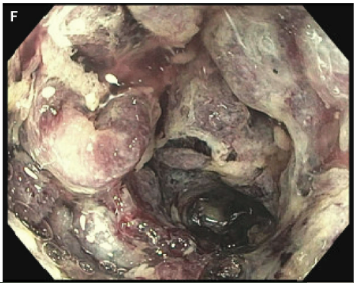
This case report of a girl presenting with abdominal pain and diarrhea identifies a rare etiology, catastrophic antiphospholipid syndrome (CAPS). CAPS can result in ischemic colitis. This patient underwent a colonoscopy which was normal in rectum but then became abnormal in the sigmoid colon:

“CAPS is thought to result from the binding of antiphospholipid antibodies to cell surfaces, which activates endothelial cells, monocytes, and platelets and leads to inflammation, complement activation, and thrombosis. The formation of thrombi in patients with antiphospholipid antibodies is thought to be a multihit process.7 The presence of antiphospholipid antibodies in the blood is the first event, but the antibodies typically do not cause disease until another event occurs.”

Management of antiphospholipid antibodies: “Thrombotic disease manifestations are important in guiding therapy. For patients with antiphospholipid antibodies and no history of clotting, anticoagulation for primary thromboprophylaxis is generally not recommended…For patients with antiphospholipid antibodies and a history of unprovoked thrombosis (e.g., patients with APS), long-term thromboprophylaxis is recommended…For patients with more severe presentations — such as this patient, who had CAPS with thrombosis in multiple organs — treatment is more aggressive and involves targeting multiple steps within the CAPS cascade.”

From ChatGPT

My take: This 16 yo had a severe presentation and the case is a reminder that there are multiple reasons besides IBD for a teenager to have bloody diarrhea and abdominal pain.

Related blog posts:

Another Study Justifying Higher Infliximab Dosing in Pediatrics

S Lawrence et al. JPGN 2022; 75: 601-607. Optimized Infliximab Induction Predicts Better Long-Term Clinical and Biomarker Outcomes Compared to Standard Induction Dosing

In this retrospective observational cohort study (n=140 children), patients were started on 5 mg/kg/dose during induction. 78 children had “optimized dosing” with an infliximab level drawn prior to 3rd dose. A level <15 mcg/g was considered subtherapeutic. It is noted that combination therapy was much higher in the standard (not optimized) group (95% vs 42%).

Key findings:

  • Combined corticosteroid-free clinical and biomarker remission (CRP < 5 mg/L) was higher in the optimized compared to the standard cohort [65/78 (83%) vs 25/62 (40%), P < 0.001]. Remission rates correlated with trough levels; those in clinical remission had a median level of 3.6 compared to 2.0 in those without clinical remission.
  • The median post-induction trough was higher in the optimized group 4.2 mg/L vs 1.9 mg/L.
  • The optimized group were significantly more likely to achieve a therapeutic level (5 mg/L or greater): 44% vs 18%.

My take:

  1. The “optimized” group was not very well optimized –only 44% had a therapeutic level >5, but still performed much better than the standard group (which more often had combination therapy). This indicates a need to start with higher doses and reinforces the need for therapeutic drug monitoring.
  2. This study further shows that 5 mg/kg dosing is inadequate. In the standard group, even with combination therapy, only 18% achieved therapeutic levels.
  3. This article will be another one to include to try to persuade insurance companies that kids are different and need higher doses of infliximab.
  4. Though inconvenient for families, dosing more frequently is more effective than higher doses for improving trough levels (ie 5 mg/kg q4 wks results in better trough levels than 10 mg/kg q8 wks).

Here are some additional references on this topic (from a recent appeal):

For pediatrics, studies have shown that utilizing dosing of 5 mg/kg/dose results in subtherapeutic dosing in around 80%, especially if low albumin.  This places patients at high risk for developing antibodies to infliximab and complications from Crohn’s disease.

  1. LE Bauman et al Inflamm Bowel Dis 2020 Feb 11;26(3):429-439. Improved Population Pharmacokinetic Model for Predicting Optimized Infliximab Exposure in Pediatric Inflammatory Bowel Disease. The authors identified 228 pediatric patients with IBD and developed a pharmacokinetic model using weight, albumin, sedimentation rate and antibodies to infliximab (ATI) to help predict infliximab dosing that would achieve a therapeutic trough level (>5 mcg/mL). In their study, they also simulated 1000 patients and found that only 24% of patients receiving 5 mg/kg q8weeks achieved a therapeutic level; this increased to 56% for 10 mg/kg q8weeks
  2. Frymoyer A, Piester TL, Park KT. JPGN. 2016;62(5):723-727. Infliximab dosing strategies and predicted trough exposure in children with Crohn’s disease. Only 21% of children in this modeling study achieved a trough level >3 if the albumin was 3 or lower. The goal for trough level is NOW >5.
  3. JM Shapiro et al. JPGN 2016; 62: 867-72. Durability of Infliximab Is Associated With Disease Extent in Children With Inflammatory Bowel Disease.  In this study with 98 pediatric patients, 70% with extensive disease required dose escalation.
  4. Ungar B, Levy I, Yavne Y, et al. Clin Gastroenterol Hepatol. 2016;14(4):550-557.e552. Optimizing Anti-TNF-alpha therapy: serum levels of Infliximab and Adalimumab are associated with mucosal healing in patients with inflammatory bowel diseases. Getting good levels important to achieve healing/remission.
  5. NV Castelle et al. Clin Gastroenterol Hepatol 2022; 20: 465-467. Patients With Low Drug Levels or Antibodies to a Prior Anti-Tumor Necrosis Factor Are More Likely to Develop Antibodies to a Subsequent Anti-Tumor Necrosis Factor. Good levels are associated wtih fewer antibodies to infliximab.

Related blog posts:

On a recent trip to Florida, we picked up more than 40 sand dollars on a morning beach walk. This was during a cold snap, at low tide and after a storm.

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

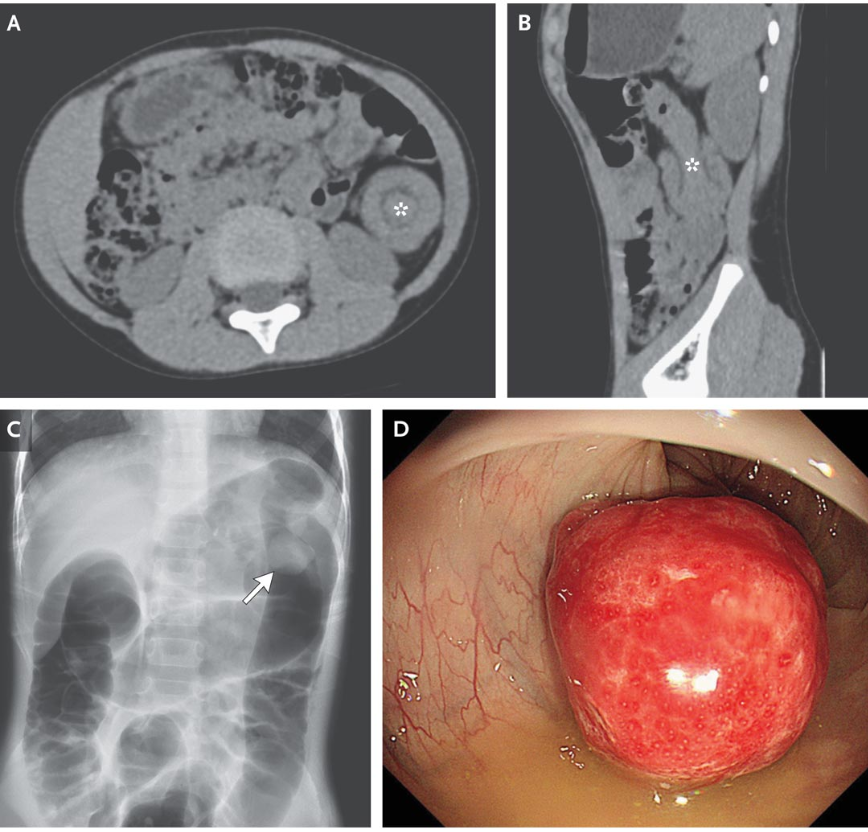
Image from NEJM: Colocolonic Intussusception

From NEJM Twitter feed:

“Colonic intussusception is a rare cause of intestinal obstruction in children, and most cases are ileocolic rather than colocolonic. A pathologic lead point, typically a juvenile polyp, is present in the majority of cases.” In this case, panel D shows a 2.5 cm pedunculated polyp which was thought to be the lead point.

Related blog posts:

“Is Salt at Fault?” in Inflammatory Bowel Disease

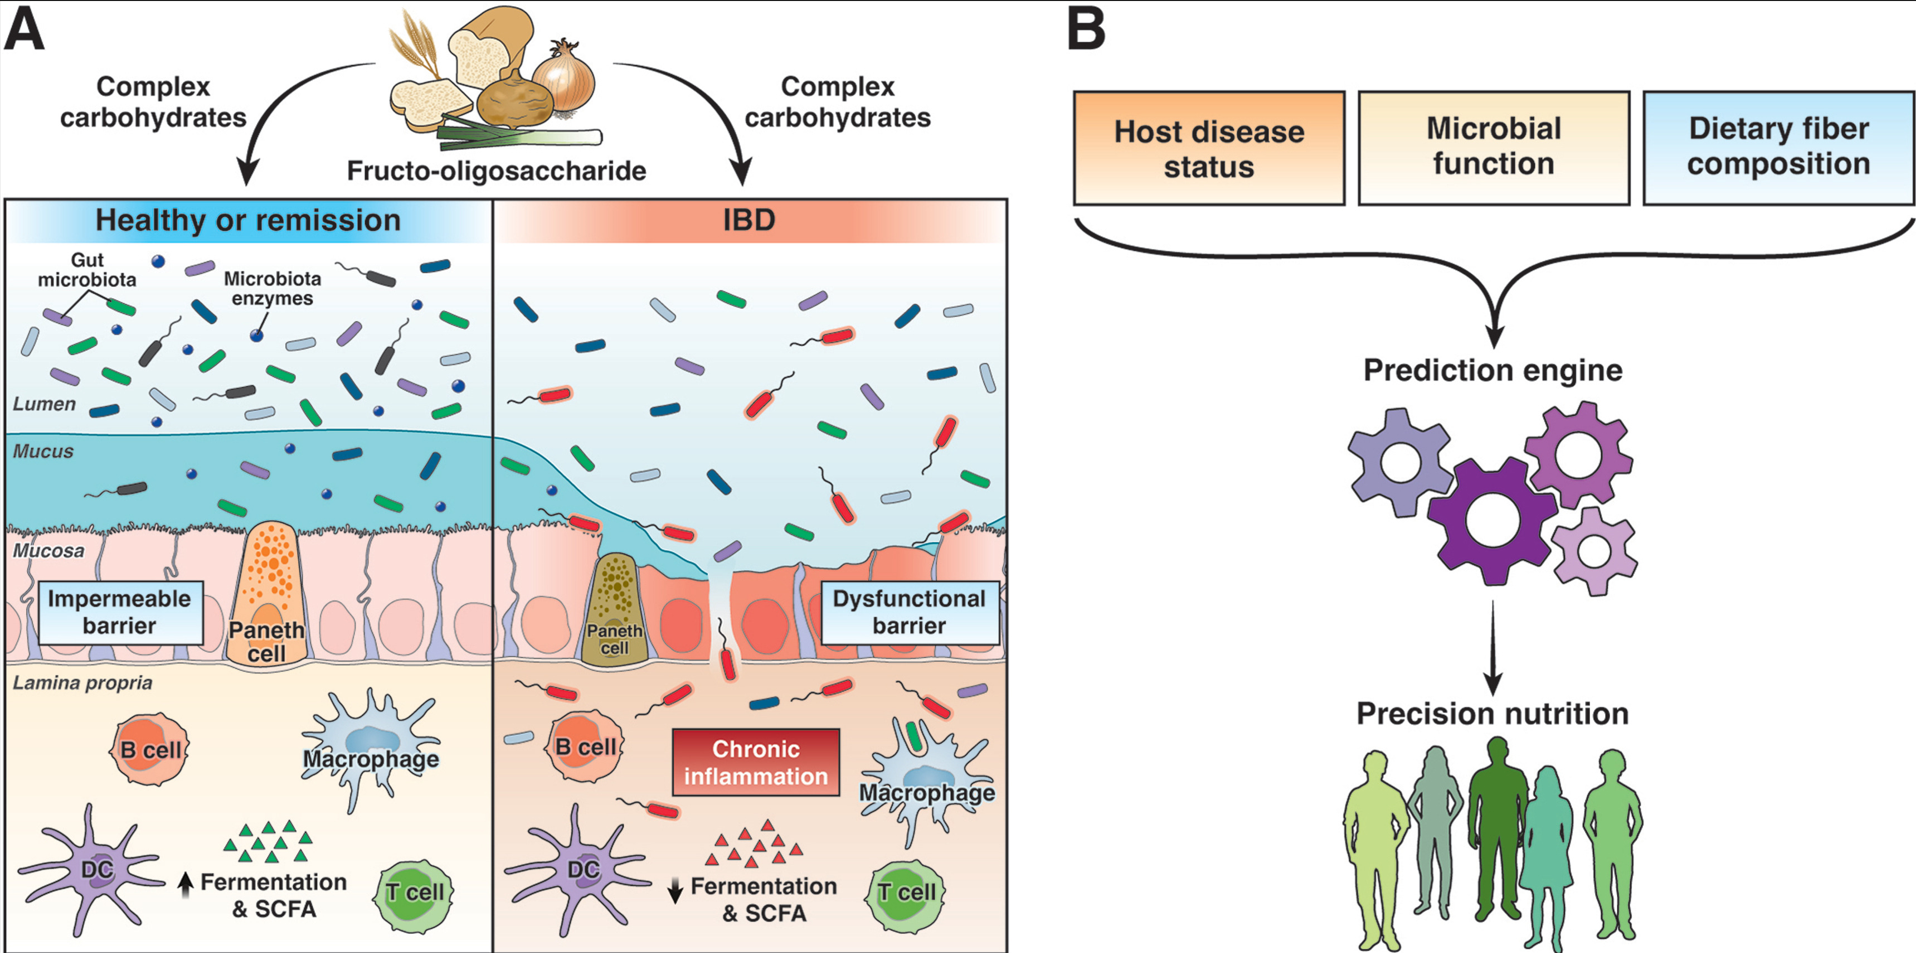
R Kuang et al. Inflamm Bowel Dis 2023; 29: 140-150. Is Salt at Fault? Dietary Salt Consumption and Inflammatory Bowel Disease

This review looks at the potential role of salt in relation to the epidemiology of inflammatory bowel disease. The general focus is that the prevalence/incidence of IBD has been increasing and there must be environmental/dietary factors involved. Could salt be one of those causal factors or is it merely a temporal association?

Key points:

  • Ultra-processed foods make up more than half of the daily caloric intake in developed countries such as the United States! and Canada and between one-third to one-fifth of diets in middle-income countries such as Brazil and Mexico.. Ultra-processed foods involve “fractioning of whole foods into substances, chemical modifications of these substances, frequent use of cosmetic additives and sophisticated packaging that allow producers to create highly profitable, convenient, and hyperpalatable products.” Ultra-processed foods are typically high in sugar, unhealthy fats, and salt and low in dietary fiber, protein, vitamins, and minerals. They are also calorie dense. For Americans, the primary source of sodium in the diet is from commercially processed foods.
  • At present, the typical American consumes over 40% more salt on a daily basis than is re-commended. Added salt is a key component of UPFs, whose increased consumption has been closely linked to this rise in the IBD incidence. Even though salt is a key component of UPFs, it has received limited attention in the investigation of IBD...Excess salt contributes to greater monocyte and T-cell-driven inflammation and a parallel loss of immunoregulatory mechanisms involving M2 macrophages and Tregs in the Th17 axis.
  • The authors argue that improvement in IBD with exclusive enteral nutrition is another factor indicating a potential role for salt reduction as beneficial. “Although these ultra-processed liquid nutrition formulas were high in sugars, emulsifiers, and carrageenan, they were very low in sodium content.”

My take: It is not clear what impact salt has on IBD. However, too much salt causes problems well beyond hypertension and may contribute to several inflammatory conditions, including IBD, asthma, and rheumatoid arthritis.

Related blog posts:

Unrelated website information: IBD-EII is a website which has tried to organize/summarize some of the more important IBD articles including a timeline of these publications and evidence for specific medications.

Atlanta Botanical Gardens. Garden Nights, Holiday Lights exhibit

Useful Endoscopic Tricks for Stricture Management and Magnets

JL Yasuda et al. JPGN 2023; 76: 77-79. Measurement of Stricture Dimensions Using a Visual Comparative Estimation Method With Biopsy Forceps During Endoscopy

This quick study looked at using biopsy forceps in 191 endoscopies to estimate esophageal stricture narrowing. Key findings:

  • Lin’s concordance correlation coefficient was 0.92 (95% confidence interval: 0.89–0.94) between the visual diameter estimates and the fluoroscopic stricture measurements.
  • Correlation was strongest for smaller to mid-sized stricture diameters
  • Yellow biopsy forceps open wide to ~6 mm and standard orange biopsy forceps ~7 mm
  • Dimensions of the actual scope can be helpful in estimating a stricture. Some pediatric scope have 5-6 mm diameter and standard scopes ranging from 8.0-9.8 mm

My take: This study shows that commonly available endoscopic tools can be used to more accurately estimate stricture diameter.

Related blog posts:

K Guilcher et al. JPGN Reports 3(4):p e257, November 2022. | DOI: 10.1097/PG9.000000000000025. Open Access! Innovative Makeshift Technique for Removing Ingested Rare Earth Magnets “In this case, a makeshift technique of a prototype magnet in a net attracted the buried magnets within the food bolus and allowed successful retrieval of all intragastric magnets at once.” My take: This is a clever way to co-opt the enemy (the magnets). However, other useful approaches: 1. Many times an endoscopic forceps will attract the magnets 2. Using fluoroscopy, can be helpful in locating difficult to visualize objects

Atlanta Botanical Gardens: Garden Lights, Holiday Lights (with and without 3-D glasses)