Celiac Disease Identified After Family Index Case

MJ Gould et al. JPGN 2023; 76: 49-52. Characteristics of Pediatric Patients With Celiac Disease Identified Due to an Affected First-Degree Family Member

In this retrospective study, 49 patients were screened due to an affected first-degree relative with celiac disease. They were compared to 178 patients who were screened for other clinical indications. Key findings:

  • Although 51% of patients screened due to an affected first-degree relative were asymptomatic, their disease histology and TTG levels were as severe as those screened for symptoms suggestive of celiac disease (in the comparison group 16% were asymptomatic). 

Comments:

  1. “Previous studies have shown that asymptomatic adolescents and those diagnosed with CD by serologic screening are less likely to adhere strictly to a GFD when compared to younger children and adults diagnosed because of classical symptoms” (Dig Dis Sci. 2008 Jun; 53(6): 1573–1581).”
  2. Some individuals who are thought to be asymptomatic, clinically improve with a gluten free diet (GFD). In one study, “the GFD group also had reduced indigestion (P=.006), reflux (P=.05), and anxiety (P=.025), and better health, based on the visual analog scale (P=.017), than the gluten-containing diet group” (Gastroenterology  2014 Sep;147(3):610-617).

My take: In this study, being asymptomatic (identified due to affected first-degree relative) was NOT associated with milder celiac disease based on serology or histology.

Relate blog posts:

Garden Lights, Holiday Lights at Atlanta Botanical Gardens

IBD Updates: Understanding Newest IBD Therapies for Kids- Bowel Sounds, Hispanic Patients with IBD, More on Intestinal Ultrasound

Bowel Sounds Link: Joel Rosh talks small molecules and biologics

This is another good chat. Dr. Rosh provides a lot of information about the newest IBD agents. Overall, the episode indicates a very enthusiastic experience with IL-23 targeting agents like risankizumab (perhaps the ‘Michael Jordan’ of biologics) and with JAK agents like tofacitinib and upadacitinib. Dr. Rosh’s experience with regard to safety of these newer agents has been very positive. For tofacitinib, the typical dosing alluded to in the podcast was 10 mg twice a day (not three times a day). The potential adverse effects, though unlikely in the pediatric population, are carefully discussed with families and monitored.

So far, Dr. Rosh has not found a niche for ozanimod. In addition, he briefly discusses therapeutic drug monitoring. With regard to using vedolizumab as a first-line agent for ulcerative colitis, he often uses the VARSITY study (BE Sands et al NEJM 2019; 381: 1215-26) to justify this to payers. There is a sad element to the podcast though –Dr. Rosh admits to being a lifelong Mets fan!

Related blog posts:

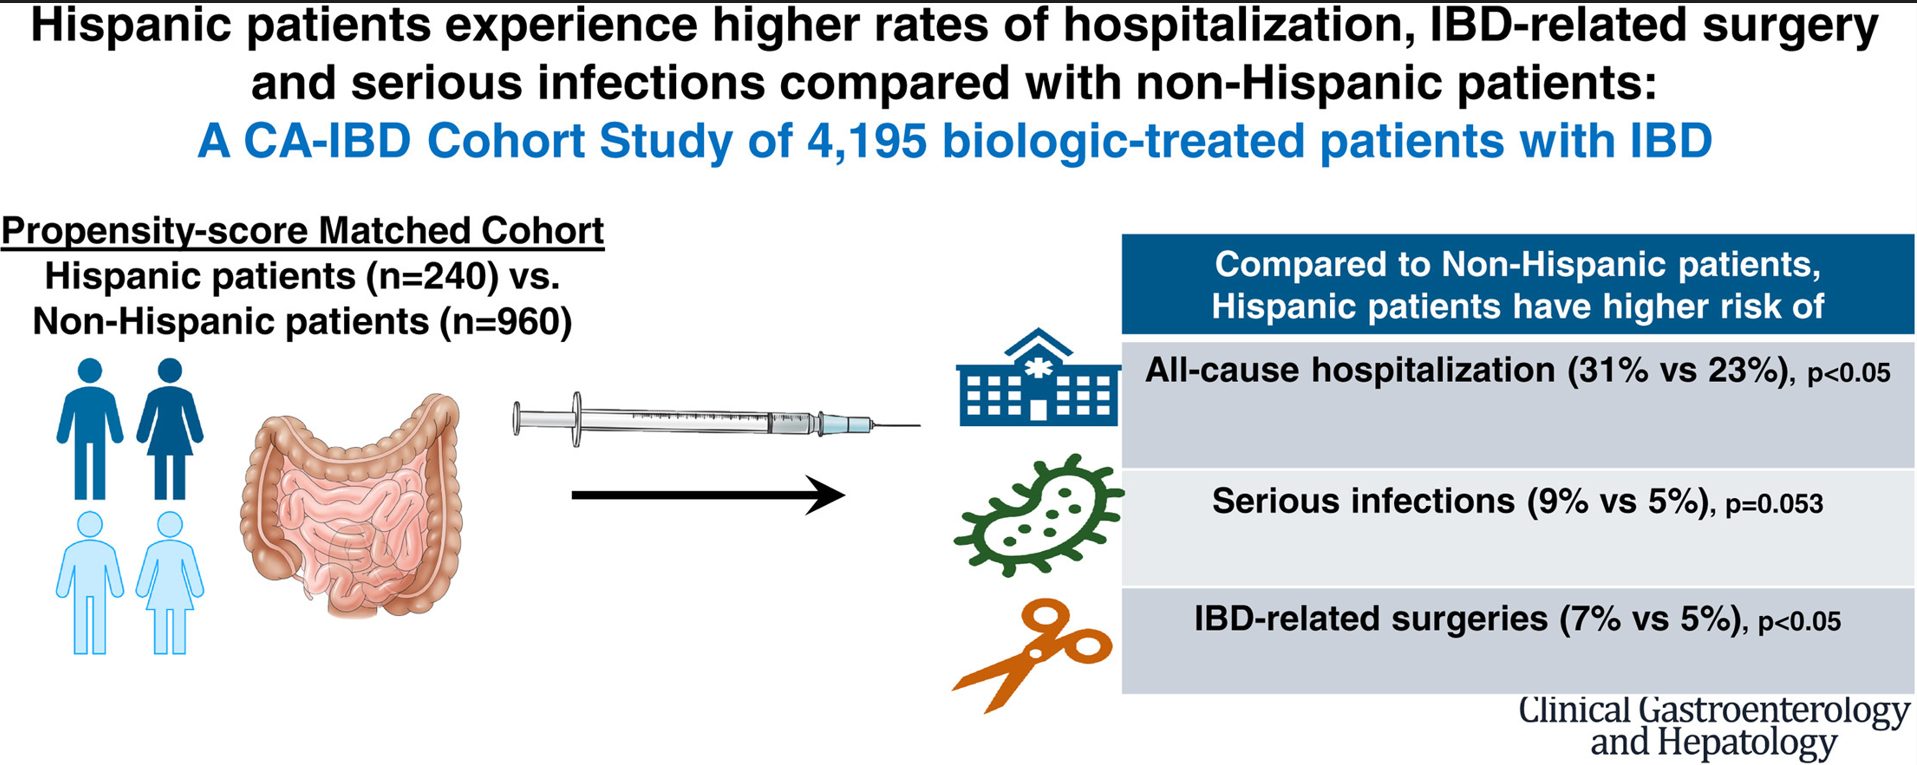
NH Nguyen et al. Clin Gastroenterol Hepatol 2023; 21: 173-181. Open Access! Effectiveness and Safety of Biologic Therapy in Hispanic Vs Non-Hispanic Patients With Inflammatory Bowel Diseases: A CA-IBD Cohort Study

Key findings in this retrospective study with 240 Hispanic patients:

  • Within 1 year of biologic initiation, Hispanic patients had higher rates of hospitalizations (31% vs 23%; adjusted hazard ratio [aHR], 1.32; 95% CI, 1.01–1.74) and IBD-related surgery (7.1% vs 4.6%; aHR, 2.00; 95% CI, 1.07–3.72), with a trend toward higher risk of serious infections (8.8% vs 4.9%; aHR, 1.74; 95% CI, 0.99–3.05).
  • The authors state “these findings suggest that biologic agents may not be as effective or safe in Hispanic patients as they are in non-Hispanic Caucasians… Besides biological factors, socioeconomic factors related to costs and access to care, which contribute to delayed initiation of biologics, and/or limited postinitiation monitoring, leading to higher rates of unplanned health care utilization.”

T Kucharzik et al. Clin Gastroenterol Hepatol 2023; 21: 153-163. Open Access! Early Ultrasound Response and Progressive Transmural Remission After Treatment With Ustekinumab in Crohn’s Disease (STARDUST study)

Key findings:

  • IUS showed that ustekinumab-treated CD patients achieved progressive IUS response (46.3%) and transmural remission (24.1%) through week 48, with a more robust response in the colon and biologic-naive patients
  • Fair/moderate reliability (κ = 0.21–0.51) was observed between week 4 IUS response and week 48 overall endoscopic response and fecal calprotectin/complete biomarker outcomes.

Meds for Obesity: AAP Guidelines

Selected recommendations:

  • In children 10 y and older, pediatricians and other PHCPs should evaluate for lipid abnormalities, abnormal glucose metabolism, and abnormal liver function in children and adolescents with obesity (BMI ≥95th percentile) and for lipid abnormalities in children and adolescents with overweight (BMI ≥85th percentile to <95th percentile). 
  • Pediatricians and other PHCPs should provide or refer children 6 y and older (Grade B) and may provide or refer children 2 through 5 y of age (Grade C) with overweight (BMI ≥85th percentile to <95th percentile) and obesity (BMI ≥95th percentile) to intensive health behavior and lifestyle treatment.
  • Pediatricians and other PHCPs should offer adolescents 12 y and older with obesity (BMI ≥95th percentile) wt loss pharmacotherapy, according to medication indications, risks, and benefits, as an adjunct to health behavior and lifestyle treatment. 
  • Pediatricians and other PHCPs should offer referral for adolescents 13 y and older with severe obesity (BMI ≥120% of the 95th percentile for age and sex) for evaluation for metabolic and bariatric surgery to local or regional comprehensive multidisciplinary pediatric metabolic and bariatric surgery centers. 

My take: As with the AGA, the AAP has now recommended the widespread adoption of pharmacologic therapy for use in patients with obesity. It appears that treatment would be required indefinitely, though, given the likelihood of weight gain when treatment is stopped (reviewed on a future post).

Related blot posts:

 Garden Lights, Holiday Lights at Atlanta Botanical Gardens
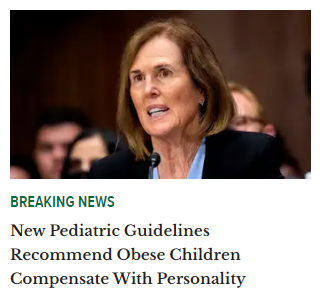
The Onion’s Take on the New AAP Guidelines:

Why Vonoprazan Is More Effective For Erosive Esophagitis Than a Proton Pump Inhibitor

L Laine et al. Gastroenterol 2023; 164: 61-71. Open Access! Vonoprazan Versus Lansoprazole for Healing and Maintenance of Healing of Erosive Esophagitis: A Randomized Trial

Editorial: DA Katzka, PJ Kahrilas. Gastroenterol 2023; 164: 14-15. Open Access! Potassium-Competitive Acid Blocker Suppression of Gastric Acid in Erosive Esophagitis: Is Stronger and Longer Better?

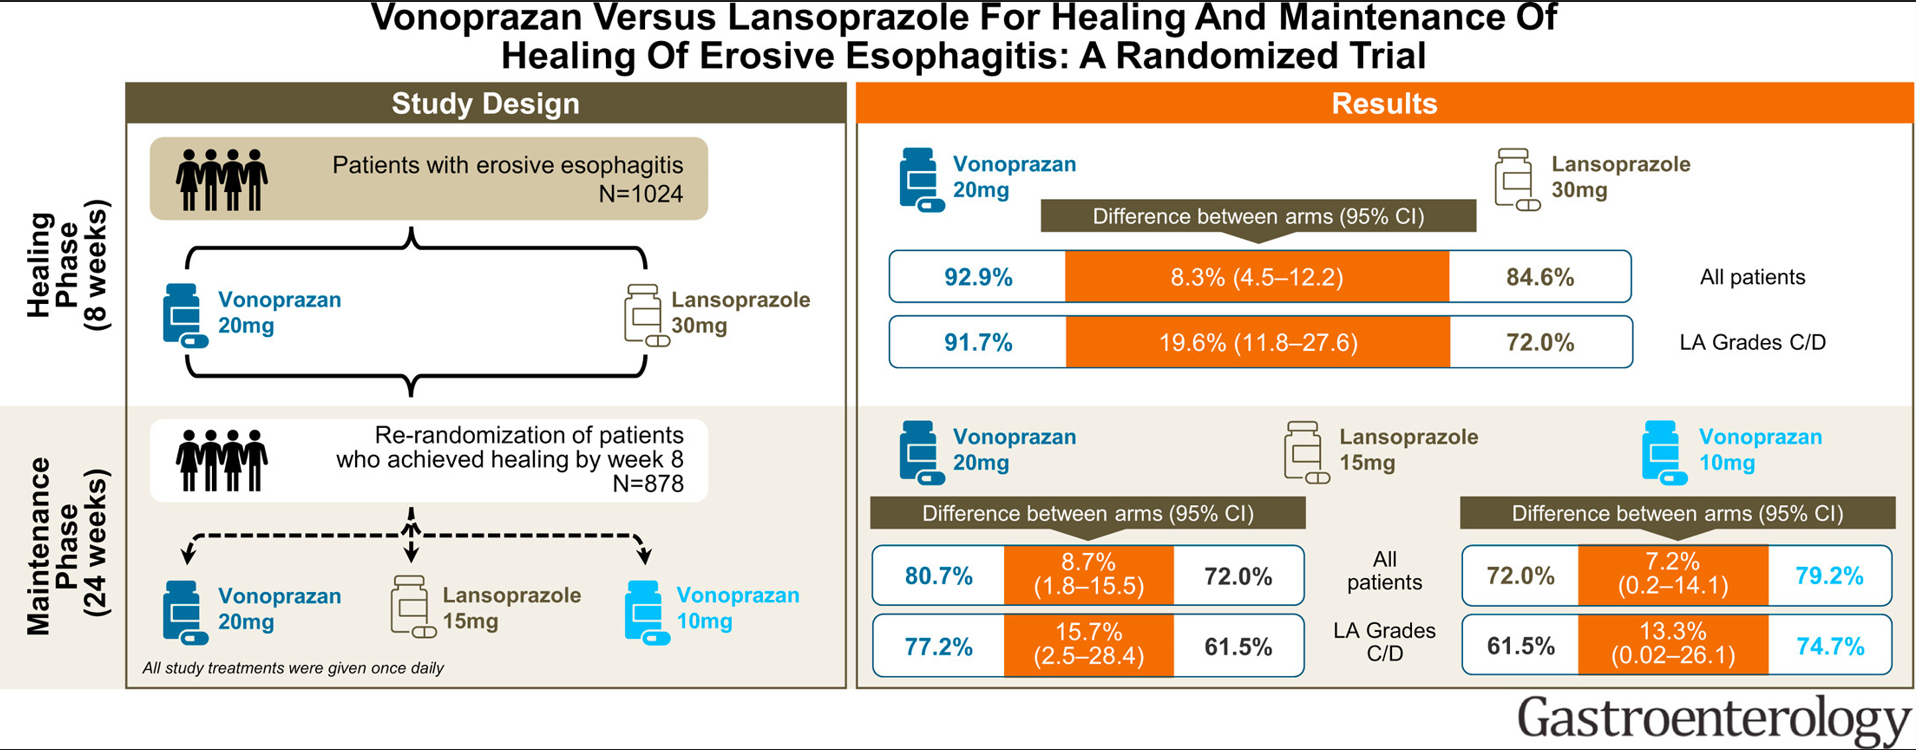
Methods: Adults with erosive esophagitis were randomized to once-daily vonoprazan, 20 mg, or lansoprazole, 30 mg, for up to 8 weeks (healing phase, n=1024). Patients with healing were rerandomized to once-daily vonoprazan, 10 mg, vonoprazan, 20 mg, or lansoprazole, 15 mg, for 24 weeks (maintenance phase, n=878). 

Key findings: (see graphical abstract)

  • In the healing phase, vonoprazan was noninferior to lansoprazole in the primary analysis and superior on the exploratory analysis of healing: 92.9 vs 84.6% (difference, 8.3%). It is noted that studies in Asian populations found smaller differences in healing between these medications.
  • Vonoprazan had superior healing Los Angeles Classification Grade C/D esophagitis at week 2 (difference, 17.6%)
  • Vonoprazan was superior with regard to maintenance of healing Grade C/D esophagitis (20 mg vs lansoprazole (difference, 15.7%) and 10 mg vs lansoprazole (difference, 13.3%).
  • The entire group maintenance healing rates in this trial were lower than in a prior randomized trial in Japan. In the current study at 24 weeks, vonoprazam 20 mg, vonprazan 10 mg and lansoprazole 15 mg had maintenance of healing in 81%, 79%, and 72% respectively compared with 98%, 95%, and 83% in the trial from Japan

The editorial provides a lot of insight into this now FDA-approved therapy for H pylori. Vonoprazan’s application to expand FDA approval is underway: FDA Accepts Review of NDA for Vonoprazan From Phathom Pharmaceuticals (June 3, 2022).

Key points from editorial:

  • Among their shortcomings, PPIs are far from perfect in healing high-grade (Los Angeles class C and D) esophagitis, resulting in the common practice of twice-daily dosing. Furthermore, up to 35% of patients with Los Angeles class C and D esophagitis remain unhealed at 8 weeks, even with twice-daily PPI use.5,6
  • Mechanism of action: Vonoprazan is a potassium-competitive acid blocker (PCAB) . It, reversibly binds to the α-subunit of H+, K+-ATPase to compete with potassium binding. Vonoprazan is acid stable, eliminating the need for enteric coating and allowing for rapid onset of action. Because it achieves high and sustained (half-life is approximately 9 hours) concentrations rapidly in the parietal cell secretory canaliculi, maximal acid inhibition is achieved quickly after a single dose.
  • Because it is not metabolized through the hepatic CYP2C19 or CYP3A4 enzymes, vonoprazan is much less prone to drug–drug interactions.
  • Safety: For the issue of long-term adverse events associated with PPI use…, the proposed mechanisms for these primarily relate to the effects of chronic acid inhibition and/or hypergastrinemia, and there is no reason to think that a PCAB would be any different than a PPI.

My take: There are a lot of individuals with ongoing heartburn & reflux despite PPI treatment. It is likely that vonoprazan will be targeted for patients with more severe erosive esophagitis and refractory symptoms. It is likely that the cost to U.S. patients will be substantially higher than the cost of PPIs.

Related blog posts:

Maternal Mortality in Georgia

Dr. Kathleen Toomey, Commissioner and State Health Officer at Georgia, in an AJC report (Jan 21, 2023):

“We are going to see an increase in maternal mortality during the time of COVID,” Toomey said. “It’s sad but not unexpected.“

Toomey spoke during budget hearings at the state Capitol, saying her agency is pivoting away from an all-hands-on-deck pandemic focus. She said her department would use some of its available bandwidth now to focus on the maternal mortality issue.

For the years 2018-2020, DPH posted pregnancy-related deaths for white women at 22.7 deaths per 100,000 births, and pregnancy-related deaths for Black women at 48.6 deaths per 100,000 births. It did not post overall figures for those years.

In another study (see below) on maternal mortality, it is noted that the mortality rate was 62% higher in states with restrictive abortion policies, likely related to poor availability of health care.

The Commonwealth Fund report (12/4/22): The U.S. Maternal Health Divide: The Limited Maternal Health Services and Worse Outcomes of States Proposing New Abortion Restrictions

My take: Improving maternal mortality should be near the top of the list of priorities and is a good area to try to mitigate health care disparities.

And on a lighter note –Tonight Show Interview with George Santos (Jon Lovitz). Thanks to Steven Liu for sharing this.

Meckel’s Scan: “Who are you going to believe, me, or your lying eyes?”

The title quote is generally attributed to Groucho Marx. YD Neugut, I Novak. J Pediatri 252; 30. Open Access! The Continued Importance of the Meckel Scan (50 Years Ago in The Journal of Pediatrics)

This brief article is a quick review of the continuing importance of the Meckel scan, 50 years after the publication: Jaros R, Schussheim A, Levy LM. Preoperative diagnosis of bleeding Meckel’s diverticulum utilizing 99m technetium pertechnetate scinti-imaging. J Pediatr 1973;82:45-9.

However, I take exception to this one line (hence this post’s title): “Now, premedication with H2 antagonists often is used to enhance tracer uptake into gastric tissue, and a Meckel scan has high sensitivity and specificity, both approaching 100%.3“

On planet Earth, the test’s sensitivity does NOT approach 100%. It would be more accurate to cite several references regarding the test’s sensitivity. For example, Kwak et al, in a retrospective review of 360 children (368 scans), found a sensitivity of only 65% (J Nuclear Med 2013; 54 (supplement 2) 535. Utility of Meckel’s scan: Retrospective review of 368 cases).

My take: A Meckel’s scan is very helpful when it is abnormal due to its high specificity. However, its sensitivity is suboptimal and many children need surgery for a Meckel’s diverticulum even with a negative scan.

Related blog posts:

Legacy bicycle trail in Sarasota, FL.

Combination Therapy for Eosinophilic Esophagitis

MA Buendia et al. JPGN Reports 3(4):p e273, 2022. DOI: 10.1097/PG9.0000000000000273. Relapse of Eosinophilic Esophagitis on Dupilumab

Yesterday’s post reviewed the landmark study leading to dupilumab’s FDA approval. Today’s case report shows that we have a lot we need to learn about its use.

The authors present a case report of a patient with eosinophilic esophagitis (EoE) who had ongoing active EoE while receiving topical steroids (TS) and PPI (and previously dietary elimination therapy). He achieved remission after the addition of dupilumab. “When his TS were weaned after achieving remission, his disease relapsed with worsening of his dysphagia and a peak eosinophilic count (PEC) of 55 eosinophils per high power field (eos/hpf). Upon restarting TS to his ongoing dupilumab, symptoms fully resolved, and he achieved histologic remission (PEC 10 eos/hpf).”

My take: This study indicates that there are some patients need dupilumab and topical steroids in combination, rather than monotherapy. Reliable biomarkers to more easily determine response and/or to predict optimal therapy are clearly needed.

Sunset at Siesta Key, FL

Landmark Dupilumab Study for Eosinophilic Esophagitis

ES Dellon et al. NEJM 2022; 387; 2317-2330. Dupilumab in Adults and Adolescents with Eosinophilic Esophagitis

This study was pivotal for receiving FDA approval of dupilumab (dupixent) for the treatment of EoE (the only FDA approved therapy). Background: “Dupilumab, a fully human monoclonal antibody, blocks interleukin-4 and interleukin-13 signaling, which have key roles in eosinophilic esophagitis..Standard-of-care treatments for eosinophilic esophagitis include food elimination diets, proton-pump inhibitors (PPIs), swallowed topical glucocorticoids (applied to the esophagus by swallowing), and, in the case of strictures, esophageal dilation.11,12 However, the rates of response are variable (30 to 40% of patients may not have a response to first-line treatments).”

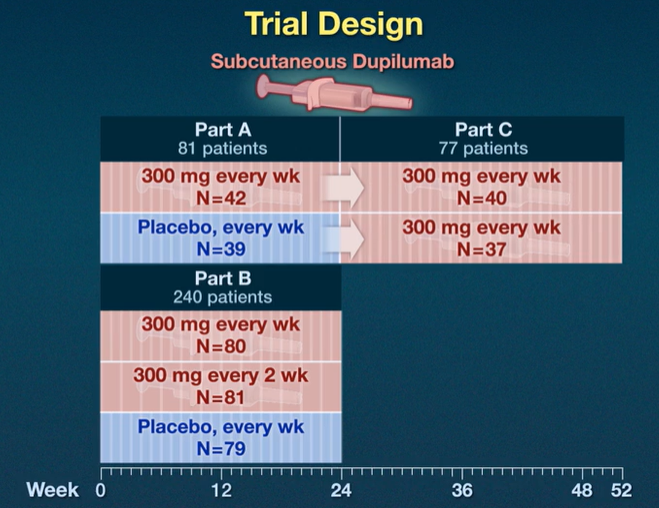
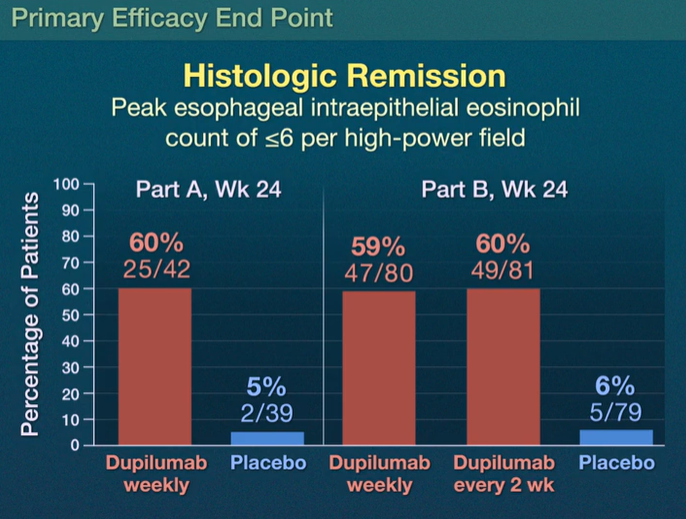
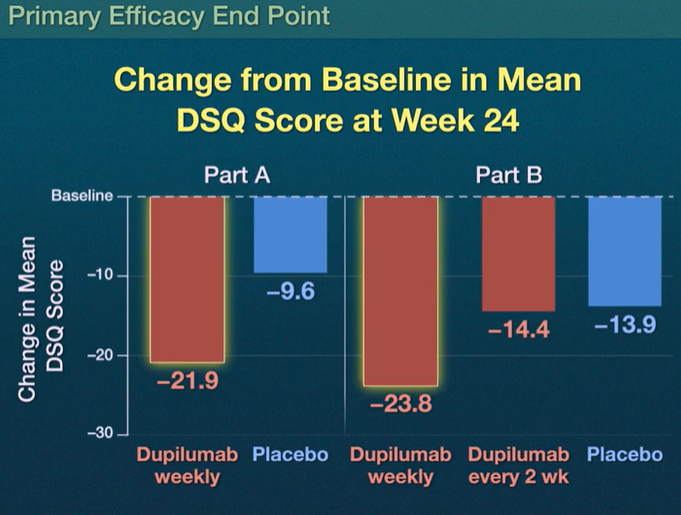
Key findings from three-part study (see images below):

  • Part A: Histologic remission occurred in 25 of 42 patients (60%) who received weekly dupilumab and in 2 of 39 patients (5%) who received placebo
  • Part B: Histologic remission occurred in 47 of 80 patients (59%) with weekly dupilumab, in 49 of 81 patients (60%) with dupilumab every 2 weeks, and in 5 of 79 patients (6%) with placebo 
  • Dysphagia Symptom Questionnaire (DSQ) scores:  the scores improved with weekly dupilumab as compared with placebo, with differences of –12.32 (95% CI, –19.11 to –5.54) in Part A and –9.92 (95% CI, –14.81 to –5.02) in Part B (both P<0.001) but not with dupilumab every 2 weeks (difference in Part B, –0.51; 95% CI, –5.42 to 4.41)
  • The most common adverse effect was injection site reactions. There were 10 serious adverse events; none of these “were considered by the trial investigators to be related to the trial regimen.”

In the associated commentary, (pg 2379-2380), Dr. Alex Straumann notes that since EoE is localized to the esophagus, whether a patients should be treated with a systemically acting medication, “particularly in light of the fact that topical glucocorticoids have been shown to be as efficacious as systemically acting prednisone.”

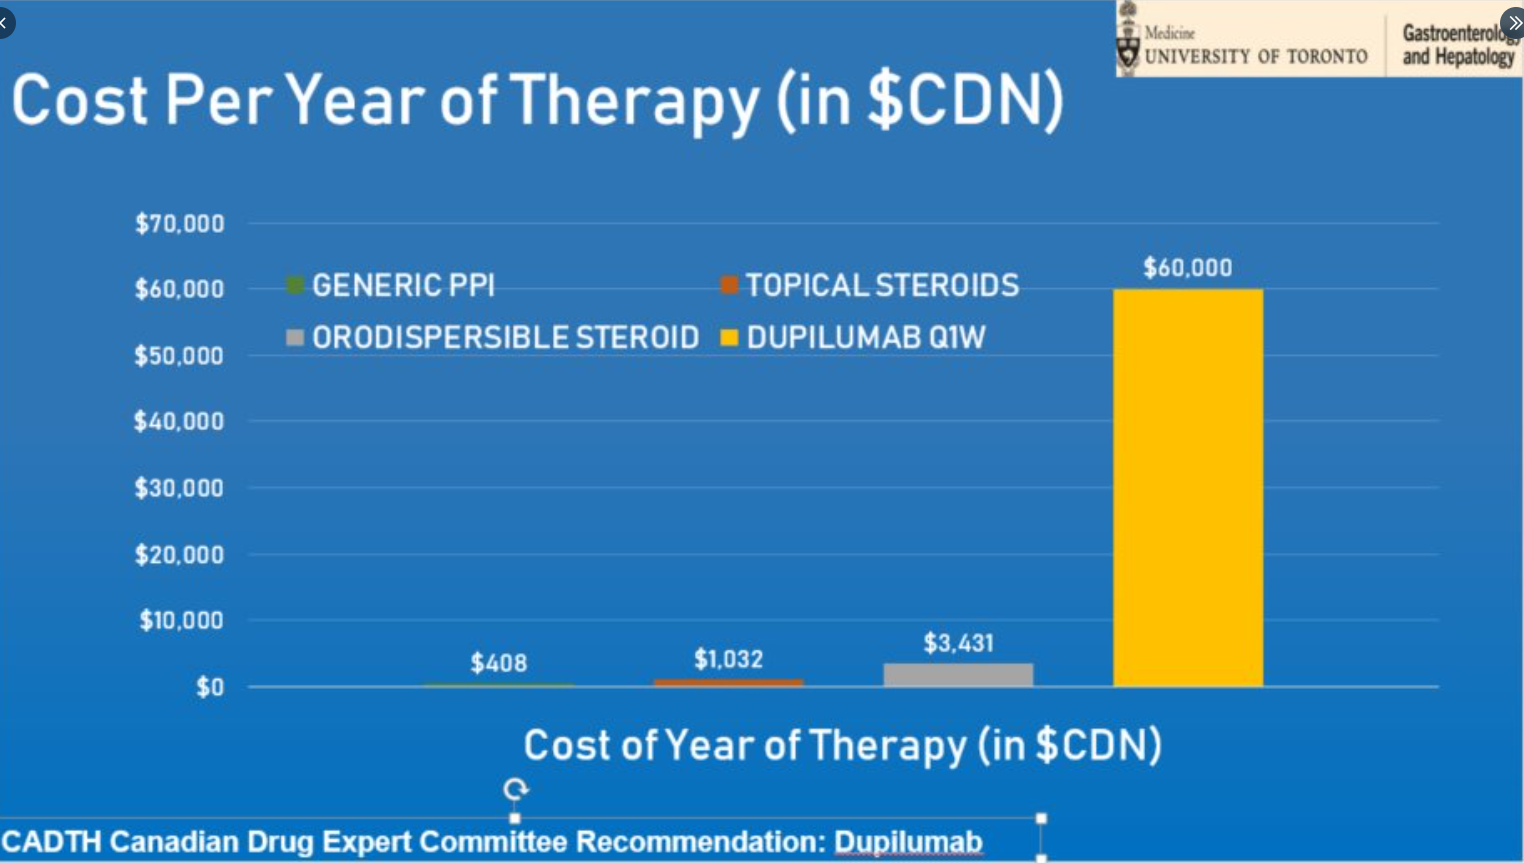
My take (borrowed in part from editorial): It remains unclear whether dupilumab “is better than the good old topical glucocorticoids in improving disease outcomes, particularly in light of considerable costs associated with this treatment.” Due to its cost (see below), dupillumab is likely best situated as a 2nd line treatment at this time for most patients.

Related blog posts:

Cost comparison (from Laura Targownwik on twitter):

ChatGPT Passes the Bar, an MBA exam, and Earns Medical License?

Related blog post: Have you tried out ChatGPT?

Besides cheating on essays for school, it is amazing what ChatGPT can do.

  1. It can pass the USMLE. MedPage Today: AI Passes U.S. Medical Licensing Exam
  2. It can pass the bar exam. ABA Journal: AI program earned passing bar exam scores on evidence and torts; can it work in court?
  3. It can pass an MBA exam, Fortune: ChatGPT passed a Wharton MBA exam and it’s still in its infancy. One professor is sounding the alarm
  4. It can write scientific abstracts: Nature: Abstracts written by ChatGPT fool scientists. Researchers cannot always differentiate between AI-generated and original abstracts

Other uses:

  • Food recipes -type ingredients you have at home, and ask it for a recipe
  • Explain complicated topics at age-appropriate levels
  • Travel itinerary (can specify if active vacation, with kids, specific goals)
  • Recommendation letters
  • Resumes
  • Lesson plans
  • Solve complex math problems in step-by-step fashion
  • Provide scientific/journal references
  • Write music in almost any genre
  • Write essays and develop ideas for novels
  • Provide personal advice
  • Create content in multiple languages
  • Medication appeal letters
  • Write or fix computer coding/software
  • Develop questions for speaker question and answers
  • Prep for interview

My take: Only George Santos can claim more accomplishments than ChatGPT (AI). It is important to verify the information that ChatGPT provides –it is sometimes wrong.