Cheap Technology for Button Battery Ingestions

Typical Button Battery

Typical Button Battery

An NPR report regarding “the results of .. experiments published Monday in the Proceedings of the National Academy of Sciences show that a prototype shield is effective at keeping small, 11 millimeter batteries from damaging the esophagus after being swallowed.”  This would be worthy endeavor to pursue.  The larger buttons (20 millimeters in diameter) “are particularly dangerous. One out of 8 children [under 6 years old] who swallow this larger battery are going to have a serious debilitating complication.”  Here’s the link: Battery Shield

Here’s an excerpt regarding the shield:

Microscopic metal particles are embedded in the shield, which is a millimeter thick. When a battery is inserted into a device, the pressure from the device’s cover or a spring that holds the battery in place pushes the metal particles together. The shield then acts like a switch, conducting electricity.

When the battery is free, floating down a child’s esophagus, for instance, there’s not enough pressure to make the microparticles smush together. The shield then acts as an insulator…

The shield’s material is commercially available and currently used in touch-screen devices where a gentle press of a fingertip can complete a circuit.

Related blog posts:


"Great Power" for Damaging an Esophagus

“Great Power” for Damaging an Esophagus

NASPGHAN Notes –Last Word for this Year

This blog entry has abbreviated/summarized several presentations. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.

IBD Treatment: Targets for the Modern Age –Eric Benchimol (Children’s Hospital of Eastern Ontario)

Goal: Review mucosal healing and best targets to measure to predict prognosis

Treat-to-target:

  • Regular assessment of disease activity using objective outcome measures.
  • Adjust treatment if not accomplishing goal.
  • Proven helpful in rheumatoid arthritis, hypertension, diabetes, and hypercholesterolemia.

Old targets:

  • “Clinical remission”
  • “Feeling better”
  • Indices: PCDAI, CDAI, Harvey-Bradshaw
  • Problem: Active disease is not well-predicted by symptoms or laboratory markers
  • 2nd Problem: Active symptoms not always due to active IBD (could be due to functional complaints)
  • PUCAI score in ulcerative colitis does reflect ulcerative colitis severity fairly well

New Targets

  • High correlation with outcomes
  • Cost-effective
  • Available

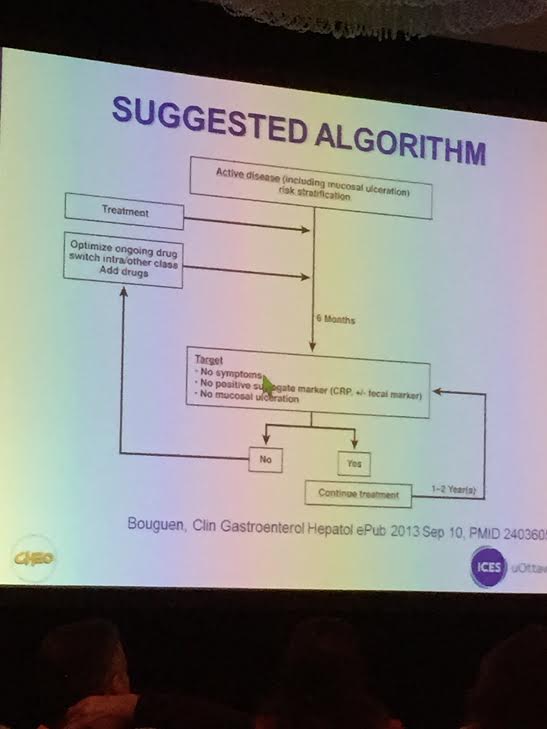
Is mucosal healing achievable?   If you were scoped and adjustments made in therapy, then much higher rate (HR >4) of remission. Bougen, Clin Gastroenterol Hepatol 12: 978.  Endoscopy may be best way to assess mucosal healing.  Since it is invasive, efforts have been made to identify surrogate markers.

Treat-to-Target Algorithm

Treat-to-Target Algorithm

Surrogate Markers

  • Ultrasound –can be useful but operator-dependent
  • MRE had 83% accuracy for endoscopic remission: Gastroenterol 2014; 146: 374.
  • Calprotectin not as accurate in children? Am J Gastroenterol 2014; 109: 637. Sensitivity high 97%, specificity for remission 68%
  • CRP –if elevated, higher risk of complications or surgery. However, sensitivity is much lower for disease activity than calprotectin/imaging studies for active disease
  • Drug levels. Therapeutic IFX trough levels (and adalimumab) are highly predictive of mucosal healing.

Bottomline (my interpretation): Resolution of clinical symptoms and improvement in bloodwork is not good enough.  When/timing to assess with sensitive surrogate markers is still uncertain.  In many patients, endoscopy is needed to assure adequate improvement; however, in others, a followup imaging study (eg. MRE) or sensitive stool assays may be the best approach.

A related story (from AGA’s Today in Medicine email feed & pointed out to me by Ben Gold) indicates that estimation of clinical symptoms is not accurate:

Survey Suggests Severity Of IBD Is Underestimated By Gastroenterologists.

MedPage Today (10/31, Walsh, 186K) reports that survey results presented at a medical conference indicate that “the severity of inflammatory bowel disease is significantly underestimated by gastroenterologists.” Researchers found that “a total of 55% and 67% of physicians who participated in a web-based survey rated cases of Crohn’s disease and ulcerative colitis as being mild when they were actually moderate.” Meanwhile, “for case studies that represented severe disease, 76% and 81% of the physicians gave ratings of either moderate or mild for Crohn’s disease and ulcerative colitis, respectively.”


Related blog posts:

Risk Stratification in Pediatric IBD: Are we there yet? Jeffrey Hyams (Connecticut Children’s

Initially, Dr. Hyams described the exploding head syndrome; many attendees might have thought they had this due to information/”big data” overload, but this syndrome is a sleep disorder/parasomnia event.  Here’s a link to the image from his talk.  Then, Dr. Hyams reviewed data on risk stratification:

  • Mutations: Some genetic mutations are associated with disease severity
  • Still needed: specific pediatric data
  • Microbiome: Some profiles associated as prognostic factors in pediatric RISK study
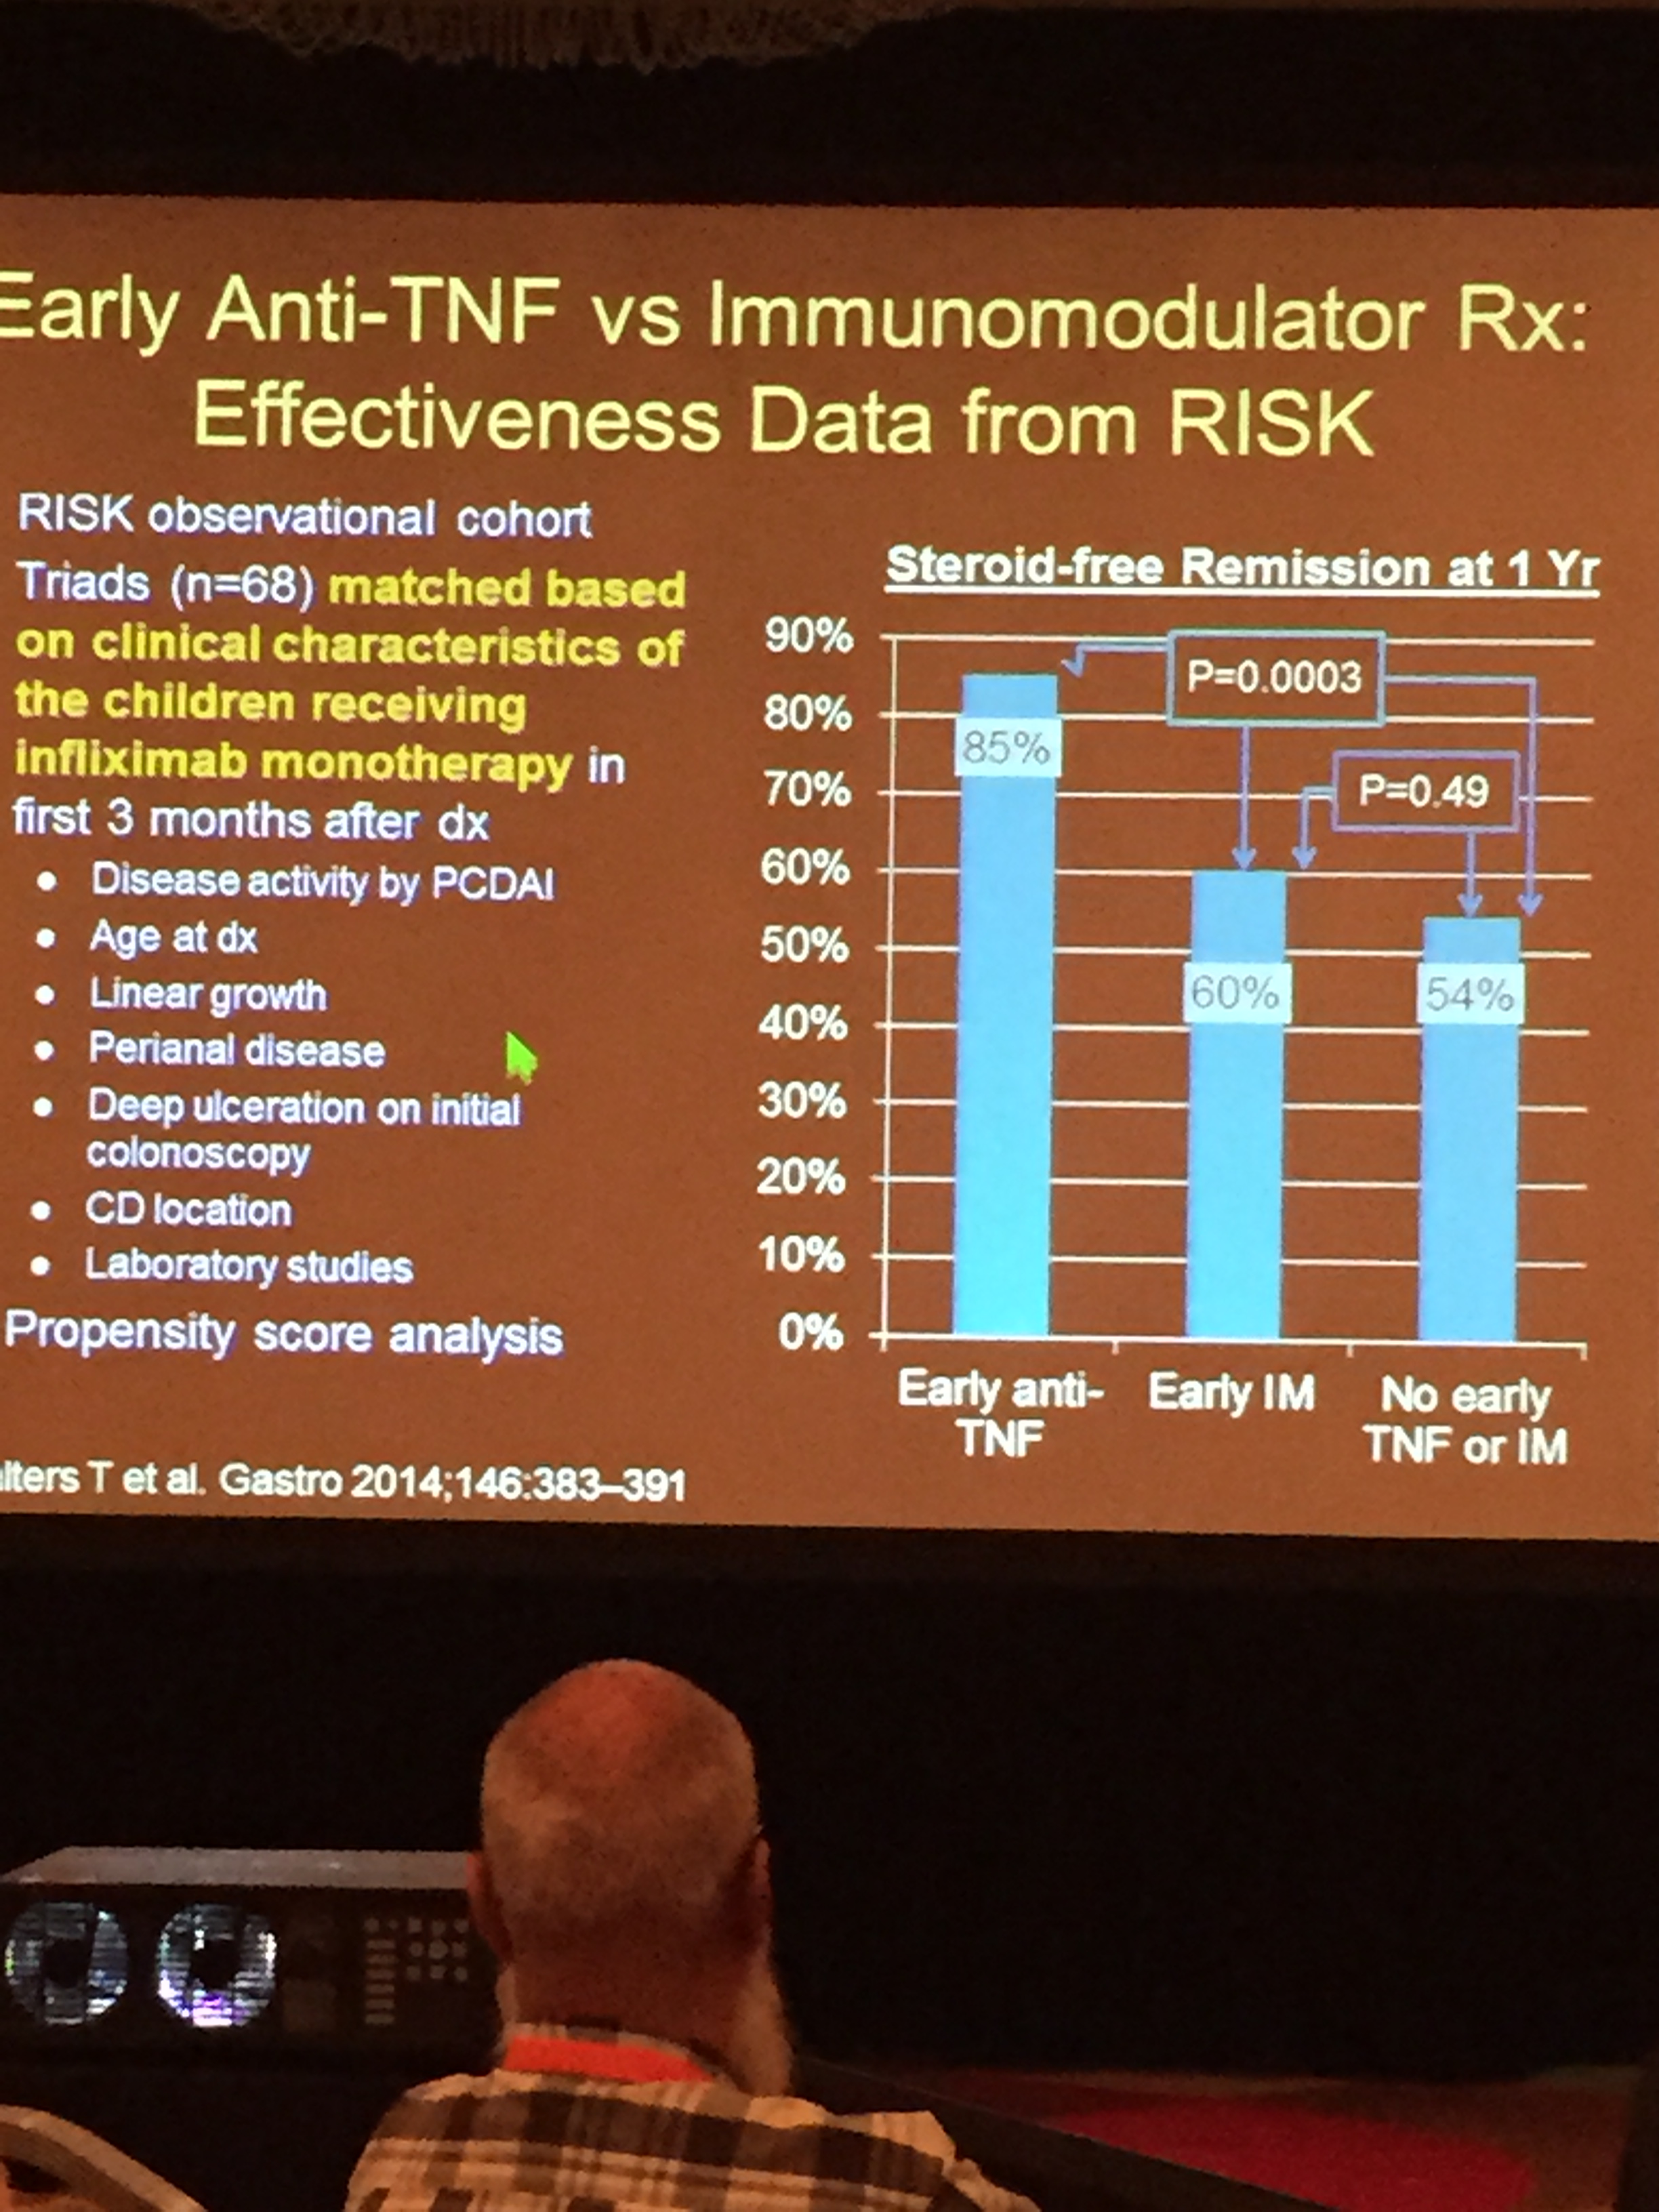
  • Early anti-TNF associated with improved outcomes (using propensity analysis) Gastroenterol 2014; 146: 383.

Bottomline: Not there yet with risk stratification. Many factors environmental, genetic susceptibility, immune response, and treatment need to be sorted out with “big data.”

Key Clinical Questions for your practice at this time:

  • Does this patient have known risk factors for doing poorly?
  • Am I using current therapies properly?
  • What is the risk of undertreated disease? This needs to be considered with discussion of safety of IBD meds.

Cross Examination of Cross-Sectional Imaging in IBD –Sudha Anupindi (Radiology/CHOP)

  • For the most part, barium studies discouraged (eg. UGI/SBFT) by speaker; radiation ~1 mSv.
  • CT (conventional) widely available and easy –if needed urgently/middle of night.

Initial presentation: imaging of choice

  • MR enterography –no radiation, better contrast resolution, best for perianal disease, able to evaluated peristalsis. Two limitations: cost, interpretation
  • CT enterography –fewer motion artifacts (0.6 seconds), lower cost, increased availability, better spatial resolution radiation reduced with current technology at most Children’s hospitals: 1-2 mSv

Abdominal ultrasound holds promise as alternative imaging with lower cost.


More NASPGHAN Meeting Notes: IBD Hot Topics

“The best preparation for tomorrow is to do today’s work superbly well”  –William Osler (quote cited in NEJM 2014; 371: 1565-66).

This blog entry has abbreviated/summarized the presentations. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.

For me, these lectures were a useful review and represent an effort to achieve Osler’s objective of doing superb work.  If I had to choose a single issue that may affect my practice: when initiating infliximab, consider checking week 14 trough levels of infliximab and optimize dosing.

The role of the microbiome in IBD   –Subra Kugathasan (Emory)

This was a terrific lecture though with some overlap with a number of other presentations at the meeting. The lecture reviewed how to interpret microbiome studies and what we are learning from these studies with regard to inflammatory bowel disease.

Enteral Nutrition and Microbiota –conclusion:

  • EN may work by suppressing the entire microbiota in Crohn’s disease thus lowering antigenic effect to the gut
  • Some microbes may be pro-inflammatory and others pro-fibrotic
  • Chicken and egg: preliminary evidence suggests that dysbiosis is probably a preceding predisposing factor rather than due to the consequence of having inflammatory bowel disease.

The Role of Drug Monitoring in Inflammatory Bowel Disease –Jennifer Strople (Children’s Hospital of Chicago)

TPMT Testing/thiopurine metabolite monitoring

  • goal: minimize adverse effects and optimize thiopurine dosing.
  • those with lower (but not absent) activity may be best candidates for treatment with azathioprine/6-mercaptopurine (thiopurines).
  • normal TPMT testing does NOT exclude complications like bone marrow suppression or pancreatitis.
  • obtaining TPMT at baseline is cost-effective
  • goal of 6-thioguanine level of >235 (odds ratio favorable of responding to/remission with treatment)
  • drug levels: allows monitoring for noncompliance; limitation of costs and using levels inappropriately. Routine testing “has no role in patients who are doing well on acceptable doses of thiopurines”
  • younger patients often need higher doses

Monitoring for anti-TNF Therapy

  • Loss of response most common in first year of therapy.
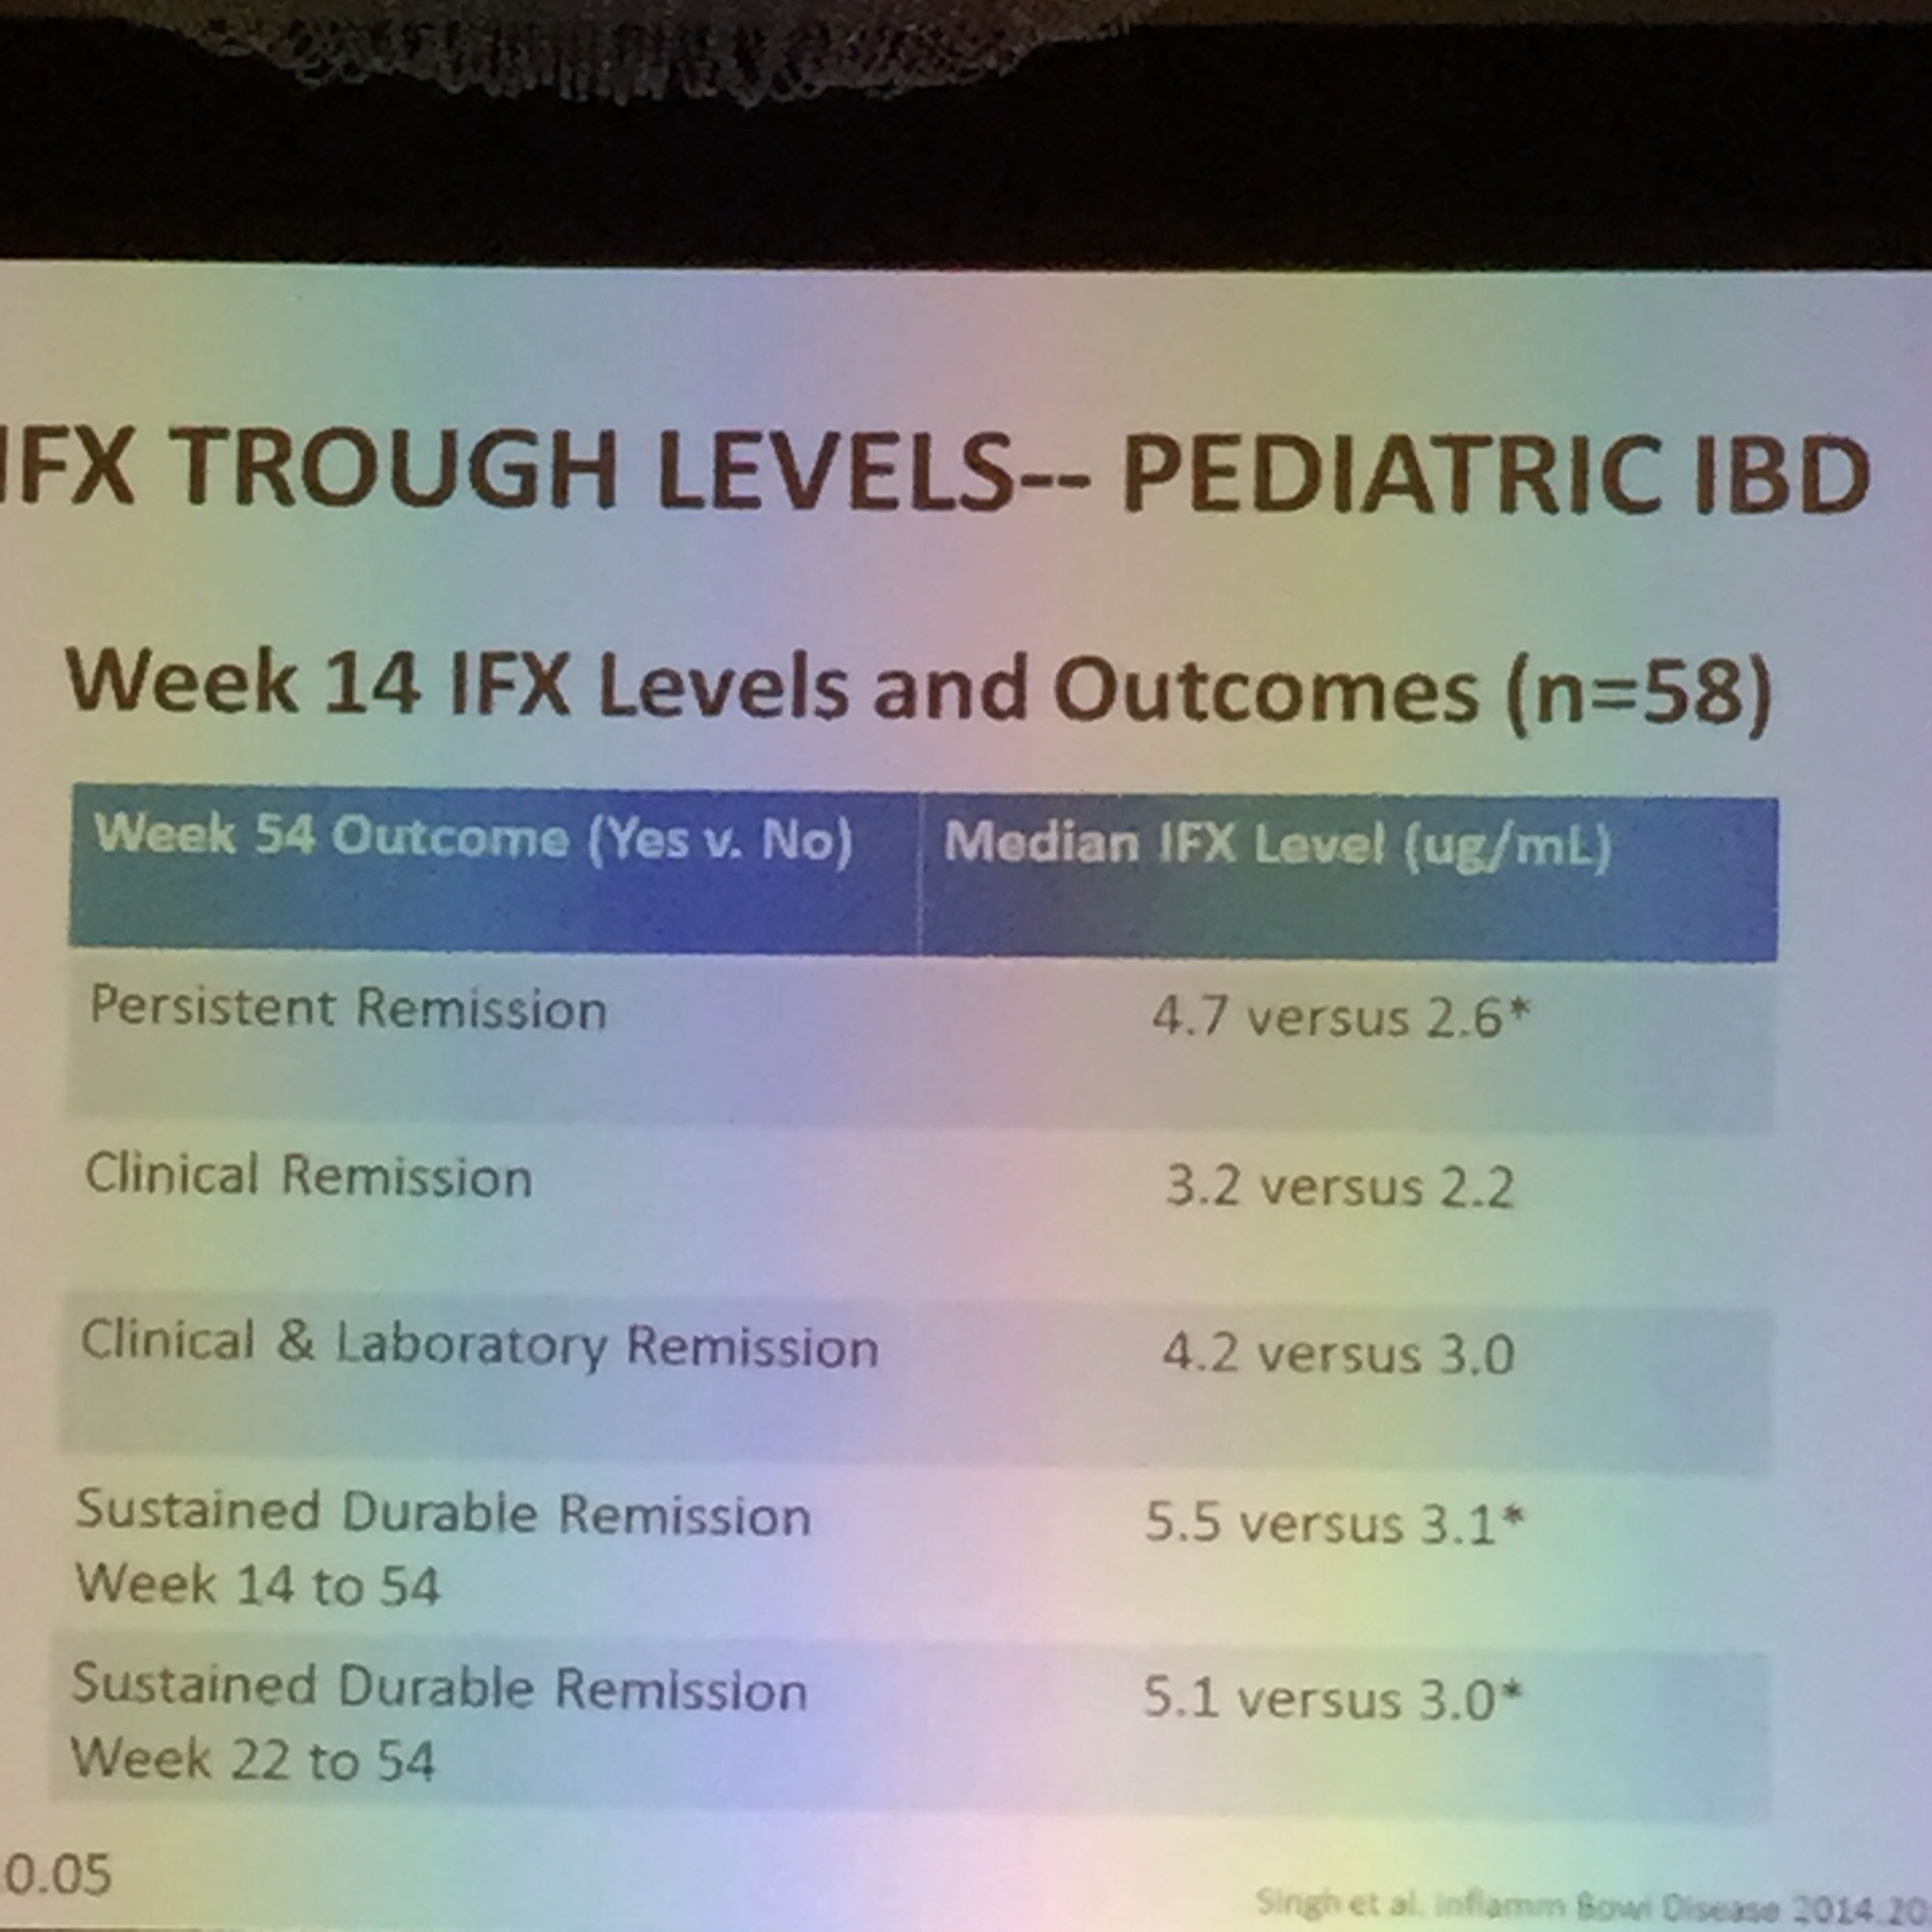
  • For infliximab (IFX), IFX trough levels >3 mcg/mL predicted sustained response. Gut 2014; 63: 1721.
  • Week 14 IFX levels predict outcomes:
IFX Levels at 14 weeks

IFX Levels at 14 weeks

  • Preliminary data with ulcerative colitis shows that troughs >3.7 mcg/mL increases likelihood of mucosal healing and remission.
  • Undetectable trough levels of IFX associated with increased risk of colectomy with ulcerative colitis Gut 2010 59: 49
  • If a patient develops high levels of anti-drug antibodies (ADAs), this makes likelihood of response to medications unlikely. The specific ADA level is helpful; high levels of drug antibody are particularly problematic. If low levels of drug without ADAs, then increasing dose is typically effective.
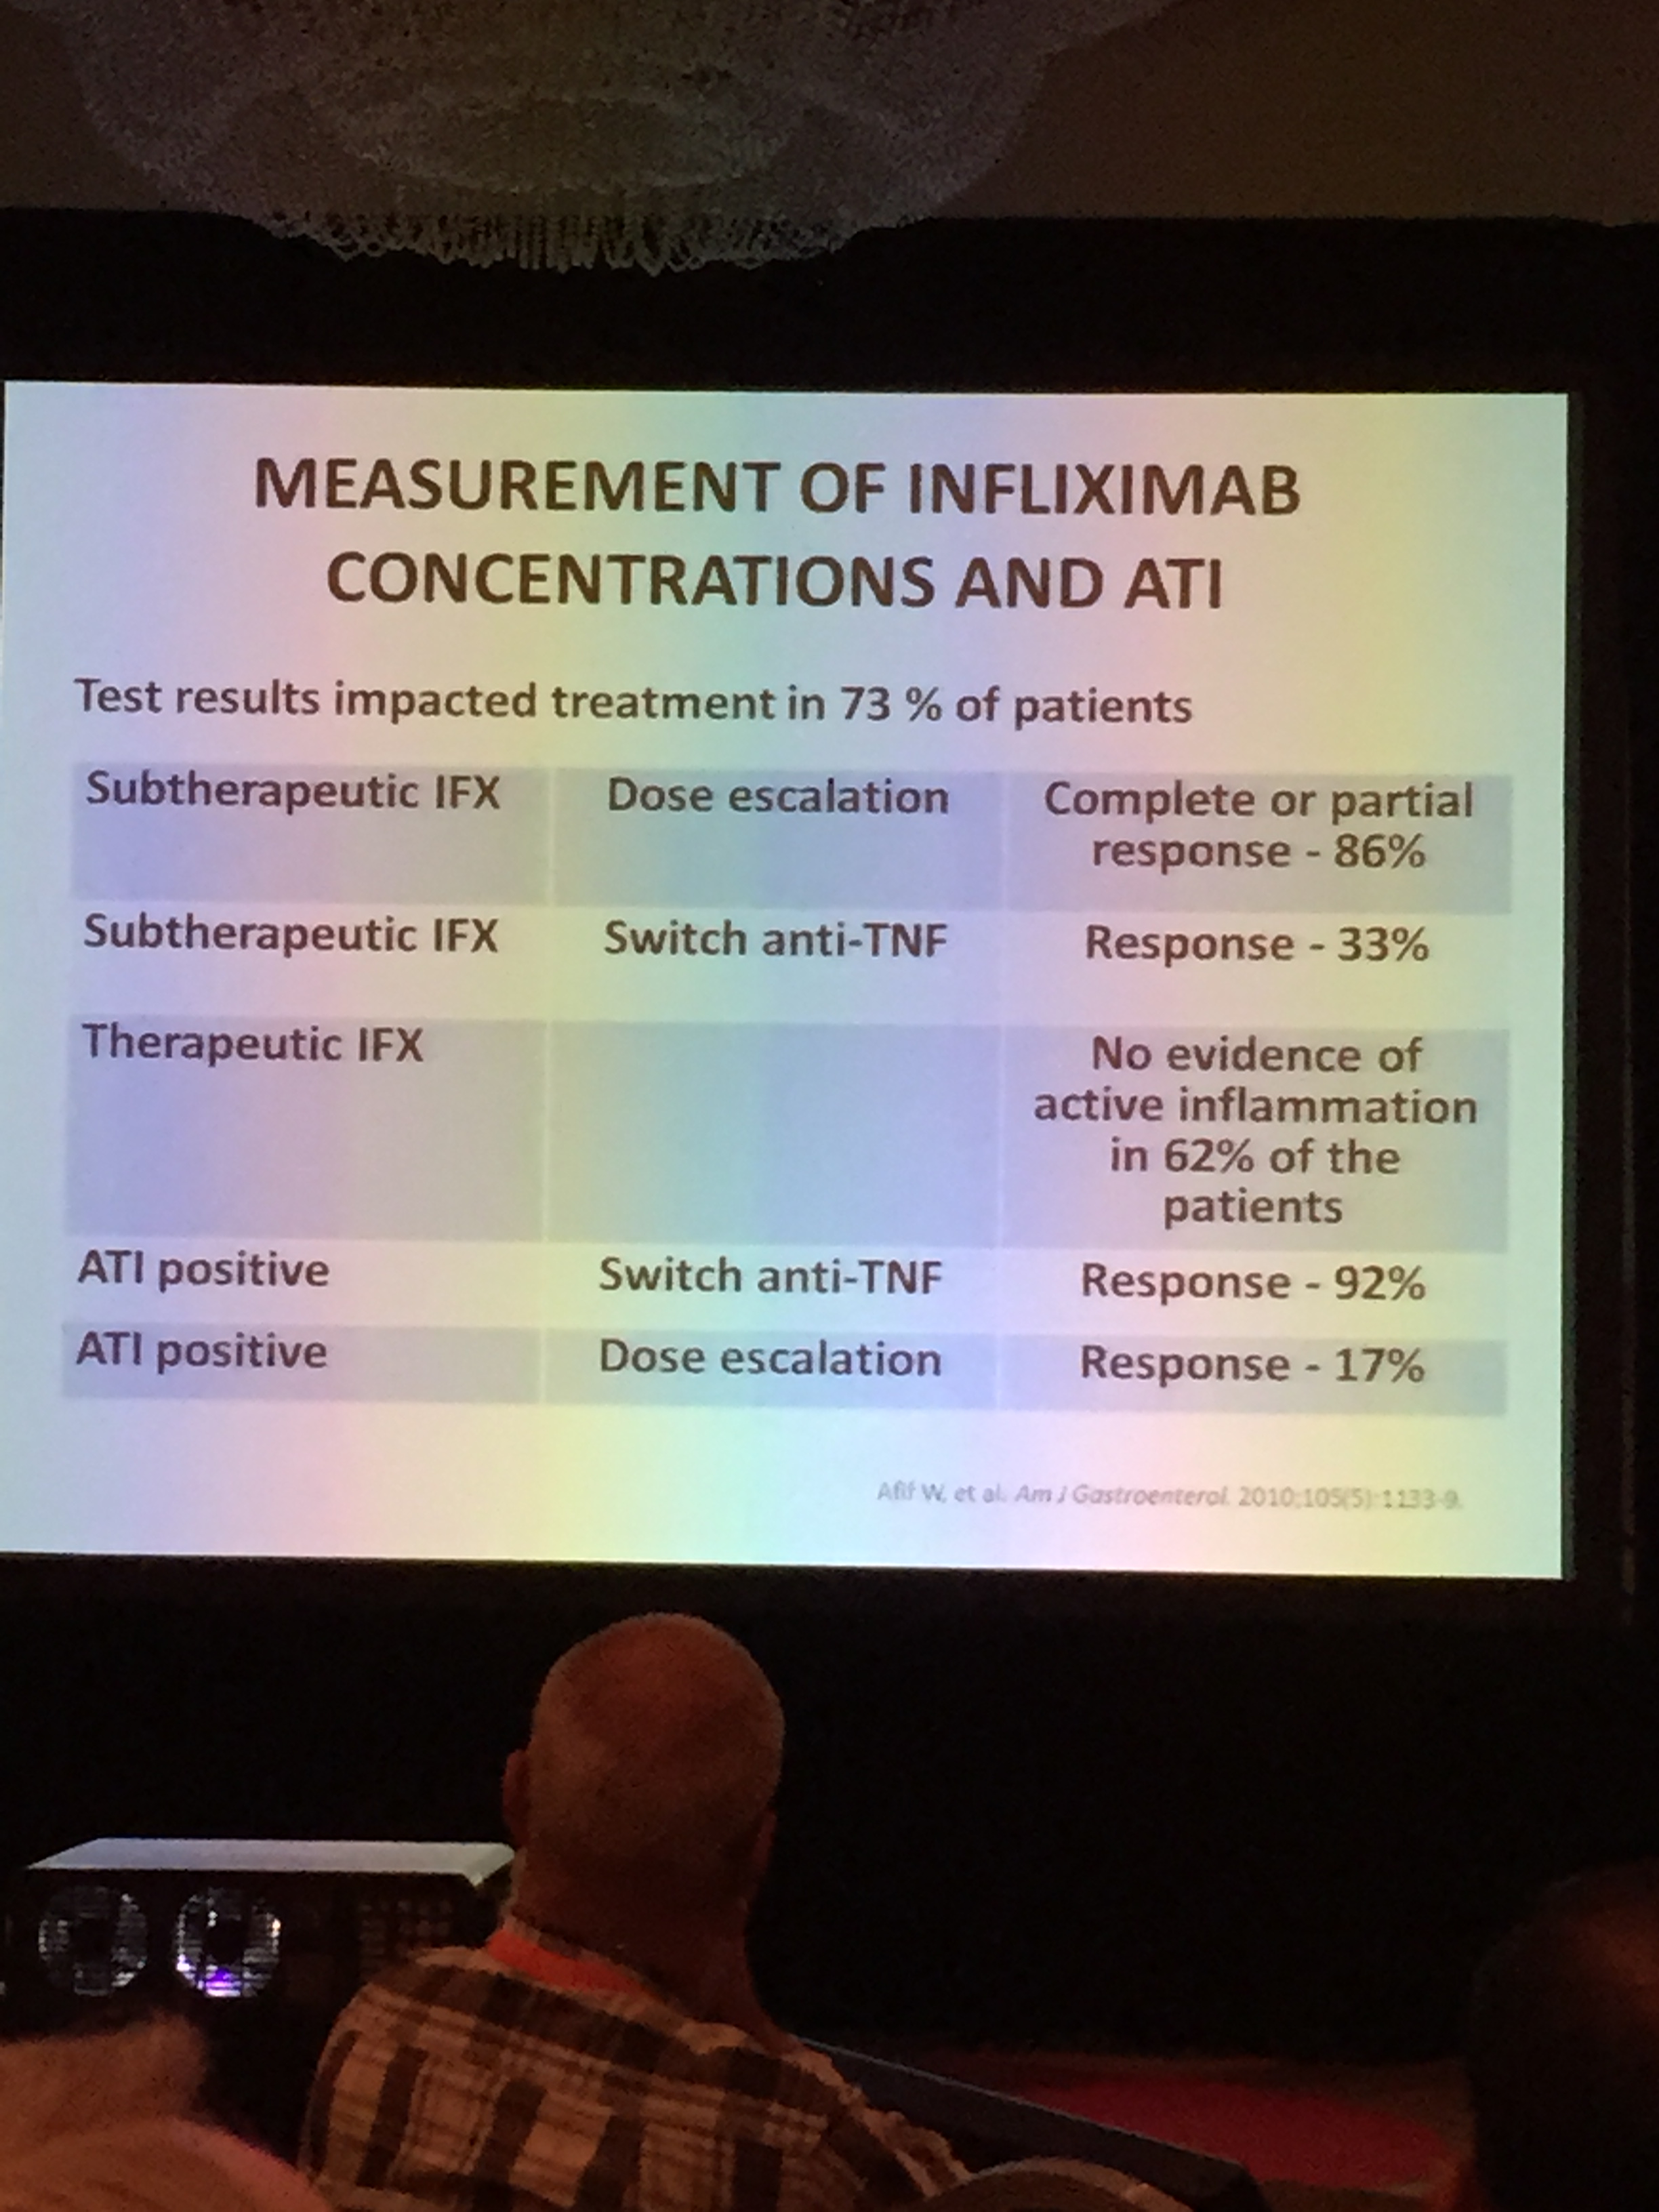
IFX Algorithm

IFX Algorithm

  •  If losing response to therapy and if active disease is present, then check drug concentration. If subtherapeutic with no ADAs or low ADAs, dose escalation with or without immunomodulator is indicated.
  • If subtherapeutic with high ADA, then change drug
  • If therapeutic level, then may need to change to different anti-TNF or drug class.

Related posts on this topic:

Debate: Immunomodulators versus Biologic agents 

  • James Markowitz –consider starting with immunomodulators
  • Maria Oliva-Hemker –consider starting with biologics

In the face of the “Biologic Tsunami,” Dr. Markowitz suggested –“Don’t throw the baby out with the bathwater”

  • Reviewed infliximab data, and adalimumab data. 1-year remission rates 50-60%.
  • Durability of infliximab may be influence by immunomodulators (IMs): patients who had IM prior to IFX had better durability of response:  45% durability in those who had no IM prior to biologic, 53% durability in those who had IM for ❤ months, 66% durability in those who had IM for >6 months prior to IFX.
  • Adult data showing lack of efficacy with IMs influenced by different characteristics compared with children (eg. different disease location, ~40-50% of adults were smokers)
  • Reviewed toxicity of IMs and biologics
  • Children with severe disease do best with “early infliximab.”
  • IMs with 40-60% efficacy over 18 months and then relatively stable.
  • In Dr. Markowitz’ practice, IM use: girls receive thiopurines and boys receive methotrexate

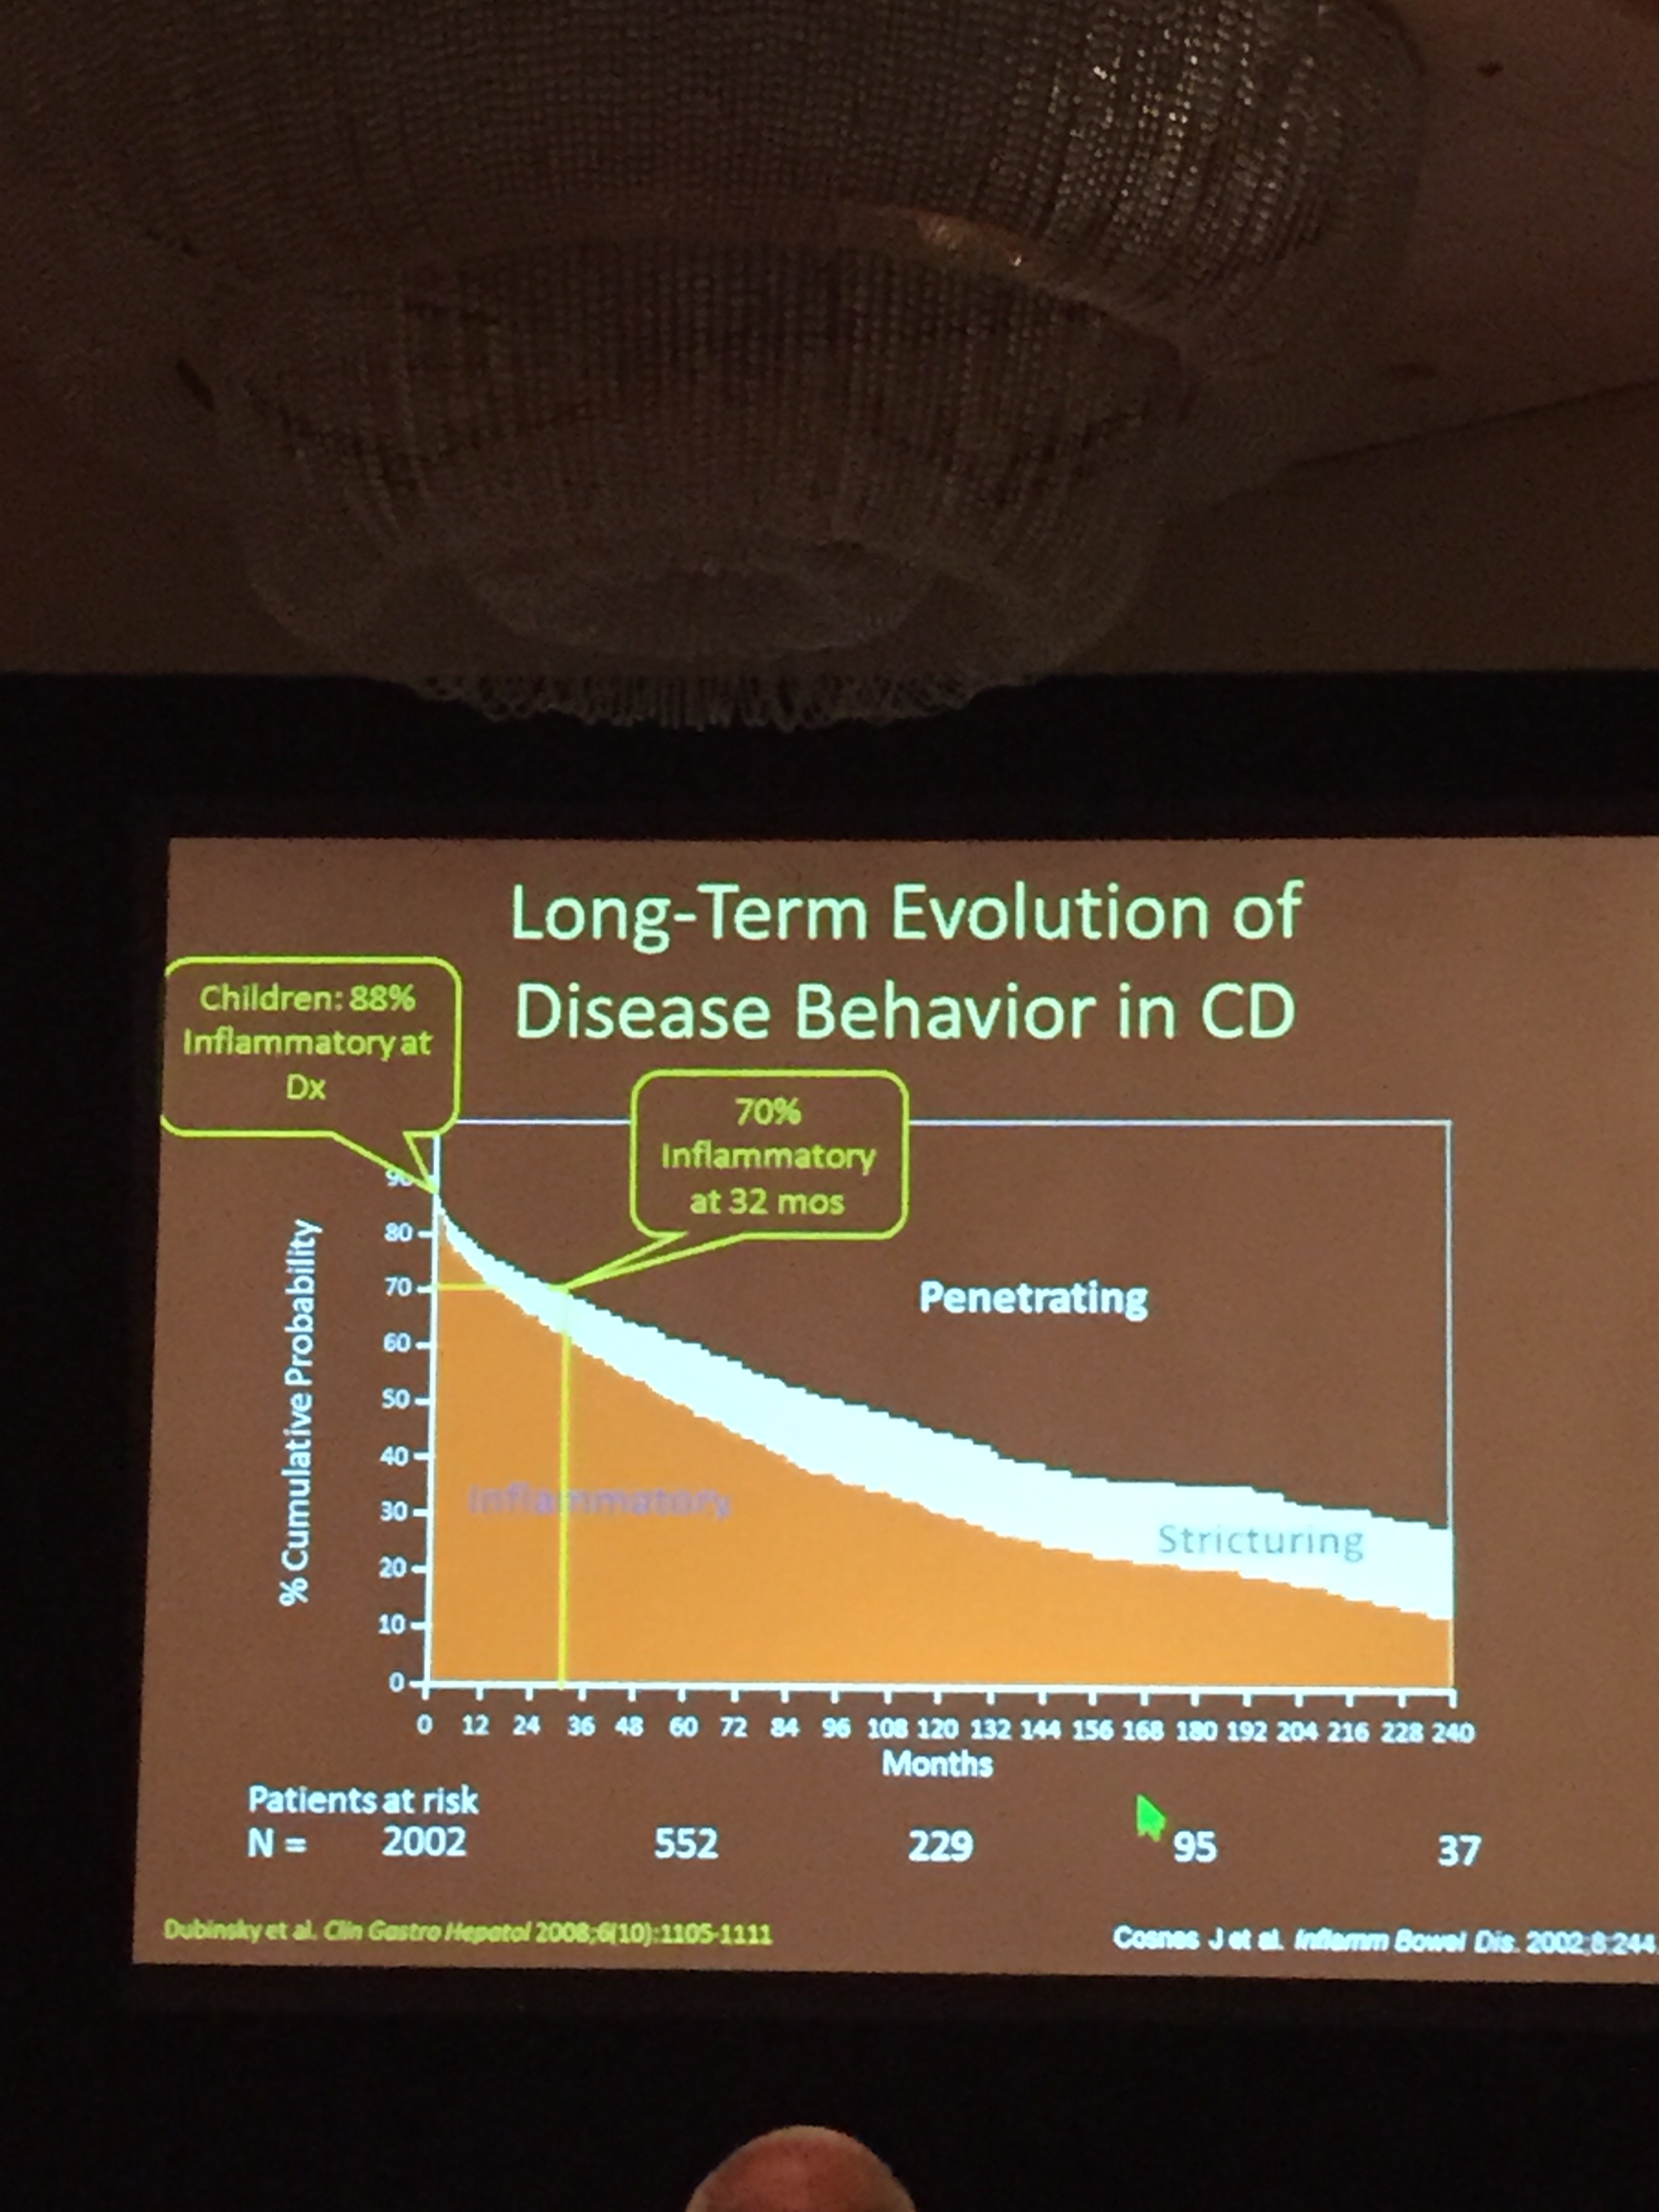
Biologics –important to start before disease phenotype changed to stricturing/penetrating disease. (See images below)

Related posts:

Early anti-TNF -RISK Cohort

Early anti-TNF -RISK Cohort


Long Term Risk of Stricturing (Cosnes et al)

Long Term Risk of Stricturing (Cosnes et al)

“The future of gastrointestinal disease and symptom monitoring: biosensor, E-portal, and social media”

At this year’s NASPGHAN meeting, the keynote lecture was given by Brennan Spiegel.  (Brennan Spiegel, MD (@BrennanSpiegel) | Twitter) This was a great talk!

This blog entry has abbreviated/summarized the presentation. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.

Challenges in healthcare:

  • Time with patient is limited/poorly-timed in comparison to health care needs.
  • Care is reactive rather than proactive.
  • Care is expensive.

We spend all our time within walls of our clinic/hospital, but patients spend 99% time outside


How do we tailor care to the individual and make it more cost-effective? How do we get there?  Potential/Emerging Tools:

    • Patient provider portals (including mobile)
    • Social media
    • Wireless biosensors


Key question for patients: What is the most important goal for you/your family today?

How to improve communication with family? Electronic medical records often designed for billing rather than educating

MyGiHealth website/soon-to-be-app.  Here’s a link to YouTube video introduction.

  • HISTORY: Trained computer to interview patient re: abdominal pain –where, timing, risk factors for H pylori, etc.
  • Symptoms and severity: constipation, abdominal pain, gas/bloating, heartburn, diarrhea, dysphagia, incontinence, nausea/vomiting (Promise scales –percentiles).
  • Computer history looked better than history by physician (example below with fictional patient). If history obtained prior to physician coming into room, this would allow physician more time to communicate with patient rather than documenting (Related post: Aptly titled “The Cost of Technology” | gutsandgrowth)
  • Man vs Machine (Spiegel in press Am J Gastro 2014). History performed well with regard to billing complexity and completeness.
  • THIS IS COOL!
  • Physician still needed to analyze information and make diagnosis/treatment plan.
  • Also website/app with EDUCATION applicable to patient.
History by computer outperformed physicians

History by computer outperformed physicians

Obtaining information outside the confines of the office can help overcome Hawthorne effect. (Related blog post: Checklists -Helpful? Overhyped? Hawthorne Effect …). Passive vs Active monitoring.

Twitter: “What you say on twitter may be seen by everyone all over the word instantly”

  • Tool for epidemiologic data.
  • Marketing/advertising
  • Recruiting for clinical studies
  • Measure consumer sentiment
  • Educate patients/providers
  • Forge patient affinity groups
  • Monitor patients for clinical practice
  • Help to manage and direct care

Mayo clinic is studying the impact of social media.

Example of patients initiating research. “Spontaneous Coronary Artery Dissection: A Disease-Specific Social Networking Community-Initiated Study” Lead author: Marysia Tweet

Biosensors:

  • “91% of people keep their phone within 3 feet of themselves 24 hours a day.”
  • Can be used to track intake of food, air quality, movements etc
  • Current sensors: Fit bit, amigo (?sp), shine (?sp), Zeo (for sleep) others.
  • Fitbit: Calories, distance, active time, sleep time
  • More advanced sensors for athletes. Stride dynamics can predict marathon winner at mile 16!
  • Wireless sleep (eg. Zeo) monitor equivalent to formal sleep study
  • Q Sensor –can measure stress: physical ,cognitive, emotional (watching horror movie)
  • Hapi fork –can tell if you are eating too fast (correlated with BMI)
  • Proteus –monitors intake
  • Propeller –monitors MDI use for asthma (FDA approved)
  • AbStats Digestion Sensor –adheres to abdomen and can provide neurogastroenterology data. Green light –will tolerate feeds, Yellow light –will tolerate clears

75,000 health apps available at this time.

Recommended Reading by Dr. Spiegel: The Creative Destruction of Medicine by Eric Topol.  The Creative Destruction of Medicine: How the Digital …


Parenteral Lipids & Cholestasis –a Little More Data

A recent publication in JPGN indicates that resuming low dose soy-based parenteral lipid can be effective in patients (n=7) whose cholestasis had resolved on a fish oil-based parenteral lipid. It does not resolve the larger question of whether fish oil-based parenteral lipids are truly more effective than soy-based parenteral lipids (see previous blog links below).

Here’s the abstract:

Objectives: Intestinal failure associated liver disease (IFALD) contributes to significant morbidity in pediatric intestinal failure (IF) patients. However, the use of parenteral nutrition (PN) with a fish oil-based IV emulsion (FO) has been associated with biochemical reversal of cholestasis and improved outcomes. Unfortunately, FO increases the complexity of care: as it can only be administered under FDA compassionate use protocols requiring special monitoring, is not available as a 3-in-1 solution and is more expensive than comparable soy-based lipid formulation (SO). Due to these pragmatic constraints a series of patient families were switched to low-dose (1 g/kg/day) SO following biochemical resolution of cholestasis. This study examines if reversal of cholestasis and somatic growth are maintained following this transition.

Methods: Chart review of all children with IFALD who switched from FO to SO following resolution of cholestasis. Variables are presented as medians (interquartile ranges). Comparisons performed using Wilcoxon signed-rank test.

Results: 7 patients aged 25.9 (16.2,43.2) months were transitioned to SO following reversal of cholestasis using FO. At a median follow up 13.9 (4.3,50.1) months there were no significant differences between pre- and post-transition serum alanine and aspartate aminotransferases, direct bilirubin, and weight-for-age z-scores. Due to recurrence of cholestasis, one patient was restarted on FO after four months on SO.

Conclusions: Biochemical reversal of IFALD and growth were preserved after transition from FO to SO in 6/7 (86%) patients. Given the challenges associated with the use of FO, SO may be a viable alternative in select home PN patients.

Related blog posts:


NASPGHAN Postgraduate Course 2014 -Intestinal Inflammation

This blog entry has abbreviated/summarized the presentations. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.

Link: PG Course Syllabus – FINAL (entire syllabus)

The speakers reviewed a lot of IBD material (both at the postgraduate course and at the meeting); much of it has been has been covered in previous blog posts:

Early Onset Inflammatory Bowel Disease –Scott Snapper (Boston Children’s Hospital) pg 170 in Syllabus

  • If one has a 1st degree relative with Crohn’s disease: 26-fold increased risk for IBD compared with 8-fold increased risk if 1st degree relative has ulcerative colitis
  • 30% of children have one or more family members with IBD
  • Concordance rate much greater in monozygotic vs dizygotic twins: 10-15% in UC and 25-30% in Crohn’s with monozygotic

Infantile IBD (age <2 years)

  • Often isolated colonic disease
  • Severe course – refractory to multiple immunosuppressant medications, often requiring surgery, occasionally fatal
  • > 40 % with one or more family members with IBD
  • 25% with infantile IBD have this as their first manifestation of underlying immunodeficiency (pg 174): IPEX, CGD, NEMO, Wiscott-Aldrich, XIAP, common variable immunodeficiency
  • NEOPICS: interNational Early Onset Pediatric IBD Cohort Study. Expanded to 80 Centers (250 scientists) on 5 continents with access to over 1000 VEO-IBD patients
  • IL10 Receptor defect results in infantile onset IBD. Hematopoietic stem cell therapy can be curative. Increased risk of B-cell lymphomas.
  • NCF2 variant (NADPH Oxidase Gene) found in 4% of   (n=11/268)
  • TTC7A mutations (identified by whole exome sequencing) cause apoptotic enterocolitis, intestinal atresias, and SCID (severe combined immunodeficiency) –may not benefit by stem cell transplantation
  • Immune workup for VEO-IBD: immunoglobulins, DHR for CGD, lymphocyte subsets. If negative, further genetic testing (candidate gene testing &/or exome sequencing)

Surgery in Crohn’s Disease –Jason Frischer (Cincinnati Children’s)

  • 28% of CD patients need surgery within 10 years of CD diagnosis; 5.7% within one year.
  • Reviewed principles: conserve bowel, reserved for complications/does not cure Crohn’s disease, strictures can be treated without resection.

Perioperative care

  • Preop-“no answer with regard to biologics,” steroids are detrimental (goal <20 mg of prednisone).  Biologics may increase risk of infections (could be related to specific level) but this is unclear.
  • Postop: thromboprophylaxis

Surgical problems (JPGN 2013; 57: 394 NASPGHAN Guidelines): Abscess, Fistula, Stricture

  • Abscess: percutaneously drain abscess if >2 cm and can remove drain when having less than 10 mL/day. Surgery reserved if refractory to conservative treatment –?timing
  • Strictures: steroids to minimize acute inflammation.  Stricturolplasty rare in pediatrics –used only in those without fistulas. Most common stricturolplasty: Heineke-Mikulicz.
  • In Crohn’s patients at Cincinnati children’s who have undergone ileostomy, long-term only 46% able to have intestinal continuity

Crohn’s and UC ‐ What to do when anti‐TNF isn’t working? –Athos Bousvaros (Boston Children’s) pg 190 in Syllabus

Off-label IBD drugs in children for medically-refractory disease.

Potential Rescue treatments

  •  Calcineurin inhibitors for UC (eg. tacrolimus, cyclosporine)
  •  Thalidomide for Crohn disease
  •  Natalizumab for Crohn disease –>not being used anymore. PML risk
  •  Vedolizumab for Crohn disease and UC
  •  Ustekinumab for Crohn disease
  •  Tofacitinib for UC

Before off-label drugs:

  • Optimize TNF: Make sure the diagnosis is right (eg. exclude CGD), Minimize risk of loss of response (combination therapy, optimize dose, scheduled infusions)
  • Consider surgery -strictures, ulcerative colitis, limited disease

Data for tacrolimus from Boston. n=46. (Watson et al, IBD Journal 2011).  Used most frequently with severe UC.

Data for thalidomide –31 of 49 achieved remission. Lazzerini et al, JAMA. 2013;310(20):2164‐2173.  Side effects -birth defects, neuropathy.  STEPS program.

Data for vedolizumab. Feagan et al NEJM 2013; 369:699.  Remission (in the responders) for ulcerative colitis at 52 weeks:

  • 45% of patients getting vedolizumab monthly
  • 42% of patients getting it every other month
  • 16% of patients randomized to placebo

For Crohns’ disease , Vedolizumab also works in Crohn’s disease, but it takes time (Sands et al: Gastroenterology 2014 147:618‐627)

Off-label does not equate to experimental! pg 199:

FDA Statement: The FD&C Act does not, however, limit the manner in which a physician may use an approved drug. Once a product has been approved for marketing, a physician may prescribe it for uses or in treatment regimens or patient populations that are not included in approved labeling. Such “unapproved” or, more precisely, “unlabeled” uses may be appropriate and rational in certain circumstances, and may, in fact, reflect approaches to drug therapy that have been extensively reported in medical literature.


“Luminitis:” When Inflammation is Not IBD (Microscopic Colitides) –Robbyn Sockolow (Weill Cornell Medical School) pg 180 in Syllabus

Microscopic Colitis -pediatric prevalence unknown (JPGN 2013;57:557-561). Nonbloody diarrhea with normal-appearance grossly.

  • Lymphocytic Colitis (>20 intraepithelial lymphocytes/100 colonocytes) -Normal crypt architecture
  • Collagenous Colitis -Thick layer (up to 30 micrometers) of collagen in the tissue and increased lymphocytes in colon

Eosinophilic colitis

  • At-risk groups?  Infants & post-transplant patients (tacrolimus trigger?) (Saeed et al Pediatr Transplantation 2006: 10: 730–735)
  • Associated with food allergy, IBD, autoimmune diseases
  • Elevated serum IgE.


Microbial Signature in Crohn’s

This recent study (summarized in earlier post today/Dr. Barnard’s talk) provides more information on the microbiome in patients with pediatric Crohn’s.  Here’s a link to full article: Specific transcriptome and microbiome signature in pediatric Crohn’s   Here’s the abstract:

Interactions between the host and gut microbial community likely contribute to Crohn disease (CD) pathogenesis; however, direct evidence for these interactions at the onset of disease is lacking. Here, we characterized the global pattern of ileal gene expression and the ileal microbial community in 359 treatment-naive pediatric patients with CD, patients with ulcerative colitis (UC), and control individuals. We identified core gene expression profiles and microbial communities in the affected CD ilea that are preserved in the unaffected ilea of patients with colon-only CD but not present in those with UC or control individuals; therefore, this signature is specific to CD and independent of clinical inflammation. An abnormal increase of antimicrobial dual oxidase (DUOX2) expression was detected in association with an expansion of Proteobacteria in both UC and CD, while expression of lipoprotein APOA1 gene was downregulated and associated with CD-specific alterations in Firmicutes. The increased DUOX2 and decreased APOA1 gene expression signature favored oxidative stress and Th1 polarization and was maximally altered in patients with more severe mucosal injury. A regression model that included APOA1 gene expression and microbial abundance more accurately predicted month 6 steroid-free remission than a model using clinical factors alone. These CD-specific host and microbe profiles identify the ileum as the primary inductive site for all forms of CD and may direct prognostic and therapeutic approaches.

From Cincinnati Children’s Pediatric Insights (summary of findings):

“The discovery of specific bacterial populations and a core gene signature associated with Crohn’s disease could lead to new diagnostic testing and improved treatment for inflammatory bowel disease (IBD), according to a study led by researchers at Cincinnati Children’s.

‘This study identifies a set of bacteria that are associated with symptoms, and a group of anti-inflammatory genes that are associated with intestinal damage in children with Crohn’s disease,’ says Lee (Ted) Denson, MD, Medical Director of the Inflammatory Bowel Disease Center, senior investigator for the study, published online July 8 in the Journal of Clinical Investigation. Yael Haberman Ziv, MD, was the study’s first author.

Denson’s team studied tissue samples from the ileum, the lowermost portion of the small intestine, in a large number of children with Crohn’s disease. They found specific types of bacteria and a “core” gene expression signature, both of which appear to affect inflammatory changes in the gut. Certain genes in the core signature appeared to be specifically associated with intestinal damage from deep ulcers.”


Basic Science Year in Review –#NASPGHAN 2014

John Barnard –Basic Science Year in Review

“Emerging Trends and Provocative Findings in Basic Science”

This blog entry has abbreviated/summarized this terrific presentation. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.  To minimize these issues, I have placed a link to most of Dr. Barnard’s slides which he shared:

2014 John Barnard Slides

“Big Data” –big increase in “big data” cited in pubmed over past year.

  • Good read on this subject: Foreign Affairs: The Rise of Big Data Kenneth Cukier

Scientific fraud –more attention to this issue this past year. Two papers in Nature were retracted. One researcher committed suicide and one arrested. Scientific fraud undermines important messages & ruins credibility of other important advances.

CRISPR-Cas9: Gene editing.  CRISPRs –“RNA guides”  Cas9: “molecular scissors” (endonucleases)

“Genome editing has never been easier.”  Examples:

  • Cell Stem Cell 2013: 13: 653-58. “Functional repair of CFTR by CRISPR-Cas9”
  • Also, genome editing has been used in mouse model of tyrosinemia.

Liver regeneration in zebrafish. Implication: Liver cells will be regenerated in humans. Gastroenterol 2014; 146: 789.

Microbiome Big Data:

  • J Clin Invest 2014; 124: 3617. This was a very important and complex study.  The slides explaining this study start at slide 35.
  • Pediatric Crohn disease exhibit specific ileal transcriptome and microbiome signature.
  • RISK study (CCFA). Treatment-naïve, 28 sites.
  • 1281 ileal host genes in ileocolonic Crohn’s, 1055 in Colonic Crohn’s had ileal host genes =82% similar, 232 host genes in ulcerative colitis –18% similar to ileocolonic Crohn’s.
  • Tissue microbiomes are where changes are noted; changes are not evident in luminal microbiome.
  • Antibiotics worsen dysbiosis.
  • Microbiome at diagnosis strongly correlates with Crohn’s disease.

Microbiome –affects the entire body:

  • J Clin Invest 2014; 124: 3391. Incorporation of microbes with genetically-engineered E coli can prevent obesity in mice

Recommended Reading by Dr. Barnard: “Missing Microbes” How the overuse of antibiotics is fueling our modern plagues. Martin Blaser


NASPGHAN Postgraduate Course 2014 -Endoscopy Module

This blog entry has abbreviated/summarized the presentations. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.  Link to full syllabus:

PG Course Syllabus 2014

The Dreaded Wake-Up Call (Part A) –Maercedes Martinez (NY Presbyterian Hospital) (pg 55 syllabus)

Variceal Bleeding – “When RED is not attractive”

Discussed presentation of varices (gastric/esophageal), etiologies, association with portal hypertension. Reviewed variceal grading.

Medical management:

  • PICU admit
  • Avoid over-transfuse (goal ~ 8 g/dL)
  • Correct coagulopathy
  • Role of platelets is controversial/if trouble with endoscopy, may be helpful
  • Suggested dosing for octreotide/somatostatin: 2 mcg/kg bolus then 1-2 mcg/kg/hr (typically max 100 mcg/hr), antibiotics
  • Most patients do not require emergency overnight endoscopy.
  • Sclerotherapy and banding reviewed -including complications.
  • Transjugular intrahepatic portosystemic shunts (TIPS) and Surgical options briefly discussed

The Dreaded Wake-Up Call (Part B) –Lee Bass (Children’s Hospital of Chicago) (pg 67 in syllabus)

Nonvariceal GI Bleeding Management

  • Start with ABCs -airway, breathing, cardiovascular –fluid resuscitation/blood products
  • Restrictive transfusion strategy (Hgb <7 as threshold) (Villanueva et al NEJM 2013) helpful for survival in adults
  • Treatment with PPI improves rates of high risk stigmata on endoscopy
  • Prokinetics can improve identication of bleeding lesions
  • Preparation for endoscopy is most important (slide on page 70 of syllabus)
  • Also on page 70, pictures of typical findings with GI bleeding: nonbleeding vessel, adherent clot, spurting blood, oozing blood, and flat pigmented spot and clean base
  • Endoscopic management -combination of two techniques appears to be more effective than single method. injection, thermal probe, hemoclips, hemospray (not available in U.S.

Endoscopic Interventions for Biliary Tract Disease — Victor Fox (pg 75 in Syllabus)

Choledocholithiasis is most common need for interventional biliary endoscopy and increasing related to increase risk with increase in obesity.(Buxbaum J. Gastrointest Clin N Am 2013;23:251‐75)

Requires advanced training to achieve high level of skill and experience

  • >200 cases needed to achieve selective cannulation required for interventions
  •  Acquisition and maintenance of skills by pediatricians is controversial

Other points:

  • No equipment is favorably designed for young or small children
  • Success and complication rates are similar as in adults (Varadarajulu S, et al. Gastrointest Endosc 2004;60:367)
  • Discussed biliary strictures (etiologies, management/stents), choledochocele, papillotomy, bile leak (Soukup ES et al. J Pediatr Surg 2014;49:345‐8)
  • “Most strictures and leaks can be successfully managed endoscopically without need for surgical intervention”

Take-home message: Endoscopic biliary interventions are increasingly employed in children with similar safety and technical success as adult patients

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.