“White Nipple Sign” (aka Mount St. Helens’ sign) and Varices

M Najem, E Dong. N Engl J Med 2024;390: e47. Esophageal Varices, White-Nipple Sign, and Portal Hypertensive Gastropathy

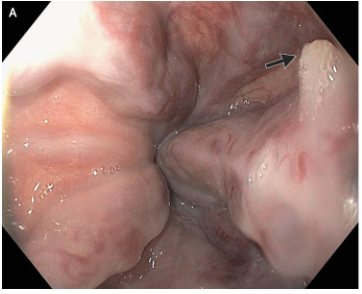
This case reported on a 66 year old with cirrhosis and variceal bleeding. “One varix had a “white-nipple sign” (Panel A, arrow), which indicates recent variceal hemorrhage and results from the formation of a fibrin plug at the site of a resolved thrombus.”
Related article: N Khan, A Shapiro. Case Rep Gastroenterol. 2011 May-Aug; 5(2): 386–390. The White Nipple Sign: Please Do Not Disturb

“Though not widely mentioned as a stigma of recent variceal hemorrhage, this finding was first reported by Chung and Lewis in 1984 [4]. They described it as a white nipple on top of a varix protruding into the lumen and noted its presence in up to 5% of cases of variceal bleeding. It was thought to represent a platelet-fibrin plug at the site of recent variceal rupture. They noted that dislodgement would be accompanied by jet-like bleeding and called it ‘Mount St. Helens’ sign’ due its volcanic-like eruption…As Chung and Lewis [4] initially suggested, it should ‘alert the endoscopist to take urgent measures to avert a disaster’. Recognizing it as such, attempts to dislodge the lesion must be avoided and endoscopic therapy should be undertaken.”

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
Predicting Enteral Nutrition Therapy Response in Patients with IBD

B White, et al. Infammatory Bowel Diseases, 2024; XX, 1–13
https://doi.org/10.1093/ibd/izae107
. Open Access! Inflammation-related Proteins Support Diagnosis of Inflammatory Bowel Disease and Are Modified by Exclusive Enteral Nutrition in Children With Crohn’s Disease, Especially of Ileal Phenotype

Background/Methods: The authors characterized the plasma levels of inflammation-related proteins (IRPs) in children with CD and ulcerative colitis (UC) compared with noninflammatory controls (non-IBD) and explored the effect of EEN in children with CD. Population included children with CD (n = 53), UC (n = 11), and non-IBD (n = 19). For 18 children with active CD, IRPs were measured before and after 8 weeks of EEN.

Key findings:

  • Compared with non-IBD, patients with active UC and CD had different levels of 27 (24 raised, 3 decreased) and 29 (26 raised, 3 decreased) IRPs, respectively.
  • Exclusive enteral nutrition modified the levels of 19 IRPs (13 increased, 6 decreased including CCL23, interleukin-24, interleukin-6, and MMP-1). 
  • More pronounced changes in IRP profile were observed in patients with ileal involvement and a ≥50% decrease in fecal calprotectin during EEN.

The discussion notes that “these profiles also helped to uncover some of the underlining pathological mechanisms, with CD demonstrating enhanced levels of IRPs related to IFN-γ and Th1-associated pathways, whereas in UC we observed an enrichment in IRPs related to Th17 pathways.”

My take (borrowed from authors): Inflammation-related protein profiles could help to stratify patients likely to respond to treatment with EEN.

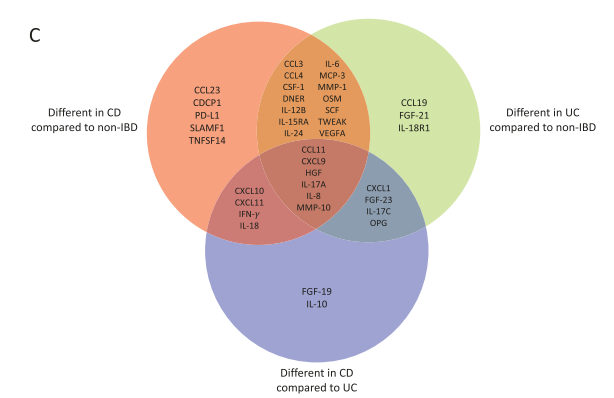
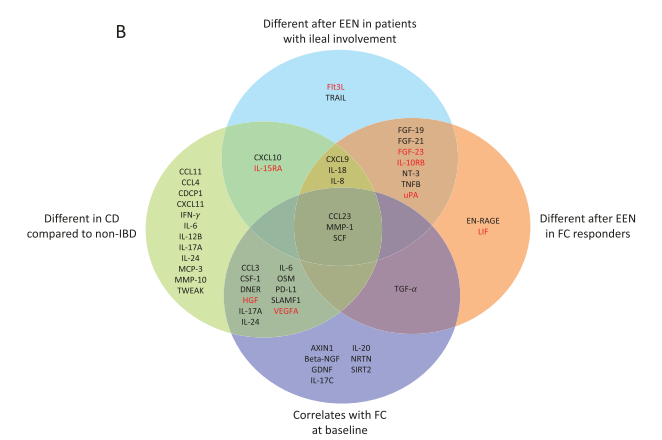
, Venn diagram of the proteins found to be signifcantly different between each IBD
subtype compared to non-IBD controls and between each IBD subtype.
Venn diagram summarizing the main significant (P ≤ .05) differences or correlations found in IRPs. Proteins highlighted in red were shown to significantly interact with thiopurines

Related blog posts:

Safety and Efficacy of Potassium Competitive Acid Blockers (3 Studies)

J Arai et al. Clin Gastroenterol Hepatol 2024; 22: 1217-1225.Association Between Vonoprazan and the Risk of Gastric Cancer After Helicobacter pylori Eradication

Methods: Using a population-based claims database in Japan, the authors identified patients who were prescribed a clarithromycin-based first regimen of Hp eradication between 2015 and 2018.

Key findings:

  • Among 54,055 patients, 568 (1.05%) developed gastric cancer (GC) during the follow-up period (mean, 3.65 years).
  • The cumulative incidence of GC was 1.64% at 3 years, 2.02% at 4 years, and 2.36% at 5 years in potassium-competitive acid blocker (PCAB) users and 0.71% at 3 years, 1.04% at 4 years, and 1.22% at 5 years in H2RA users. 
  • Limitations: retrospective study with issues of selection bias and confounding.

In the discussion, the authors note PCABs are being used not only for Hp eradication but for peptic ulcers, reflux and several abdominal symptoms. “According to the results of our study, longer use of PCABs was particularly associated with the increased risk of GC after Hp eradication…it might be better to switch strong acid inhibitors including PCABs ad PPIs to H2RAs before reaching a lengthy prescription period (eg. more than 3 years).”

————————————————-

X Peng et al. Clin Gastroenterol Hepatol 2024; 22: 1210-1216. Open Access! Efficacy and Safety of Vonoprazan-Amoxicillin Dual Regimen With Varying Dose and Duration for Helicobacter pylori Eradication: A Multicenter, Prospective, Randomized Study

This multicenter, prospective, randomized controlled, noninferiority trial enrolled patients (n=516) with treatment naive H pylori infection from 5 clinical centers. All patients received vonoprazan at 20 mg 2/day. The high dose amoxicillin was 750 mg 4/day and the low dose 1000 mg 2/day.

Key findings:

  • The high-dose amoxicillin combination with vonoprazan regimen, for either 10 or 14 days, was effective and safe in eradicating H pylori, whereas the low-dose amoxicillin regimen for 10 days was less effective. The high-dose per protocol eradication rates were 90.9% vs 94.5 for 10 vs 14 days compared to 82.0% in the low-dose per protocol eradication rate (for 14 days).

—————————————————–

Q Zhuang et al Am J Gastroenterol 2024; 119(5):p 803-813, May 2024. Open Access! Comparative Efficacy of P-CAB vs Proton Pump Inhibitors for Grade C/D Esophagitis: A Systematic Review and Network Meta-analysis. (see prior post: Improved Efficacy with Vonoprazan for Severe Esophagitis). This maintenance treatment group mainly included PPI patients receiving a relatively low once-daily dose (e.g. omeprazole 20mg, lansoprazole 15 mg and esomeprazole 20 mg). Treatment failure rates noted below:

My take: These studies indicate that PCABs are more effective at healing erosive esophagitis as well as H pylori gastritis. However, particularly in patients with Hp infection, the use of PCABs is associated with an increased risk of gastric cancer. The exact long-term risk of strong acid inhibition is unclear, especially in those without a history of Hp infection.

Related blog posts:

Ulcerative Colitis Therapy for Castaways? And PYRAMID Safety Data

S Kedia et al. Clin Gastroenterol Hepatol 2024; 22: 1295-1306. Open Access! Coconut Water Induces Clinical Remission in Mild to Moderate Ulcerative Colitis: Double-blind Placebo-controlled Trial

Background: “Coconut water (CW) possesses anti-inflammatory properties, can potentially manipulate the microbiome, is a rich source of dietary potassium,” and may be an effective treatment for mild to moderate ulcerative colitis (UC).

Methods: Along with standard medical therapy, four hundred mL of CW (200 mL 2/day) or placebo fluid was administered for 8 weeks to adults (CW, n = 49; placebo, n = 46) with mild to moderate UC

Key findings:

  • Clinical response (57.1% vs 28.3%; odds ratio [OR], 3.4), remission (53.1% vs 28.3%; OR, 2.9), and proportion of patients with fecal calprotectin (FCP) <150 μg/g (30.6% vs 6.5%; OR, 6.3) all significantly favored CW group
  • There was not a significant difference in endoscopic outcomes

The authors indicate CW may be a useful adjunct for mild to moderate colitis but should be avoided in those patients taking medications that affect potassium and those with chronic kidney disease.

My take: This would be a good study to repeat to confirm whether CW is helpful for colitis. Certainly too much CW (a high FODMAP beverage) can contribute to a laxative effect and elevated potassium in some people. If a person with colitis is stranded on an island, CW may help until a rescue arrives.

Related blog posts:

D Ahuja et al. Clin Gastroenterol Hepatol 2024; 22: 1286-1294. Impact of Treatment Response on Risk of Serious Infections in Patients With Crohn’s Disease: Secondary Analysis of the PYRAMID Registry

In this prospective observational real-world treatment registry…

Key findings:

  • Of 1515 adalimumab-treated patients, 763 (50.4%) were classified as responders at 6 months
  • Compared with nonresponders, responders were less likely to have moderate to severe symptoms (55.6% vs 33%), or require steroids (45.5% vs 17.3%) or opiates (6.6% vs 1.3%) at baseline
  • During follow-up evaluation, using stabilized inverse probability of treatment weighting, responders were 34% less likely to experience serious infections compared with nonresponders (hazard ratio, 0.66)

The study results are similar to a registry-based rheumatoid arthritis study by Strangfeld et al (Ann Rheu m Dis 2011; 70: 1914-1920), which showed effective treatment was associated with less steroid use and a decline int risk of serious infections.

My take: This study indicates that lack of control of CD increases the risk for complications and infections. So, while patients are concerned about medication adverse effects, the complications of foregoing treatment or ineffective treatment are usually more concerning.

Evaluation of Hematochezia in Infants with Congenital Heart Disease

S Pradham et al. J Pediatr 2024; 269: 113992. Management of Hematochezia in Infants with Congenital Heart Disease Admitted to the Acute Care Cardiology Unit: A Multicenter Retrospective Pilot Study

Methods: This was a multicenter retrospective review of patient characteristics and evaluation of all hematochezia events in patients (n=121 patients with 180 events) with CHD <6 months admitted to acute care cardiology unit at 3 high-volume tertiary care centers from February 2019 to January 2021. In total, 61% of affected patients had single-ventricle physiology (38% hypoplastic left heart syndrome). Most patients (81%) were full-term.

Key findings:

  • 77% of hematochezia events were benign, and 23% were due to necrotizing enterocolitis (NEC). There were no surgical interventions for NEC or deaths from NEC. 
  • Those with NEC were significantly younger (34 vs 56 days, P < .01) and smaller (3.7 vs 4 kg, P < .01). Single-ventricle physiology was significantly associated with NEC.
  • Bloodwork (CBC, WBC, CRP, Blood Culture) did not aid diagnosis

My take: If concerned about NEC which is increased in those with congenital heart disease, obtain an AXR. Overall, the outcomes of NEC in this cohort were good –all resolved with medical management.

Related blog posts:

Huntingdon Lake (Sandy Springs, Atlanta)

Relooking at 6-Year Data of Maralixibat for Alagille Syndrome

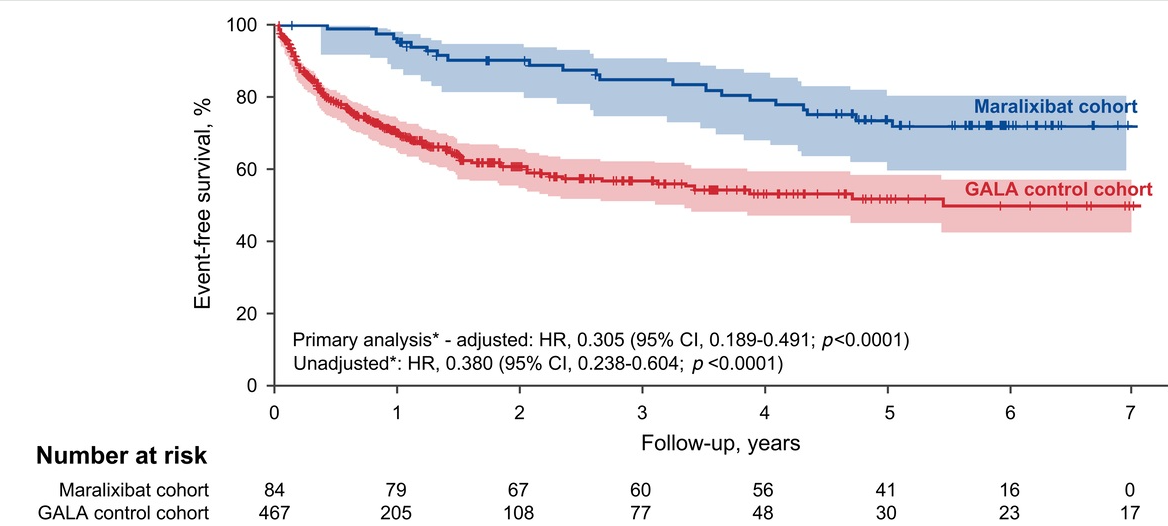
BE Hansen et al. Hepatology 2024; 79: 1279-1292. Open Access! Event-free survival of maralixibat-treated patients with Alagille syndrome compared to a real-world cohort from GALA

This study compared “6-year outcomes from maralixibat trials with an aligned and harmonized natural history cohort from the Global ALagille Alliance (GALA) study.”

Based on a quick review, some the data appears to overlap a recent report in the same journal: RJ Sokol et al. Hepatology 2023; 78: 1698-1710. Open Access! Predictors of 6-year event-free survival in Alagille syndrome patients treated with maralixibat, an ileal bile acid transporter inhibitor (See blog post: Six Year Data for IBAT Inhibitor Treatment for Alagille Syndrome).

In the current study, “event-free survival, defined as the time to first event of manifestations of portal hypertension (variceal bleeding, ascites requiring therapy), surgical biliary diversion, liver transplant, or death, was analyzed by Cox proportional hazards methods.”

Key findings:

  • Event-free survival in the maralixibat cohort (n=84) was significantly better than the GALA cohort (n=469) (HR, 0.305)
  • Transplant-free survival showed similar results (aHR, 0.33)

In their discussion, the authors note that much of the improvement in event-free survival is due to improvement in pruritus which is a main indication for liver transplantation. They speculate that improvement in event-free survival is also related to more broad-based clinical improvement (observed in ICONIC study), perhaps due to reduction in retained hepatic bile acids.

One of the limitations, reliance on a historical control, is discussed. “Historical control comparison is useful when there are ethical concerns regarding the recruitment of patients for long-term control arms requiring several years of study in life-threatening or debilitating diseases.”

My take: In this real-world comparison, Maralixibat, clearly was associated with improved outcomes. How much of this was due to relief of intractable pruritus and how much of this may be due to other biologic factors remains uncertain.

Related blog posts:

Do PPIs Increase the Risk of Eosinophilic Esophagitis in Patients with Esophageal Atresia?

TC Tang et al. JPGN 2024;78:1317–1328. Proton pump inhibitors, antibiotics, and atopy increase the risk of eosinophilic esophagitis in children with esophageal atresia

In this retrospective study (2005-2020) with 184 children, key findings:

  • Of 184 children with EA, 46 (25%) developed EoE during this period
  • Children with EoE and EA received PPI for significantly higher durations (p = .018) and at significantly higher cumulative doses (p = .017) than controls. (Controls were children with EA who did not develop EoE)
  • Food allergy (adjusted odds ratio [aOR], 7.317, family history of atopy (aOR, 3.504), and infantile antibiotic exposure (aOR, 1.040) were also significantly associated with an increased risk of developing EoE in the EA cohort

Discussion: “This is congruent with the emerging evidence in the general pediatric population that there is an increased risk of EoE development in individuals who undergo acid suppressive therapy. A possible explanation for these findings is that acid suppressants inhibit gastric parietal cell function and elevate the gastric pH, thereby impairing peptic digestion of dietary allergens, potentiating sensitization, and facilitating the development of allergic diseases like EoE.” Other potential explanations could include PPIs could increase mucosal permeability and/or contribute to dysbiosis.

“Hence, the routine use of PPIs for the first year of life as recommended by the current guidelines may need to be revisited..”

My take: This study shows a clear association of PPIs with development of EoE in this cohort. Due to the study design, it is difficult to be confident regarding causality due to possible selection bias (patients who received PPIs may be those with more predisposition to EoE). Nevertheless, this study suggests that prolonged use of PPIs, even in groups at risk for reflux damage, needs to be carefully considered and possibly directed by objective markers of reflux.

Related blog posts:

Arches National Park

Expert Advice on Gluten Introduction and Risk of Celiac Disease

H Szajewska et al. JPGN 2024; https://doi.org/10.1002/jpn3.12280. Open Access! Early diet and the risk of coeliac disease. An update 2024 position paper by the ESPGHAN special interest group on coeliac disease

Key points:

  • Breastfeeding, whether any amount, exclusive, or of any duration, does not reduce the risk of developing CD
  • Introducing gluten into an infant’s diet at any time between completed 4 months (≥17 weeks) and 12 months of age does not affect the cumulative incidence of CD

Related blog posts:

Survodutide, Dual Glucagon Receptor/GLP-1 Receptor Agonist, for MASH (Phase II Trial)

AJ Sanyal et al. NEJM 2024; DOI: 10.1056/NEJMoa2401755. A Phase 2 Randomized Trial of Survodutide in MASH and Fibrosis

Background/Methods: “Dual agonism of glucagon receptor and glucagon-like peptide-1 (GLP-1) receptor may be more effective than GLP-1 receptor agonism alone for treating metabolic dysfunction–associated steatohepatitis (MASH). The efficacy and safety of survodutide (a dual agonist of glucagon receptor and GLP-1 receptor) in persons with MASH and liver fibrosis” was studied in “48-week, phase 2 trial, we randomly assigned adults with biopsy-confirmed MASH.” (n=293)

“Dual agonism of glucagon receptor and GLP-1 receptor may be more effective than GLP-1 receptor monoagonism for treating MASH, because the extrahepatic benefits of GLP-1 receptor agonism (glucose control, reduced appetite, and weight loss) are combined with direct hepatic effects (increased energy expenditure, lipolysis, and mobilization of hepatic fat) associated with glucagon receptor agonism.”

Key findings:

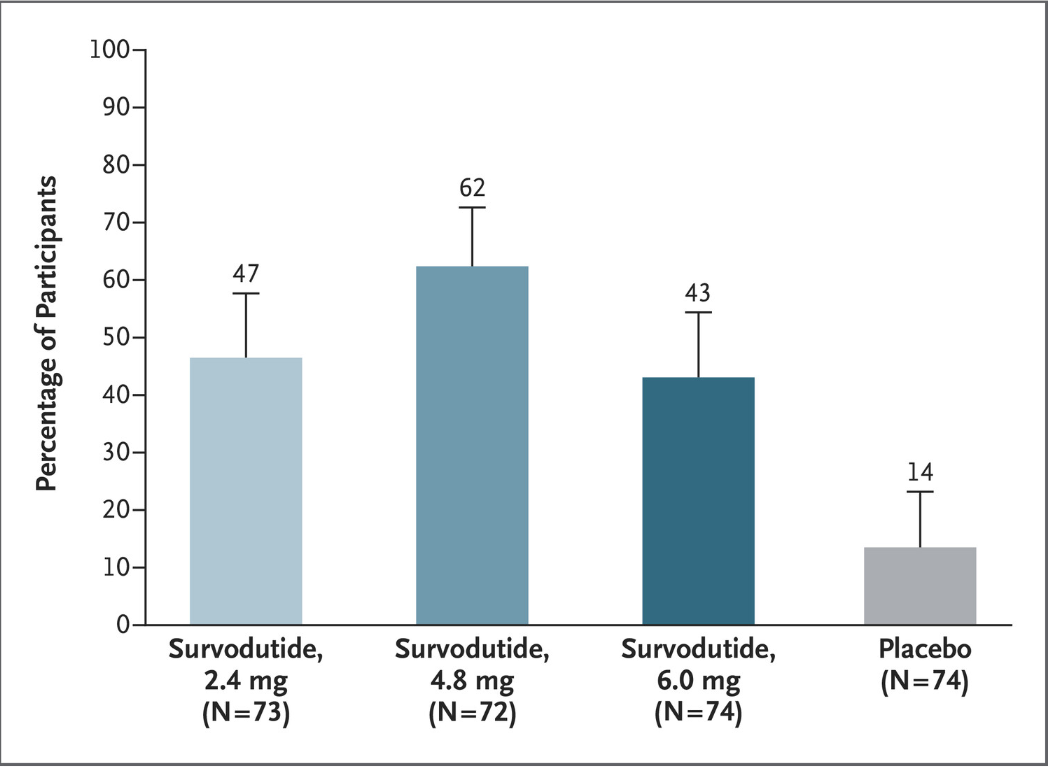
  • Improvement in MASH with no worsening of fibrosis occurred in 47% of the participants in the survodutide 2.4-mg group, 62% of those in the 4.8-mg group, and 43% of those in the 6.0-mg group, as compared with 14% of those in the placebo group
  • A decrease in liver fat, assessed by MRI-PDFF, content by at least 30% occurred in 63% of the participants in the survodutide 2.4-mg group, 67% of those in the 4.8-mg group, 57% of those in the 6.0-mg group, and 14% of those in the placebo group; improvement in fibrosis by at least one stage occurred in 34%, 36%, 34%, and 22%, respectively. 
  • Adverse effects were more frequent with survodutide than with placebo included nausea (66% vs. 23%), diarrhea (49% vs. 23%), and vomiting (41% vs. 4%); serious adverse events occurred in 8% with survodutide and 7% with placebo.
Primary Endpoint at 48 weeks. The primary end point was histologic improvement (reduction) in metabolic dysfunction–associated steatohepatitis (MASH) with no worsening of fibrosis at week 48.

The discussion notes that “in a phase 2 trial, treatment with the GLP-1 receptor monoagonist semaglutide resulted in a significantly higher percentage of patients with MASH resolution than placebo but not in a significantly higher percentage of patients with improvement in fibrosis stage.26” Thus, the improvement in fibrosis, which was seen in this study with survodutide,will need to be examined in future studies.

My take: Earlier this year, the selective thyroid hormone receptor beta agonist resmetirom gained conditional approval from the Food and Drug Administration as the first pharmacotherapy for MASH with moderate-to-advanced liver fibrosis.5  It looks like there will be a number of pharmacologic agents available in the coming years. Cost and availability will be ongoing concerns. In addition, determining when/how these agents will be used in the pediatric population will not be clear for quite a long time.

Related blog posts:

Also, A Few Years Ago –Button Battery Changes

It turns out that Duracell has been trying to reduce button battery ingestions for a few years (in 2020) by coating the sides of the batteries with a bitter tasting no-toxic chemical. I only recently found out about this. “Duracell uses Bitrex, a non-toxic, man-made substance that’s considered the world’s most bitter, to create the coating. The coating is harmless if consumed, but it’s designed to encourage children to spit out the battery immediately.” (Anecdotally, one of our endoscopy nurses said she tried the battery and she did not think it was very bitter.) The packaging is also very difficult to open without scissors.

Advice from their website: “If your child swallows a battery, go to the emergency room.
If you have other questions or concerns, call 1-800-498-8666 or visit www.batteryingestionhotline.com.”

Related blog posts: