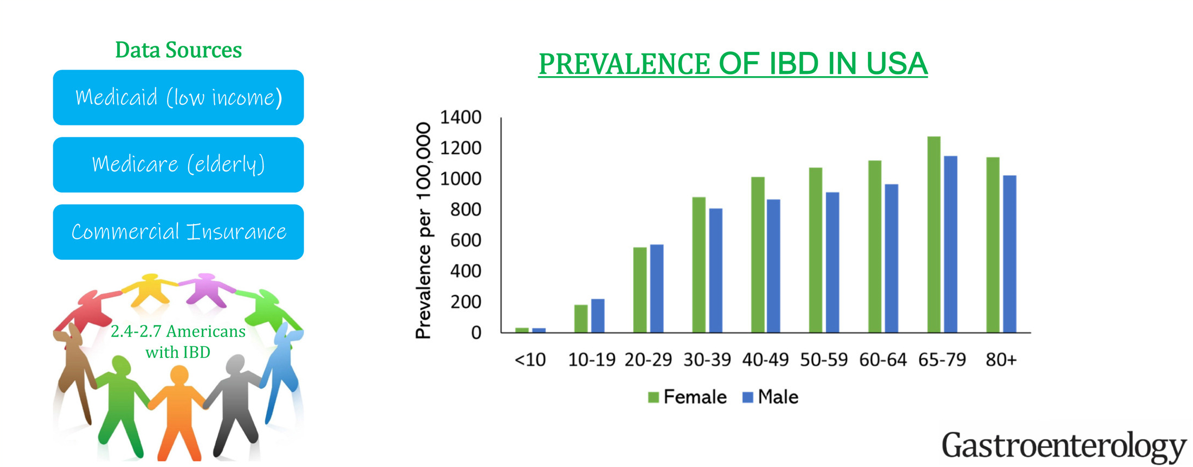
U.S. IBD Prevalence: 7 in 1000

JD Lewis et al. Gastroenterology 2023 Nov;165(5):1197-1205.e2. doi: 10.1053/j.gastro.2023.07.003. Incidence, Prevalence, and Racial and Ethnic Distribution of Inflammatory Bowel Disease in the United States

This “INPUT” (INcidence, Prevalence, Treatment and OUTome in Patients with IBD) study used 4 different data sets to provide “the clearest depiction to date of IBD [epidemiology] in the U.S.

Key findings:

  • The age-, sex- and insurance-standardized prevalence of IBD was 721 per 100,000 population. This equates to estimated 2.39 million Americans with IBD.
  • Sub-category prevalence: the prevalence of IBD per 100,000 population was 812 in White, 504 in Black, 403 in Asian, and 458 in Hispanic Americans.

My take: The prevalence of IBD continues to increase and the U.S. has one of the highest rates in the world.
Related blog posts:

Granulomatous Lung Disease: Case for GI Doctors

JB McCannon et al. NEJM 2023; 389: 1902-1911. Case 35-2023: A 38-Year-Old Woman with Waxing and Waning Pulmonary Nodules

In this case report, A 38-year-old woman was evaluated because of dyspnea, chest discomfort, and waxing and waning pulmonary nodules. She had a prior history of ulcerative colitis. This article reviews reasons for pulmonary nodules including cancer, infection, vasculitis, connective tissue disorders, sarcoidosis and inflammatory bowel disease (IBD) which has a number of pulmonary manifestations including necrobiotic nodules.

In this case, the granulomatous lung disease was attributed to be an extraintestinal manifestation of IBD. She was treated with TNF-alpha targeted therapy which has been effective in a prior case report (J Crohns Colitis 202; 14: 480-489).

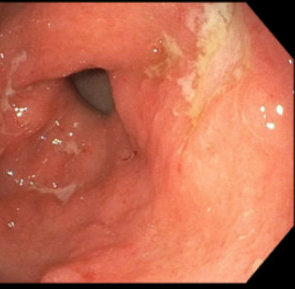
My first reaction to this article — I have seen this! However, our case was atypical in that the 15 year old patient presented with respiratory symptoms (no preceding GI diagnosis). It was noted that her gastric wall was severely thickened as an incidental finding on her chest CT which showed extensive tiny pulmonary nodules. Her endoscopy showed disease isolated to her stomach. Both her gastric findings and CT of her chest resolved with infliximab treatment. This included mucosal healing of her stomach on followup endoscopy.

CT scan showing severely thickened gastric wall
Mucosal appearance of stomach with erythema and numerous ulcerations prior to treatment

Related blog post: IBD Update January 2015 (Part 1) NEJM 2014; 371: 2418-27 -case report of 9 yo with  Crohn’s Disease and pulmonary nodules

Genetic Test to Help Determine Need for Combination Therapy with Anti-TNF

V Solitano et al. Clin Gastroenterol Hepatol 2023; 21: 3019-3029. HLA-DQA1∗05 Genotype and Immunogenicity to Tumor Necrosis Factor-α Antagonists: A Systematic Review and Meta-analysis

Key findings:

  • On meta-analysis of 13 studies (3756 patients; median follow-up, 12 months; 41% with variants), HLA-DQA1∗05 variants were associated with 75% higher risk of immunogenicity compared with non-carriers (relative risk, 1.75) with considerable heterogeneity (I2 = 62%) (low certainty evidence).
  • In addition, patients with HLA-QQA1*05 variants had clinical loss of response (LOR) in 67% compared to 30% in those without this variant (wild-type); thus, a 124% higher risk of LOR.
  • Positive and negative predictive values of HLA-DQA1∗05 variants for predicting immunogenicity were 30% and 80%, respectively
  • Proactive therapeutic drug monitoring, but not concomitant use of IMMs, IMIDs, and TNF-α antagonist-type, modified this association.

My take:

  • The ~40% of individuals with HLA-DQA1*05 variants are at higher risk of LOR and are more likely to benefit from both therapeutic drug monitoring and probably from use of combination (with immunomodulator) therapy.
  • The positive predictive value (30%) is low indicating that the majority of patients with these variants will not develop anti-drug antibodies within 12 months.
  • In those with negative testing for HLA-DQA1*05 (~60%), the higher negative predictive value indicates a patient is more likely to do well with monotherapy.
  • HLA-DQA1*05 testing is available commercially (usually part of Celiac HLA typing).

Related blog posts:

This is the Initiation Well at Quinta da Regaleira in Sintra, Portugal.
It is pretty cool because it seems to start at ground level and then goes down many floors.
There is an exit to a number of tunnels at the lower level.

What’s Changing in IBD Care: Hospitalization Rates and Authorizations

The Good News:

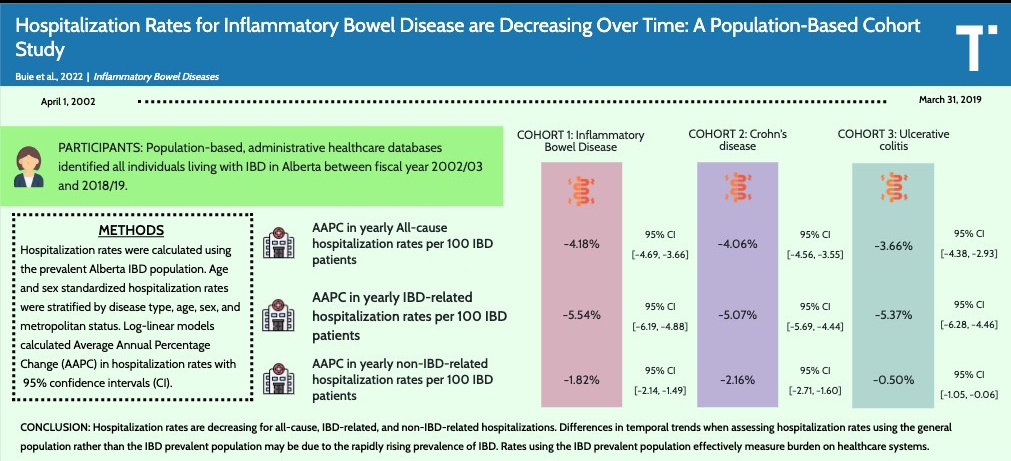
MJ Buie et al. Inflamm Bowel Dis 2023; 29: 1536-1545. Open Access! Hospitalization Rates for Inflammatory Bowel Disease Are Decreasing Over Time: A Population-based Cohort Study

This population-based administrative data cohort study provides annual IBD hospitalization rates in Alberta, Canada.

Key findings:

  • From 2002-2003 to 2018-2019, all-cause hospitalization rates decreased from 36.57 to 16.72 per 100 IBD patients (Average Annual Percentage Change (AAPC), −4.18%)
  • Inflammatory bowel disease–related hospitalization rate decreased from 26.44 to 9.24 per 100 IBD patients (AAPC, −5.54%)
  • The absolute number of hospitalizations, however, likely did not improve because this is affected by the increase in IBD prevalence. In Alberta, there was a 3-fold increase from 2002 to 2018 (general population increased 1.4 fold during this period)

“The last 2 decades have seen the introduction of several advanced therapies with novel mechanisms of action.22 The introduction of these therapies has been accompanied by changes in management strategies that include earlier introduction of advanced therapies based on risk stratification, treat-to-target, and monitoring strategies.5,23–26 These advancements include risk stratification, allowing for earlier introduction of advanced therapies; proactive clinical management algorithms to monitor disease activity; and therapeutic drug monitoring allowing for continued concentration-based dosing.23–26The net effect of these medical advances shifted IBD management from the hospital to the outpatient setting.27“

The Bad News:

DK Choi et al. Inflamm Bowel Dis 2023; 29: 1658-1661. Delays in Therapy Associated With Current Prior Authorization Process for the Treatment of Inflammatory Bowel Disease

This retrospective study of 1693 prior authorizations (PAs) from 2020-2021. Key findings:

  • 1397 PA initially approved, 209 first-level PAs approved, 23 second-level PAs approve, and 11 external review requests approved. In total 97% (1640 of 1697) were approved
  • Dose escalations had the lowest approval rate of 67.6%
  • FDA approval had favorable OR for PA approval of 4.45
  • The median time to biologic initiation was 21 days, with appeals causing further delays to initiation

Median Days to Determination by Insurance Level:

  • Prior authorization: 11 days
  • First level appeal: 29 days
  • Second level appeal: 51 days
  • External review request: 73 days

My take: The PA process usually results in few denials (if pursued) but does result in significant delays in therapy. At the same time, these newer therapies have been associated with improvement in hospitalizations rates.

Related blog posts:

COMBO-IBD Study -Combination Immunomodulator Use and Thresholds

AJ Yarur et al. Clin Gastroenterol Hepatol 2023; 21: 2908-2917. Open Access! Combination Therapy With Immunomodulators Improves the Pharmacokinetics of Infliximab But Not Vedolizumab or Ustekinumab

In this prospective cohort with 369 patients, treatment included the following 113 infliximab, 133 vedolizumab, and 123 ustekinumab. All patients received standard dosing (eg. 5 mg/kg/dose every 8 weeks with infliximab). Per Table 1, dose of thiopurine was 100 mg (range 50-150, “using a 2:1 ratio of azathioprrine and mercaptopurine”); most patients received methotrexate at a dose of 12.5 mg. Key findings:

  • Infliximab levels were much improved in patients receiving combination therapy with either a thiopurine or methotrexate. In those patients receiving a thiopurine, a threshold of 6-TGN ≥146 was considered optimal.
  • Patients receiving combination therapy with methotrexate or a thiopurine and a 6-TGN concentration ≥146 pmol per 8 × 108 RBCs, and those with baseline infliximab level ≥12.3 μg/mL had a lower rate of secondary nonresponse when compared with those on monotherapy, thiopurine with 6-TGN <146 pmol per 8 × 108 RBCs, and baseline infliximab level <12.3 μg/mL (88.2 vs 11.8% [P = .04], 71.2 vs 45.5% [P = .04])
  • Ustekinumab and vedolizumab levels were NOT increased in patients receiving an immunomodulator

My take: This study reinforces the idea that there are pharmacokinetic benefits of combination therapy with infliximab (and extrapolated to other anti-TNF agents); there is a lack of benefit for most patients receiving ustekinumab and vedolizumab. Even with ustekinumab and vedolizumab, it is possible that patients with more severe disease may still benefit independent of pharmacokinetic effects on biologic agent.

Higher doses of infliximab monotherapy with therapeutic drug monitoring may achieve similar results as combination therapy. However, patients switching from one anti-TNF to another due to immunogenicity/antidrug antibodies are particularly likely to benefit from combination therapy. In addition, a recent ImproveCareNow study showed better outcomes for pediatric patients who received methotrexate with adalimumab (see below).

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

How Much Ustekinumab (Stelara) Is Needed to Get a Good Response

K Chen et al. Inflamm Bowel Dis 2023; 29: 1499-1503. Serum Ustekinumab Concentrations Are Associated With Improved Outcomes With the Magnetic Resonance Index of Activity for Crohn’s Disease

This retrospective trial included thirty three patients with Crohn’s disease (CD) receiving maintenance ustekinumab (UST). The simplified Magnetic Resonance Index of Activity (sMARIA) and biomarkers were correlated with UST levels. The authors utilized a homologous mobility shift assay (HMSA) (Prometheus) for their UST levels.

Key findings:

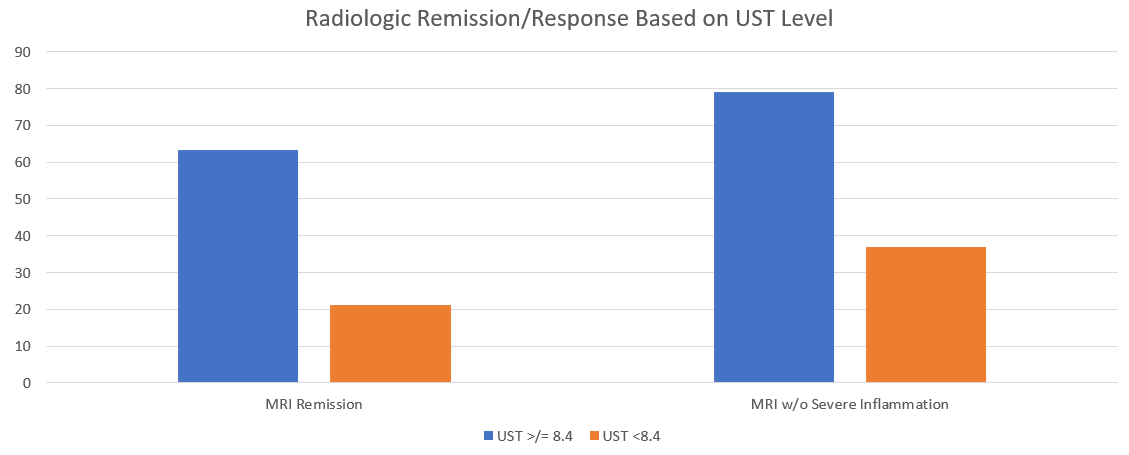
With UST level greater or equal to 8.4, radiologic remission was seen in 63% compared to 21% in those with levels <8.4. Similarly, the absence of severe inflammation was seen in 78.9% of those with higher levels compared with only 36.8% in those with levels below 8.4.
Both findings were clinically-significant P=.01
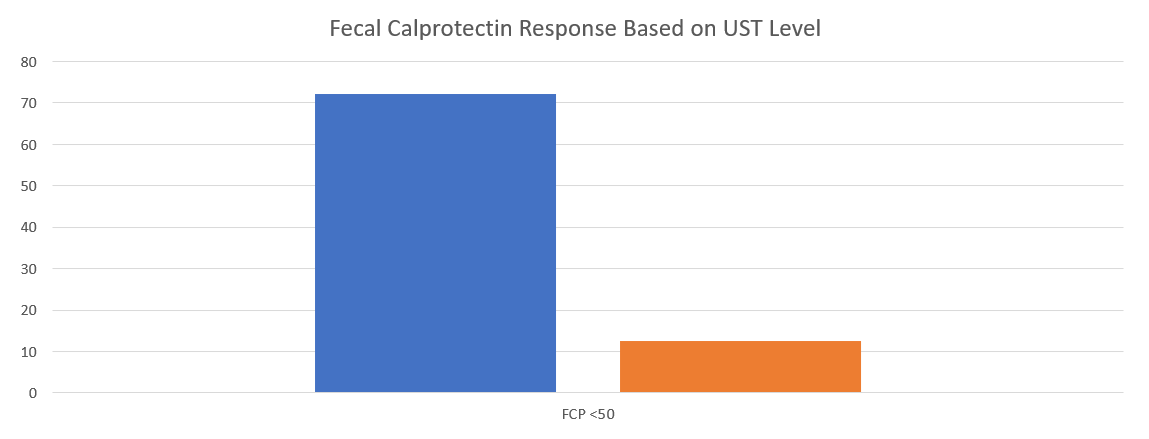
With UST levels greater or equal to 6.1, FCP less than 50 was seen in 72.2% compared to only 12.5% in those with a level less than 6.1. P<.01

My take: This study show the need for higher levels of UST to achieve optimal outcomes. Levels of at least 8.4 appear to be a good target.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

When Patients Have an IBD Flare, It Might Be Something Else -Case in Point

R Paknikar et al. NEJM 2023; 389: 1321-1326. Digging into the Histology

In this case report, a 33-year-old man (from the midwest) with ulcerative colitis (diagnosis seven years prior) who was receiving treatment with tofacitinib (a Janus kinase inhibitor) presented to the hospital with fatigue (x 8 months) and bloody diarrhea. He also had had fevers (x 4 months), 23 lb weight loss, and drenching night sweats. Before tofacitinib, treatment had included adalimumab and azathioprine. He had undergone a sigmoidoscopy two months prior to presentation.

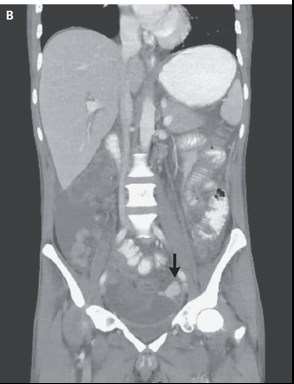
His workup included a CXR showing diffuse reticulonodular opacities, a CT scan showing thickening in the colon and extensive infection workup. On the third hospital day, he had a perforation and resection which led to the diagnosis of invasive histoplasmosis.

My take: This article is useful for understanding how to workup secondary infections in IBD patients on long-term immunosuppressive agents.

One example: “testing for 1,3-β-d-glucan can serve as an adjunctive test for invasive fungal infections caused by fungi expressing 1,3-β-d-glucan in their cell walls, including candida, aspergillus, Pneumocystis jirovecii, Histoplasma capsulatum, and coccidioides; such testing has a high negative predictive value for infection with these organisms. In contrast, cryptococcus and blastomyces produce very low levels of 1,3-β-d-glucan in their cell walls and are therefore not readily detected by serum testing for the cell-wall antigen.”

CT showed  shows diffuse wall thickening in the rectosigmoid colon and extravasation of extraluminal contrast material (arrow) into the area adjacent to the sigmoid colon, with layering of the contrast material, findings that are thought to indicate a perforation.

Related blog posts:

The Quality of Evidence for Dietary Treatments in Inflammatory Bowel Disease

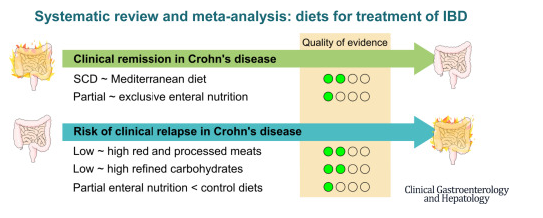
BN Limketkai et al. Clin Gastroenterol Hepatol 2023; 21: 2508-2525. Open Access! Dietary Interventions for the Treatment of Inflammatory Bowel Diseases: An Updated Systematic Review and Meta-analysis

This was a systematic review of prospective controlled trials (n=27) of solid food diets for the induction or maintenance of remission in IBD.

Key findings:

  • For induction of remission in Crohn’s disease (CD), the Mediterranean diet was similar to the Specific Carbohydrate Diet (low certainty of evidence), and partial enteral nutrition (PEN) was similar to exclusive enteral nutrition (very low certainty of evidence).
  • PEN reduced risk of relapse (very low certainty of evidence), whereas reduction of red meat or refined carbohydrates did not (low certainty of evidence).
  • For ulcerative colitis, diets were similar to controls (very low and low certainty of evidence).

My take: Most of the dietary treatments for IBD have low to very low certainty of evidence regarding their effectiveness. Dietary changes are very likely to be helpful but more studies with rigorous endpoints are still needed.

Related blog posts:

Risk Factors for Inflammatory Bowel Disease: Antibiotics (Part 2)

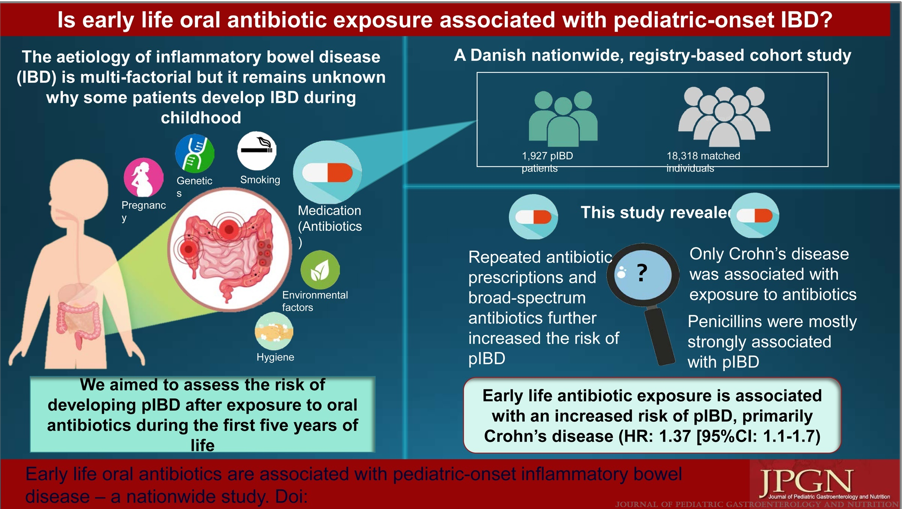
AB Jawad et al. JPGN 2023; 77: 366-372.Early Life Oral Antibiotics Are Associated With Pediatric-Onset Inflammatory Bowel Disease-A Nationwide Study

Key findings:

  • Oral antibiotic exposure during the first 5 years of life was associated with a higher risk of developing pIBD (HR = 1.33,  P <0.0001). The risk was also increased if patients had ≥4 antibiotic prescriptions compared to no antibiotics (HR = 1.33, P <0.0001).
  • Broad-spectrum antibiotics increased the risk of pIBD compared to narrow-spectrum antibiotics (HR = 1.29, P < 0.0001).
  • When stratified by IBD subtypes, only Crohn disease was significantly associated with exposure to antibiotics (HR = 1.37, P = 0.002).

My take: This study indicates that antibiotics (and/or serious infections) are associated with an increased the risk of pediatric Crohn’s disease but the absolute risk is very low. We still have a lot to learn about how environmental exposures, including diet, infections, antibiotics, and pollution, contribute to the increasing prevalence of inflammatory bowel disease.

Related blog posts:

Risk Factors for Inflammatory Bowel Disease: Ultra-Processed Food (Part 1)

N Narula et al. Clin Gastroenterol Hepatol 2023; 21: 2483-2495. Open Access! Food Processing and Risk of Inflammatory Bowel Disease: A Systematic Review and Meta-Analysis

JA Fitzpatrick et al. Clin Gastroenterol Hepatol 2023; 21: 2478-2480 (editorial). Open Access! Ultra-processed Foods and Risk of Crohn’s Disease: How Much is Too Much?

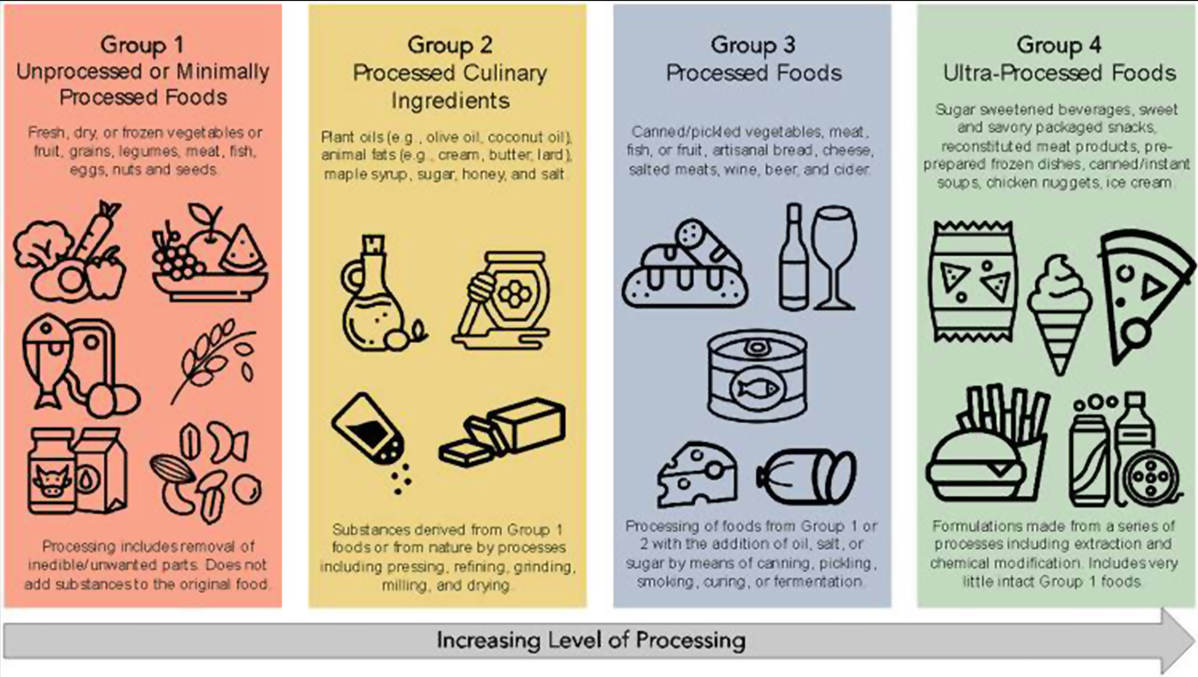
Figure 1 from editorial: The NOVA classification of food

A total of 1,068,425 participants were included (13,594,422 person-years) among 5 cohort studies published between 2020 and 2022. The average age of participants ranged from 43 to 56 years. Key findings:

  • Crohn’s disease:  During follow-up, 916 participants developed CD, and 1934 developed UC. There was an increased risk for development of CD for participants with higher consumption of ultra-processed foods compared with those with lower consumption (HR, 1.71; 95% CI, 1.37–2.14; I2 = 0%) and a lower risk of CD for participants with higher consumption of unprocessed/minimally processed foods compared with those with lower consumption (HR, 0.71; 95% CI, 0.53–0.94; I2 = 11%). 
  • Ulcerative colitis: There was no significant association between risk of UC and ultra-processed foods (HR, 1.17; 95% CI, 0.86–1.61; I2 = 74%) or unprocessed/minimally processed foods (HR, 0.84; 95% CI, 0.68–1.02; I2 = 0%).

The associated editorial by Fitzpatrick et al, notes that “there are plausible mechanisms that explain the associations of higher UPFs and development of CD, such as: (1) displacing the intake of minimally processed foods and subsequently reducing exposure to beneficial micronutrients, antioxidants, and phytochemicals; (2) driving overconsumption of total calories7; and (3) increasing exposure to non-nutritive food substances that have been implicated in the development of CD in pre-clinical studies…The notion is that a lower UPF intake is better, but a cutoff value remains elusive.”8

My take (borrowed from editorial): “the population studies have indicated that the extremes of UPF intake are related to risk of CD and that such associations are underpinned by plausible biological mechanisms, suggesting causality.”

Related blog posts: