Mortality Risk from Childhood Inflammatory Bowel Disease

A recent study (O Olen et al. Gastroenterol 2019; 156: 614-22) was summarized quite succinctly by NEJM journal watch:

Using the Swedish National Patient Registry data, investigators identified 9442 incident cases of IBD diagnosed in patients under age 18 years from 1964 through 2014. Based on 139,000 person-years of follow-up, results were as follows:

  • There were 259 deaths among people with IBD (133 were from cancer and 54 from digestive disease).
  • The all-cause mortality rate in these patients was 2.1/1000 person-years, compared with 0.7 in matched reference individuals from the general population.
  • The average age at death was 61.7 compared with 63.9 years in the reference group.
  • The hazard ratio for death was 3.2 and was higher in those with ulcerative colitis (HR, 4.0), especially if they had concomitant primary sclerosing cholangitis (HR, 12.2), a first-degree relative with ulcerative colitis (HR, 8.3), or a history of surgery (HR, 4.6).
  • Mortality risks were similar when limited to the period after the introduction of biologics (2002–2014).

My take: This study found that having IBD diagnosed in childhood increased the risk of mortality (~1 extra death for every 700 patients followed for 1 year) especially in patients with concomitant PSC and in patients with severe ulcerative colitis.  The study did not see an effect of the newest therapies but was underpowered to directly assess this effect.

Related blog post:


Chattahoochee River, near Azalea Drive

 

Safety of Senna-Based Laxatives

A recent study  (Vilanova-Sanchez A, et al. J Pediatr Surg 2018; 53: 722-7) provides reassurance regarding the safety of senna-based laxatives in kids.

The authors performed a literature review and reviewed their personal experience (2014 to 2017) of prescribing Senna in 640 patients. In this cohort, 230 (36%) had functional constipation.

Key findings:

  • Besides abdominal cramping or diarrhea during the first weeks of administration, there were no other long-term side effects from Senna found in the pediatric literature with long-term treatment
  • At their institution, 83 (13%) patients presented minor side effects such as abdominal cramping, vomiting or diarrhea, almost half (48%) of which resolved spontaneously within two weeks.
  • “We did not see any side effects in 540 (84.3%) patients.”  The median length of treatment was 338 days and median dose was 17.5 mg.  “430 (80%) of them are currently taking Senna.”
  • 17 patients (2.2%) developed blisters during their treatment. Patients who developed blisters had higher doses 60 mg/day; 60 [12–100] vs. 17.5 [1.7–150] (p < 0.001). All of the blistering episodes were related to night-time accidents, with a long period of stool to skin contact.

In their discussion, the authors note that senna and other anthranoid glycosides are not absorbed in the small intestine.  They are maintained as prodrugs until they reach the large intestine where they are metabolized to the active form. In addition, “despite an extensive search of both the medical and lay literature we did not find any reference to long term tolerance due to treatment which we find is a frequently mentioned concern by families and clinicians”

The authors comments on the study from Nationwide Children’s Hospital website:

  • “The safety profile of senna is as good as or better than many common medications a person would be on, including over-the-counter medications routinely given to very young children, and tolerance does not appear to be a concern,” says Dr. Levitt, who is also a professor of Surgery at The Ohio State University College of Medicine. “We hope this paper will make physicians more comfortable in using senna-based laxatives, and that they will be more widely used.”
  • Senna is often more effective than polyethylene glycol. This study shows that it is safe as well.  “A physician should consider senna as the first line medication,” says Dr. Levitt.

My take: Many patients who come to pediatric gastroenterologists have not responded to polyethylene glycol.  Senna has been effective in many of these patients as part of a bowel regimen which usually includes behavior modification and diet.

Related blog posts:

Pictures from Joshua Tree National Park

NY Times: The Battle Over Fecal Transplantation

NY Times: Drug Companies and Doctors Battle Over the Future of Fecal Transplants

This article highlights a concern that pharmaceutical companies may persuade the FDA to regulate fecal transplants similar to medications.  This will exponentially increase the cost and limit the access to beneficial human excrement. Thanks to one of my sons for pointing out this commentary to me.

An excerpt:

As pharmaceutical companies seek to profit from the curative wonders of human feces, doctors worry about new regulations, higher prices and patients attempting DIY cures…

The clash is over the future of fecal microbiota transplants, or F.M.T., a revolutionary treatment that has proved remarkably effective in treating Clostridioides difficile, a debilitating bacterial infection that strikes 500,000 Americans a year and kills 30,000…

At the heart of the controversy is a question of classification: Are the fecal microbiota that cure C. diff a drug, or are they more akin to organs, tissues and blood products that are transferred from the healthy to treat the sick? The answer will determine how the Food and Drug Administration regulates the procedure, how much it costs and who gets to profit…

Human feces, it turns out, are a potential gold mine, for both medical researchers and drug makers…

Inspired by the success of fecal transplants for C. diff, scientists are racing to develop similar treatments for an array of ailments and disorders, among them obesity, autism, ulcerative colitis, and Alzheimer’s and Parkinson’s diseases…

For now, most of the material used in fecal transplants comes from OpenBiome, the public stool bank in Cambridge …The material comes from donors who earn $40 a pop and must pass intensive screenings and regular medical checkups. “It’s harder to become a stool donor than it is to get into M.I.T.,” said Carolyn Edelstein, who runs the organization…The F.D.A. has ramped up oversight of OpenBiome’s production, leading to more rigorous testing and higher prices, which will double to $1,600 this month.

Related blog posts:

From NY Times Twitter Feed

IBD Update March 2019

Briefly noted:

W El-Matary et al. Inflamm Bowel Dis 2019; 25: 150-5. This retrospective study of 667 children with Crohn’s disease who were prospectively enrolled in an inception study found that 85 (12.7%) had fistulizing perianal disease. The mean infliximab (pre-fourth dose) was 12.7 mcg/mL in responders compared with 5.4 mcg/mL in the active disease group.  My take: Higher trough levels are desirable in those with fistulizing disease.

LJT Smits et al. Inflamm Bowel Dis 2019; 25: 172-9. In a  prospective cohort with 83 patients with IBD (57 with Crohn’s disease) with at least 2 years of followup, 66% of IBD patients continued CT-P13 after switching from Remicade; two patients developed anti-drug antibodies.  The absolute numbers suggest no adverse impact of a single switch to the biosimilar product.

Related blog posts:

A Tinsley et al. Inflamm Bowel Dis 2019; 25: 369-76. This study documents the increased risk of influenza and increased influenza complications among IBD patients based on a database cohort of 140,480 patients (with and without IBD). The risk of hospitalization was 5.4% in patients with IBD compared with 1.85% in non-IBD patients.

Related blog post: Almost Everybody Needs Flu Shot -IBD Patients at Higher Risk

YY Xu et al. Inflamm Bowel Dis 2019; 25: 261-9. This meta-analysis included 18 nonrandomized controlled trial studies with 1407 patients who received preoperative infliximab and 4589 patients.  The authors showed that preoperative infliximab was not associated with any statistically significant differences for the 2 groups for any complications, reoperation, readmission or mortality.

CN Bernstein et al. Inflamm Bowel Dis 2019; 25: 360-8. This study, using population-based administrative health data (Manitoba) found increased burden of psychiatric disorders in IBD: compared with controls the incidence rate ratio for depression was 1.58, for anxiety 1.39, for bipolar disorder 1.82, and for schizophrenia 1.64.

Related blog post: #NASPGHAN17 Psychosocial Problems in Adolescents with IBD

View from Ryan Mountain, Joshua Tree National Park

More Cases of Hepatocellular Carcinoma after Fontan

Several years ago, there were 4 cases of hepatocellular carcinoma (HCC) following Fontan procedure reported in the NEJM. (Reviewed in this blog: Hepatocellular carcinoma after Fontan Procedure).

Another recent report describes 3 patients who presented with HCC more than 10 years after Fontan procedure.  The age of these patients varied from 20 to 28 years. The authors use the term Fontan-Associated Liver Disease (FALD).  They note that FALD is strongly associated with the interval from the procedure, increasing in frequency with more time following surgery.  The risk of FALD is 4.4 times greater between years 11-15 years than in the first 10 years.

The authors recommend screening for HCC in patients 10 years after Fontan procedure. They suggest a baseline MRI followed by biannual ultrasounds and alpha-fetoprotein tests.

Related blog posts:

Warren Peak, Joshua Trree National Park

Teaching an Old Liver New Tricks

A recent retrospective study (JD de Boer et al. Liver Transplantation 2019; 25: 260-74) helps address the question of whether/when a geriatric liver is too old for donation.

The authors culled data from 2000-2015 from 17,811 first liver transplantations performed in the Eurotranplant region.

Key findings:

  • 2394 (13%) transplants were performed with livers ≥70 years old
  • Graft survival was reduced from donors with a history of diabetes (HR 1.3) and in recipients with hepatitis C virus (HCV) antibody (HR 1.5)
  • “Although donor age is associated with a linearly increasing risk of graft loss between 25 and 80 years old, no differences in graft survival could be observed when “preferred” recipients were transplanted” with older grafts (HR 1.1).
  • Preferred recipients: 1. HCV-Ab neg, 2. Recipient >45 years old, 3. BMI <35 kg/m2, 4. cold ischemia time < 8 hours. 26% of recipients were considered “preferred” recipients
  • Utilization of livers from donors ≥70 years old increased from 42% (2000-2003) to 76% (2013-2015).
  • The median donor age increased from 42 to 55 years old from 2000 to 2015.
  • The oldest transplanted liver was 98 years old!

The overall Kaplan-Meier survival curves are given in Figure 2 and there is a clear trend of better graft and patient survival with donors <70 years of age.  However, Figure 4 shows that graft survival with “preferred” recipients was essentially identical when comparing grafts from donors <70 compared to >70.  However, when comparing graft survival from donors <40 compared to donors >70, there appeared to be a small advantage for the younger organs, though this did not meet statistical significance. (HR 1.2 CI 0.96-1.37).

My take: Given the shortage of available livers, the use of older donor organs is a necessity and can be accomplished without significant loss of grafts in selected patients.

Related blog posts:

Joshua Tree National Park


NY Times: Five Things I Wish I’d Known Before My Chronic Illness

A recent article describes some of the challenges of dealing with Crohn’s disease (thanks to Kayla Lewis for pointing out this reference).

NY Times: Five Things I Wish I’d Known Before My Chronic Illness

Key Points:

  • “Your relationships change” “It’s hard to be a good employee when you need extended time off. It’s hard to be a good friend when you cancel plans last minute. It’s hard to be a good partner or parent when you barely have the energy to get out of bed. “
  • “Everyone offers you advice” “So unless someone asks for your advice, don’t offer it. If you’re on the receiving end of misguided advice, say something like, “I appreciate that you’re trying to help, but my doctors and I think this treatment is best right now” or “There’s no known cure for my disease, but I’d love if you donated toward the research to find one!”
  • “You have to educate yourself — and everyone else“
  • “Support is everything”  Online communities can be helpful. ” The Crohn’s and Colitis Foundation has resources to help you find one. For a sometimes embarrassing “bathroom disease” like IBD, this is especially vital.”

Joshua Tree National Park

Economic Costs of Gluten Free Diet

A recent study (AR Lee et al. Nutrients; 2019, 11, 399). Open access: Persistent Economic Burden of the Gluten Free Diet) quantifies the additional costs of a gluten free diet (GFD) in the U.S. Thanks to Kipp Ellsworth for this reference.

The authors conducted a “market basket” study to establish the cost of a GFD. “A market basket is a group of products that are purchased by consumers …for this study, the market basket was food that would necessitate a GF substitute, including staple foods, snack foods, and commonly used ready-made or convenience meals.”

Key findings:

  • GF products were more expensive, overall the increase was 183%.  This is an improvement from a 2006 study which found the increase overall at 240% (adjusted for inflation).
  • Mass-market products were 139%  more expensive than wheat-based versions

Discussion:

  • Cost is identified as a frequent reason for nonadherence with diet, cited by 33% in one study
  • Overall, the burden of GFD is more frequently related to the restrictive nature of the diet which leads to a negative impact on quality of life. According to the authors, in one study (Am J Gastroenterol 2014; 109: 1304-11), treatment burden for celiac was ranked higher than for diabetes hypertension, and congestive heart failure

My take: This study shows the significant economic burden of a GFD.  In Italy, the  “government offers celiac patients vouchers to buy gluten-free food — up to 140 euros per month.” (NPR: Italy, Land of Pizza and Pasta)

Related blog posts:


FDA’s Very Limited Ability to Regulate Dietary Supplements

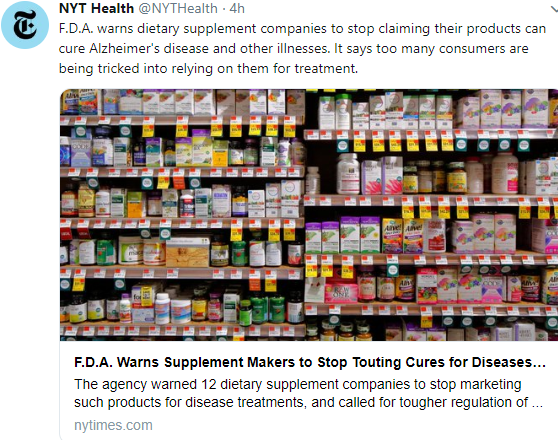
NY Times: Supplement Makers Touting Cures for Alzheimer’s and Other Diseases Get F.D.A. Warning

An excerpt:

The Food and Drug Administration on Monday warned 12 sellers of dietary supplements to stop claiming their products can cure diseases ranging from Alzheimer’s to cancer to diabetes.

At the same time, Dr. Scott Gottlieb, the agency’s commissioner, suggested that Congress strengthen the F.D.A.’s authority over an estimated $40 billion industry, which sells as many as 80,000 kinds of powders and pills with little federal scrutiny…

The F.D.A.’s oversight is based on a 1994 federal law, which imposed minimal reporting and labeling requirements on the makers of vitamins, minerals and herbs — a fledgling industry at the time. To prevent a company from selling a product, the law requires the F.D.A. to prove that it is unsafe…

There are now between 50,000 and 80,000 dietary supplements on the market, according to the F.D.A. The agency also says that three of every four American consumers now take a dietary supplement regularly.

Related blog posts: