Encouraging Safety Data for Ustekinumab & ESPGHAN Obesity Position Paper

WJ Sandborn et al. Inflamm Bowel Dis 2021; 27: 994-1007. Full text: Safety of Ustekinumab in Inflammatory Bowel Disease: Pooled Safety Analysis of Results from Phase 2/3 Studies

Methods: Data from 6 ustekinumab phase 2/3 CD and UC studies were pooled, and safety was evaluated through 1 year; this included 2574 patients (1733 patient-years of follow-up)

Key Safety findings –Events per 100 patient years -placebo vs ustekinumab respectively:

  • Adverse events: 165.99 [95% CI, 155.81–176.67] vs 118.32 [95% CI, 113.25–123.55])
  • Serious AEs: 27.50 [95% CI, 23.45–32.04] vs 21.23 [95% CI, 19.12–23.51])
  • Infections 80.31 [95% CI, 73.28–87.84] vs 64.32 [95% CI, 60.60–68.21])
  • Serious infections: 5.53 [95% CI, 3.81–7.77] vs 5.02 [95% CI, 4.02–6.19])
  • Malignancies excluding nonmelanoma skin cancer: 0.17 [95% CI, 0.00–0.93] vs 0.40 [95% CI, 0.16–0.83])
  • Major cardiovascular events were rare with 2 in placebo group 0.34 and 2 in the ustekinumab group 0.12

More key findings:

  • No cases of progressive multifocal leukoencephalopathy or reversible posterior leukoencephalopathy
  • Antibodies to ustekinumab were identified in 3.6% of patients

My take: This study showed similar safety between ustekinumab and placebo, but is limited by short followup. The authors note that 5-year data from ustekinumab’s use with psoriasis has found no safety signals for malignancy.

Related blog posts:

Unrelated article: E Verduci et al. JPGN 2021; 72: 769-783: Full text: Role of Dietary Factors, Food Habits, and Lifestyle in Childhood Obesity Development: A Position Paper From the European Society for Paediatric Gastroenterology, Hepatology and Nutrition Committee on Nutrition
Why I Didn’t Like a Study on Resilience Plus One

P Sehgal et al. Inflamm Bowel Dis 2021; 27: 791-796. High Levels of Psychological Resilience Associated With Less Disease Activity, Better Quality of Life, and Fewer Surgeries in Inflammatory Bowel Disease

This cross-sectional study with 229 patients examined the relationship between inflammatory bowel disease (IBD) activity and resilience based on the Connor-Davidson Resilience Scale questionnaire (high resilience score ≥ 35).

Key findings:

  • High resilience was noted in 27% of patients with UC and 21.5% of patients with CD.
  • Among patients with UC, those with high resilience had a mean Mayo score of 1.54, and those with low resilience had a mean Mayo score of 4.31, P < 0.001.
  • Among patients with CD, those with high resilience had a mean HBI of 2.31, and those with low resilience had a mean HBI of 3.95, P = 0.035.
  • In multivariable analysis, high resilience was independently associated with lower disease activity in both UC (P < 0.001) and CD (P = 0.037) and with higher QoL (P = 0.016).
  • High resilience was also associated with fewer surgeries (P = 0.001) among patients with CD.

Reading this study, made me think of Galen’s assertion about a different treatment, circa 100 AD:   “All who drink of this remedy recover in a short time except those whom it does not help, who all die. It is obvious, therefore, that it fails only in incurable cases.” In the case of this study, the remedy is resiliency.

This study is intriguing and adds to the literature that mental health and IBD may be a two-way street: mental health may affect IBD and IBD activity may affect mental health. However, it is difficult to prove causation in a cross-sectional study. Reverse causation is possible; that is higher disease burden may result in lower resilience.

Also, it is not clear to me that resilience is a particularly modifiable factor. Some may interpret this study in a ‘blame the victim’ mode. I think a lot of individuals would think they are resilient but most do not know until they face a difficult situation. Perhaps, Mike Tyson’s assertion is more apt: “Everyone has a plan until they get punched in the mouth.”

My take: This study does not prove that resilience helps prevent IBD activity, though being resilient is nice if you have it.

Plus one: JR Rosh et al. J Crohns Colitis. 2021 May 26; jjab089. doi: 10.1093/ecco-jcc/jjab089. (EPUB). Ustekinumab in Pediatric Patients with Moderately to Severely Active Crohn’s Disease Pharmacokinetics, Safety, and Efficacy Results from UniStar, a Phase 1 Study This was a “multicentre, 16-week, double-blind induction dose-ranging study (NCT02968108), patients aged 2-<18 years; patients were randomized (1:1) to one of 2 weight range-based intravenous induction doses: 130mg vs 390mg in patients ≥40kg and 3mg/kg vs 9mg/kg in patients <40kg. At week 8, all patients received a single subcutaneous ustekinumab maintenance dose of 90mg in patients ≥40kg or 2mg/kg in patients <40kg..” (Kudos to my partner, Stanley Cohen, one of the authors)

Key finding:  Pharmacokinetics were similar to those in adults with Crohn’s disease. However, serum ustekinumab concentrations were lower among those with body weight <40kg…These results suggest a different dosing regimen may be required for patients <40kg

Related blog posts:

Image below from Anne’s Beach (Lower Matecumbe Key, Florida)

Steroids for Some with Short Gut, Poor Agreement on Endoscopy Findings, and Ending Surprise Bills

Briefly noted:

  1. F Wang et al JPGN 2021; 73: 17-22. Glucocorticoids Improve Enteral Feeding Tolerance in Pediatric Short Bowel Syndrome With Chronic Intestinal Inflammation In this retrospective study with 15 patients who had histologically-confirmed chronic intestinal inflammation, glucocorticoids (budesonide or prednisone) were associated with clinical improvement. Key findings: 7 of the 15 patients gained enteral autonomy. 6 of 7 of those had eosinophilic infiltrates as part of their histologic findings. 11 of 15 had a reduction in parenteral calories.
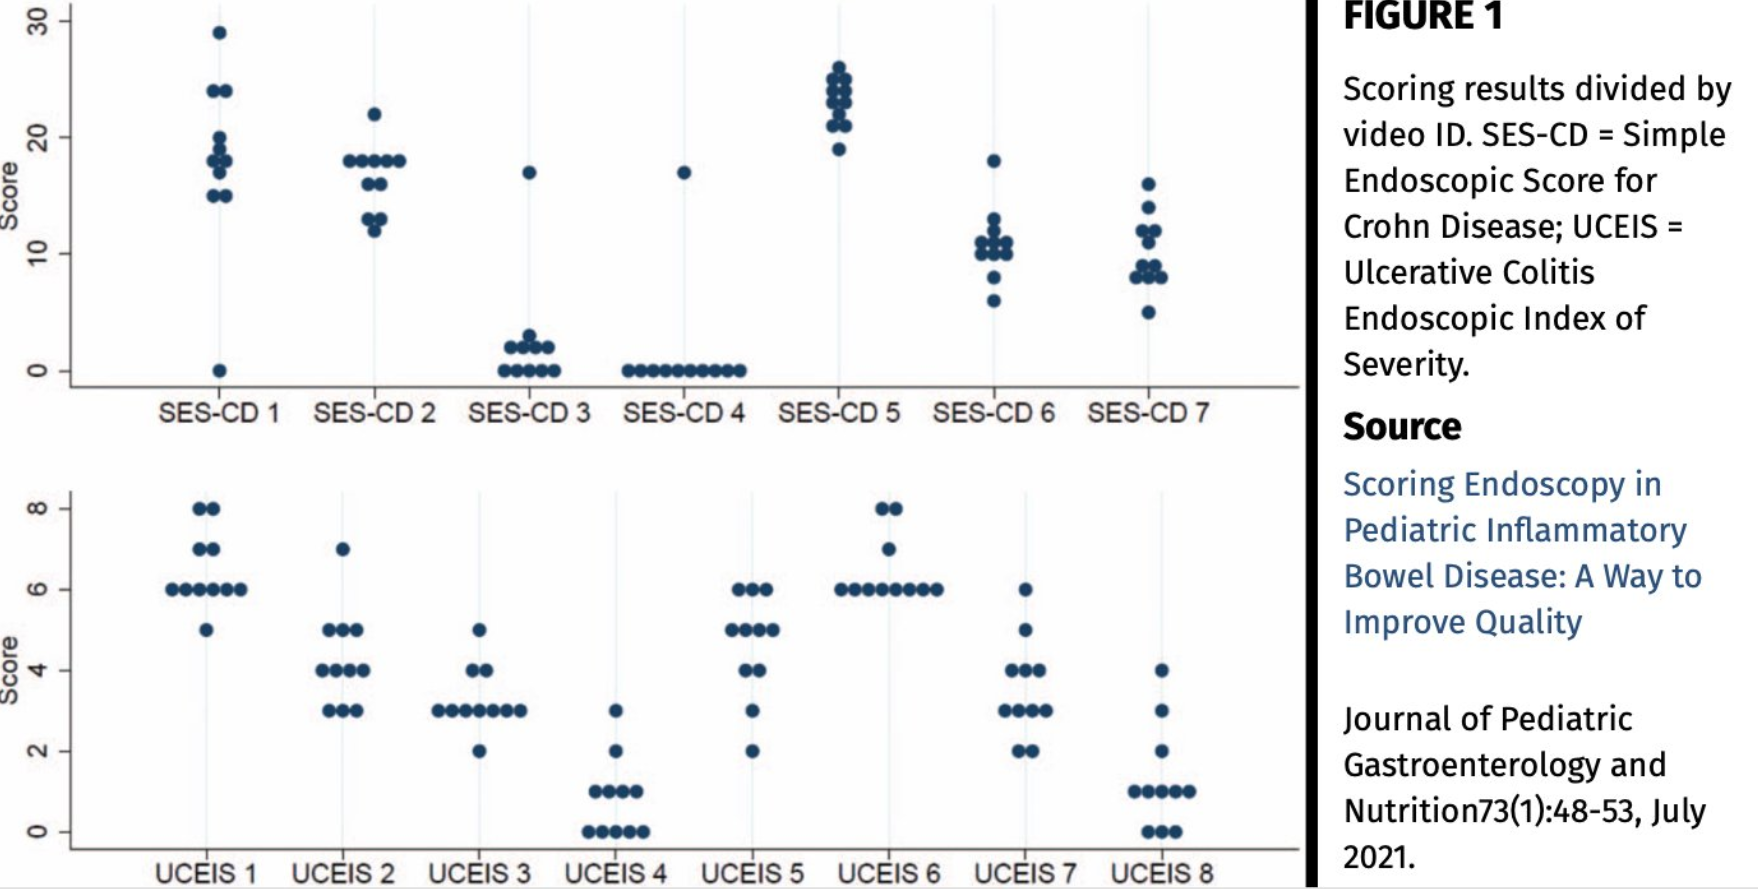
  2. L Norsa et al JPGN 2021; 73: 48-53. Scoring Endoscopy in Pediatric Inflammatory Bowel Disease: A Way to Improve Quality This study showed very poor agreement between 11 pediatric GIs in evaluating videos of 15 endoscopies (see below). Key finding: Intraclass correlation was 0.298 (95% confidence interval [CI]: 0.13–0.55) for ulcerative colitis (UC) and 0.266 (0.11–0.52) for Crohn disease (CD). My take: This study indicates either a need for rigorous training of endoscopists and/or need for AI review of endoscopy.
  3. NY Times 7/2/21: Full text: For Surprise Medical Bills, It’s the Beginning of the End Key issues for regulators: define a standard price for out-of-network care, determine what hospitals and doctors will need to do to notify patients they are not in their insurance network, and establish a complaint system for consumers who believe they were illegally billed.

Related blog posts:

From JGPN twitter feed

Pediatric Adoption of “Treat to Target” & Difficulty “Unlearning”

A good article for the next journal club: Clinical Practice Survey of Repeat Endoscopy in Pediatric Inflammatory Bowel Disease in North America (J Moses et al. JPGN 2021; 73: 61-66)

Key findings:

  • 65% of respondents (n=238 of 2300 responded to survey) perform repeat endoscopy to assess for endoscopic remission in pediatric IBD as part of routine clinical practice (usually 9 to 12 months later)
  • “Symptoms are not sufficient to follow IBD patients” was reported by 82% of those who repeat endoscopy
  • “I perform endoscopy based on clinical, biomarker, and/or imaging trends” was reported by 81% of those who do not repeat endoscopy
  • In those inclined to do repeat endoscopy (n=134 total), the authors state there was a significant difference based on years in practice but this is difficult to discern based on the data presented in Table 1; the numbers in both groups are much greater than the number of total patients in each group. They state in the repeat endoscopy group (n=134), the practitioner experience was n=58 (1-5 yrs), n=43 (6-10 yrs), n= 34 (11-15 yrs), and 70 (>15 yrs) and the “no repeat group” (n=67 total) was n=43 (1-5 yrs), n=33 (6-10 yrs), n=21 (11-15 yrs), and n=37 (>15 yrs). Apparently, according to the discussion, those in practice more than 15 years were less likely to recommend a ‘treat-to-target’ endoscopy.
  • There is also a discrepancy in the report with regard to ImproveCareNow participation, stated to be 63% in the abstract and 71% in the results section

Discussion: I would propose that the first part of a journal club start with these two lines from the discussion: “As the paradigm of clinical endpoints has evolved in the management of IBD, there has been a shift from using clinical symptoms to drive major therapeutic decisions to using endoscopic assessment. This lag time to adopt new practices in medicine has been highlighted in research demonstrating the slow adoption of new clinical practices by physicians, possibly related to the difficulty with “unlearning” common practices and shifting to new ones.” As an aside, 77% of the survey respondents were in an academic practice; it would be fun to see how the section chief views this assertion.

While the majority of survey respondents supported repeat endoscopy in all patients, the discussion point above is making a different distinction (“drive major therapeutic decisions”). I think a much higher proportion of practitioners would endorse endoscopy prior to major therapeutic decisions. However, with regard to supporting more widespread routine followup in all of those in clinical remission, the discussion references data from a single retrospective pediatric cohort study with 104 patients (Inflamm Bowel Dis 2017; 23: 1447-1453), that 30% of patients in clinical remission had active disease on endoscopy.

My take: As alluded to in the conclusion, long-term data from prospective studies are needed to determine the benefit (or lack of benefit) of followup endoscopy, especially in patients with combined clinical/biomarker remission.

Related blog posts:

Radiomic Imaging in Crohn’s Disease

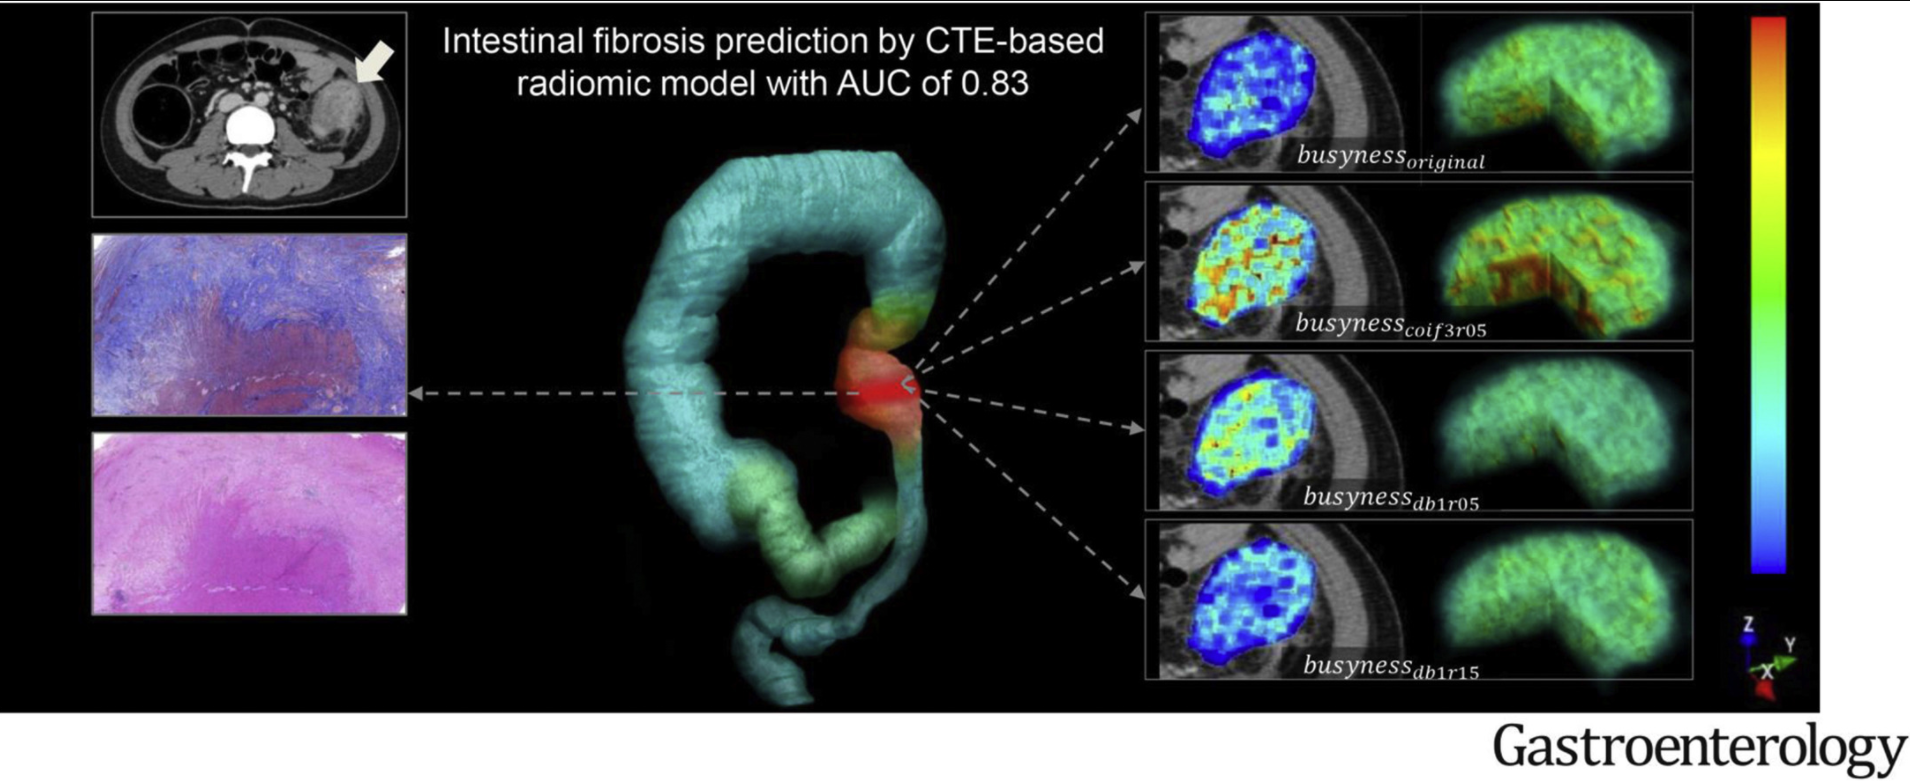
X Li et al. Gastroenterol 2021; 160: 2303-2316. Development and Validation of a Novel Computed-Tomography Enterography Radiomic Approach for Characterization of Intestinal Fibrosis in Crohn’s Disease

Methods: This article describes the development a computed-tomography enterography (CTE)–based radiomic model (RM). This retrospective multicenter study included 167 CD patients who underwent preoperative CTE and bowel resection. 1454 radiomic features were extracted from venous-phase CTE and a machine learning–based RM was developed based on the reproducible features using logistic regression. The RM was validated in an independent external test cohort recruited from 3 centers.

Key findings:

  • In the training cohort, the area under the ROC curve (AUC) of RM for distinguishing moderate–severe from none–mild intestinal fibrosis was 0.888.
  • In the test cohort, the RM had an AUC of 0.816.
  • RM was more accurate than visual interpretations by either radiologist (radiologist 1, AUC = 0.554; radiologist 2, AUC = 0.598; both, P < .001) in the test cohort

My take: This CT approach with RM allowed for accurate characterization of intestinal fibrosis in CD. The images look pretty cool too.

SC Option for Infliximab

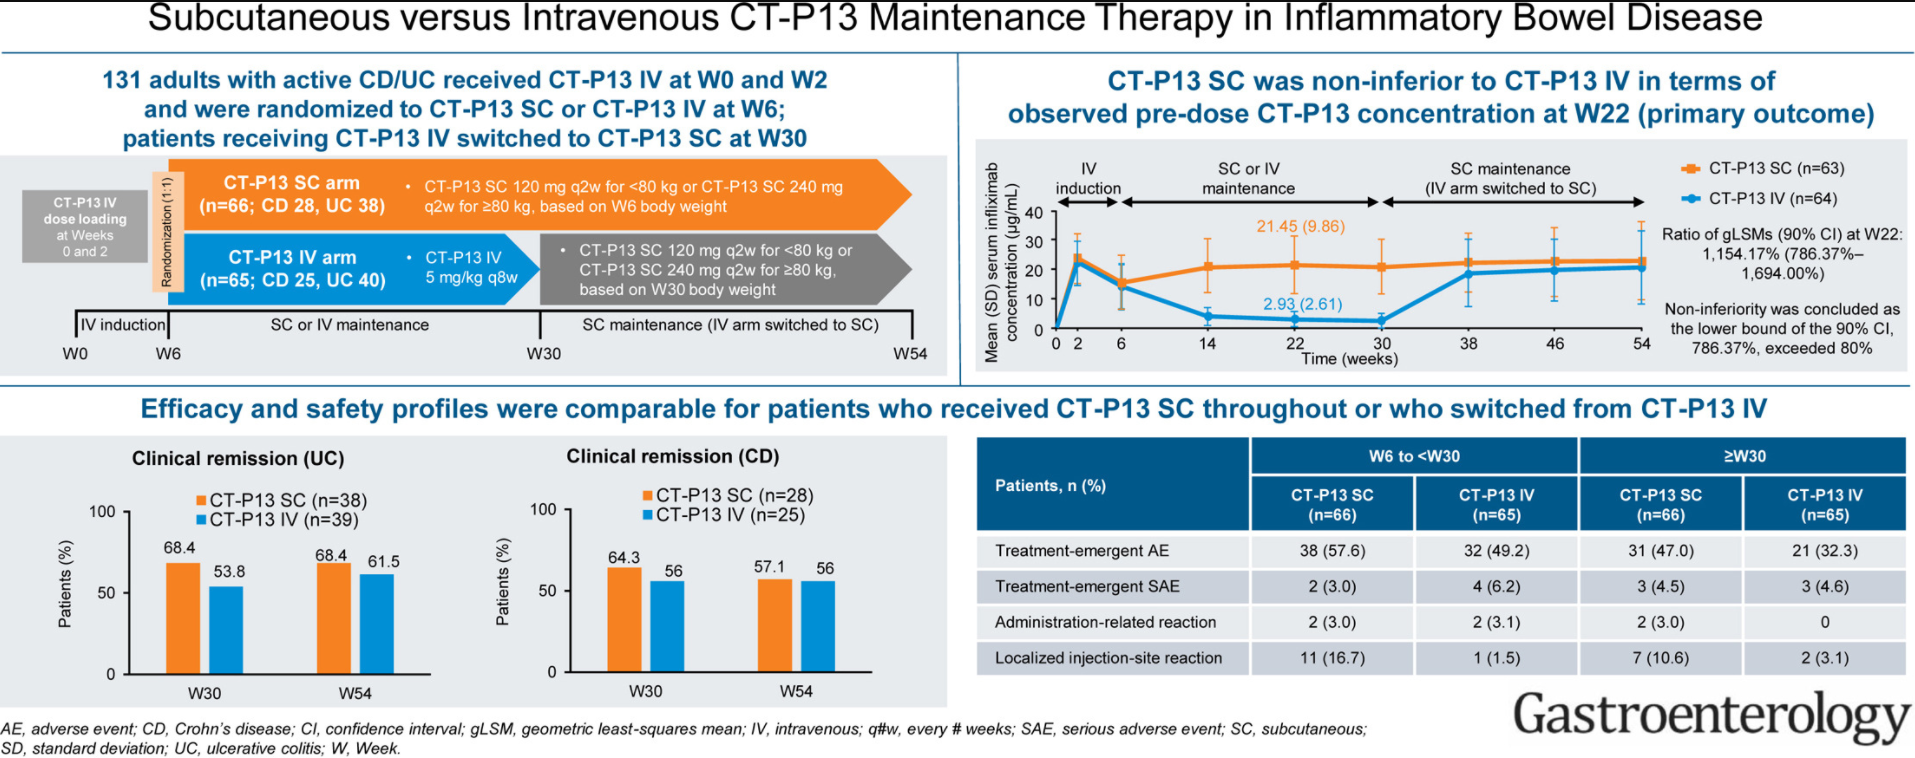
S Schreiber, S Ben-Horin et al. Gastroenterol 2021; 160 2340-2353. Full text: Randomized Controlled Trial: Subcutaneous vs Intravenous Infliximab CT-P13 Maintenance in Inflammatory Bowel Disease

Methods: Overall in this phase 1 randomized, open-label study in patients with either ulcerative colitis or Crohn’s disease, 66 and 65 patients were randomized to CT-P13 SC (every 2 weeks) and CT-P13 IV, respectively

Key findings: The pharmacokinetic noninferiority of CT-P13 SC to CT-P13 IV, and the comparable efficacy, safety, and immunogenicity profiles

These findings are in agreement with similar studies performed in patients with Rheumatoid Arthritis.

My take: If confirmed with additional studies, it is likely that SC infliximab treatment will be a useful alternative to intravenous infliximab. This is similar to data presented with vedolizumab which is currently administered intravenously.

Graphical Abstract

Is Non-Celiac Wheat Sensitivity an Autoimmune Disorder?

A recent study (P Mansueto et al. Am J Gastroenterol 2021; 116: 1015-1023. Autoimmunity Features in Patients With Non-Celiac Wheat Sensitivity). Thanks to Ben Gold for this reference.

The authors prospectively and consecutively studied 91 patients with Non-Celiac Wheat Sensitivity (NCWS) (F?M ratio 7:1); 76 healthy blood donors (HBD) and 55 patients with a diagnosis of irritable bowel syndrome (IBS) unrelated to NCWS served as controls.

NCWS was diagnosed based on absence of celiac serology, absence of villous atrophy (while receiving a gluten-containing diet), negative IgE-testing for wheat allergy (either serum or skin prick tests) along with resolution of symptoms off wheat and symptom reappearance wiht a DBPC wheat challenge.

Key findings:

  • Twenty-three patients with NCWS (25.3%) presented with autoimmune diseases (ADs); autoimmune thyroiditis (16 patients, 17.6%) was the most frequent. The frequency of ADs was higher in patients with NCWS than in HBD (P = 0.002) and in patients with IBS (P = 0.05).
  • In the NCWS group, antinuclear antibodies tested positive in 71.4% vs HBD 19.7%, and vs patients with IBS 21.8% (P < 0.0001 for both).
  • The frequency of extractable nuclear antigen antibody (ENA) positivity was significantly higher in patients with NCWS (21.9%) than in HBD (0%) and patients with IBS (3.6%) (P = 0.0001 and P = 0.004, respectively).
  • Among NCWS with comorbid autoimmunity, duodenal lymphocytosis was present in ~80% and others had eosinophilic infiltration (~90%), both suggestive of ongoing immune activation. (Duodenal eosinophilic infiltration was also noted in ~60% of those who had absence of autoimmune disease too)

The associated editorial by Galipeau et al notes that only 16% of those who self-report as “gluten-sensitive” will actually fulfill the current consensus criteria for a diagnosis of NCWS. The diagnosis is problematic because of the absence of a validated biomarker. While the current study shows association with autoimmune markers, other studies have shown some have markers of immune activation and others with non-IgE-mediated food sensitivities.

My take: These type of studies help us understand NCWS. Yet, without a more definitive biomarker, many people will be on a gluten-free diet needlessly.

Related blog posts:

Dry Tortugas National Park (FL)

Colorectal Cancer: Rare in Pediatrics

A recent retrospective single-center in Turkey study (2013-2018) reports 5 cases of colorectal cancer (CRC).

E Polat et al. JPGN Reports; 2021 – Volume 2 – Issue 1 – p e039 Full text: Colorectal Carcinoma in Childhood

Key points:

  • Patients were between 12-16 yrs of age and presented with bloody stools and weight loss
  • “CRC in childhood is very rare, usually diagnosed at an advanced stage and often has poor prognosis. CRC in children are mostly sporadic, roughly 10% of cases may have a predisposing condition…familial adenomatous polyposis, hereditary nonpolyposis colorectal cancer, Gardner syndrome, Turcot syndrome, Peutz-Jeghers syndrome, juvenile polyposis of colon, and ulcerative colitis.”

Review of Pyoderma Gangrenosum

K Vaidy et al. JPGN Reports 2020; Full text: Treatment of Pyoderma Gangrenosum in Pediatric Inflammatory Bowel Disease

This in-depth report reviews pyoderma gangrenosum including the differential diagnosis, the pathophysiology/genetics, presentation/diagnosis and treatment approaches. Anti-TNF therapy: “Currently available published data support using an anti-TNF-α biologic agent as first-line therapy for severe PG therapy in pediatric IBD, as well as for those cases that have not responded to local therapies.”

Related blog posts -PG:

What Can We Conclude from Five Patients Treated with a Combination of Infliximab and Tofacitinib?

Most often a letter to the editor would not grab my attention. A recent letter did: Full Text: Tofacitinib Is Safe and Effective When Used in Combination With Infliximab for the Management of Refractory Ulcerative Colitis (R Gilmore et al. Clin Gastroenterol Hepatol 2021; 1302-1303; reply 1303-1304 by JA Berinstein et al.)

This reported case series with 5 patients with severe ulcerative colitis (UC) who received a combination of tofacitinib and infliximab for at least 90 days were retrospectively reviewed. Tofacitinib dosing was de-escalated to 5 mg twice daily after 8 weeks. Thiopurine therapy was stopped with tofacitinib initiation.

Key findings:

  • Median duration of combination therapy was 9 months (range, 4–12 months). At 90 days, all patients had a reduction in Mayo score of ≥3. Four patients improved clinically and biochemically (Table 1), with 3 patients achieving steroid-free remission.
  • The only adverse event reported was one patient developing varicella zoster.

The authors letter title regarding tofacitinib being “safe and effective” is clearly overstated. The reply notes that in limited experience the group from the University of Michigan had a 50-year-old man develop severe pulmonary and CNS disease due to acquisition of legionnaires disease while on combination tofacitinib and infliximab.

My take: (borrowed from reply) “Efficacy and safety data obtained through rigorous randomized trials are needed…it is possible that long-term use of combination tofacitinib and infliximab will lead to an unacceptable risk of infection.”

Another study of tofacitinib: GR Lichtenstein et al. Inflamm Bowel Dis 2021; 27: 816-825. Tofacitinib, an Oral Janus Kinase Inhibitor: Analysis of Malignancy (Excluding Nonmelanoma Skin Cancer) Events Across the Ulcerative Colitis Clinical Program Key finding: With an exposure of 2576.4 patient years & 124 overall cohort tofacitinib-treated patients, 20 developed a malignancy

Related blog post:

Key West, FL