Economic Burden of Inflammatory Bowel Disease, Fewer Operations and Emerging Treatments

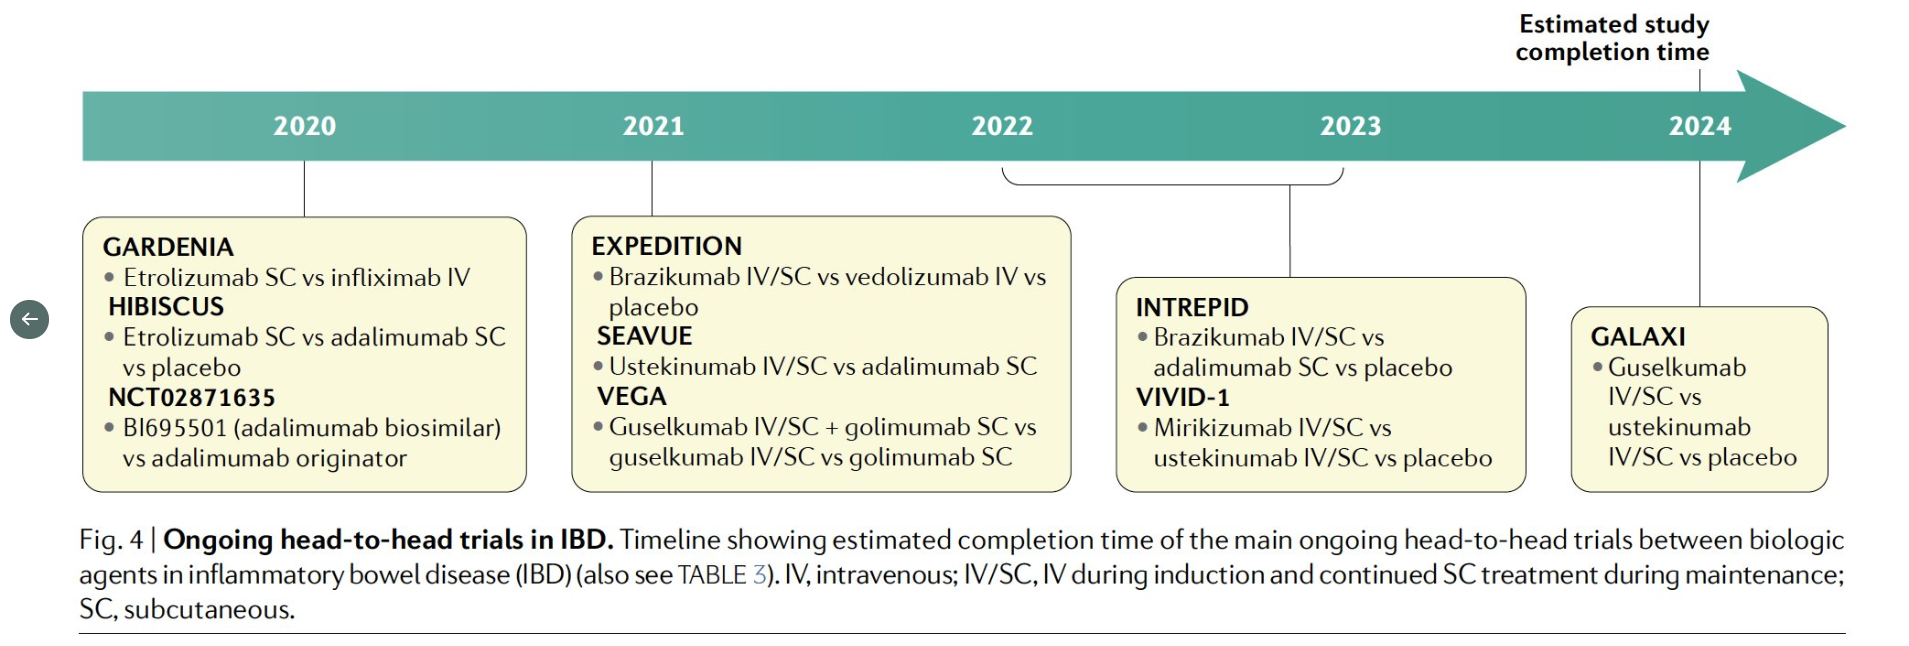
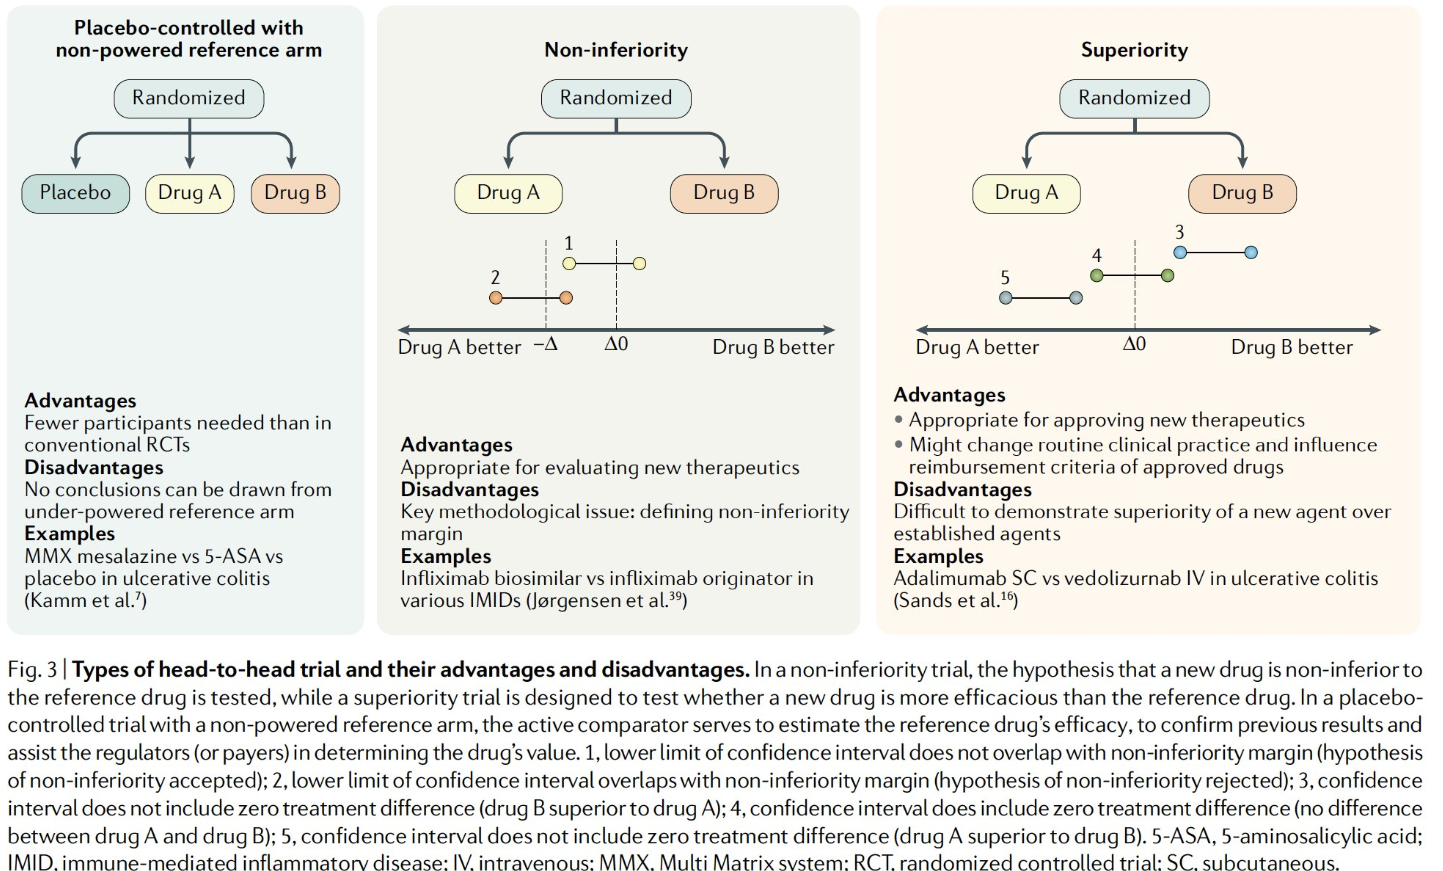
Pouillon, L., Travis, S., Bossuyt, P. et al. Head-to-head trials in inflammatory bowel disease: past, present and future. Nat Rev Gastroenterol Hepatol (2020). https://doi.org/10.1038/s41575-020-0293-9 (Thanks to KT Park for this reference)

An excerpt:

This Perspective provides an overview of the past, current and future concepts in IBD trial design, with a detailed focus on the role of comparative research and the challenges and pitfalls in undertaking and interpreting the results from such studies.
Related blog posts:

GR Lichenstein et al. Clin Gastroenterol Hepatol 2020; 18: 889-97.  Using Truven MarketScan Insurance Claims data (2008-2015) from more than 160,000 patients with inflammatory bowel disease (IBD), the authors estimated economic burdens from Crohn’s disease (CD) and ulcerative colitis (UC).

  • For CD, lifetime incremental cost was $416,352 on average, but was $707,711 if diagnosis was established between 0-11 years of age. The lifetime costs, $622,056, consisted of $273,056 for outpatient care, $164,298 for inpatient care, $163,722 for pharmacy costs, and $20,979 for emergency room care.
  • For UC, lifetime incremental cost averaged $230,102, but was $369,955 if diagnosis was established between 0-11 years of age. The lifetime costs, $405,496, consisted of $153,670 for outpatient care, $123,190 for inpatient care, $105,142 for pharmacy costs, and $13,493 for emergency room care.
  • The lifetime costs for UC and CD were both greater than that for rheumatoid arthritis ($100,273) and for type 2 diabetes ($89,064).
  • Related blog post: IBD Shorts 2020  Cost of IBD Care is Increasing. From Healio Gastro: Chronic inflammatory disease expenditures nearly double over last 2 decades

T Shinagawa et al. Clin Gastroenterol Hepatol 2020; 18: 898-907.  In this study from Japan with 1871 patients with CD, the 5- and 10-year reoperation rates were 23.4% and 48.0% respectively.  However, reoperation rates were significantly lower after 2002 than prior with HR 0.72.  Postoperative use of immunomodulators (OR 0.60) and anti-TNF therapy (HR 0.71) were associated with a reduced the risk of reoperation.
IBD Updates: Depression and Crohn’s Disease, Blood Tests in Pediatric IBD

LW Gaines et al. Inflamm Bowel Dis 2020; 26: 423-8. In this study with 3307 adults with Crohn’s disease (CD) and baseline demographics, CD activity and an affective-cognitive index of depression, the authors used structural equation models to determine the likelihood of whether depression triggers CD activity or whether CD activity triggers depression.  Key findings: “The hypothesis that an affective-cognitive depression predicts patient-reported exacerbation of CD is 218 times more likely to account for the data than the converse.”   (Depression is likely to increase CD activity rather than be due to CD activity).

JJ Ashton et al. Inflamm Bowel Dis 2020; 26: 469-76. Among 256 patients (dx 2013-17) in Southhampton-PIBD database, there were 151 with CD, 95 with UC and 10 IBD-unclassified.  Key findings:

  • 9% presented with all normal blood tests (tests analyzed if available: CRP, ESR, Albumin, platelets, packed cell volume, wbc, ALT)
  • Normal labs were more common with UC compared to CD: 14.4% vs 5.3%

RC Ungaro et al. AP&T; 2020; DOI: 10.1111/apt.15685.  (Thanks to Ben Gold for this reference).  Systematic review with meta-analysis: efficacy and safety of early biologic treatment in adult and paediatric patients with Crohn’s disease. A total of 18 471 patients were studied, with  a median follow-up of 64 weeks (range 10-416). Meta-analysis found that early use of biologics was associated with higher rates of clinical remission (OR 2.10 [95% CI: 1.69-2.60], n = 2763, P < 0.00001), lower relapse rates (OR 0.31 [95% CI: 0.14-0.68], n = 596, P = 0.003) and higher mucosal healing rates (OR 2.37 [95% CI: 1.78-3.16], n = 994, P < 0.00001) compared with late/conventional management. Conclusions: Early biologic treatment is associated with improved clinical outcomes in both adult and paediatric CD patients, not only in prospective clinical trials but also in real-world settings.

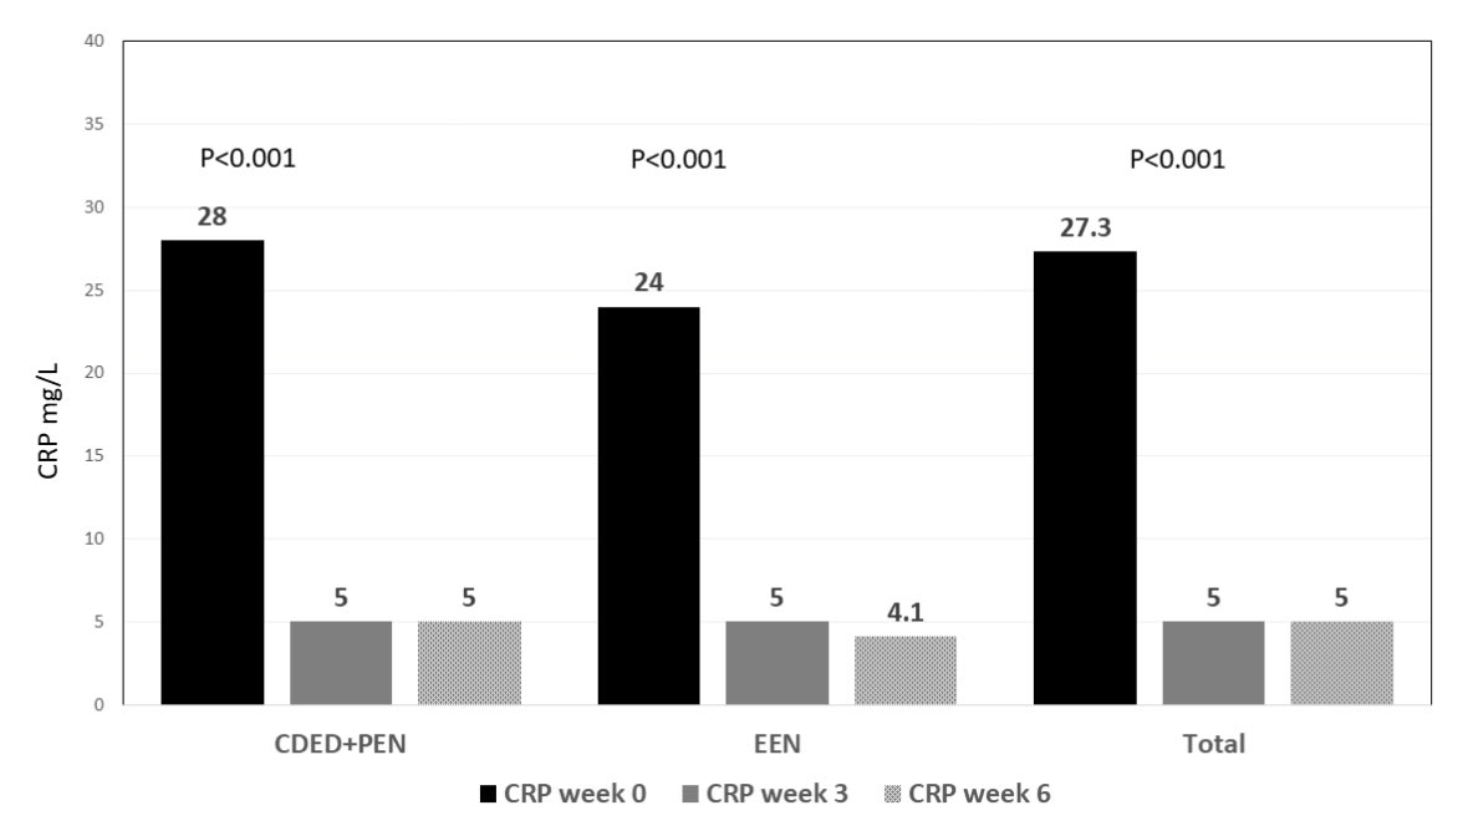
RS Boneh et al. Dietary Therapies Induce Rapid Response and Remission in Pediatric Patients With Active Crohn’s Disease Clin Gastroenterol Hepatol (online April 14, 2020, in press) Thanks to KT Park’s Twitter feed for this reference.

  • Methods: We collected data from the multicenter randomized trial of the CD exclusion diet (CDED). We analyzed data from 73 children with mild to moderate CD (mean age, 14.2±2.7 y) randomly assigned to groups given either exclusive enteral nutrition (EEN, n=34) or the CDED with 50% (partial) enteral nutrition (n=39). Patients were examined at baseline and at weeks 3 and 6 of the diet. Remission was defined as CD activity index scores below 10 and response was defined as a decrease in score of 12.5 points or clinical remission. Inflammation was assessed by measurement of C-reactive protein.
  • Results: At week 3 of the diet, 82% of patients in the CDED group and 85% of patients in the EEN group had a dietary remission (DiRe). Median serum levels of C-reactive protein had decreased from 24 mg/L at baseline to 5.0 mg/L at week 3 (P<.001). Among the 49 patients in remission at week 6, 46 patients (94%) had a DiRe and 81% were in clinical remission by week 3. In multivariable analysis, remission at week 3 increased odds of remission by week 6 (odds ratio, 6.37; 95% CI, 1.6–25; P=.008) whereas poor compliance reduced odds of remission at week 6 (odds ratio, 0.75; 95% CI, 0.012–0.46; P=.006).
  • Conclusions: For pediatric patients with active CD, dietary therapies (CDED and EEN) induce a rapid clinical response (by week 3).

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition


AGA Guidelines: Moderate to Severe Ulcerative Colitis

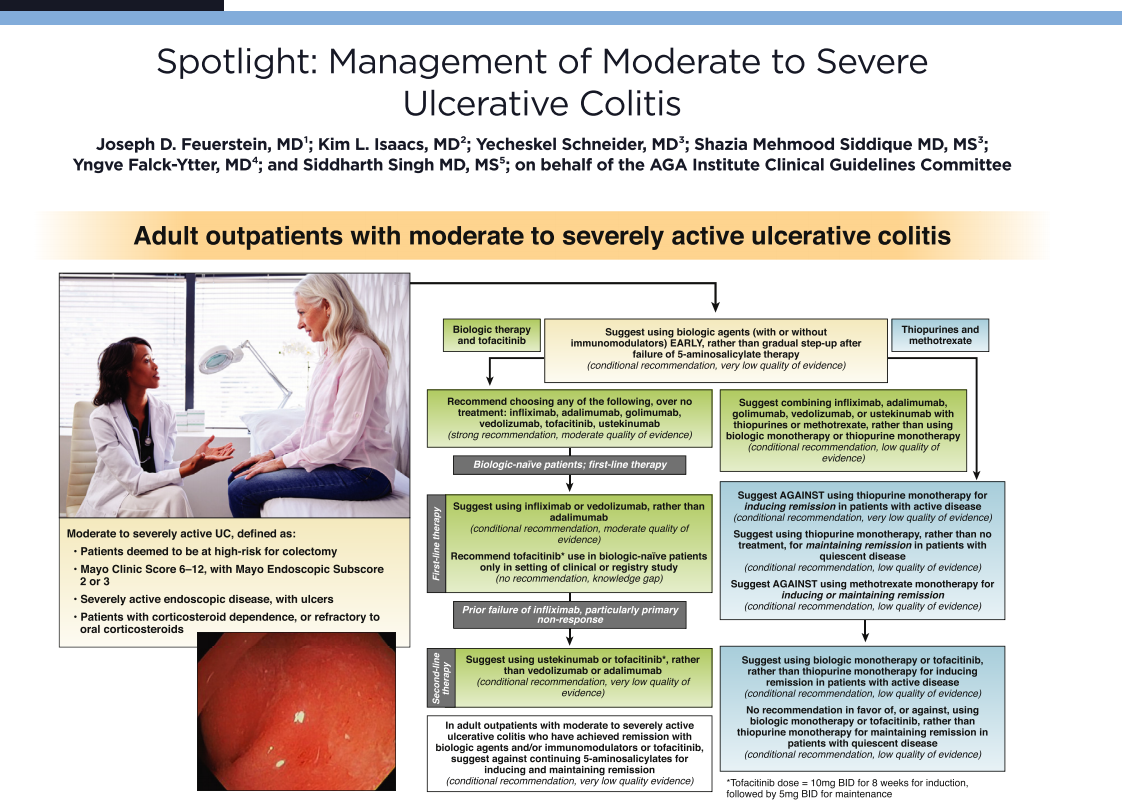
Full Text: JD Feuerstein et al. Gastroenterol 2020; 158: 1450-61. AGA Clinical Practice Guidelines on the Management of Moderate to Severe Ulcerative Colitis

Full Tex PDF: AGA Clinical Practice Guidelines on the Management of Moderate to Severe Ulcerative Colitis


Associated articles included the following:

  • Clinical decision support tool (1462-63)
  • PDF: Spotlight (summary -images above) (1464)
  • Technical Review (1465-96)

Key recommendations:

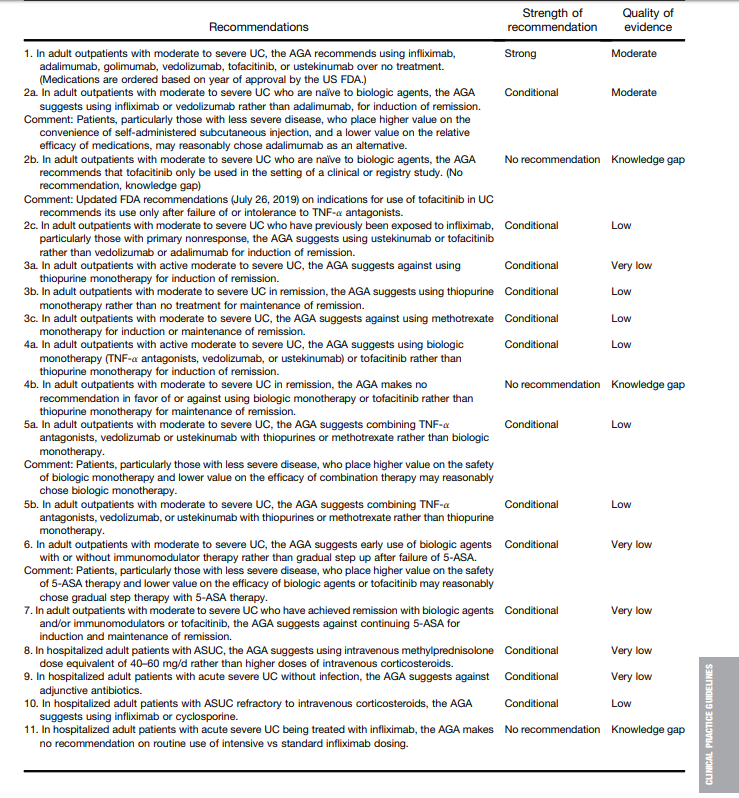
  • 2a. In adult outpatients with moderate to severe UC who are naïve to biologic agents, the AGA suggests using infliximab or vedolizumab rather than adalimumab, for induction of remission. Comment: Patients, particularly those with less severe disease, who place higher value on the convenience of self-administered subcutaneous injection, and a lower value on the relative efficacy of medications, may reasonably chose adalimumab as an alternative
  • 2c. In adult outpatients with moderate to severe UC who have previously been exposed to infliximab, particularly those with primary nonresponse, the AGA suggests using ustekinumab or tofacitinib rather than vedolizumab or adalimumab for induction of remission.
  • 6. In adult outpatients with moderate to severe UC, the AGA suggests early use of biologic agents with or without immunomodulator therapy rather than gradual step up after failure of 5-ASA. Comment: Patients, particularly those with less severe disease, who place higher value on the safety of 5-ASA therapy and lower value on the efficacy of biologic agents or tofacitinib may reasonably chose gradual step therapy with 5-ASA therapy.
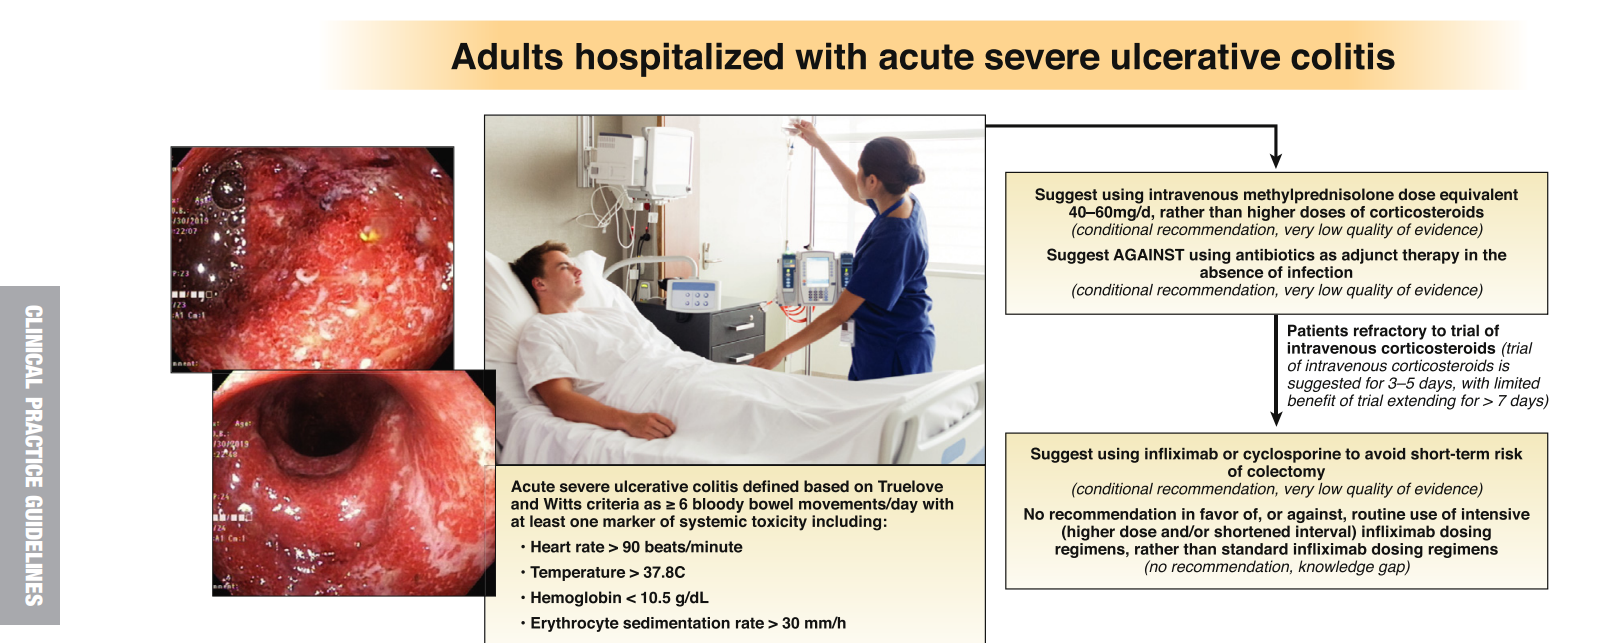
  • 10. In hospitalized adult patients with ASUC refractory to intravenous corticosteroids, the AGA suggests using infliximab or cyclosporine

Summary of recommendations:

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

New and Improved Biomarker Blood Test for Crohn’s Disease?

A recent study (G D’Haens, O Kelly, R Battat et al. Gastroenterol 2020; 158: 515-26,editorial 463) describes the development and validation of a blood test panel to assess Crohn’s disease (CD) endoscopic activity level.  The authors evaluated a blood test which measured 13 proteins in the blood using samples from 278 patients.  Then there were two validation cohorts:

  • 116 biologic-naive CD patients -cohort 1
  • 195 biologic-exposed CD patients -cohort 2

The blood tests were used to develop an endoscopic healing index (EHI) score (0-100). Higher scores indicate greater disease activity.

Key findings:

  • EHI values below 20 identified remission with a sensitivity of 97.1%  and 83.2% in cohorts 1 & 2 respectively; specificity was 69% and 37% respectively.
  • EHI values below 50 points identified patients with highest specificity of 100% and 88% in cohorts 1 and 2 respectively.
  • EHI AUROC (area under the receiver operating characteristic curve) did not differ significantly from that of fecal calprotectin and were higher than measurement of serum CRP (in cohort 1 but not cohort 2).

The editorial notes that the EHI performed much better in younger, biologically-naive patients and that the EHI could potentially be incorporated into a treat-to-target strategy which would potentially entail followup endoscopy in those with EHI >50.

My take: While the stool calprotectin has some logistical barriers in many patients, the EHI is likely a much more expensive test and needs further validation.  For now, the combination of CRP and calprotectin are the best noninvasive biomarkers to assess CD activity.

Briefly noted: Vedolizumab-Induced Pulmonary Toxicity -Case report of a patient with ulcerative colitis who developed interstitial lung disease (Gastroenterol 2020; 158: 478-9).

Related blog posts:


Efficacy of Anti-TNF Agents for Internal Fistulas and Study of Antibiotics and Development of IBD

G Bougen et al. Clin Gastroenterol Hepatol 2020; 18: 628-36.  This retrospective study (n=156, median age 32 years) found that anti-TNF therapy delays or prevents surgery for almost half of patients with Crohn’s disease who had luminal fistulas.  Key findings:

  • With a median followup of 3.5 years, “68 patients (43.6%) underwent a major abdominal surgery.”
  • Fistula healing occurred on average 1 year after the introduction of anti-TNF treatment
  • The presence of a stricture or abscess increased the likelihood of surgery.
  • Three patients died from intestinal adenocarcinomas, one patient died from melanoma (6 months after initiation of anti-TNF therapy), one patient died from sepsis (3 months after initiation of anti-TNF therapy, and 32 patients (20.5%) developed an intestinal abscess.

My take: Therapy with anti-TNF agent, in the setting of a luminal fistula, is a reasonable option, especially in the absence of a concurrent stricture.

FS Troelsen, S Jick. Inflamm Bowel Dis 2020; 26: 440-7, editorial 448-9. Using a UK database, the authors identified 461 cases of ulcerative colitis (UC) and 863 cases of Crohn’s disease (CD) and then matched each case to 4 controls. Key findings:

  • There was no association between ever use of antibiotics and UC, OR 1.02 or CD, OR 1.01 compared to never use of antibiotics
  • CD was associated with antibiotic exposure before age 5 (OR 2.2) in analysis restricted to individuals followed from birth
  • A slight increase was seen for CD in ever users of quinolones (OR 1.76, CI 1.00-3.11) and metronidazole (OR 1.43, CI 0.87-2.34)

In the editorial, Charles Bernstein notes that “it may be that specific types of antibiotics…at specific times in a person’s life have differential risks for IBD development. Also, it may be that what triggers IBD in children is different than what triggers IBD later in life.”

Duke University -late Fall 2019

IBD Pediatric Costs & Cannabis Still No Data for IBD

Happy birthday to my favorite follower!!!


A recent single-center study (AW Fondell et al. Inflamm Bowel Dis 2020; 26: 635-40, editorial by Joel Rosh, 641-2) examined the first-year costs of children with inflammatory bowel disease (IBD) in 2016.  There were 67 patients (43 with Crohn’s disease (CD), and 24 with ulcerative colitis (UC)).

Key findings:

  • Mean cost was $45,753; $43,095 for CD, $50,516 for UC
  • Severe CD (n=11) was $71,176 and severe UC (n=5) was $134,178; it is notable that only one patient with CD had surgery and only one patient with UC had surgery.
  • Overall cost distribution: 37% from infusion costs, 25% hospital costs, 18% outpatient procedures, 10% outpatient oral medications, 7% outpatient imaging and 3% outpatient visits.
  • 69% of CD patients and 33% of UC patients received biologics
  • 21% (n=9) of CD patients and 45% (n=11) of UC patients were hospitalized
  • Private payer reimbursement was a mean of $51,269 compared to $24,610 mean for Medicaid.

Limitations: 

  • In any cost analysis, many assumptions are needed.  For medications, for example, the author used pharmaceutical retail prices.  The actual costs are near-impossible to calculate as every insurance policy and every hospital system has a multitude of charges based on proprietary negotiations.
  • While this data comes from a referral center, all of the patients in the study were from Connecticut.

Due to the expense of care, Dr. Rosh points out that many insurers have often mandated the use of “standard dosing” of biologic therapy, “ignoring that robust data” indicate that this dosing is “the exception rather than the rule in pediatric IBD patients.”  These type of short-sighted interventions could affect long-term medical outcomes.

My take: There clearly are areas where costs can be reduced (eg. lower infusion costs, lower endoscopy costs, biosimilars).  However, no amount of cost cutting will change the conclusion that good care for IBD is expensive.

Briefly noted: TS Kafil et al. Inflamm Bowel Dis 2020; 26: 502-9.   This study examined evidence for cannabis effectiveness in IBD.  After performing a literature search, the authors could only identify five randomized controlled trials (n=185).  Each study used different doses, formulations and routes of administration.  No studies evaluated maintenance treatment and relapse in CD or UC.  Findings: “no firm conclusions can be made regarding the safety and effectiveness of cannabis and cannabionoids in adults with CD and UC.”

Related blog posts:


Cobb County -Concord Covered Bridge Historic District


Narrowing the Workup for Chronic Abdominal Pain –Carlo DiLorenzo Was Right!

In the good old days when we could have large meetings, Carlo DiLorenzo gave a terrific summary of recurrent abdominal pain (#NASPGHAN19 Postgraduate Course -part 3).  One of the slides, shown below, is supported by a new study (J Zeevenhooven et al. J Pediatr 2020; 219: 76-82)

In this recent reterospective study, the authors examined 853 patients, of whom 102 (12%) had an organic disorder; all had abdominal pain >2 months. The authors compared two diagnostic strategies:

  • Group 1: anti-TTG IgA, fecal calprotectin, Giardia, along with blood tests (hemoglobin, CRP, ESR)
  • Group 2: anti-TTG IgA, fecal calprotectin, and Giardia (if diarrhea)

Calprotectin was considered normal if <50 mcg/g,  “gray zone” if 51-250, mildly elevated if 251-1000, and elevated/active inflammation if >1000.

Key findings:

  • Sensitivity of the strategies was 90% and 88% for Group 1 and Group 2 respectively
  • In the presence of 1 or more alarm symptoms, the sensitivity was 92% for both strategies.
  • The sensitivity/specificity of calprotectin varied based on the cutoff value.
    • For >50, the sensitivity 75%, specificity 87%, PPV 44%, and NPV 96%
    • For >250, the sensitivity 48%, specificity 99%, PPV 82%, and NPV 93%
    • For >1000, the sensitivity 38%, specificity 100%, PPV 98%, and NPV 92%

Alarm symptoms

  • Alarm symptoms that were statistically different in the organic group included the following:
    • Chronic diarrhea (P <.001), occurred in 32% organic compared to 6% functional
    • GI blood loss (P <.001) , occurred in 35% organic compared to 5% functional
    • Recurrent vomiting (P=.029), occurred in 10% organic compared to 5% functional
    • Perianal complications (P=.001), occurred in 6% organic compared to 1% functional
    • Impaired growth (P=.023), occurred in 4% organic compared to 1% functional
  • Interestingly, the study found that having a positive family history of IBD/celiac/FMF did not differentiate functional and organic patients, occuring in 12% and 15% respectively.
  • Pain in RUQ or lower region also did not differentiate functional and organic patients, occuring in 3% and 4% respectively.
  • The authors note that 30 (29%) patients with organic disease did not have an identified alarm symptom -this compares to 479 (64%) patients with functional disease did not have an identified alarm symptom

From my experience with our recent study (Digestive Diseases (Full Text): Diagnostic Yield Variation with Colonoscopy among Pediatric Endoscopists) which focused on diagnostic yield with colonoscopy, it is clear that there are significant limitations with data collection in a retrospective study regarding recurrent abdominal pain.  Even the definition of chronic diarrhea may vary considerably among practitioners.  At the same time, we did find that an abnormal calprotectin had the highest diagnostic yield (See related blog post for summary: Our Study: Provider Level Variability in Colonoscopy Yield)

It is surprising to me that only 10 patients (1%) in their cohort were identified as having impaired growth.

My take: This study shows that anti-TTG testing and calprotectin are the most useful tests in children with persistent abdominal pain.  The addition of hemoglobin, CRP, and ESR “can be left out in the clinical evaluation of chronic abdominal pain in children.”  The authors advocate, as well, for a prospective cohort study to confirm their observations.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Brief Updates: COVID-19/Hydroxychloroquine, GALD, Anorexia Nervosa, and Esophaeal-gastric Dissociation Outcomes

Recent reports indicate that hydroxychloroquine is not likely effective for COVID-19.  Submitted manuscript: Outcomes of hydroxychloroquine usage in United States veterans hospitalized with Covid-19 Commentary from Politco: More deaths, no benefit from malaria drug in VA virus study

An excerpt: A malaria drug widely touted by President Donald Trump for treating the new coronavirus showed no benefit in a large analysis of its use in U.S. veterans hospitals….The study was posted on an online site for researchers and has been submitted to the New England Journal of Medicine, but has not been reviewed by other scientists….About 28% who were given hydroxychloroquine plus usual care died, versus 11% of those getting routine care alone. About 22% of those getting the drug plus azithromycin died too, but the difference between that group and usual care was not considered large enough to rule out other factors that could have affected survival…The NIH and others have more rigorous tests underway.

HS Fischer et al. JPGN 2020; 70: 444-9. This study examined outcomes of 12 patients with gestational alloimmune liver disease over an 11 year period. Key findings:

  • Median age at diagnosis of neonatal acute liver failure (NALF): 2 days
  • All 12 received exchange transfusion ET).  Common signs: hypoglycemia, hyperferritinemia, cholestasis, and coagulopathy. Direct bilirubin typically increased after ET.
  • Outcomes: survival without transplantation occurred in 10 of 12.  Two patients died including one after liver transplantation.
  • “Most cases of NALF are due to GALD and should be timely treated with ET and IVIG.”  Current testing is lacking with regard to sensitivity and specificity, “early ET [and IVIG] before reaching a definitive diagnosis was associated with favorable outcomes.”

Related blog posts:

JE Mitchell, CB Peterson. Anorexia Nervosa (good review). NEJM 2020; 382: 1343-51.

Key points: 

  • Anorexia nervosa is a severe psychiatric disorder
  • Indications for hospitalization include profound hypotension or dehydration, severe electrolyte abnormalities, arrhythmias or severe bradycardia, suicide risk or BMI ≤15

Related blog posts:

S Battaglia et al. JPGN 2020; 70: 457-61. This retrospective study examined outcomes in 30 patients with severe neurologic impairment who underwent esophageal-gastric dissociation (E-GD) between 2000-18 and had a median follow-up of 3.5 years. E-GD was completed at a median age of 6.5 years. “Primary” E-GD was done in 23 and “Rescue” (after fundoplication) was done in 7 patients.

  • Hospitalizations and episodes of chest infections significantly decreased; weight improved
  • Vomiting and reflux resolved in all patients
  • 6 (20%) experienced early complications including 3 who needed surgery (1 obstruction, 1 volvulus, and 1 pyloric obstruction); 3 (10%) had late complications (adhesions/obstruction in 1, incisional hernia in 1, large para-esophageal hernia in 1)
  • There were no surgery-related deaths

The authors, in their discussion, compare primary E-GD with fundoplication.  Many of the referenced studies indicate that E-GD may have improved outcomes in the population of children with severe neurologic impairment, but also with a higher frequency of complications.  They conclude that E-GD “is a valid alternative to fundoplication…but is is just as effective and feasible when undertaken as a ‘Rescue’ procedure following failed surgical antireflux treatment.”

My take: The frequency of fundoplication operations have dropped markedly with increasing use of gastrojejunal tube placement.  In my view, I would usually recommend E-GD for ‘rescue’ after fundoplication failure.

A recent yard sign from my wife for neighborhood walkers during the pandemic


Bigger Data Needed and Other IBD Updates April 2020

R Pittayanon et al. Gastroenterol 2020; 158: 930-46.  In this systematic review of the relationship between gut microbiota and inflammatory bowel disease, 48 studies and 45 articles were included from a total of 2631 citations.  Overall, the authors found inconsistent results with differences in the abundances of some bacteria in IBD. My take: These microbiota studies use ‘big data’ to look for abnormal patterns in patients with IBD.  Overall, most of these studies support a reduced diversity among patients with IBD.  Specific variation in microbes varies widely and remains unclear if they are a cause or a consequence of IBD.

J Piercy et al. JPGN 2020; 70: 318-23. Among 90 adolescents with IBD, “perfectionistic concerns (self-critical and socially prescribed perfectionism) were associated with higher rates of adolescent-reported externalizing symptoms” Thus, perfectionism may help with self-management but lead to more stress and psychosocial symptoms.

S Jardine et al. Gastroenterol 2020; 158: 1000-15. This study used both TTC7A-knockout cells and a zebrafish model to screen compounds that have been FDA approved for treatment of inflammatory bowel disease caused by TTC7A deficiency.  The authors identified leflunomide that reduces apotosis and levels of active caspase 3 in TTC-7A-knockout cells and restored gut motility along with improvement of intestinal cell survival in zebrafish. This study has some amazing figures detailing the changes induced by leflunomide. My take: Although some centers have offered hematopoetic stem cell transplant (with dismal results), there is NOT a currently accepted treatment for TTC7A deficiency-induced IBD.  This study suggests an agent which may help.

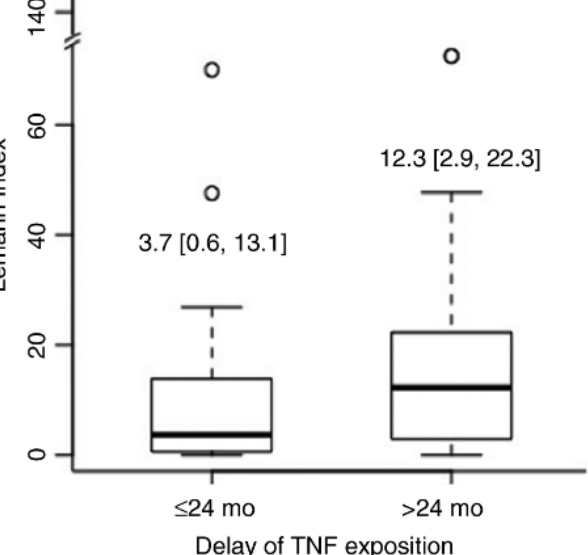
CLD Prevost et al. AP&T 2020. https://doi.org/10.1111/apt.15681 Key finding:  Among patients exposed to anti‐TNF, the Lémann Index was lower in those who were exposed in the first 2 years of their disease (P = 0.015).  My take: Early treatment with anti-TNF agents can reduce risk of permanent bowel damage. This was seen as well in the RISK study which showed that anti-TNF therapy reduced the development of penetrating disease. (Related post: CCFA Update 2017, Part 3)

Full link: Bowel damage and disability in Crohn’s disease: a prospective study in a tertiary referral centre of the Lémann Index and Inflammatory Bowel Disease Disability Index

Two Studies: 1. COVID-19 Transmissibility 2.Fecal Microbiota Transplantation in 372 Children

A study in Nature suggests that more than 40% of SARS-CoV-2 infections (COVID-19 viral infections) are spread in the presymptomatic stage: Temporal dynamics in viral shedding andtransmissibility of COVID-19 (Thanks to Steven Liu for this reference).

An excerpt:
We report temporal patterns of viral shedding in 94 patients with laboratory-confirmed COVID-19 and modeled COVID-19 infectiousness profiles from a separate sample of 77 infector–infectee transmission pairs. We observed the highest viral load in throat swabs at the time of symptom onset, and inferred that infectiousness peaked on or before symptom onset. We estimated that 44% (95% confidence interval, 25–69%) of secondary cases were infected during the index cases’ presymptomatic stage, in settings with substantial household clustering, active case finding and quarantine outside the home. Disease control measures should be adjusted to account for probable substantial presymptomatic transmission.

——————————-

A recent retrospective multi-center study (MR Nicholson et al. Clin Gastroenterol Hepatol 2020; 18: 612-9) provides data on fecal microbiota transplantation (FMT) for Clostridium difficile infection (CDI). Congratulations to one of my partners, Jeffery Lewis, who is one of the coauthors. This paper’s abstract is noted in a separate blog: Large Study Show FMT Efficacy/Safety in Children.

Though this is a pediatric study, the authors included patients up to 23 years.  335 of the patients had followup for at least 2 months following FMT.

Key findings:

  • 81% of patients had a successful outcome after a single FMT and 86.6% after single or repeated FMT
  • Higher success rates were associated with fresh donor stool (OR 2.66), FMT via colonoscopy (OR 2.41), and with not having a feeding tube (OR 2.08)
  • Though not reaching statistical significance, patients with inflammatory bowel disease had a high failure rate of 23% (26/111).  Short bowel syndrome patients had a 50% failure rate (5/10), solid organ transplant recipients had a 56% failure rate (5/9), and patients with feeding tubes had a 32% failure rate (21/65).
  • Seventeen patients (4.7%) had a severe adverse event during the 3-month follow-up period, including 10 hospitalizations; however, the majority were unrelated to FMT. Specific adverse reactions that were related or may have been included aspiration pneumonia on day of procedure (n=1), IBD flare/colectomy (n=5), and vomiting/dehydration (n=1)
  • Common adverse reactions included diarrhea, abdominal pain, and bloating. (These symptoms have been reported in up to 70% of adults following FMT.)

The authors note that a prior systematic review had indicated that delivery of FMT via colonoscopy was more successful in adults (95% vs 88%), though there are some additional risks with colonoscopy.

It is worth considering that the failure rate in some patients could be due to misdiagnosis, particularly in certain populations like patients with IBD and or organ transplant recipients.  In these populations, PCR assays may result in false-positive diagnosis and should be confirmed with an ELISA assay.   While eradication of CDI with FMT improves clinical symptoms and reduces the use of antibiotics the true benefit and risks will not be known for a long time.  Does FMT increase or reduce the risk of downstream infections, autoimmune disease, and metabolic syndrome?

My take: Many of the concerns with FMT can only be adequately addressed with prospective studies (with strict definitions of CDI) and longer followup.

Related blog posts:

Island Ford, Sandy Springs