Federal Policies Changing Medical Standards

BA Barsky et al. N Engl J Med 2026;395:419-421. Medical Standards by Federal Fiat

An excerpt:

“Historically, the federal–state division of authority over medical practice has been strict. This division is evident in health care financing and medical product regulation, for example. States license physicians and set standards for medical care, often incorporating standards established by the medical profession while allowing broad discretion for physician judgment.1

The Trump administration has attempted to alter the balance of federal–state authority in the area of gender-affirming care in two important ways. First, in June 2025, the U.S. Department of Justice (DOJ) issued administrative subpoenas to more than 20 health systems and clinics providing gender-affirming care, demanding unusually broad information related to off-label prescribing of puberty blockers and hormones…The DOJ’s subpoenas, however, demanded information at the heart of physician judgment and the patient–doctor relationship, including physicians’ case-specific clinical assessments justifying off-label prescriptions and information that could be used to identify patients, including children, by name…

The second federal disruption came in December 2025, when Secretary of Health and Human Services Robert F. Kennedy, Jr., issued a declaration stating that gender-affirming care for children and adolescents is unsafe and does not meet professionally recognized standards of care…

Much of the authority and discretion now held by medical professionals and the states would move upward to a federal government that would exert expanded control over the health care that patients receive. Such a shift would potentially force all states to accept a single federal standard of care in various areas of medicine while concentrating immense medical power in the hands of political appointees. Federal authority over health care standards is appropriate in some instances. But this authority should be established using a proper legal process — Congress acting within its enumerated constitutional powers, or the executive branch acting under properly delegated authority — not by fiat.”
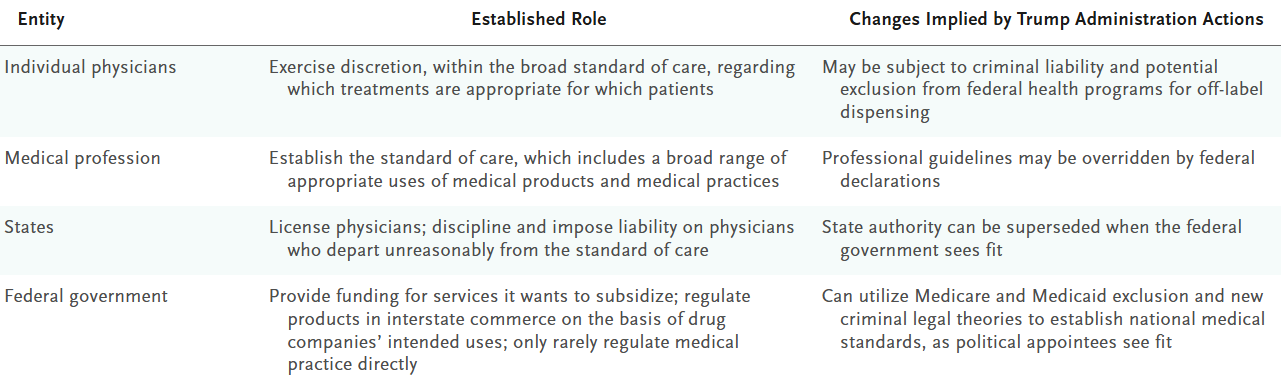
Established Roles for Setting the Medical Standard of Care
and Changes Implied by Trump Administration Actions.

My take: While this issue primarily affects a narrow area currently, it is not difficult to imagine that other administratioins could similarly impose policies affecting other sensitive decisions like abortion (expanding or limiting options), contraceptive availability, discussions about guns, and viability decisions.


Dr. Michael Wilsey: Endoscopy Pearls and Ergonomics (Part 2)

Dr. Michael Wilsey gave our group an excellent update on Endoscopy Pearls and Ergonomics. My notes below may contain errors in transcription and in omission. Along with my notes, I have included many of his slides.

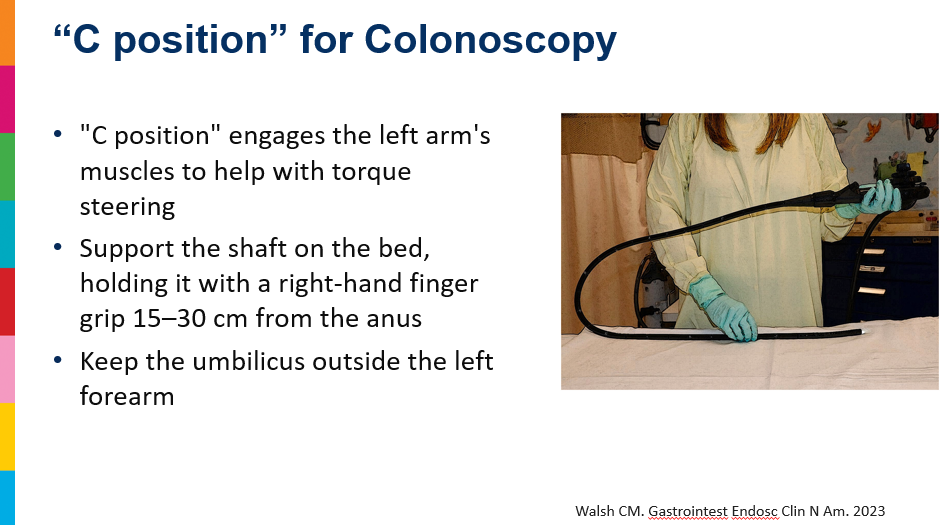
Yesterday’s post focused on endoscopy pearls. Today’s post focuses on ergonomics. Most of the attendees realized that we could use a lot of improvement in this area after listening to this presentation. This issue is likely of even greater importance in those with a high endoscopy case load.

  • A high percentage of gastroenterologists/pediatric gastroenterologists develop injuries related to repetitive endoscopy procedures.  These can be mitigated using proper ergonomics.  Although this advice is pretty straight forward, a lot of endoscopists could benefit from careful attention to this.
Areas included neck/upper back (44.0%), thumb (42.0%), hand/finger (38.0%), lower back (36.0%).
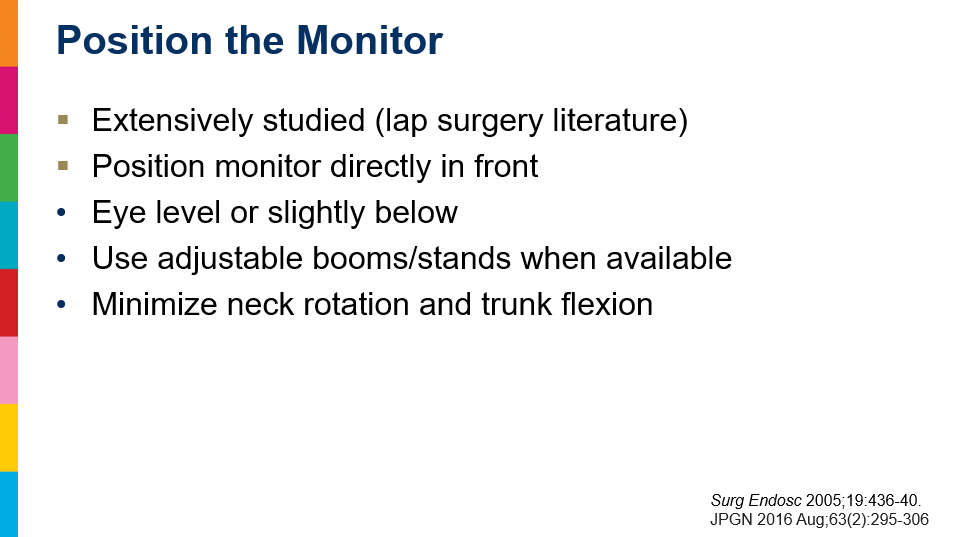
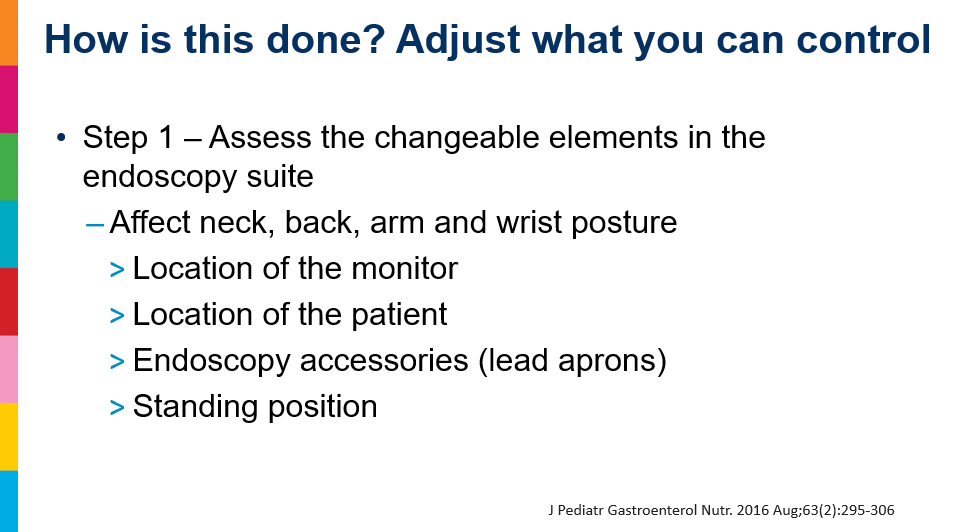
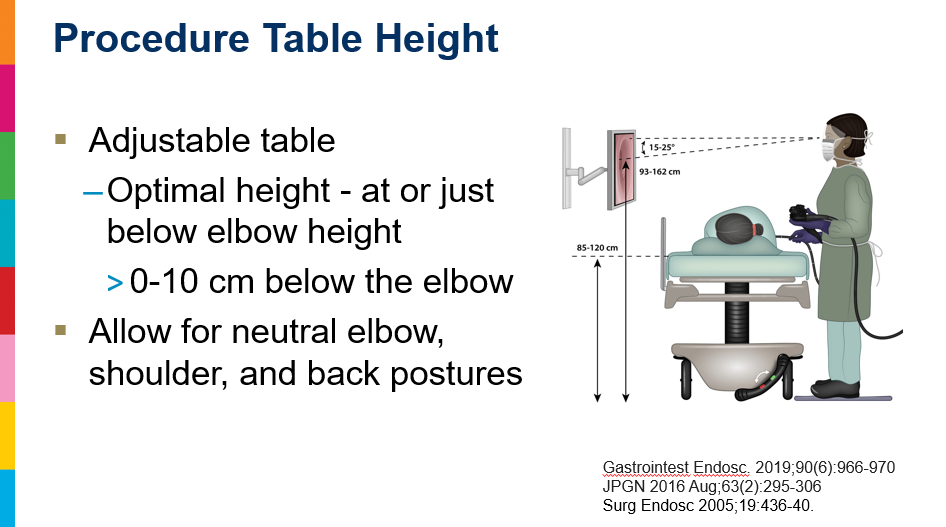
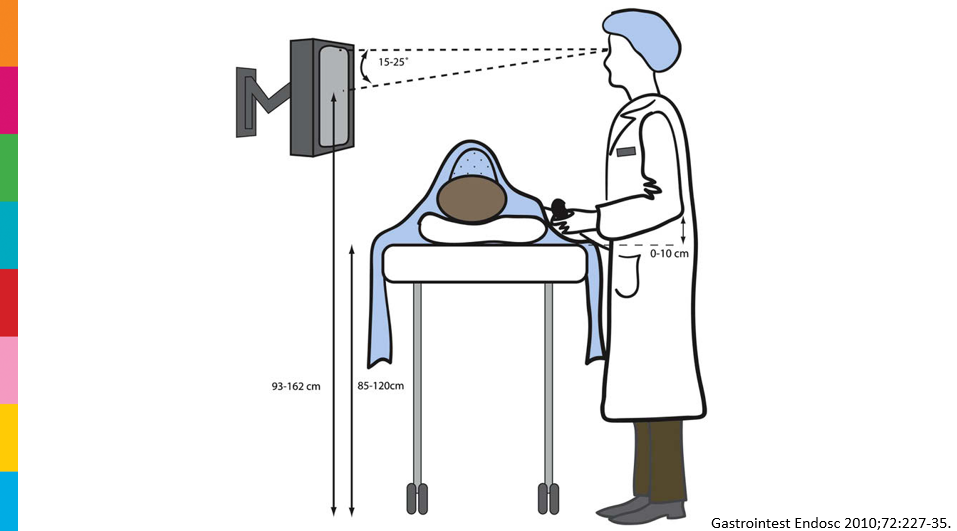
  • Keep Monitor near eye level and in front of you (don’t torque your neck)
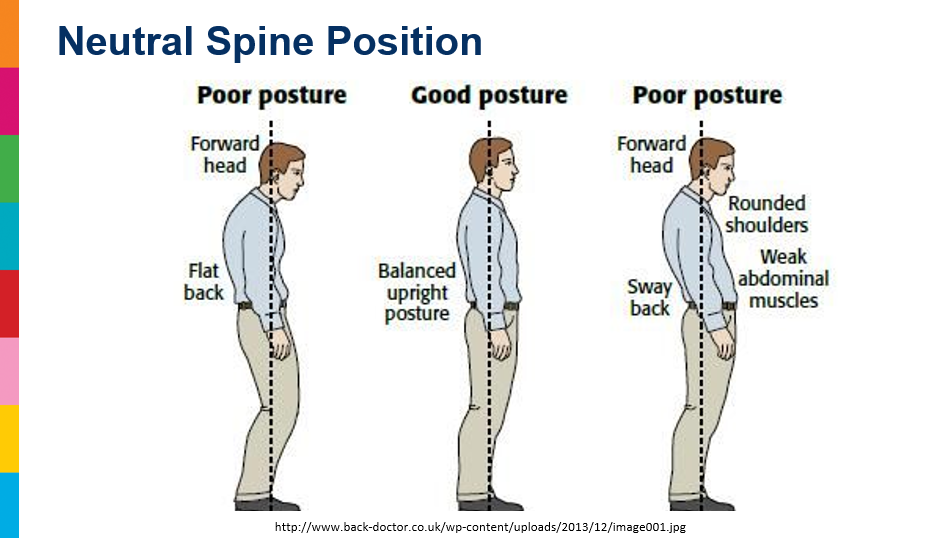
  • Maintain good posture. Can start by standing upright against a wall
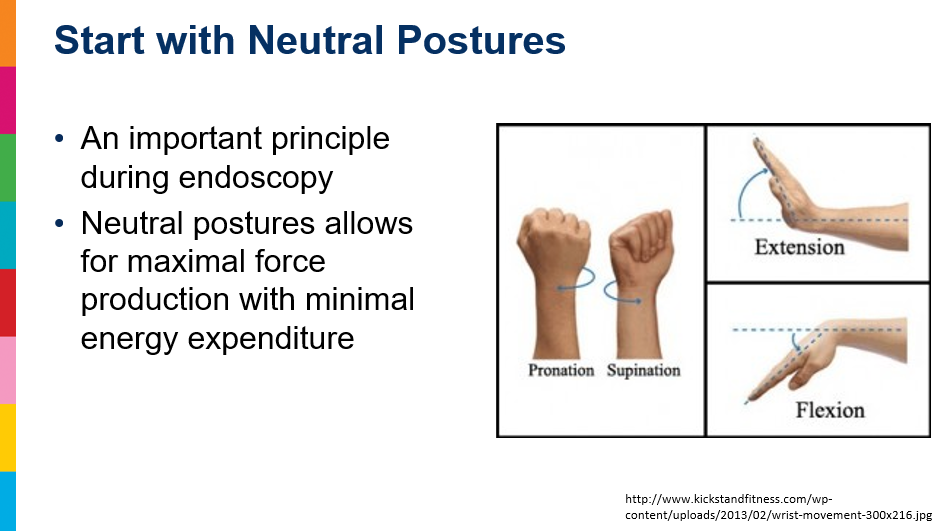
  • Position bed so elbows can be in a fairly neutral position with bed not more than 10 cm below elbows
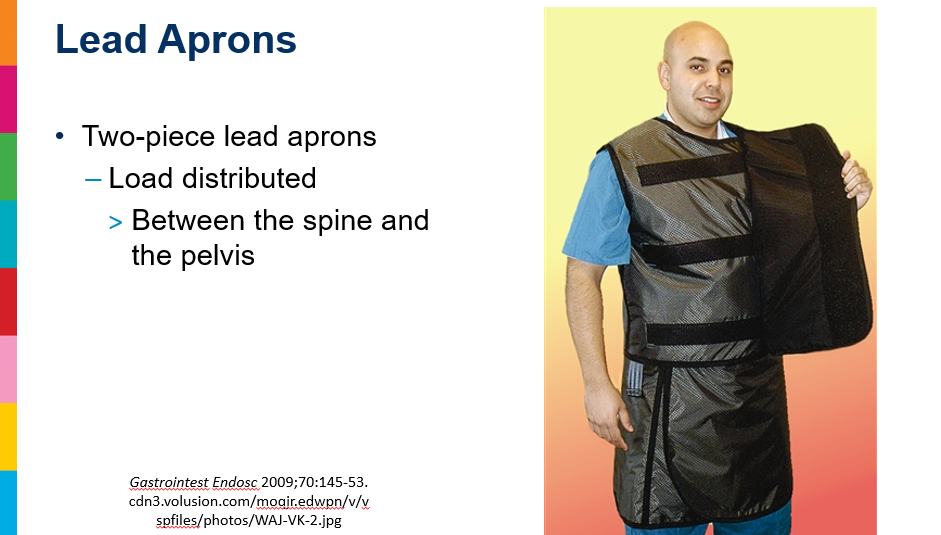
  • Two-piece lead aprons helpful to distribute weight better
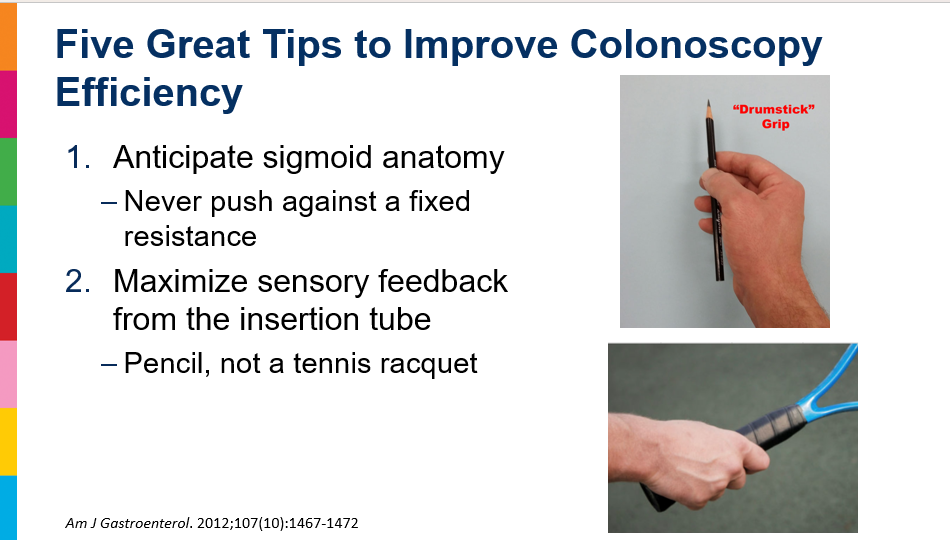
  • Handle endoscope more like holding a pencil than using a firm grip
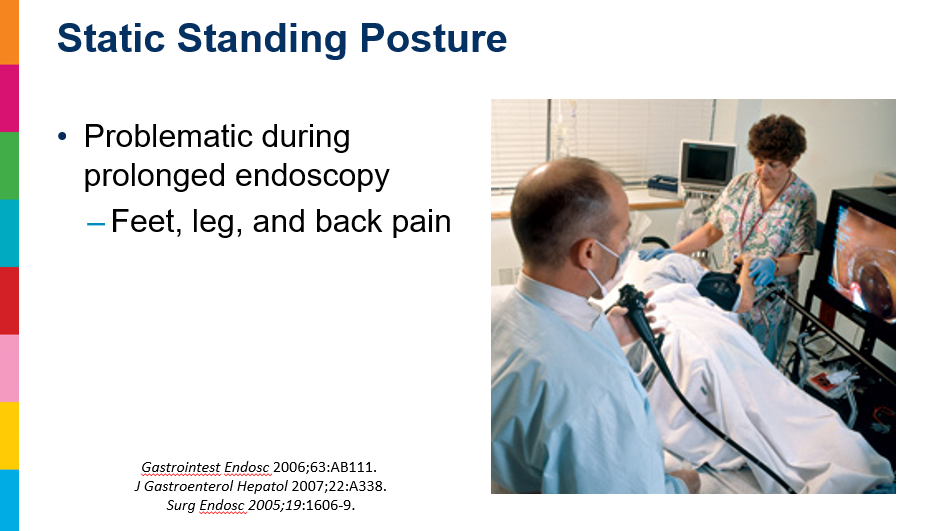
  • Cushioned mat and cushioned soles can help with standing posture/fatigue

Dr. Michael Wilsey: Endoscopy Pearls and Ergonomics (Part 1)

Dr. Michael Wilsey gave our group an excellent update on Endoscopy Pearls and Ergonomics. My notes below may contain errors in transcription and in omission. Along with my notes, I have included many of his slides.

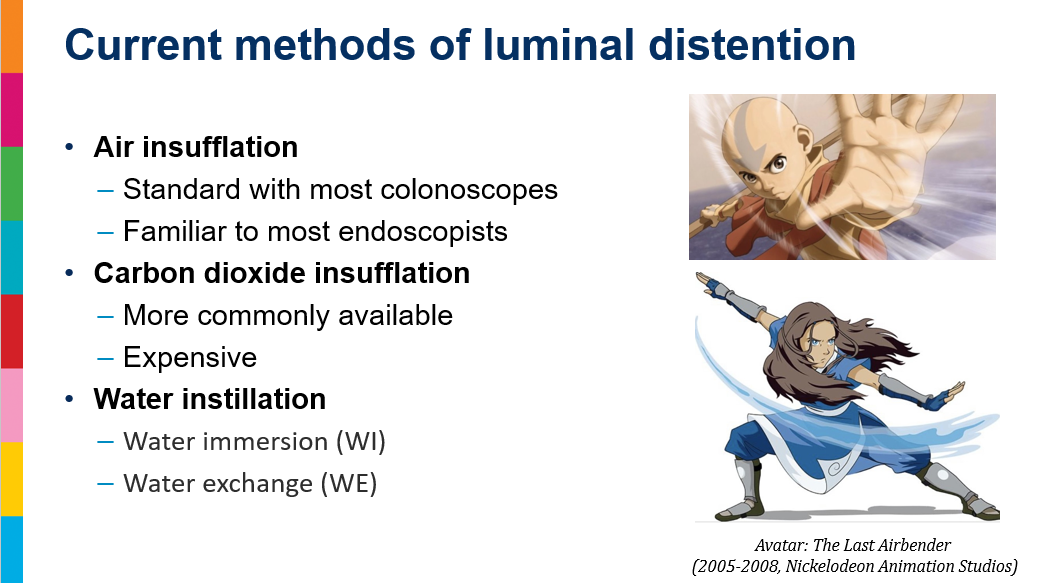
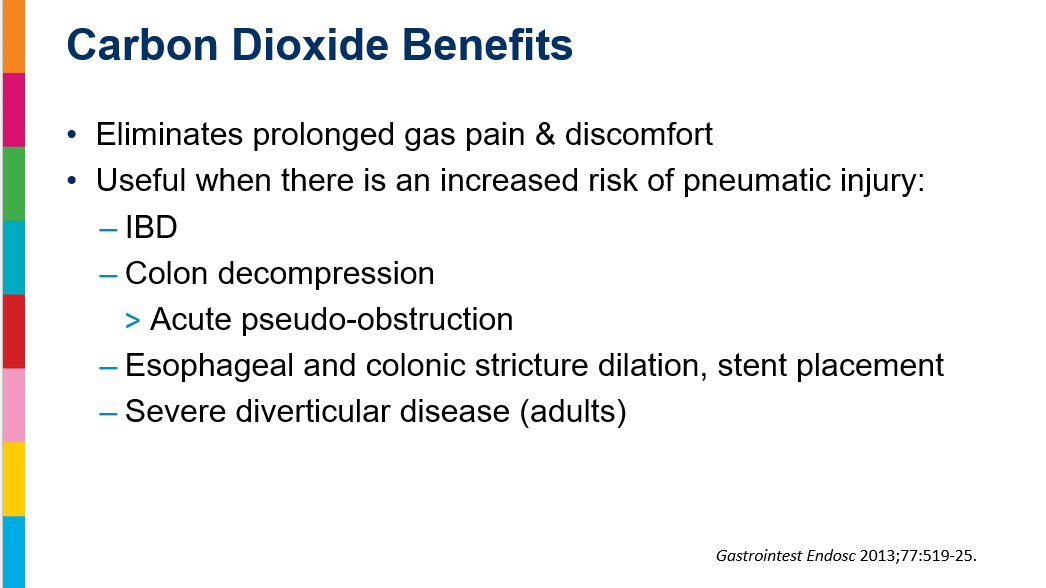
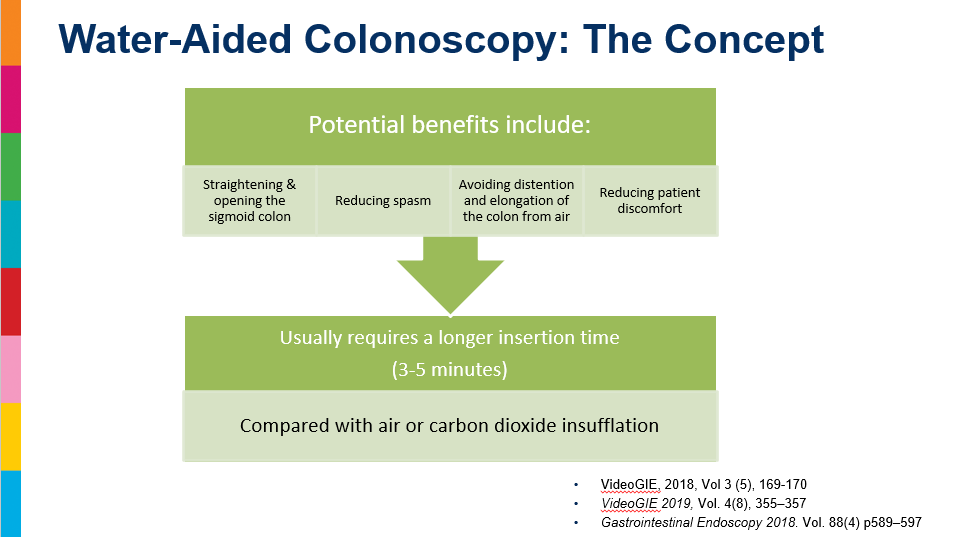
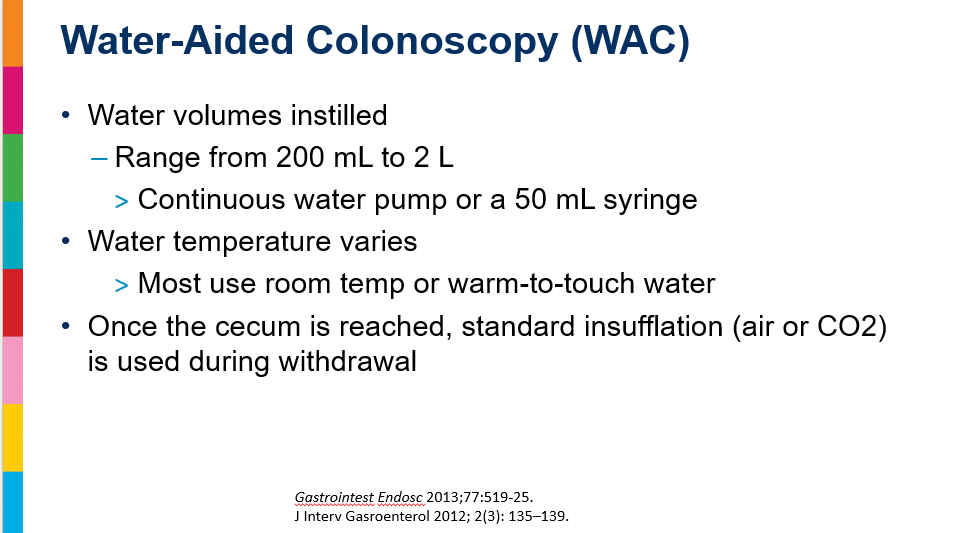
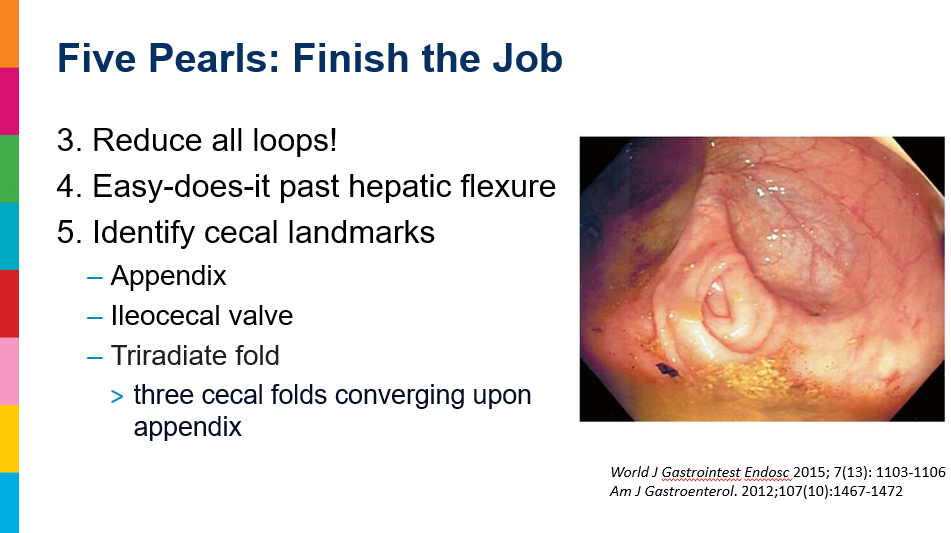
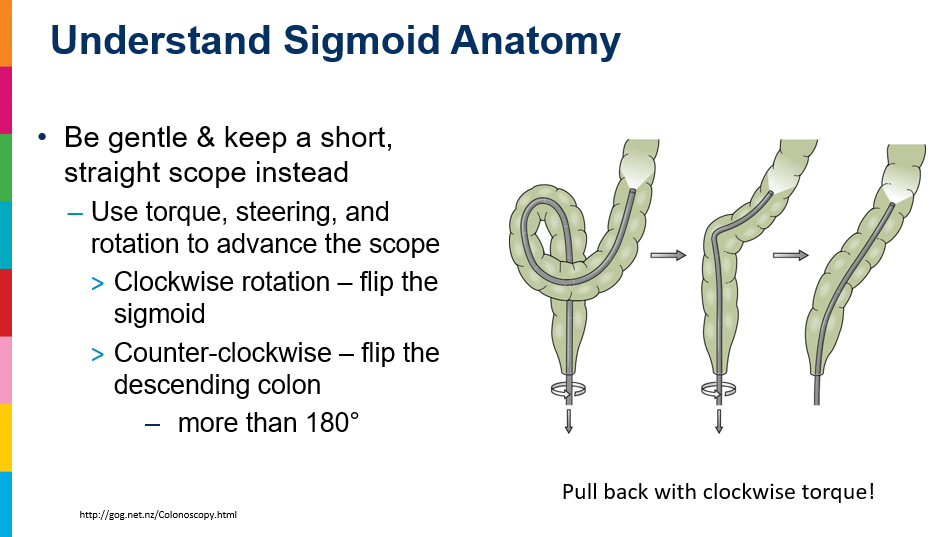
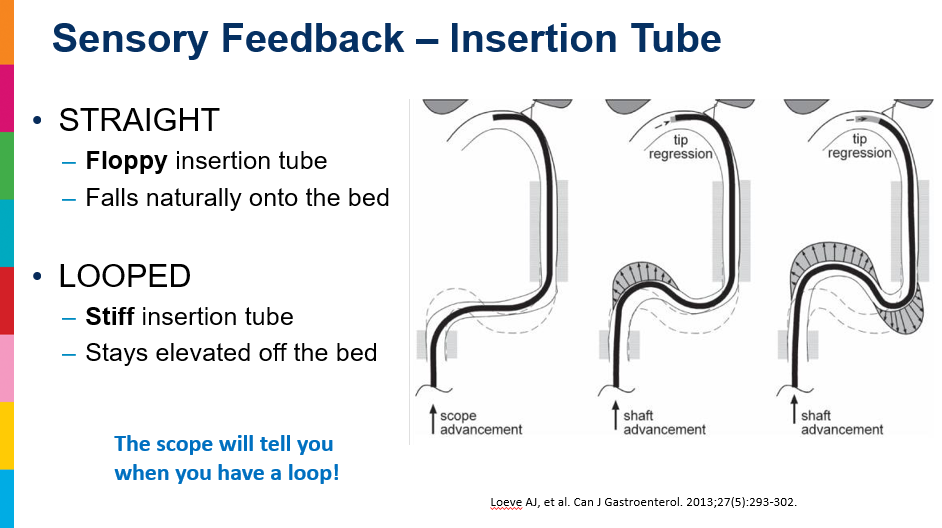
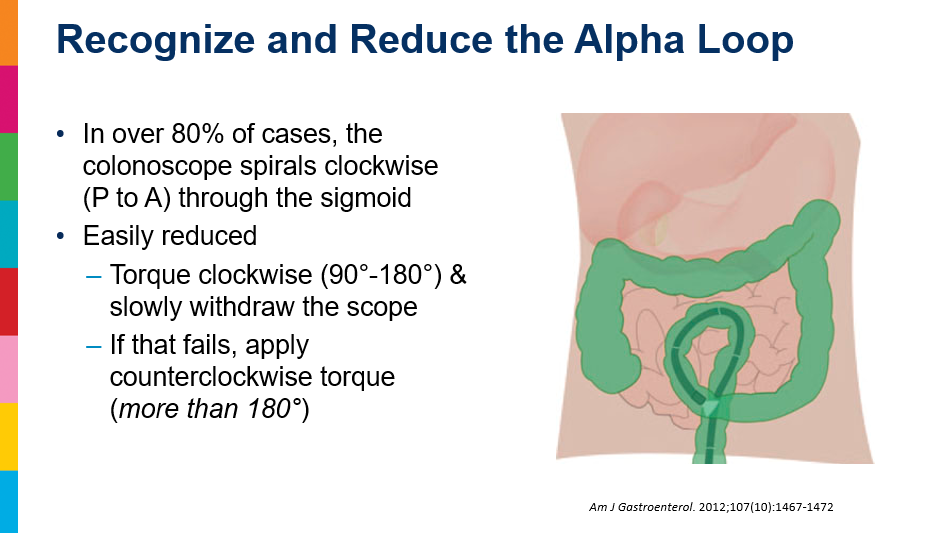
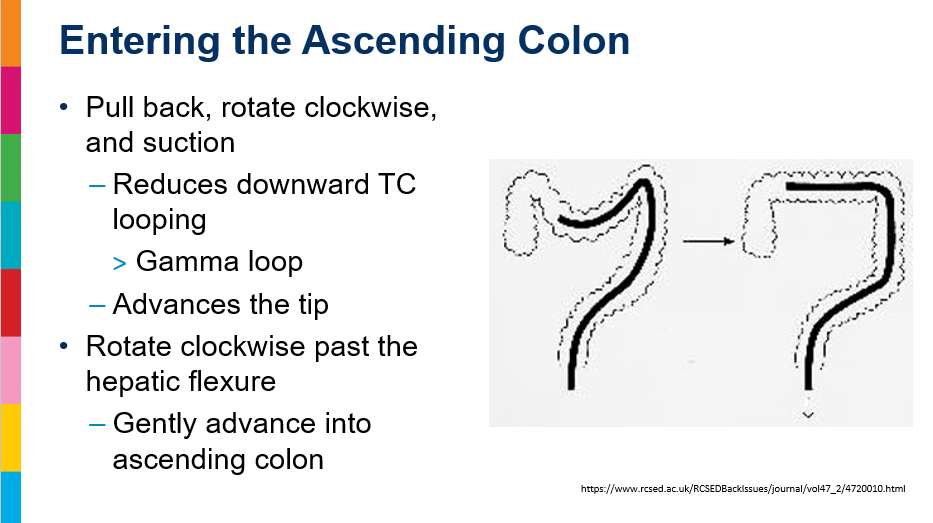
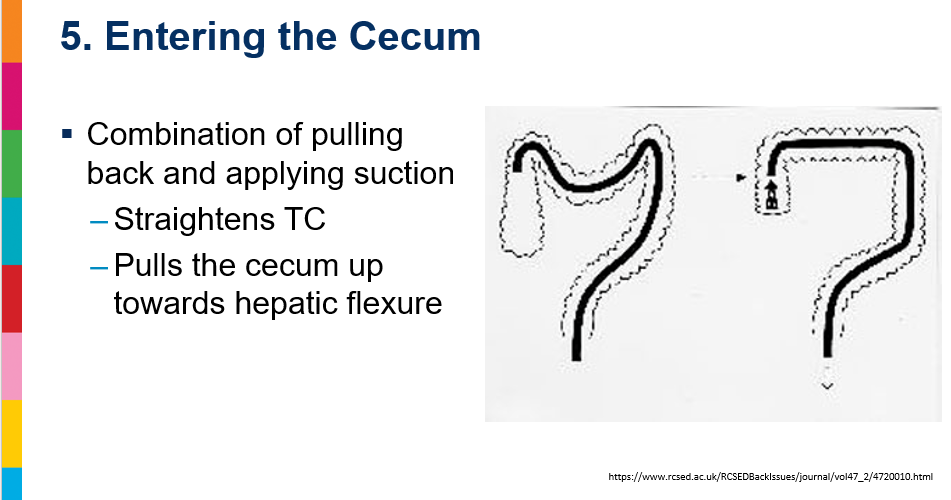
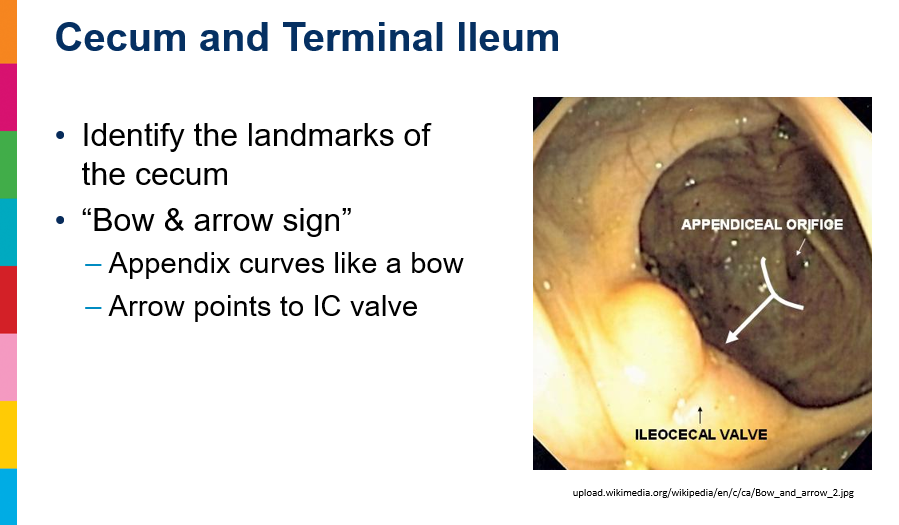
Endoscopy Pearls:

  • Video Link to show techniques:
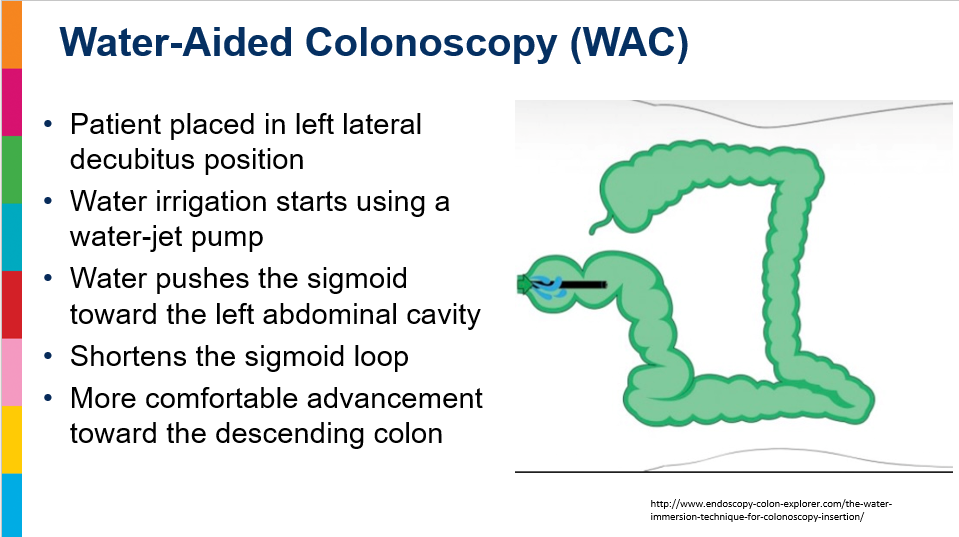
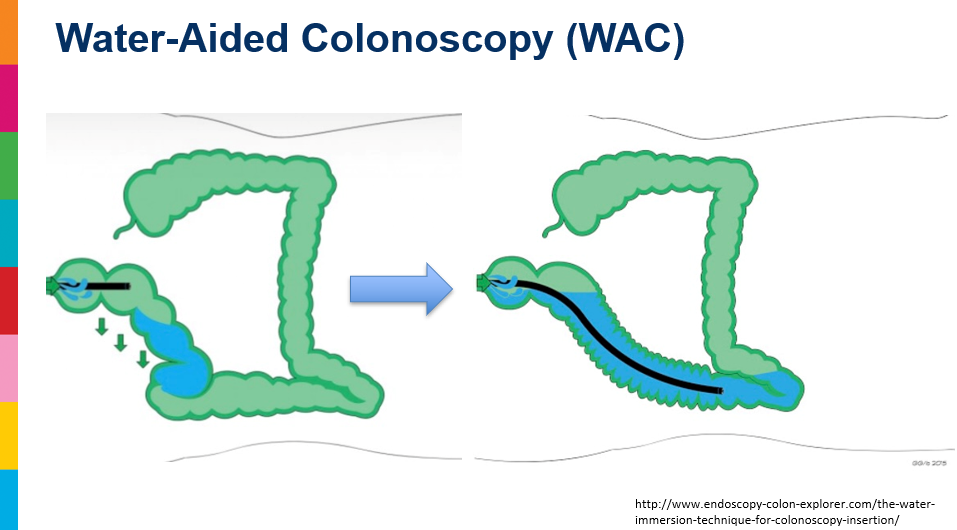
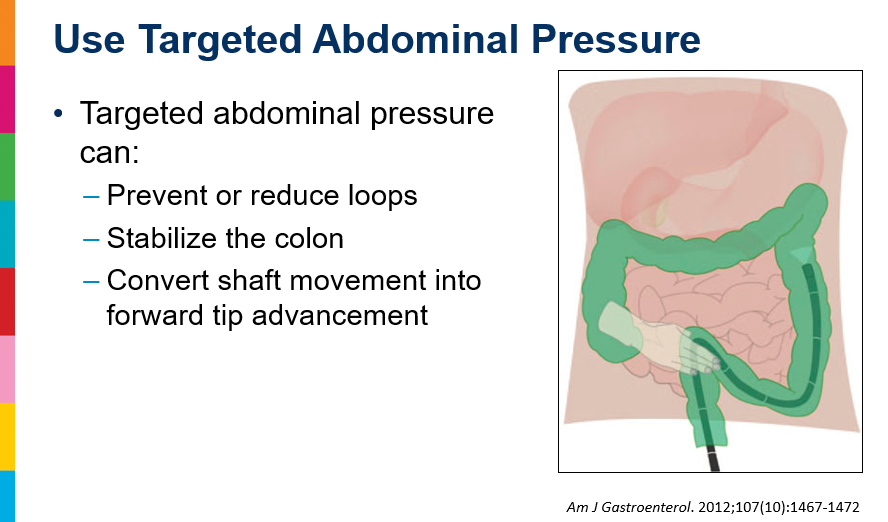
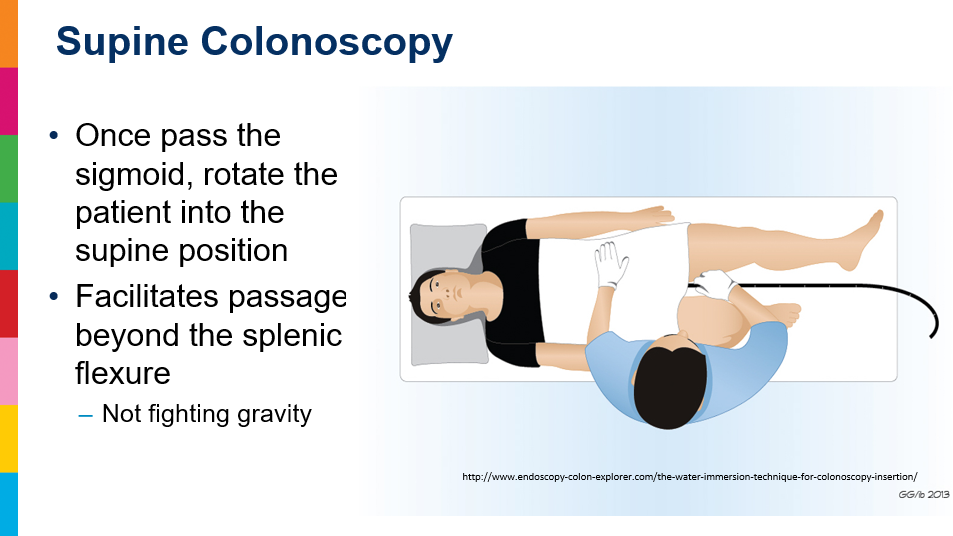
    • YouTube (~6 minute): How to Perform a Water-aided colonoscopy. Sergio Cadoni, Sauid Ishaq, VideoGIE, Volume 3, Issue 5, 2018; Pages 169-170.
    • Residue can be suctioned while infusing more water, which helps to clean the colon, but if there is too much residue, it is very difficult to see clearly enough to insert the colonoscope properly.
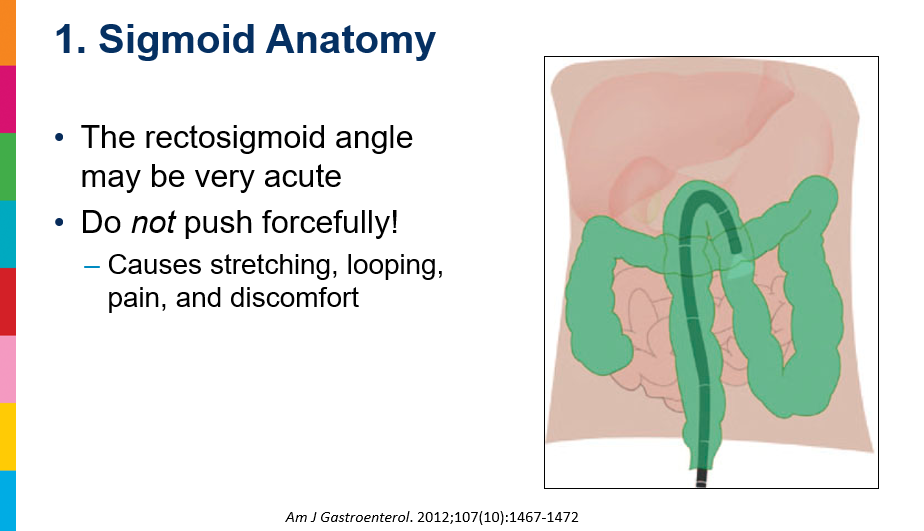
    • The water immersion technique starts with the patient in the left lateral position so that the progressive irrigation of water eases down the sigmoid by gravity on the left abdominal quadrant. Instead of syringes, the use of water flushing pumps allows one to better adjust the quantity of water needed according to the morphology of the sigmoid and does not delay the maneuvers of scope progression.
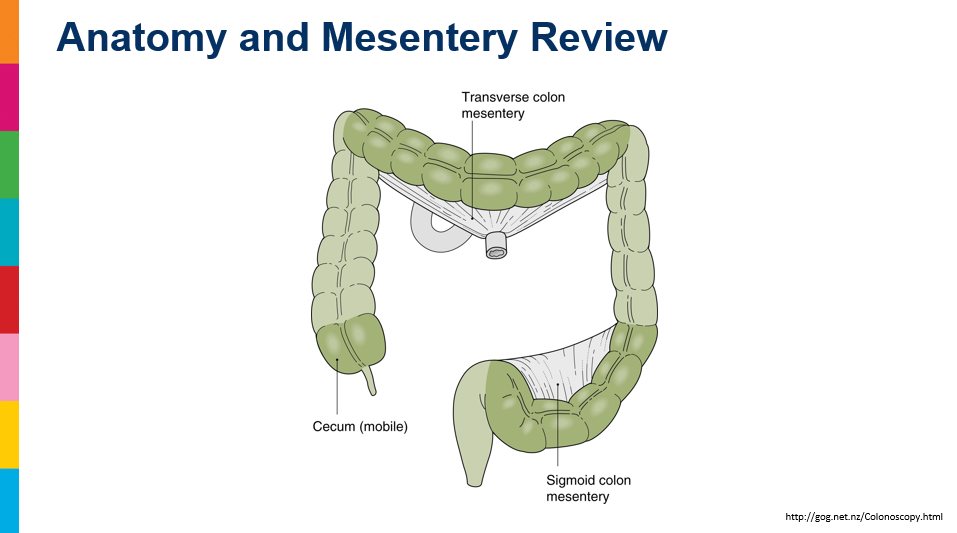
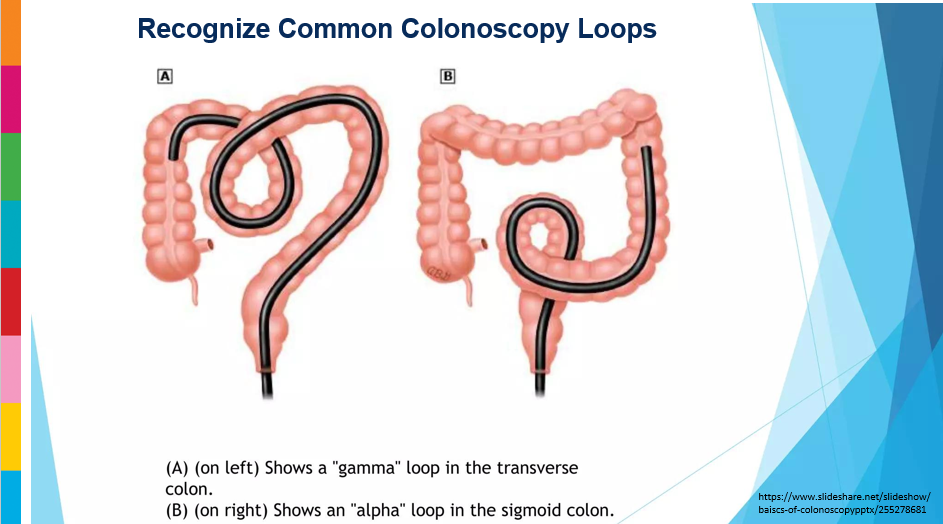
  • Anatomy: sigmoid and transverse colon are more mobile. They are suspended by mesenteries (the transverse mesocolon and sigmoid mesocolon), which allow them to swing or shift freely in the abdomen, unlike the other fixed parts of the colon.

Related blog posts:

Optimizing PPI Therapy for Eosinophilic Esophagitis with CYP2C19 Genotyping

P Bose et al. American Journal of Gastroenterology. DOI: 10.14309/ajg.0000000000004117 Dose May Matter: CYP2C19 Genotype and Proton-Pump Inhibitor Response in Pediatric Eosinophilic Esophagitis

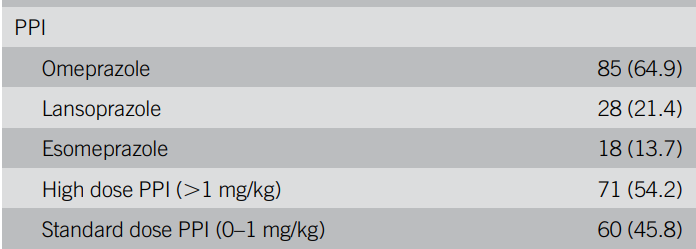
Methods: A cohort study of pooled data from 2 tertiary-care pediatric centers (Riley Children’s Health,Indianapolis, IN, and Children’s Hospital of Philadelphia, Philadelphia, PA) was conducted. N=131, mean age 8.5 yrs. Individuals with certain CYP2C19 polymorphisms were classified as normal (NMs), intermediate/slow(IMs), and rapid metabolizers (RMs) of PPIs based on the presence of normal function (*1), loss-of-function (*2), or gain-of-function (*17) alleles. PPI choice and dosing:

Key findings:

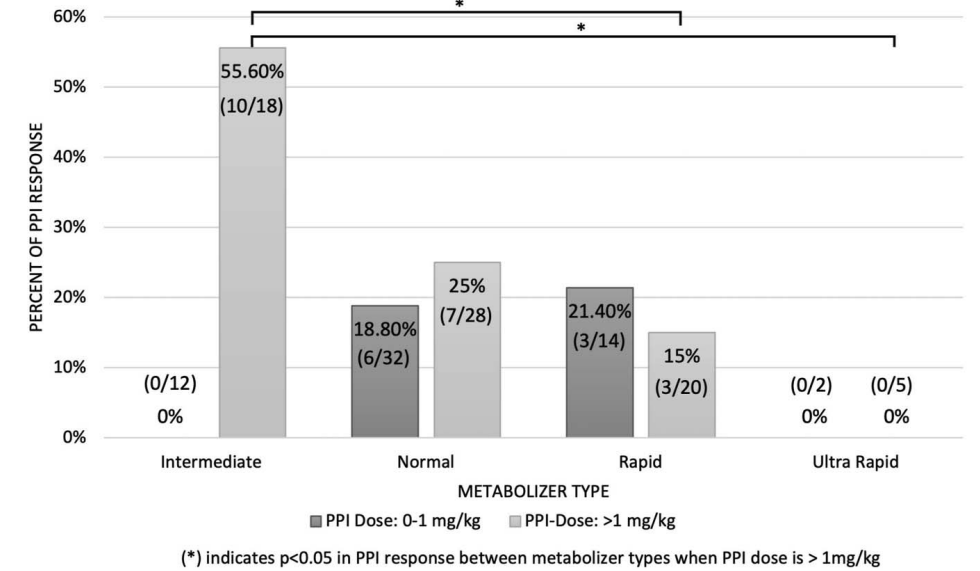
  • PPI response occurred in 22.1% of subjects (29/131)
  • Overall, IMs had the highest proportion of PPI response at 33.3% (10/30), followed by NM of 21.7% (13/60) and RM of 14.6% (6/41) (P 5 0.205).
  • No ultra-rapid metabolizers had a response.

Discussion: “Atypical dosing for PPI use in EoE may be related to mechanisms of action apart from gastric acid suppression, such as inhibiting eosinophil migration or restoring esophageal mucosal barrier integrity, which have been previously proposed.”

There may have been a selection bias in this population. The methods section does not detail these cohorts precisely. It is unclear if all patients in these centers undergo CYP2C19 genotype testing. In most centers, CYP2C19 genotype testing is uncommon and may be more likely in those who have not responded to therapy.

My take:

  1. CYP2C19 genotype testing may help determine whether PPI therapy is likely to work for a patient with EoE and influence the dosage selected. This is not a new concept. It was noted at a NASPGHAN meeting in 2017.
  2. In those with unfavorable CYP2C19 genotype, either an alternative therapy or a PPI that is not metabolized with CYP2C19 (eg. rabeprazole) should be considered.

Related blog posts:

Complimentary, Alternative, and Integrative Medical Therapie Use in a Pediatric DGBI Cohort

A VonAxelson et al. J Pediatr Gastroenterol Nutr. 2026;83:282–284. Patterns in integrative medicine usage among pediatric patients in a disorders of gut–brain interaction clinic

In a retrospective cohort (n=331, mean age 15 years) from a DGBI clinic, the patterns of integrative medicine usage were evaluated. The most common comorbidities in the sample were anxiety (61%), sleep disturbance (36%), and depression (32%). The most common DGBI diagnoses in the study were FD (58%) and IBS (57.4%), with FAP-NOS being third most frequent 10.6%).

Key findings:

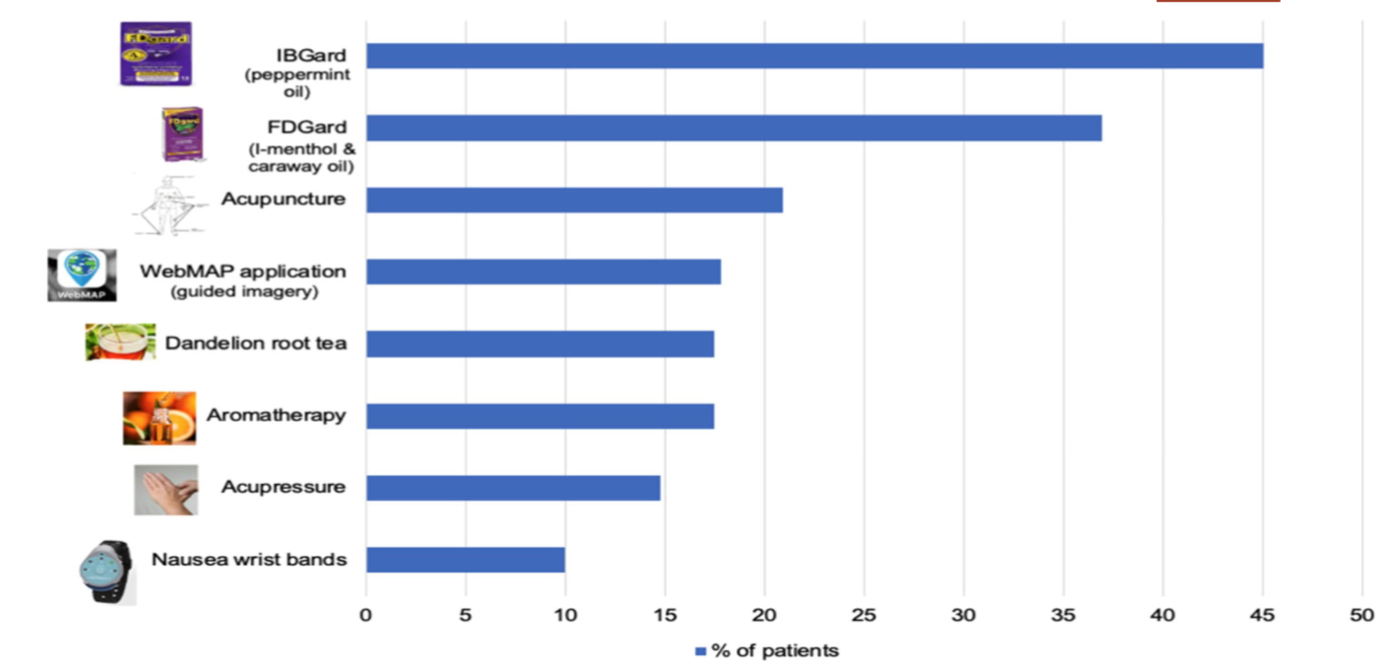
  • In total, 59% of patients were receiving some form of integrative treatment
  • Peppermint oil, caraway oil, and acupuncture were the most used in this practice. 

Limitations: “While this study does identify trends in IM strategies for management of DGBI, it is limited by retrospective design, so identifying use of many IM techniques may be underrepresented (ginger, L-glutamine, aloe vera, etc). These might have been used but were not reported or recorded in charts.”

My take: Whatever you want to call it, complementary, alternative or integrative, it is clear that many patients are using non-traditional therapies trying to improve their symptoms. This cohort may have higher use as they are from a specialty multidisciplinary DGBI clinic rather than a general pediatric gastroenterology or general pediatric cohort.

Related blog posts:

Discordinate Recommendations for Celiac Screening with Down Syndrome

VN Dargenio et al. J Pediatr Gastroenterol Nutr. 2026;83:304–313. A systematic review of celiac disease recommendations for children with Down syndrome

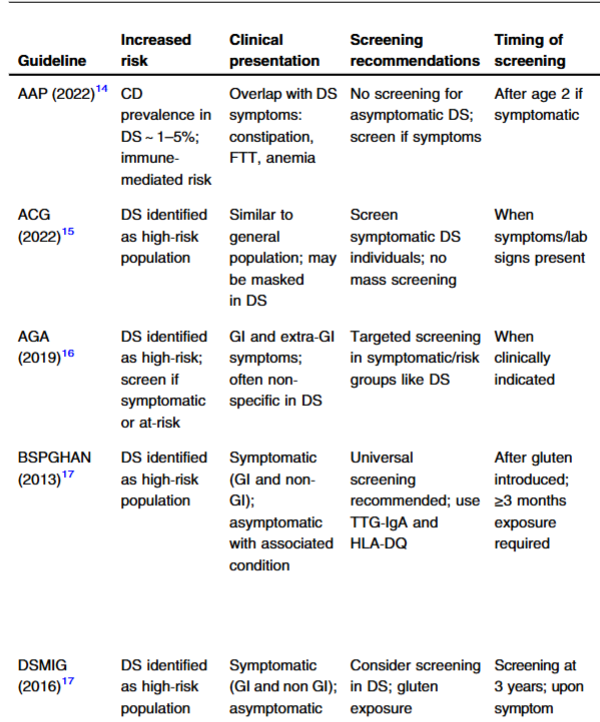
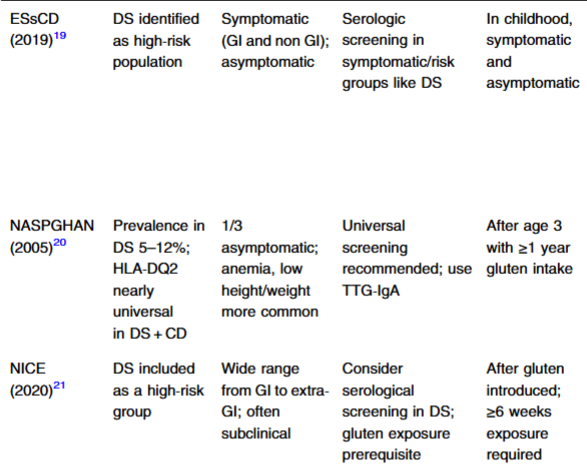
Background: “CD [celiac disease] prevalence in DS is higher than in the general population.10 The overlapping symptoms between CD and DS, such as growth failure, fatigue, GI disturbances, and, less frequently, neurological and behavioral problems, pose significant diagnostic challenges, as these are often attributed to underlying DS comorbidities, leading to delays in recognizing CD.411 

Guidelines:

The authors note wide variation in the prevalence of CD in DS in various studies. “A meta-analysis of 31 studies including 4383 individuals found a pooled prevalence of biopsy-confirmed CD of 5.8% (95% CI 4.7%–7.2%), with slightly higher rates in children (6.6%) compared to mixed-age samples (5.1%)31…these findings align with the 5%–13% prevalence range documented in earlier European studies2

The authors recommend the following strategy:

“Given the high prevalence of asymptomatic and atypical presentations, reliance on symptoms alone is insufficient. A pragmatic strategy should initiate with universal serological screening for all children with DS after gluten introduction (12–24 months of age), followed by periodic re-screening every 2–3 years, using tTG-IgA with total IgA assessment, supplemented by IgG-based assays in the context of the high rate of selective IgA deficiency in DS.”

My take: There are wide discrepancies in the recommendations for screening for celiac disease in asymptomatic individuals with Down syndrome.

Related blog posts:

Evaluation of the Rumination Severity Index (RumSI) and Usefulness for Clinical Practice

JS Khoo, D Yang et al. J Pediatr Gastroenterol Nutr. 2026;83:251–257. The rumination severity index: Development and evaluation of a scoring tool for rumination syndrome

Methods: 66 children with rumination syndrome (RS) completed the 7-item RumSI and PedsQL questionnaires between 2018 and 2023.

RumSI Scoring: Skipped meals, weight loss due to vomiting, and use of a feeding tube or parenteral nutrition were each dichotomized, with absence of the symptom assigned a score of zero for each item and presence of the symptom assigned a score of 1.5σ = 4, where σ is the standard deviation of the combined vomiting/re-swallowing score. Both skipped days of school and social activities in the past 60 days were grouped into categories of 0, 1–4, 5–9, 10–19, 20–39, and 40–60 and assigned integer values of zero to five. The overall RumSI score was calculated by summing the six individual components (vomiting/re-swallowing, skipped meals, weight loss, use of feeding tube or parenteral nutrition, skipped days of school, and skipped days of sports/social activities).

Key Findings:

  • RumSI scores ranged from 0 to 26.5 (mean 10.6 ± 7.2) out of a total possible 28, with higher scores indicating worse rumination symptoms
  • RumSI and PedsQL scores were significantly negatively correlated (r = −0.45, p < 0.001), with every 1-point increase in RumSI score associated with a 1.3-point decrease in PedsQL total score
  • Higher RumSI scores were associated with co-morbid conditions including depression, functional dyspepsia, functional nausea/vomiting, gastroparesis, and postural orthostatic tachycardia syndrome

My take: Currently, the RumSI score would be cumbersome in clinical practice (in the absence of an embedded calculator). However, the questions on the RumSI are very useful and I already made a smartphrase to help capture this information on patients with suspected rumination. Also, the RumSI should be useful for research studies by offering a common scoring system to define and track disease burden.

Related blog posts:

Negative Study: Nortriptyline for Functional Dyspepsia

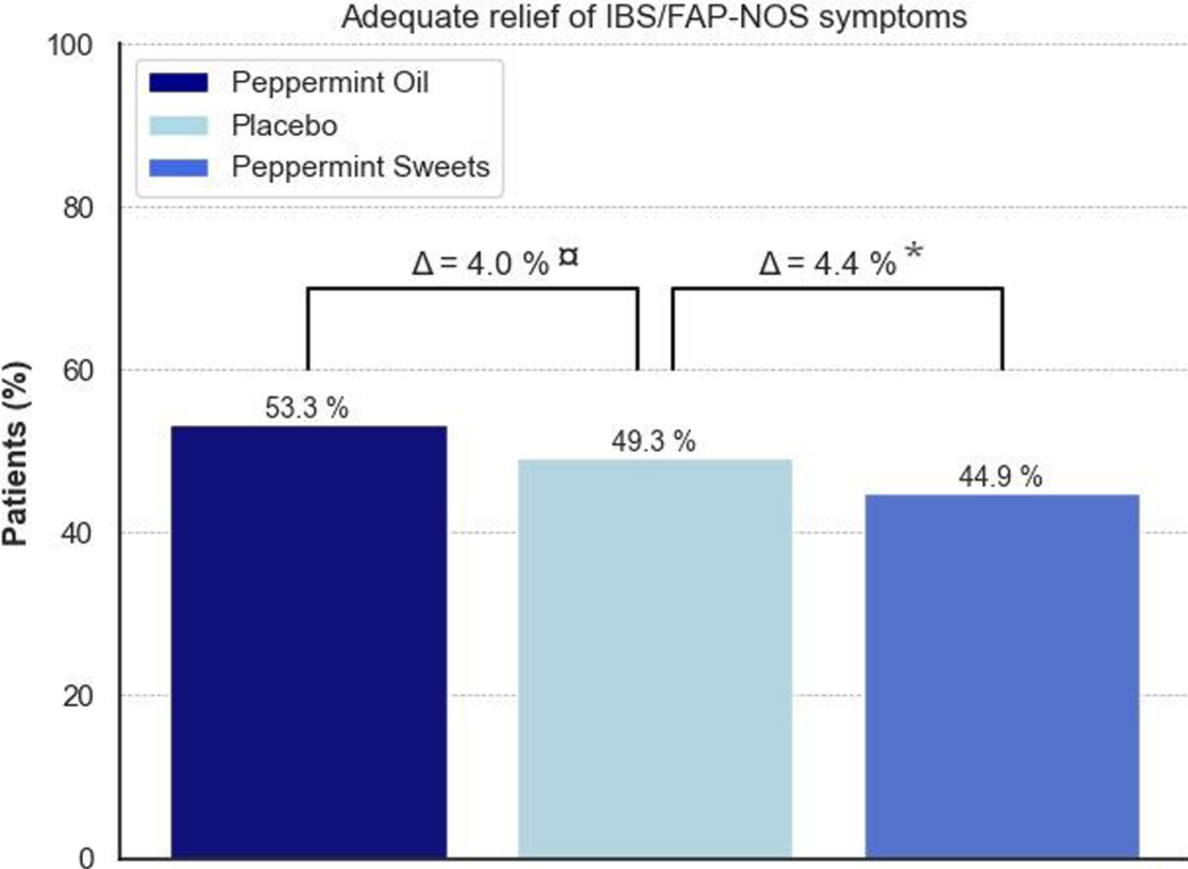
Yesterday’s post showed that peppermint oil/sweets were not superior to placebo for management of pediatric IBS. Today’s study, likewise, shows that nortriptyline was not superior to placebo for functional dyspepsia, another DGBI. At the same time, the trials also showed fairly high response rates along with low adverse effect rate.

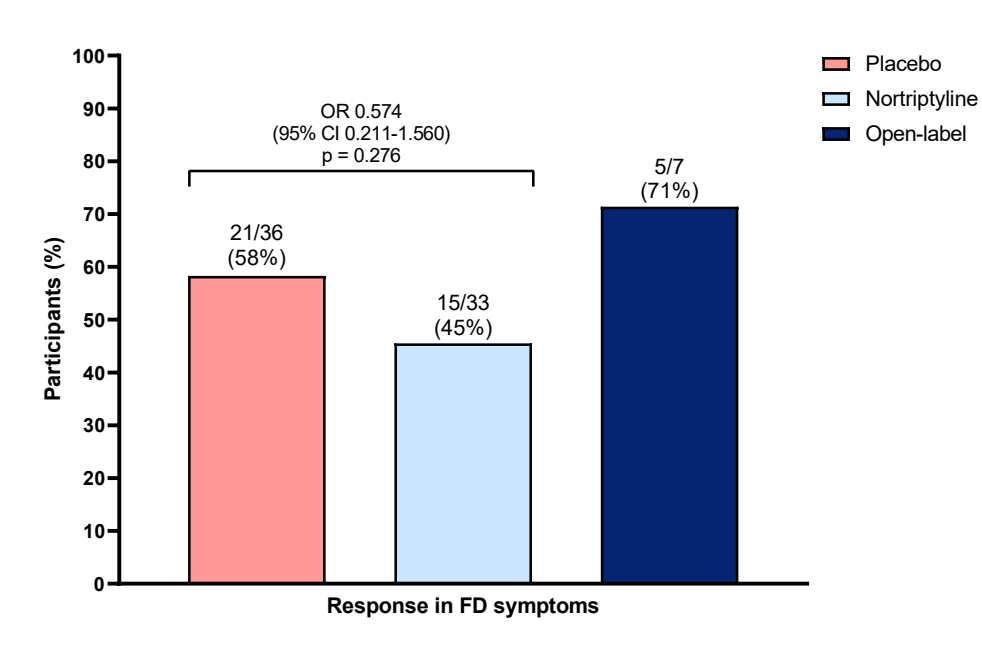
Methods: This was a multicenter, RCT of patients with FD (functional dyspepsia) in primary, secondary, and tertiary care. Sixty-nine participants were randomly assigned to nortriptyline (weeks 1–2: 10 mg; weeks 3–4: 25 mg; weeks 5–12: 50 mg) vs placebo for a 12-week treatment. The primary outcome was clinical response based on a decrease in FD symptoms of at least 30% compared with baseline, in 50% of the last 10 weeks of the treatment period.

Key finding:

  • The primary outcome showed no significant difference in response for nortriptyline compared with placebo (45% vs 58%; odds ratio [OR], 0.574)
  • There was no significant difference in adverse events between the nortriptyline and placebo group
  • Nortriptyline plasma levels were significantly higher in responders compared with non-responders (13.0 μg/L vs. vs 9.0 μg/L; P = .003)
  • The belief to have received nortriptyline showed a higher response rate than the belief to have received placebo (77% vs 36%; OR, 11.439; P = .004)

The accompanying editorial makes several important points:

  • “Placebo response is intrinsic to all DGBI trials. Across pediatric and adult populations, placebo response rates of 30% to 60% are common.3–5 Symptom fluctuation, regression to the mean, expectation bias, and cognitive–affective modulation of visceral perception all contribute. In children, parental expectations and heightened suggestibility may further amplify contextual effects. Nevertheless, they also highlight that placebo effects are an integral part of the therapeutic response seen in DGBI trials and clinical practice.”
  • “Expectancy effects deserve deliberate consideration in both trial design and clinical care. The nortriptyline trial elegantly demonstrated that participants’ belief or expectation about treatment allocation was more strongly associated with response than the medication itself…In clinical practice, clear explanations, symptom validation, confident framing of the treatment rationale, and a strong clinician–patient alliance can ethically harness expectancy and placebo effects to enhance response.6
  • “Neither study suggests that pharmacologic therapy has no role in management. The association between higher nortriptyline plasma levels and response leaves open the possibility that a subset of patients derive biological benefit. Likewise, peppermint oil was safe and well-tolerated. However, these trials caution against overinterpreting modest signals from small or uncontrolled studies and emphasize the importance of adequately powered, methodologically rigorous trials in conditions characterized by high placebo response.”

My take: Rigorous pharmacologic studies show that medications, to date, recommended for patients with DGBIs have difficulty outperforming placebo; yet, there is a high response in patients with DGBIs. In this setting, the use of medications with a low incidence of adverse effects and plausible beneficial effects continue to have a role in improving symptom control.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

A Randoized Trial of Peppermint Oil for Pediatric Irritable Bowel Syndrome

N Vermeijden et al. Clinical Gastroenterology and Hepatology, 2026; 24, 2286-2296. Peppermint Oil and Sweets in Pediatric Irritable Bowel Syndrome and Functional Abdominal Pain: A Randomized Trial

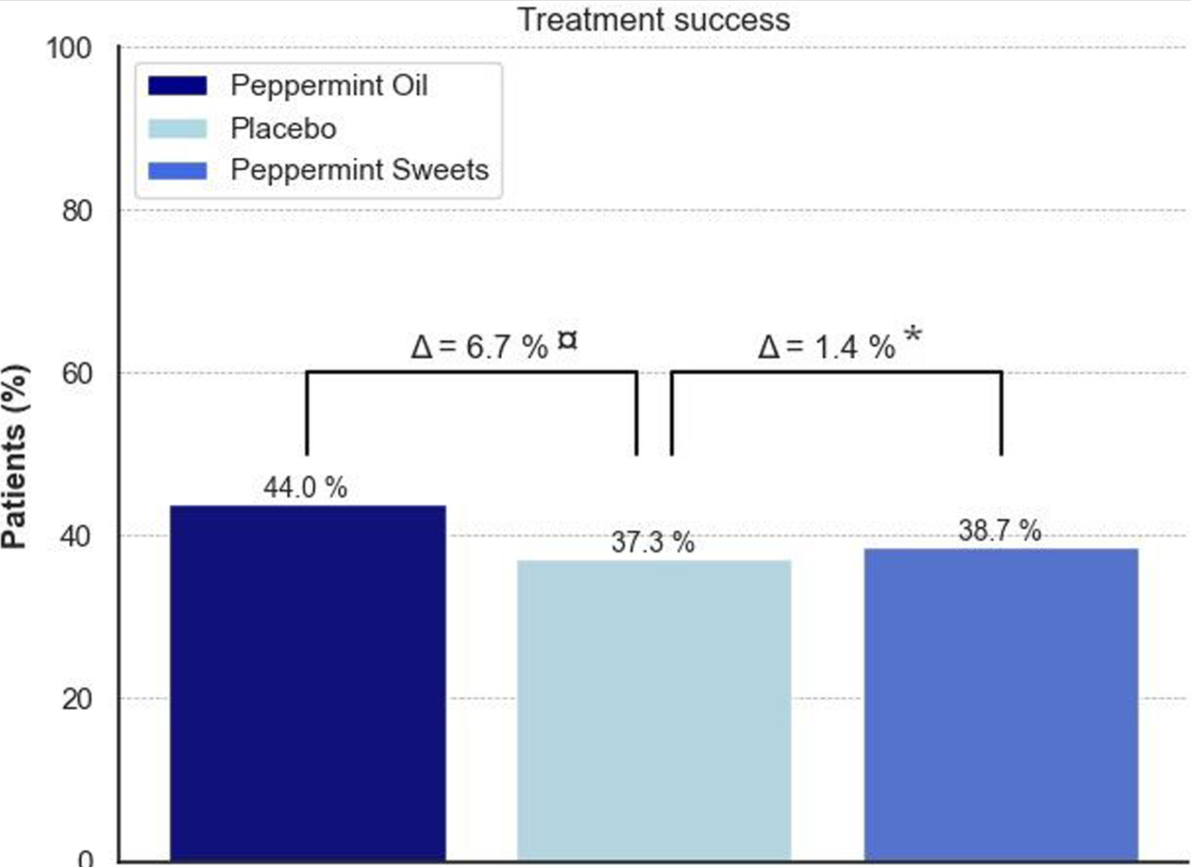
Methods: A large randomized controlled trial evaluated 228 children and adolescents aged 8 to 18 years across multiple hospitals.  The primary endpoint was treatment success, defined as a ≥30% reduction of abdominal pain intensity after 8 weeks. 

Key finding:

  • Treatment success rates—measured as a 30% or greater drop in pain intensity after 8 weeks—were similar for peppermint oil (44.0%), peppermint sweets (38.7%), and placebo (37.3%)

My take: The overall response rate for peppermint oil, peppermint sweets and placebo ranged from 37% to 44%. Given its safety, it should still be considered a useful treatment for pediatric IBS (see more on this tomorrow). It is listed as a recommended therapy in recent guidelines with low evidence of effectiveness.

Related blog posts:

The Safety and Effectiveness of Early Anti-tumor-necrosis-factor Therapy for Penetrating Crohn’s Disease in Pediatrics

BD Constant et al. American Journal of Gastroenterology Publish Ahead of Print, July 1, 2026. | DOI: 10.14309/ajg.0000000000004104. The Safety and Effectiveness of Early Anti-tumor-necrosis-factor Therapy for Penetrating Crohn’s Disease Complications in Children

Methods: This was a multicenter retrospective study examining the safety of anti-TNF therapy in children (n=203) with Crohn’s disease (CD) who developed internally penetrating complications (IPCs; abscesses and inflammatory masses). The exposure timeframe was anti-TNF administration within 30 days of IPC diagnosis.

Key findings:

  • In Cox analyses, early anti-TNF was not linked to infectious serious adverse events (iSAE), noninfectious CD-related SAE, or surgeries, but was associated with increased combined clinical-biochemical-corticosteroid-free remission (hazard ratio 1.65).
  • Surgical risk differed by percutaneous drainage (PD) status: patients receiving early anti-TNF and PD had lower risk versus PD alone (event-free survival 58% vs 15%, log-rank P = 0.04).

My take: For many years, my practice has been to use early anti-TNF even in patients with internally penetrating complications. This study confirms that anti-TNF therapy may be beneficial in this setting.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition