Sodium Bicarbonate Locks to Prevent Central Line Infections

K McNevin, BE Rosete et al. J Pediatr Gastroenterol Nutr. 2026;82:1303–1308. A comparison between sodium bicarbonate and ethanol for central line locks in pediatric patients with intestinal failure

Background: Since 2022, there has been growing interest in the use of sodium bicarbonate locks. This dates back to 2018, when Belcher pharmaceuticals managed to get the FDA to designate Ethanol as an orphan drug with a subsequent increase in cost (at that time) to ~$10,000 for a 10-vial pack (10-day supply) (Related post: FDA ‘Safety Initiative’ Now Means an Ounce of Ethanol Costs $30,000). As such, many (?most) children with intestinal failure (IF) no longer had access to Ethanol Lock Therapy which prevents life-threatening infections to their central lines. Sodium bicarbonate has been shown to inhibit bacterial proliferation by impeding bacterial adherence and preventing biofilm formation.1516 

Methods: A retrospective cohort study was conducted in pediatric patients with IF (19 children who received ethanol locks and 36 with sodium bicarbonate locks) followed by the Intestinal Rehabilitation Program at Seattle Children’s Hospital who received ethanol or sodium bicarbonate locks from 2018 to 2023.

Volume of the lock was calculated based on the documented catheter length when available and by drawing back from the line until blood return was obtained when length unavailable. Ethanol locks were withdrawn from the catheter after the dwell while SBL were flushed.

Key findings:

  • Rates of CLABSI were similar between the ethanol and sodium bicarbonate lock cohorts (2.03 per 1000 catheter days and 1.59 per 1000 catheter days; p = 0.617)
  • The sodium bicarbonate group had a lower rate of line replacement (2.21 in the EL group and 0.00 in the SBL group (p = 0.01) and trended toward a lower rate of line repair with1.94 in the EL group and 1.07 in the SBL group (p = 0.23).

Discussion:

  • “While alternatives exist and may also be effective, SBL has the added benefit of a substantially lower cost. At the time this manuscript was written, based on SCH mediation wholesaler data, the cost of 1 mL of ethanol (Ablysinol®) was $186.66 whereas 1 ml of sodium bicarbonate 8.4% was $0.18.”

My take (borrowed from the authors); Based on these data, SBL should be considered as a primary option for lock therapy in children with IF.

Related blog posts:

Seljalandsfoss in Iceland (attribution: Jennifer Hochman)

Severe Consequences of Pediatric Perianal Crohn’s Disease

A Strom et al. Clin Gastroenterol Hepatol 2026; 24: 1960-1969. Perianal Disease in Pediatric-Onset Crohn’s Disease: Incidence, Disease Course, and Long-Term Outcomes

Methods: In this nationwide Danish registry, a pediatric-onset CD cohort from 1980 to 2022 was identified. Outcomes for patients with and without perianal disease were examined.

Key findings:

  • There were 2356 patients with pediatric-onset CD, of whom 769 (32.6%) developed perianal CD. The cumulative incidence of perianal CD was 14.0%, 21.1%, and 28.1% after 1, 5, and 10 years.  After 30 years, the incidence rate was 45.2%.
  • A stoma was required in 308 (40.1%) and 147 (9.3%) patients with and without perianal disease, respectively (aHR, 2.8).
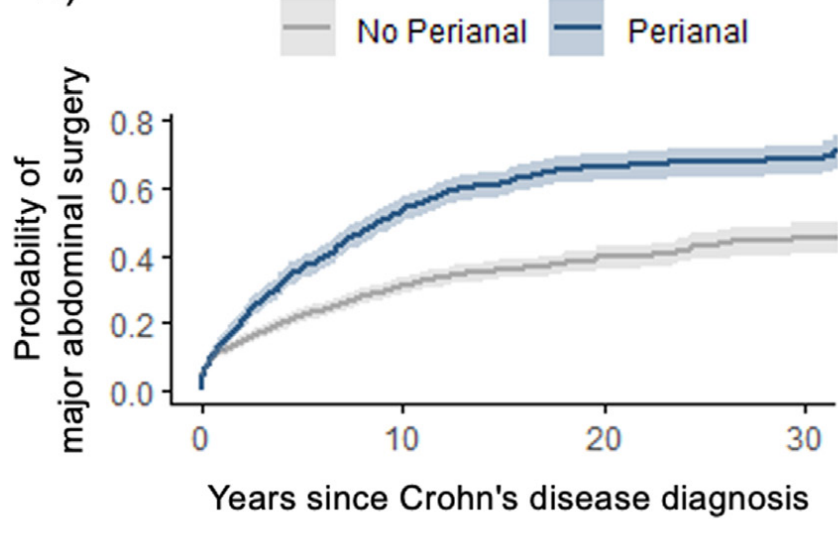
Probability of Major Abdominal Surgery in Patients with and without Perianal Disease
  • When comparing patients with/without perianal disease, the aHR for major abdominal surgery, cancer, and mortality were 1.5, 0.8, and 1.5 , respectively.
Probability of Mortality in Patients with and without Perianal Disease
  • When comparing patients with/without perianal disease, the aHR for mortality was 1.5. Of mortalities, 35 had perianal disease (4.6%; mortality rate, 2.2/1000 person-years) and 33 did not (2.1%; mortality rate, 1.4/1000 person-years). However, the confidence interval was 0.9-2.7) indicating the precision of this finding is low.

Discussion: “In our study, patients without perianal disease were diagnosed with CD more frequently in recent decades than patients with perianal disease. The differences in distribution of CD diagnosis over calendar years may be due to shorter follow-up among patients diagnosed with CD in recent decades, improved treatment delaying disease progression, and increased detection of milder CD phenotypes over time.”

My take: This study reinforces and quantitates the view that having perianal Crohn’s disease portends an increased risk for severe complications. With improving treatments, perhaps the outcomes will be more favorable now and in decades hence.

Related blog posts:

Use of Proton Pump Inhibitors in Infants

M Lassalle, et al. The Journal of Pediatrics: Clinical Practice 2026; 21: 200214. Open Access! Use of Proton Pump Inhibitors in Infants: Nationwide Cohort Study Based on the French EPI-MERES Register

Methods: This studied children born between 2010 and 2021 using the French National Health Data System registry (EPI-MERES). PPI use was identified through prescriptions before age 1 year.

Key findings:

  • There were 703,891 PPI users among the 8,222,100 children included.
  • The incidence of PPI use was 54.4 per 100 person-years among children with hospital-diagnosed gastroesophageal reflux disease (GERD) (+ 33.6% between 2010 and 2021), and 7.9 per 100 person-years in those without (+ 63.6%).
  • PPI use was associated with extreme prematurity (aOR=1.91), digestive diseases (aOR=5.60), respiratory diseases, aOR, 2.73, neurological diseases (aOR=1.59), and with high maternal socioeconomic level (first quintile of deprivation index [least deprived] vs fifth quintile [most deprived] (aOR=1.80)
  • The median age at initiation of PPI treatment decreased over time, supporting the idea that PPI use may have become more commonplace.

Discussion:

  • The presence of underlying diseases may increase the use of PPIs as it is “consistent with the hypothesis that more frequent interactions with the healthcare system may be closely associated” increased prescriptions of PPIs.
  • Potential adverse PPI effects: “Early life PPI exposure has been associated with an increased risk of respiratory and gastrointestinal infections. [Also, there are] associations with immune-mediated diseases potentially mediated by microbiome alterations, including asthma,25,26 allergic disorders,26,27 and inflammatory bowel disease.28
  • “PPI use in children aged <1 year may be appropriate, especially for esophagitis,1 but is not needed if the symptoms do not interfere with growth and development,1 and there is no evidence supporting empirical PPI therapy for diagnosing GERD in infants.1

My take: This study shows that PPI use before age 1 has increased sharply in France since 2010. This coincides with high usage in infants elsewhere despite lack of proven efficacy. However, a recent study from Boston showed a declining trajectory of PPI use (see related posts). This indicates that a consistent message that most infants should not be treated with PPIs may be effective.

Related blog posts:


Transnasal/Transoral Endoscopy May Be Better Suited For Adults

V Patel et al. JPGN Rep. 2026; 1-6doi:10.1002/jpr3.70220. Open Access! Use of single-use ultra-slim endoscopes for evaluation of pediatric esophageal varices: A pilot feasibility study

*Two of the study authors have financial ties to the manufacturer of the ultra-slim endoscopes.

Methods: Ten pediatric subjects (including one that was 2.9 years of age) with suspected or known esophageal varices (EV) underwent surveillance endoscopy using the ultra-slim endoscope (transoral or transnasal endosocpy [TNE]) followed by the standard gastroscope under sedation. Esophageal findings were analyzed using images from both procedures by two independent endoscopists. 

Key findings:

  • EV were identified in 8/10 subjects (Grade I (4), Grade II (3), and Grade II/III (1))
  • Endoscopic grading matched between both endoscopes in 7/8 (87.5%) cases
  • Three subjects required endoscopic intervention with either sclerotherapy (n = 1) or band ligation (n = 2)
  • Limitation: High risk stigmata of recent bleeding such as red wale signs or fibrin plugs were not assessed and documented in this study. These features are important for risk stratification; thus, understanding whether the ultra-slim endoscope reliably identifies these stigmata is needed

In the discussion, the authors note that “our study demonstrates the potential for considering TNE for EV evaluation in a lower cost, lower acuity setting.” In my view, this is a flawed argument, particularly in pediatrics.

  1. For varices, many of the children need therapeutic endoscopic intervention. Thus, outside of a study design, this requires an additional procedure (and additional cost).
  2. In pediatric gastroenterology, most clinicians do their endoscopic procedures in a hospital-based setting and/or in affiliation with hospitals. While this can provide additional safety for risky procedures, this drives up costs. In fact, this study which promotes TNE for cost savings does not report the anticipated costs. However, in a previous study, the cost of TNE exceeded that of a standard endoscopy (including anesthesia) in an endoscopy center. Though, the cost of TNE was less than a standard hospital-based endoscopy (Related blog post: Transnasal Endoscopy in Unsedated Children to Monitor Eosinophilic Esophagitis).

My take: This technology would be better suited for adults with eosphageal conditions. First of all, most adult GI physicians are not employed by hospitals. Thus, there is a much greater likelihood of cost savings. Secondly, avoiding an additional day missing work is usually a bigger factor for adult patients. However, if there is a need for preauthorization for reimbursement of the procedure, this could negate this potential benefit as well.

Related blog posts:

Beached Fishing Boats by Jules Achille Noel, The Art Institute of Chicago

Discordant Clostridiodes difficile Testing In Patients with Inflammatory Bowel Disease

P Ramakrishan et al. Inflamm Bowel Dis 2026; 32: 1313–1320. Discordant Clostridioides difficile testing as a predictor of inflammatory bowel disease therapy escalation

Background: “In the general population, individuals with discordant tests (PCR+/TOX−) have similar outcomes to PCR− individuals, suggesting that this group represents individuals colonized with C. difficile.[14]”

Methods: In this retrospective study (n=117), outcomes assessed included CDI-directed therapy or escalation of IBD treatment.

Key findings:

  • 79% (93/117) were PCR+/TOX and 21% (24/117) were PCR+/TOX+
  • PCR+/TOX+ patients had significantly higher CRP (98 vs 6 mg/L, P = .005)
  • PCR+/TOX patients had more severe underlying IBD and higher rates of steroid use (48% vs 21%, P = .02) and were significantly more likely to require IBD therapy escalation (54% vs 25%, P = .004). Multivariable analysis showed PCR+/TOX status (odds ratio [OR], 3.2) was a significant predictor of IBD treatment escalation. Antibiotic use did not significantly alter the need for escalation among PCR+/TOX  patients.

Discussion:

  • “Most IBD patients who are PCR+/TOX  are colonized with C. difficile, and IBD treatment could be considered rather than delaying for CDI therapy.”

My take: In patients with IBD, PCR-positivity for C diff is frequently a false positive due to high rates of colonization in this population. Patients who have their infection confirmed with an immunoassay are much more likely to respond to C diff therapy.

Related blog posts:

Resources:

National Civil Rights Museum in Atlanta, GA. One of the powerful exhibits is a Woolworth lunch counter replica with headphones.  With your eyes closed, the exhibit challenges you to keep your hands on the counter as one receives menacing threats like ‘Boy, I’m going to kill you.’ 

Confusing Guidance and “Conditional” Recommendations for Probiotic Use in Pediatric Irritable Bowel Syndrome and Functional Abdominal Pain

R Francavilla et al. J Pediatr Gastroenterol Nutr. 2026;83:3–6. Open Access! From evidence to advice: How uncertainty shapes probiotic guidance in pediatric irritable bowel syndrome

Key points:

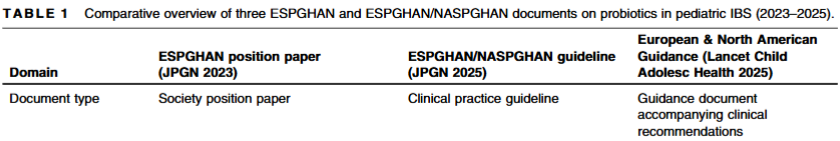
  • “Recent guidance documents of the European Society for Paediatric Gastroenterology Hepatology and Nutrition (ESPGHAN) and North American Society for Pediatric Gastroenterology, Hepatology and Nutrition (NASPGHAN) on probiotic use in pediatric irritable bowel syndrome (IBS) do not simply converge toward a shared recommendation.13 Rather, they illustrate an evolution in how scientific uncertainty is operationalized in clinical advice. “
  • “The ESPGHAN Position Paper Probiotics for the Management of Pediatric Gastrointestinal Disorders represents the most structured approach among the three documents, treating probiotics as strain-specific interventions evaluated against predefined clinical outcomes.1 In functional abdominal pain disorders, healthcare professionals may recommend Limosilactobacillus reuteri DSM 17938 to reduce pain intensity, while in pediatric IBS Lactobacillus rhamnosus GG may be recommended to reduce pain frequency and intensity. These recommendations are accompanied by explicit dosing ranges, defined clinical targets, and formal appraisal of evidence certainty (moderate) and strength of recommendation (weak).”
  • “The joint ESPGHAN/NASPGHAN guideline on treatment of IBS and functional abdominal pain—not otherwise specified in children aged 4–18 years represents a shift in emphasis.2 L. rhamnosus GG is conditionally suggested as a therapeutic option for pediatric IBS, supported by moderate overall certainty of evidence and a small, reported effect size. Multistrain probiotics and synbiotics are likewise framed as options that may be suggested, but with low certainty of evidence. In contrast to earlier ESPGHAN position papers, the guideline does not specify detailed dosing regimens, treatment duration, or stopping rules.”
  • “This reframing extends further in the European and North American guidance addressing IBS and functional abdominal pain in childhood.3 …Within this framework, probiotics are positioned less as therapies to be prescribed and more as adjunctive measures to be discussed with families, including in primary care settings.”

Conclusions from authors: “At a policy level, conditional recommendations do not operate in a neutral context…Probiotics are widely available, variably regulated, and commonly perceived as harmless. In pediatric IBS, where symptoms are chronic, placebo responsiveness is high, and pharmacological options are limited, conditional guidance may be interpreted as tacit approval for routine use, regardless of modest effect sizes…their use may drift from deliberate intervention toward habitual supplementation.”

My take: I rarely recommend probiotics for pediatric IBS. Even simple dietary changes are much more likley to be beneficial. In addition, there is a concern about the lack of quality control in the production of probiotics.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Guidelines for Hirschsprung’s Disease

D Rossi et al. J Pediatr Gastroenterol Nutr. 2026;83:185–207. Open Access! Updated European Reference Network for rare Inherited and Congenital Digestive and Gastrointestinal Anomalies guidelines for the management of rectosigmoid Hirschsprung’s disease 2025

These guidelines cover recommendations for diagnosis, pre- and postoperative care, poor functional outcomes, long-term follow-up, and Hirschsprung’s-associated enterocolitis.

Some specific recommendations:

Diagnosis:

Preoperative Care:

  • Routine screening for all patients with rectosigmoid Hirschsprung’s disease (HSCR))with ultrasound for congenital anomalies of kidney and urinary tract (CAKUT) and systematic assessment of nutritional status.

Operative Care:

Hirschsprung’s-Associated Enterocolitis:

  • Table 9 provides extensive advice for bowel management strategies/evaluation in children with fecal incontinence.
  • Table 11 discussed genetic testing, noting that RET gene should be considered. Genetic counseling is recommended in those patients with a family history of Hirschsprung’s disease.

My take: This article provides good advice for optimizing care for patients with Hirschsprung’s disease.

Related blog posts:

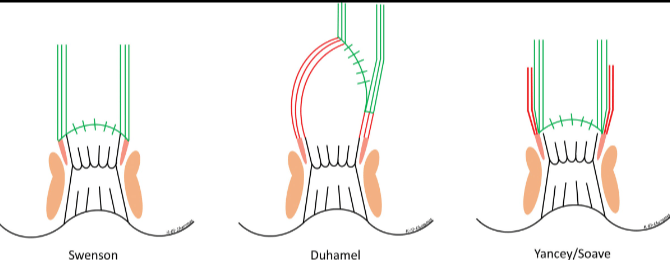
Diagrams of 3 common pull-through operations for Hirschsprung disease.
From left to right: full-thickness rectosigmoid dissection (Swenson), a recto-rectal pouch procedure (Duhamel), and an endorectal dissection (Soave). JPGN 2023; 76(4):533-546.

Impact of 5‐Aminosalicylic Acid Discontinuation in Children with Ulcerative Colitis Receiving Biologic Therapy

G D’Arcangelo et al. J Pediatr Gastroenterol Nutr 2026; 83: 96-107. Open Access! Impact of 5-Aminosalicylic acid discontinuation in children with ulcerative colitis on biologic therapy: A propensity score-matched study

Background: Several adult-based studies have found that discontinuing 5-ASA at the initiation of anti-TNF therapy is not associated with worse clinical outcomes. “Ungaro et al. analyzed data from over 3500 patients in the United States and Denmark and found no increased risk of adverse outcomes following mesalamine discontinuation after the initiation of anti-TNF therapy.18 Based on this evidence, the American Gastroenterological Association recommends discontinuing mesalamine in patients with moderate-to-severe UC who are starting biologics or small molecules and achieve remission.19 However, this recommendation is based on low-quality evidence, and pediatric guidelines do not offer a similar directive.2

Methods: Retrospective, multicenter, case–control study which included 227 pediatric patients in the final analysis after matching (85 [37.5%] cases and 142 [62.5%] controls].

Key findings:

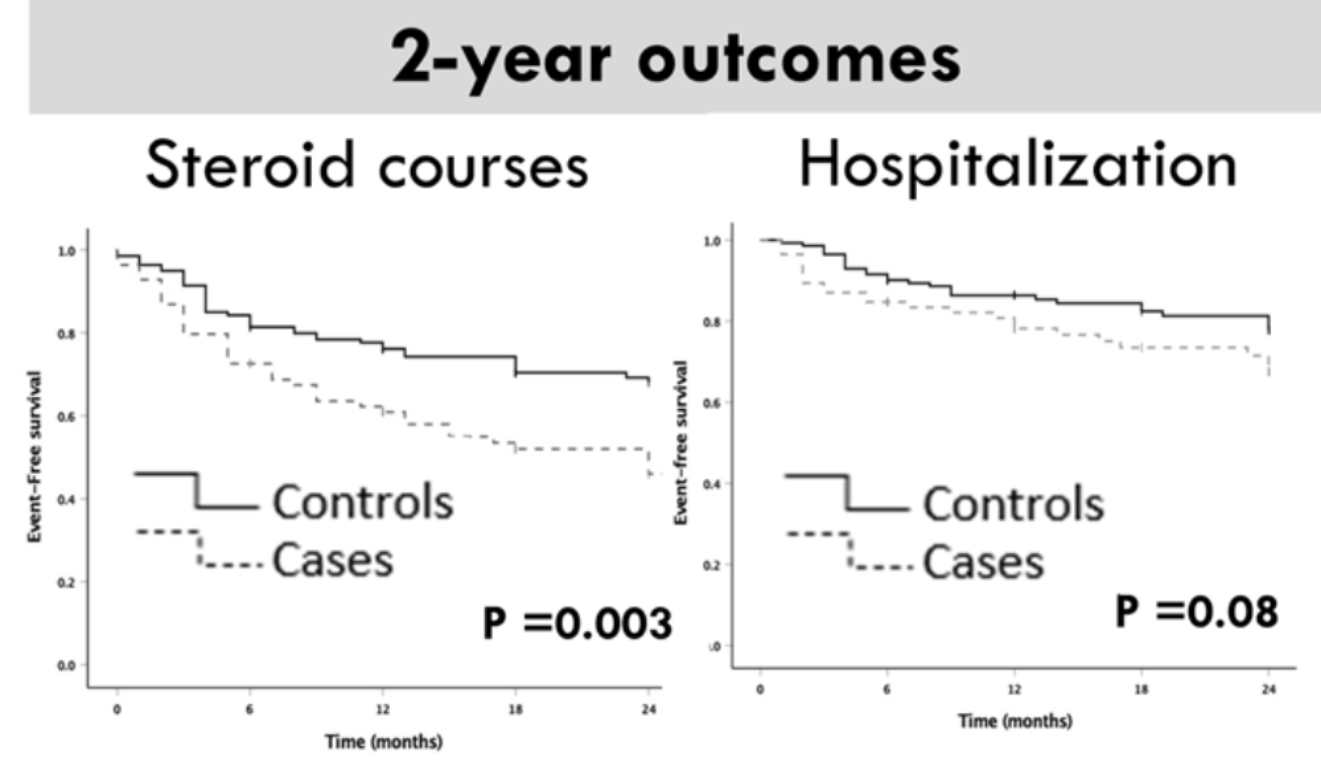
  • Children who discontinued 5-ASA were at higher risk of courses of steroids (Log-Rank p = 0.003) and hospitalization (p = 0.08). This finding persisted with multivariate Cox regression analysis.
  • “Fixed timepoint analyses showed a statistically significant increase in the odds of adverse outcomes at the 6-month follow-up (including hospitalizations and acute severe colitis), with no significant differences detected at 12, 18, or 24 months, and only a non-significant trend toward higher hospitalization risk over time.”

My take: This is an intriguing study with a small sample size of pediatric IBD patients. Given the findings in adults, it is customary to stop 5-ASA at the time of initiation of biologic therapy. However, this study indicates that pediatric patients—who often present with more extensive and severe disease—may have some benefit from overlapping these therapies, especially during the first six months. A prospective pediatric study would be helpful.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Elevated Amylase is Common in Pediatric Patients with Inflammatory Bowel Disease

F Vázquez López et al. J Pediatr Gastroenterol Nutr. 2026;83:79–86. Hyperamylasaemia in paediatric inflammatory bowel disease: Aetiology, outcomes and genetic determinants

Methods: This was a retrospective study with 334 pediatric patients, followed for ≥2 years (study duration was 7 years). Elevated amylase was considered to be above the laboratory’s reference range (102 U/L).

Key findings:

  • Hyperamylasaemia was found in 62/334 patients (18.6%), with 29% of these presenting at diagnosis
  • Hyperamylasaemia resolved in 77% of patients; in the majority (85%), spontaneously and in the remainder after medication withdrawal
  • One patient developed acute pancreatitis and one had recurrent pancreatitis

My take: It is best to avoid routinely checking an amylase if pancreatitis is not suspected; it could lead to ‘a wild goose chase.’ Most cases of elevated amylase are benign and self-limiting.

Related blog posts:

A deer in the middle of the Chattahoochee at Island Ford

Sheila McBrayer: Swallow Dysfunction and Swallow Evaluation in Infants

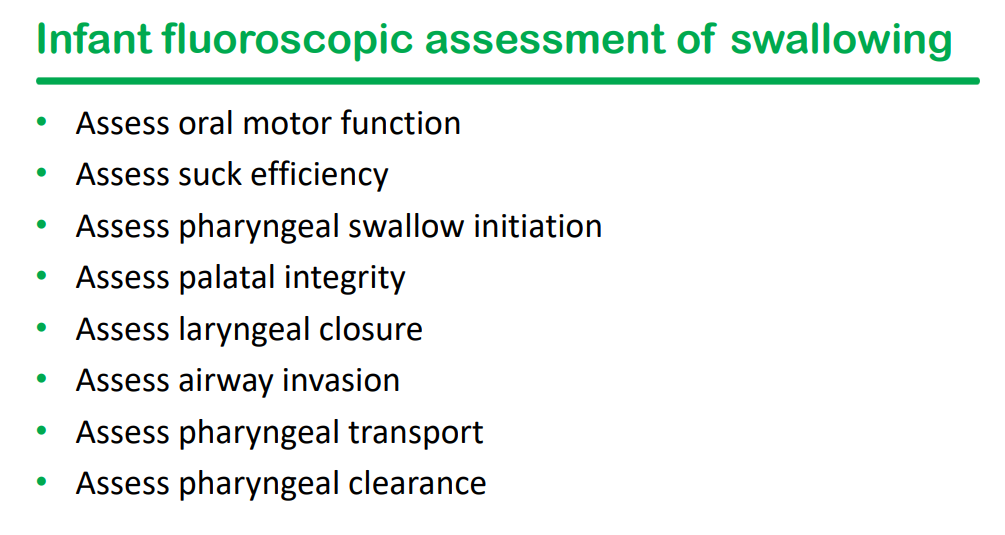
Recently, Sheila McBrayer SLP gave our group a terrific update on swallow dysfunction and swallow studies in infants. She is a nationally-certified speech-language pathologist with more than 20 years of experience at Children’s Healthcare of Atlanta. She has led initiatives in advanced swallowing assessment, worked to standardize instrumental swallowing assessments across the hospital campuses, and presented at regional and national conferences on NICU feeding topics. My notes below may contain errors in transcription and in omission. Along with my notes, I have included many of her slides.

Key points:

  • Video fluoroscopic swallow study )VFSS) is preferred nomenclature over modified barium swallow (MBS) or oral pharyngeal motility study (OPMS)
  • Study duration is important.  Watch swallow for 2:30 minutes if feasible (KE McGrattan, et al Ped Radiology 2020; 50: 199-206)
  • Clinical evaluation accurately identifies aspiration in 56.7% in one study (may be better in a lower risk population).  Thus, if concerned about aspiration, an objective study (e.g. VFSS) is needed
  • Analysis of sounds during feeding may provide insight into risk of aspiration
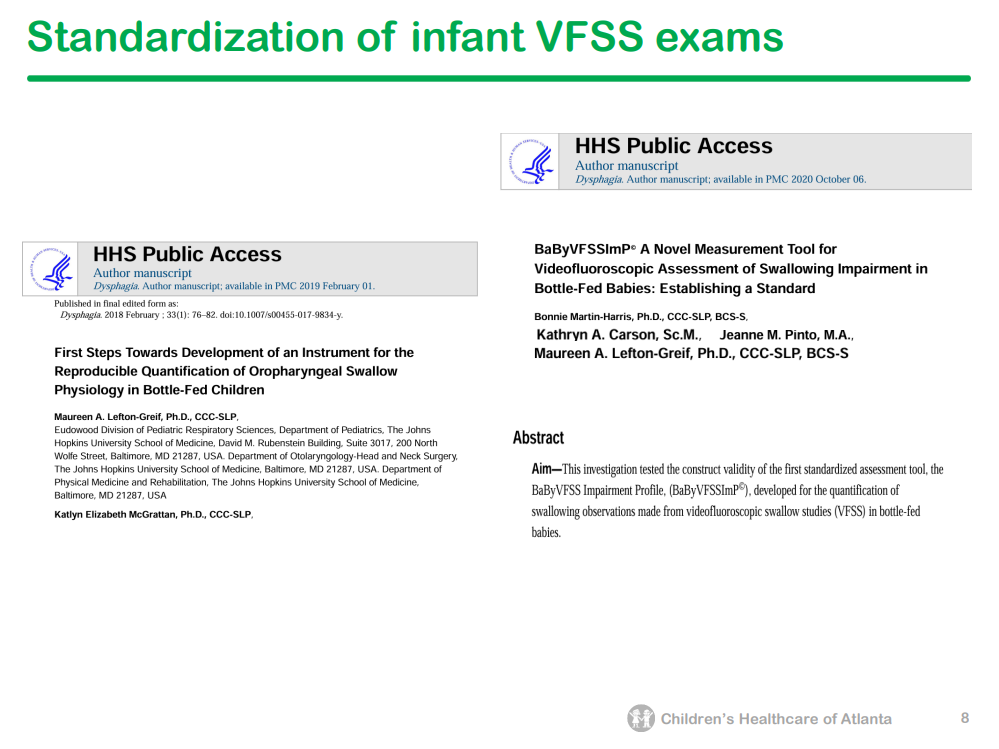
  • Ongoing efforts to standardize evaluation protocol.  BaByVFSSimP tool (for bottle feeding)
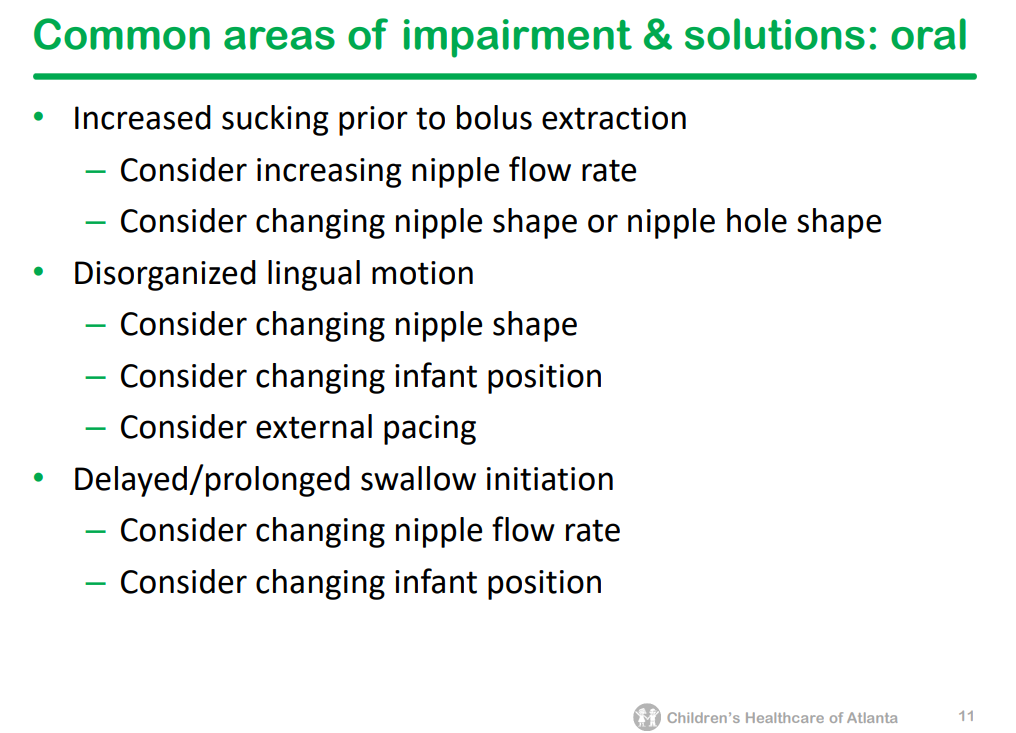
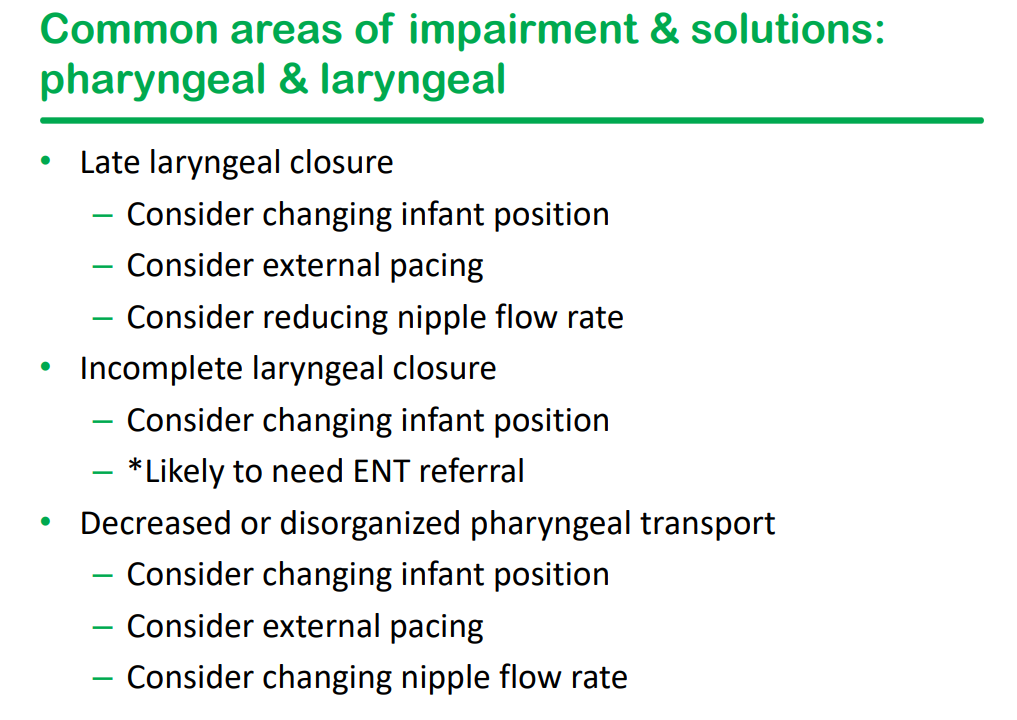
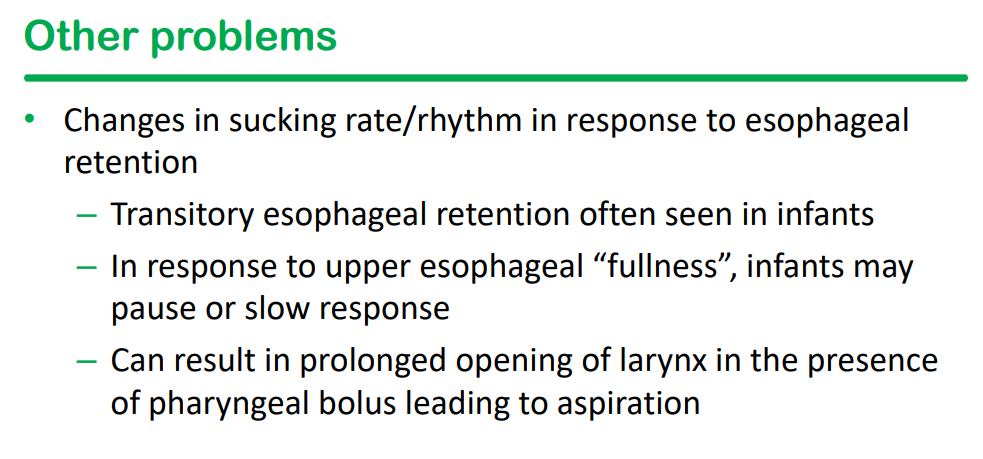
  • Common impairments: increased sucking prior to bolus movement, disorganized lingual motion, late/incomplete laryngeal closure, disorganized or decreased pharyngeal transport, esophageal retention, and suck-swallow ratio variability
  • If unilateral cord dysfunction, feed infant with position to allow the better functioning vocal cord to be lower
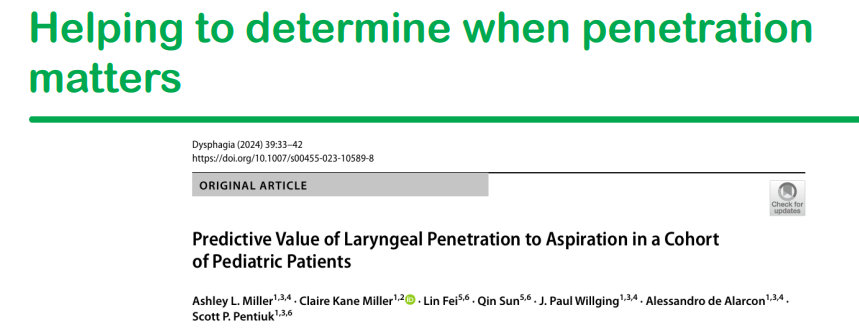
  • When to care about penetration: deeper (e.g. touching vocal folds) and more frequent penetration.  Deeper penetration should be considered as similar risk as aspiration on swallow study
  • Thickening feeds can be difficult

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition