IBD ‘Pearls’

A clinical pearl is “a short, straightforward piece of clinical advice.” Here are a few:

2015 DDW abstract –#536 DR Hoekman et al “Non-trough IFX concentrations reliably predict trough levels and accelerate dose-adjustment in Crohn’s disease.”  This abstract examined data from 20 CD patients.  The authors noted that infliximab concentrations of 15 mcg/mL or higher at week 4 and 7.5 mcg/mL or higher at week 6 appeared to predict trough concentrations of 3 mcg/mL or higher at week 8.

U Kopylov et al. Inflamm Bowel Dis 2015; 21: 1847-53.  This nested case control study identified 19,582 eligible patients.  Key findings:

  • Treatment with thiopurines for more than 5 years did not increase the risk of lymphoma, melanoma or colorectal cancer.
  • There was an association between thiopurine use and nonmelanoma skin cancer (OR 1.78).
  • No association was found between the risk of the evaluated malignancies and anti-TNFα medications

K Huth et al. Inflamm Bowel Dis 2015; 21: 1761-68. This prospective cohort study completed over 2 successive influenza seasons showed that offering education and access to vaccination improved rates of vaccination from 47% (2011-12) to 75% (2013-14).  The education module is available: www.cheo.on.ca/en/IBDflu

KH Katsanos et al. “Review article: non-malignant oral manifestations in inflammatory bowel disease” Aliment Pharmacol There 2015; 42: 40-60. (Thanks to Ben Gold for this reference). This review article provides extensive information about oral lesions in IBD, differential diagnosis, numerous pictures, and management recommendations.  Some oral lesions are directly related to IBD, others can be induced by vitamin deficiencies or by medications.

One of my pet peeves -I avoid using straws

One of my pet peeves -I avoid using straws.  I heard this statistic several years ago and also see too many littered straws.

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
Nutrition Symposium Georgia AAP (Part 1)

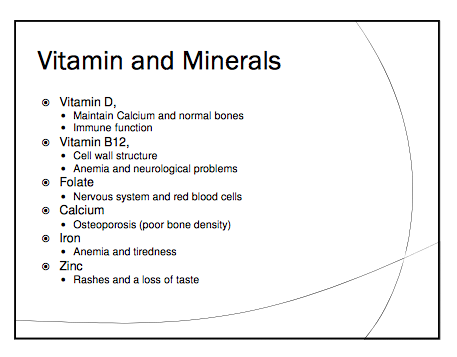
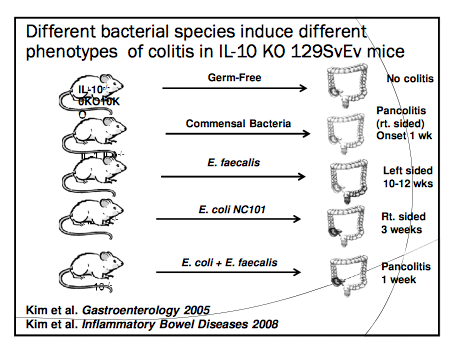
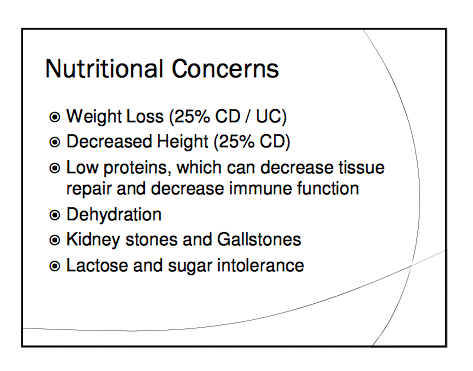
At this year’s nutrition symposium, Dr. Stan Cohen presented the latest information on nutrition and inflammatory bowel disease.  His entire presentation will be on the Nutrition4Kids website.  While I took a few pictures, my notes from his presentation were minimal, mainly because I had to give a talk afterwards.  He reviewed how the microbiome can be influenced by diet and that this in turn can result in phenotypic changes.  Specific complications from poor diet/nutrient deficiencies were discussed.  In addition, data from exclusive enteral nutrition and the specific carbohydrate diet were presented. Here are some slides from his lecture (also available at Georgia AAP Symposium Website):

Screen Shot 2015-11-13 at 5.55.55 PM

Screen Shot 2015-11-13 at 5.57.12 PM

Screen Shot 2015-11-13 at 5.57.27 PM

Screen Shot 2015-11-13 at 6.01.10 PM

Related blog posts:


Why the Genetics of Inflammatory Bowel Diseases Matter Now

A terrific update on the genetics of inflammatory bowel diseases (DPB McGovern, S Kugathasan, JH Cho. Gastroenterol 2015; 149: 1163-76) explains why and how this information matters right now.  The article is a little difficult to read due to its review of highly technical material.

Here’s what I think were the key points:

  • Big advances in understanding the genetics started with the first genome-wide association studies (GWAS) using genome-wide single nucleotide polymorphisms (SNP) chips in 2005.  “The conceptual basis of GWAS is that most complex (ie, not single-gene Mendelian) genetic disorders are polygenic, being driven by multiple common genetic polymorphisms.”
  • “Early GWAS identified the most significant loci.”  Now, more than 200 loci associated with IBD have been identified with GWAS and Immunochip data. Table 1 lists these loci over 4 pages.  About 2/3rds of these are associated with Crohn’s disease (CD) and ulcerative colitis (UC) whereas the remaining 1/3rd are unique to either CD or UC.
  • These loci provide insight into disease mechanisms. NOD2 mutations result in “impaired activation of NF-κB” This supported “the general concept that deficiencies of innate immune cell function represent a central factor in Crohn’s disease, distinguishing it from ulcerative colitis.”
  • ATG16L1 gene mutation “establish the fact that the CD risk allele is correlated with impaired autophagy.”  This is leading directly into treatment efforts.
  • IL23R.  “The most significant association is Arg381Gln…confers a 2- to 3-fold protection against development of IBD.”  The protective effect is thought to be due to “decreased numbers of interleukin (IL)-23 dependent CD4+ Th17 and CD8+ Tc17 cells…decreasing IL-23 signaling, such as through monoclonal antibody blockade of anti-p40 or anit-p19 may be beneficial.”
  • FUT2 mutations.  These mutations affect the mucus layer in Crohn’s disease.
  • Studies in non-Caucasians highlight other susceptibility regions.
  • “Currently, sequencing of the whole exome has become not only a practical method but also a cost-effective option to identify functionally relevant variants in the protein encoding regions of the genome.”

Very Early Onset IBD:

  • Whole exome sequencing (WES) identified XIAP (X-linked inhibitor of apoptosis) in a case of boy with very early onset (VEO) IBD.  XIAP is a positive regulator of NOD2 function.  WES has also identified FOXP3, and IL10RB genes.
  • “The VEO group experiences a more severe disease course and more frequently shows a positive family history for IBD in support of higher genetic load.”  Table 2 lists ~40 genes associated with VEO.  These genes are involved in epithelial barrier function, neutropenia/defects in phagocyte function, hype-and autoinflammation, and  regulatory T cells and immune regulation.

Genetic Testing Will Impact Current Therapies and Help Explain Extraintestinal Manifestations:

  • Currently testing for TPMT variations is recommended prior to use of thiopurines due to concerns of toxicity in individuals with decreased metabolism of these medications.  However, genetic testing can identify other individuals with propensity to leukopenia (eg. NUDT15 polymorphism) and those with increase risk for pancreatitis (eg. HAL-DQA1-HLA-DRB1)
  • Primary Sclerosing Cholangitis (PSC) is associated with numerous genetic loci as well. PSC “genetically is more similar to UC than to CD.” Most other extraintestinal manifestation studies have been underpowered.
  • IBD share more genetic similarity to spondyloarthropathy (SpA) than any other immune-mediated diseases.  “The vast majority of shared susceptibility loci are concordant between IBD and SpA.”
  • With regard to psoriasis, the genetic relationship to IBD is complex.  Anti-TNF agents can cause psoriaform lesions in IBD patients.  In addition, anti-IL17a therapy, “so successful in psoriasis, appears to worsen Crohn’s disease” but not in those with a TNFSF15 variant.  Specific genotyping may help identify which patients with CD are susceptible to psoriaform lesions and those who may improve with therapy typically given for psoriasis.

My take: This article shows how understanding genetics of IBD is providing insight into pathophysiology and more personalized treatment approaches.

Briefly noted: EM Stoffel, CR Boland. Gastroenterol 2015; 149: 1191-1203. Excellent review of the genetics and genetic testing for Hereditary Colorectal Cancer.  The review includes polyposis syndromes and Lynch syndrome.

Atlanta Botanical Gardens

Atlanta Botanical Gardens

Just Saying…Vaccines Don’t Trigger Inflammatory Bowel Disease

The other day I was having a fun discussion on words that we may choose before providing information that others might not like.  Some examples:

  • “No offense but”…
  • “Don’t take this the wrong way”…
  • “Just saying”…

A recent report (GP de Chambrun et al. Clin Gastroenterol Hepatol 2015; 13: 1405-15) debunks claims that vaccines increase the risk of inflammatory bowel disease (IBD).  A report by Thompson NP et al (Lancet 1995; 345: 1071-74) suggested that measles vaccination could increase risk of IBD.  In the current study, the researchers examined 11 previous studies for review and meta-analysis.  Vaccines included: BCG, DPT, smallpox, poliomyelitis, pertussis, H1N1,measles, mumps, rubella, and combined MMR.  This study included 2399 patients with IBD and 33,747 controls. Bottomline: “Results of this meta-analysis show no evidence supporting an association between childhood immunization or H1N1 vaccination in adults and risk of developing IBD.” With regard to the measles vaccine in particular, the relative risk was 1.33 (CI 0.31 -5.80) in cohort studies and the relative risk was 0.85 (CI 0.60 -1.20) in case-control studies.

What types of words do you hear people use before saying something someone is not going to like?

Related posts:

1000th Tweet: GI Symptoms Preceding IBD Diagnosis

Another milestone for this blog: since 2012, the blog has been publicized on twitter; this is the 1000th tweet. It is also 1314th blog post over nearly 4 years.

A recent study (H Singh et al. Clin Gastroenterol Hepatol 2015; 13: 1302-09) indicates that children with inflammatory bowel disease (IBD) were more likely to have gastrointestinal symptoms in each of the 4 years before the diagnosis of IBD than children without IBD.

In this study, the researchers identified all children with IBD from a population-based Manitoba database; Manitoba had a population of 1.27 million in 2012.  651 children were matched with 5950 controls without IBD.  The study’s Table 1 & 2 indicates that children with IBD had increased clinic visits prior to diagnosis:

  • 54-66 months prior: standardized rate ratio for number of ambulatory visits 1.15; & for ≥1 visit due to GI symptoms odds ratio 1.44
  • 42-54 months prior: standardized rate ratio for number of ambulatory visits  1.22; & for ≥1 visit due to GI symptoms odds ratio 2.05
  • 30-42 months prior: standardized rate ratiofor number of ambulatory visits 1.19; & for ≥1 visit due to GI symptoms odds ratio 2.16
  • 18-30 months prior: standardized rate ratio for number of ambulatory visits 1.23; & for ≥1 visit due to GI symptoms odds ratio 2.93
  • 6-18 months prior: standardized rate ratio for number of ambulatory visits  1.15; & for ≥1 visit due to GI symptoms odds ratio 5.23

There was not a clear trend in increased symptoms between those who developed Crohn’s disease compared with Ulcerative Colitis. In addition, the study noted a trend towards decreased colectomy and resective surgery in Crohn’s in the time period 2002-2010 compared with 1987-2001.  One limitation of this study is the few number of pediatric gastroenterologists in Manitoba (only 1 before 2003); the lack of pediatric gastroenterology availability could impact timely diagnosis.

My take: This data shows that GI symptoms still predate diagnosis in many children and indicate a potential for diagnosis delay. The authors note that noninvasive tools like stool calprotectin have not been widely adopted (at least in Manitoba) and could be helpful in reducing diagnostic delays.

Estes Park, Colorado

Estes Park, Colorado

Stress and IBD Flareups

Over the years, I’ve had several experiences in which some patients had flareups of their inflammatory bowel disease (IBD) in relation to specific stresses (eg. going to away camp).  This was not just stomach pain but instead bloody diarrhea.  While this is very infrequent, I’ve come to believe that there may be some individuals who develop IBD flareups in response to stress. A recent study (Targownik LE, et al. AJG 2015; 110, 1001-1012 | doi:10.1038/ajg.2015.147) suggests that most of the time when individuals report a flareup in response to stress, that there is not objective evidence of increased inflammation.

The Relationship Among Perceived Stress, Symptoms, and Inflammation in Persons With Inflammatory Bowel Disease

From Abstract:

METHODS:

Participants were recruited from a population-based registry of individuals with known IBD. Symptomatic disease activity was assessed using validated clinical indices: the Manitoba IBD Index (MIBDI) and Harvey Bradshaw Index (HBI) for Crohn’s disease (CD), and Powell Tuck Index (PTI) for ulcerative colitis (UC). Perceived stress was measured using Cohen’s Perceived Stress Scale (CPSS). Intestinal inflammation was determined through measurement of fecal calprotectin (FCAL), with a level exceeding 250 μg/g indicating significant inflammation. Logistic regressions were used to evaluate the association between intestinal inflammation, perceived stress, and disease activity.

RESULTS:

Of the 478 participants with completed surveys and stool samples, perceived stress was associated with symptomatic activity (MIBDI) for both CD and UC (1.07 per 1-point increase on the CPSS, 95% confidence interval (CI) 1.03–1.10 and 1.03–1.11, respectively). There was no significant association between perceived stress and intestinal inflammation for either CD or UC. Active symptoms (MIBDI ≤3) were associated with intestinal inflammation in UC (odds ratio (OR) 3.94, 95% CI 1.65–9.43), but not in CD (OR 0.98, 95% CI 0.51–1.88).

CONCLUSIONS:

Symptomatic disease activity was unrelated to intestinal inflammation in CD and only weakly associated in UC. Although there was a strong relationship between perceived stress and gastrointestinal symptoms, perceived stress was unrelated to concurrent intestinal inflammation. Longitudinal investigation is required to determine the directionality of the relationship between perceived stress, inflammation, and symptoms in IBD.

Related blog posts:

For worried hikers in Yellowstone

For worried (“stressed”) hikers in Yellowstone

Working on Transition Readiness

A recent study (Gray WN, et al. Inflamm Bowel Dis 2015; 21: 1125-31) examines preparedness of patients with inflammatory bowel disease (IBD) on the verge of transitioning to adult gastroenterologists from pediatric gastroenterologists.

Using a population of 195 patients (16-25 years), the authors used the Transition Readiness Assessment Questionnaire (TRAQ).  Scoring system:

  • 5= Yes, I always do this when I need to
  • 4= Yes, I have started doing this
  • 3= No, but I am learning to do this
  • 2= No, but I want to learn
  • 1= No, I do not know how

Specific Readiness Skills & Mean Scores (more complete data listed in Table 3):

  • Taking medicines correctly and on own 4.66
  • Arranging for ride to medical appointment 4.39
  • Managing money and budgeting 3.69
  • Calling doctor about unusual change in health 3.64
  • Reordering and getting refills on time 3.60
  • Calling doctor’s office to schedule an appointment 3.09
  • Getting financial help with school or work 2.92
  • Knowing what health insurance covers 2.60
  • Applying for health insurance if coverage lost 2.44

Key finding: “Only 5.6% older adolescents/young adults …met our institutional benchmark.”

To help with transition readiness the authors recommend the CDHNF/NASPGHAN Transition Checklist for parents and starting on transition issues between 12-15 years of age.  Transition checklist available here: Transitioning a Patient With IBD From Pediatric to Adult Care –this is a simple 2-page handout!

Conclusion: Most patients need more work on transition readiness.  If patients are not prepared, it is more likely that this will lead to medical setbacks.

Briefly noted:

“Exercise Decreases Risk of Future Active Disease in Patients with Inflammatory Bowel Disease in Remission” Inflammatory Bowel Dis 2015; 21: 1063-71. This prospective study used the CCFA’s Partners’ internet-based cohort. 227 of 1308 (17.4%) Crohn’s disease (CD) patients and 135 of 549 (24.6%) Ulcerative colitis/indeterminate colitis (UC/IC) patients developed active disease after 6 months.  Key finding: Higher exercise level was associated with decreased risk of active disease for CD (adjusted relative risk 0.72) and UC/IC (adjusted relative risk 0.78).  Take-home point: While there are several limitations to this study, it does seem likely that regular physical exercise is a good idea (not just in patients with IBD).  In this population, subjective markers of disease activity (sCDAI and SCCAI) improved in those who exercised more.

Zoo Atlanta

Zoo Atlanta

New Mutations: Achalasia, Pseudoobstruction, & IBD

The ability to use whole exome sequencing and widely available genetic testing is yielding a plethora of new information regarding the genetic causes for many conditions.  In gastroenterology, here are a few recent examples:

  • Shteyer E, et al. “Truncating mutation in the nitric oxide synthase 1 gene is associated with infantile achalasia.” Gastroenterology. 2015 Mar;148(3):533-536.e4. doi: 10.1053/j.gastro.2014.11.044. Epub 2014 Dec 3.
  • Bonora E, et al. “Mutations in RAD21 Disrupt Regulation of APOB in Patients with Chronic Intestinal Pseudo-Obstruction” Gastroenterology 2015; 148: 771-82.  Genetic defect in RAD21 identified in Turkish family with consanguinity; in addition, APOB48 serum levels was identified as a potential biomarker for intestinal pseudo-obstruction and intestinal ganglion numbers.
  • Alonso A, et al. “Identification of Loci for Crohn’s Disease Phenotypes Using a Genome-Wide Association Study.” Gastroenterology 2015; 148: 794-805. Variants in MAG11, CLCA2, 2q24.1, LY75 identified as associated with Crohn’s phenotypes.

For me, I am not sure whether these findings should be considered mundane or amazing. On the one hand, each of the findings helps understand these diseases; yet, I came across all of these articles in the span of 24 hours and from the same journal.

Brains and Bowels: Kids with IBD Do Fine in School

Screen Shot 2015-05-04 at 8.11.32 PM

A recent study (Singh H, et al. J Pediatr 2015; 166: 1128-33) showed that overall academic performance was not affected for children with inflammatory bowel disease (IBD).

Study characteristics:

University of Manitoba Database IBD population (n=337) was matched by age, sex, and area of residence to 10 randomly selected controls (n=3093).

Key findings:

  • There were no significant differences in the 2 groups in standardized scores or enrollment in grade 12
  • Lower socioeconomic status and diagnosis with a mental health problem (6-month before or after IBD diagnosis) were independent predictors of worse outcomes

Akin to the quote above, I’ve often felt that it is difficult to think clearly when having severe bowel dysfunction.  At the same time, some of our patients accomplish so much despite their physical setbacks.

Bottomline: This study provides reassurance that children with IBD should be able to complete their course work.

Chicago

Chicago


Keeping Up with Clostridium Difficile

It is difficult to keep up with all of the relevant publications regarding Clostridium difficile–there are so many.  This likely reflects its emergence as a frequent and important pathogen.

Recent references:

  1. Sandberg KC et al. “Disproportionate Rise in Clostridium difficile Associated Hospitalizations Among US Youth with Inflammatory Bowel Disease, 19978-2011.” JPGN 2015; 60: 486-92 (editorial 421-22).
  2. Leffler DA, Lamont JT. NEJM 2015; 372: 1539-48.

In the first study, the researchers note that there has been a 5-fold increase in inflammatory bowel disease (IBD) hospitalizations with concomitant Clostridium difficile infection (CDI).  Whereas, the hospitalization without CDI increased 2-fold.  Associated with this 5-fold increase in hospitalizations, there were increased costs and longer length of stays.  Interestingly, IBD patients with CDI had a  lower likelihood (OR 0.31) of colectomy in this study. This epidemiology yields more questions than answers.  Certainly, a significant fraction of this increase is due to the use of more sensitive PCR-based assay. In addition, many of these patients may not be symptomatic due to CDI; it can be difficult to determine if IBD symptoms are due to IBD or due to CDI. Even treatment with antibiotics like vancomycin does not fully differentiate as the response could be nonspecific.

In the second review, severe useful points were made.

Risk factors:

  • Antibiotics –this remains most important risk factor
  • Older age (especially if >65 years)
  • Possible acid suppression -not confirmed in some studies when adjusting for coexisting conditions
  • Inflammatory bowel disease
  • Immunosuppression
  • Chronic kidney disease

Diagnosis:

  • Use of DNA assays has allowed for detection of “low levels of toxigenic organisms of uncertain clinical significance.”  Thus, these assays may detect clinically-insignificant infections.
  • Endoscopy is rarely needed, but sometimes helpful in ovelapping conditions like coexistent CDI from IBD
  • Negative PCR assay has a negative predictive value of “more than 95% in average-risk groups.”
  • Testing and treating persons with solid stools is not recommended

Prevention:

  • Probiotics “have an uncertain effect on the prevention of C difficile infection, and their routine use for the prevention or treatment of active infection is not recommended.”  The authors note that initial favorable studies of antibiotic-associated diarrhea were underpowered and that more recent studies have shown mixed results.  In studies of patients with unusually high rates of CDI, probiotics were shown to confer benefit.

Treatment:

  • Metronidazole and vancomycin remain 1st line treatments.
  • Fidaxomicin use has been limited due to expense, but has been shown to reduce recurrence of CDI in those who do not have the b1/NAP1/027 strain.
  • Alternative antimicrobials, including rifaximin, nitazoxanide and others, are “not recommended except in cases of unacceptable adverse effects.”
  • For recurrent infection, 1st line approach is retreatment with either metronidazole & vancomycin. Second recurrences are often treated with fidaxomicin or tapered vancomycin course.
  • Fecal microbial transplantation –noted to be highly effective and safe as salvage therapy. The precise components that are important are uncertain; however, “the phyla Bactteroidetes and Firmicutes are thought to comprise critical components.”  “More work is neede to understand the possible role for fecal microbial transplantation for primary CDI”

Bottomline: CDI remains an important pathogen and significantly complicates the management of IBD.

Related blog posts: