
ACG Guideline for Small Intestinal Bacterial Overgrowth

Link to full PDF: ACG Clinical Guideline: Small Intestinal Bacterial Overgrowth

M Pimentel et al. Am J Gastroenterol 2020;00:1–14. https://doi.org/10.14309/ ajg.0000000000000501; published online January 8, 2020

One key point is that the authors acknowledge that almost all of their recommendations are based on a very low level of evidence.  In fact, only one of their 6 recommendations in Table 1 is considered to have more evidence and it is rated as low level of evidence.

The article provides an in-depth review of small intestinal bacterial overgrowth including underlying homeostasis mechanisms/pathophysiology (Tables 3 & 4) and treatments.  For those needing treatment, the authors list options in Table 5 including rifaximin, amoxicillin-clavulanic acid, ciprofloxacin, doxycycline, metronidazole, neomycin, norfloxacin, tetracycline, and trimethoprim-sulfamethoxazole.
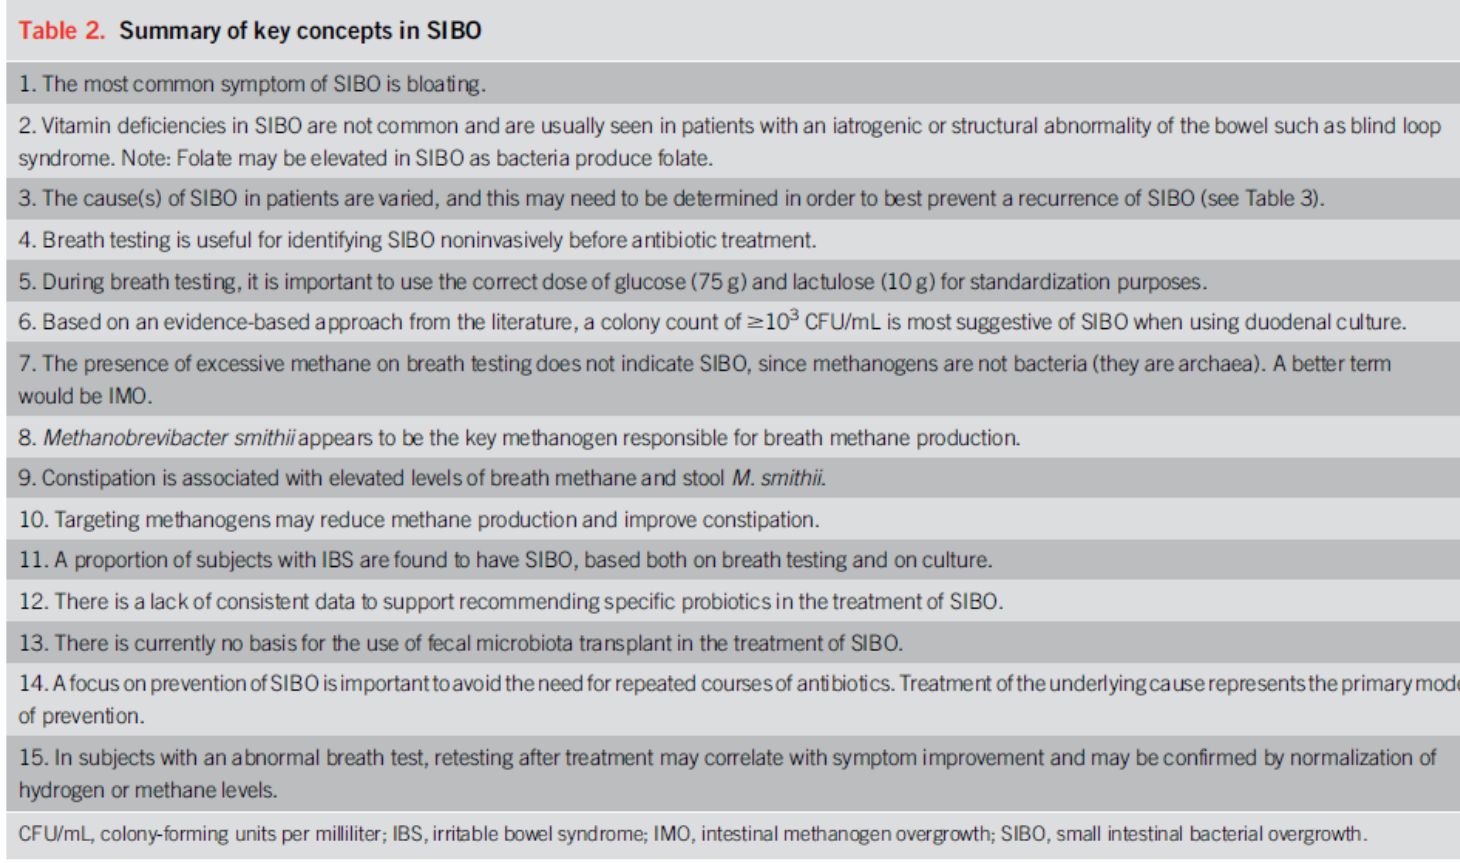
Image Available from Lizzie Aby Feed

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.


New Therapy for Eosinophilic Esophagitis

In a report (I Hirano, ES Dellon et al. Gastroenterol 2020; 158: 111-22) on a phase 2 trial with 47 adults, the authors show that weekly subcutaneous injections of dupilumab (300 mg) was associated with improvement in eosionophilic esophagitis.

Dupilumab, a fully human monoclonal antibody, antagonizes the interleukin-4 receptor-alpha component of the type 2 receptor, thereby inhibiting signaling of IL-4 and IL-13. Dupilumab has shown “efficacy in pediatric and adult atopic dermatitis, asthma, and chronic sinusitis with nasal polyposis” and is FDA-approved for use in these disorders.

Key findings:

  • Dupilumab was associated with improvement in dysphagia as measured by the Straumann Dysphagia Instrument with a mean reduction of 3.0 compared to 1.3 in the placebo group at week 10 (P=.0304)
  • Dupilumab was associated with improvement in histology, at week 12, the peak eosinophil count had dropped by a mean of 86.8 (P<.0001 vs. placebo)
  • Dupilumab was associated with improvement in endoscopic parameters as assessed by endoscopic reference score which dropped by 1.6 (P -.0006 vs placebo)
  • No serious adverse effects were evident.  Nasopharyngitis was noted in 17% in the dupilumab group compared to 4% of placebo-treated patients.  Injection site erythema was noted in 35% (vs. 8% in placebo group

Of note, the study was sponsored by pharmaceutical companies and many of the authors (including both lead authors) were either affiliated with these companies.

My take: This study indicates that Dupilumab has at least short term efficacy and safety for eosinophilic esophagitis.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Neurologic Toll of Celiac Disease

A recent prospective cohort study (M Hadjivassiliou et al. Clin Gastroenterol Hepatol 2019; 17: 2678-86) shows an alarmingly-high level of neurologic deficits in 100 consecutive adults (mean age 43 years) with a new diagnosis of celiac disease.

Key findings:

  • Gait instability in 24%
  • Persistent sensory symptoms in 12%; peripheral neuropathy was identified in 2%
  • Frequent headaches in 42%
  • Abnormal results from Brain MRI in 60%; 25% had brain white matter lesions beyond expectation for age group and 46% had abnormal MR spectroscopy of the cerebellum
  • Anti-TG6 antibodies were detected in 40% of patients and this subgroup had significant atrophy of subcortical brain regions compared to patients who were Anti-TG6 antibody-negative

Some neurologic findings improve on a gluten-free diet (GFD).  In previous studies of patients with CD and headaches, 75-80% improved or subsided after a year of strict adherence to a GFD.

My take: This study indicates that early diagnosis of celiac disease along with strict adherence to a gluten-free diet is likely to prevent permanent neurologic disability.

Related blog posts:

How Often Do Adults Develop Celiac Disease After Negative Testing?

RS Choung et al. Gastroenterol 2020; 158: 151-9.  

Full abstract link: (which has link to full text): “Community-Based Study of Celiac Disease Autoimmunity Progression in Adults”

Methods: In this prospective cohort study, waste blood samples from residents of a community were tested for CeD autoimmunity at 2 time points. We analyzed waste blood samples from 15,551 adults for tTGA and, if titer results were above 2 U/mL, for endomysial antibody. The median interval between the two time points was 8.8 years.

Results:

  • Of the serum samples collected at the first time point, 15,398 had negative results for tTGA, and 153 had positive results for tTGA (>4 U/mL). Based on medical records, 6 individuals received a diagnosis of celiac disease, for a cumulative incidence of celiac disease diagnosis of 0.06% over 10 years.
  • Forty-nine (0.32%) individuals with a negative result from the first serologic test for tTGA had a positive result from the second test
  • Among the 153 adults who were tTGA positive at the first time point, 31 (20%) had a subsequent diagnosis of celiac disease, 81 (53%) remained positive for tTGA without a clinical diagnosis of celiac disease, and 41 (27%) had negative test results for tTGA at the second time point.

Highlights in IBD from Two 2019 Meetings: American College of Gastroenterology and United European Gastroenterology Week

Gastroenterology & Hepatology. December 2019 – Volume 15, Issue 12, Supplement 5

Excerpts from William Sandborn Commentary which are at the end of this supplement along with references:

Vedolizumab

In the VARSITY study (An Efficacy and Safety Study of Vedolizumab Intravenous [IV] Compared to Adalimumab Subcutaneous [SC] in Participants With Ulcerative Colitis), 769 patients with ulcerative colitis were randomized to a year of therapy with either adalimumab at the US Food and Drug Administration (FDA)-approved dose or vedolizumab at the FDA-approved dose…This shows that the idea that vedolizumab (and anti-integrin therapy) is slower-acting than anti-TNF therapy is not correct, and that both of these classes of drugs can work fairly quickly in a number of patients.

Dr Brian Bressler and colleagues looked at the effectiveness of anti-TNF therapy in the real world when used second line after failing first-line biologic therapy with vedolizumab…The study conducted by Dr Bressler and colleagues, which included both Crohn’s disease patients and ulcerative colitis patients, found that the results were fairly similar whether patients received first-line biologic therapy with an anti-TNF agent or whether patients received first-line therapy with vedolizumab… It is generally thought that vedolizumab is a safer therapy than anti-TNF therapy, so with the finding from this study, a reasonable treatment approach could be to start with vedolizumab and see if it works…

Dr Christina Chambers and colleagues identified outcomes for pregnancy in 223 women, 53 of whom received vedolizumab. The researchers found that there were no major structural birth defects reported in the vedolizumab group, compared to 5.7% and 5.3% in the disease-matched group and healthy control group, respectively. Thus, there seemed to be no signal for an increased malformation risk in patients who were undergoing treatment with vedolizumab and became pregnant.

Adalimumab

The SERENE trials are a set of head-to-head trials, one for ulcerative colitis and one for Crohn’s disease, comparing standard-dose adalimumab to a more intensive induction regimen of adalimumab…

For both ulcerative colitis and Crohn’s disease, the SERENE trials showed that the current FDA-approved dosing regimen is effective and that more intensive induction therapy does not improve outcomes over time. Thus, there is no utility in giving high induction doses. 

Tofacitinib

Over 1000 patients who had been treated with tofacitinib were examined…during induction and maintenance of the placebo-controlled portion of the tofacitinib clinical trials, there were a total of 5 deep vein thrombosis and pulmonary emboli events. All 5 occurred in patients who were receiving placebo; none of these events occurred in patients who were receiving tofacitinib…[And] There was a total of 5 deep vein thrombosis and pulmonary emboli events during this long-term extension…Looking at the ulcerative colitis clinical trial data that I presented, it is somewhat reassuring that we did not see the same elevation in risk for deep vein thrombosis and pulmonary emboli that was seen in the high-risk rheumatoid arthritis patient population.

Mont Royal (Montreal)

More Good News for PPIs: NO Increased Risk of Dementia

From ACG SmartBrief (thanks to Ben Gold for this):

A study published in The American Journal of Gastroenterology found no link between the use of proton-pump inhibitors and increased dementia risk. The study, led by Muhammad Ali Khan, MD, examined 11 studies with a combined 642,949 participants, and researchers said “PPI use among patients who have a valid indication for it, should not be curtailed because of concerns about dementia risk.”

The American Journal of Gastroenterology: January 2, 2020 – Volume Publish Ahead of Print – Issue – p doi: 10.14309/ajg.0000000000000500

Abstract

INTRODUCTION:

Long-term use of proton pump inhibitors (PPIs) has been associated with a wide variety of potentially serious adverse effects including a possible increased risk of dementia. Studies evaluating this association have reached divergent conclusions. We aimed to evaluate this proposed association further and to assess the quality of the evidence in its support.

METHODS:

We searched MEDLINE, EMBASE, ISI Web of Science, and Cochrane databases for studies examining a link between PPI use and dementia, up to February 2019. Studies reporting summary results as hazard ratio (HR) or odds ratio (OR) were pooled using the DerSimonian and Laird random-effects model for meta-analyses. Methodological quality of individual observational studies was assessed using the Newcastle-Ottawa scale and the overall quality of evidence rated as per the GRADE approach.

RESULTS:

We identified and included 11 observational studies comprising 642,949 subjects; 64% were women. Most studies were short-term ranging from 5 to 10 years. There were 158,954 PPI users and 483,995 nonusers. For studies summarizing data as adjusted HR, pooled HR for all causes of dementia was 1.10 (0.88–1.37); for Alzheimer dementia only, it was 1.06 (0.72–1.55). For studies summarizing data as adjusted OR, pooled OR for all causes of dementia was 1.03 (0.84–1.25) and for Alzheimer dementia only 0.96 (0.82–1.11). Per Newcastle-Ottawa scale assessment, 10 studies were of high quality and 1 was of moderate quality. By applying GRADE methodology, quality of evidence for both outcomes was very low.

DISCUSSION:

We found no evidence to support the proposed association between PPI use and an increased risk of dementia. PPI use among patients who have a valid indication for it, should not be curtailed because of concerns about dementia risk.

Related blog posts:

P’tit Train du Nord Linear Park


POEM vs Surgical Myotomy for Achalasia -Randomized Trial

A recent randomized trial (YB Werner et al. NEJM 2019; 381: 2219-29) compared peroral endoscopic myotomy (POEM) and laparoscopic Heller’s myotomy (LHM) for idiopathic achalasia in 221 patients.

Key findings:

  • Clinical success at 2-year followup was observed in 83% in the POEM group and 82% in the LHM group. Clinical success was defined as Eckardt score of 3 or less without the use of additional treatments.
  • Serious adverse events occurred in 2.7% of POEM group and 7.3% of LHM group
  • At 3 months following procedure, 57% of the POEM group and 20% of LHM group had reflux esophagitis; the rates were 44% and 29% at 2 years, respectively.

My take: This study demonstrates similar outcomes between POEM and LHM.  As a practical matter, local expertise is likely a crucial component in choosing between these options.

Related blog posts:

More Details on Drug-Resistant E coli Transmitted by Fecal Microbiota Transplant

In June 2019, the FDA delivered a warning about the potential danger of transmitting drug-resistant E coli with fecal microbiota tranplantaion (FMT).  (FDA Warning for FMT)

A report on this issue has now been published: Z DeFilipp et al. NEJM 381: 2043-50, editorial M Blaser pgs 264-6.

The authors describe two patients, a 69 year-old with cirrhosis and a 73 year-old sp stem cell transplantation, who developed bacteremia due to transmission of a drug-resistant (extended-spectrum beta-lactamase [ESBL]) E coli following FMT which was delivered by oral capsules. The latter patient died from sepsis. The two patients had a genomicly-identical strain isolated that was also found in the donated aliquot.

In the commentary, a couple of important points:

  • “Up to now, the complications have been infrequent [from FMT], and for recurrent C difficile infection, the benefits of FMT clearly outweigh the risks; however, as the use of FMT is broadened and more compromised patients are treated, complications may be more frequently observed.”
  • “In the short term, improved and uniform screening of FMT material is needed to reduce the risks.”

My take: Both of these patients who became developed bacteremia were at risk for more severe infections.  However, we need to remain aware that severe complications can and do occur with FMT.  In context, though, there are risks of severe complications from routine use of antibiotics as well.

Frontenac Hotel, Quebec City

Only 3% Make It Through the Donor Screening Process for Fecal Microbiota Transplantation

A recent letter (Z Kassam et al. NEJM 2019; 381: 2070-2) describes the arduous process involved in being selected as a stool donor for fecal microbiota transplantation (FMT).

In a previous blog (2015), it appeared that 17% of donors were accepted for FMT: Rejected! Most Stool is Not Good Enough for FMT This current review of the donor program from a stool bank (OpenBiome) prospectively evaluated 15,317 donor candidates from 2014-2018.

Key finding:

  • Only 3% (n=386) made it through all the steps to become donors

Reasons for exclusion:

Stage 1: common reasons for exclusion:

  • geographical -living too far away to donate regularly
  • BMI >30
  • social history
  • travel history
  • not in age range

Stage 2: “failing” the 200-item clinical assessment –common reasons for exclusion:

  • lost to followup
  • allergic disorders/asthma
  • receiving medications/supplements
  • mental health concerns
  • infectious disease history
  • social history/sexual history/other reasons

Stage 3: “failing” the stool and nasal screening which included (in 2016) carbapenem-resistant Enterobacteriacea (CRE), extended-spectrum beta-lactamase-producing organisms (ESBL) and MRSA. –common reasons for exclusion:

  • lost to followup
  • infectious disorders (including C diff in 7 patients)

Stage 4: “failing” serological screening

  • lost to followup
  • abnormal LFTs, CBC or infection

Related blog posts:

Island Ford, Sandy Springs, GA



