Georgia AAP Nutrition Symposium 2019: Care of the NICU (Premature Infant) Graduate

This year’s Georgia AAP Nutrition Symposium featured lectures targeting the NICU graduates and children with allergies (tomorrow). My notes from these lectures could contain errors of omission or transcription.

Greg Sysyn

Link to slides: The Care and Feeding of the Tertiary NICU October 10 2019

Key points:

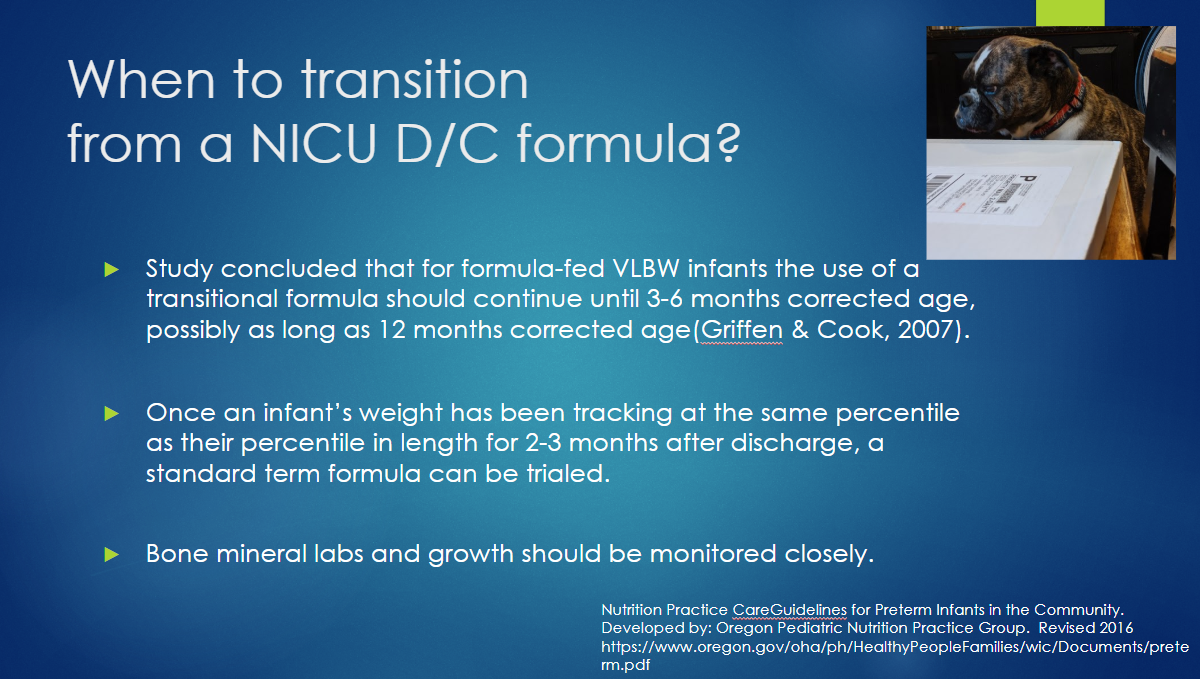
When can NICU graduates take a standard formula?  ‘When at normal weight at term or beyond for 2-3 months (tracking along a good percentile)’ –but keep in context (how big are parents); otherwise use preterm formula up to 52 weeks post-conceptional age. Studies have shown that formula-fed VLBW infants use of a transitional formula should continue until 3-6 months of age, possibly as long as 12 months of age.

Related blog posts:


Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) and changes in diet should be confirmed by prescribing physician.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Georgia AAP Nutrition Symposium 2019: Food Allergy Immunotherapy

This year’s Georgia AAP Nutrition Symposium featured lectures targeting the NICU graduates (yesterday) and children with allergies. My notes from these lectures could contain errors of omission or transcription.

Luqman Seidu — Food Allergy Immunotherapy: it’ll drive you nutty

Key Points:

  • Currently, it is hard to quantitate food-related mortality/anaphylaxis. It is much more common to have anaphylaxis due to medications.
  • Immunotherapy –can establish tolerance but needs to be considered in terms of efficacy, safety, ease of compliance.   Goal is sustained unresponsiveness so that there is an end in sight to treatment.
  • Multiple modalities, SLIT (sublingual and then swallowed), OIT (oral), EPIT (Epicutaneous therapy), OIT with anti-IgE therapy
  • 1 peanut =250-300 mg (important number to keep in mind, as many studies aim for ~1000 mg, which is ability to ingest ~3 peanuts).
  • EPIT -peanut patch.  1-yr study –goal was 1000 mg or 10-fold increase in tolerance without reaction.  97% compliance with study. Safer approach and better adherence but takes longer to get response.  Lower response at 1 yr –takes ~2 yr to get similar response
  • OIT therapy allows more rapid attainment of tolerance but lower compliance and higher rates of systemic reactions compared to EPIT.  A standardized product will be available soon; an FDA advisory committee has approved a peanut product (Palforzia). (NPR has reported on this as well: Peanut Allergy Treatment Palforzia)
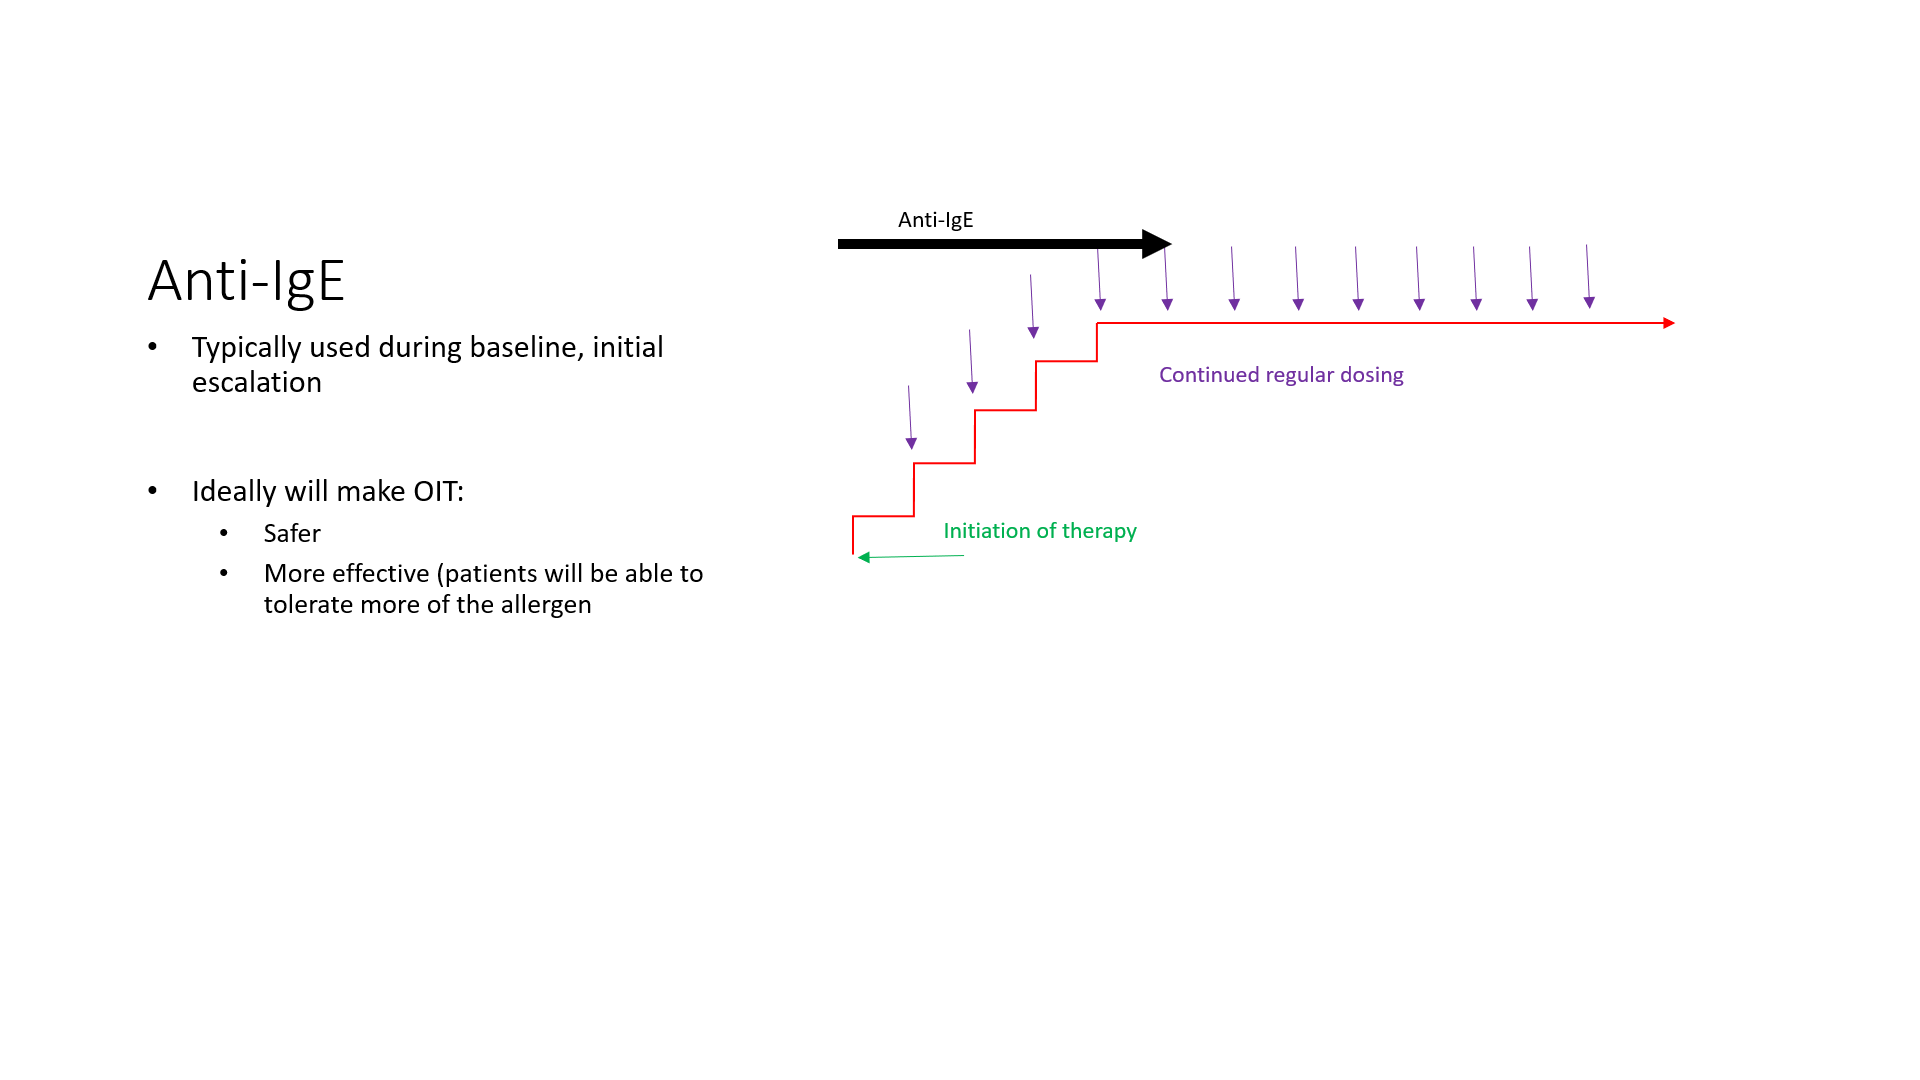
  • Anti-IgE therapy (eg. Xolair).  Can use to desensitize for multiple foods at the same time.

Though not discussed in this talk, it is important for GI physicians to recognize that oral immunotherapy has been shown to trigger new onset EoE in 2.7% (AJ Lucendo et al. Ann Allergy Asthma Immunol 2014; 113: 624-9).

Related blog posts:


Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) and changes in diet should be confirmed by prescribing physician.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

#NASPGHAN19 Intestinal Failure Session Part 2

Our Spooky Pumpkin

Here are some notes and a few slides from NASPGHAN’s plenary session.  There could be errors of transcription in my notes.

Benjamin Gold, NASPGHAN president and part of our GI group, GI Care For Kids, welcomed everyone to the meeting.

Link to NASPGHAN_Annual_Meeting_Program 2019

Beth Carter  Trophic Growth Factors: A Practical View

Key Points:

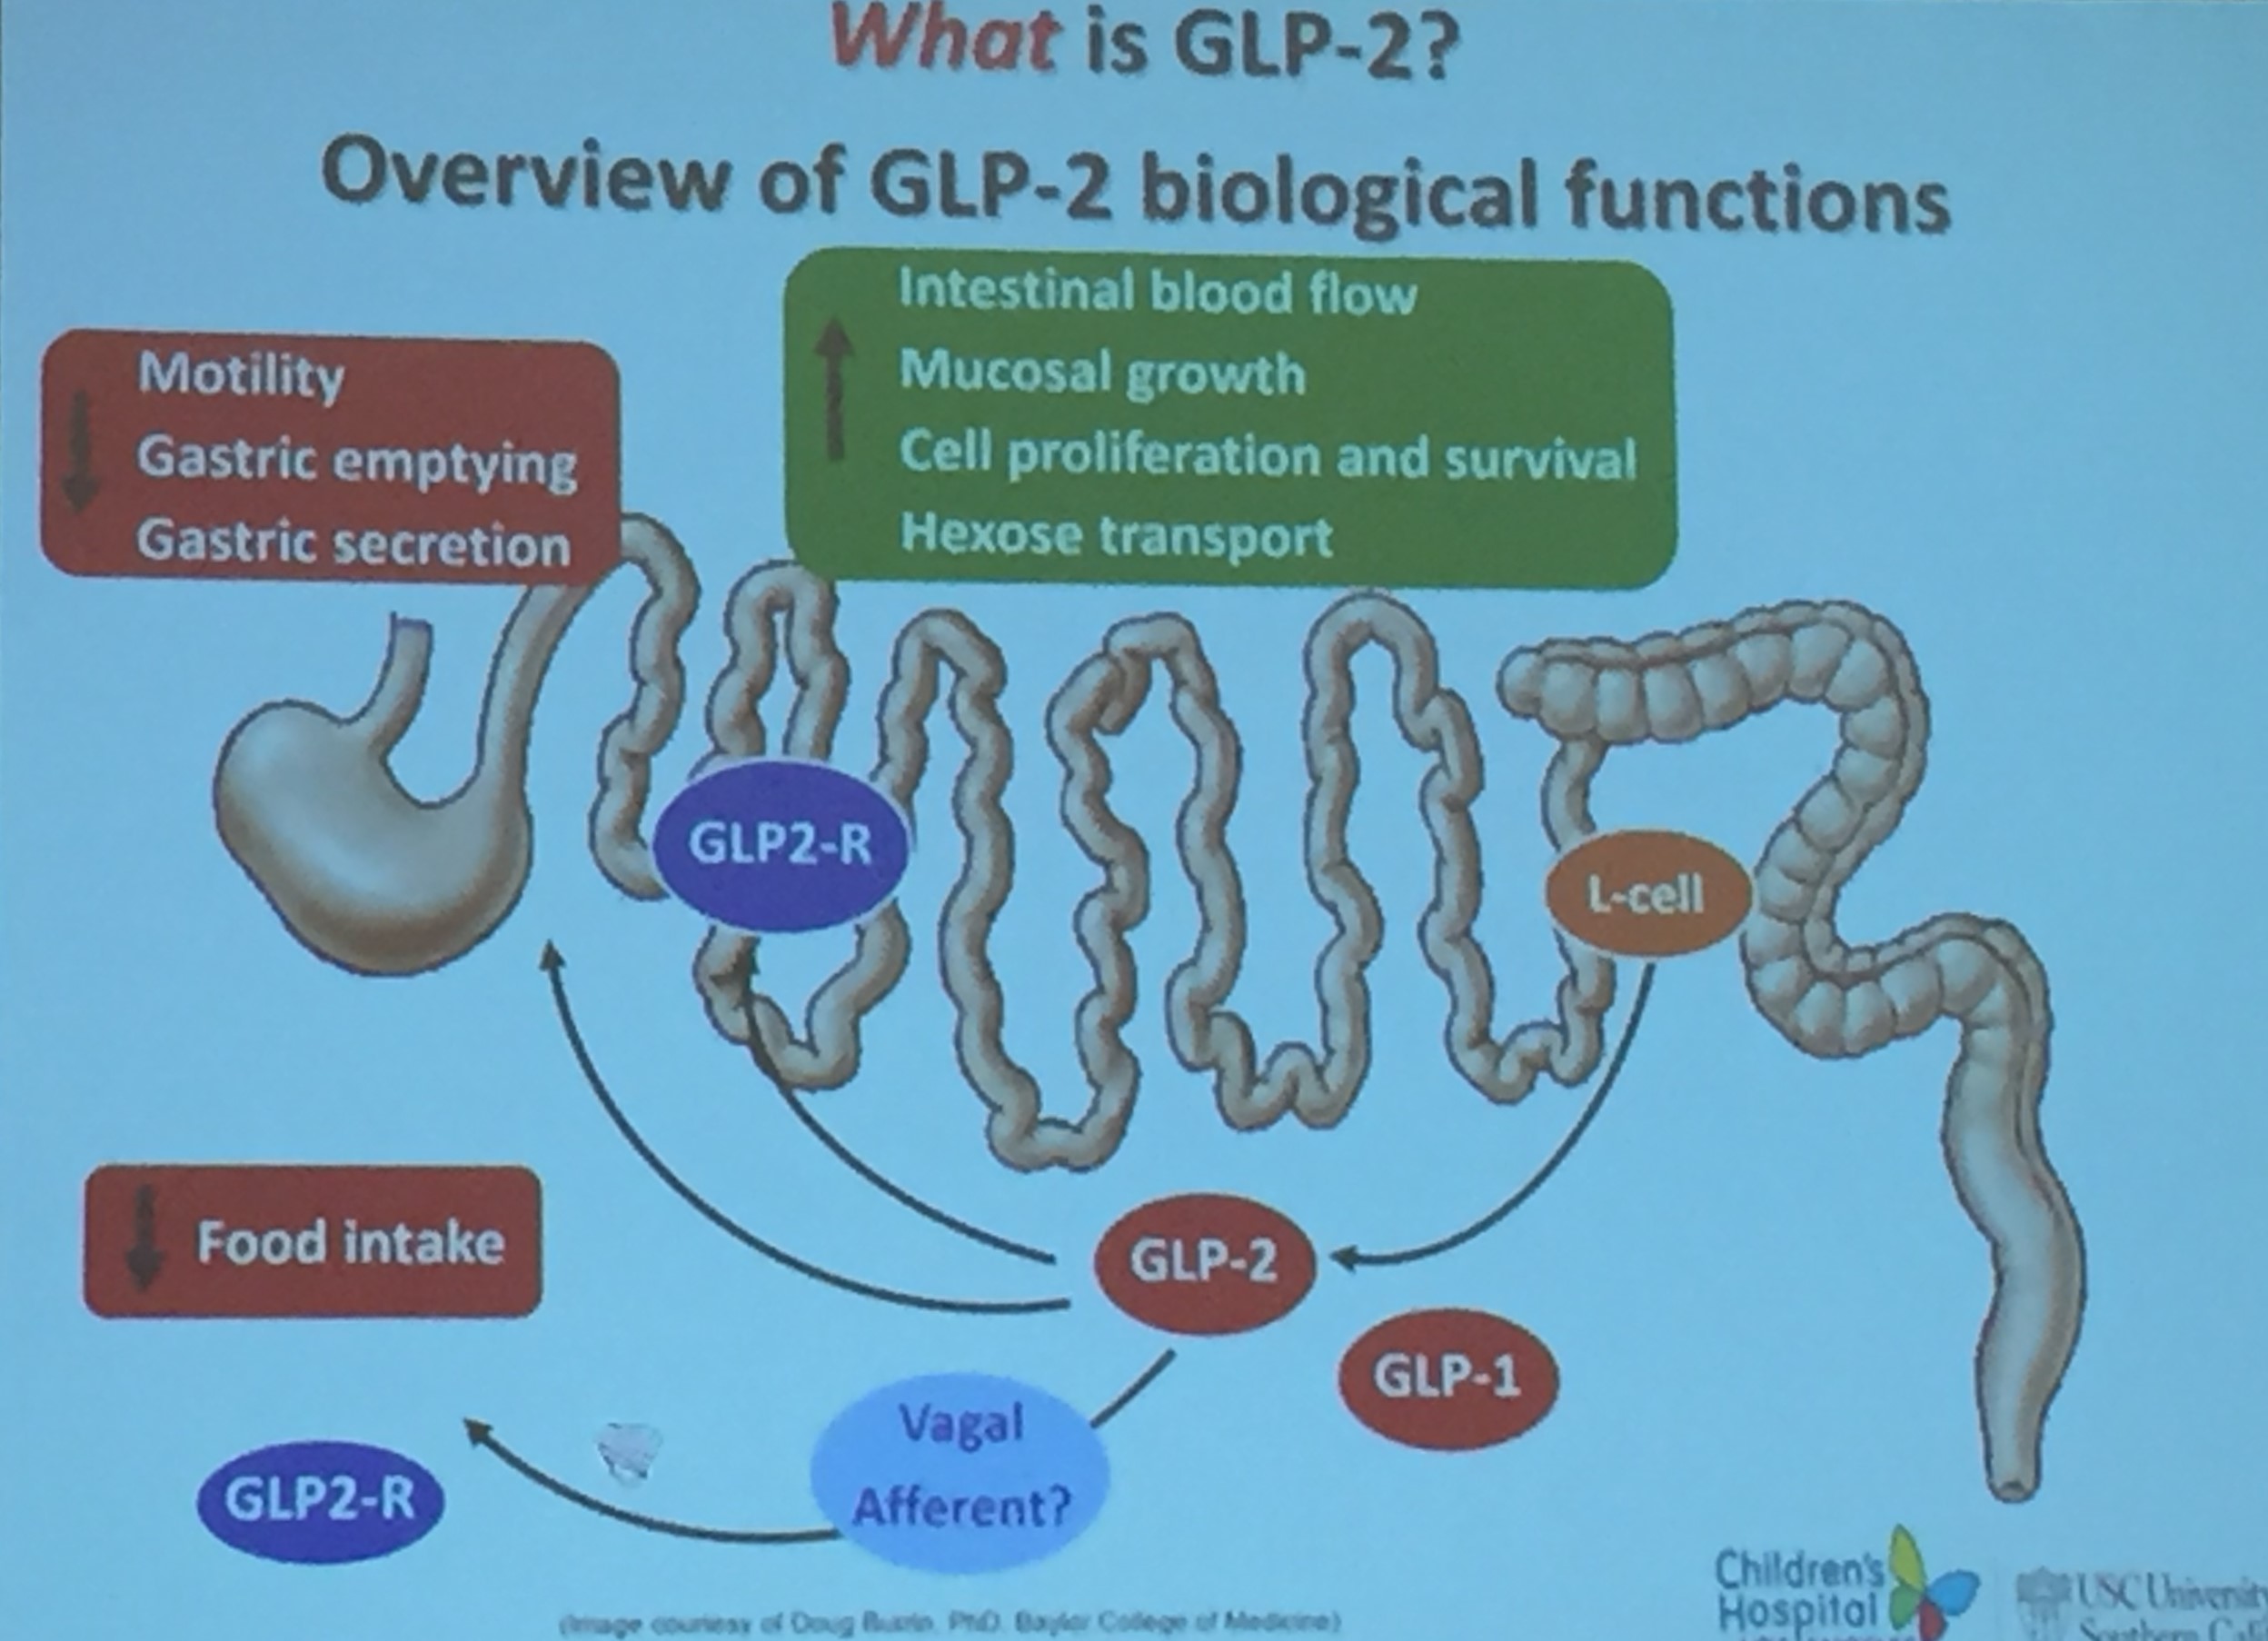
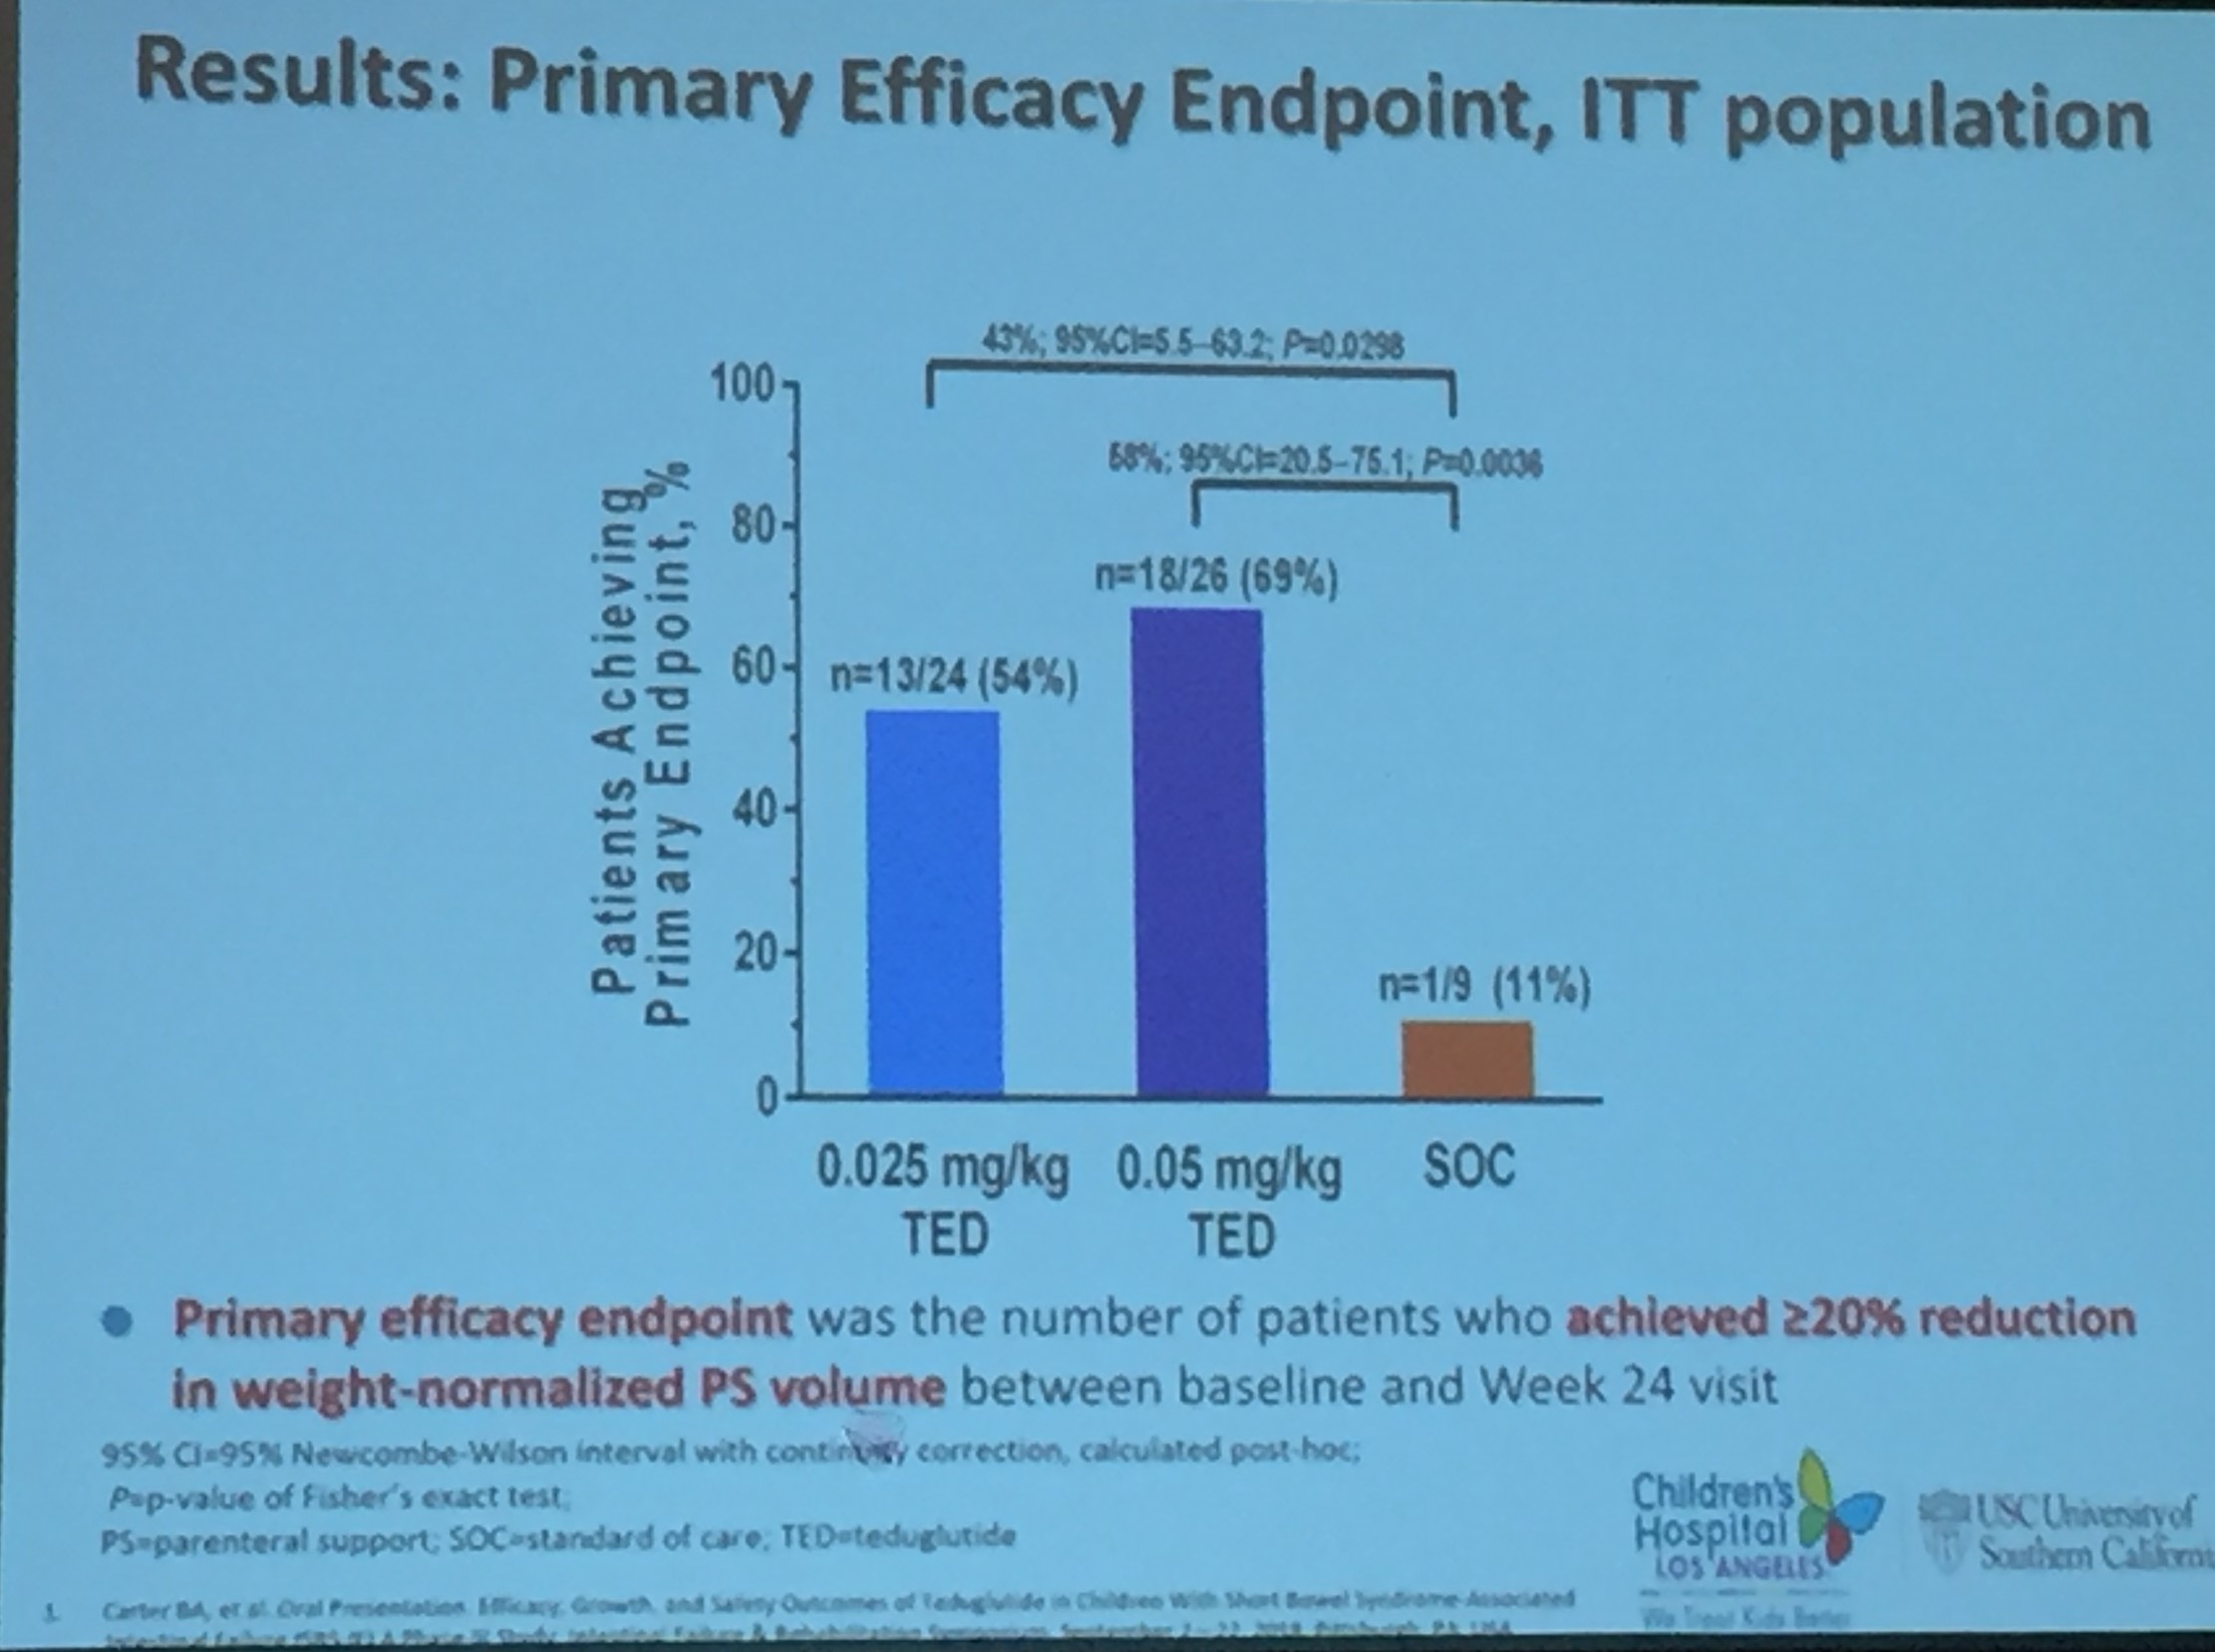
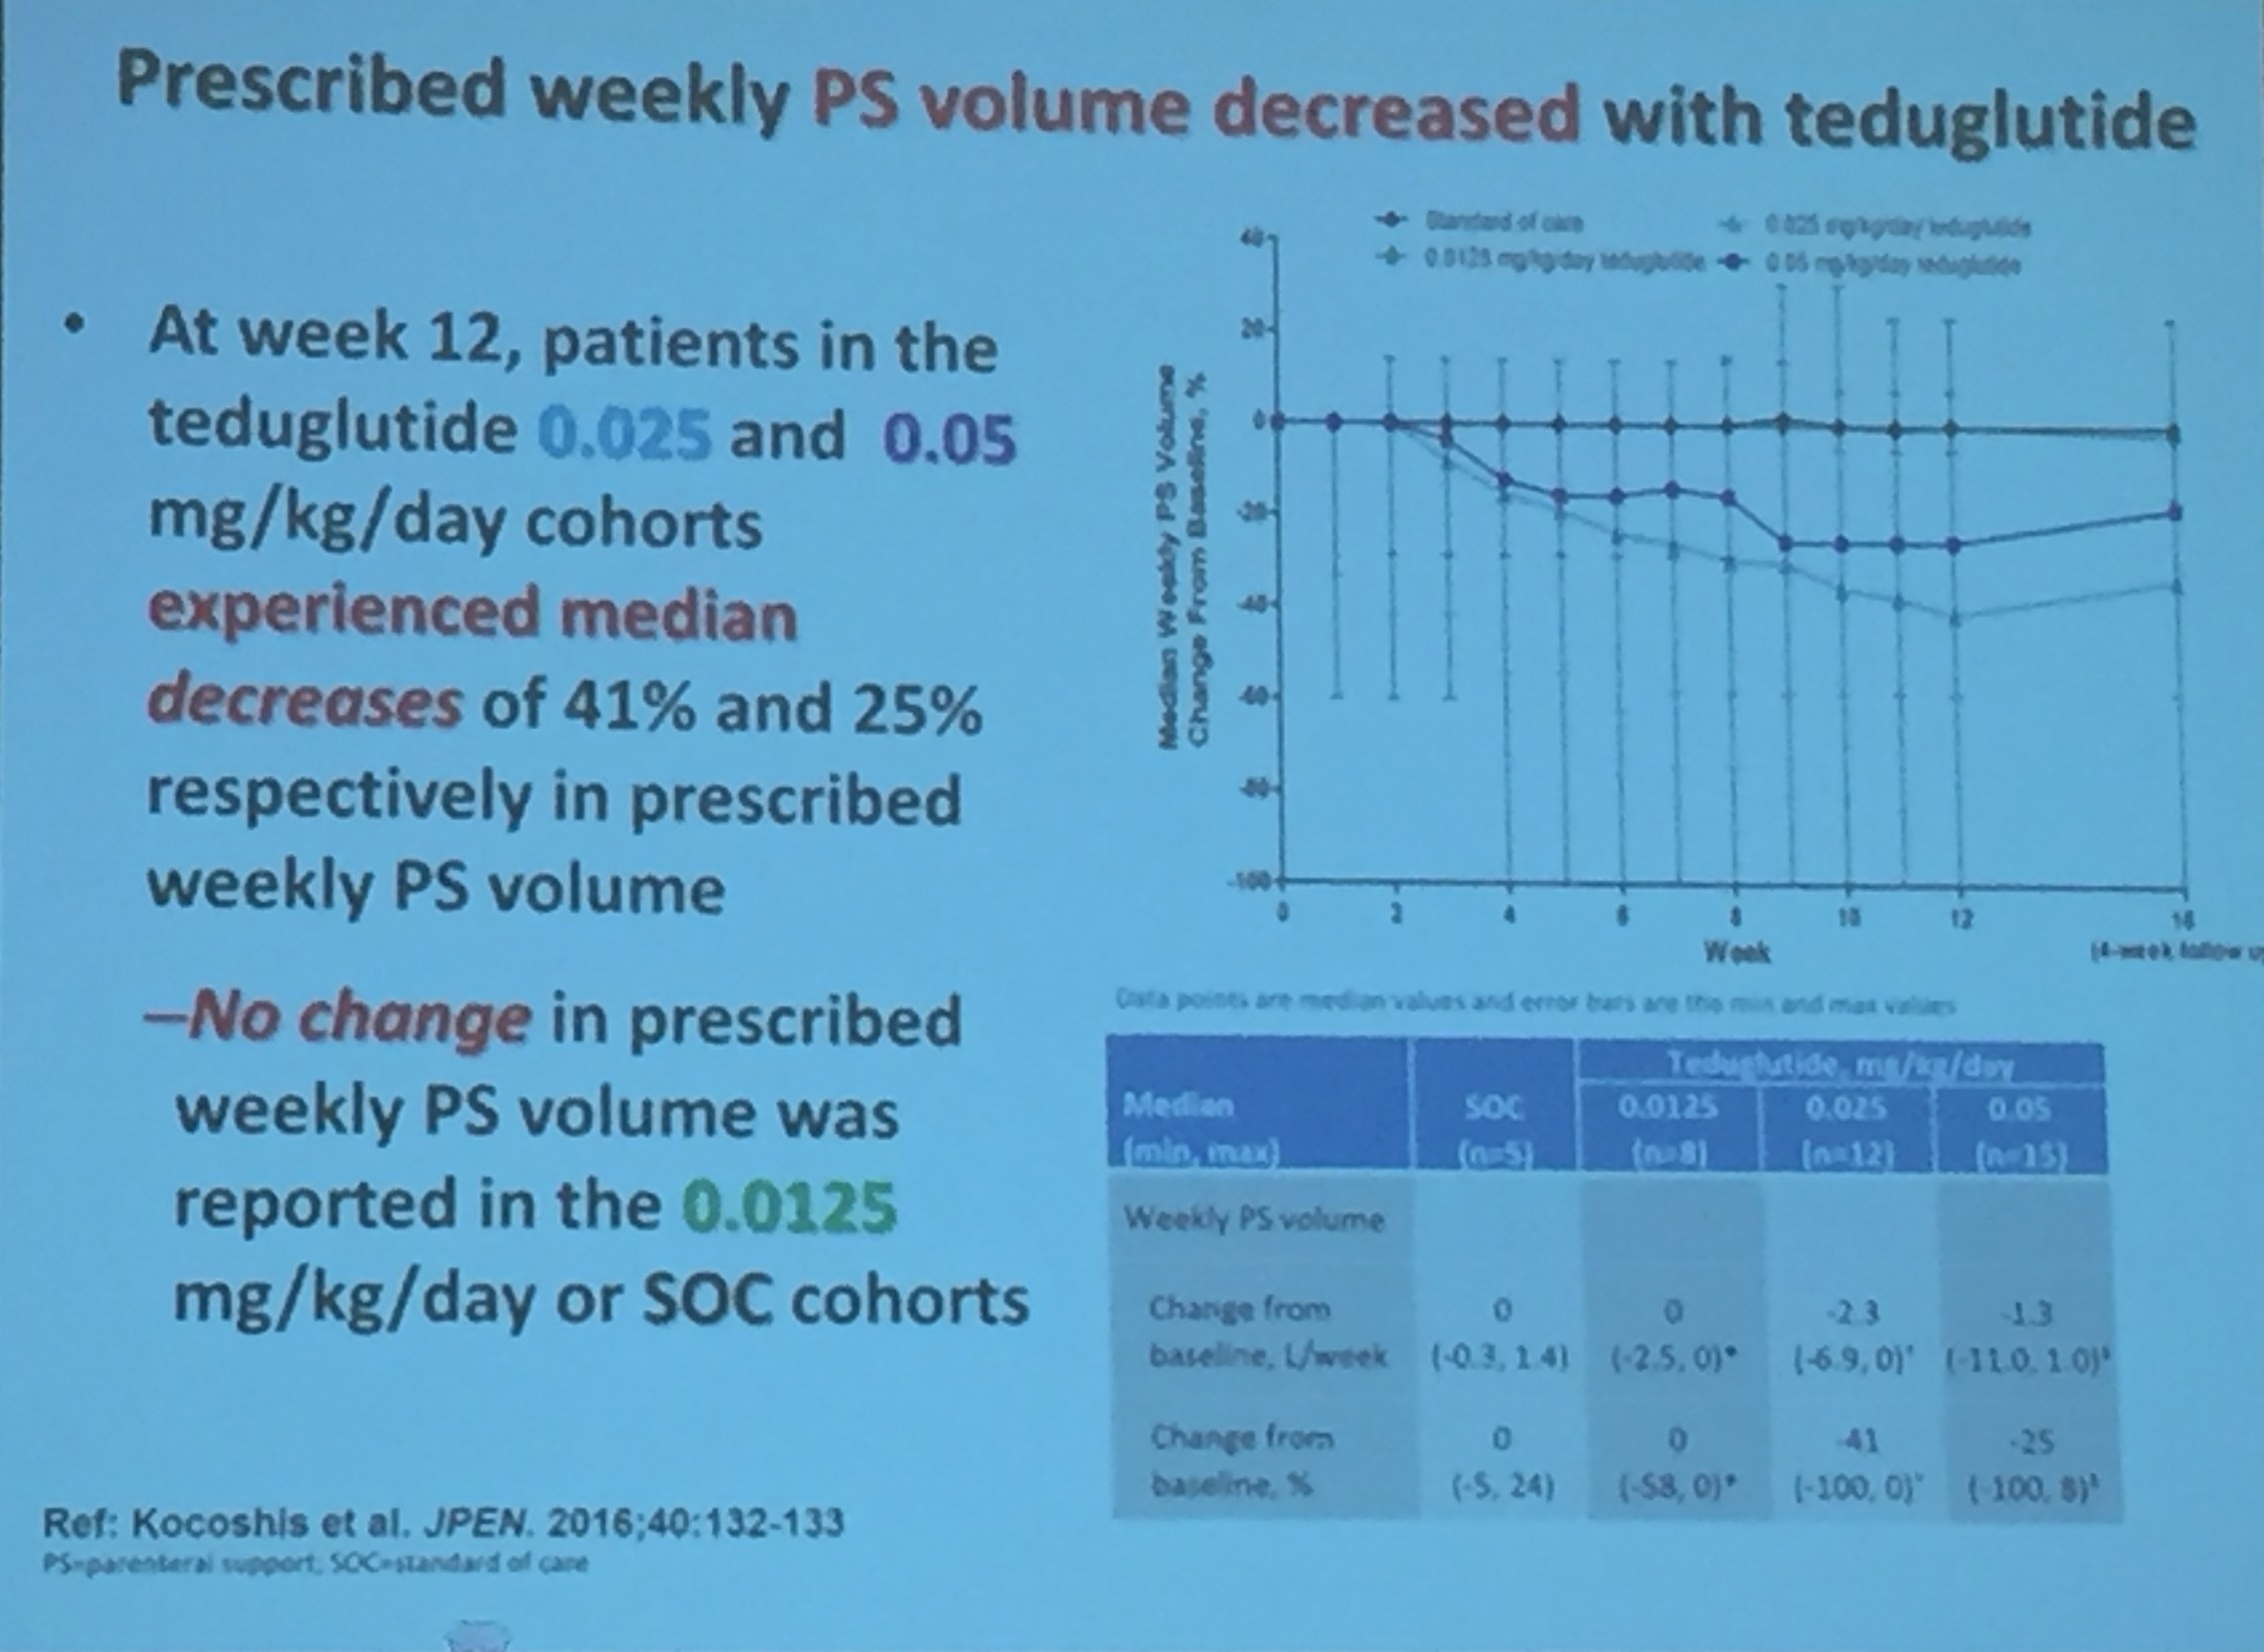
  • GLP-2 has been approved as agent for intestinal failure for children (May 2019)
  • Studies thus far have shown good safety but concerns remain (?increased risk of polyposis, increased growth of neoplasm) and as such increased surveillance needed for patients receiving GLP-2
  • Cost in adults ~$295,000 per year
  • Most patients need to continue GLP-2 to maintain effect

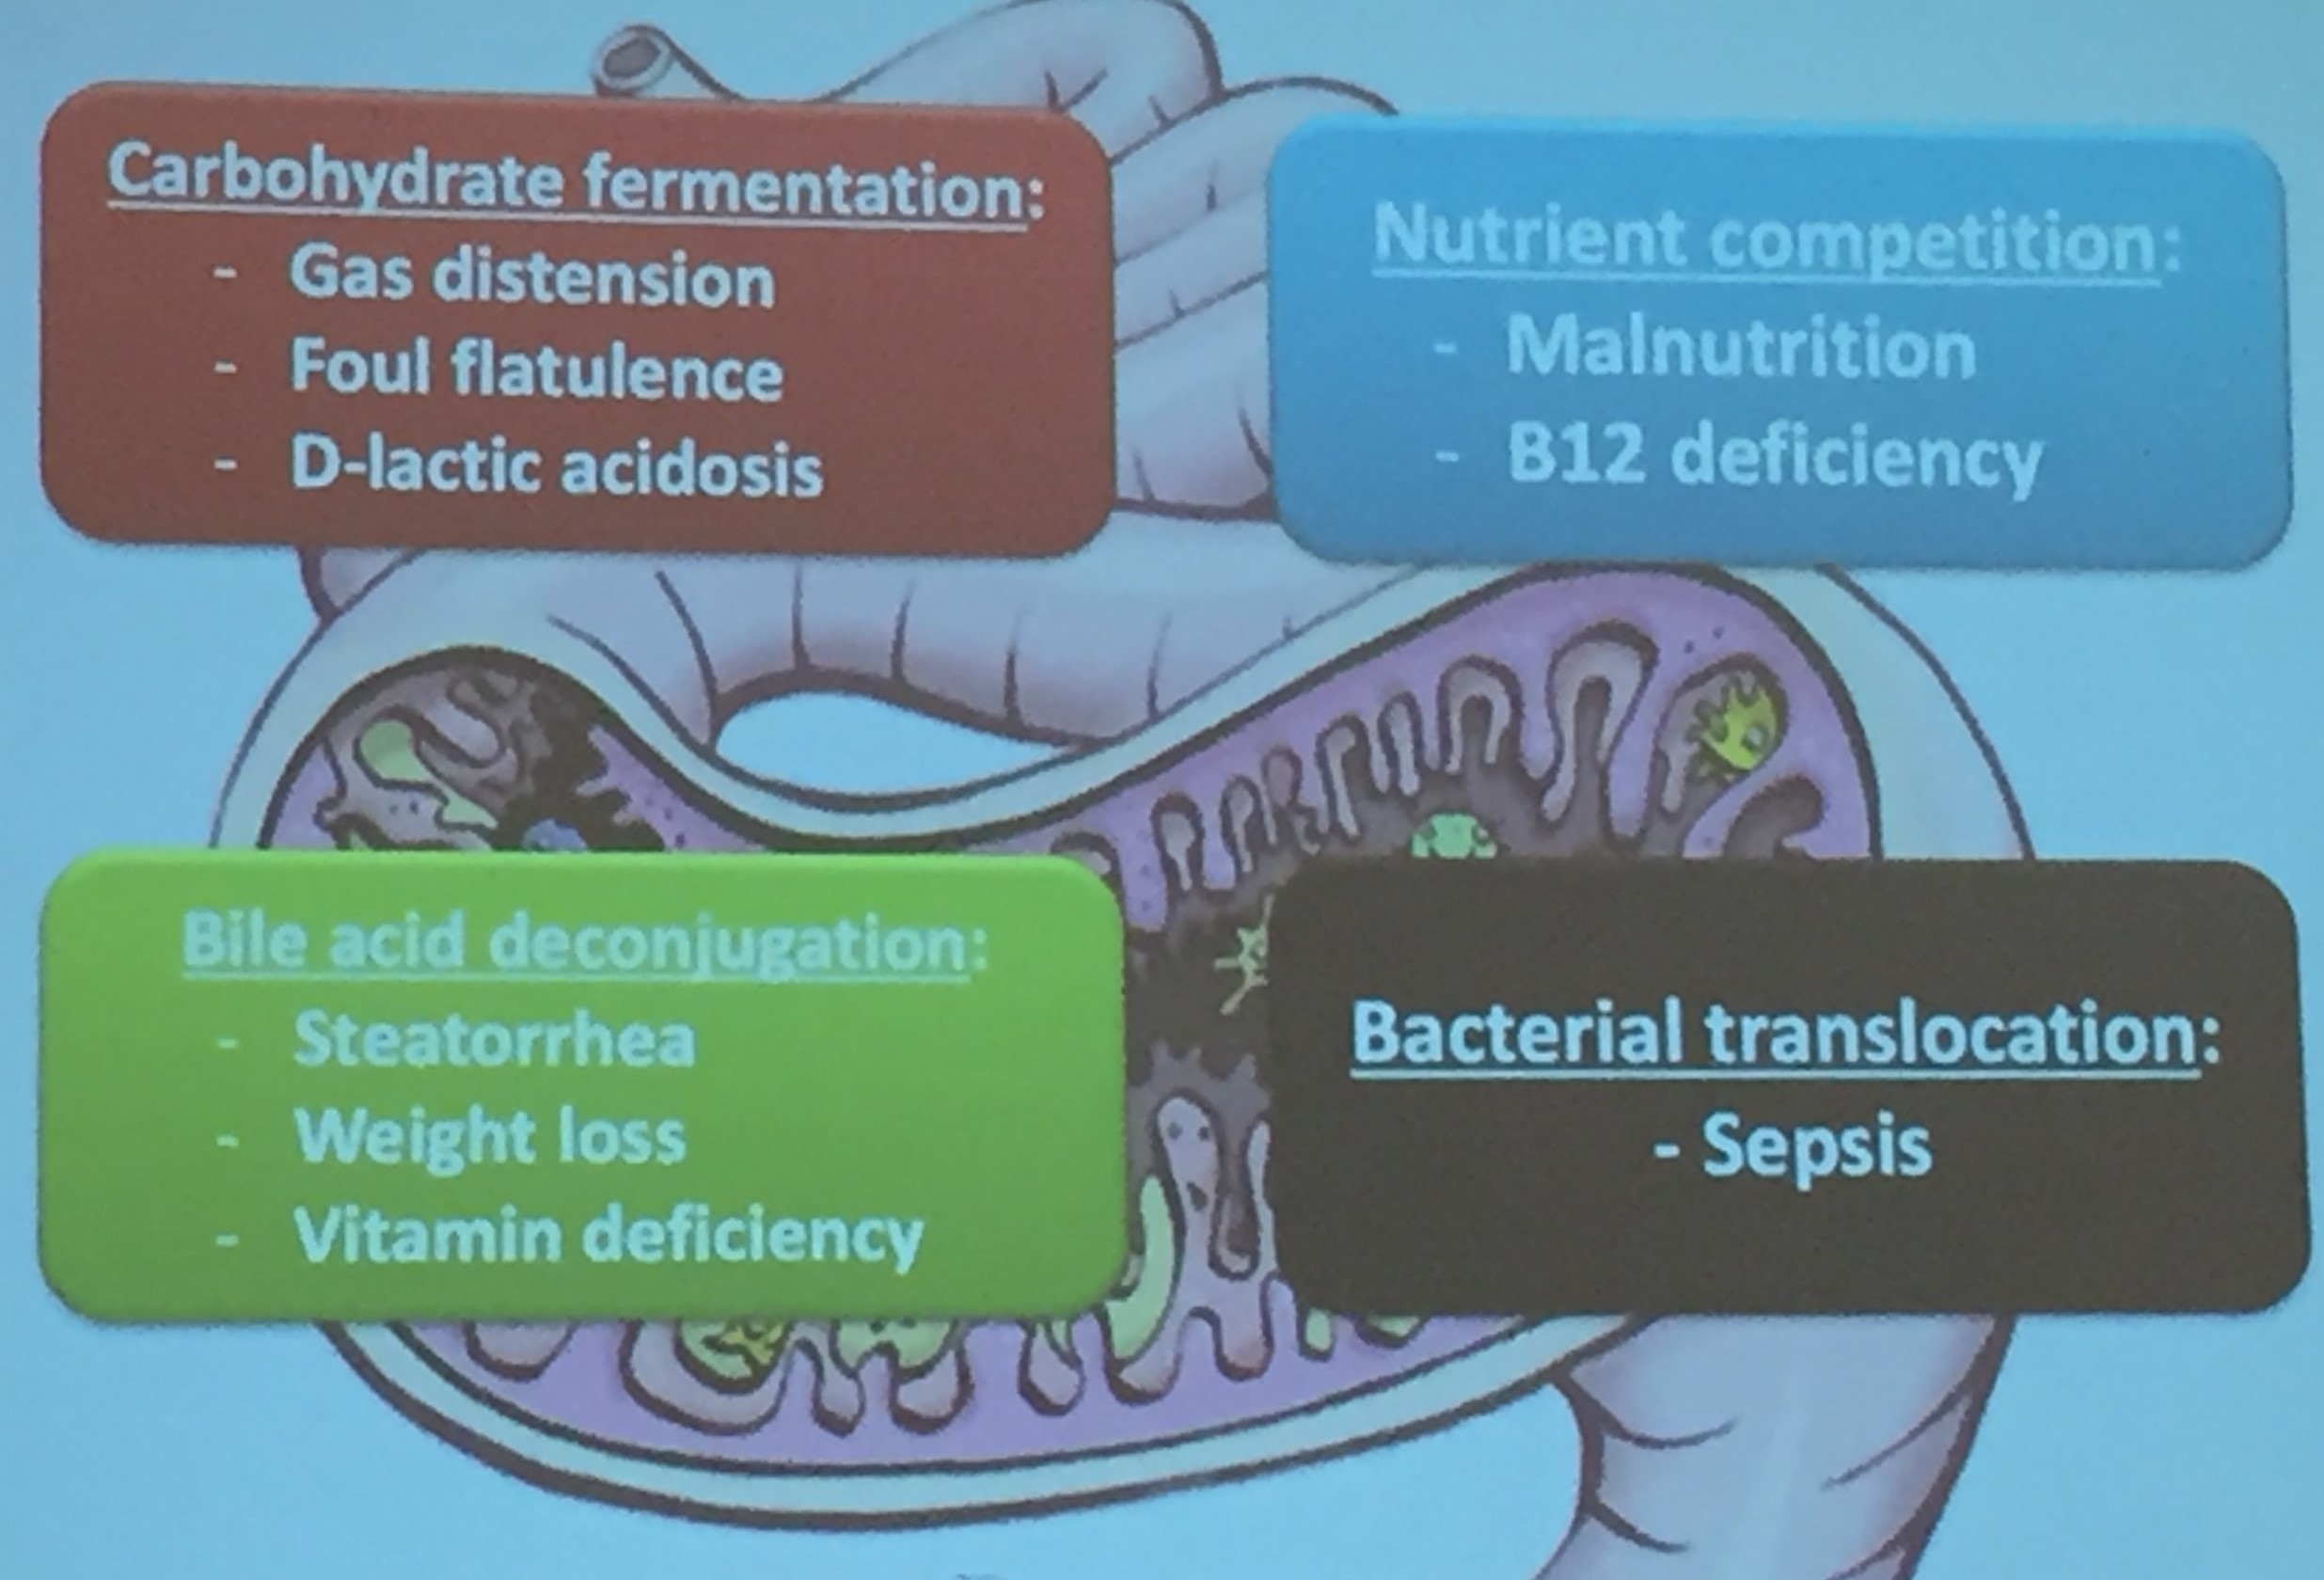
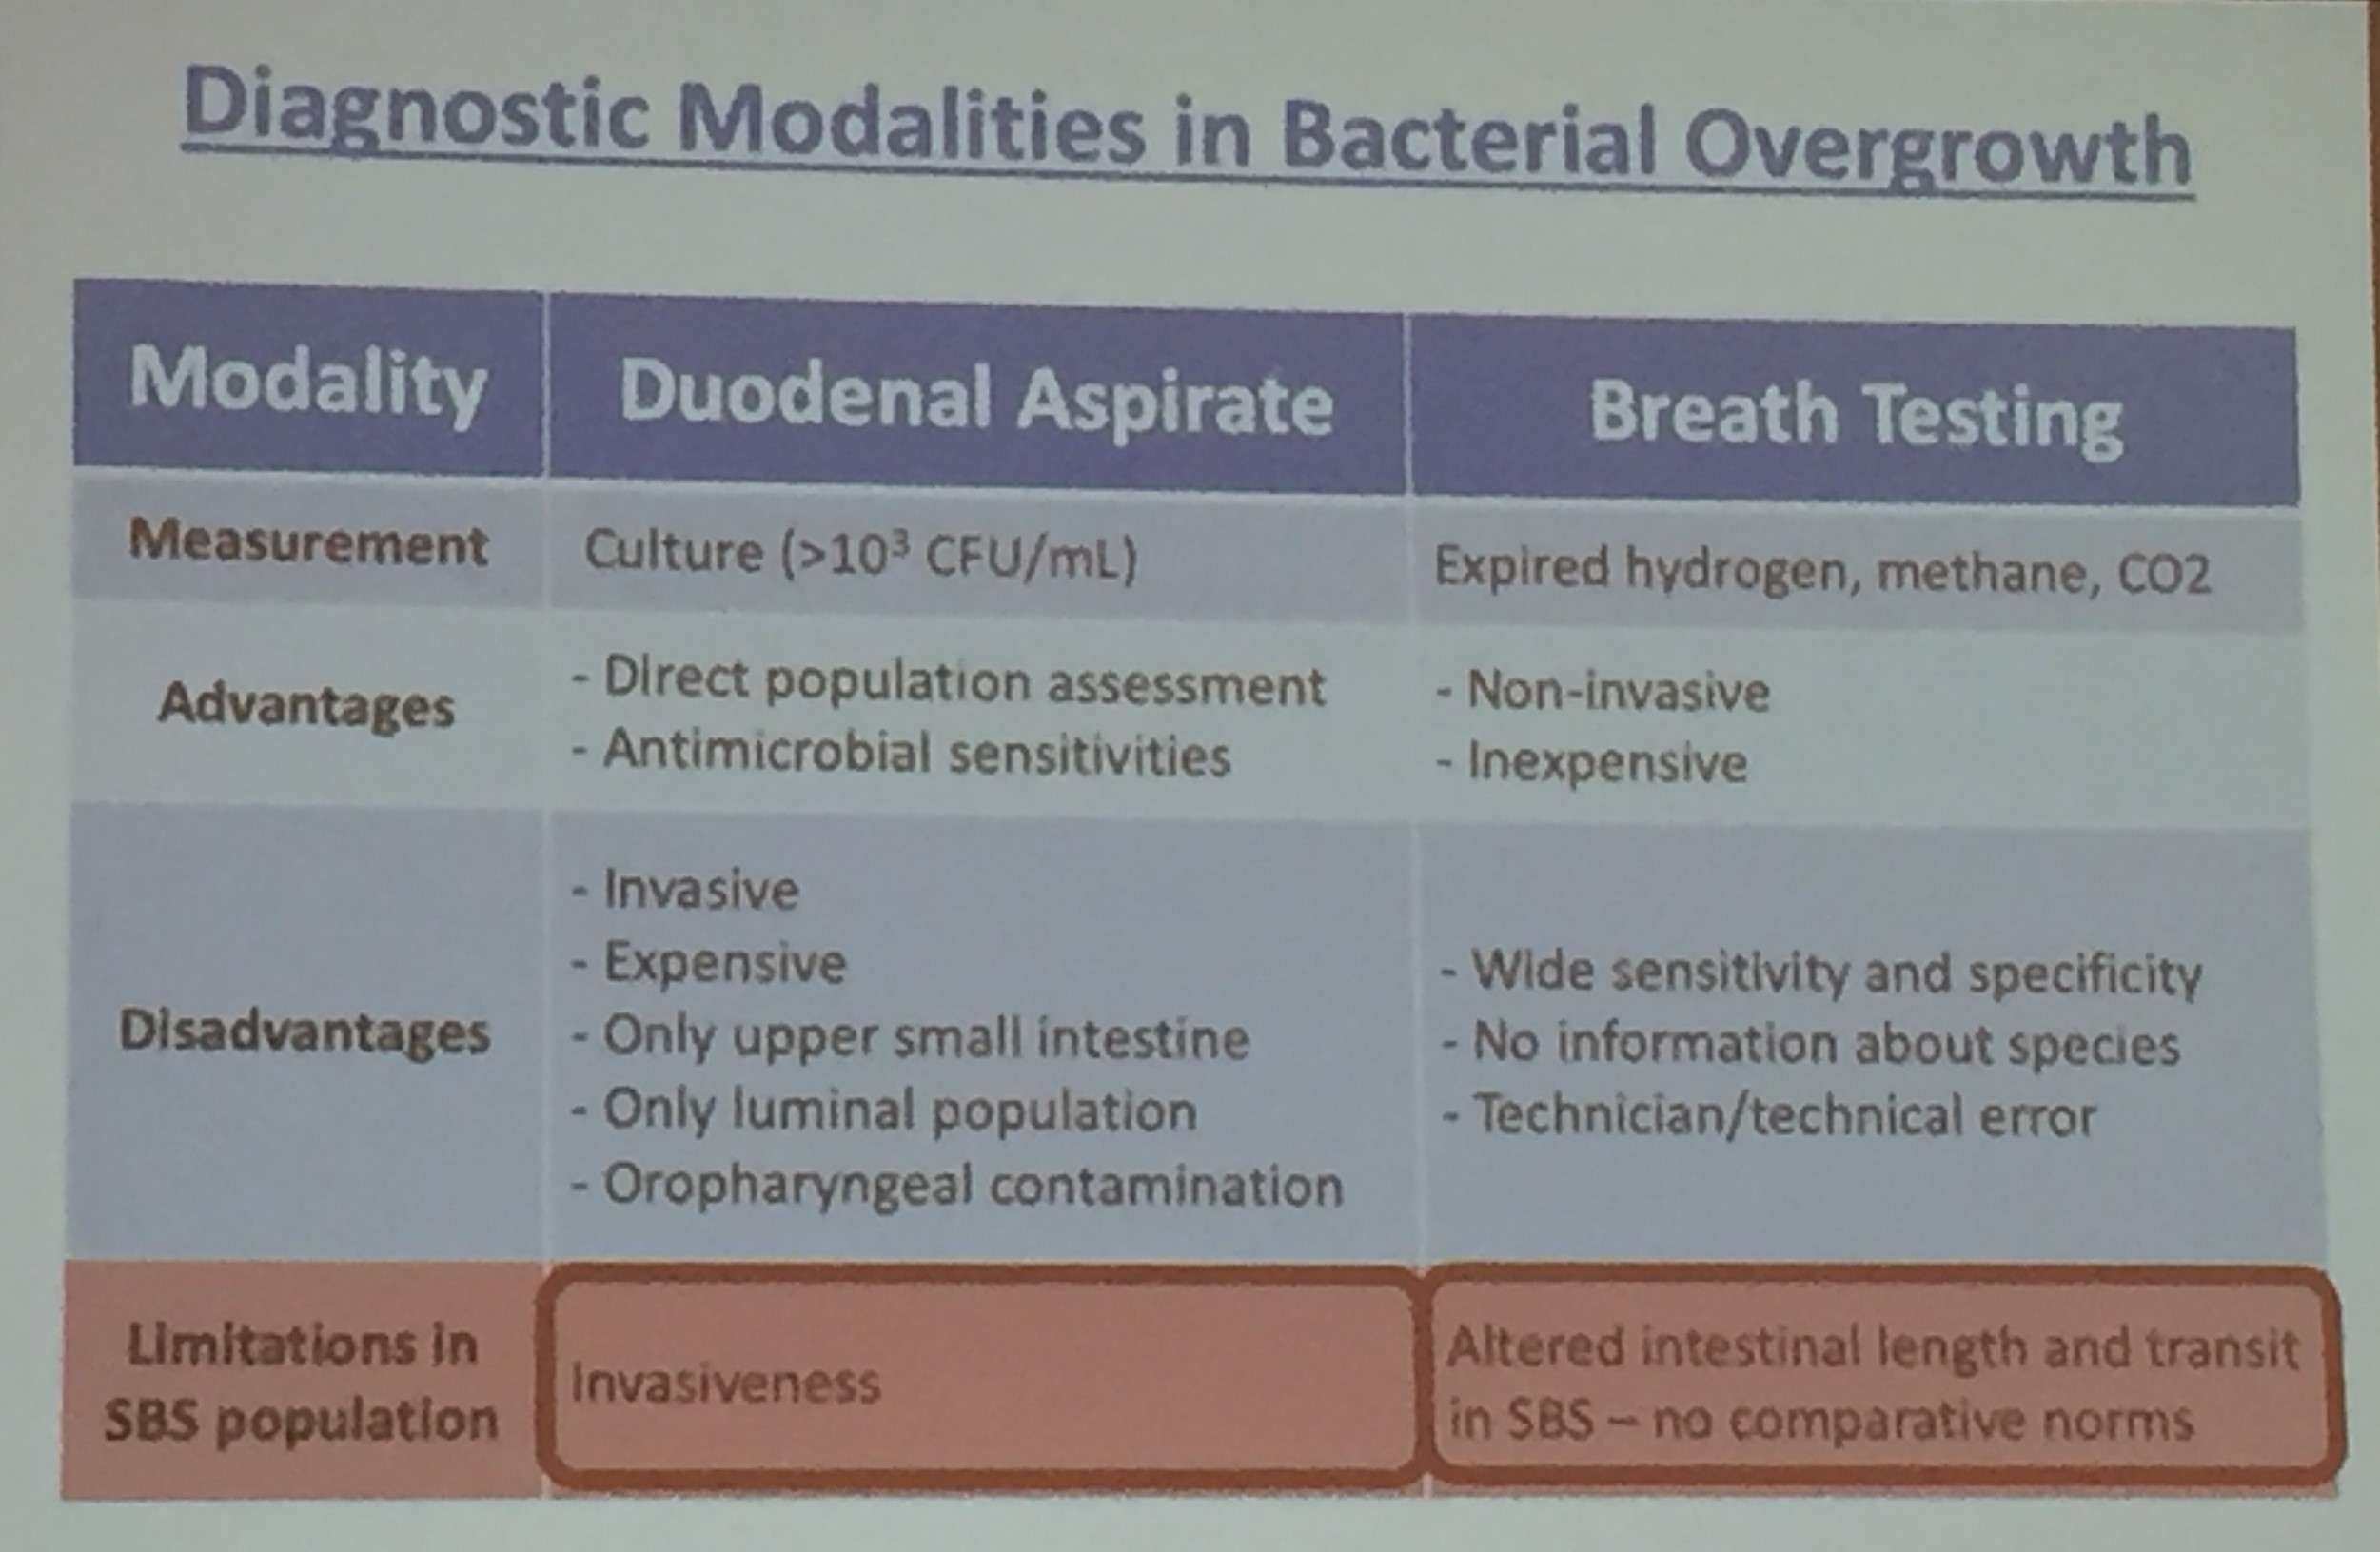
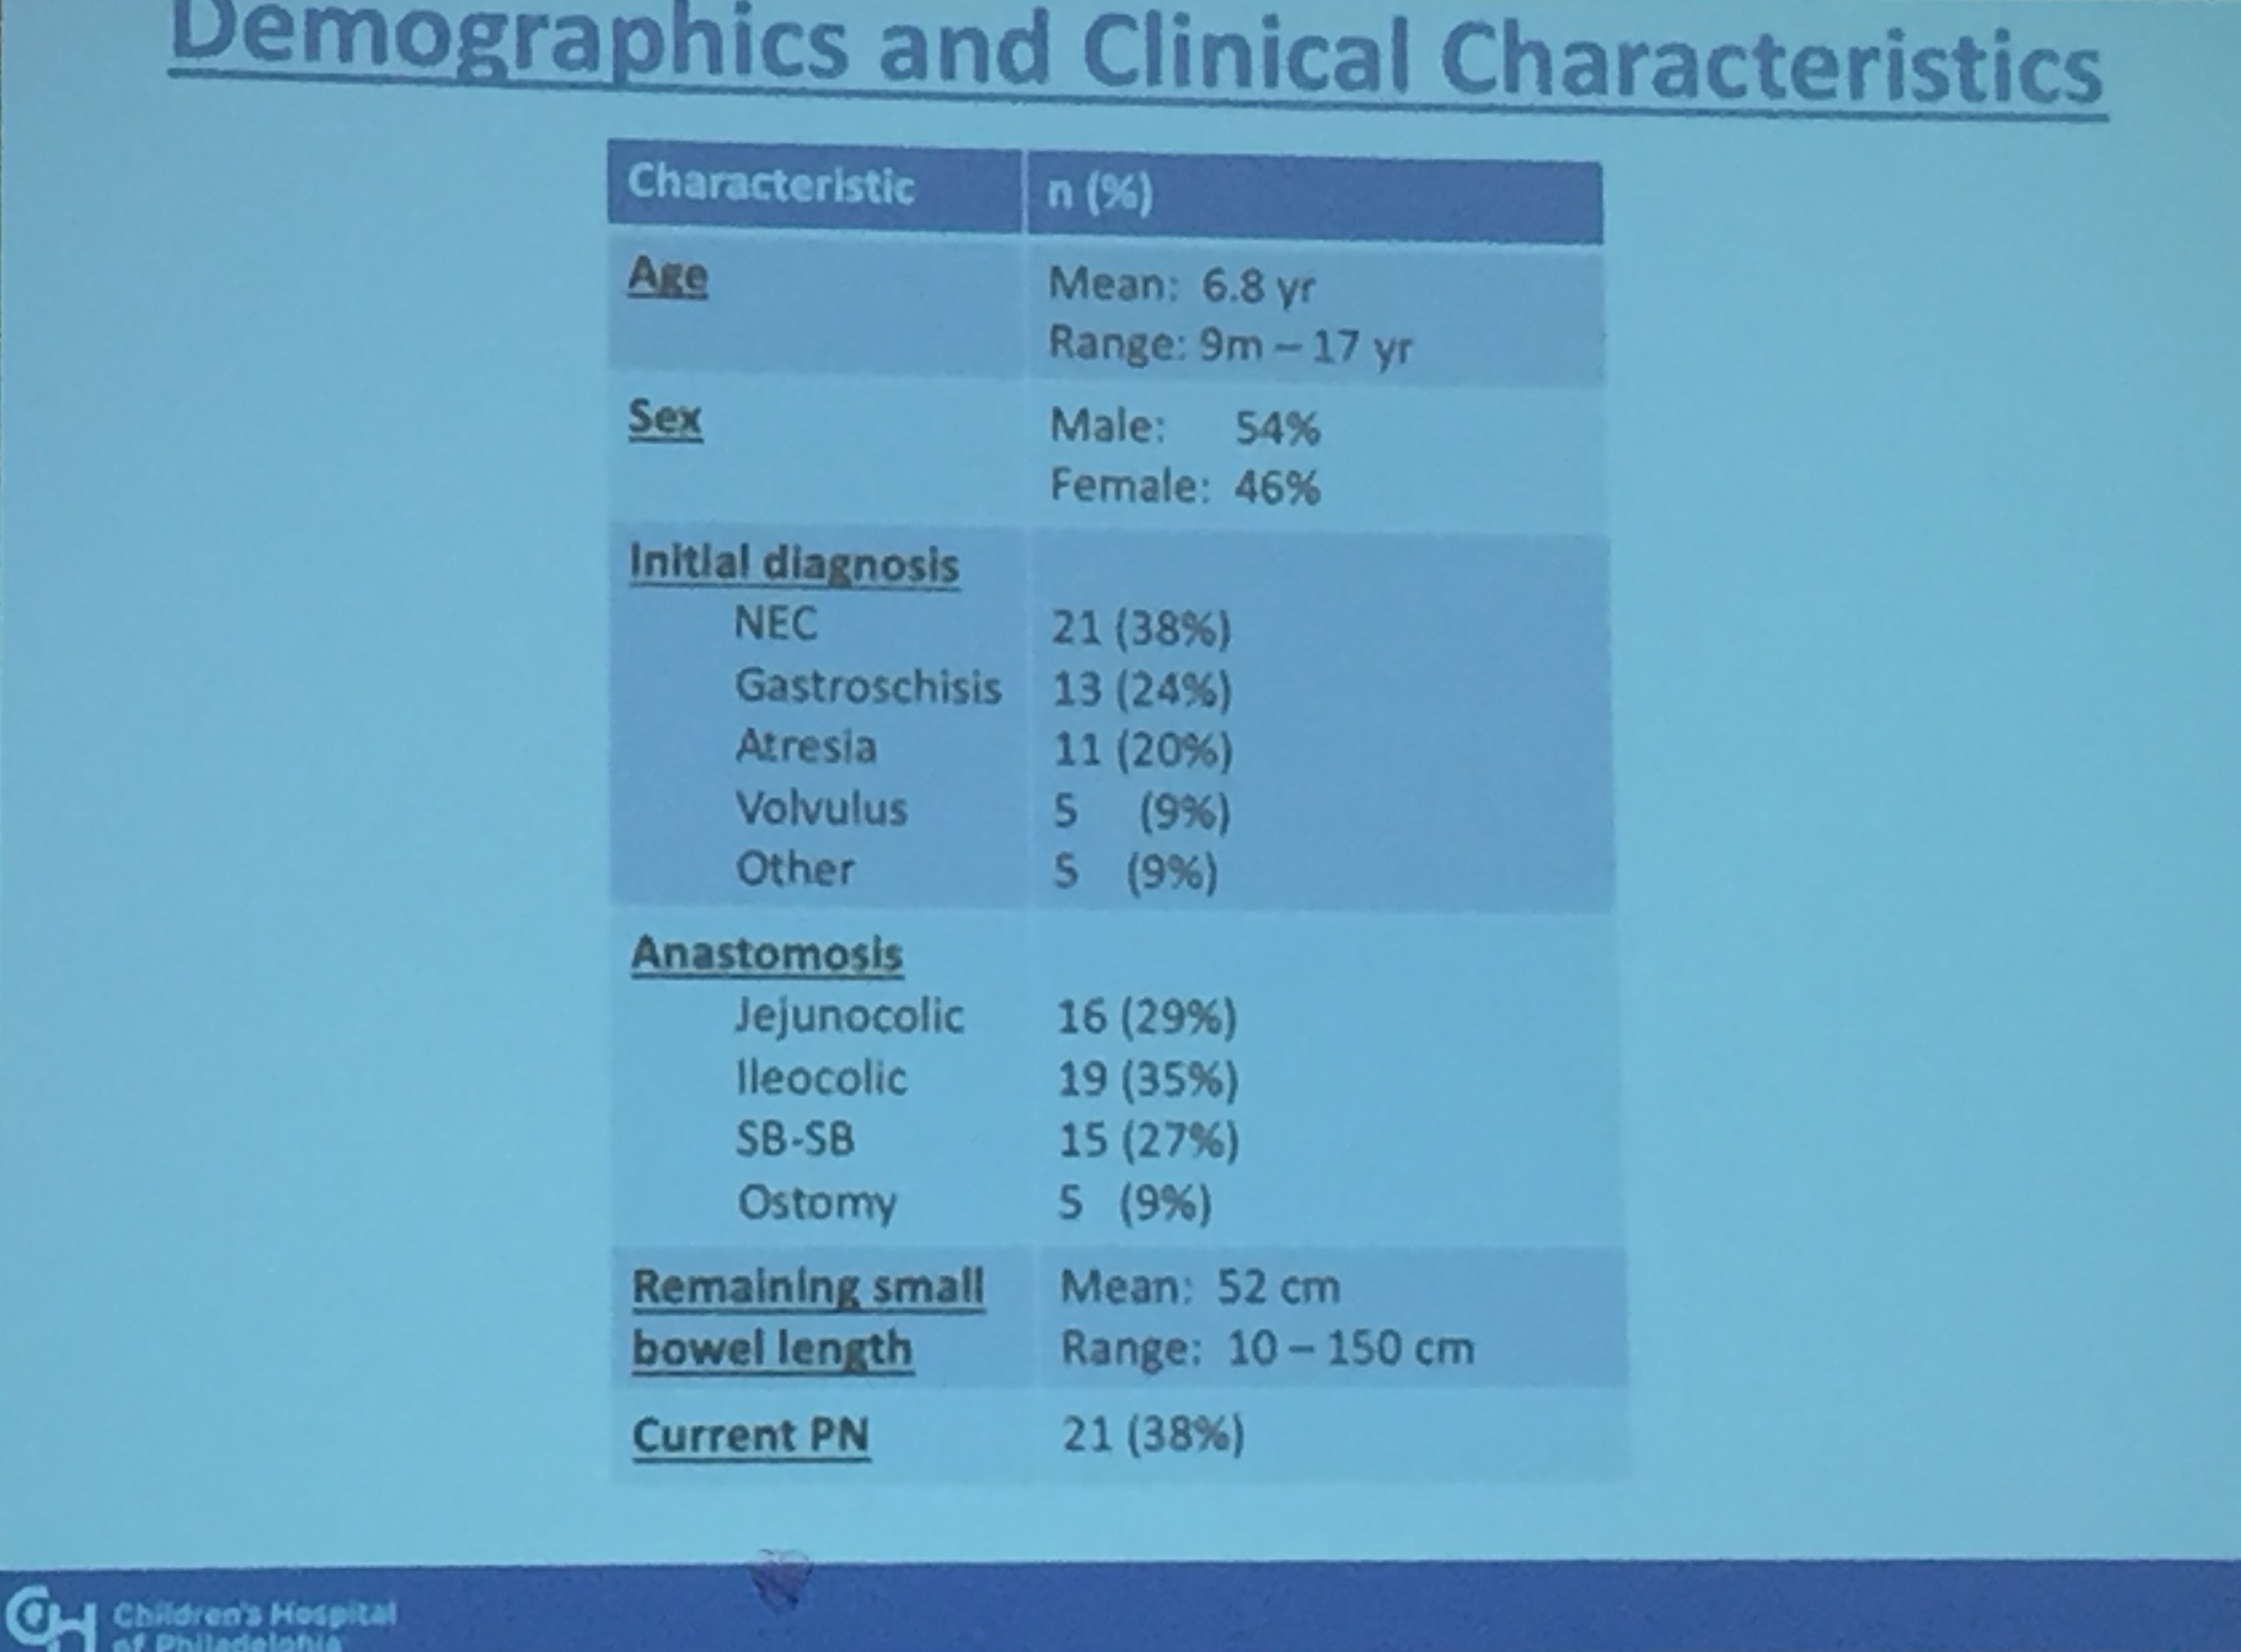
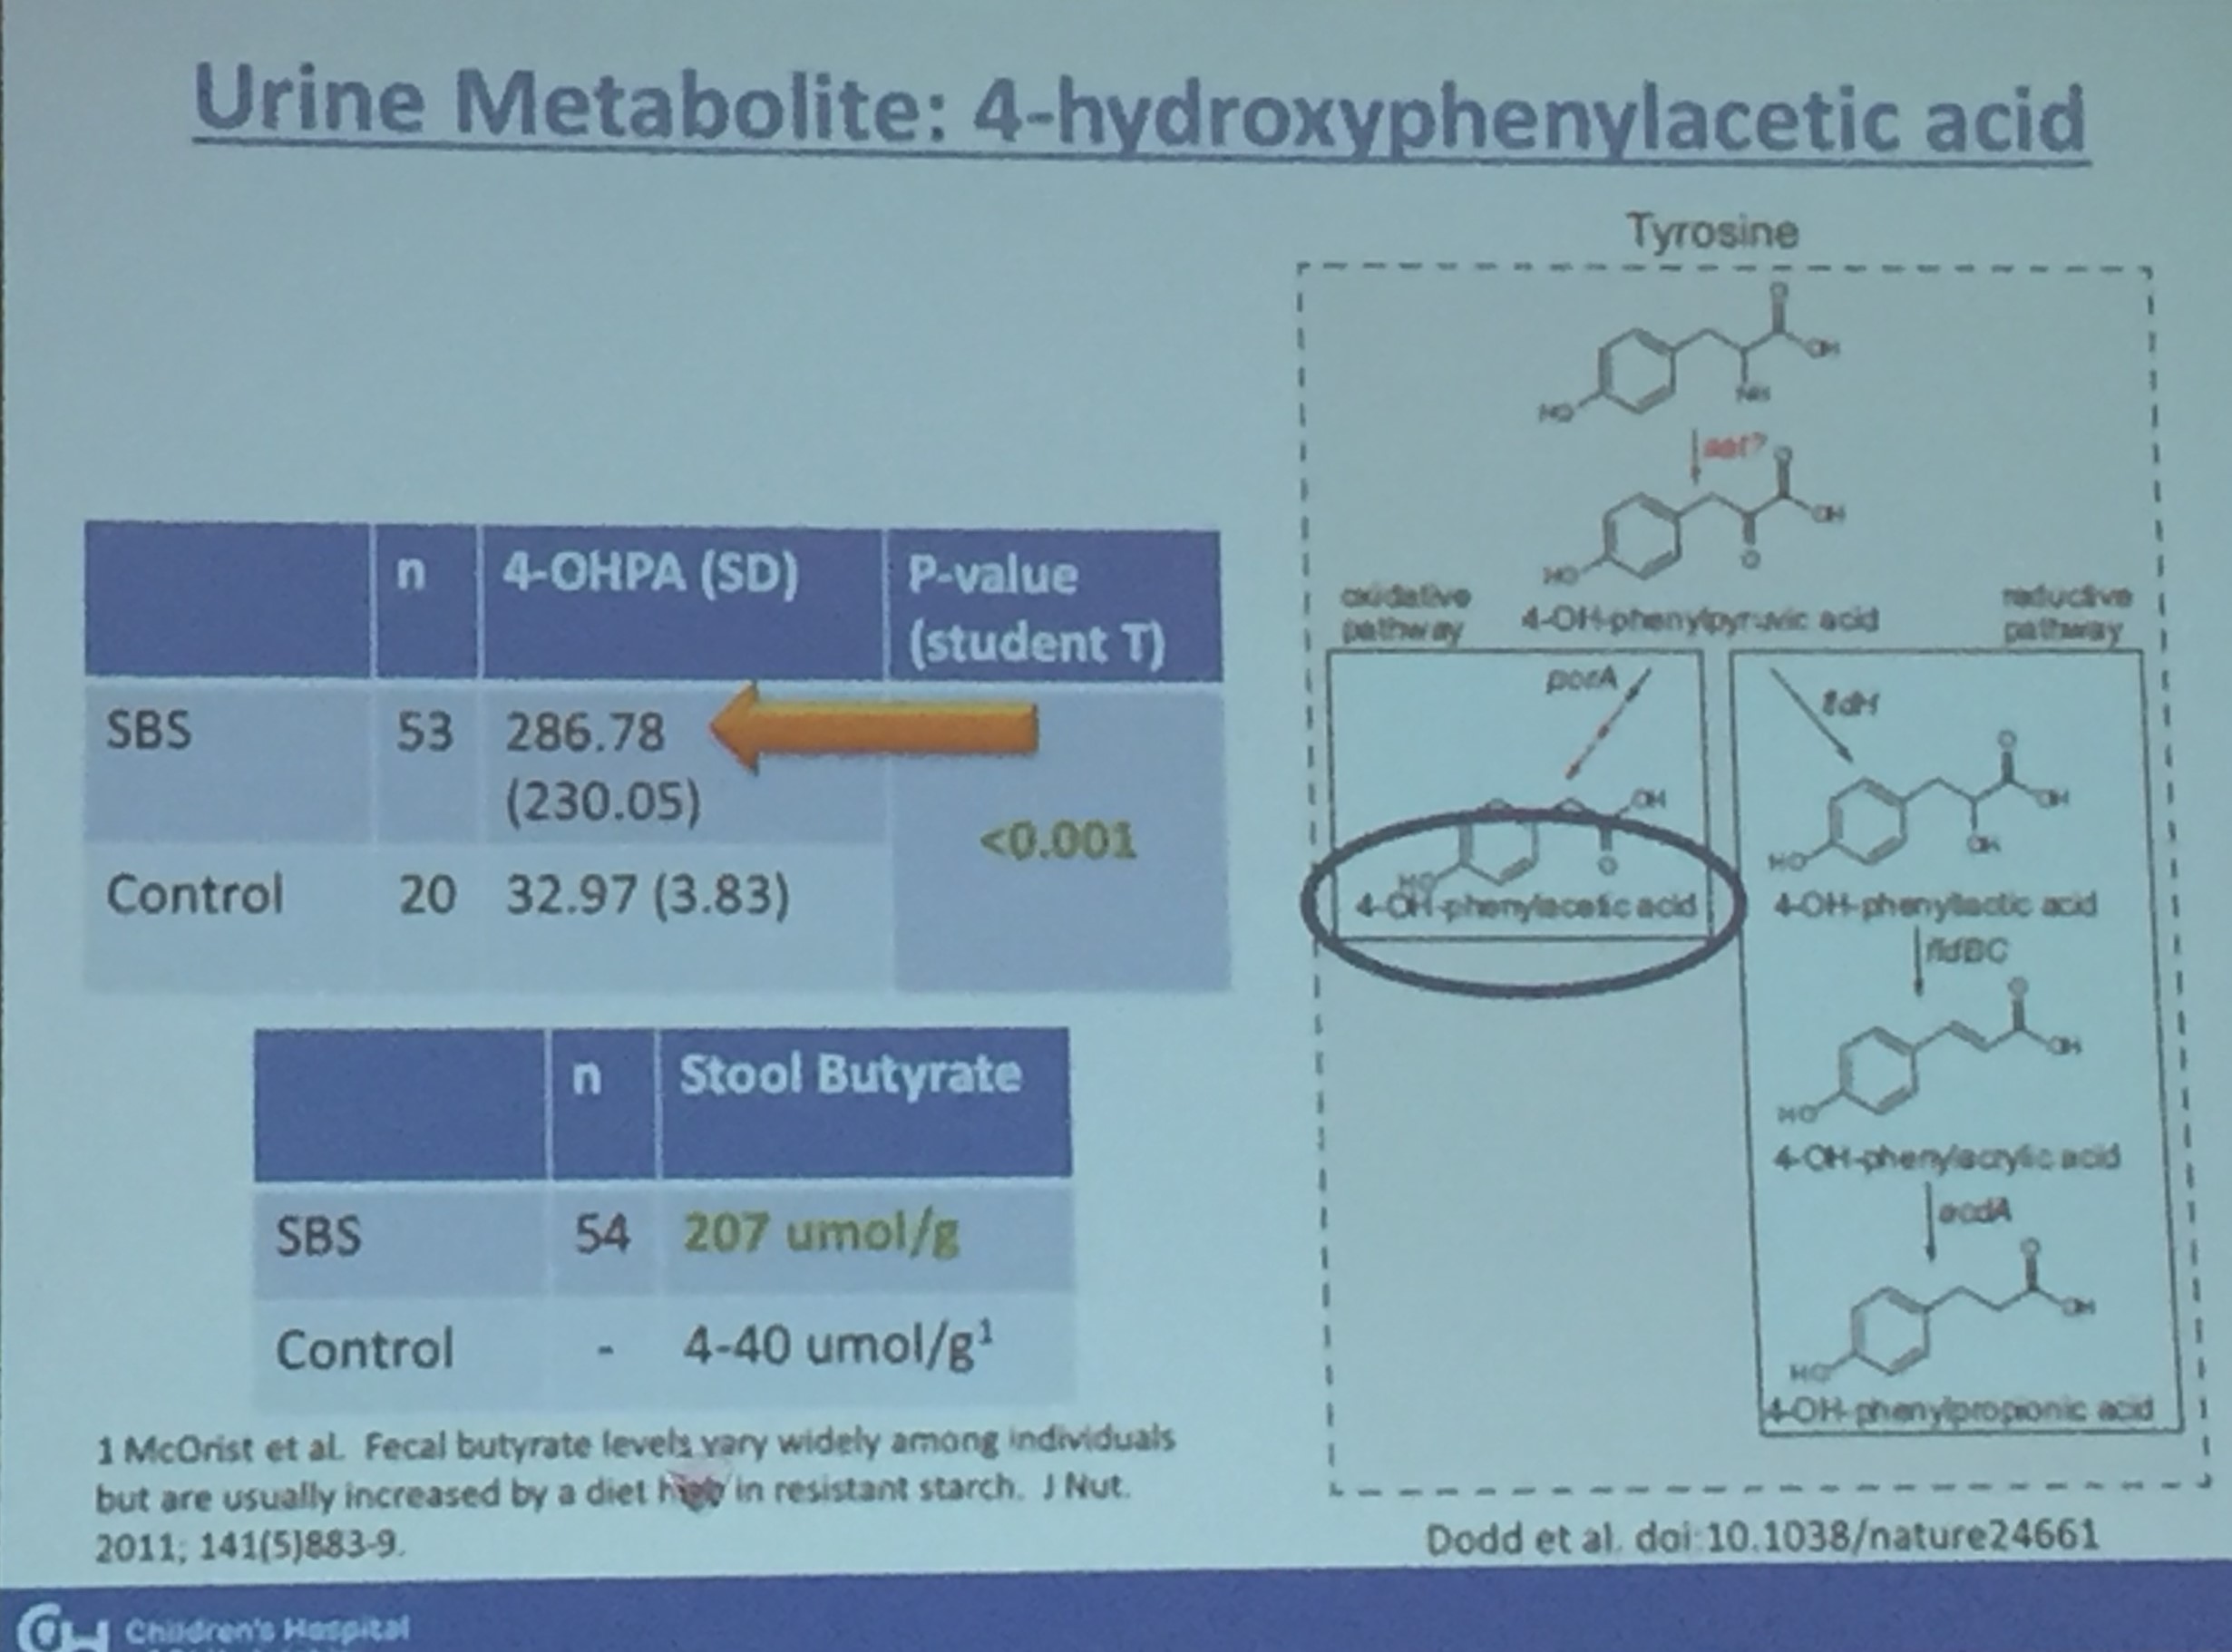
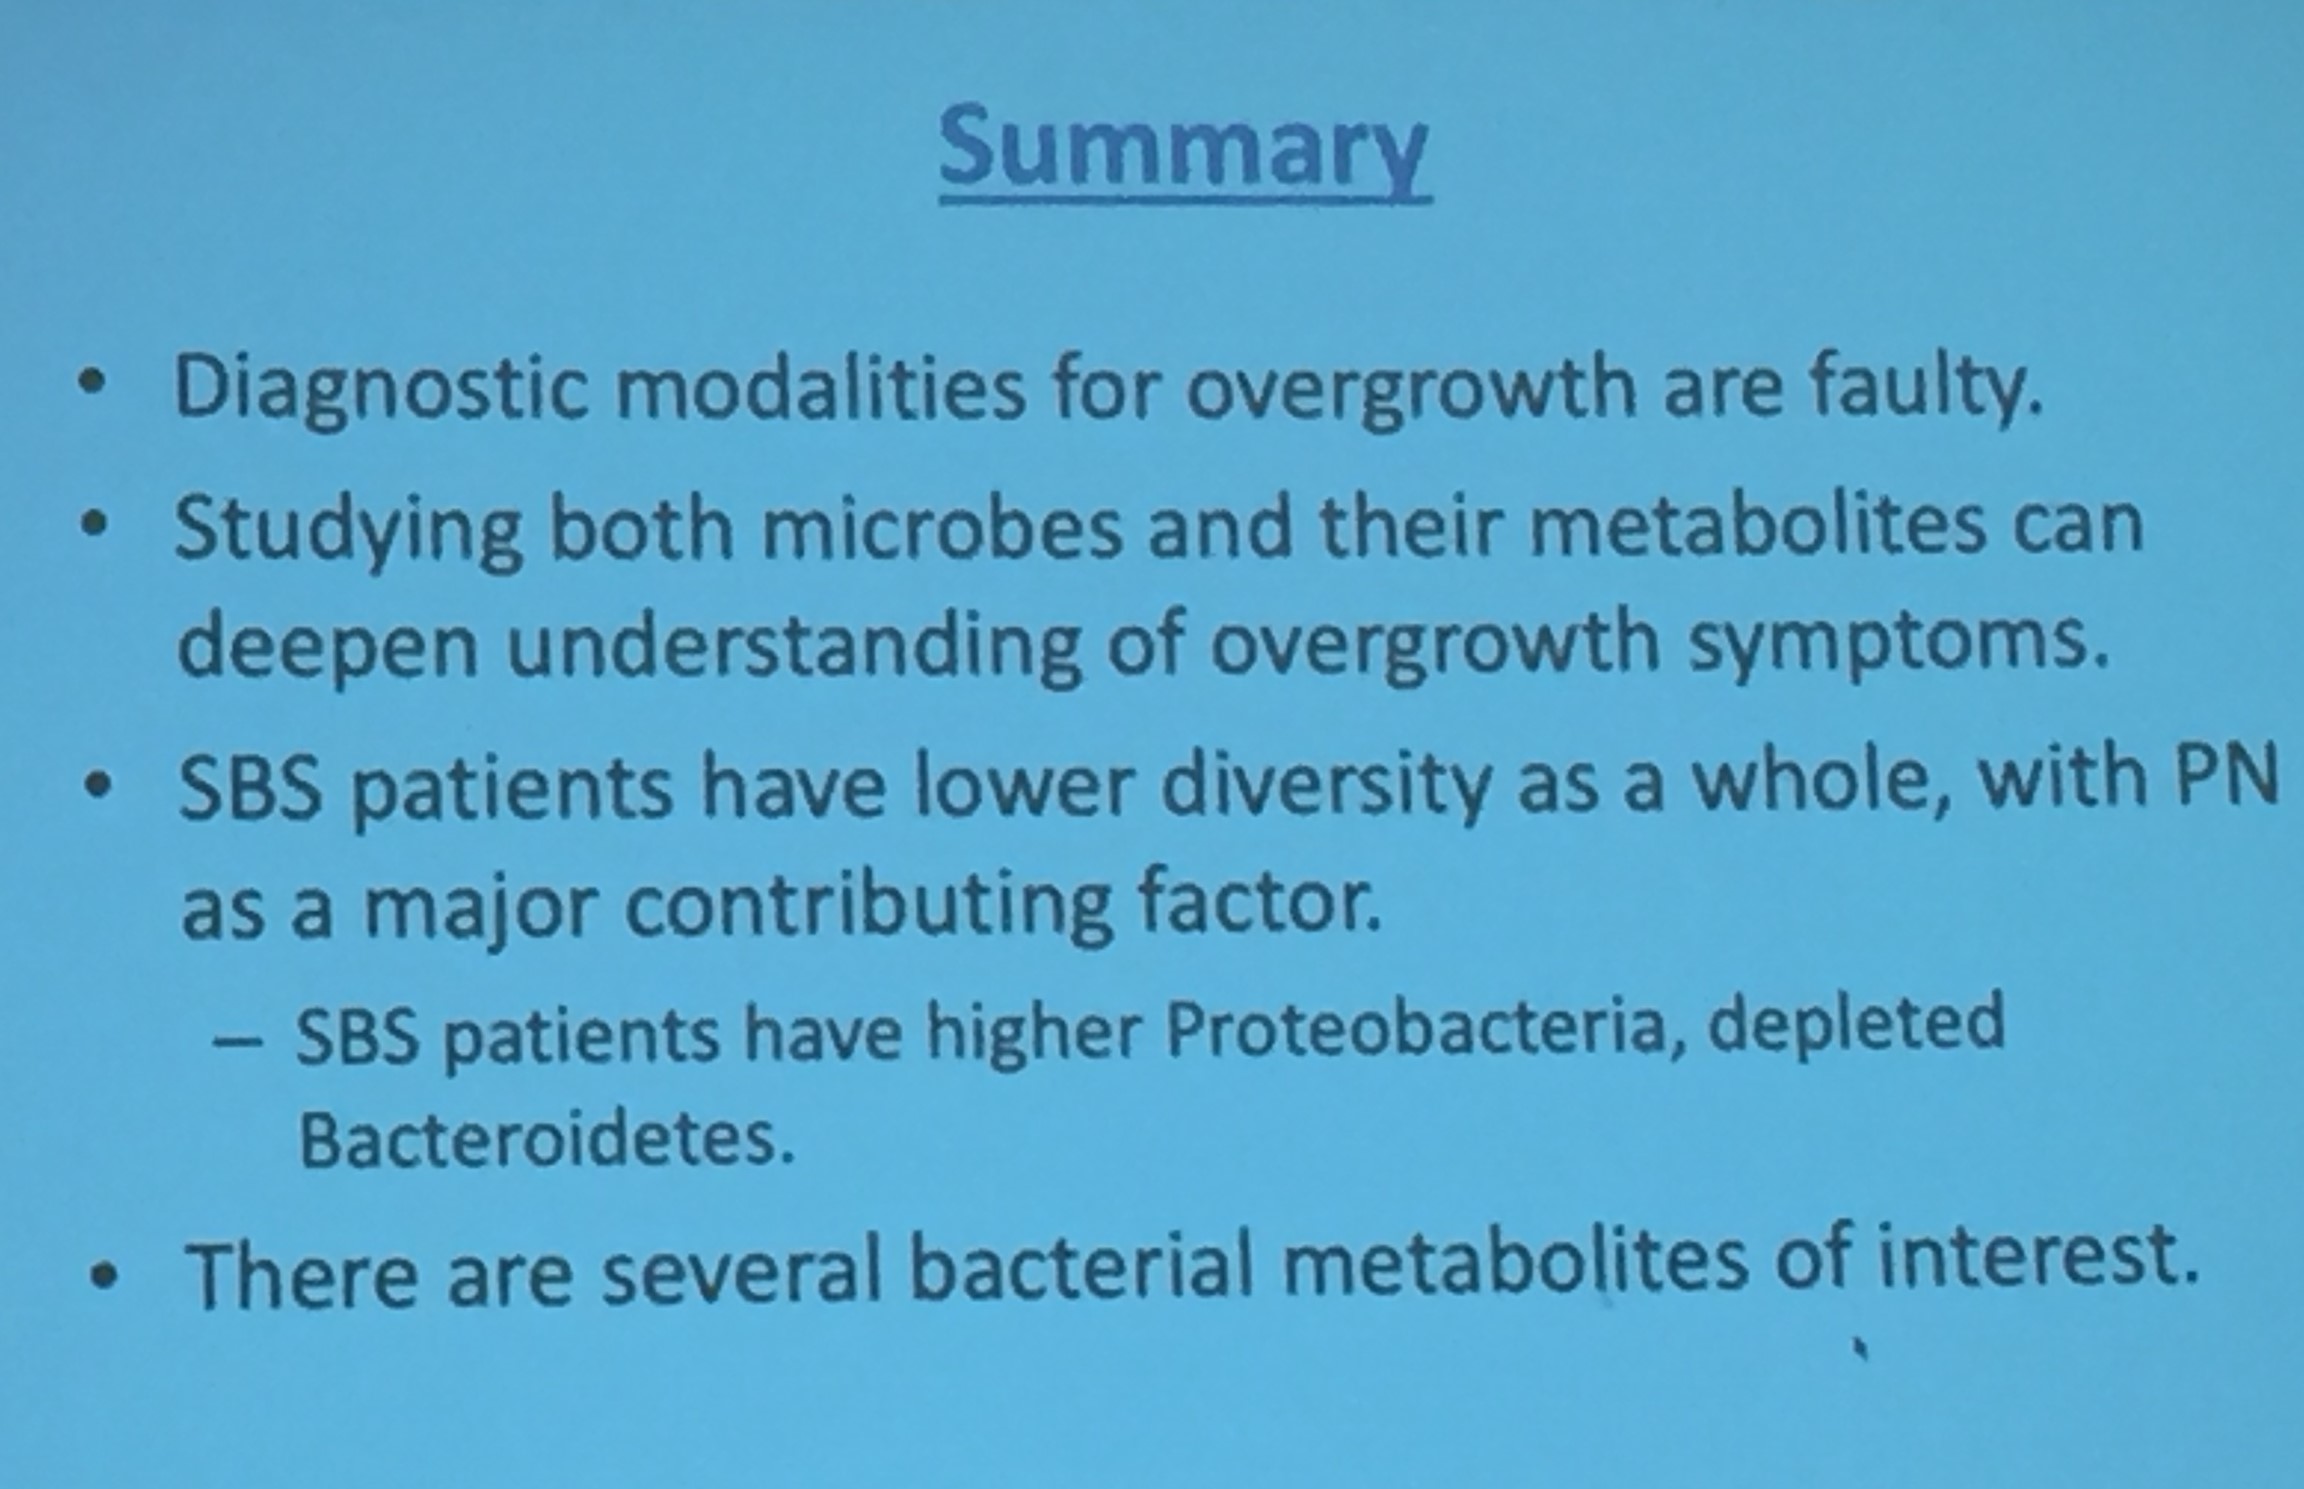
Arthur Kasti  Abstract 218  Microbial Metabolites as Markers of Intestinal Dysbiosis in Pediatric Short Bowel Syndrome

This was a terrific presentation. Key points:

  • Microbiome in SBS patients is less diverse
  • Current diagnosis of bacterial overgrowth is difficult and definitive diagnosis is often impractical
  • Several metabolites may be helpful in diagnosis of bacterial overgrowth

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

#NASPGHAN19 Intestinal Failure Session Part 1

Here are some notes and a few slides from NASPGHAN’s plenary session.  There could be errors of transcription in my notes.

Benjamin Gold, NASPGHAN president and part of our GI group, GI Care For Kids, welcomed everyone to the meeting.

Link to NASPGHAN_Annual_Meeting_Program 2019

John Kerner  Potential Role of New Fat Emulsions

Key points:

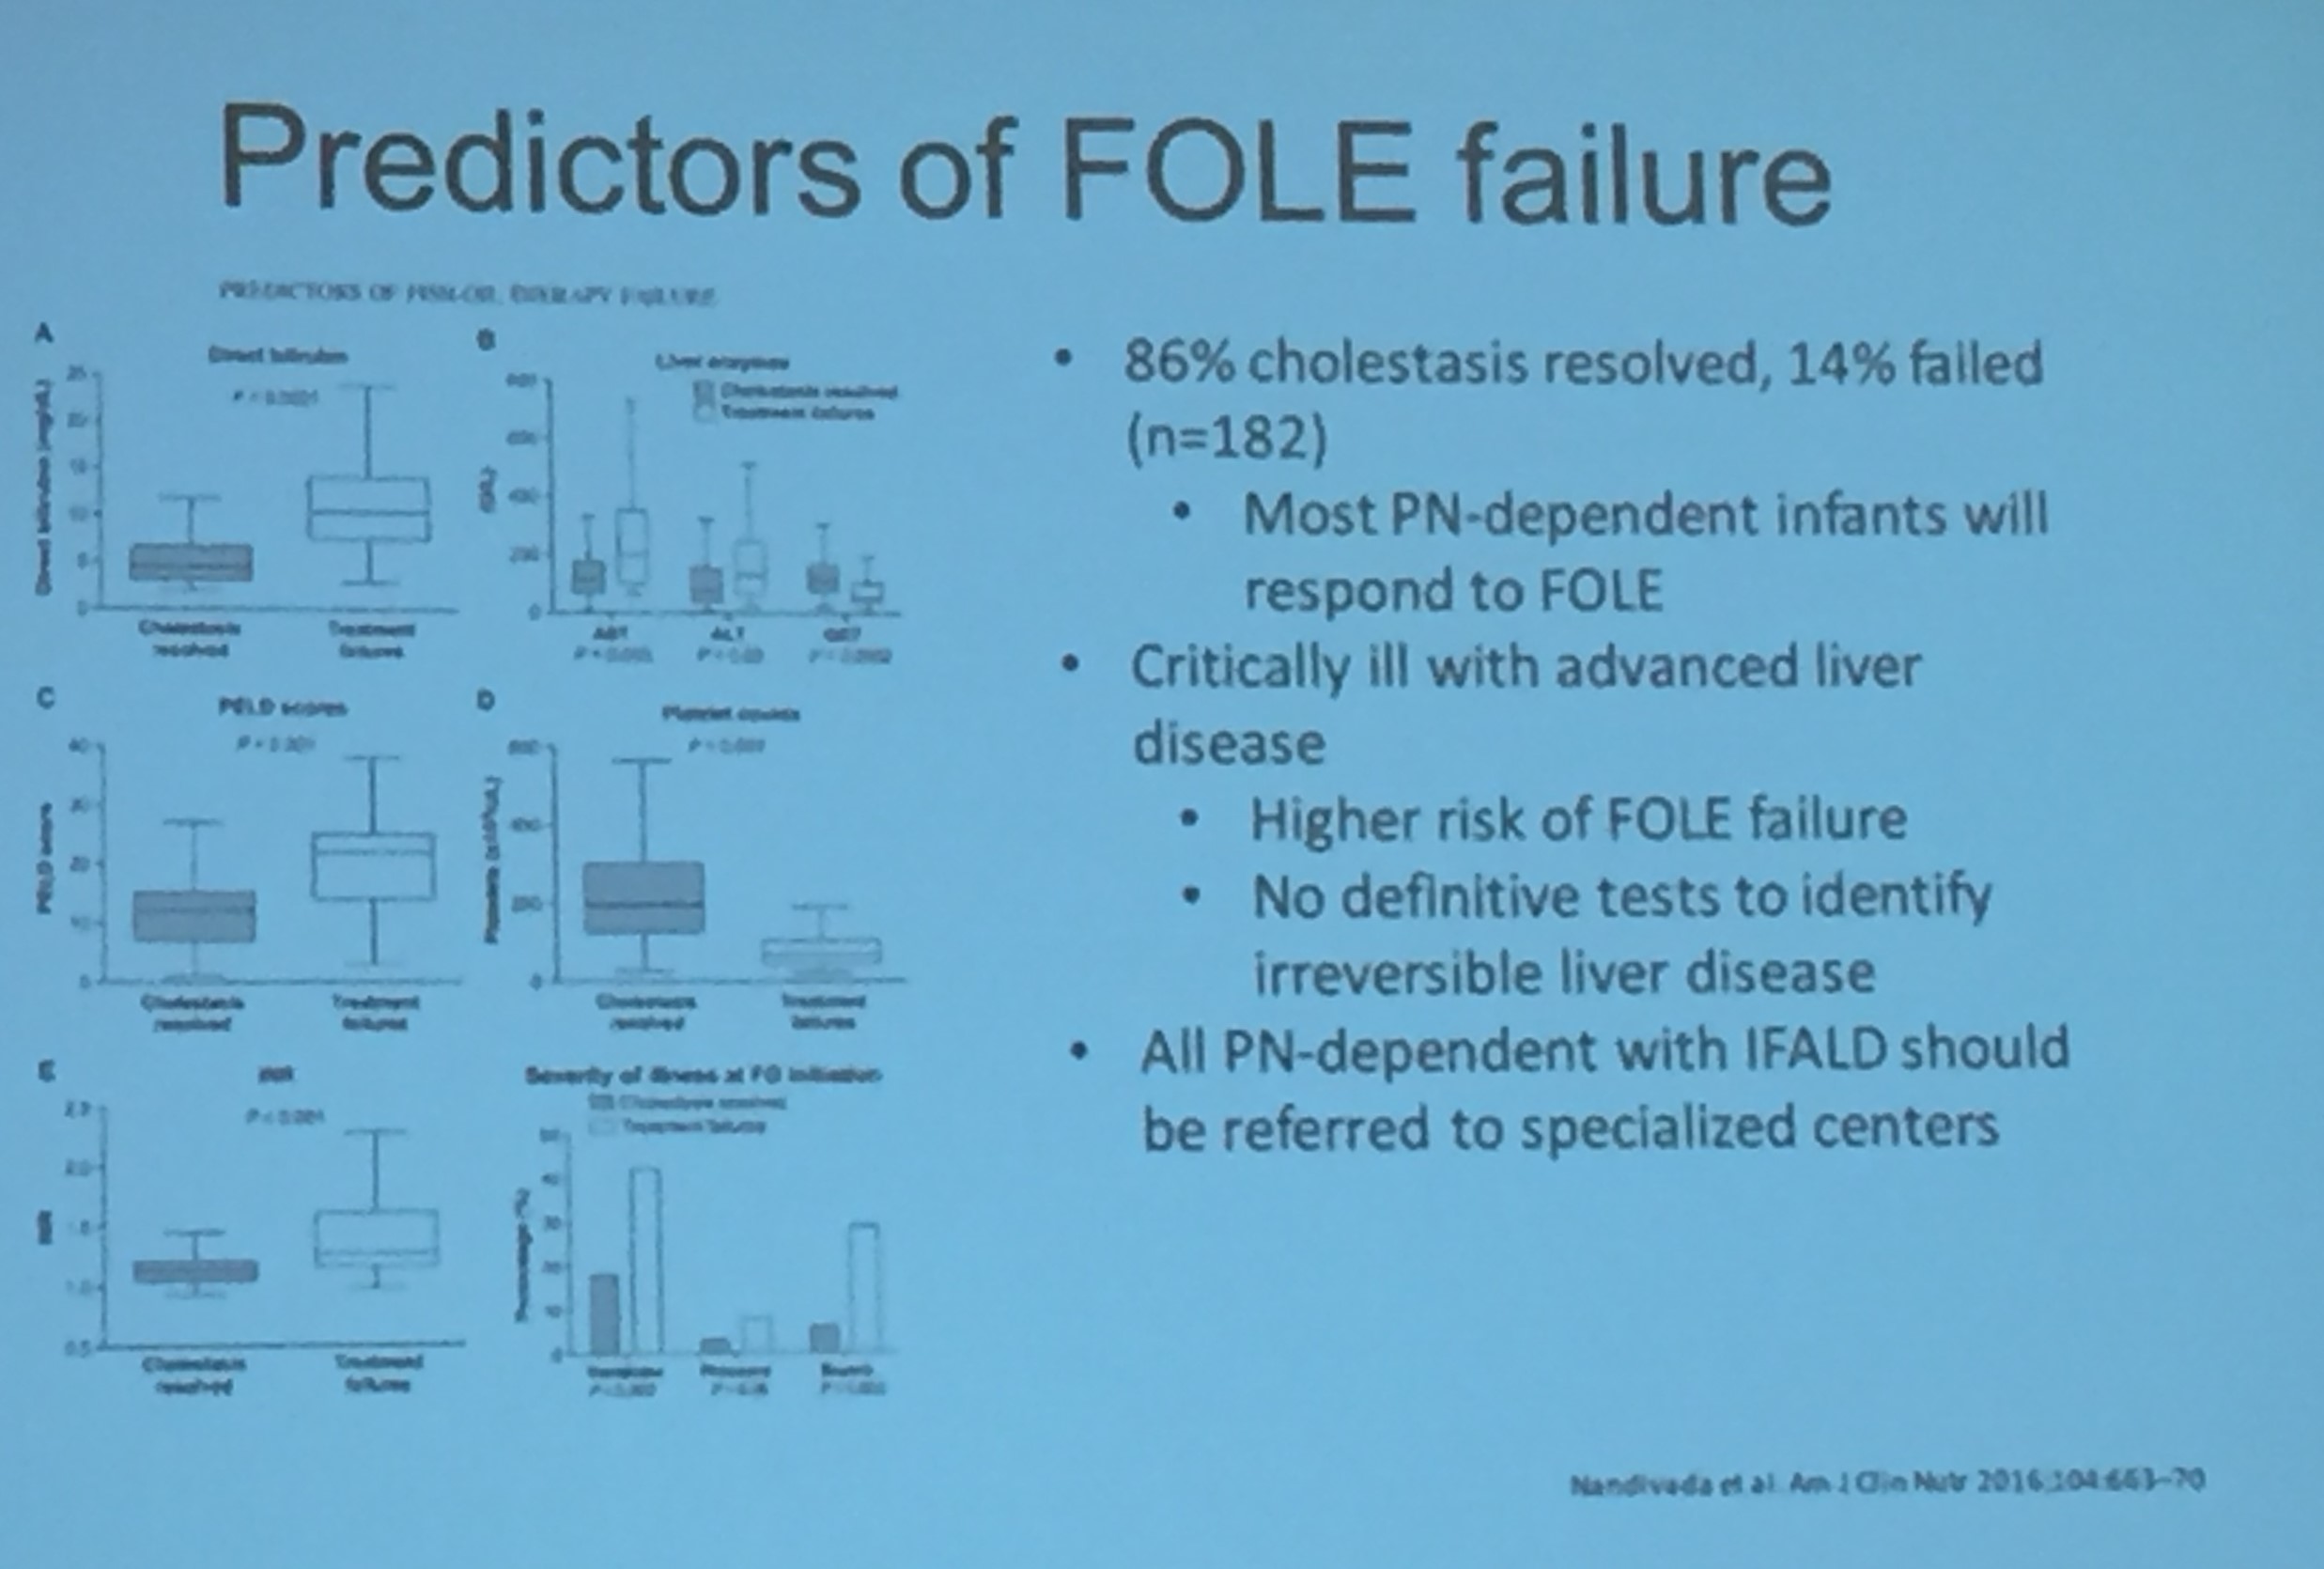
  • Both SMOFlipid and Omegaven help prevent and/or treat parenteral nutrition associated cholestasis.
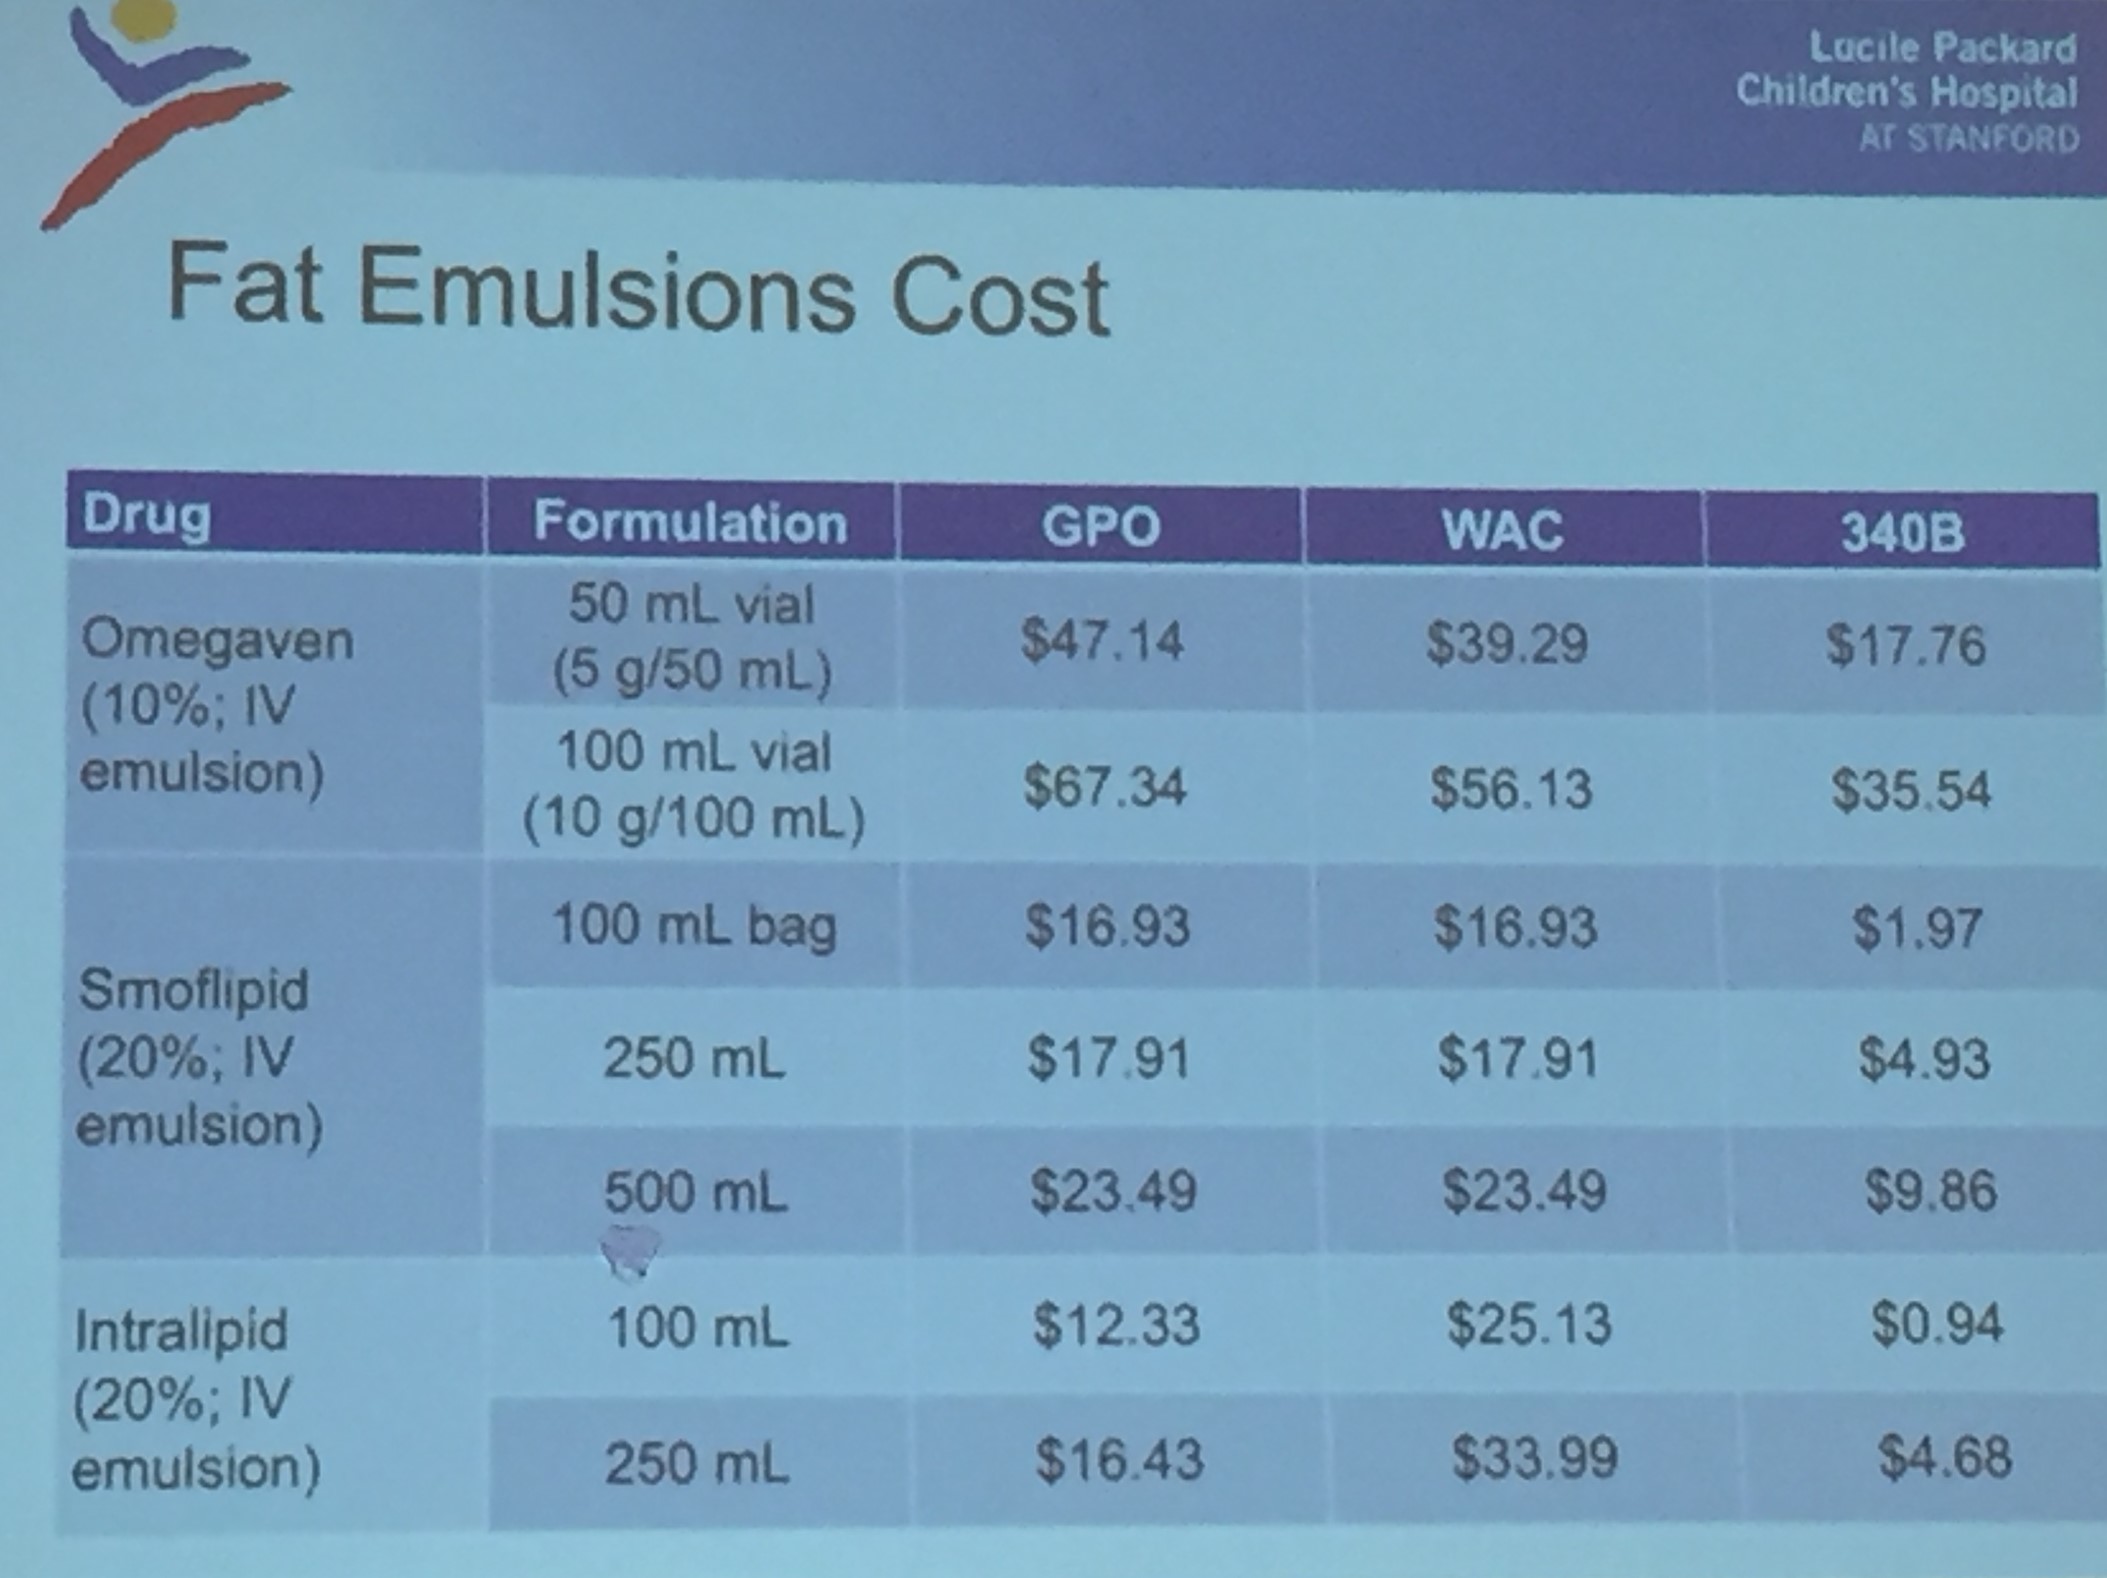
  • SMOFlipid is much less expensive (see slide below) -50 gm of SMOFlipid ~$5 compared to 10 gm of Omegaven at $35, thus omegaven costs more than 30 times SMOFlipid.
  • Though SMOFlipid is not FDA approved in children, it is being used widely and allows for increased calories compared to lipid minimization with intralipid and could improve neurocognitive outcomes.
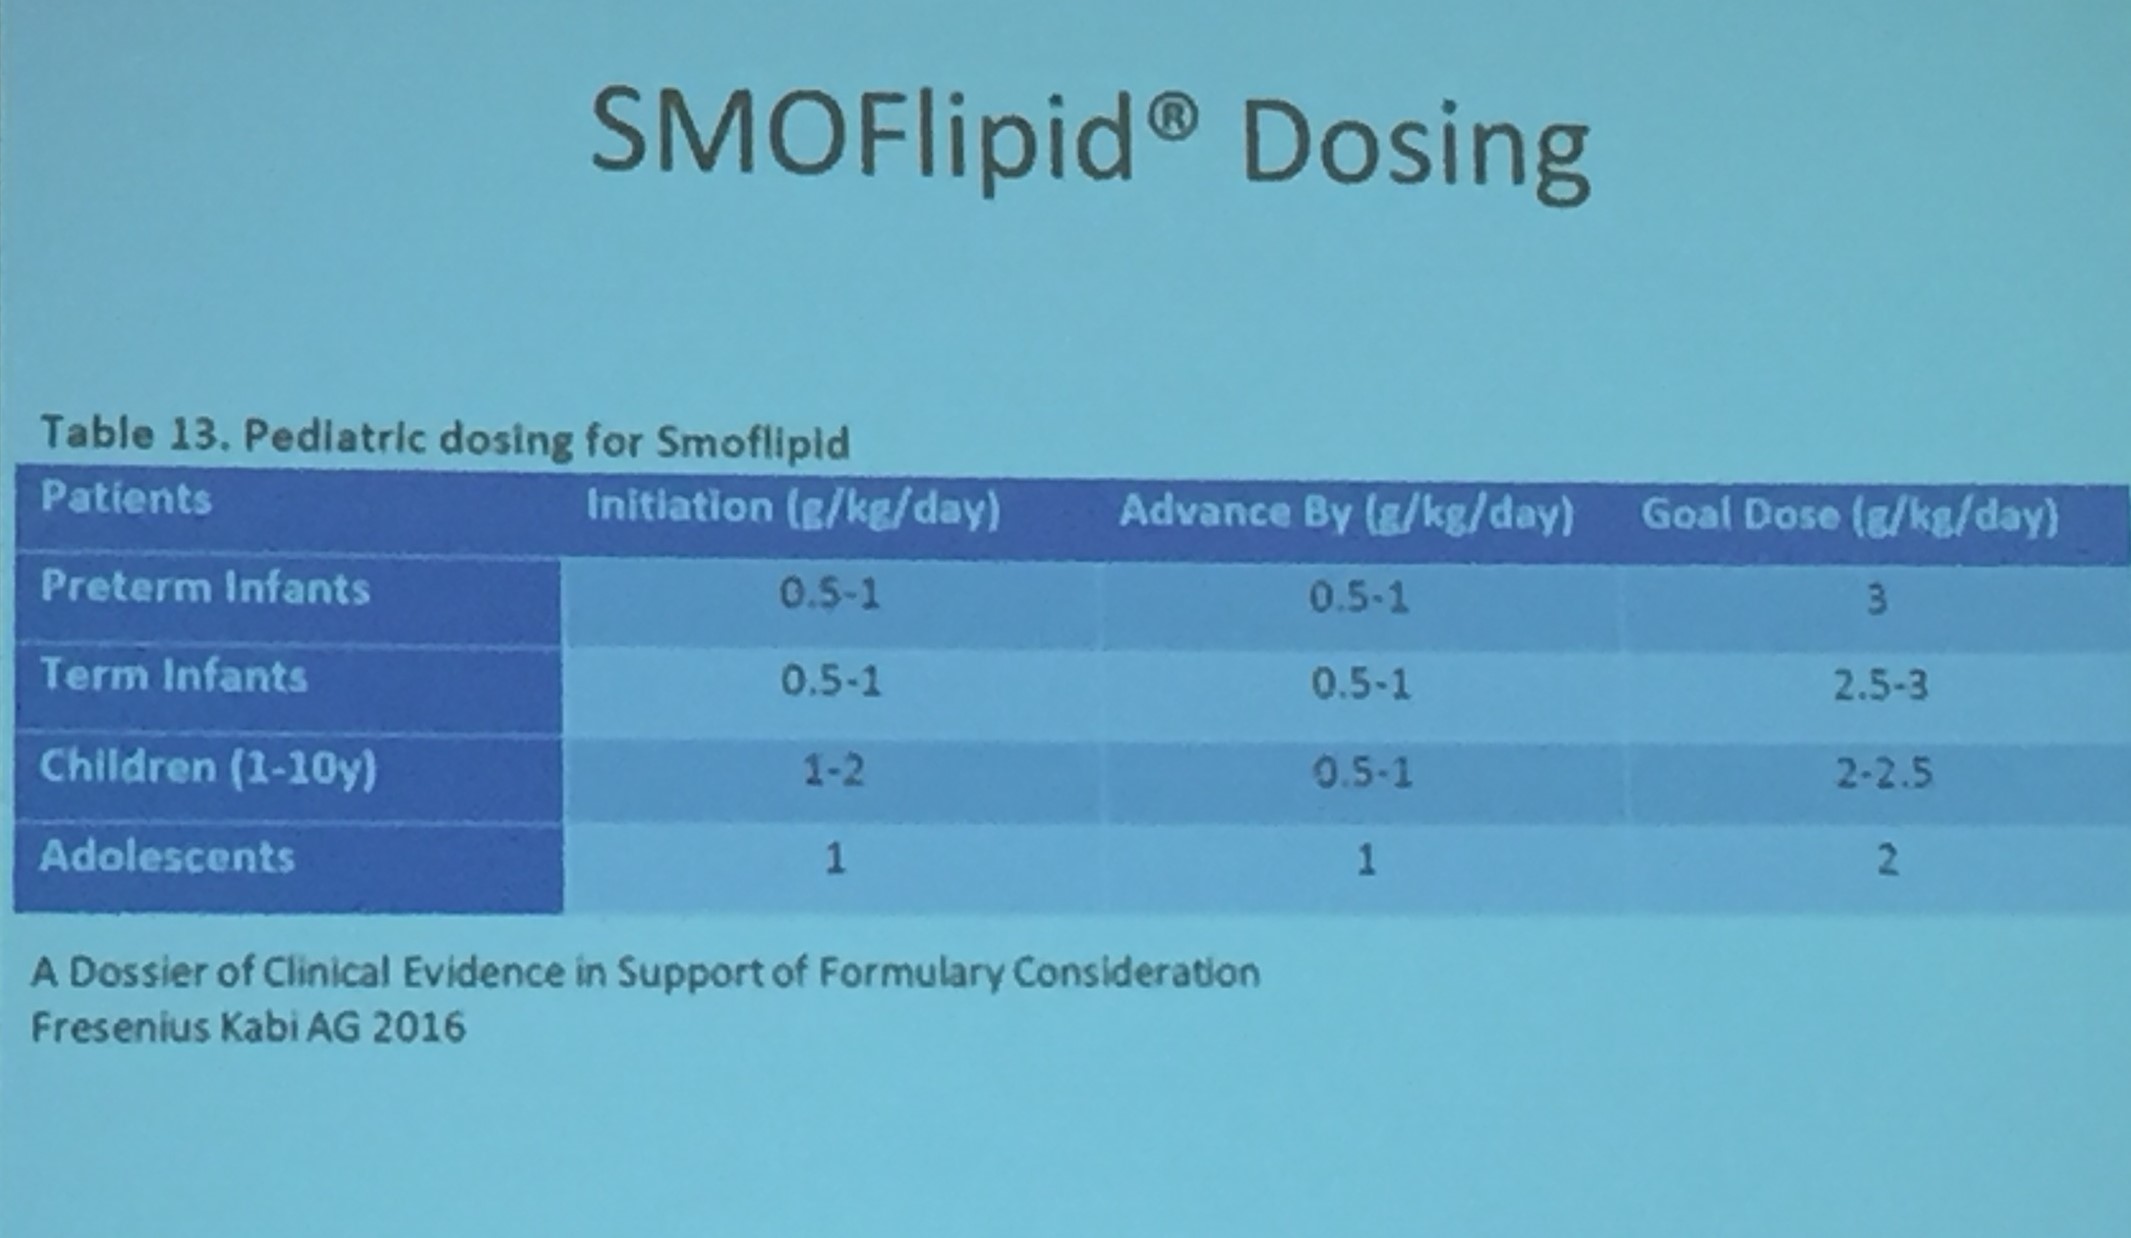
  • SMOF dosing (listed below) with goal of 3 g/kg in preterm infants.
  • Resolution of cholestasis does not mean reversal of cirrhosis.  Thus, lipid emulsion intervention at earlier stage may be important.

Bram Raphael  Getting In Line: Towards a Clinical Practice Guideline For CVC Salvage

Key points:

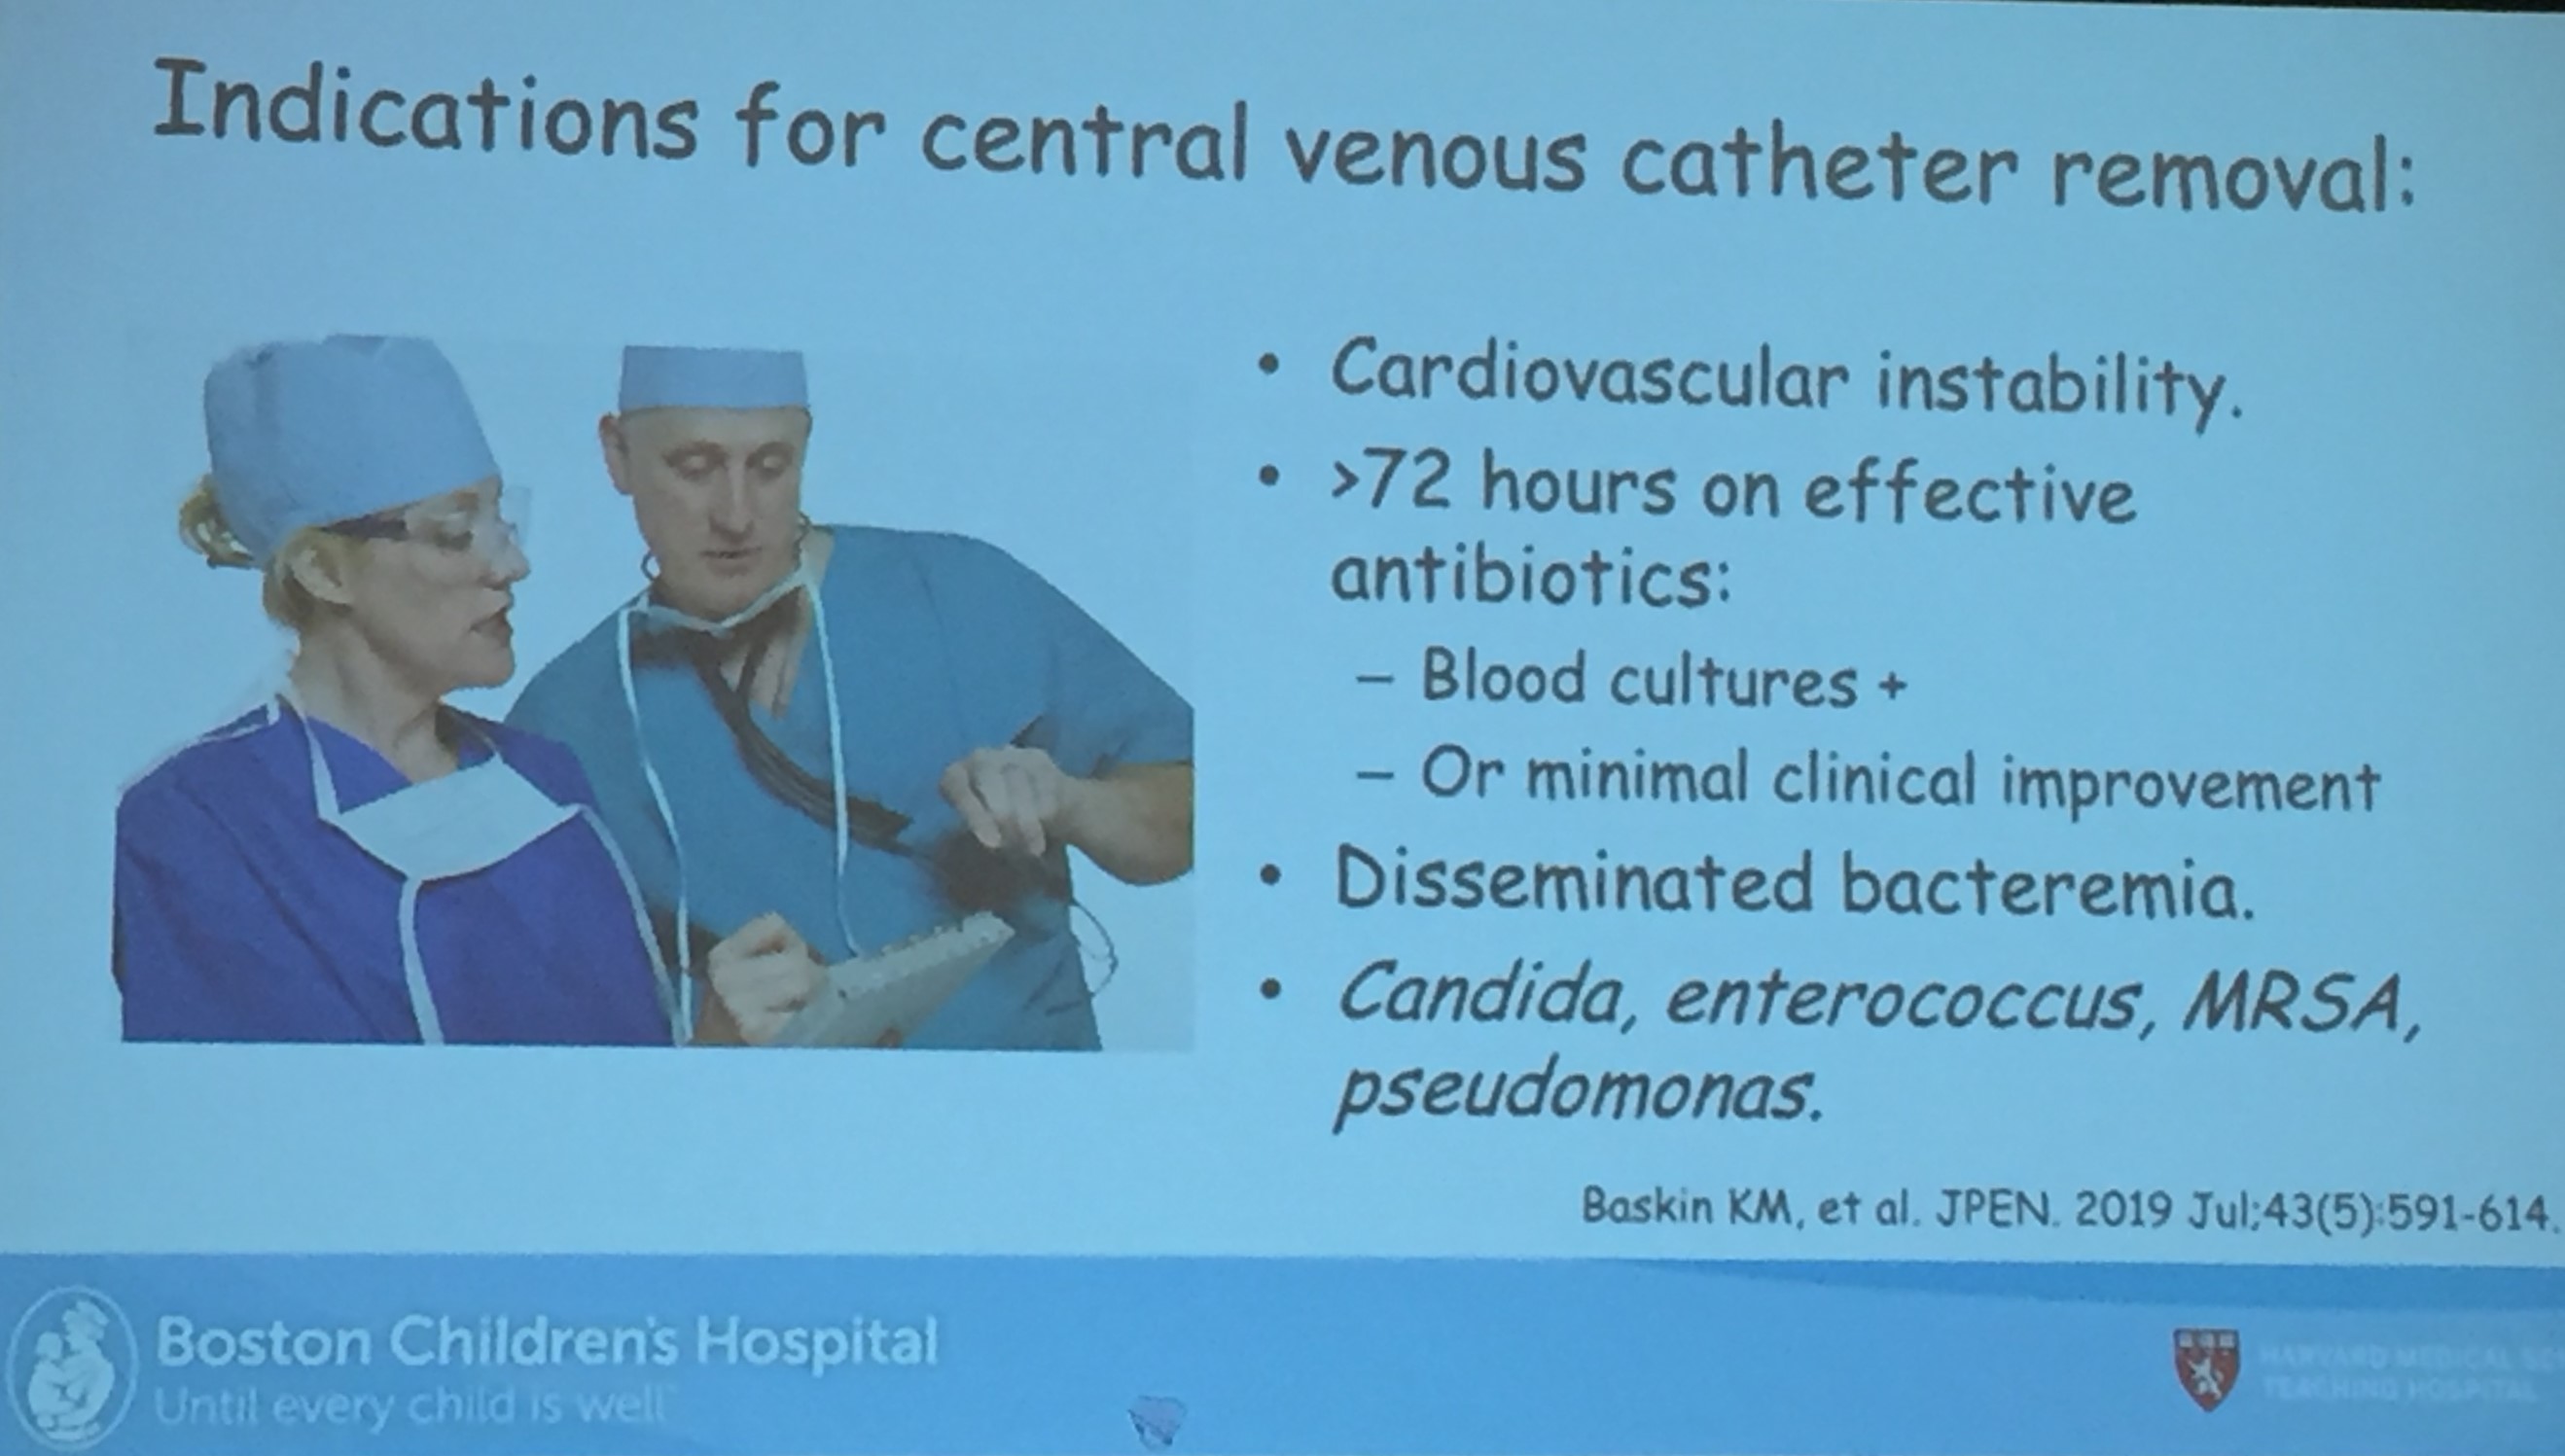
  • Several infections are very difficult to clear, especially yeast, enterococcus, and pseudomonas
  • Salvaging central lines may obviate the need for multi-visceral transplant which carries a 5-year ~50% mortality rate
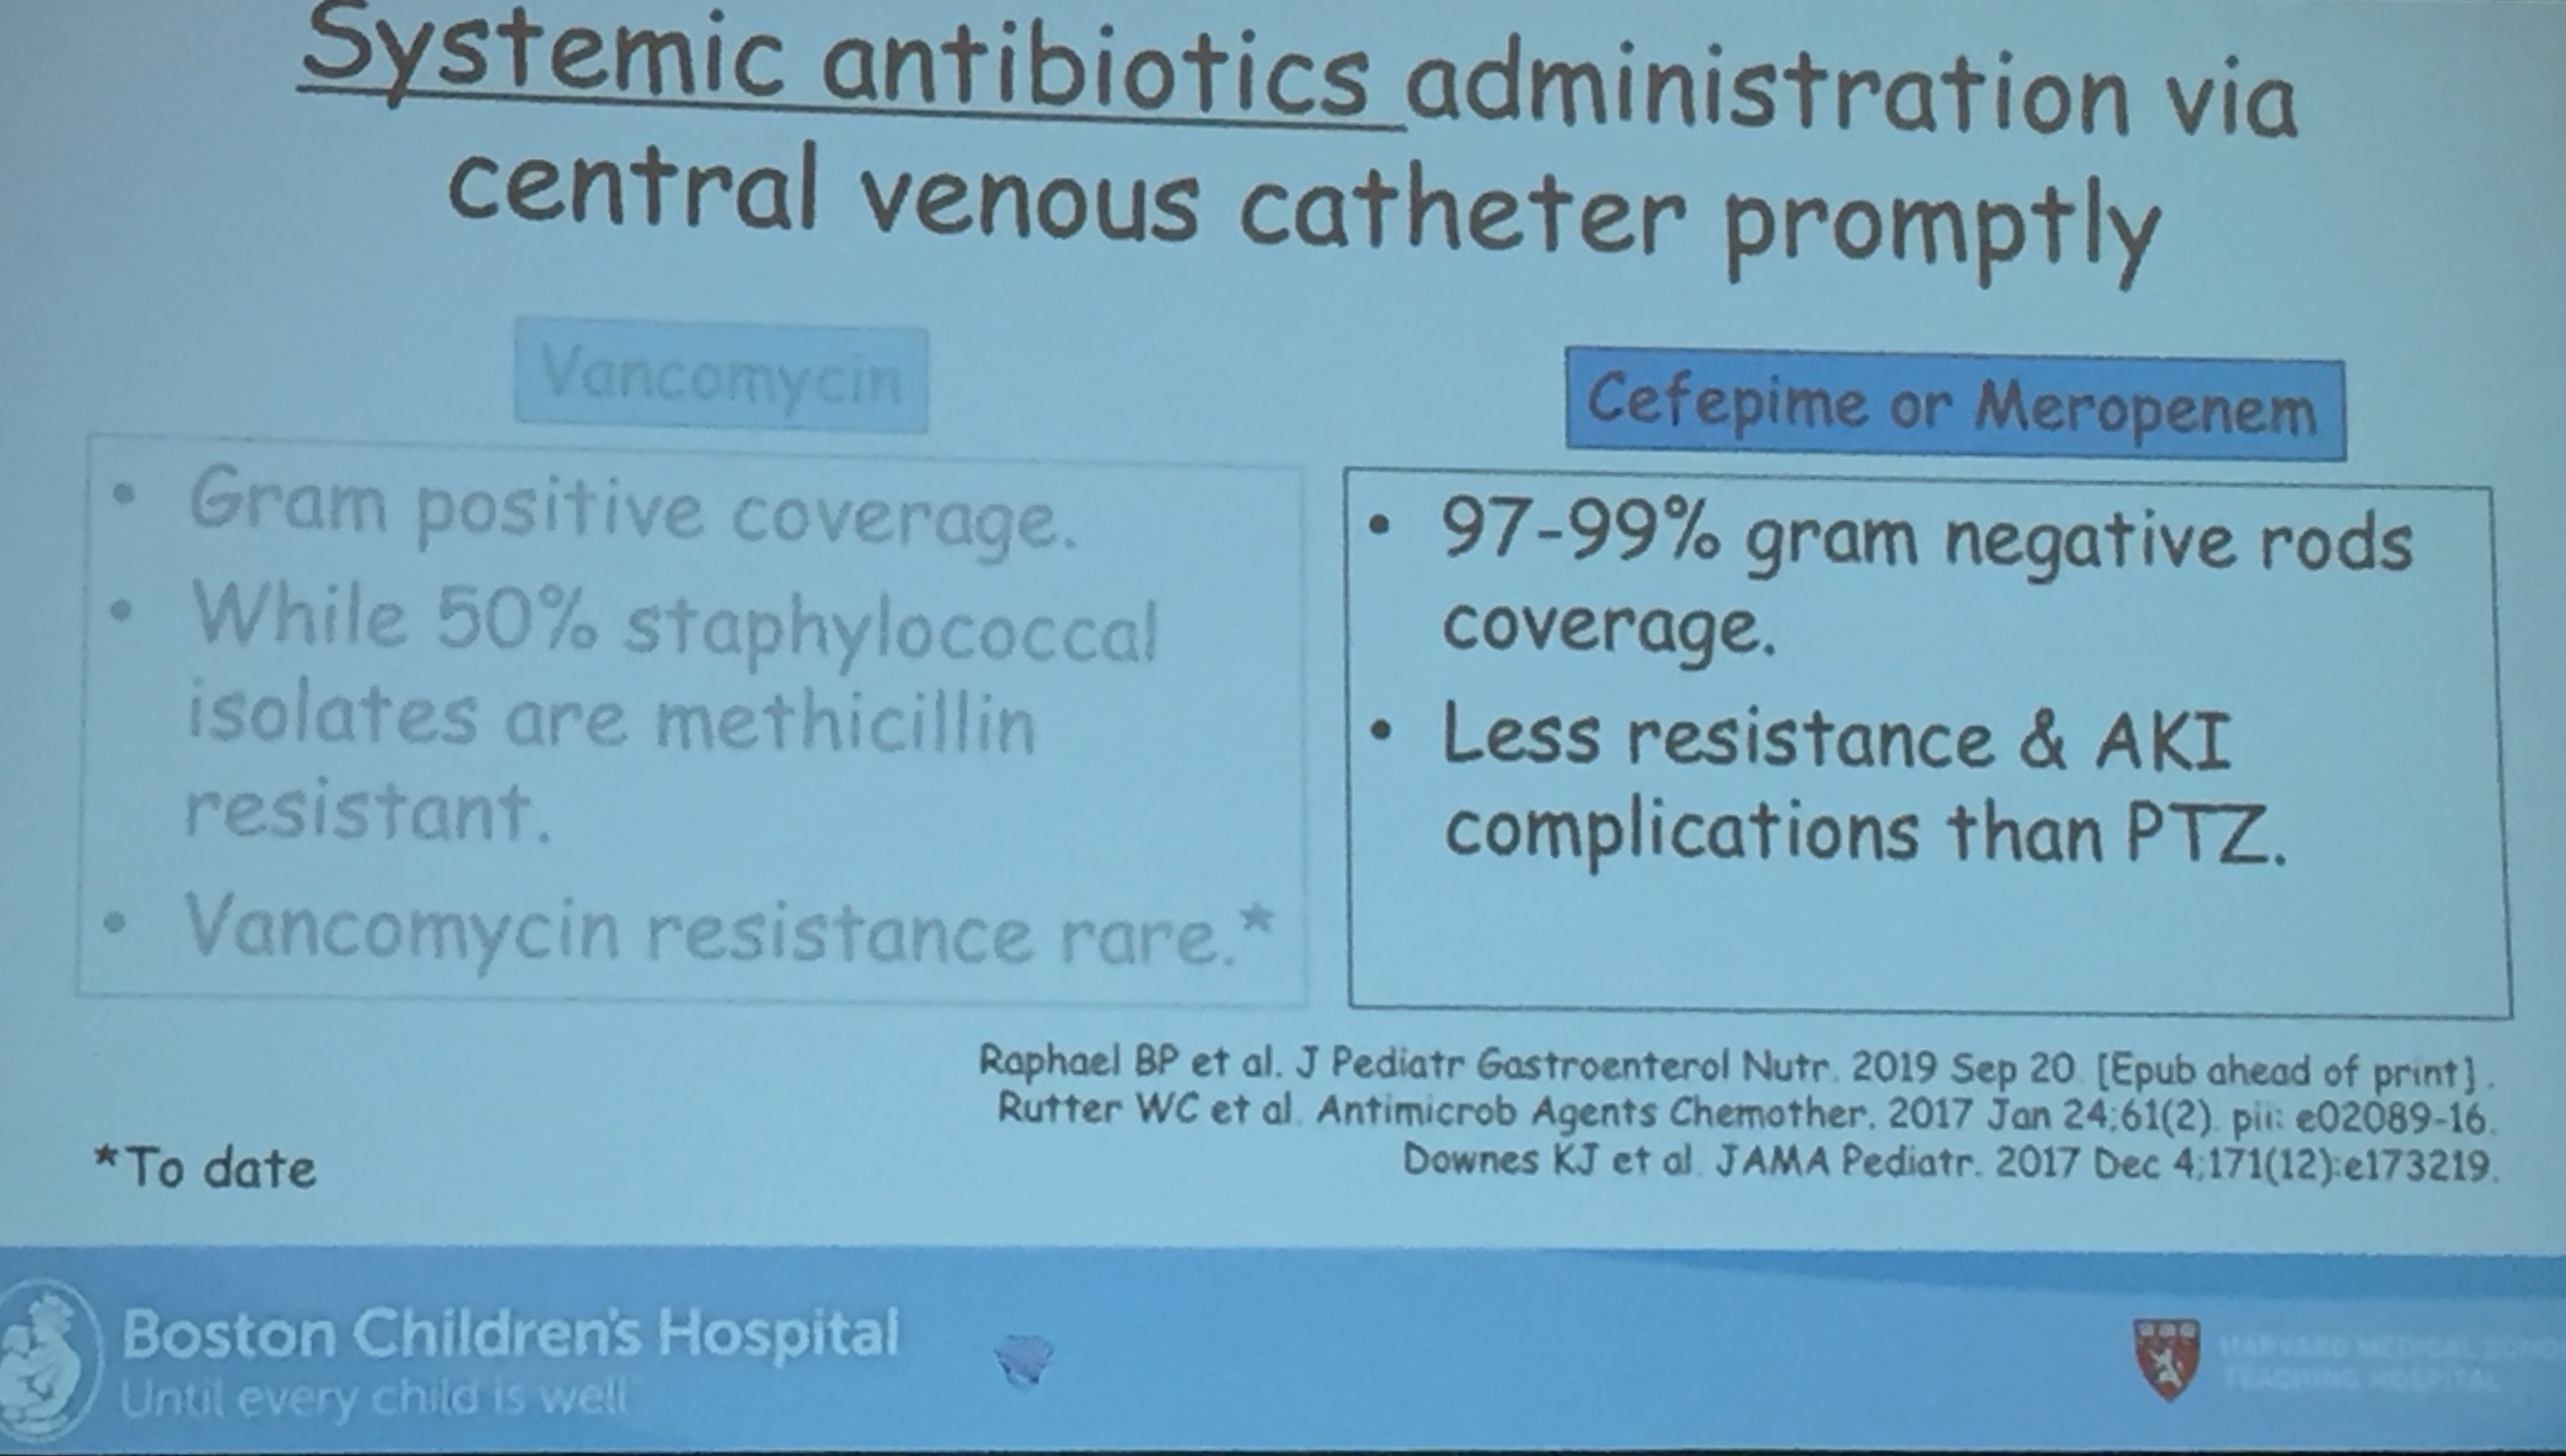
  • Cefepime provides good gram-negative coverage; consider meropenem in those with septic shock

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Food Safety Lecture–It is Still A Jungle Out There

Yesterday, I posted a blog that tried to summarize some of William Balistreri’s talk on Global Health.  He gave a 2nd Excellent Lecture on Food Safety at the Georgia AAP Nutrition Symposium.  One audience member suggested that this lecture was well-paired with the previous lecture as the awareness of food-borne illnesses might deter gluttony.

This lecture was packed with information regarding food safety; he highlighted the extensive and frequent food-borne illnesses.

Key points:

  • The problem of food-borne illness was put under a spotlight by Upton Sinclair in The Jungle (1906) which led to reforms in meat packing industry.  However, more work is needed
  • FSMA -Food Safety Modernization Act was signed into law in 2011; it’s aim is to create a proactive rather than reactive approach, Historic opportunity to increase food safety
  • Food-borne illnesses: 1 in 10 persons worldwide will be sick every year & leads to 1/2 million deaths worldwide each year.  125,000 deaths in children
  • Food-borne illnesses: 48 million cases in U.S. each year (CDC estimates) and 3000 deaths (MMWR 64:2, 2015)
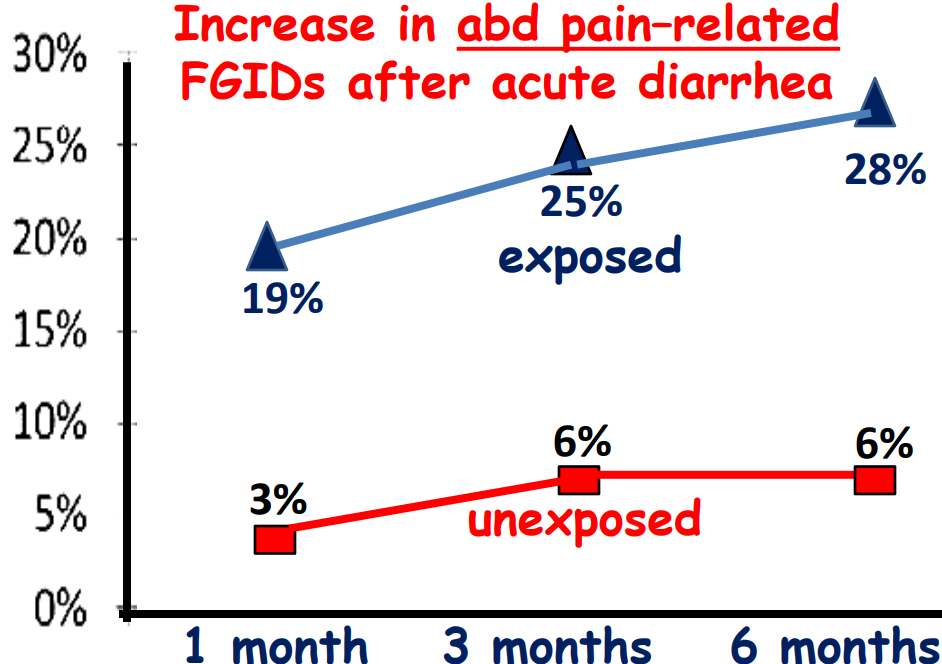
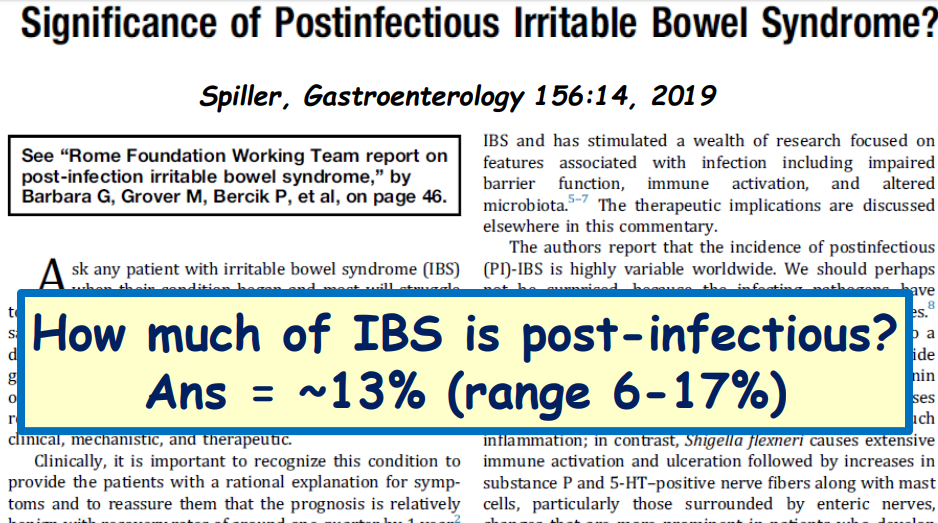
  • Besides significant mortality rates for food-borne illnesses, they also contribute to post-infectious irritable bowel syndrome (~13% of all cases) and these illnesses can be indefinite
  • Social media, including “IwasPoisoned.com” and Yelp, will likely help identify outbreaks more quickly.  Newer molecular technologies during food processing has the potential to improve food safety.

Resources:

  • For those who want to keep up food-borne illnesses, Dr. Balistreri recommended food safety news, which provides daily emails. Link to subscribe: Food Safety News
  • Two books that were recommended: The Poison Squad by Deborah Blum and Outbreak by Timothy Lytton
  • The CDC has plenty of advice and a useful pamphlet regarding the key 4 steps with food preparation: Clean, Separate, Cook, Chill. https://www.cdc.gov/foodsafety/keep-food-safe.html
  • Another resource: FoodSafety.gov

Link to full talk slides PDF: FOOD SAFETY (10-10-19)  I have placed about 20 slides below which summarize much of the information that he conveyed.


“The Paramount Health Challenge for Humans in the 21st Century”

I had the privilege recently of introducing William Balistreri as the keynote speaker for the Georgia AAP Nutrition Symposium.  Dr. Balistreri is a personal hero for me; someone I admire greatly.  Hopefully, if he reads this, he will forgive me for forgetting to mention in my introduction that he also is a Lacrosse coach for one of his grandchildren’s team.

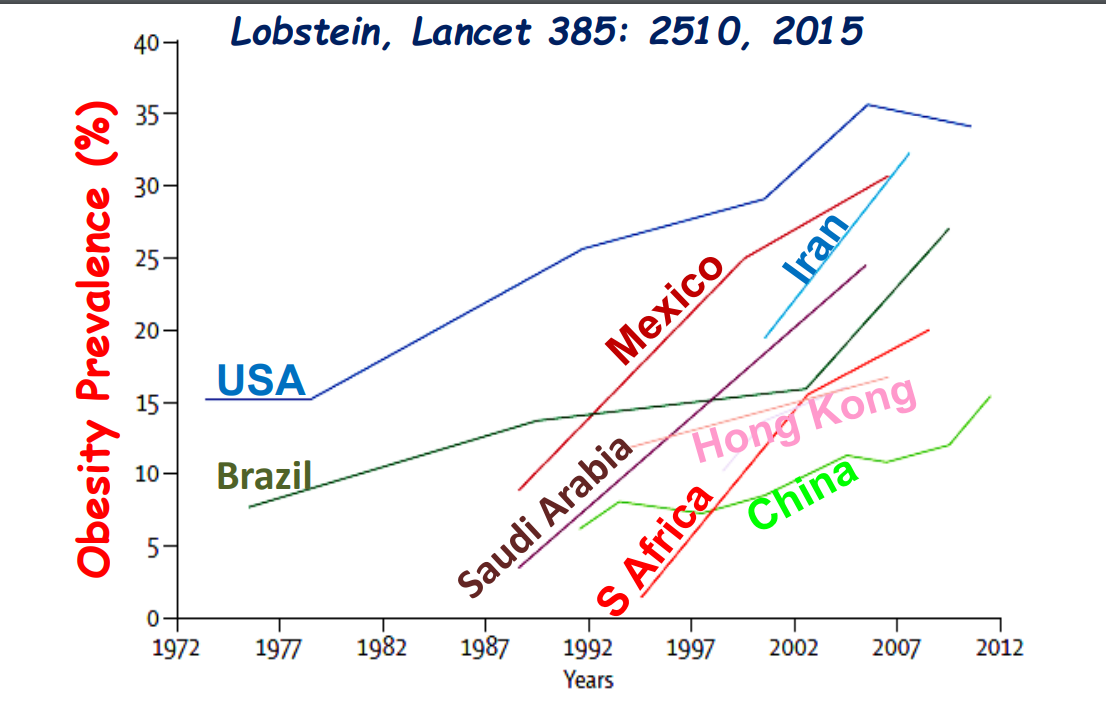
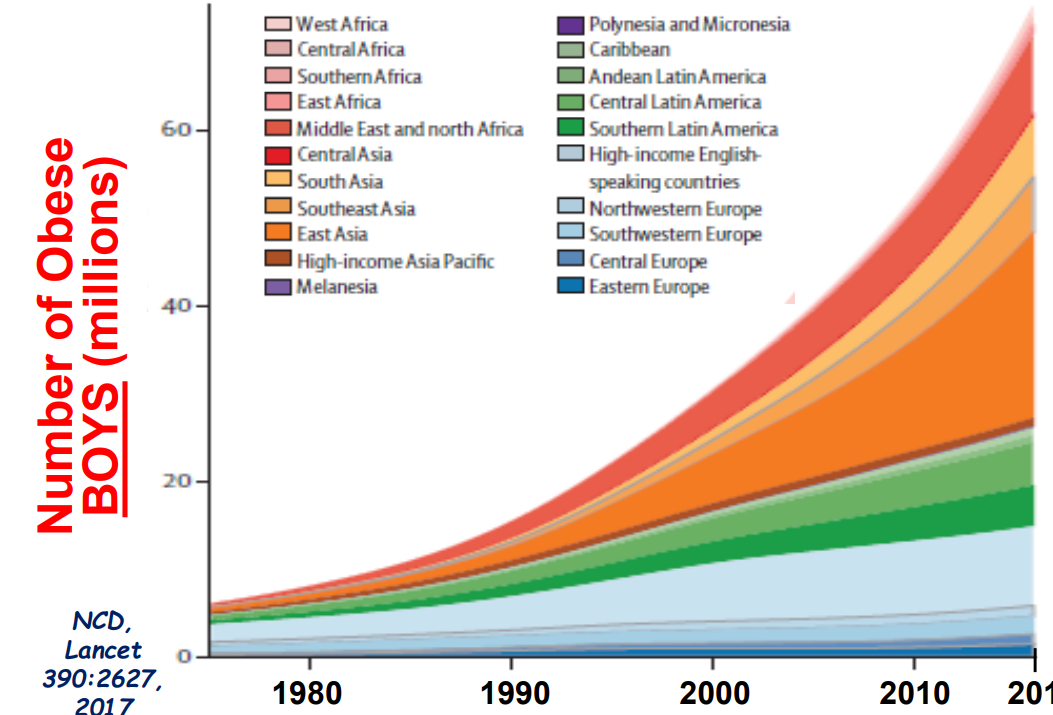
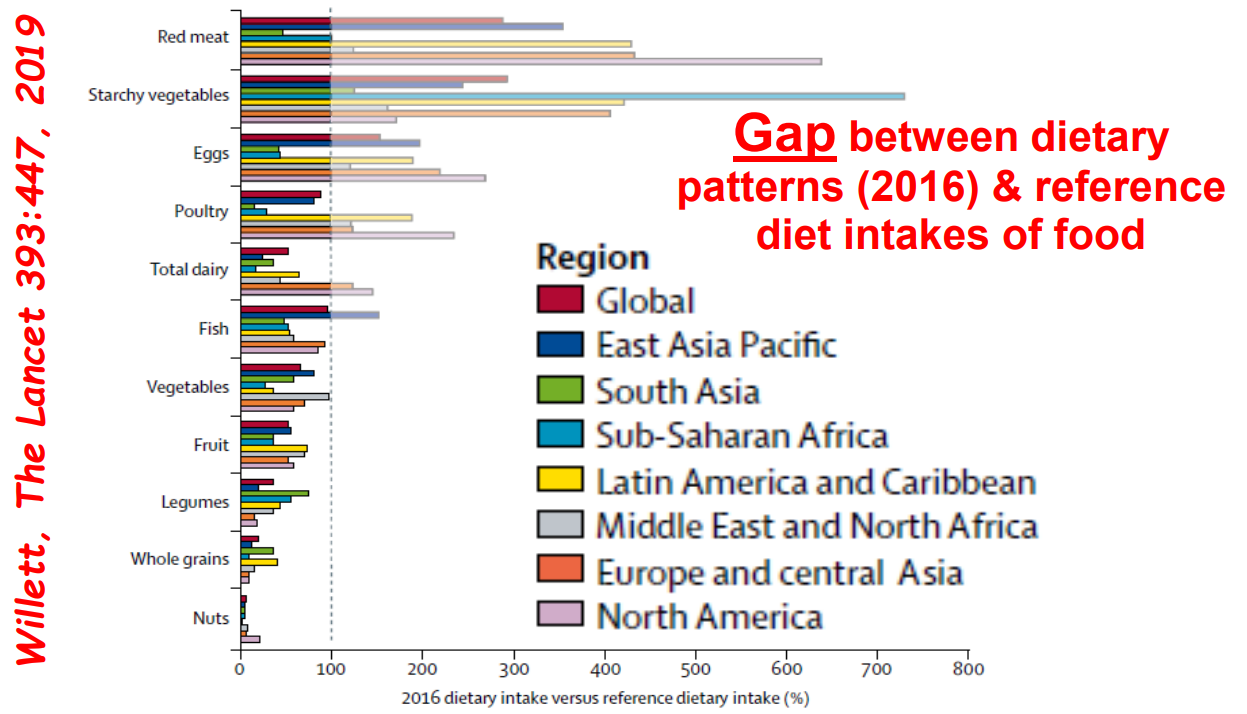
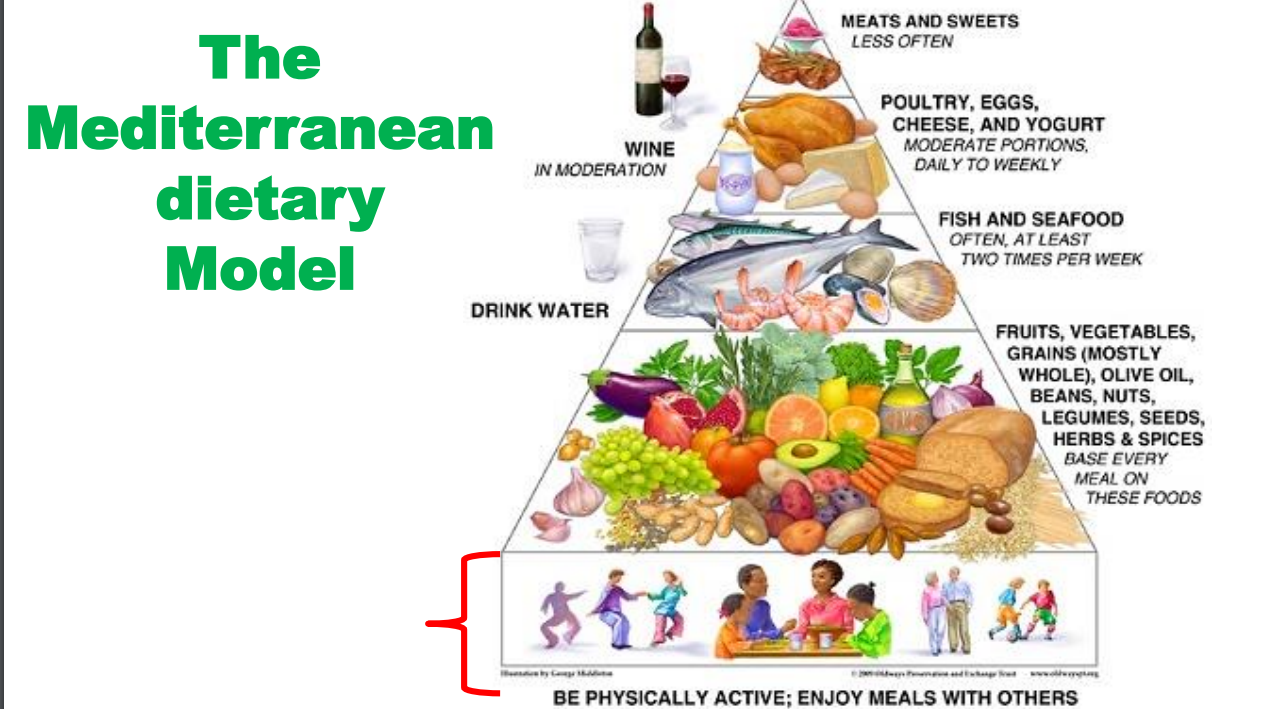
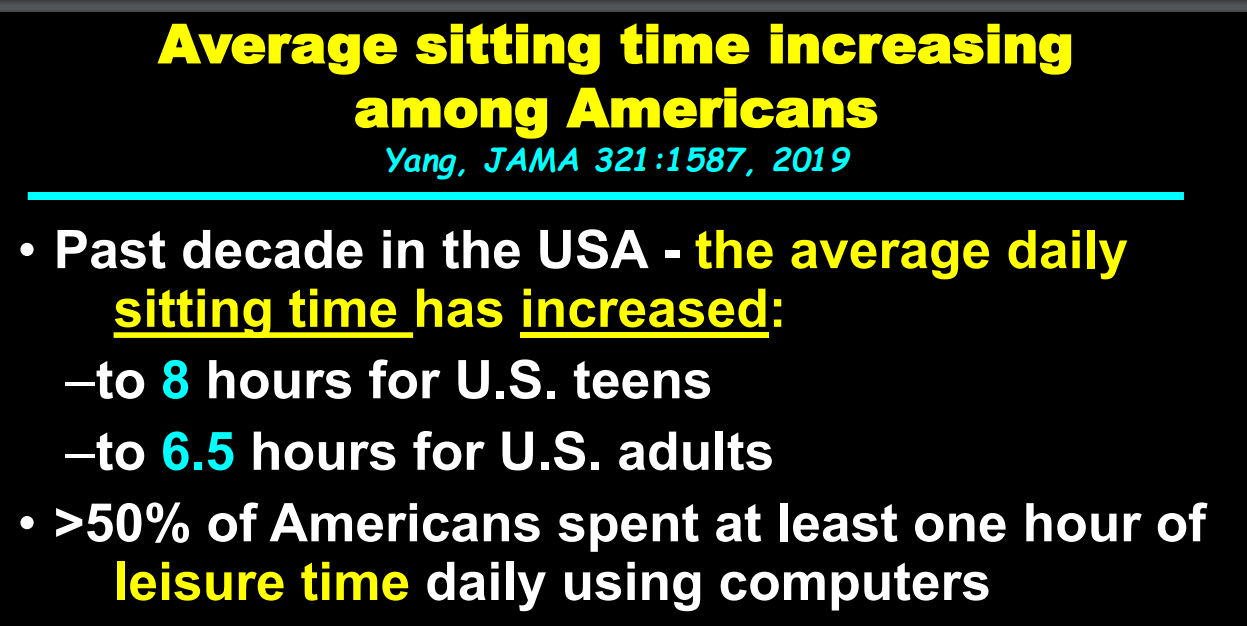
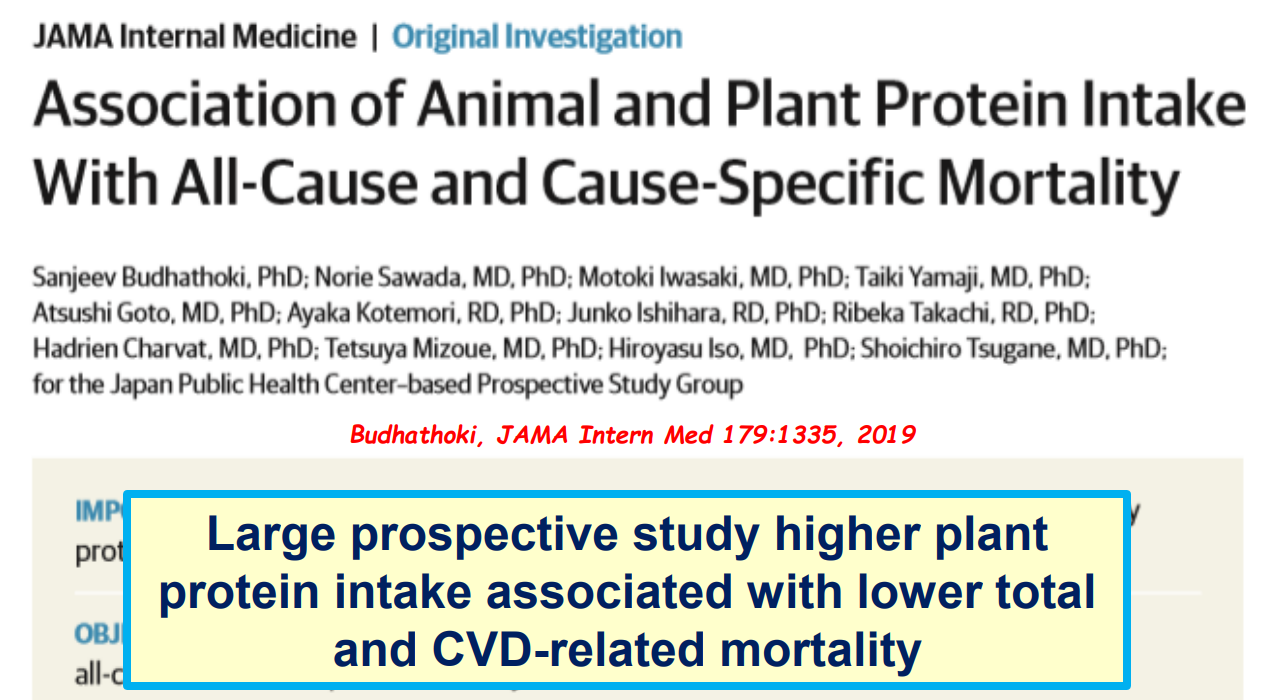
He gave a tour de force presentation on the global challenge of obesity.  In addition, he discussed undernutrition, endobariatrics, gastroenteritis, climate change and even food waste; 40% of U.S. food is thrown away. In Finland, there is a ‘Grocery Store Happy Hour‘ for distribution of reduced cost/free groceries which may help reduce food waste.  In general, I try to condense what I read or hear –that was pretty much impossible with this lecture which was packed with information based on the latest research as well as information dating back to the 5th Century BC/Plato.  What follows are some of my favorite slides.

Here is a link to the full talk: WHAT’S HOT in Pediatric Gastroenterology? Global Nutrition Lecture (10-10-19)

Two Articles received the most attention:

  1. LANCET Commission on Global Syndemic (Obesity, Undernuturition, and Climate Change)
  2. EAT- LANCET Commission on Healthy Diets

What Can Be Done?

Additional References:

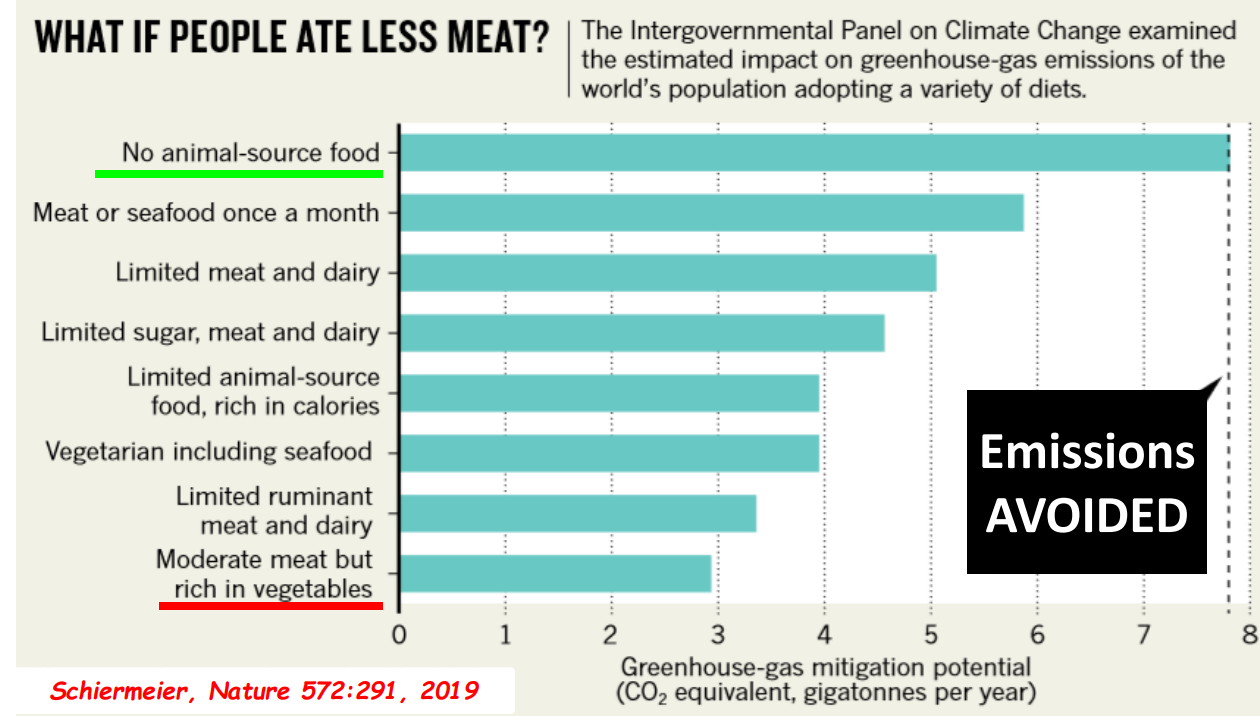
A recent book (not discussed in lecture) provides related information. “We Are The Weather” by Jonathan Foer, was reviewed this past weekend in the NY Times: Meat is Murder: “[This book] has a point, and that is to persuade us to eat fewer animal products. Foer makes the case that, for Americans and citizens of other voracious meat-eating countries, this is the most important individual change we can make to reduce our carbon footprints.” However, the reviewer, Mark Bittman, states that “we’re not good at making positive decisions about our future. And we’re really not good at denying ourselves cheap pleasures like cheeseburgers.”  He advocates for stronger laws, government leadership, and pricing the products to account for their true costs in terms of their contributions to climate change, public health, and environmental degradation.

Related blog posts:


NASPGHAN/ESPGHAN Position Paper: Nutrition Support for Children with Chronic Liver Disease

M Mouzaki et al. JPGN 2019; 69: 498-511. Full text link: Nutrition Support of Children with Chronic Liver Diseases: A Joint Position Paper of the North American Society for Pediatric Gastroenterology, Hepatology, and Nutrition and the European Society for Pediatric Gastroenterology, Hepatology, and Nutrition 

Figure 2 (above) outlines an approach to assuring adequate intake of nutrients

Table 2 (above) provides an approach to laboratory monitoring. The authors recommend measuring every 3-6 months for most of the vitamins and micronutrients listed in this table

Table 3 (above) provides recommendations for specific elements of nutritional support.

Figure 1 (above) describes pathophysiology of malnutrition.

My take: This position paper provides useful advice for approaching nutritional support in children with chronic liver disease. Defining the specific patients in which these guidelines may be applicable requires individual assessment.  Thus, the authors note that the guidelines “should not be construed as establishing a legal standard of care or as encouraging, advocating, requiring, or discouraging any particular treatment.”

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Nutrition Group: OK to Continue Red Meat Consumption

Here’s the full text study: Unprocessed Red Meat and Processed Meat Consumption: Dietary Guideline Recommendations From the Nutritional Recommendations (NutriRECS) Consortium (Published: Ann Intern Med. 2019. DOI: 10.7326/M19-1621)

In the same issue, there are several studies and an associated commentary: Meat Consumption and Health: Food for Thought by Aaron Carroll and Tiffany Doherty.

  • The recommendations from this study relate to the health effects of meat consumption.  Considerations of environmental impact or animal welfare did not bear on the recommendations.
  • “We developed the Nutritional Recommendations (NutriRECS) international consortium to produce rigorous evidence-based nutritional recommendations adhering to trustworthiness standards…”
  • “We suggest that individuals continue their current consumption of both unprocessed red meat and processed meat (both weak recommendations, low-certainty evidence).”
  • “Despite our findings from our assessment of intake studies versus dietary pattern studies suggesting that unprocessed red meat and processed meat are unlikely to be causal factors for adverse health outcomes (131416), this does not preclude the possibility that meat has a very small causal effect.”
  • “Other dietary guidelines and position statements suggest limiting consumption of red and processed meat because of the reported association with cancer (1244–46).”
  • “In terms of how to interpret our weak recommendation, it indicates that the panel believed that for the majority of individuals, the desirable effects (a potential lowered risk for cancer and cardiometabolic outcomes) associated with reducing meat consumption probably do not outweigh the undesirable effects (impact on quality of life, burden of modifying cultural and personal meal preparation and eating habits). The weak recommendation reflects the panel’s awareness that values and preferences differ widely, and that as a result, a minority of fully informed individuals will choose to reduce meat consumption.”**

A useful commentary from the NY Times: Eat less Red Meat, Scientists Said. Now Some Believe That Was Bad Advice.

An excerpt:

{According to the new report] If there are health benefits from eating less beef and pork, they are small, the researchers concluded. Indeed, the advantages are so faint that they can be discerned only when looking at large populations, the scientists said, and are not sufficient to tell individuals to change their meat-eating habits

Already they have been met with fierce criticism by public health researchers. The American Heart Association, the American Cancer Society, the Harvard T.H. Chan School of Public Health and other groups have savaged the findings…

Dr. Hu, of Harvard, in a commentary published online with his colleagues. Studies of red meat as a health hazard may have been problematic, he said, but the consistency of the conclusions over years gives them credibility…

Questions of personal health do not even begin to address the environmental degradation caused worldwide by intensive meat production. Meat and dairy are big contributors to climate change, with livestock production accounting for about 14.5 percent of the greenhouse gases that humans emit worldwide each year.

My take:  Though the title says it is ‘OK to Continue Red Meat Consumption’ –overall, my suspicion is that limiting red meat is probably good for one’s health, though the effect is probably small.

**After publication of these guidelines, it was subsequently revealed that lead author had not disclosed previous research ties to meat and food industry.  See Here: Scientist Who Discredited Meat Guidelines…

Related Blog Posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.


Dietary Therapy for Inflammatory Bowel Disease –Useful Update

Recently, Lindsey Albenberg, DO (from CHOP) provided an excellent update on dietary therapy for Crohn’s disease.  She was an invited speaker from CHOA as part of a nutritional support professional development series.  Thanks to Kipp Ellsworth for coordinating this.

Full Slide Set: Nutritional therapies for IBD

Key points from lecture:

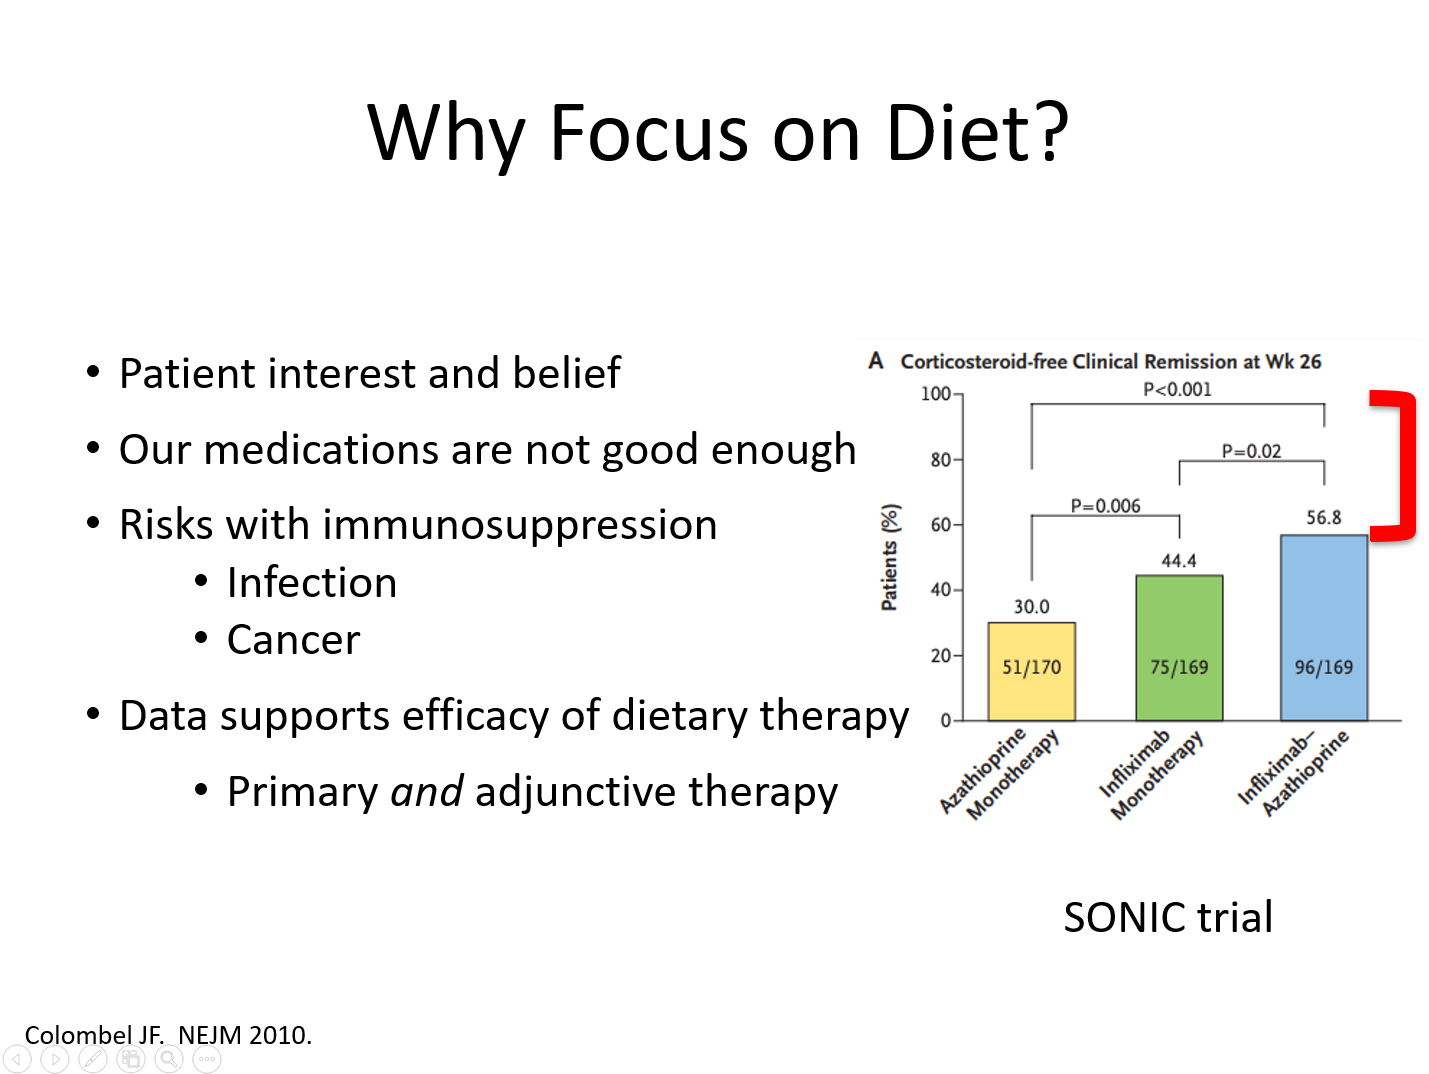
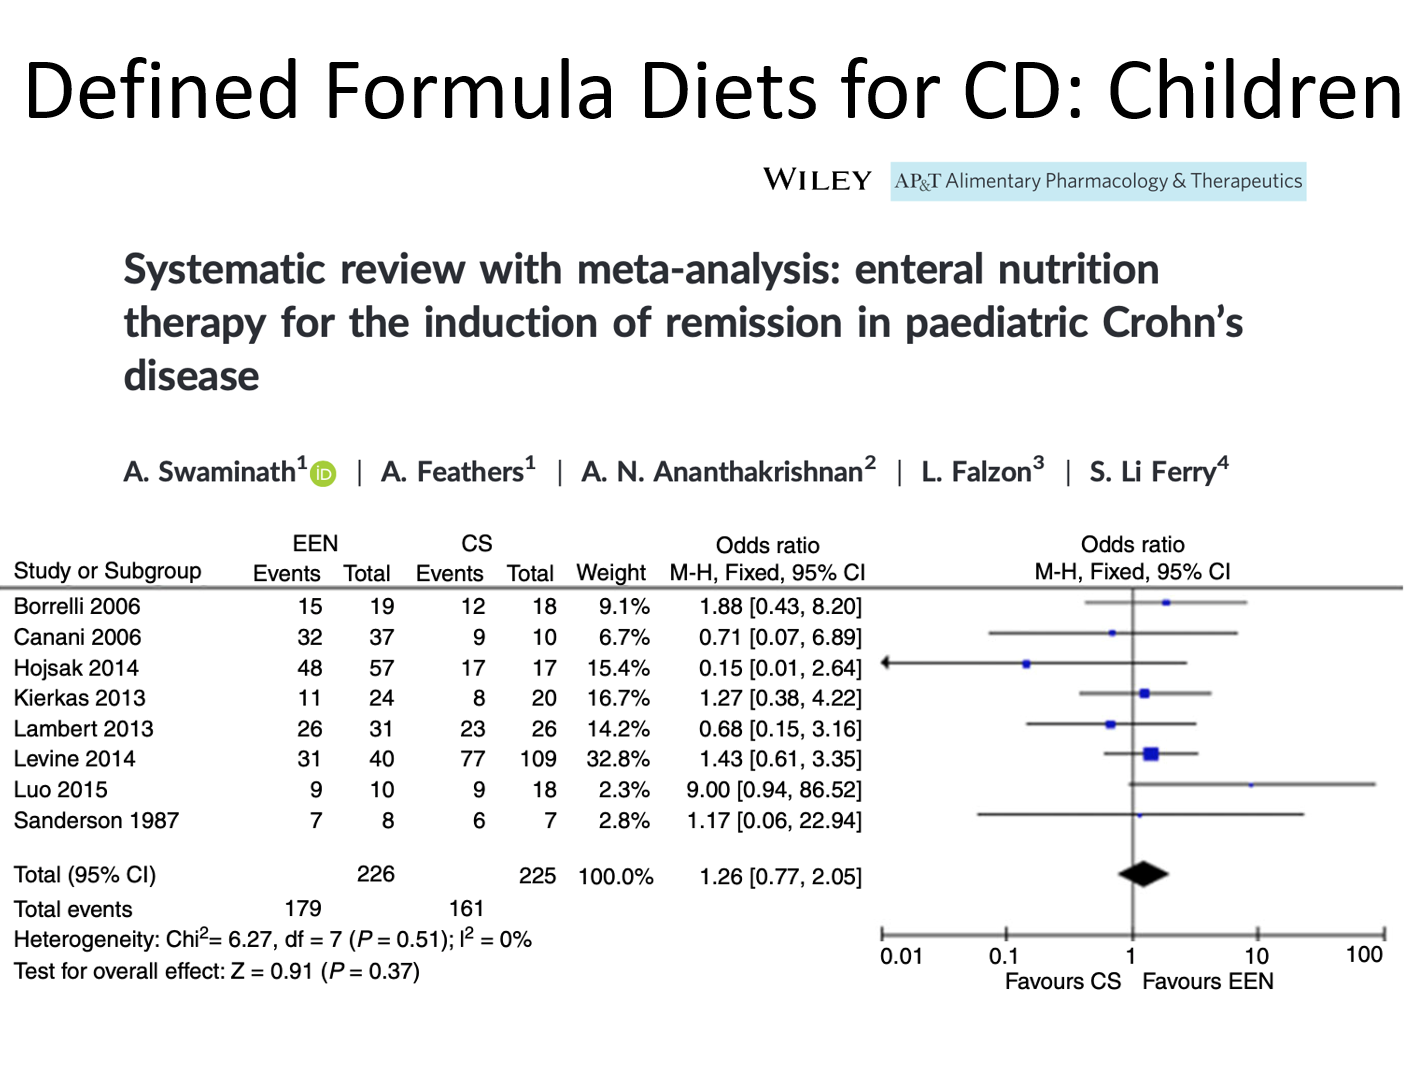
  • At CHOP, exclusive enteral nutrition (EEN) is the main dietary approach for Crohn’s disease (CD) advocated due to better proof of its effectiveness
  • In children, EEN is as effective as steroids for clinical improvement and better in terms of mucosal healing
  • EEN therapy can be given regardless of CD location
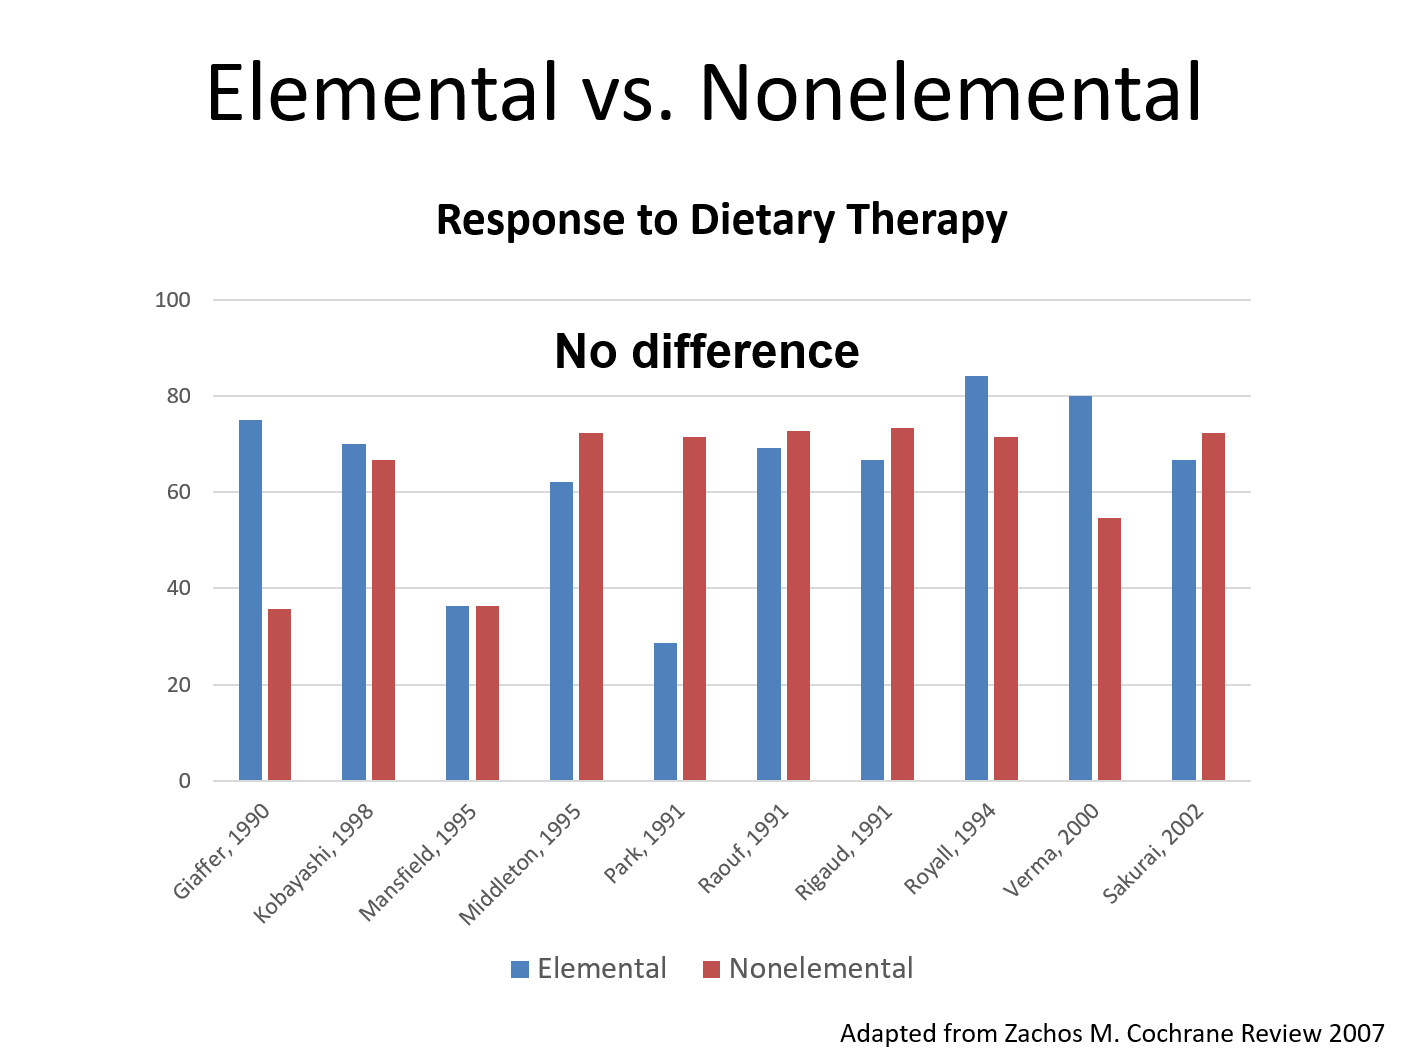
  • For EEN, there is no difference in response between elemental and nonelemental formulas
  • For EEN to be effective, at least 80-90% of all calories need to be administered during induction
  • At CHOP, EEN is often administered at time of diagnosis and oral approach is tried first
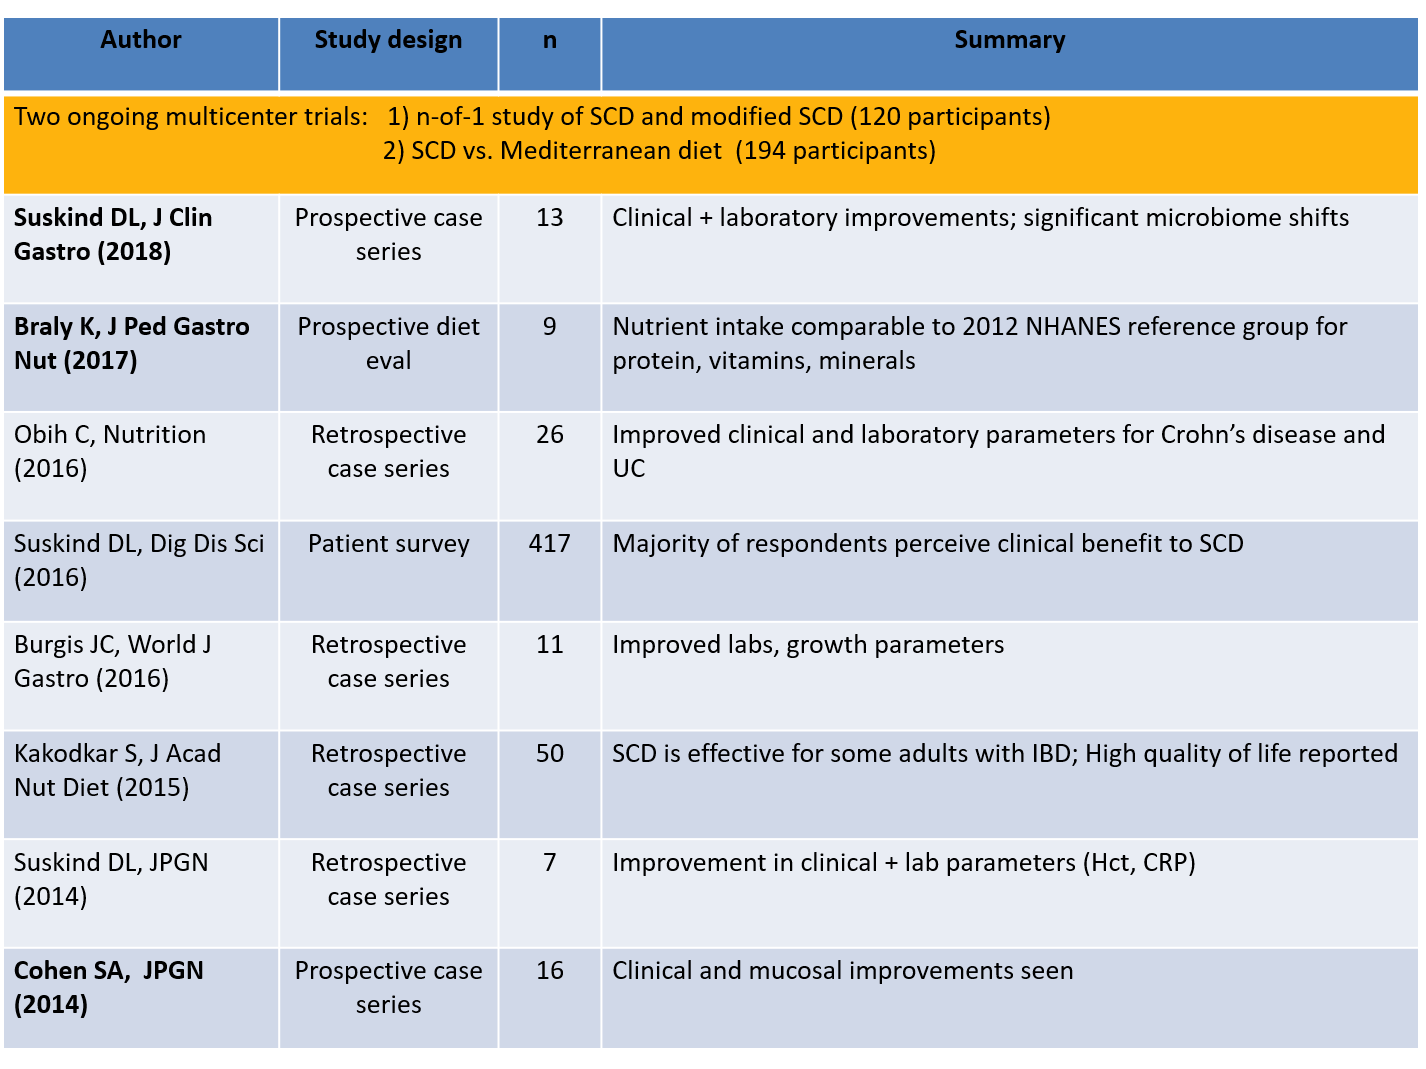
  • Newer dietary approaches are being studied and may be effective.  Diets like the specific carbohydrate diet (SCD) can be considered, particularly in patients with milder disease.


The following slide presents SCD diet studies –mostly small studies except for 2016 survey study.

Related blog posts:


Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition


What Infants and Toddlers Should and Should NOT Be Drinking

NY Times: What Should Young Children Drink? Mostly Milk and Water, Scientists Say

An excerpt:

A panel of scientists issued new nutritional guidelines for children on Wednesday, describing in detail what they should be allowed to drink in the first years of life. The recommendations, among the most comprehensive and restrictive to date, may startle some parents.

Babies should receive only breast milk or formula, the panel said. Water may be added to the diet at 6 months; infants receiving formula may be switched to cow’s milk at 12 months. For the first five years, children should drink mostly milk and water, according to the guidelines.

Children aged 5 and under should not be given any drink with sugar or other sweeteners, including low-calorie or artificially sweetened beverages, chocolate milk or other flavored milk, caffeinated drinks and toddler formulas.

Plant-based beverages, like almond, rice or oat milk, also should be avoided. (Soy milk is the preferred alternative for parents who want an alternative to cow’s milk.)…

Young children should drink less than a cup of 100 percent juice per day — and that none at all is a better choice…Children do not need juice and are better off eating fruit, the panel said. ..

With the exception of soy milk, plant-based milks are poor in protein. Though they are often fortified, scientists do not know whether people are able to absorb these nutrients as efficiently as those naturally present in other foods.
Formulas marketed for toddlers are usually unnecessary, since most toddlers eat solid food

My take: These recommendations provide good advice.