How Much Infliximab Can You Give to Young Children?

A recent case series (A Assa et al. JPGN 2020; 71: 516-520. Therapeutic Drug Monitoring-guided High-dose Infliximab for Infantile-onset Inflammatory Bowel Disease: A Case Series) describes four infants (2 mo-12 mo) with infantile-onset IBD who received high doses of infliximab.

Treatments regimens utilized infliximab dosing of 10-22 mg/kg/dose with initial three doses over 2-4 weeks. Other prior treatments in these patients included antibiotics (eg. vancomycin/gentamicin) and corticosteroids. Sulfasalazine was administered in two of the patients.

Other Key Points:

  • The authors noted that patients gradually transitioned to every 4 week therapy whild seeking to maintain trough concentrations >10 mcg/mL.
  • Infants have several risk factors for inadequate serum infliximab levels. Infliximab clearance is not linearly weight-related and infants are “most susceptible for under-dosing.”
  • Infliximab distribution in infants & children differs from adults with more peripheral compartment distribution, leading to lower trough levels.
  • Severity of disease impacts infliximab levels and can cause a ‘sink’ effect

The authors note that higher doses may increase adverse events, including infections

My take: This study shows that highly-selected patients may need both accelerated and higher doses of infliximab to enable response. It adds to the literature that children, in general, are at high risk of under-dosing with ‘standard’ infliximab dosing.

Related blog posts:

NEJM: Competing Visions for U.S. Health Policy, Evolocumab for Pediatric Familial Hypercholesterolemia, and the Cervical Cancer Vaccine

A recent commentary (M Fiedler. NEJM 2020; 383: 1197-99. Competing Visions for the Future of Health Policy) describes two competing approaches to U.S. healthcare policy.

  • The current administration has supported legislation which would repeal or sharply curtail many of the Affordable Care Act’s (ACA’s) coverage provisions and is “asking the U.S. Supreme Court to strike down the entire ACA.”  Their approach views “existing federal coverage programs, particularly those serving lower-income people, [as] too expansive.”
  • The main alternative approach aims for expanded insurance coverage and deep subsidies to cover low- and moderate-income individuals.
  • Areas of potential agreement include encouraging competition to lower costs as well as making prices more transparent to encourage patients to seek out lower-priced alternatives.

My take: Overall, I favor more expansive health care coverage.


RD Santos et al. NEJM 2020; 383: 1317-1327. Evolocumab in Pediatric Heterozygous Familial Hypercholesterolemia

Methods: In this 24-week, randomized, double-blind, placebo-controlled trial with pediatric patients (n=157) with heterozygous familial hypercholesterolemia, patients 10 to 17 years of age were treated with evolocumab.  All had been receiving lipid-lowering treatment before screening and had LDL cholesterol level of 130 mg/dL.

Key finding: At week 24, the mean percent change from baseline in LDL cholesterol level was −44.5% in the evolocumab group and −6.2% in the placebo group.

My take: Long-term data are needed.  However, in high risk patients who have not responded to other intensive treatment, evolocumab may be worthwhile.


J Lei et al. NEJM 2020; 383: 1340-1348. HPV Vaccination and the Risk of Invasive Cervical Cancer

Methods: We used nationwide Swedish demographic and health registers to follow an open population of 1,672,983 girls and women who were 10 to 30 years of age from 2006 through 2017.

Key findings:

  • After adjustment for all covariates, the incidence rate ratio was 0.12 (95% CI, 0.00 to 0.34) among women who had been vaccinated before the age of 17 years and 0.47 (95% CI, 0.27 to 0.75) among women who had been vaccinated at the age of 17 to 30 years.

My take: HPV vaccine (aka ‘Cervical Cancer Vaccine’) may lower the risk of cancer by 88% in those vaccinated before the age of 17 years.

From The Onion

Should We Be Worried About Phthalates?

Short answer -you should always be worried about words that are so difficult to spell.

Two years ago, this blog highlighted recommendations from the AAP regarding food additives (Food Additives and Child Health).

More information of phthalates is available from the Cincinnati Children’s website: Phthalates and Your Health. The backdrop to this article is in relation to a recently published study Pubertal Growth, IGF-1, and Windows of Susceptibility: Puberty and Future Breast Cancer Risk (F Biro et al. Journal of Adolescent Health 2020).

Key points from Cincinnati Children’s website:

  • Phthalates have been used for many years to make plastics softer and more flexible. These plastics are so common that more than 95 percent of all people have detectible levels of phthalates in their urine. They can be found in everything from perfumes and shampoos to food packaging, detergents, vinyl flooring and shower-curtains.
  • These chemicals act like hormones, which in turn can disrupt the function of natural hormones, which can increase diabetes risk and interfere with male genital development.
  • These chemicals also are considered “obesogens,” which means they contribute to the risk of obesity. For these reasons, several types of phthalates have been banned from use in baby toys and teething rings since 2009, but they can still be found in many consumer products.
  • To avoid exposures, some tips include the following:
    • Minimize plastics used for food storage and avoid heating food in plastic. Use glass, ceramic and stainless steel containers when possible.
    • Minimize use of other plastic products with the recycling code numbers 3 and 7. Those coded 1, 2 or 5 are phthalate-free.
  • Increase consumption of fruits and vegetables, foods more frequently that are known to contain “phytoestrogens”.
  • The National Institute of Environmental Sciences offers this document: “Phthalates: the everywhere chemical.”

My take: Environmental research is quite difficult.  Yet, we know that changes in our environmental exposures are directly related to many adverse health outcomes since changes in disease frequencies related to genetics is a much slower process.

Outcomes Associated with Delayed Diagnosis in Pediatric Crohn’s Disease

A Ricciuto et al. Journal of Crohn’s and Colitis; 2020. jjaa197, https://doi.org/10.1093/ecco-jcc/jjaa197 Link: Diagnostic Delay Is Associated with Complicated Disease and Growth Impairment in Paediatric Crohn’s Disease

Methods: “We conducted a national, prospective multi-centre IBD inception cohort study, including 1399 children. Diagnostic delay was defined as time from symptom onset to diagnosis >75 th percentile.”

Key findings:

  • In CD, diagnostic delay was associated with a 2.5-times higher rate of strictures/internal fistulae (HR 2.53, 95% CI 1.41-4.56)
  • Every additional month of diagnostic delay was associated with a decrease in height-for-age z-score of 0.13 standard deviations
  • Diagnostic delay was more common in CD, particularly small bowel CD

My take: Delays in diagnosis in this study were associated with stricturing/internal fistulising complications and growth impairment in paediatric CD.  It is likely that inadequate treatment would increase the risk of these problems as well.

Related blog posts:

IBD Briefs -October 2020

EV Loftus et al.  AP&T  2020; 52: 1343-1365. Full text: Long‐term safety of vedolizumab for inflammatory bowel disease

GEMINI long‐term safety (LTS) study results –initiated 2009:

  • Enrolled patients (UC, n = 894; CD, n = 1349) received vedolizumab 300 mg IV every 4 weeks. Total of 7999 patient years of vedolizumab exposure.
  • Vedolizumab discontinuation due to AEs occurred in 15% (UC) and 17% (CD) of patients.
  • There were no new trends for infections, malignancies, infusion‐related reactions, or hepatic events, and no cases of progressive multifocal leukoencephalopathy
  • Conclusion from authors: “The safety profile of vedolizumab remains favourable with no unexpected or new safety concerns.”

Related blog posts:

AS Faye et al. Inflamm Bowel Dis 2020; 26: 1368-1376. Fertility Impact of Initial Operation Type for Female Ulcerative Colitis Patients (link includes video abstract)

Surgical options include Ileal pouch–anal anastomosis (IPAA), rectal-sparing colectomy with end ileostomy (RCEI), and ileorectal anastomosis (IRA). Conclusions based on “a patient-level state transition microsimulation in TreeAge Pro:”… “Despite an increased risk of infertility, our model results suggest that IPAA may be the optimal surgical strategy for female UC patients aged 20–30 years who desire children. For patients aged 35 years, RCEI should additionally be considered, as QALYs for RCEI and IPAA were similar.”   In older age group, RCEI’s increase rate of childbirth (28%), decrease time to childbirth (14 months) and 77% reduction in IVF are important factors.

Related blog posts:

R Tariq et al. Inflamm Bowel Dis 2020; 26: 1415-1422. Efficacy of Fecal Microbiota Transplantation for Recurrent C. Difficile Infection in Inflammatory Bowel Disease

In this retrospective study with 145 patients,  the overall cure rate of CDI after FMT was 80.0%, without CDI recurrence at median follow-up of 9.3 (range, 0.1–51) months. The authors concluded that “fecal microbiota transplantation effectively treats recurrent CDI in IBD patients but has no apparent beneficial effect on the IBD course.”

Related blog posts:

Isle of Palms (July 2020)


What’s Missing In Pediatric IBD Care

A recent single-site cross-sectional survey (HK Michel et al. J Pediatr 2020; 224: 94-101. Gaps Exist in the Comprehensive Care of Children with Inflammatory Bowel Diseases) of parents (n=161) and adolescents(n=84)  identified gaps in the comprehensive care of pediatric patients with inflammatory bowel disease (IBD).

Key points:

  • Discussions about family/peer relationships, school/extracurricular activities, and mood were not addressed in 30%-40% of participants.
  • Adolescents frequently reported that no one had talked to them about substance use (40%), sexual health (50%), or body image (60%)
  • 75% of adolescents and 76% of their parents reported that no one had discussed transitioning to an adult provider.

There is likely a wide variability in addressing psychosocial issues among providers and centers.  Limitations for this type of study includes recall bias and selection bias.

The associated editorial (MJ Ladinsky, MB Cohen, pg 20-22) urge us to ‘Mind the Gap.’  This likely means allowing sufficient time and arranging opportunities for teens to speak directly (& alone) with care provider.  Like other aspects of care, establishing a standardized approach is likely to be helpful.

My take: As noted on this blog previously, emotional health issues are likely more important than other aspects of IBD care that attract more consistent attention (eg. vaccination); the message is clear that these needs need to be addressed.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Best Screening For Celiac At All Ages

Another study (MR Khan et al. J Pediatr 2020; 224: 158-61. The Utility of IgA-Based Serologic Markers in Diagnosing Celiac Disease in Children 24 Months of Age or Younger) shows that tissue transglutaminase (TTG) IgA is the best first test, even in children less than 2 years of age.

This was a multicenter retrospective study with 150 children, mean age was 18 months.

Key findings:

  • ~98% of children <2 years of age with celiac disease had an elevated TTG IgA
  • “These findings are consistent with recently published European guidelines, which endorse TTG IgA…as the initial screening test regardless of age.”
  • IgG-based test should be reserved for IgA-deficient children, which was noted in 5.5% of this cohort.
  • Endomysial antibody (EMA) had excellent specificity in this study but was less sensitive; it was negative in 13 of 66 (19.7%) of children with celiac disease (positive in 80%).

My take: TTG IgA is a good first step; based on clinical presentation, further testing (eg. endoscopy) could be warranted in highly-selected cases with negative results.

Related blog posts:

Leading Medical Journals Condemn U.S. Pandemic Response

Multiple prestigious journals have weighed in on the U.S. pandemic response.


From Science Editor-in-Chief
From Nature
Also, from Nature

From The Lancet:

“If logic and justice prevail in the next presidential
administration, universal health coverage, a fairer society,
stronger health institutions, more energetic global
engagement, and a robust research agenda will be the
foundations for America’s renewal. We all have a stake in
America’s success.”

Transanal Irrigation Device -Pediatric Experience

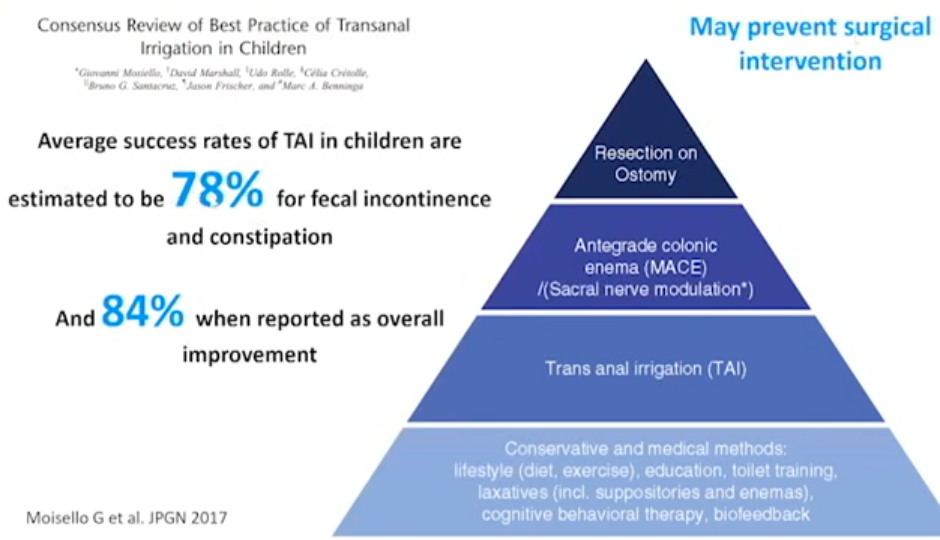
A recent retrospective study (S Patel et al. JPGN 2020; 71: 292-297. Impact of Transanal Irrigation Device in the Management of Children With Fecal Incontinence and Constipation) provides some useful experience in the management of constipation related to bowel dysfunction (n=147), including patients with neurogenic bowel dysfunction (NBD) related to spinal cord defects (NBD, n=85), refractory constipation (RC, n=43), or anorectal malformations (ARMs, n=19).

The authors elaborate on their protocol which includes flushing with warm tap water (on average) 15 mL/kg, generally once a day.  They note that the device is contraindicated in patients <2 years of age and/or within 3 months of anal/colorectal surgery.  The Peristeen device has been FDA approved since 2012.

Key findings:

  • For all patient groups, there was significant improvement in symptoms of fecal incontinence and constipation (P ≤ 0.001).
  • Abdominal pain was improved in the NBD and RC group, but not significantly in the ARM group.

My take: As with other treatment options for these problems, the key to success is adequate upfront training.  The authors note that their training sessions typically last 1-2 hours. A limiting factor with this treatment can be cost.

Useful link: Peristeen Bowel Management

Related blog entries:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition


ANMS Virtual Symposia on Constipation

For those wanting a state-of-the-art review on constipation:

YouTube (1:01) ANMS Virtual Symposia on Constipation

Dr. Jose Garza (one of my partners) gives the first lecture focused on pediatrics -first 18 minutes.

A few points:

  • Miralax is safe (time: 13:45)
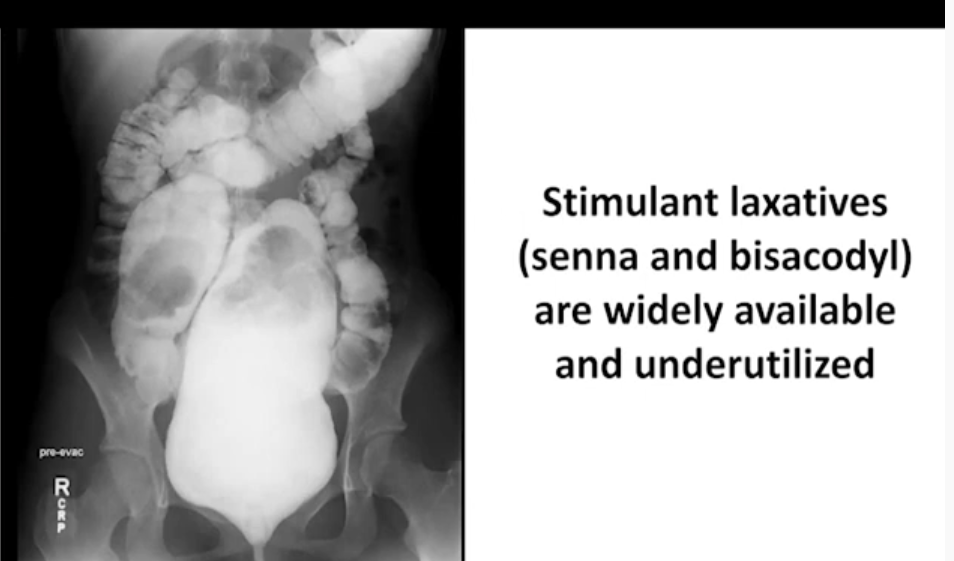
  • Senna and bisacodyl are safe and have not been shown to cause dependence (time 14:55)