What Our Office Is Recommending: School and Pediatric IBD Patients

We are getting a lot of calls from families trying to figure out what they should be doing for their children with inflammatory bowel disease in regards to school attendance.  Here is what our ICN team has developed:

School guidance during Covid pandemic:

With the flood of information in the lay and scientific media, GI Care for Kids wanted to assure that our patients and families who had children with inflammatory bowel disease (IBD), Crohn’s or ulcerative colitis, had some guidance in making important decisions about beginning the 2020-2021 school year.  Currently, research shows that just having IBD, DOES NOT put a person more at risk for acquiring (i.e. catching) coronavirus (COVID-19) infection.  In addition, research suggests that biologics (e.g. Remicade, Humira) DO NOT seem to increase the risk for more severe Covid related illnesses.

However, steroids, thiopurines (e.g. 6-MP; azathioprine, immuran) and prograf DO appear to have a larger effect on increasing risk for more severe coronavirus infection and COVID-19 disease.  Additional research is being carried out with oldest patients (e.g. > 65 years of age) who appear to be at increased risk for infection and COVID-related disease, and, other co-morbid conditions (e.g. obesity, diabetes, cardiovascular disease) being at highest risk for COVID-19 disease as well.

All patients should practice good hand hygiene, wear masks at all times outside of the house, and observe social distancing.  If your family does not feel that return to a traditional school building is in your child’s best interest, please let us know, and we will help make sure we support you from a medical standpoint. 

For further information on the status of coronavirus in people with IBD world-wide, young or old, please go to: www.covidibd.org.

Additional information about the status of COVID-19 can be found at the following websites:


Also, this:

Facebook link (1:22 min): This is what happens when a Special Effects guy stays at home with his son during lockdown


Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Emerging IBD Treatment: Selective Jak Inhibitor, Upadacitinib

Two recent large studies examined the use of Upadacitinib, an oral JAK1 inhibitor, for Crohn’s disease and for Ulcerative Colitis.

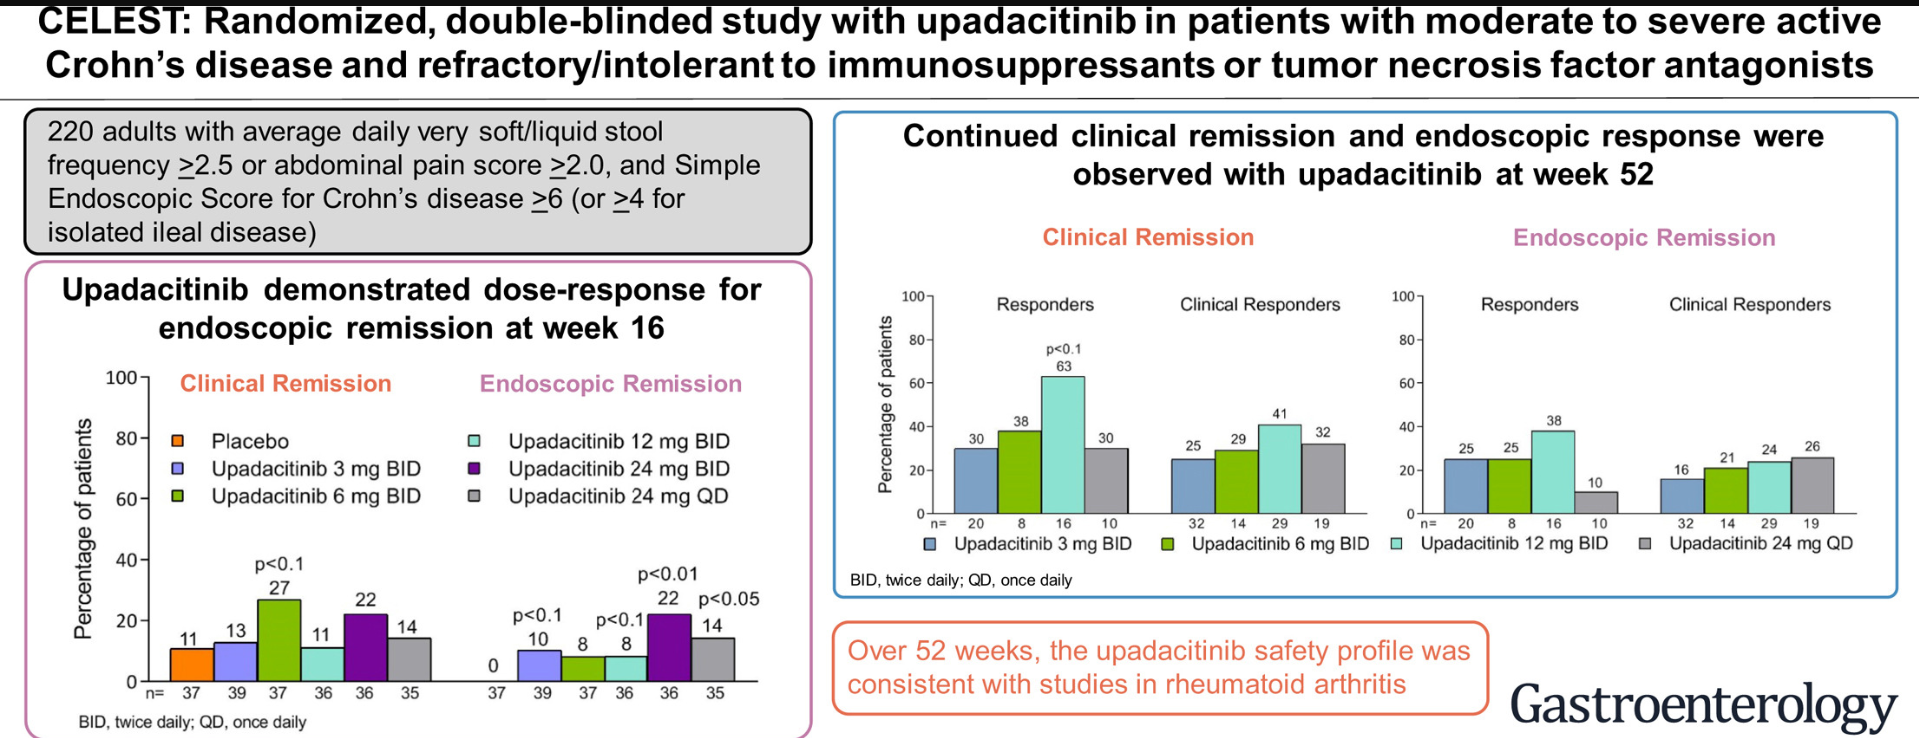
The first study, “CELEST,” (n=220) is the “first to evaluate the efficacy, safety, pharmacokinetics, and dose-response of upadacitinib immediate-release formulation in patients with moderate to severe CD and refractory to TNF antagonist therapy using PRO-based clinical and endoscopic endpoints… Nearly half of the patients enrolled in CELEST (44% [96/220]) were taking oral corticosteroids at baseline and underwent a mandatory taper starting at week 2.” The key findings are noted in the graphical abstract (below). A couple of additional points:

  • During the induction period, the 24-mg twice-daily dose exhibited the most consistent association with meaningful improvements for multiple clinical and endoscopic endpoints at week 12 or 16
  • Clinical remission was achieved by 13% of patients receiving 3 mg upadacitinib, 27% of patients receiving 6 mg upadacitinib (P < .1 vs placebo), 11% of patients receiving 12 mg upadacitinib, and 22% of patients receiving 24 mg upadacitinib
    twice daily, and by 14% of patients receiving 24 mg upadacitinib once daily, vs 11% of patients receiving placebo.
  • Endoscopic remission was achieved by 10% (in 3 mg group) (P < .1 vs placebo), 8% (in 6 mg and 12 mg groups) (P < .1 vs placebo), 22% (in 24 mg BID group) (P < .01 vs placebo), and 14% (in 24 mg QD group) (P < .05 vs placebo) of patients receiving upadacitinib, respectively, vs none of the patients receiving placebo
  • Upadacitinib was also associated with improvements in quality of life, based on IBDQ, observed as early as week 8
  • AEs reported in this study were consistent with those previously observed in clinical trials with JAK inhibitors. Two patients had myocardial infarction events and 1 patient had a mesenteric vein thrombosis.
  • Limitations: sample size, lack of placebo control during maintenance

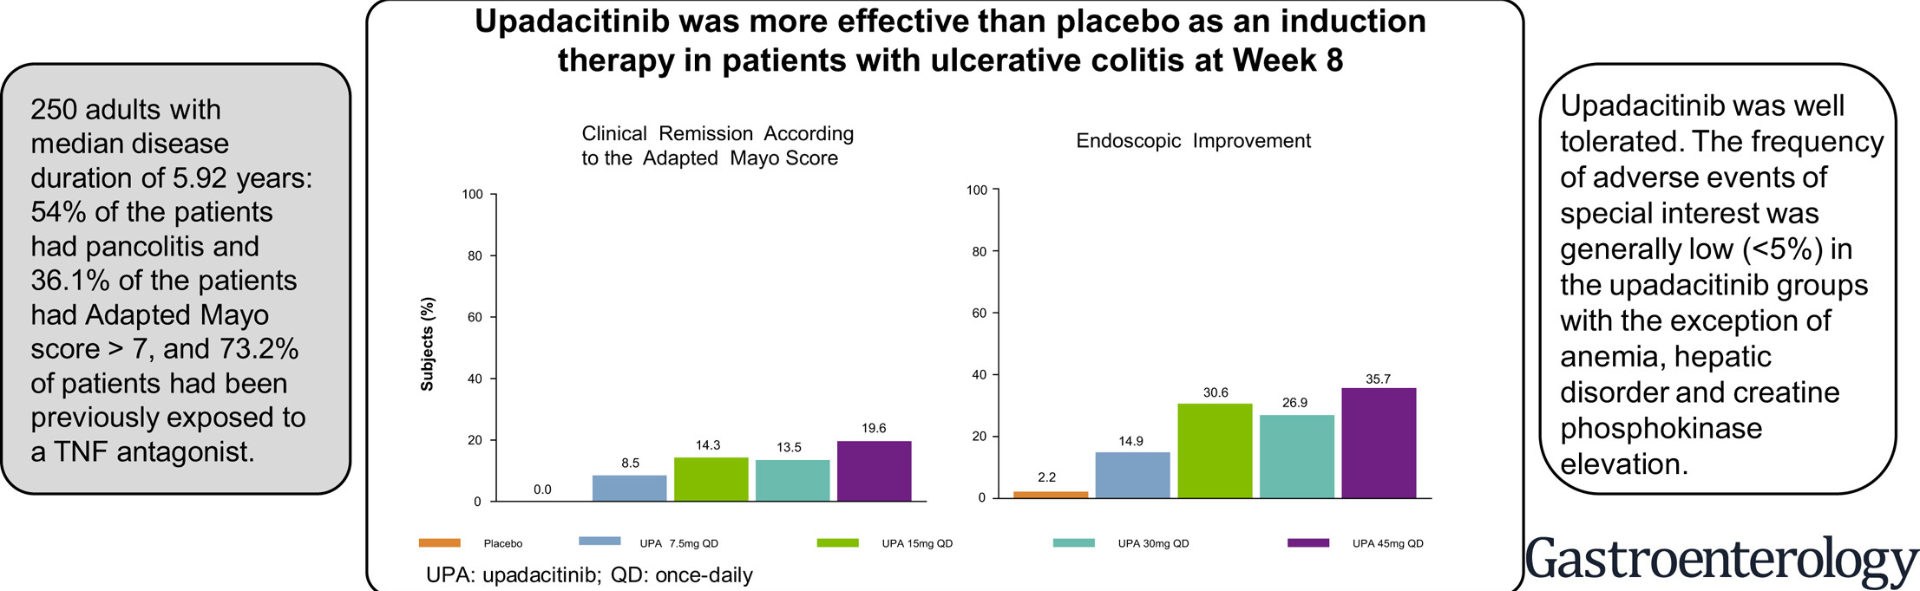
The second study, “U-ACHIEVE,” for ulcerative colitis (n=250) notes that in cellular assays upadacitinib is up to 60-fold selective for JAK1 over JAK2 and >100-fold selective over JAK3.  The study incorporated a new definition for the primary endpoint of clinical remission using the adapted Mayo score with a more stringent criterion than previous studies. A consistent dose-response relationship with upadacitinib for this primary endpoint was observed. Other points:

  • Upadacitinib was more effective than placebo for inducing remission in patients with moderately to severely active ulcerative colitis
  • The onset of action was rapid, as shown by improvement in the partial
    Mayo score at week 2
  • Endoscopic improvement at week 8, defined as endoscopic subscore of 1, was achieved in 14.9%, 30.6%, 26.9%, and 35.7% of patients receiving upadacitinib 7.5 mg, 15 mg, 30 mg, or 45 mg, respectively, compared with 2.2% receiving placebo (P ¼ .033, P < .001, P < .001, and P < .001 compared with placebo, respectively)
  • Histologic improvement was demonstrated in all treatment arms
  • The types of AEs reported in this study were similar to those previously observed in clinical trials with JAK inhibitors. In the 45 mg daily arm, one patient developed herpes zoster and one participant developed deep venous thrombosis/pulmonary embolism (26 days after discontinuation of study medication)

My take: Upadacitinib looks quite promising for ulcerative colitis and is likely to be helpful in a smaller subset of patients with Crohn’s disease.  HIgher doses appear to be more effective but are likely to be associated with higher rates of adverse events. Further studies, including pediatric trials, are needed.


Ustekinumab Over Vedolizumab as 2nd Line Agent for Crohn’s Disease

A recent study: Ustekinumab is associated with superior effectiveness
outcomes compared to vedolizumab in Crohn’s disease patients with prior failure to anti-TNF treatment. VBC Biemans et al. Aliment Pharmacol Ther 2020; 52: 123-134.  Thanks to Ben Gold for this reference.

Methods: Crohn´s disease patients, who failed anti-TNF treatment and started
vedolizumab or ustekinumab in standard care as second-line biological, were
identified in the observational prospective Dutch Initiative on Crohn and
Colitis Registry.  128 vedolizumab- and 85 ustekinumab-treated patients fulfilled
the inclusion criteria. Median age in the cohorts were 37 and 39 respectively.

Key findings (at 52 weeks):

  • After adjusting for confounders, ustekinumab-treated patients were more likely to achieve corticosteroid-free clinical remission (odds ratio [OR]: 2.58, 95% CI: 1.36-4.90, P = 0.004), biochemical remission (OR: 2.34, 95% CI: 1.10-4.96, P = 0.027), and combined corticosteroid-free clinical and biochemical remission (OR: 2.74, 95% CI: 1.23-6.09, P = 0.014).
  • Safety outcomes (infections: OR: 1.26, 95% CI: 0.63-2.54, P = 0.517; adverse events: OR: 1.33, 95% CI: 0.62-2.81, P = 0.464; hospitalisations: OR: 0.67, 95% CI: 0.32-1.39, P = 0.282) were comparable between the two groups

My take: This study indicates that ustekinumab is likely a more effective 2nd line agent for Crohn’s disease.

Related blog posts:

Phase 3 Trial of Budesonide for Eosinophilic Esophagitis & COVID-19 Deaths in U.S.

NY Times article:  U.S. Coronavirus Cases Are Rising Sharply, but Deaths Are Still Down

This article explains why deaths from COVID-19 have not increased despite increasing number of infections.  Three main reasons: increased testing -detects many with less severe symptoms, younger population are being infected, and new treatment approaches may be helping.  However, “the dip in coronavirus mortality will not necessarily last. As more people socialize, those with milder infections might end up ferrying the pathogen to vulnerable individuals…Recent upswings in coronavirus case numbers leave experts apprehensive of what’s to come. Death, when it occurs, tends to trail infection by about two to four weeks.”


The Budesonide Oral Suspension (BOS) resulted in 62% of BOS patients meeting the threshold of < 15 eos/hpf compared to 1% of placebo patients. From lead author, Ikuo Hirano: “the results of the BOS trial showed that BOS successfully treated both the symptoms and signs of EoE. The positive results will hopefully lead to an approved, safe and effective therapy for EoE.”

Abstract from ACG Meeting October 2019:

Abstract: Efficacy of Budesonide Oral Suspension for Eosinophilic Esophagitis in Adolescents and Adults: Results From a Phase 3, Randomized, Placebo-Controlled Trial

Introduction: Eosinophilic esophagitis (EoE) is a chronic immune-mediated disease for which there is an unmet clinical need for new therapies. The safety and efficacy of budesonide oral suspension (BOS) for the treatment of EoE has been demonstrated in a previous phase 2 study. The current phase 3 study evaluated the efficacy and safety of BOS in a large cohort of patients with EoE. 

Methods: This randomized, double-blind, placebo-controlled trial (SHP621-301; NCT02605837) investigated the safety and efficacy of BOS in patients (11–55 years) with EoE and dysphagia. Patients were randomized 2:1 to 2.0 mg BOS or placebo twice daily (b.i.d.) for 12 weeks (Figure 1). Co-primary endpoints were histologic (peak eosinophil count ≤6 eosinophils/high-powered field [eos/hpf]) and dysphagia symptom (≥30% decrease in symptoms as measured by the Dysphagia Symptom Questionnaire [DSQ]) responses after 12 weeks of therapy. Secondary endpoints included change in DSQ score and change in EoE Endoscopic Reference Score (EREFS) from baseline to final treatment period. Safety was also assessed.

Results: A total of 322 patients were randomized (BOS, n=215; placebo, n=107), of whom 318 patients received at least one dose of double-blind therapy (BOS, n=213; placebo, n=105) (Table). The primary outcomes were achieved, with significantly more histologic and symptom responders in the BOS-treated than the placebo-treated group (53.1% vs 1.0%, p< 0.001; 52.6% vs 39.1%, p=0.024, respectively; Figure 2). Improvements in mean DSQ score from baseline to week 12 were significantly greater in the BOS group (n=197) than the placebo group (n=89) (−13.0 vs −9.1; p=0.015). Similarly, improvements in mean EREFS scores were significantly greater with BOS (n=202) than placebo (n=93) (−4.0 vs −2.2; p< 0.001). In total, 61.0% of patients reported a treatment-emergent adverse event (TEAE) (BOS, 61.0%; placebo, 61.0%). Only 2.5% of patients experienced a TEAE leading to dose discontinuation (BOS, 1.4%; placebo, 4.8%). Few patients had severe or serious TEAEs on BOS or placebo.  No life-threatening TEAEs were reported.

Discussion: This phase 3 trial demonstrated the efficacy of BOS as induction therapy for EoE. BOS resulted in significant improvements in histologic, symptomatic and endoscopic endpoints compared with placebo. The majority of TEAEs were mild to moderate and comparable between placebo and BOS. A double-blind, placebo-controlled maintenance study (SHP621-302) is ongoing.

Related blog posts:

Island Ford, Sandy Springs


Eosinophilic Esophagitis -Up to Date Dietary Management Review

A recent terrific review article (H Bashaw et al. JPEN 2020; https://doi.org/10.1002/jpen.1738) provides a good advice on nutritional therapy for eosinophilic esophagitis (Thanks to Kipp Ellsworth for sharing this reference).

Full text: Tutorial: Nutrition Therapy in Eosinophilic Esophagitis—Outcomes and Deficiencies

An excerpt:

  • “Diet elimination addresses the root cause of inflammation, treats EoE by removing the underlying trigger(s) of inflammation, and is a preferred approach for many patients… A registered dietitian is essential to ensure adequate macronutrients and micronutrients are present in the diet and to educate families in learning to read labels and prevent contamination.”
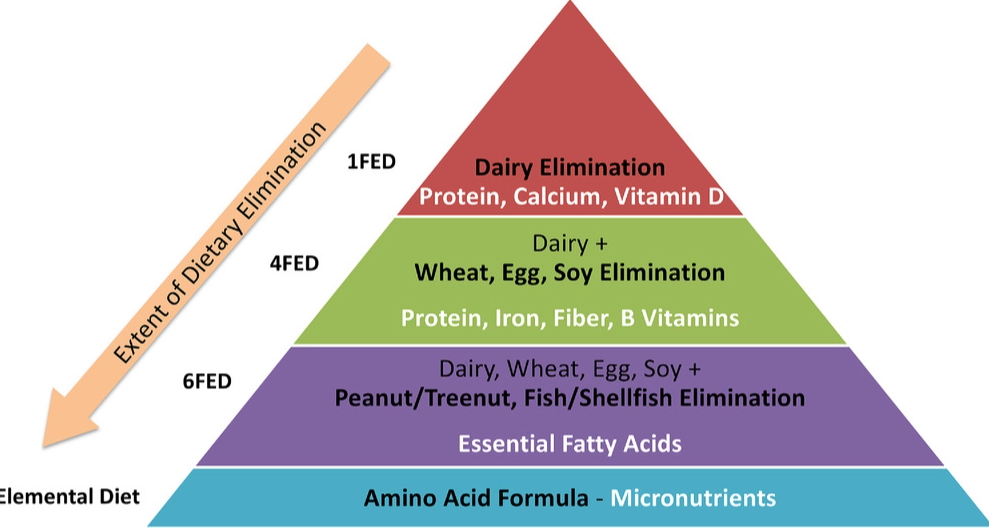
  • ” Each type of elimination diet is associated with inherent nutrition risks.” Table 1 lists the potential nutrient deficiencies with each diet.

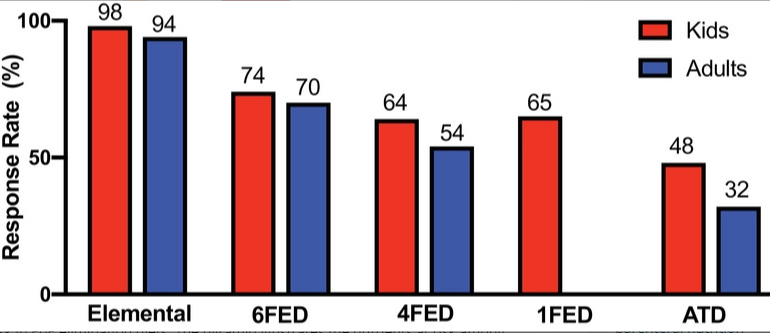
While the response rate is lower with fewer food group elimination, “the benefits of eliminating fewer foods from the diet include improved adherence, greater dietary variety, and a shorter time frame for reintroduction, with fewer endoscopies needed to identify triggers”

My take: As with topical steroids and PPI treatment, dietary treatment for EoE has to be maintained to be effective.  Concerns for adherence with medications are applicable for dietary therapy as well.

Related blog posts:

IBD Update -July 2020

X Roblin et al. Gut 2020; DOI: 10.1136/gutjnl-2019-319758 Addition of azathioprine to the switch of anti-TNF in patients with IBD in clinical relapse with undetectable anti-TNF trough levels and antidrug antibodies: a prospective randomised trial. Key Findings:

  • Rates of clinical failure and occurrence of unfavourable pharmacokinetics were higher in monotherapy compared with combination therapy
  • At 24 months, survival rates without clinical failure and without appearance of unfavourable pharmacokinetics were respectively 22% versus 77% and 22% versus 78% (p<0.001 for both) in monotherapy versus combination therapy

RC Ungaro et al. Clin Gastroenterol Hepatol 2020; 18: 1152-60.  The authors retrospectively analyzed 3178 patients with Crohn’s disease and found that stopping mesalamine therapy in individuals who were starting biologic therapy did NOT increase their risk of adverse clinical events.  They caution that their findings should be validated in a prospective study.

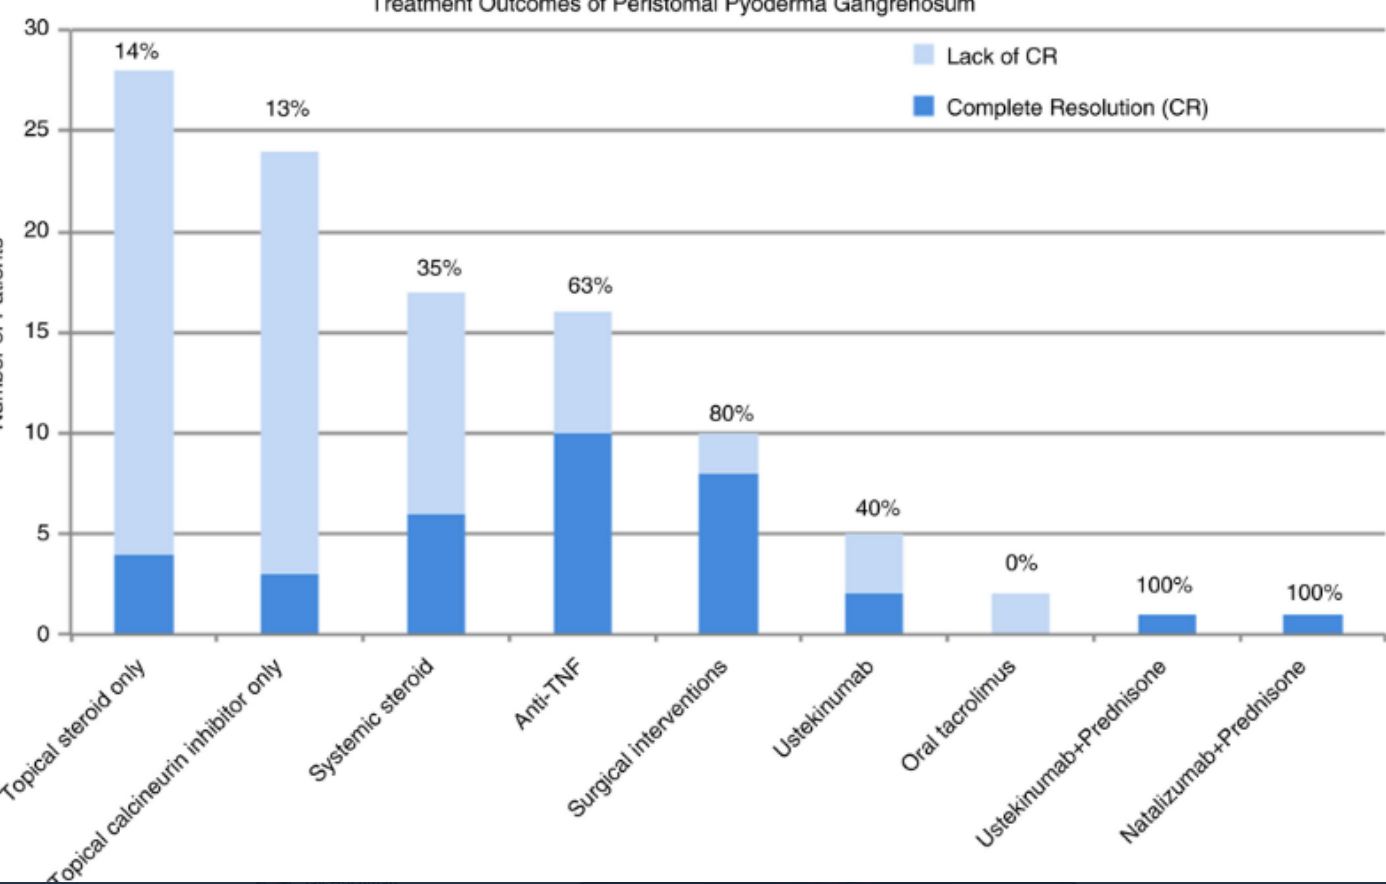
J Wang et al. AP&T. https://doi.org/10.1111/apt.15766. Full Text: Risk factors and treatment outcomes of peristomal pyoderma gangrenosum in patients with inflammatory bowel disease Key finding: “Complete resolution with topical corticosteroids and calcineurin inhibitors alone were low (14% and 13% respectively). Higher rates of complete resolution were reported with anti‐tumour necrosis factor (TNF) agents (63%) and surgical interventions (80%).”

B Verstockt et al. Clin Gastroenterol Hepatol 2020; 18: 1142-51. The authors found that expression of 4 genes in colon tissue could be used to predict which patients will enter endoscopic remission with vedolizumab therapy.  Given the increasing number of expensive therapies for IBD, the ability to predict likely success with treatment rather than selecting empirically would be a huge advance.

ST Leach et al. JPGN 2020; 70: 580-5. The authors found that fecal calprotectin was overall the best fecal biomarker for pediatric Crohn’s disease (=156 patients); however, FA12  (aka S100A12) at 5 mcg/g predicted mucosal healing with greater specificity (87% vs 70%) –though this is related in part to the cut-off values. For calprotectin to have greater specificity (>90%), a cut-off of <100 mcg/g lowered the sensitivity to 63%. FA12 also performs better in younger children as calprotectin levels are higher in this age group in healthy children.

Curcumin Was NOT Effective For Post-operative Crohn’s Disease, Goldman Sachs Take on Masks

NBC/NY Link: Goldman Sachs Says National Mask Mandate Could Slash Infections, Save Economy From 5% Hit


Briefly noted: G Bommelear et al. Clin Gastroenterol Hepatol; 2020; 18: 1553-60. Oral Curcumin No More Effective Than Placebo in Preventing Recurrence of Crohn’s Disease After Surgery in a Randomized Controlled Trial

Methods:

  • Double-blind randomized controlled trial at 8 referral centers in France, from October 2014 through January 2018, with 62 consecutive patients with CD undergoing bowel resection.
  • Patients received azathioprine (2.5 mg/kg) and were randomly assigned to groups given oral curcumin (3 g/day; n = 31) or an identical placebo (n = 31) for 6 months, and were then evaluated by colonoscopy.
  • The primary endpoint: postoperative recurrence of CD in each group (Rutgeerts’ index score ≥i2) at month 6

Key findings:

  • Postoperative recurrence at 6 months: (Rutgeerts’ index score ≥i2): 58% receiving curcumin vs 68% receiving placebo (P = .60).
  • Severe recurrence: 55% receiving Curcumin 55%vs 26% receiving placebo –had a severe recurrence of CD (Rutgeerts’ index score ≥i3) (P = .034).
  • Clinical recurrence of CD (CD activity index score >150) at 6 months: 30% with curcumin compared with 45%  receiving placebo (P = .80)

My take: Curcumin was ineffective in preventing recurrent post-operative Crohn’s disease

Related blog posts:


Liver Shorts -June 2020

SH Ibrahim et al. Hepatology 2020; 71: 1474-85.  Thorough review of liver diseases in the perinatal period and relationship of the maternal-infant interactions.  Liver diseases discussed include GALD which has “strikingly normal or near normal transaminases” despite liver failure (most common etiology).  Treatment for GALD includes IVIG (1 g/kg) along with subsequent double-volume exchange transfusion.  The review covers maternally-transmitted viral infections, fatty liver disease, and acute fatty liver disease of pregnancy (AFLP); AFLP is most commonly caused by LCHAD but can be caused by other defects in fatty acid oxidation.

RT Khalaf, RJ Sokol. Hepatology 2020; 71: 1486-98. This review focuses on intestinal failure-associated liver disease (IFALD).  The review provides an in-depth discussion of intravenous lipid emulsions and other factors implicated in the pathogenesis.

  • Risk factors: bacterial overgrowth, central line infections, recurrent sepsis, prematurity, parenteral nutrition composition, and micronutrient imbalances
  • Protective factors: early enteral nutrition, cycled parenteral nutrition, glucagon-like peptide 2, preservation of ileocecal valve, small bowel lengthening when appropriate
  • While the authors acknowledge that lipid minimization often improves cholestasis, they advise caution due to concern for both essential fatty acid deficiency and detrimental effects on brain growth.
  • Prevention of central line infections with use of ethanol locks is important and effectively reduces the rate by more than 80% (though currently costs of ethanol locks have skyrocketed: FDA Safety Initiative Complicit in Ethanol Costing $30,000 for 1 oz)
  • The authors note that long-term survival from intestinal transplantation is only 40% at 10 years indicating benefit of ongoing parenteral nutrition management if feasible.

Related blog posts:

PL Valentino et al. JPGN 2020; 70: 547-54. This article discusses potential management of Wilson disease diagnosed in infancy based on ATP7B genetic testing. Very little evidence presented.  Suggests starting Zinc therapy at an early age and monitoring for copper deficiency along with efficacy.  More precise recommendations regarding urine copper goals for children would be helpful as well.

Large (n=112, median age 38 years) prospective observational study of Acute Hepatic Porphyria. L Gouya et al. Hepatology 2020; 71: 1546-58. Key findings from EXPLORE group:

  • Chronic symptoms were noted in 65%; 46% had daily symptoms. Symptoms including body pains, trouble sleeping/tiredness, anxiety, GI symptoms (eg. nausea) and weakness.
  • During the 2-year study period, 88% experienced a total of 483 attacks; 77% of these attacks required treatment at a health care facility or hemin administration
  • Median annualized attack rate was 2.0
  • UrineDelta-aminolevulinic acid (ALA) and porphobilinogen (PBG) compared with upper limit of normal at baseline and increased further during attacks.
  • At baseline, 16% had elevations of liver aminotransferases
  • Related reference: M Balwani et al. Hepatology 2017; 66: 1314-22. Acute Hepatic Porphyrias -Review. Current recommendations include gene sequencing to confirm all biochemical cases. Biochemical tests are spot urine testing of porphobilinogen (PBG), 5-aminolevulinic acid (ALA), and porphyrins. A normal urine PBG in symptomatic patients “excludes the three most common acute hepatic porphyrias.”  For those with abnormal studies, this reference is a handy.

Automated ascites pump. F Wong et al. Liver Transplantation 2020; 26: 651-61. In this study with 30 patients, interventional radiology placement of an “alfapump” helped manage refractory ascites in cirrhosis.

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition
How Very Early Onset-Inflammatory Bowel Disease is Different, Plus One

A recent retrospective study (JR Kelsen et al. Inflamm Bowel Dis 2020; 26: 909-18) compares children diagnosed with inflammatory bowel disease at different age points and their outcomes.  During a 9 year study span (2008-16), there were 229 subjects diagnosed as very-early onset (<6 years, VEO), 221 diagnosed as intermediate onset (6-10 years), and 521 diagnosed as older onset (> 10 years)

Key findings:

  • VEO-IBD patients were significantly more likely to have had a diverting ileostomy and colectomy than the older patients.  Diverting ileostomy rates: 12.2%, 4.1%, and 1.2% respectively.  Colectomy rates: 7.4%, 4.1%, and 1.7% respectively.
  • Ileocecal resections were significantly higher in the older-onset IBD population. In the older group, these resections were noted in 64/521 (12.2%) compared to 1/229 (0.4%) in the VEO group and 10/221 (4.5%) in the intermediate group.
  • VEO-IBD patients had higher medication failure rates at 1 year into treatment and were more frequently readmitted to the hospital. For infliximab (IFX), failure rates were 62.4% for VEO subjects compared to 14.6% for older-onset subjects.  For adalimumab, the respective rates were 53.2% vs. 7.2%.
  • Targeted therapy was successfully used almost exclusively in the VEO-IBD population

My take: Children with VEO-IBD have a more severe disease course than older children.  Since monogenetic disorders occur in ~8% of the VEO population, targeted therapies are more likely; however; ~2% of older children also have a monogenetic disorder and as such, targeted therapy could be important in this group as well.

Related review article: J Ouahed et al. Very Early Onset Inflammatory Bowel Disease: A Clinical Approach With a Focus on the Role of Genetics and Underlying Immune Deficiencies. Inflamm Bowel Dis 2020; 26: 820-842.  This is a useful review.  A couple of key points:

  • “There are no quality studies assessing the use of nutritional approaches in VEO-IBD”
  • Stem Cell Transplantation NOT efficacious in these disorders (per Table 3): TTC7A, STXBP2, IKBKG (NEMO)

Related blog posts:

Iodine Deficiency in Extremely Low Gestational Age Newborns Receiving Parenteral Nutrition

Briefly noted: N Kanike et al. Nutrients 2020, 12(6), 1636; https://doi.org/10.3390/nu12061636 (from Kipp Ellsworth Twitter feed)

Full text: Risk of Iodine Deficiency in Extremely Low Gestational Age Newborns on Parenteral Nutrition

Background/Methods: Extremely Low Gestational Age Newborns (ELGAN) do not receive Iodine supplementation while on parenteral nutrition (PN)….We measured urine iodine levels and thyroid function tests in 50 mother–infant dyads at birth, at 1 week, 1, 2, 3 months and near discharge. In our study, 64% of mothers were iodine deficient at the time of delivery.

Key findings:

  • At 1 month of age, ELGAN on PN developed iodine deficiency (p = 0.017) and had high thyroglobulin levels of 187 (156–271) ng/mL
  • Iodine levels improved with enteral feeds by 2 months of age (p = 0.01).

My take: The authors note that “Iodine supplementation during pregnancy and postnatally should be considered to avoid iodine deficiency.”  In addition, in those at risk, there needs to be monitoring and treatment of hypothyroidism.

Related blog posts: