Solitary Rectal Ulcer Syndrome: How Often is It Solitary? How Often is There an Ulcer?

A recent restrospective review of 140 pediatric cases (median age 12 years) of solitary rectal ulcer syndrome (SRUS) (U Poddar et al. JPGN 2020; 71: 29-33) highlights the fact that in many, there are multiple ulcerations and in some there are none.

Key findings:

  • Most had dsynergic defecation with prolonged sitting on the toilet (94%), excessive straining (98%), feeling of incomplete evacuation (93%) or “rectal digitation” (51%)
  • Rectal bleeding was presenting feature in 94%
  • Colonoscopy showed in 72% (n=101); a single ulcer was noted in (60%) (n=84)  -thus in those with an ulcer, 83% were solitary.
  • Of the 113 with adequate followup, 63% had clinical improvement and healing of ulcer was documented in 36/82 (44%)
  • The most common treatment was hydrocortisone enema with bulk laxative (n=73) with “improvement” in 52, “better” in 16, and no response in 5 (8.2%).  Other frequent treatments: sulfasalazine enema with bulk laxative (n=12), and bulk laxative alone (n=22)
  • Most children (95/140) were older than 10 years; only 2 were ≤5 years

My take: Asking carefully about dysnergic bowel habits will make this diagnosis much easier.  Many children with SRUS have erythema and not a solitary ulcer; in addition, lesions can be ulcerative or polypoid.

Related blog post: One more cause of rectal bleeding

Does The Degree of Villous Atrophy Affect Long-Term Outcomes with Celiac Disease? Plus One

S Kroger et al. JPGN 2020; 71: 71-7.  This study, conducted from 1966-2014, examined long-term outcomes of individuals diagnosed with celiac disease in childhood. This study examined 906 children and sent questionnaires to 503 adults (212 responded) who were diagnosed in childhood.

Key findings:

  • More recent diagnosis (after 2006) has been associated with children having milder lesions, more often diagnosis due to screening (rather than symptoms) 30% vs. 25%, less anemia (16% vs 21%), less growth disturbances (22% vs. 36%), and lower TTG-2 titers (mean 64 U/L vs 120 U/L.
  • Among adults completing questionnaire, severity of villous atrophy at childhood diagnosis did not predict complications, persistent symptoms, quality of life, or adherence with glute-free diet

RV Lopez et al. JPGN 2020; 71: 59-63. Influence of the 2012 European Guidelines in Diagnosis and Follow-up of Coeliac Children With Selective IgA Deficiency. This study showed that the guidelines were used incorrectly for individuals with selective IgA deficiency, using a 10-fold elevation of TTG IgG instead of TTG IgA. The associated editorial (pg 2 by P Gillett) recommends “we should perform endoscopy in all sIgAD patients.”  In addition, this population may merit followup endoscopy at much lower threshold due to difficulty using serology for follow-up.

My take: Children with severe villous atrophy due to celiac disease can respond fully to a gluten-free diet.  In the small subset of individuals with selective IgA deficiency, a no-biopsy diagnosis is not recommended.

Related blog posts:

“Health Insurance Is Broken”

From The Onion:


Almost every Sunday, I spend hours reading the local AJC and the NY Times — a great way to start the week.

On July 5th, the NY Times review section discussed the topic of ‘The Economy We Need.’ The article discussed rising problems with wealth inequity and associated problems including higher mortality rates.  The first article states that “if income had kept pace with overall economic growth since 1970, Americans in the bottom 90 percent of the income distribution would be making an extra $12,000 per year, on average.”

The greater inequities are the direct result of policy changes and can be changed. The subsequent articles detail myriad issues from tax policy that bolster wealth inequality (eg. lower inheritance taxes), minimum wage which requires many to rely on government assistance, legacy admissions to elite colleges, corporation stock buybacks (which come at the expense of lower benefits/wages), policies that discourage unions, and corporations that have stopped profit sharing (except for the highest-paid executives).

The article with the most relevance for health care providers: NY Times: “Health Insurance Is Broken” by Jeneen Interlandi. Link to online version: Employer-Based Health Care, Meet Massive Unemployment

Key points:

  • “The nation spends an average of $3.5 trillion on health care –more than Japan, Germany, France, China, the United Kingdom, Italy, Canada, Brazil, Spain, and Australia combined — ant still loses more people to preventable and treatable medical conditions than any of those countries do…America has created the most expensive, least effective health care system in the modern world.”
  • The problem has deep roots.  One of the issues with the cost, at least historically, has been “price insensitivity.”  “If the insurer is paying, nobody looks at the bill.”…Hospitals ramped up equipment purchases, workforces, specialty clinics and “passed [the price hikes] from hospitals to insurers to customers.”‘
  • “Employer-based insurance is heavily subsidized by the federal government …[and] are not much different than the ones granted to low-income Americans through Medicaid and the Affordable Care Act.”
  • “The country will have to stop making employers the sole source of health care for so many people.”  Alternatives could include single-payer system or ‘public option.’

My take: The U.S. health care system costs too much and has gaping problems with lack of coverage and inequities. These problems have worsened with the current pandemic.

Related article: NY Times:  The U.S. Is Lagging Behind Many Rich Countries. These Charts Show Why.

Related blog posts:

Probiotics in Preemies: Lifesaving Therapy

Lots of studies have indicated that probiotics may be beneficial in premature newborns; the problem is that there are currently no FDA-approved probiotics for preterm infants. The use of probiotics as a non-regulated FDA product leads to the potential risk of contamination due to inconsistent quality control as well as variability in the strains and concentrations.  The risks are not inconsequential as there has been a report of 29-week infant who died from mucormycosis due to probiotic contamination with mold.

Despite the potential problems with probiotics in this population, their usage is increasing as described in a recent multicenter retrospective cohort study (KD Gray et al. J Pediatr 2020; 222: 59-64) which took place between 1997-2016 with 78,076 infants (23-29 weeks gestational age) in 289 NICUs.

Key findings

  • 3626 (4.6%) received probiotics
  • Probiotic use increased over the study period (>10% in 2015 & 2016)
  • By matching 2178 infants who received probiotics with 33,807 without probiotics, the authors determined that those received probiotics had a decrease likelihood of necrotizing enterocolitis (OR 0.62) and death (OR 0.52).  The authors observed an increase in Candida infection (OR 2.23); though, this is an infrequent infection and the absolute difference in risk was <1%
  • Limitations: “similar to many previous studies, there was great variation in probiotic products and organisms, as well as a lack of dosing information, which made it unclear which product, organism, or dose might be most effective.”  Also, other contributing factors like consumption of breastmilk and antibiotic exposure are not detailed in this report.

My take: Probiotics could be life-saving for premature infants. It would be nice if we could find out which strains work and which ones do not as well as to assure safe manufacturing processes.

Related blog posts:

More Iron Infusions, Less Blood Transfusions in Kids with Inflammatory Bowel Disease; COVID-19 Transmission in Children


Briefly noted: AE Jacobson-Kelly et al. J Pediatr 2020; 222: 141-5. In this retrospective multicenter cohort study (2012-2018), the authors used the Pediatric Health Information System administrative database (n= 8007 with 28 260 admissions, <21 yrs of age). Key findings:

  • Anemia was documented in 29.8% of admissions.  IV iron was given in 6.3% of admissions and blood transfusions in 7.4%
  • A steady increase in the proportion of IBD admissions received IV iron, from 3.5% in 2012 to 10.4% in 2018 ( P < .0001), and the proportion of admissions with red cell transfusions decreased over time from 9.4% to 4.4% ( P < .0001).

Related blog posts:


Myth or Fact: Joint Hypermobility is Related to Pediatric Functional Abdominal Pain & Dr. Roy Link

According to a recent study (RJ Shulman et al. J Pediatri 2020; 222: 134-40), the prevalence of joint hypermobility does NOT differ in children with irritable bowel syndrome, functional abdominal pain, or healthy control children.

Methods (to reach this conclusion):

  • Children (median age ~9.5 years) with irritable bowel syndrome (n=109), functional abdominal pain (n=31), and healthy controls (n=69) completed a prospective 2-week pain and stooling diaries.  In addition, children and parents reported on measures of anxiety, depression, and somatization. Children were recruited from both primary care and tertiary care settings
  • Joint hypermobility was determined using Beighton criteria using a goniometer and examined cutoffs at both ≥4 or ≥6).

Key findings:

  • Beighton scores were similar between the groups, as was the proportion with joint hypermobility.  Beighton scores were not related to abdominal pain or stooling characteristics.
  • Beighton score ≥4: IBS 35%, FAP 36%, healthy controls 36%.
  • Beighton score ≥6: IBS 12%, FAP 13%, healthy controls 9%.
  • Children reported depression more frequently in those with Beighton scores ≥6 and somatization was greater in those with a score ≥4.

Discussion:

  • “It is well-recognized that patients with joint hypermobility syndromes (eg, Ehlers-Danlos syndrome, Marfan) commonly have GI symptoms.” However, joint hypermobility is common —in this study’s healthy control group 36% had a score ≥4 and 9% had a score ≥6.
  • This study is in agreement with a school-based study (n=136) (M Saps et al. JPGN 2018; 66: 387-90).
  • Limitations: This study population had a median age of ~9.5 years; thus, these findings need to be determined in an older children

My take: There does not appear to be an increased risk of functional GI disorders in children with joint hypermobility. Thus, looking for joint laxity/hypermobility in children with abdominal pain is not needed.

Related blog posts:

Also, a link to Dr. Roy (Benaroch).  Roy is an Atlanta pediatrician and he explains, with the help of Batman and Luigi, the term ‘index’ case and when one is considered exposed: Dr. Roy Covid Pathway

COVID-19: Universal Mask Wearing (JAMA) and Israel’s Concerning Experience with Opening Schools

JAMA Editorial (July 14, 2020) JT Brooks, JC Butler, RR Redfield (all authors from CDC), JAMA. Published online July 14, 2020. doi:10.1001/jama.2020.13107: Universal Masking to Prevent SARS-CoV-2 Transmission—The Time Is Now

An excerpt:

In this issue of JAMA, Wang et al present evidence that universal masking of health care workers (HCWs) and patients can help reduce transmission of severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) infections.1 In the largest health care system in Massachusetts with more than 75 000 employees, in tandem with routine symptom screening and diagnostic testing of symptomatic HCWs for SARS-CoV-2 infection, leadership mandated a policy of universal masking for all HCWs as well as for all patients. The authors present data that prior to implementation of universal masking in late March 2020, new infections among HCWs with direct or indirect patient contact were increasing exponentially, from 0% to 21.3% (a mean increase of 1.16% per day). However, after the universal masking policy was in place, the proportion of symptomatic HCWs with positive test results steadily declined, from 14.7% to 11.5% (a mean decrease of 0.49% per day). Although not a randomized clinical trial, this study provides critically important data to emphasize that masking helps prevent transmission of SARS-CoV-2…. the public needs consistent, clear, and appealing messaging that normalizes community masking. At this critical juncture when COVID-19 is resurging, broad adoption of cloth face coverings is a civic duty, a small sacrifice reliant on a highly effective low-tech solution that can help turn the tide favorably in national and global efforts against COVID-19.

Related blog posts:

Some of the uptick in cases likely related to lack of concern and not using masks

Adjustment of azathioprine dose in NUDT15 intermediate metabolizers, COVID-19 in Georgia & COVID-19 Phase 1 Vaccine Study

LA Jackson et al. NEJM 2020; DOI: 10.1056/NEJMoa2022483. Link:  An mRNA Vaccine against SARS-CoV-2 — Preliminary Report  The mRNA-1273 vaccine induced anti–SARS-CoV-2 immune responses in all participants (n=45), and no trial-limiting safety concerns were identified.

______________________________________________________________________

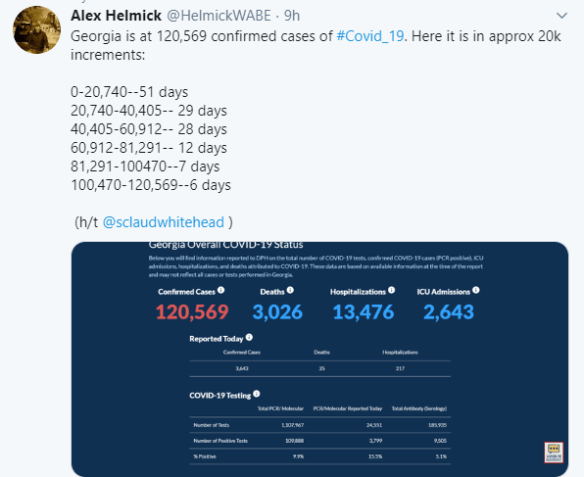
COVID-19 in Georgia (Data from 7/13/20):

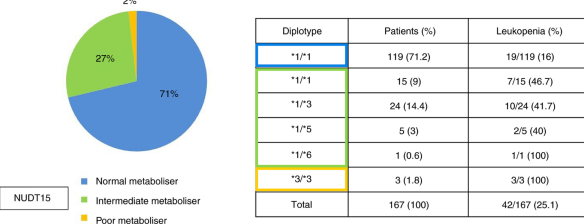
B Kang et al. AP&T 2020; https://doi.org/10.1111/apt.15810. Thanks to Ben Gold for this reference. Full text: Adjustment of azathioprine dose should be based on a lower 6‐TGN target level to avoid leucopenia in NUDT15 intermediate metabolizers

Background: “In addition to TPMT polymorphisms, a recent genome‐wide association study reported that a missense variant of nudix hydrolase 15 (NUDT15 ), which encodes a novel thiopurine‐metabolizing enzyme, was strongly associated with thiopurine‐induced leucopenia especially in Asians”

Key findings:

  • Among the 167 pediatric patients included, leucopenia was observed in 16% (19/119), 44% (20/45) and 100% (3/3) of the NUDT15 normal, intermediate and poor metabolizers respectively (P  < 0.001)
  • There was a positive association between 6‐TGN levels and leucopenia among the NUDT15 intermediate/TPMT normal metabolizers
  • In order to reduce the development of thiopurine‐induced leucopenia (<15%) in NUDT15 intermediate metabolizers, adjustment of azathioprine doses should be based on a lower 6‐TGN target level (<167.1 pmol/8 × 108 RBC)

Limitations: single-center, retrospective study and possible selection bias

My take: While 6-TGN levels between 235-400 are typically considered therapeutic, individuals with intermediate metabolism are at increased risk for leukopenia and may respond at lower levels.  This study indicates that careful dosing and close monitoring is needed for NUDT15 intermediate metabolizers

Related blog posts:
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition


Scrutiny Over Expertise with Dietary Guidelines

From NY Times: Scientific Panel on New Dietary Guidelines Draws Criticism from Health Advocates

An excerpt:

More than half the members of a panel considering changes to the nation’s blueprint for healthy eating have ties to the food industry…

Marion Nestle, a nutrition expert at New York University who served on the advisory panel in 1995, said the large number of experts with industry ties reflected the dearth of public funding for nutrition science, which forces many researchers to accept funding from food companies and industry associations. “Anyone who thinks it’s not OK to accept corporate money would never get appointed to that committee,” she said. “That’s considered so biased that you’re too biased to function.”

Despite concerns about this year’s process, Ms. Nestle said she believed the new guidelines would likely resemble the recommendations that were issued five years ago. The bigger issue, she said, is that most Americans will find the guidelines hard to decipher and unsure how to apply them to their own eating habits.

“Every five years, the guidelines get longer and more complicated,” she said. “In my view, the advice is the same: Eat your vegetables don’t gain too much weight and avoid junk foods with a lot of salt, sugar and saturated fat.”

My take: Most well-informed individuals lack confidence that this the administration is working to improve dietary guidelines, regardless of who is selected to be on their committees.

Related blog posts:

Don’t Miss: Annual Aspen Conference on Pediatric Gastrointestinal Disease: Advances in Pediatric Liver Disease and Liver Transplantation (Online)

This year I had planned to go back to what many consider the best learning conference in our field, the Annual Aspen Conference.  This conference alternates yearly between GI topics and liver topics.  What has made this conference so great:

  • Intimate setting
  • Terrific faculty
  • Chance to enjoy the surroundings with friends and families after the lectures

Due to the pandemic, this year’s course will be curtailed and online.  While this changes the setting, it is still a great opportunity and a heck of a lot easier to attend. It will take place 1:00-2:30 pm Tues, Weds, and Thurs next week (July 14-16).  You can register for a day or for all 3 days. Course description and faculty are listed below.

Also, there is a pre-conference SCAVENGER HUNT.  (This appears to be mainly to help with promotion of the conference sponsors.) By participating, attendees will be eligible for  raffle prizes awarded during the webinar:
•  Snowmass Camelback
•  Snowmass Winter Gloves
•  Snowmass Hat
•  Snowmass Socks
The GRAND PRIZE is FREE 2021 CONFERENCE REGISTRATION!