VN Dargenio et al. J Pediatr Gastroenterol Nutr. 2026;83:304–313. A systematic review of celiac disease recommendations for children with Down syndrome
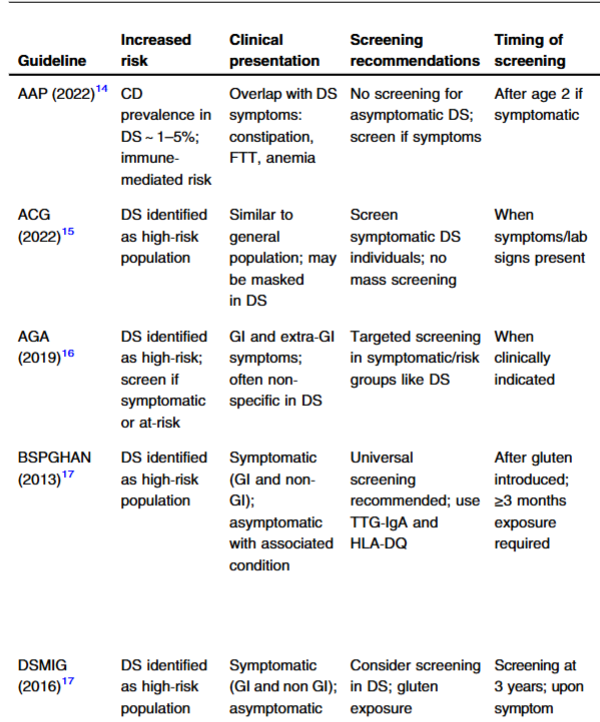
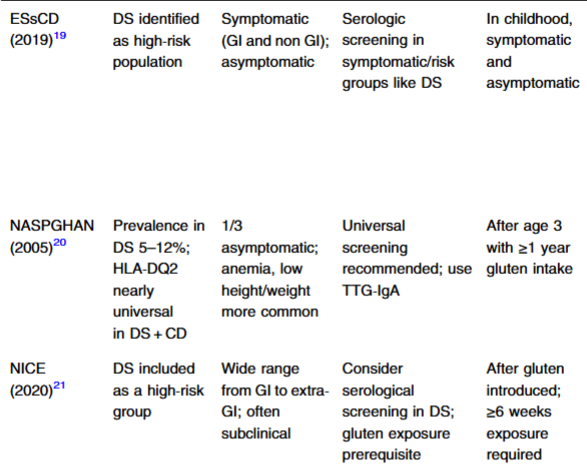
Background: “CD [celiac disease] prevalence in DS is higher than in the general population.10 The overlapping symptoms between CD and DS, such as growth failure, fatigue, GI disturbances, and, less frequently, neurological and behavioral problems, pose significant diagnostic challenges, as these are often attributed to underlying DS comorbidities, leading to delays in recognizing CD.4, 11
Guidelines:
The authors note wide variation in the prevalence of CD in DS in various studies. “A meta-analysis of 31 studies including 4383 individuals found a pooled prevalence of biopsy-confirmed CD of 5.8% (95% CI 4.7%–7.2%), with slightly higher rates in children (6.6%) compared to mixed-age samples (5.1%)31…these findings align with the 5%–13% prevalence range documented in earlier European studies2“
The authors recommend the following strategy:
“Given the high prevalence of asymptomatic and atypical presentations, reliance on symptoms alone is insufficient. A pragmatic strategy should initiate with universal serological screening for all children with DS after gluten introduction (12–24 months of age), followed by periodic re-screening every 2–3 years, using tTG-IgA with total IgA assessment, supplemented by IgG-based assays in the context of the high rate of selective IgA deficiency in DS.”
My take: There are wide discrepancies in the recommendations for screening for celiac disease in asymptomatic individuals with Down syndrome.
JS Khoo, D Yang et al. J Pediatr Gastroenterol Nutr. 2026;83:251–257. The rumination severity index: Development and evaluation of a scoring tool for rumination syndrome
Methods: 66 children with rumination syndrome (RS) completed the 7-item RumSI and PedsQL questionnaires between 2018 and 2023.
RumSI Scoring: Skipped meals, weight loss due to vomiting, and use of a feeding tube or parenteral nutrition were each dichotomized, with absence of the symptom assigned a score of zero for each item and presence of the symptom assigned a score of 1.5σ = 4, where σ is the standard deviation of the combined vomiting/re-swallowing score. Both skipped days of school and social activities in the past 60 days were grouped into categories of 0, 1–4, 5–9, 10–19, 20–39, and 40–60 and assigned integer values of zero to five. The overall RumSI score was calculated by summing the six individual components (vomiting/re-swallowing, skipped meals, weight loss, use of feeding tube or parenteral nutrition, skipped days of school, and skipped days of sports/social activities).
Key Findings:
RumSI scores ranged from 0 to 26.5 (mean 10.6 ± 7.2) out of a total possible 28, with higher scores indicating worse rumination symptoms
RumSI and PedsQL scores were significantly negatively correlated (r = −0.45, p < 0.001), with every 1-point increase in RumSI score associated with a 1.3-point decrease in PedsQL total score
Higher RumSI scores were associated with co-morbid conditions including depression, functional dyspepsia, functional nausea/vomiting, gastroparesis, and postural orthostatic tachycardia syndrome
My take: Currently, the RumSI score would be cumbersome in clinical practice (in the absence of an embedded calculator). However, the questions on the RumSI are very useful and I already made a smartphrase to help capture this information on patients with suspected rumination. Also, the RumSI should be useful for research studies by offering a common scoring system to define and track disease burden.
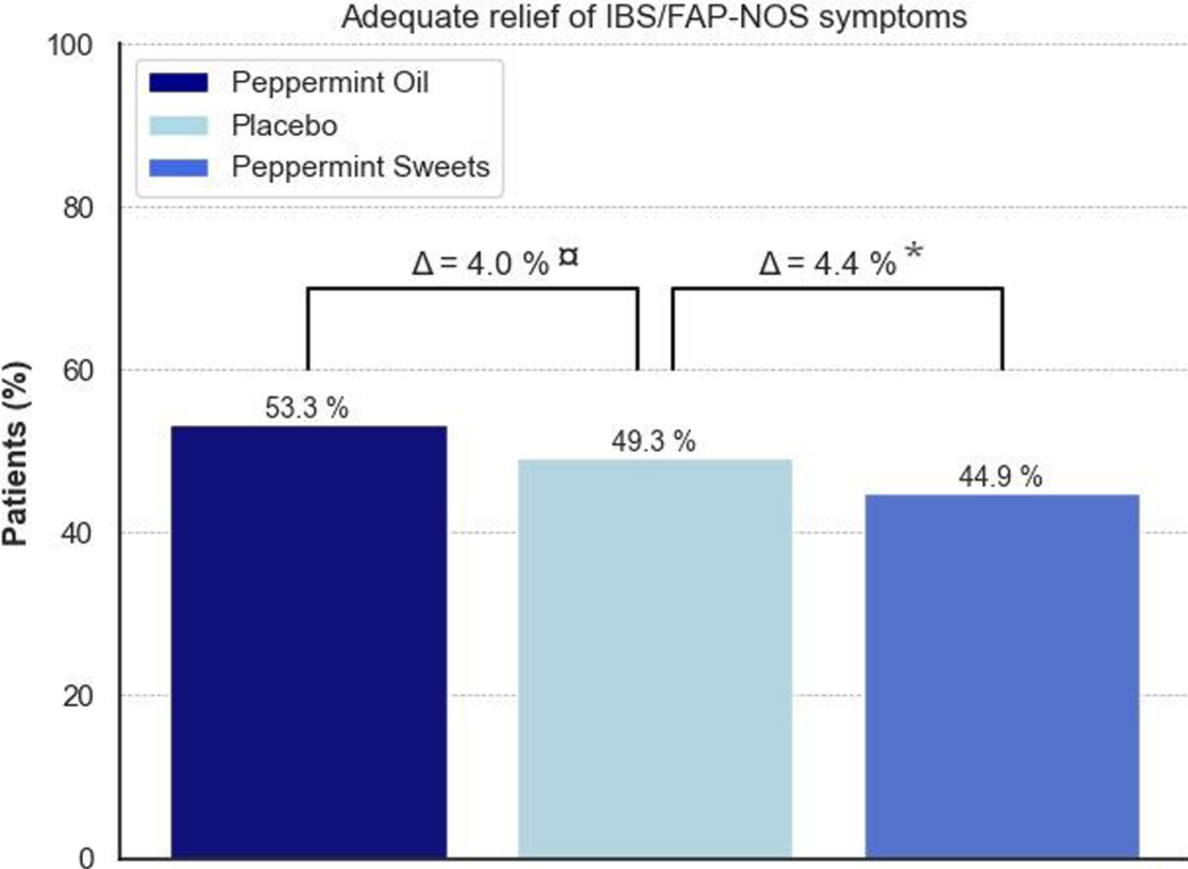
Yesterday’s post showed that peppermint oil/sweets were not superior to placebo for management of pediatric IBS. Today’s study, likewise, shows that nortriptyline was not superior to placebo for functional dyspepsia, another DGBI. At the same time, the trials also showed fairly high response rates along with low adverse effect rate.
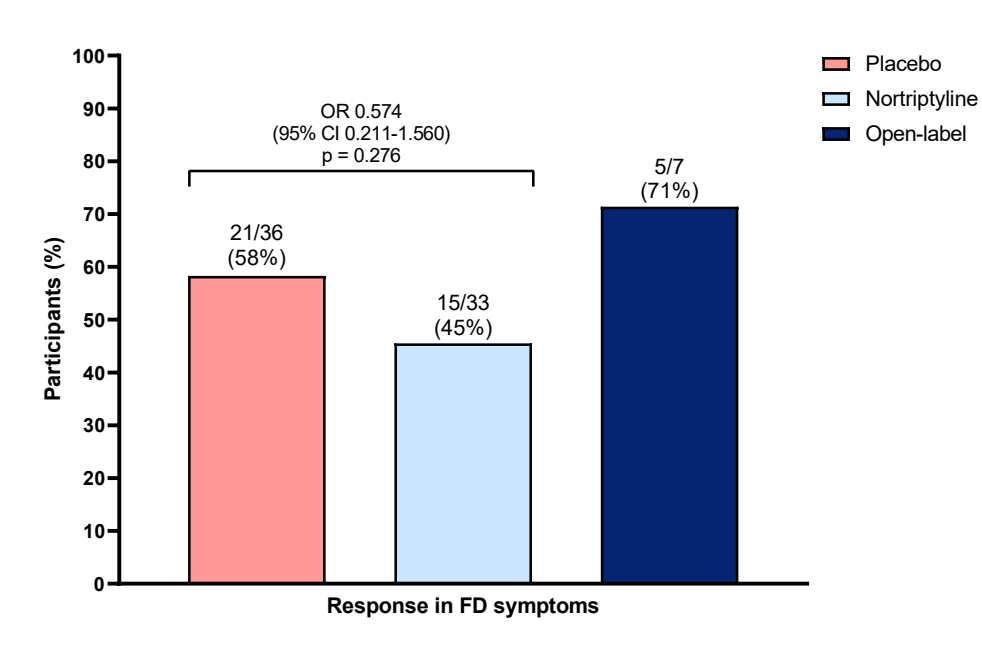
Methods: This was a multicenter, RCT of patients with FD (functional dyspepsia) in primary, secondary, and tertiary care. Sixty-nine participants were randomly assigned to nortriptyline (weeks 1–2: 10 mg; weeks 3–4: 25 mg; weeks 5–12: 50 mg) vs placebo for a 12-week treatment. The primary outcome was clinical response based on a decrease in FD symptoms of at least 30% compared with baseline, in 50% of the last 10 weeks of the treatment period.
Key finding:
The primary outcome showed no significant difference in response for nortriptyline compared with placebo (45% vs 58%; odds ratio [OR], 0.574)
There was no significant difference in adverse events between the nortriptyline and placebo group
Nortriptyline plasma levels were significantly higher in responders compared with non-responders (13.0 μg/L vs. vs 9.0 μg/L; P = .003)
The belief to have received nortriptyline showed a higher response rate than the belief to have received placebo (77% vs 36%; OR, 11.439; P = .004)
The accompanying editorial makes several important points:
“Placebo response is intrinsic to all DGBI trials. Across pediatric and adult populations, placebo response rates of 30% to 60% are common.3–5 Symptom fluctuation, regression to the mean, expectation bias, and cognitive–affective modulation of visceral perception all contribute. In children, parental expectations and heightened suggestibility may further amplify contextual effects. Nevertheless, they also highlight that placebo effects are an integral part of the therapeutic response seen in DGBI trials and clinical practice.”
“Expectancy effects deserve deliberate consideration in both trial design and clinical care. The nortriptyline trial elegantly demonstrated that participants’ belief or expectation about treatment allocation was more strongly associated with response than the medication itself…In clinical practice, clear explanations, symptom validation, confident framing of the treatment rationale, and a strong clinician–patient alliance can ethically harness expectancy and placebo effects to enhance response.6“
“Neither study suggests that pharmacologic therapy has no role in management. The association between higher nortriptyline plasma levels and response leaves open the possibility that a subset of patients derive biological benefit. Likewise, peppermint oil was safe and well-tolerated. However, these trials caution against overinterpreting modest signals from small or uncontrolled studies and emphasize the importance of adequately powered, methodologically rigorous trials in conditions characterized by high placebo response.”
My take: Rigorous pharmacologic studies show that medications, to date, recommended for patients with DGBIs have difficulty outperforming placebo; yet, there is a high response in patients with DGBIs. In this setting, the use of medications with a low incidence of adverse effects and plausible beneficial effects continue to have a role in improving symptom control.
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
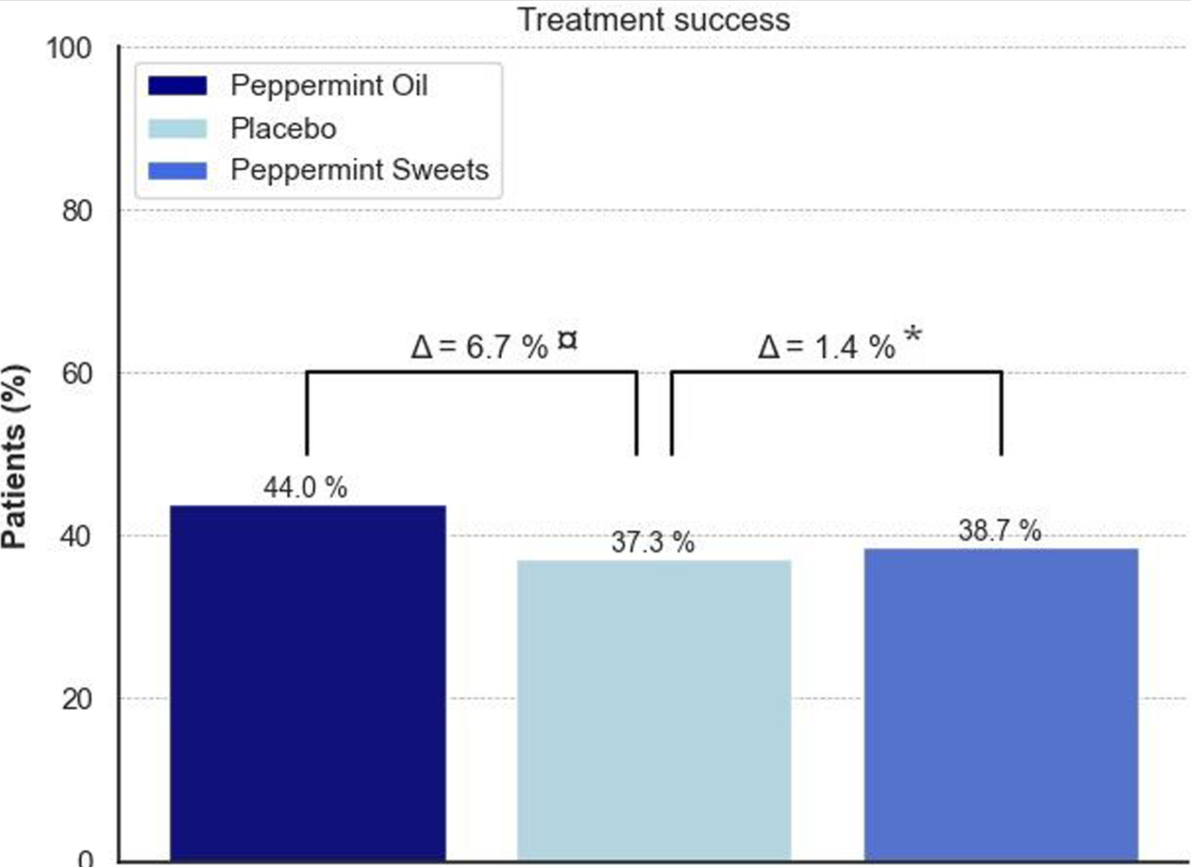
Methods: A large randomized controlled trial evaluated 228 children and adolescents aged 8 to 18 years across multiple hospitals. The primary endpoint was treatment success, defined as a ≥30% reduction of abdominal pain intensity after 8 weeks.
Key finding:
Treatment success rates—measured as a 30% or greater drop in pain intensity after 8 weeks—were similar for peppermint oil (44.0%), peppermint sweets (38.7%), and placebo (37.3%)
My take: The overall response rate for peppermint oil, peppermint sweets and placebo ranged from 37% to 44%. Given its safety, it should still be considered a useful treatment for pediatric IBS (see more on this tomorrow). It is listed as a recommended therapy in recent guidelines with low evidence of effectiveness.
Methods: This was a multicenter retrospective study examining the safety of anti-TNF therapy in children (n=203) with Crohn’s disease (CD) who developed internally penetrating complications (IPCs; abscesses and inflammatory masses). The exposure timeframe was anti-TNF administration within 30 days of IPC diagnosis.
Key findings:
In Cox analyses, early anti-TNF was not linked to infectious serious adverse events (iSAE), noninfectious CD-related SAE, or surgeries, but was associated with increased combined clinical-biochemical-corticosteroid-free remission (hazard ratio 1.65).
Surgical risk differed by percutaneous drainage (PD) status: patients receiving early anti-TNF and PD had lower risk versus PD alone (event-free survival 58% vs 15%, log-rank P = 0.04).
My take: For many years, my practice has been to use early anti-TNF even in patients with internally penetrating complications. This study confirms that anti-TNF therapy may be beneficial in this setting.
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition
K McNevin, BE Rosete et al. J Pediatr Gastroenterol Nutr. 2026;82:1303–1308. A comparison between sodium bicarbonate and ethanol for central line locks in pediatric patients with intestinal failure
Background: Since 2022, there has been growing interest in the use of sodium bicarbonate locks. This dates back to 2018, when Belcher pharmaceuticals managed to get the FDA to designate Ethanol as an orphan drug with a subsequent increase in cost (at that time) to ~$10,000 for a 10-vial pack (10-day supply) (Related post: FDA ‘Safety Initiative’ Now Means an Ounce of Ethanol Costs $30,000). As such, many (?most) children with intestinal failure (IF) no longer had access to Ethanol Lock Therapy which prevents life-threatening infections to their central lines. Sodium bicarbonate has been shown to inhibit bacterial proliferation by impeding bacterial adherence and preventing biofilm formation.15, 16
Methods: A retrospective cohort study was conducted in pediatric patients with IF (19 children who received ethanol locks and 36 with sodium bicarbonate locks) followed by the Intestinal Rehabilitation Program at Seattle Children’s Hospital who received ethanol or sodium bicarbonate locks from 2018 to 2023.
Volume of the lock was calculated based on the documented catheter length when available and by drawing back from the line until blood return was obtained when length unavailable. Ethanol locks were withdrawn from the catheter after the dwell while SBL were flushed.
Key findings:
Rates of CLABSI were similar between the ethanol and sodium bicarbonate lock cohorts (2.03 per 1000 catheter days and 1.59 per 1000 catheter days; p = 0.617)
The sodium bicarbonate group had a lower rate of line replacement (2.21 in the EL group and 0.00 in the SBL group (p = 0.01) and trended toward a lower rate of line repair with1.94 in the EL group and 1.07 in the SBL group (p = 0.23).
Discussion:
“While alternatives exist and may also be effective, SBL has the added benefit of a substantially lower cost. At the time this manuscript was written, based on SCH mediation wholesaler data, the cost of 1 mL of ethanol (Ablysinol®) was $186.66 whereas 1 ml of sodium bicarbonate 8.4% was $0.18.”
My take (borrowed from the authors); Based on these data, SBL should be considered as a primary option for lock therapy in children with IF.
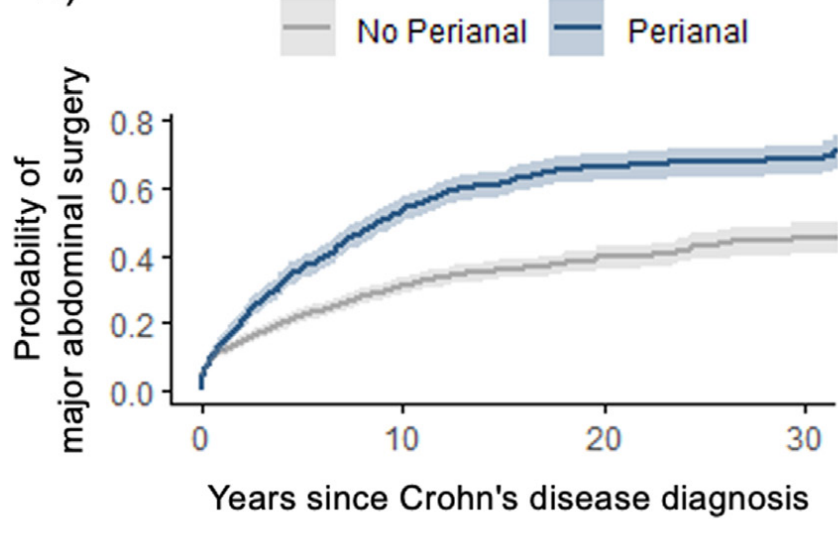
Methods: In this nationwide Danish registry, a pediatric-onset CD cohort from 1980 to 2022 was identified. Outcomes for patients with and without perianal disease were examined.
Key findings:
There were 2356 patients with pediatric-onset CD, of whom 769 (32.6%) developed perianal CD. The cumulative incidence of perianal CD was 14.0%, 21.1%, and 28.1% after 1, 5, and 10 years. After 30 years, the incidence rate was 45.2%.
A stoma was required in 308 (40.1%) and 147 (9.3%) patients with and without perianal disease, respectively (aHR, 2.8).
Probability of Major Abdominal Surgery in Patients with and without Perianal Disease
When comparing patients with/without perianal disease, the aHR for major abdominal surgery, cancer, and mortality were 1.5, 0.8, and 1.5 , respectively.
Probability of Mortality in Patients with and without Perianal Disease
When comparing patients with/without perianal disease, the aHR for mortality was 1.5. Of mortalities, 35 had perianal disease (4.6%; mortality rate, 2.2/1000 person-years) and 33 did not (2.1%; mortality rate, 1.4/1000 person-years). However, the confidence interval was 0.9-2.7) indicating the precision of this finding is low.
Discussion: “In our study, patients without perianal disease were diagnosed with CD more frequently in recent decades than patients with perianal disease. The differences in distribution of CD diagnosis over calendar years may be due to shorter follow-up among patients diagnosed with CD in recent decades, improved treatment delaying disease progression, and increased detection of milder CD phenotypes over time.”
My take: This study reinforces and quantitates the view that having perianal Crohn’s disease portends an increased risk for severe complications. With improving treatments, perhaps the outcomes will be more favorable now and in decades hence.
Methods: This studied children born between 2010 and 2021 using the French National Health Data System registry (EPI-MERES). PPI use was identified through prescriptions before age 1 year.
Key findings:
There were 703,891 PPI users among the 8,222,100 children included.
The incidence of PPI use was 54.4 per 100 person-years among children with hospital-diagnosed gastroesophageal reflux disease (GERD) (+ 33.6% between 2010 and 2021), and 7.9 per 100 person-years in those without (+ 63.6%).
PPI use was associated with extreme prematurity (aOR=1.91), digestive diseases (aOR=5.60), respiratory diseases, aOR, 2.73, neurological diseases (aOR=1.59), and with high maternal socioeconomic level (first quintile of deprivation index [least deprived] vs fifth quintile [most deprived] (aOR=1.80)
The median age at initiation of PPI treatment decreased over time, supporting the idea that PPI use may have become more commonplace.
Discussion:
The presence of underlying diseases may increase the use of PPIs as it is “consistent with the hypothesis that more frequent interactions with the healthcare system may be closely associated” increased prescriptions of PPIs.
Potential adverse PPI effects: “Early life PPI exposure has been associated with an increased risk of respiratory and gastrointestinal infections. [Also, there are] associations with immune-mediated diseases potentially mediated by microbiome alterations, including asthma,25,26 allergic disorders,26,27 and inflammatory bowel disease.28“
“PPI use in children aged <1 year may be appropriate, especially for esophagitis,1 but is not needed if the symptoms do not interfere with growth and development,1 and there is no evidence supporting empirical PPI therapy for diagnosing GERD in infants.1“
My take: This study shows that PPI use before age 1 has increased sharply in France since 2010. This coincides with high usage in infants elsewhere despite lack of proven efficacy. However, a recent study from Boston showed a declining trajectory of PPI use (see related posts). This indicates that a consistent message that most infants should not be treated with PPIs may be effective.
*Two of the study authors have financial ties to the manufacturer of the ultra-slim endoscopes.
Methods: Ten pediatric subjects (including one that was 2.9 years of age) with suspected or known esophageal varices (EV) underwent surveillance endoscopy using the ultra-slim endoscope (transoral or transnasal endosocpy [TNE]) followed by the standard gastroscope under sedation. Esophageal findings were analyzed using images from both procedures by two independent endoscopists.
Key findings:
EV were identified in 8/10 subjects (Grade I (4), Grade II (3), and Grade II/III (1))
Endoscopic grading matched between both endoscopes in 7/8 (87.5%) cases
Three subjects required endoscopic intervention with either sclerotherapy (n = 1) or band ligation (n = 2)
Limitation: High risk stigmata of recent bleeding such as red wale signs or fibrin plugs were not assessed and documented in this study. These features are important for risk stratification; thus, understanding whether the ultra-slim endoscope reliably identifies these stigmata is needed
In the discussion, the authors note that “our study demonstrates the potential for considering TNE for EV evaluation in a lower cost, lower acuity setting.” In my view, this is a flawed argument, particularly in pediatrics.
For varices, many of the children need therapeutic endoscopic intervention. Thus, outside of a study design, this requires an additional procedure (and additional cost).
In pediatric gastroenterology, most clinicians do their endoscopic procedures in a hospital-based setting and/or in affiliation with hospitals. While this can provide additional safety for risky procedures, this drives up costs. In fact, this study which promotes TNE for cost savings does not report the anticipated costs. However, in a previous study, the cost of TNE exceeded that of a standard endoscopy (including anesthesia) in an endoscopy center. Though, the cost of TNE was less than a standard hospital-based endoscopy (Related blog post: Transnasal Endoscopy in Unsedated Children to Monitor Eosinophilic Esophagitis).
My take: This technology would be better suited for adults with eosphageal conditions. First of all, most adult GI physicians are not employed by hospitals. Thus, there is a much greater likelihood of cost savings. Secondly, avoiding an additional day missing work is usually a bigger factor for adult patients. However, if there is a need for preauthorization for reimbursement of the procedure, this could negate this potential benefit as well.
Background: “In the general population, individuals with discordant tests (PCR+/TOX−) have similar outcomes to PCR− individuals, suggesting that this group represents individuals colonized with C. difficile.[14]”
Methods: In this retrospective study (n=117), outcomes assessed included CDI-directed therapy or escalation of IBD treatment.
Key findings:
79% (93/117) were PCR+/TOX− and 21% (24/117) were PCR+/TOX+
PCR+/TOX+ patients had significantly higher CRP (98 vs 6 mg/L, P = .005)
PCR+/TOX− patients had more severe underlying IBD and higher rates of steroid use (48% vs 21%, P = .02) and were significantly more likely to require IBD therapy escalation (54% vs 25%, P = .004). Multivariable analysis showed PCR+/TOX− status (odds ratio [OR], 3.2) was a significant predictor of IBD treatment escalation. Antibiotic use did not significantly alter the need for escalation among PCR+/TOX− patients.
Discussion:
“Most IBD patients who are PCR+/TOX− are colonized with C. difficile, and IBD treatment could be considered rather than delaying for CDI therapy.”
My take: In patients with IBD, PCR-positivity for C diff is frequently a false positive due to high rates of colonization in this population. Patients who have their infection confirmed with an immunoassay are much more likely to respond to C diff therapy.
Overdiagnosis of Clostridium difficile with PCR Assays In a large adult study with 293 of 1416 hospitalized adults testing positive for C. diff, virtually all CDI-related complications and deaths occurred in patients with positive toxin immunoassay test results. Patients with a positive molecular test result and a negative toxin immunoassay test result had outcomes that were comparable to patients without C difficile by either method
National Civil Rights Museum in Atlanta, GA. One of the powerful exhibits is a Woolworth lunch counter replica with headphones. With your eyes closed, the exhibit challenges you to keep your hands on the counter as one receives menacing threats like ‘Boy, I’m going to kill you.’