Methods: N=85. Liver stiffness measurement (LSM), by vibration-controlled transient elastography and noninvasive fibrosis scores (Firbosis-4, aspartate aminotransferase-platelet ratio index), were obtained before and 12 months after eradication with ledipasvir-sofosbuvir.
Key findings:
Overall, median baseline LSM was 5.8 (IQR, 4.2-6.5) and at follow-up 5.1 kPa (IQR, 4-6 kPa) (P = .045)
16 patients (19%) experienced regression, and 46 (54%) nonprogression of LSM
The median baseline FIB-4 and aspartate aminotransferase-platelet ratio index scores were 0.34 (IQR, 0.22-0.47) and 0.35 (0.24-0.57), and at follow-up 0.3 (IQR, 0.22-0.34) and 0.2 (0.18-2.8) (P < .001, <.001), respectively
Limitations: In Egypt, HCV genotype 4 is predominant; thus, findings could be different with other HCV genotypes. In addition, the ‘gold’ standard in assessing fibrosis remains a liver biopsy.
In many liver conditions, effective therapy has been associated with histologic improvement/regression. So, while the findings in this study are expected, it is still nice to see more evidence of this outcome.
My take: This study supports the notion that elimination of HCV is associated with either regression or non-progression of liver fibrosis. Treatment prior to extensive liver damage is likely both effective and cost-effective.
This retrospective study had 235 patients (median age 38 years). 90% had endoscopy at a median of 2 days from admission. Key findings:
155 of the 235 patients (66.0%) responded to steroids
78.1% (25 of 32) of patients with concurrent CRP ≥50 mg/L, albumin ≤30 g/L, and increased endoscopic severity (severe on physician’s global assessment) (maximum score = 3) did not respond to IV steroids (positive predictive value [PPV] 78.1%, negative predictive value [NPV] 87.1%).
Comparison with Truelove and Witts Score: 56 of 119 (47.1%) of those classed TWS severe did not respond to steroids. Previously TWS score of acute severe ulcerative colitis (ASUC), defined by at least 6 bloody stools per day plus at least 1 marker of systemic disturbance has been associated with a 19% risk of colectomy during admission.
My take: In patients with ulcerative colitis who present with low albumin and high CRP values, early escalation of medical therapy is highly likely; don’t forget to check a PPD or quantiferon Gold assay early on.
Dr. Joseph D. Feuerstein, gastroenterologist at Beth Israel Deaconess Medical Center in Boston… “It’s rising in incidence and prevalence throughout the world,” he said, and gastroenterologists are still trying to figure out why it shows up when it does in different people.
Crohn’s disease was first described in 1932 by Dr. Burrill B. Crohn…
Prompt diagnosis and appropriate therapy to suppress inflammation in the digestive tract are extremely important because a delay can result in scar tissue and strictures that are not reversed by medication…
Crohn’s is not curable and most patients have to stay on medication indefinitely. That can create yet another stumbling block. The biologics are very costly…
The authors hypothesized that the presence of gastroparesis would be associated with increased severity of symptoms in children with dyspepsia. They defined gastroparesis as having at least 10% retention of standardized radiolabeled meal after 4 hrs(2 eggs, 2 pieces of toast, strawberry jam, and 120 mL of water).
Key findings:
Bloating was the only symptom significantly worse in youth with gastroparesis (n=52, 50%); other symptoms that were compared included nausea, satiety, chest burning, pain and fullness.
In those with gastroparesis, only nausea correlated with retention (4 hours.; rs = 0.275, P < .05).
Girls with gastroparesis had significantly worse symptoms (except satiety) when compared with boys with gastroparesis (P < .05).
Key limitation: there are no established normative data in children; data extrapolated from adults suggest having >60% retention at 2 hours and >10% at 4 hours is abnormal; the latter is supported by a large retrospective pediatric study (n=1041, Ng et al. Am J Gastroenterol 2020; 115: 1830-9)
Comment:
In clinical practice, a GES rarely helps with clinical management. Prokinetic agents have limited effectiveness and may be used regardless of a GES result. Even in those with abnormal values, the effects of recent infections and malnutrition could contribute to an abnormal study.
My take: It is a little surprising that symptom severity was similar between children with and without abnormal GES. Given the limited clinical impact, most GES studies have limited value.
“Red Man” syndrome “calls up historical narratives that endorse and reinforce discrimination against Native American and Indigenous peoples”
Vancomycin infusion reactions are more readily documented in white males than in females and black patients. The combination of rash, itching, flushing and hives may be less apparent in some groups and/or mistaken as a true allergy.
“We recommend using the term “infusion reaction” for all non-immune-mediated drug reactions”
My take: I agree with the authors that the term “red man syndrome” should be dropped. It is both an insensitive term and also hinders appropriate diagnosis of vancomycin infusion reactions.
A recent political cartoon by Mike Lukovich had a caption/commentary on U.S. troops leaving Afghanistan: “Our times up here. We are being redeployed to a war zone.”
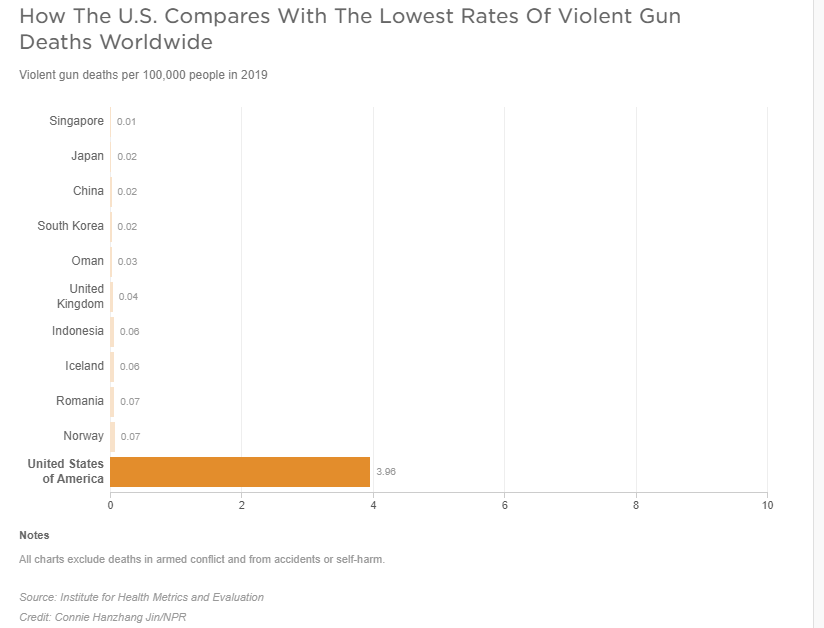
No Exaggeration: Too Many Children Are Dying in the U.S. “The sad fact is that a child or adolescent in the United States is 57% more likely to die by the age of 19 years than those in other wealthy nations.” This is due mainly to more deaths from MVAs and from gun violence.
A recent study by the APPETITE (Alberta Provincial Pediatric EnTeric Infection TEam) describes the frequency of abdominal pain with acute gastroenteritis (AGE).
This was a prospective cohort study with 2136 patients (median age 21 months) who were recruited from 2 pediatric EDs
Key findings:
In the 24 hours before enrollment, most caregivers reported moderate (28.6% [610/2136, 95% CI 26.7-30.5]) or severe (46.2% [986/2136, CI 44.0-48.3]) pain for their child.
In the ED, they reported moderate (31.1% [664/2136, 95% CI 29.1-33.1]) or severe ([26.7% [571/2136, 95% CI 24.9-28.7]) pain; analgesia was provided to 21.2% (452/2131). The most common analgesics used in the ED were acetaminophen and ibuprofen.
In their discussion, the authors note the need for research on the development of effective, safe, and timely pain management plans. In my view, all gut pain, especially in those with chronic conditions, needs more effective treatments.
My take: This is an interesting study as very little has been published about AGE and abdominal pain. The study’s conclusions are limited by the age of the participants.
In his book, Critical path, Buckminster Fuller (Fuller 1981), American architect, systems theorist, author, designer, inventor, and futurist, created the ‘knowledge doubling curve’. He noticed that until 1900 human knowledge doubled approximately every century and by the end of World War II knowledge was doubling every 25 years (Knowledge is not everything, Paul Chamberlain). Now the doubling of knowledge, in the age of the internet and social media, has become even shorter, perhaps less than a year.
I was thinking about this knowledge doubling curve after reading two practice guidances in a recent issue of Hepatology:
The first guidance is mainly for reference as pediatric gastroenterologists do not focus on reproductive health. The authors do provide guidance on contraceptive options which is an important topic for adolescents. The main guidance is disease-specific information for pregnancy in the setting of underlying liver conditions including liver transplantation, cirrhosis, viral hepatitis, autoimmune hepatitis, PSC, PBC, Wilson’s disease, hepatitis C, nonalcoholic fatty liver disease, HELLP, acute fatty liver disease of pregnancy, Budd-Chiari, FNH, hepatocellular adenoma, and others. The guidance also provides recommendations for how to evaluate abnormal liver tests in pregnancy and reviews liver medications during pregnancy (Table 4).
The second guidance reviews the following:
An overview of the current understanding of bleeding and thrombosis in cirrhosis.
An evidence‐based justification for bleeding risk assessment in patients with cirrhosis before invasive procedures, including current concepts in preprocedural testing and laboratory analysis and their role in predicting bleeding complications.
An outline of established and recently identified risk factors for venous thrombosis in the portal and hepatic venous systems in both patients with and without cirrhosis along with thrombophilia testing recommendations.
A review of the strengths and weaknesses of the various classification systems for portal vein thrombosis and a proposal for standard nomenclature regarding characterization of portal vein thrombosis location, time course, and progression.
Useful points:
In patients with cirrhosis, there are “complex hemostatic changes that are not adequately captured by traditional laboratory measures of hemostasis, such as PT, aPTT, and platelet count.”
“Because of conflicting data in the literature, there is no data-driven specific INR or platelet cut-off in which procedural bleeding risk is reliable increased.” In some studies, the authors conclude that “that the low platelet count may have been merely a reflection of advanced portal hypertension and not a causative risk factor for bleeding.”
For Platelets in the setting of cirrhosis: “Given the low risk of bleeding of many common procedures, potential risks of platelet transfusion, lack of evidence that elevating the platelet count reduces bleeding risk, and ability to use effective interventions, including transfusion and hemostasis if bleeding occurs, it is reasonable to perform both low‐ and high‐risk procedures without prophylactically correcting the platelet count...An individualized approach to patients with severe thrombocytopenia before procedures is recommended because of the lack of definitive evidence for safety and efficacy of interventions intended to increase platelet counts in patients with cirrhosis.” The authors note in Table 4, that the AASLD does not have a specific threshold for platelets, whereas other societies have used values of >30 or >50.
For INR in setting of cirrhosis: “The INR should not be used to gauge procedural bleeding risk in patients with cirrhosis who are not taking vitamin K antagonists (VKAs)…Measures aimed at reducing the INR are not recommended before procedures in patients with cirrhosis who are not taking VKAs…FFP transfusion before procedures is associated with risks and no proven benefits.”
The guidance lists a step‐by‐step treatment and surveillance algorithm for portal vein thrombosis in patients with cirrhosis (and without cirrhosis).
The guidance provides updated diagnostic, treatment, and management recommendations for sinusoidal obstruction syndrome (formerly known as hepatic-veno-occlusive disease), hereditary hemorrhagic telangiectasia, and hepatic vein thrombosis (aka Budd-Chiari).
Classification and management recommendations for idiopathic noncirrhotic portal hypertension and the portosinusoidal vascular disorders.
Surveillance and evaluation recommendations for hepatic and splenic artery aneurysms.
A review of the management issues in vascular liver disorders specific to children and guidance on early intervention in extrahepatic portal vein obstruction in children.
My take: In essence, these two articles are condensed textbooks. The first on Liver Disease, Pregnancy and Reproductive Health. And the second on Bleeding in the Setting of Chronic Liver Disease and Vascular Liver Diseases.
This study prospectively assessed for mucosal healing by endoscopy 3 to 5 months after clinical remission, PUCAI <10, was documented. Key findings:
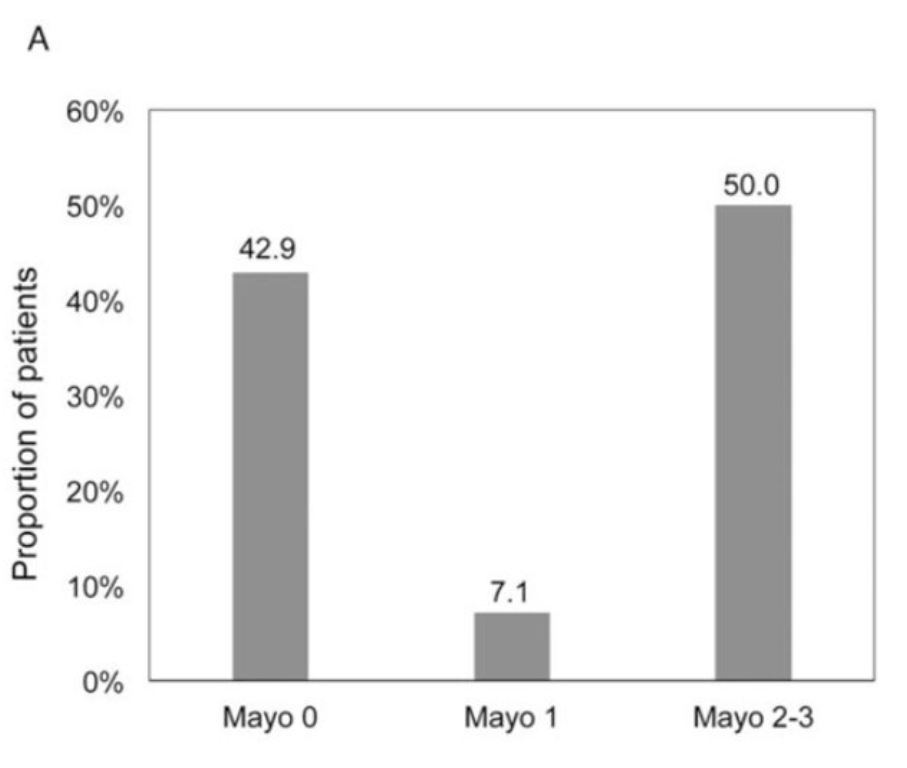
28 children in continuous clinical remission at time of sigmoidoscopy were included. Mayo 0 was present in 12/28 (43%), Mayo 1 in 2/28 (7%) and Mayo 2 to 3 in 14/28 (50%) endoscopies.
Among 23 patients with follow-up through 18 months, remission was sustained in 6/12 (50%) with Mayo score 0 to 1 versus 2/11 (18%) of patients with Mayo 2 and 3
16 (57%) of the patients were receiving 5-ASA treatment
It would have been helpful to have calprotectin values as well. In their discussion, the authors note that “a normal calprotectin is quite convincing with regard to endoscopic remission” and ECCO ESPGHAN guidelines “provide guidance that a colonoscopy should only be performed if fecal calprotectin” is >250 mcg/g.
My take: Clinical remission in ulcerative colitis should be verified. It is reasonable to start with a fecal calprotectin and if elevated to proceed with endoscopic evaluation (colonoscopy or sigmoidoscopy).
Also: new therapy for Crohn’s disease with favorable phase III study. From Pharmacy Times: Risankizumab (Skyrizi) Demonstrates Significant Improvements In Patients with Crohn Disease Two studies, ADVANCE and MOTIVATE showed similar results for Crohn’s disease. In the ADVANCE study: “40% of patients receiving 600 mg, and 32% of patients receiving 1200 mg achieved endoscopic response at week 12, compared to 12% in the placebo group.” In the MOTIVATE study, “29% and 34% of patients receiving 600 mg and 1200 mg achieved endoscopic response, respectively, compared to 11% in the placebo group.”