Increasing Prevalence of Steatotic Liver Disease in Adolescents

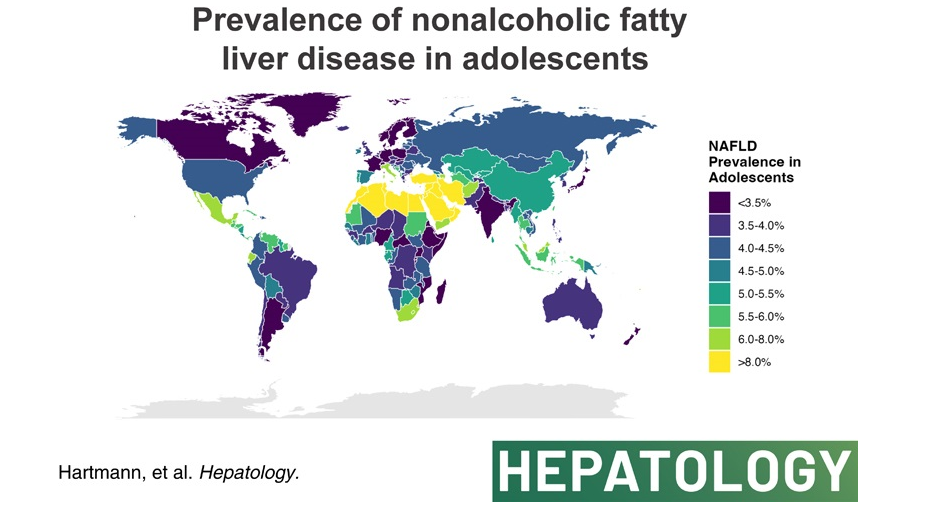
P Hartmann et al. Hepatology 2023; 78: 1168-1181. Open Access! Global and national prevalence of nonalcoholic fatty liver disease in adolescents: An analysis of the global burden of disease study 2019

The authors  analyzed data from the Global Burden of Disease Study 2019 to compare global, continental, and national prevalence rates of adolescent (15-19 yrs of age) NAFLD.

Key finding:

  • The global NAFLD prevalence in adolescents increased from 3.73% in 1990 to 4.71% in 2019 (a relative increase of 26.27%). NAFLD is now termed metabolic dysfunction-associated steatotic liver disease (MASLD).
  • High body mass index and not type 2 diabetes mellitus correlated with NAFLD prevalence in adolescents globally. 
In the associated editorial (S Xanthakos, Hepatology 78(4):p 1017-1019, October 2023, Rising tide of NAFLD in youth: A warning bell and call to action), some of the key points:

  • “The Global Burden of Disease (GBD) Study is the most comprehensive and long-standing effort to systematically and scientifically collate data on hundreds of diseases and injuries across the globe, including related clinical outcomes. Beginning in 1990, the GBD Study initially collected data on 106 conditions and 10 risk factors, across 5 age groups.1 Over time, the GBD Study has expanded through serial iterations to involve >9000 international researchers collecting data on 369 diseases and injuries across 204 countries and territories in the most recent 2019 report.1
  • ” From the GBD Study, we learned that NAFLD is the most rapidly rising cause of chronic liver disease in adolescents and adults,2 and the fastest-growing contributor to cirrhosis, liver cancer, and liver-related deaths globally.”
  • “The global prevalence of NAFLD in adolescents shows no sign of abating, rather has continued to increase steadily from 3.7% in 1990 to 4.7% in 2019.”
  • “As with all epidemiological research, the GBD study faces the primary limitation of relying on data sources that employ varying and less accurate measures of NAFLD prevalence (alanine aminotransferase and/or ultrasound primarily). However, the rigorous methodological approach employed by the GBD including frequent assessment of face validity, and the tremendous input of data sources (>80,000 in 2019) nonetheless results in the most comprehensive global data set available.”

My take (borrowed from editorial): Without intervention, “the increase in adolescent NAFLD certainly portends a future increase in NAFLD-related cirrhosis and liver-related deaths in young adults in the coming decades, and a likely escalation in cardiovascular and diabetes-related morbidity.

Related blog posts:

Treats (Tips) and Tricks for Using IBD Drugs in Patients with Hepatobiliary Comorbidities

S Massironi et al. Inflamm Bowel Dis 2023; 29: 1477-1487. Use of IBD Drugs in Patients With Hepatobiliary Comorbidities: Tips and Tricks

This review article makes a number of useful points:

  • Almost all of the IBD medications (Anti-TNF, Vedolizumab, Ustekinumab, Tofacitinib, Ozanimod) should not be used in patients with untreated hepatitis B surface antigen positivity. Antiviral prophylaxis is recommended even patients with inactive disease (HBV DNA <2000 IU/mL/normal ALT) starting 2 weeks prior to immunosuppression up to 12 weeks after immunosuppression discontinuation.
  • Anti-TNF, Vedolizumab, and Ustekinumab can be safely used in patients with cirrhosis, tofacitinib requires a dose reduction, and ozanimod is NOT recommended
  • Autoimmune hepatitis may be triggered (rarely) by use of anti-TNFs; however, these agents have been uses off-label as a rescue therapy for AIH as well.
  • Anti-TNFs do not appear worsen liver function in PSC and may be associated with improvement in MASH (NASH)
  • Drug-induced liver injury (DILI) is common with anti-TNFs, often seen between the second and fifth doses. It is “generally transient and asymptomatic.” DILI may occur with ustekinumab, tofacitinib and ozanimod.
  • Tofacitinib may have a favorable effect on PSC. A retrospective study with 5 patients reported a 28% and 39% decrease respectively in total bilirubin and alkaline phosphatase within 6 months of starting therapy, A separate study with 42 patients showed a non-significant drop in alkaline phosphatase from 150 U/L to 132 U/L at 12 month followup.
  • The authors note that in patients with cirrhosis and posttransplantation, “vedolizumab and ustekinumab should be preferred due to their safer profile linked to infectious risk.”
  • “Patients with hepatobiliary disorders are often excluded from pivotal trials.” This contributes to a significant knowledge gap for patients with these comorbid conditions which are frequent in patients with IBD

My take: I don’t think I will be too popular if I hand out copies of this article to the kids I see later today –despite the useful advice. (This post was meant to be published on Halloween)

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Rapid Genetic Testing in Liver Failure

D Bonser et al. J Pediatr 2023; 260: 113534. Rapid Genome Sequencing Diagnosis in Pediatric Patients with Liver Dysfunction

In this retrospective study with 18 pediatric patients (2019-2021) who presented with pediatric acute liver dysfunction, the authors examined the yield of rapid whole genome sequencing (rWGS). Key findings:

  • Median turnaround was 8 days. In patients with a diagnostic study, an initial report was received in a median of 4 days compared to 10 days with a non-diagnostic study.
  • 7 patients (39%) had diagnostic results including two with ornithine transcarbamylase deficiency, one with Wilson’s disease, one with PFIC type 1, one with infantile liver failure syndrome 2 (due to NBAS gene), one with GSD type 4, and one with infantile liver failure syndrome 1 (due to LARS gene).
  • Five of these patients with abnormal rWGS had liver transplantation evaluation/listing after the test results were received

One annoying aspect of the report is the authors’ attempt to suggest that the diagnostic yield should have been higher if they excluded four patients subsequently thought to have liver dysfunction due to environmental exposures. In a retrospective study, it is easy to second-guess and say that the test could have been used more selectively.

My take: This study shows that rapid whole genome sequencing is a very valuable part of the evaluation of children with severe liver dysfunction. Turnaround times have improved considerably.

Related blog posts

Villefranche-Sur-Mer, France
Cassis, France
Cassis, France

Customized Postoperative Therapy for Biliary Atresia -Does It Help?

S Pandurangi et al. J Pediatr Surg 2023; 58: 1483-1488. Customized Postoperative Therapy Improves Bile Drainage in Biliary Atresia: A Single Center Preliminary Report

This single center retrospective study compared  20 consecutive infants underwent hepatoportoenterostomy (HPE) (beginning in 2017) for biliary atresia (BA) to a historical cohort. Analysis of successful biliary drainage 3 months after HPE (defined as serum total bilirubin (TB) <2 mg/dL) was the primary endpoint; survival with native liver at 2 years was the secondary endpoint.

Protocol:

  • Cefoxitin was administered to all infants following HPE for 3-4 days.
  • Standard protocol: If the stool color normalized (pigmented), the infant received “conventional” treatment with trimethoprim-sulfamethoxazole cholangitis prophylaxis, fat-soluble vitamin supplementation with DEKAsPlus or AquaADEKs (1 mL daily), and ursodeoxycholic acid (5 mg/kg twice daily).
  • Customized protocol: If the stools were acholic (or not consistently pigmented) and </=45 days, the infants received intravenous cefoxitin or piperacillin-tazobactam and methylprednisolone, initial dose 5 mg/kg/day and decreased by 1 mg/kg/day each day thru day 5; then orally treated with dose dropped 0.25 mg/kg weekly. When switched to oral steroids, IV antibiotics were stopped and infant was placed on amoxicillin-clavulanate which was continued until TB <2 mg/dL or discontinuation of corticosteroids (whichever came first).
  • If stools were acholic and infant was >45 days, then the same treatment was given if there was liver inflammation on histology.

Key findings:

  • 8 had pigmented stools after HPE and received standard protocol.
  • 12 had acholic/inconsistent stools. All of those >45 days had liver inflammation; thus, all 12 received the customized protocol. Two infants had two cycles of steroids/antibiotics who had initial response to treatment and then worsened.
  • Sixteen of 20 (80%) infants had successful bile drainage, compared to 8 of 20 (40%) infants in the historical cohort (P = 0.0225)
  • Among the sixteen who have reached two years of age, 11 (68.8%) are alive with native livers versus 10 of 20 (50%) in the historical cohort (P = 0.0970).  This did not achieve statistical significance.

The authors established their protocol based on data from Kings College in 2016 suggesting that steroids appeared effective in younger patients who underwent HPE prior to 45 days (Peg Surg Int 2016; 32: 193-200). The START study showed no significant improvement in biliary drainage between patients receiving corticosteroids and placebo. However, in the group <70 days, 72% of infants receiving corticosteroids achieved biliary drainage compared with 57% of the placebo group (P=0.36).

My take: This is a small sample size. Perhaps, this protocol will help improve outcomes. If so, we still don’t know which factor is more important —the IV antibiotics or the high dose steroids. If these agents are helpful, are there other predictive factors –microbiome? MMP-&?

Related blog posts:

Pictures from the Villa Ephrussi de Rothschild

Don’t Put the Cart Before the Horse: Biliary Atresia Screening

R Lerer et al. JPGN Reports2023; 4(4):p e345. Open Access! Evaluation of Newborn Direct Bilirubin As Screening for Cholestatic Liver Disease

This retrospective study analyzed data from 11,965 infants who had fractionated bilirubin obtained in the nursery (2016-2019). Key findings:

  • DB of 0.6 mg/dL was chosen as the cut-off based on a high sensitivity (100%) and specificity (99%) for screening newborns for CLD
  • Out of 60 infants who met criteria for DB ≥0.6 mg/dL, only 15 (25%) had a repeat level drawn after nursery discharge; 3 (5%) were eventually diagnosed with CLD (2 with BA and 1 with Alagille syndrome)

It is fairly easy to get fractionated bilirubins on infants. Many need to get a bilirubin check and in many centers, a fractionated bilirubin is automatically generated at no additional costs. The hard part is making sure that those with abnormal values receive timely followup.

My take: It is a mistake to get fractionated bilirubins in newborns unless one has developed a plan/infrastructure to make sure those with abnormal values receive appropriate followup.

Related blog posts:

Off the coast of Southern France (near Juan-Les-Pines)

Pilot Study of Elafibranor in Children with NASH (MASH)

NP Goyal et al. JPGN 2023; 77: 160-165. An Open Label, Randomized, Multicenter Study of Elafibranor in Children With Nonalcoholic Steatohepatitis

Ten males [mean 15.1 years, standard deviation (SD) 2.2] with NASH were randomized to once daily treatment with Elafibranor: 80 mg (n = 5) or 120 mg (n = 5). Elafibranor, a dual peroxisome proliferator-activated receptor α/δ agonist, has been proposed as a treatment for nonalcoholic steatohepatitis (NASH, aka Metabolic dysfunction-associated steatohepatitis (MASH)). Key findings:

  • End of treatment mean ALT was 52 U/L (SD 20) for the 120 mg group, with a relative mean ALT change from baseline of −37.4% (SD 23.8%) at 12 weeks.
  • Elafibranor was rapidly absorbed and well tolerated.

My take: I think we are on the verge of identifying medications which will be able to improve outcomes for those with steatotic liver disease.

Related blog posts:

Rock Jumping -from Cap D;Ail Trail (near Eze, France)

Why Didn’t Screening for Biliary Atresia Improve Outcome In This Study?

ZJ Kastenberg et al J Pediatr 2023; 257: 113339. Fractionated Bilirubin Among 252 892 Utah Newborns with and Without Biliary Atresia: A 15-year Historical Birth Cohort Study

This retrospective study (2005-2019) used an administrative data from a large integrated healthcare network in Utah to identify newborns with abnormal fractionated bilirubins. since 2005, all newborns at this healthcare system had a fractionated bilirubin measured.

Key findings:

  • There were 252 892 newborns with fractionated bilirubin assessed, including 26 of those subsequently confirmed to have biliary atresia (BA).
  • Conjugated or direct bilirubin was elevated in all 26 infants with BA and an additional 3246 newborns (1.3%) without BA. The lowest direct bilirubin in the BA group was 0.6, just above cutoff value of 0.5 mg/dL. The conjugated bilirubin cutoff value wa 0.2 mg/dL.
  • The 15-year crude birth prevalence of BA was 0.68 per 10,000 births in this cohort
  • Median time to Kasai HPE was 69.5 days

This study found that all infants with BA have elevated conjugated or direct bilirubin at birth. The authors estimate that a healthcare system with about 30,000 deliveries per year, would have between 450 and 630 newborns that would require a second screen. In this group, 96 per 100,000 screened newborns (~1 in 1000) will have a positive second screen at 2-week well check and need further evaluation.

What I don’t understand about this paper is how the authors omit a discussion of the age of Kasai HPE. How is it that all of these newborns received a fractionated bilirubin and the age of Kasai HPE is not improved compared to other U.S locations that have not implemented universal testing? (Previous data from 15 ChiLDReN sites indicate age of Kasai HPE 65-70 days and unchanged over past 30 years, see blog post: Online Aspen Webinar (Part 5) -Biliary Atresia Diagnosis and Screening).

The authors note that implementation of screening could be improved with newer tests (eg. MMP-7) but that more analysis is needed to determine if screening is cost-effective and avoids harm (eg. subjecting healthy newborns to invasive testing).

My take: If universal screening is implemented, it is imperative to show that it helps and to set up the needed infrastructure to arrange appropriate followup. The first surrogate marker of this effort would be improving the age of surgical intervention.

As an aside, I find the new page numbering by The Journal of Pediatrics to be quite annoying. When you are going through the hard copy of the Journal, it is more difficult to find the articles that are listed in the table of contents because the articles are not ordered by lowest to highest numbered page. Each article is given a single page number like 113339 in this article but inside the article it is numbered page 1–10 (or however long the pages). The article prior could be a lower or higher page number. Until hard copies are eliminated, it would be an improvement if the articles could at least be ordered such that the next article would not have a lower page reference than the preceding article.

Related blog posts:

Castle Hill Park, Nice France

Be Careful with Biliary Atresia Diagnostic Biomarkers

B Aleiri et al. JPGN 2023; 77: 97-102. Matrix Metalloproteinase-7 and Osteopontin Serum Levels as Biomarkers for Biliary Atresia

In this study, serum was assessed from 32 biliary atresia (BA) patients and 27 controls.

Key findings:

  • Median MMP-7 was higher in BA (96.4 vs 35 ng/mL; P < 0.0001) with an optimal cut-off value of 69 ng/mL. Sensitivity and specificity was 68% and 93%, respectively [negative predictive value (NPV) = 71%]
  • Median osteopontin (OPN) was higher in BA (1952 vs 1457 ng/mL; P = 0.0001) and an optimal cut-off of 1611 ng/mL. Sensitivity and specificity was 84% and 78%, respectively (NPV = 81%)

The authors note that numerous studies from Asian countries have shown very high sensitivity and specificity for MMP-7. These studies used different cut-offs based on the testing kit. One limitation of this study was that samples were stored for a median of 12 years and perhaps this affected the results (some prior studies also used banked specimens).

My take: When these levels are very elevated, they are highly suggestive of BA. This study serves as a caution to note that the sensitivity at typical cut off values could be suboptimal

Related blog posts:

Le Jardin Exotique in Eze, France

Prevalence of Elevated ALT in U.S. Adolescents

AK Mischel et al. JPGN 2023; 77: 103-109. Prevalence of Elevated ALT in Adolescents in the US 2011–2018

Using NHANES data for 12-19 year olds, the authors examined rates of elevated ALT. Elevated ALT was defined as >22 U/L (females) and >26 U/L (males)  Key findings:

  • Prevalence of elevated ALT in adolescents was 16.5% overall and 39.5% among those with obesity
  • For White (W), Hispanic (H), and Asian (A) adolescents, prevalence of elevated ALT was 15.8%, 21.8%, and 16.5% overall. In overweight adolescents, 12.8% (W), 17.7% (H), and 27.0% (A), and in those with obesity, 43.0% (W), 43.5% (H), and 43.1% (A) in those with obesity, respectively
  • Prevalence was much lower in Black adolescents (10.7% overall, 8.4% for overweight, 20.7% for obesity)
  • Prevalence of ALT at 2X-ULN was 6.6% in adolescents with obesity
  • Hispanic ethnicity, age, male sex, and higher BMI were independent predictors of elevated ALT

My take: It is hard to get very excited about a mildly elevated ALT value when 1 in 6 adolescents has this as well as ~40% of adolescents with obesity.

Related blog posts:

Bougainvillea in Eze, France
View from Cap d’Ail Trail (near Eze, France)

Costs and Opportunity Costs in Pediatric Liver Transplantation

GV Mazariegos et al. Liver Transplantation 2023; 29: 671-682. Open access! Center use of technical variant grafts varies widely and impacts pediatric liver transplant waitlist and recipient outcomes in the United States

Background: Waitlist (WL) mortality is highest in children under the age of 1 year (12.5 deaths/100 WL years).2 It is thought that TVG (technical variant grafts) [including living donor (LD) and deceased donor split/partial grafts] improve outcomes.

Methods: The authors, in this retrospective study, analyzed Organ Procurement and Transplantation Network (OPTN) data on first-time LT or liver-kidney pediatric candidates listed at centers that performed >10 LTs during the study period, 2004–2020. 

Key findings:

  • Sixty-four centers performed 7842 LTs; 657 children died on the WL
  • Death from listing was significantly lower with increased center TVG usage (HR = 0.611) and LT volume (HR = 0.995)
  • Recipients of LD transplants (HR = 0.637) had significantly increased survival from transplant compared with other graft types, and recipients of deceased donor TVGs (HR = 1.066) had statistically similar outcomes compared with whole graft recipients

My take (borrowed from authors): “LD partial grafts and overall volume performed by the center in the preceding 3 years was significantly associated with increased post-LT survival. Deceased donor graft type (DD TVG vs. DD Whole) was not a predictor of post-LT survival after accounting for patient diagnosis, center volume, and other significant factors that were predictive of survival. DD TVG should not be considered an inferior graft option in experienced centers…LD grafts are associated with a survival advantage.”

BA Sayed, M Cattral, VL Ng. Liver Transplantation 2023; 29: 663-664. Open access! (editorial) Insufficient use of technical variant grafts: An unfulfilled promise in pediatric liver transplantation Key points:

  • “While outcomes have improved, with current 1- and 5-year patient survival >97% and 94%, respectively, many children continue to die on the waitlist (WL) or are removed because they are too sick.1,2
  • “As expected, these children were younger, smaller, sicker (more status 1 listings), and remained on the WL longer than children who received a transplant during the same time period…These small infants are particularly at risk because of the difficulty of obtaining an appropriately sized-matched graft. Data indicate that this problem can be solved largely by increasing the use of technical variant grafts (TVGs), which includes living donor (LD) grafts and split/reduced grafts from deceased donors (DDs).4,5
  • “This manuscript obliquely touches on another pressing issue within the pediatric LT community, namely, the core skill set of a pediatric LT surgeon. Currently, there is no such distinct designation in the North American training environment, and therefore, no training requirements exist. To provide the full spectrum of surgical care, the technical skill set should include LD hepatectomies and graft implantations, DD graft reduction/splitting, the reduction or hyper-reduction of left lateral segment grafts, and staged abdominal closure.”

My take: Where a patient is listed is a very important variable in outcomes. Choosing a low volume center without availability to perform TVG increases the risk of lethal outcomes. This information should be disclosed to families at all centers.

Also: T Miloh et al. Liver Transplantation 2023; 29: 735-744. Open access! Costs of pediatric liver transplantation among commercially insured and Medicaid-insured patients with cholestasis in the US

Health care resource utilization and costs associated with pediatric LT were retrospectively assessed using insurance claims data from the US IBM MarketScan Commercial and Medicaid databases collected between October 2015 and December 2019. Study cohort: 53 commercially insured and 100 Medicaid-insured children

  • Key findings: Commercially insured and Medicaid-insured patients averaged US $512,124 and $211,863 in medical costs and $26,998 and $15,704 in pharmacy costs, respectively

Related blog posts:

Place Massena, Nice France
Le Plongeoir (restaurant) Nice, France










