Selecting Patients with Rectal Prolapse Who May Benefit from Surgery

L Rincon-Cruz et al. JPGN 2023; 77: 603-609. Influence of Initial Treatment Strategy on Outcomes for Children With Rectal Prolapse

In this single-center retrospective cohort, the authors analyzed 67 pediatric patients with rectal prolapse who had surgical evaluation; the median duration of follow-up was nearly 4 years.. Key findings:

  • The resolution rate with surgery as initial management was 79% (n = 11/14). Medical management included stool softeners, avoiding straining, and minimizing time on toilet.
  • The resolution rate was 33% (n = 8/24) with sclerotherapy alone and additional 21% (n = 5/24) resolving after a subsequent surgical procedure
  • Medical management was successful in 100% (n=29) (patients who responded would not need subsequent procedural approach); 27 of these patients were less than 5 years of age.
  • 82% of patients had constipation
  • A psychiatric comorbidity was noted in 24 patients, 19 of whom had either sclerotherapy (n=12) or surgery (n=7).

The authors note that rectal prolapse is often self-limited with reported spontaneous resolution of 60-90%. The treatment algorithm proposed by the authors is for medical management alone if less than 5 years of age. In children older than 5 years, they recommend initial sclerotherapy (with D50W) followed by surgical correction (rectopexy or transanal resection of the prolapsing segment) if not successful after one session.

My take: I have not had to refer a patient for surgical management in more than 25 years of clinical GI practice. However, in patients older than 5 years, surgical approaches (rectopexy or resection of prolapse) may be needed in highly selected patients, like in this study which only included patients seen by surgery (referral bias).

Related blog post: How Commonly Does Cystic Fibrosis Present as Rectal Prolapse?

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.


When Hospitals Look Like The Ritz (But Cost Even More)

The Atlantic, Elisabeth Rosenthal (11/17/23): Hospitals Have Gotten Too Nice

This article starts off discussing a recent trend of how medical problems are often described as a “journey.” However, the main focus is the trend of hospitals developing expensive amenities further adding to huge medical bills.

An excerpt:

So much of being seriously ill has been rebranded in American health care as a kind of adventure…But on these journeys, you don’t get to go anywhere—except maybe the hospital or doctor’s office, which is likely, too, to have bought into the travel concept. In the past two decades, American hospitals have gotten into the business of hotel-like hospitality (illness can be fun!) rather than confine themselves to the business of disease (what a downer). And although the care might stay solid, the focus on luxurious amenities and the fancy new buildings that house them is one of the factors that have helped send costs for patients soaring that much higher, to prices well above those in other developed countries…

In recent years, tight budgets, staffing shortages, and burnout have hit American hospitals. At the same time, many health centers in the U.S.—including the most prestigious ones, and even some community hospitals—have morphed into seven-star hotels…A hospital might now boast about its views, high-thread-count sheets, or food provided by a Michelin-starred chef…

Back in 2008, researchers at the National Bureau of Economic Research estimated that a hospital investing in amenities would increase demand by 38 percent, whereas a similar investment in clinical quality would lead to only a 13 percent increase…

These amenities have a cost, and they are not worth nearly what we’re paying for them as we’re billed for $100,000 joint replacements and $9,000 CT scans. Room charges in many hospitals can exceed $1,000 a night. And “facility fees” for outpatient procedures and even office visits can reach hundreds of dollars, and simply don’t exist elsewhere. A hospital’s function is to diagnose and to heal, at a price that sick people can afford. I dream of a no-frills Target- or Ikea-like hospital for care…

How about focusing on the very basic things that health systems in the U.S. should do, but—in my experience—in many cases do not, like making it easier for patients to schedule appointments? Shortening the now lengthy wait times to see physicians who take insurance plans? Paying for adequate staffing on nights and weekends, so patients don’t linger in bed pointlessly for two days until social workers return on Monday? Or ending those two-day stays in emergency rooms when all inpatient beds are full? 

Related blog posts:

Obidos, Portugal

When is the Right Time to De-escalate Dose of Tofacitinib for Ulcerative Colitis?

A Yu et al. Clin Gastroenterol Hepatol 2023; 21: 3115-3124. Open Access! Real-World Experience With Tofacitinib Dose De-Escalation in Patients With Moderate and Severe Ulcerative Colitis

On May 30, 2018, the US Food and Drug Administration (FDA) expanded the indication of tofacitinib (Xeljanz; Pfizer), an oral Janus kinase (JAK) inhibitor, for the treatment of adults with moderately to severely active ulcerative colitis. However, the optimal dosing remains unclear.

In this “real-world” study by Yu et al, a retrospective review of 162 patients was conducted (2012-2022). 52% continued 10 mg twice daily while 48% underwent dose de-escalation to 5 mg twice daily.  The primary outcome was evidence of UC disease activity–related events: hospitalization/surgery, corticosteroid initiation, tofacitinib dose increase, or therapy switch.

Key findings:

  • Cumulative incidence rates of UC events at 12 months were similar in patients with and without dose de-escalation (56% vs 58%; P = .81)
  • An induction course with 10 mg twice daily for more than 16 weeks was protective of UC events (hazard ratio [HR], 0.37) while ongoing severe disease (Mayo 3) was associated with UC events (HR, 6.41)
  • Twenty-nine percent of patients with UC events had their dose re-escalated to 10 mg twice daily, with only 63% able to recapture clinical response at 12 months

Discussion Points:

  •  “Although the product label recommends dose de-escalation after 8 or 16 weeks, clinical practice is variable in the real-world setting… In this retrospective real-world study of moderate to severe UC patients with almost half undergoing dose de-escalation, we observed that more than half of patients experienced a UC disease activity–related event within 12 months after dose de-escalation, particularly in patients with an induction course of fewer than 16 weeks and active endoscopic disease at 6 months after induction…”
  • ” Although dose de-escalation is preferable for long-term maintenance therapy to reduce the potential lifetime risk of medication-related adverse events [eg. VTE], it must be balanced with sustained remission to prevent short- and long-term disease-related complications.”
  • “In the OCTAVE study which reported higher rates of long-term remission, patients de-escalated only after having shown clinical and endoscopic remission after 52 weeks on tofacitinib 10 mg twice daily”

My take (borrowed from authors):  “Emphasis should be placed on clinical and endoscopic evidence of improvement before consideration of dose de-escalation to ensure the highest probability of treatment success.” This advice, though, may conflict with product labelling which states that “tofacitinib induction with 10 mg twice daily beyond 16 weeks is not recommended; in fact, it is recommended to stop after 16 weeks if adequate response has not been achieved.”

Related blog posts:

Belem Tower, Lisbon

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Increasing Burden of Eosinophilic Esophagitis

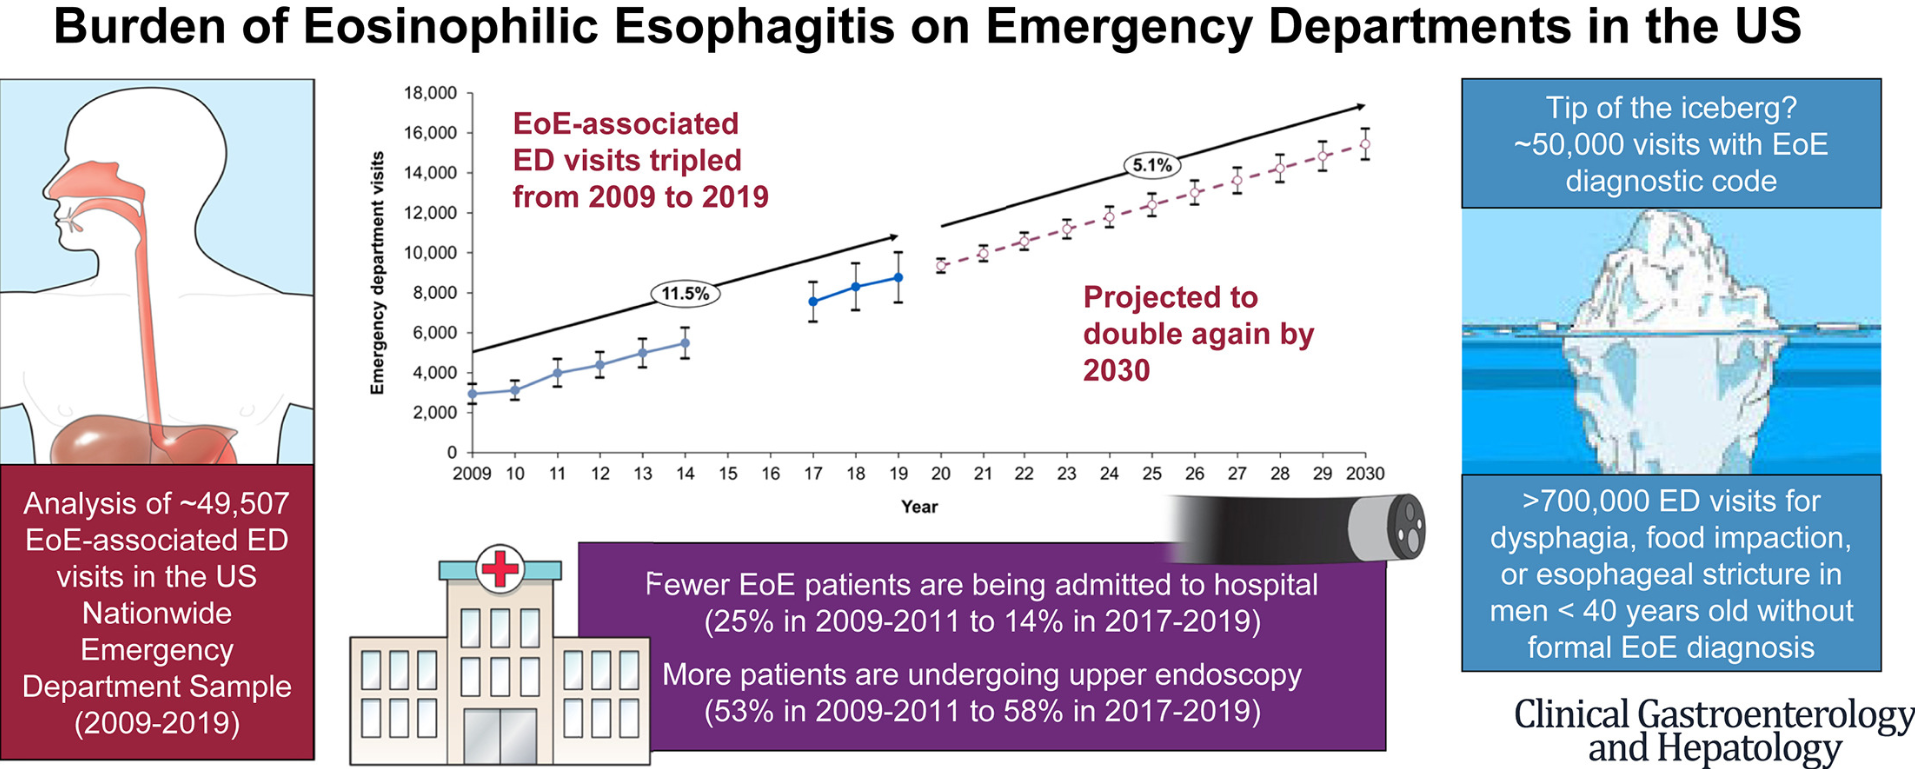
AY Lam et al. Clin Gastroenterol Hepatol 2023; 21: 3041-3050. Open Access (Partial)! Epidemiologic Burden and Projections for Eosinophilic Esophagitis–Associated Emergency Department Visits in the United States: 2009-2030

Methods: Data from the US Nationwide Emergency Department Sample (NEDS) were used to estimate weighted annual EoE-associated ED visits from 2009 to 2019. Autoregressive integrated moving average (ARIMA) models were used to project EoE-associated ED visits to 2030. NEDS is a large, publicly available, all-payer ED database in the United States, approximating a 20% stratified sample of US hospital-based EDs. 

Key points:

  1. There has been a near tripling of the frequency of EoE-associated ED visits over the course of the past decade which is correlated with an increasing prevalence of EoE. The annual volume of EoE-associated ED visits increased from 2934 in 2009 to 8765 in 2019, and is projected to reach 15,445 by 2030.
  2. Without new interventions, this article projects further increases with doubling again by 2030 (using conservative estimates).
  3. Increasingly EoE is being managed without admission, though average charges associated with ED visits for EoE have tripled since 2009. Total mean inflation-adjusted charges for an EoE-associated ED visit were $9025 US dollars in 2019.
  4. Half of EoE patients presenting to the ED required an endoscopy and 40% required a foreign body/food impaction removal.

Related blog posts:

How Reliable is a Motilist in Interpreting Manometry and FLIP Studies?

Correction: Yesterday’s post was updated after an astute observation from one of my colleagues (Jordan) to note that the pictured instrument was in fact a harpsichord rather than a piano. A harpsichord’s sound is derived from plucking a string whereas a piano’s sound comes after a hammer strikes a chord.

——–

JW Chen et al. AJG 2023; 118: 1334-1343. Interrater Reliability of Functional Lumen Imaging Probe Panometry and High-Resolution Manometry for the Assessment of Esophageal Motility Disorders

Thanks to Ben Gold for this reference. Also, congratulations to Jose Garza -our motility specialist and a coauthor of this study.

15 motility specialists completed their interpretation of 40 consecutive HRM (high resolution manometry) and 40 FLIP (functional lumen imaging probe panometry) studies. All were part of a FLIP study group. Key findings:

  • Overall, there were high levels of interrater agreement and accuracy in the interpretation of HRM and FLIP metrics and moderate-to-high levels for motility classification in FLIP
  • There were no FLIP diagnoses of normal EGJ opening in patients with established achalasia and no FLIP diagnoses of achalasia in patients with normal EGJ opening and contractility. This was true with HRM as well.
  • In non-obstructive motor disorders, raters frequently indicated that they would request alternate confirmatory testing before invasive management

My take: This is a reassuring study indicating that with the most consequential esophageal findings, there is excellent agreement among motilist interpretation. Previous studies of colonic manometry, in contrast, have found much lower levels of agreement.

Related blog posts:

Santa Justa Lift (Lisbon)

Alpha-Gal Reaction to Infliximab

G Polanco, et al. JPGN Reports 4(3):p e322, August 2023. Open Access! Delayed Hypersensitivity Reaction to Infliximab Due to Mammalian Meat Allergy

Briefly noted: Case report of a 17 yo with Crohn’s disease who developed urticaria and pruritus approximately 6 hours after her very first infliximab infusion; the patient was diagnosed with Alpha-Gal and responded to change to adalimumab which  is not glycosylated with alpha-gal.

Related blog post: Nonanaphylactic Alpha-Gal and Chronic Gastrointestinal Symptoms

Sigal Music Museum (Greenville, SC) -has a large number of very old harpsichords and pianos. A harpsichord plucks strings to make the sound whereas a piano has a small hammer that strikes the strings to make the sound. This musical instrument is a harpsichord.

Vaping-Induced Esophagitis

L Pace, K McGoogan. JPGN Reports 4(3):p e327, August 2023. Open Access! Vaping Induced Severe Erosive Esophagitis

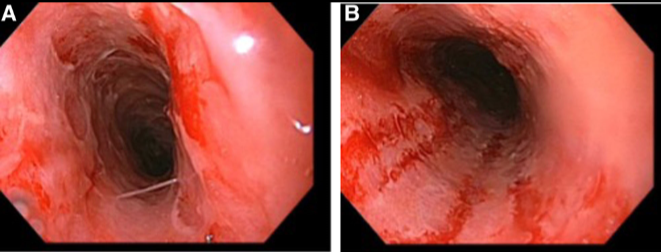
This case report describes a 17 yo with sore throat, odynophagia chest pain, and dysphagia associated with vaping. His symptoms resulted in hospitalization and he underwent an EGD on day 4 after symptoms had not improved with multiple empiric therapies.

EGD findings included .

  1. Circumferential erosive or exudative lesions) esophagitis with bleeding found throughout the entire esophagus. Given the lack of infectious etiologies, the authors made a diagnosis of vaping-associated esophagitis
  2. H pylori gastritis

My take: When adolescent patients present with esophageal symptoms, inquiring about exposure to vaping along with medications known to cause pill-esophagitis, is worthwhile.

Related blog post: Review: Infectious Esophagitis

Aerodigestive Complexity Score

HM Horita et al. J Pediatr 2023; 261: 113549. Open Access! Development of a Medical Complexity Score for Pediatric Aerodigestive Patients

Methods: The authors in this study developed a 7-point medical complexity score .  One point was assigned for each comorbid diagnosis in the following categories: airway anomaly, neurologic, cardiac, respiratory, gastrointestinal, genetic diagnoses, and prematurity. A retrospective chart review was conducted of patients (n=234) seen in the aerodigestive clinic who had ≥2 visits between 2017 and 2021. 

Improvements were followed in the Functional Oral Intake Scale (FOIS)–assigned by aerodigestive feeding therapists.6 The FOIS scale is as follows:

  • •1 = Nothing by mouth
  • •2 = Tube-dependent with minimal attempts of food or liquids (<10%)
  • •3 = Tube-dependent with consistent oral intake of food or liquids
  • •4 = Total oral diet of a single consistency
  • •5 = Total oral diet with multiple consistencies, but requiring special preparations or compensations
  • •6 = Total oral diet with multiple consistencies without special preparation, but with specific food limitations
  • •7 = Total oral diet with no restriction, or <12 months of age on age-appropriate diet

Key findings:

  • At presentation, 69.5% were not at unrestricted age-appropriate diet; 22.7% of the cohort (n = 53) were completely tube dependent
  • There were 165 patients who were not at unrestricted total age-appropriate oral diet at presentation, and the majority (54% [n = 90]) showed improvement in their FOIS scores after aerodigestive team intervention.
  • “For each 1-unit increase in complexity score, there was a 33% decrease in the odds of improvement in FOIS scores (OR, 0.66; 95% CI, 0.51-0.84; P = .001);” however, only neurological comorbidity (OR, 0.26; 95% CI, 0.13-0.53; P < .001) and airway anomaly (OR, 0.35; 95% CI, 0.15-0.79; P = .01) were significantly associated with decreased likelihood to progress in feeding based on FOIS scores
  • Of the 125 patients who were tube fed at initial presentation, 20% (n = 25) were able to achieve full oral feeding after intervention

My take: While the complexity score did correlate with likelihood of progressing with oral feedings, it appears that this score is unnecessary as likelihood of progressing is mainly related to two factors: neurological comorbidities and airway anomalies.

Related blog posts:

Current Approach for FPIES

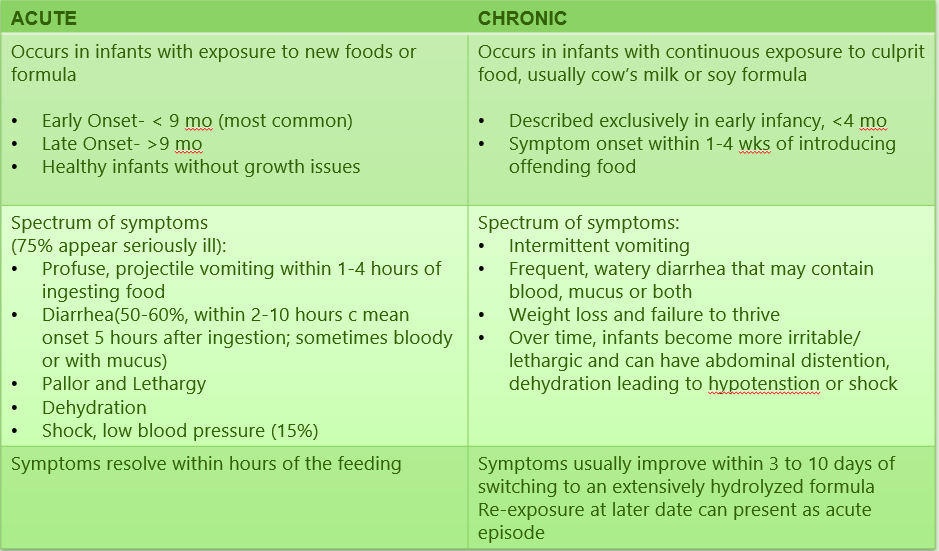
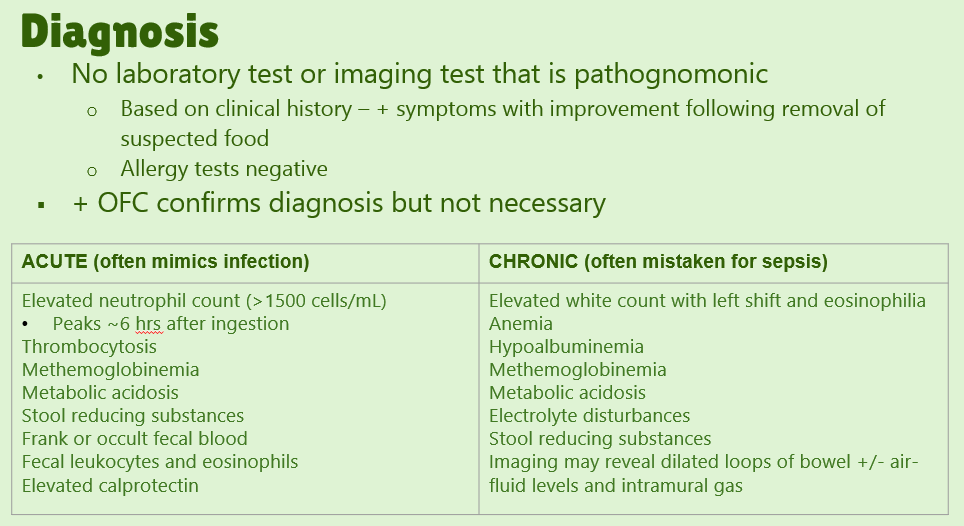
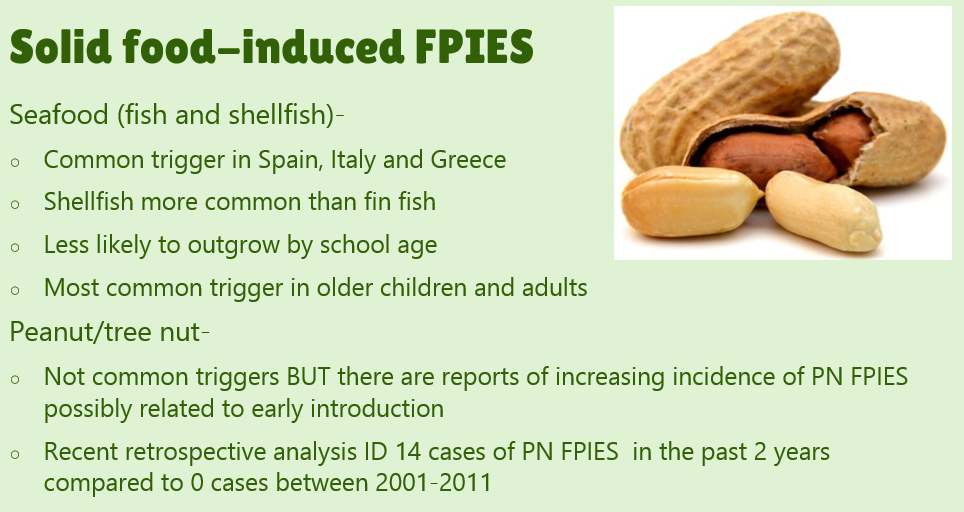
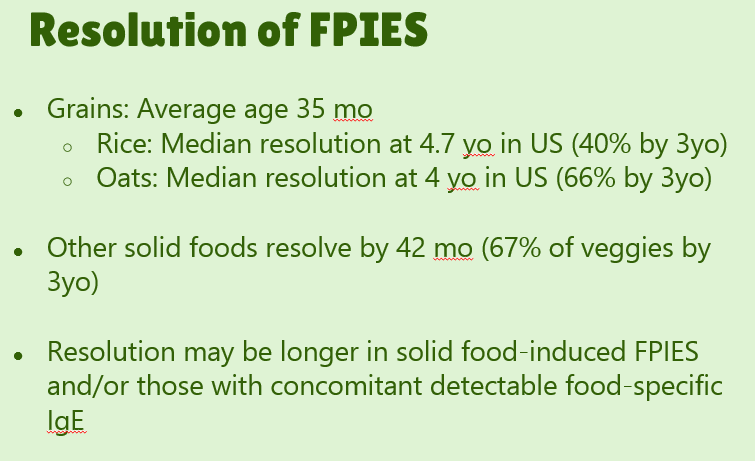
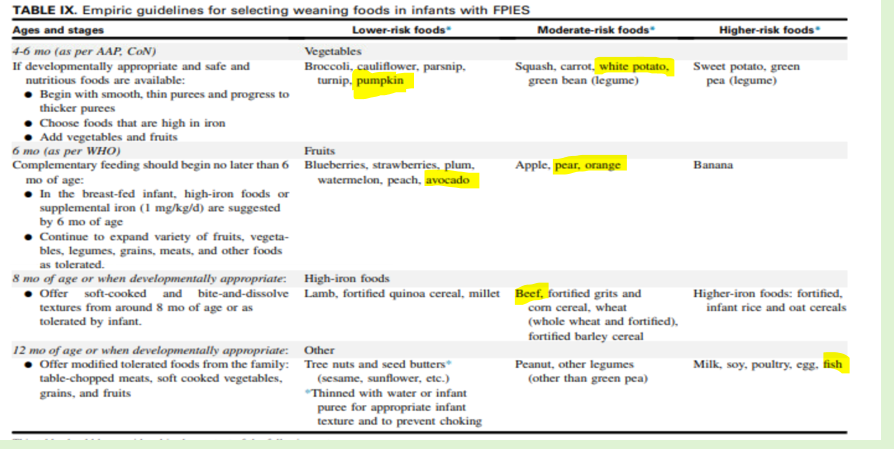
Our excellent nutritionist, Bailey Koch, recently gave our group a terrific update on FPIES. Bailey is part of the medical advisory board for THE FPIES Foundation, as is Dr. Benjamin Gold from our group. Here are many of the slides from her lecture.

Link: FPIES foundation action plan sheet:

From International guidelines:

Nowak-Węgrzyn A, Chehade M, Groetch ME, et al. Open Access: International consensus guidelines for the diagnosis and management of food protein-induced enterocolitis syndrome: Executive summary-Workgroup Report of the Adverse Reactions to Foods Committee, American Academy of Allergy, Asthma & Immunology. J Allergy Clin Immunol. 2017;139:1111-26.

Related blog posts:

From FPIES 2017 Guidelines:

  • #4. “Consider specific IgE testing of children with FPIES to their trigger food because comorbid IgE-mediated sensitization to triggers, such as CM [cow’s milk], can infer a greater chance of persistent disease.
  • ”#8. Conduct food challenges “in patients with suspected FPIES in medically supervised settings in which access to rapid fluid resuscitation is available and prolonged observation can be provided, if necessary.”
  • #14. Do not routinely obtain endoscopic evaluation as part of the evaluation of FPIES.
  • #17. Acute FPIES should be considered a medical emergency. “Approximately 15% of patients can have hypovolemic shock.”
  • #19. Consider ondansetron treatment as an adjunct (if >6 months of age)
  • #21. Do not recommend routine maternal dietary elimination of offending triggers while breast-feeding if the infant is asymptomatic.
  • #23. FPIES can occur to multiple foods.  “The majority of children (65% to 80%) have FPIES to a single food, most commonly CM.”  In one study, 5% to 10% of children reacted to more than 3 foods.
  • #26. Use hypoallergenic formula in infants who can no longer breast-feed and are given a diagnosis of FPIES caused by CM. Most will tolerate extensively hydrolyzed formulas; some may require an amino acid based formula
  • #29. Reviews natural history.  “The age of CM tolerance appears to be around 3 years” but there has been variability in reports. For FPIES due to grains, average age of tolerance is 35 months and other solid foods is 42 months.  The average age for soy is 12 months (later in some studies), for rice 4.7 years and 4.0 years for oats. For CM-FPIES with positive SPT response, a much protracted course has been reported, with older age of tolerance (~13.8 years)

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.