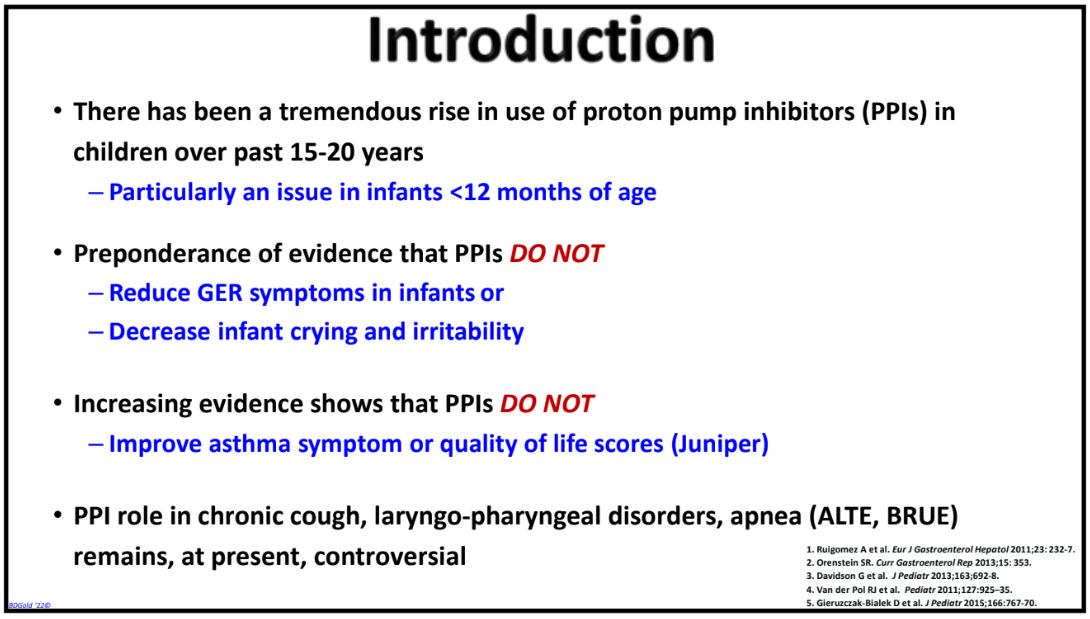
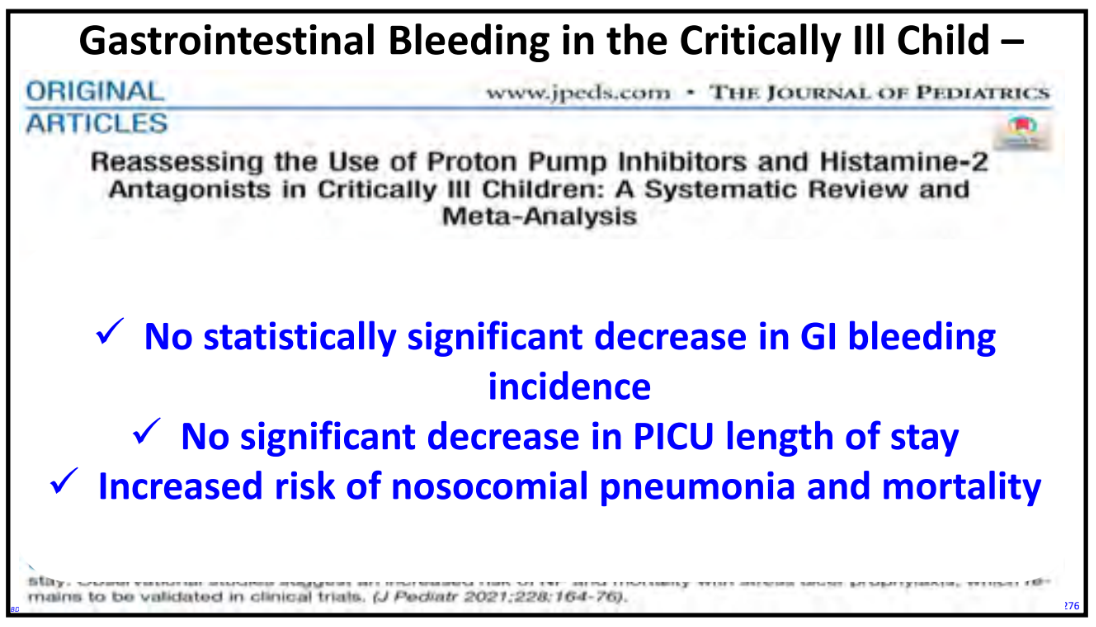
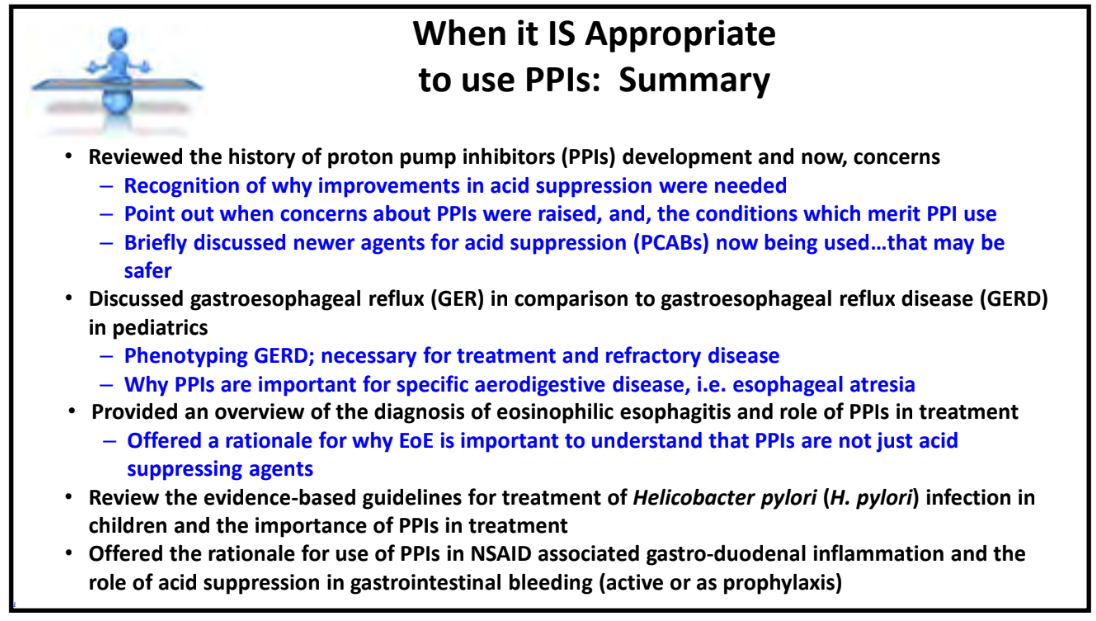
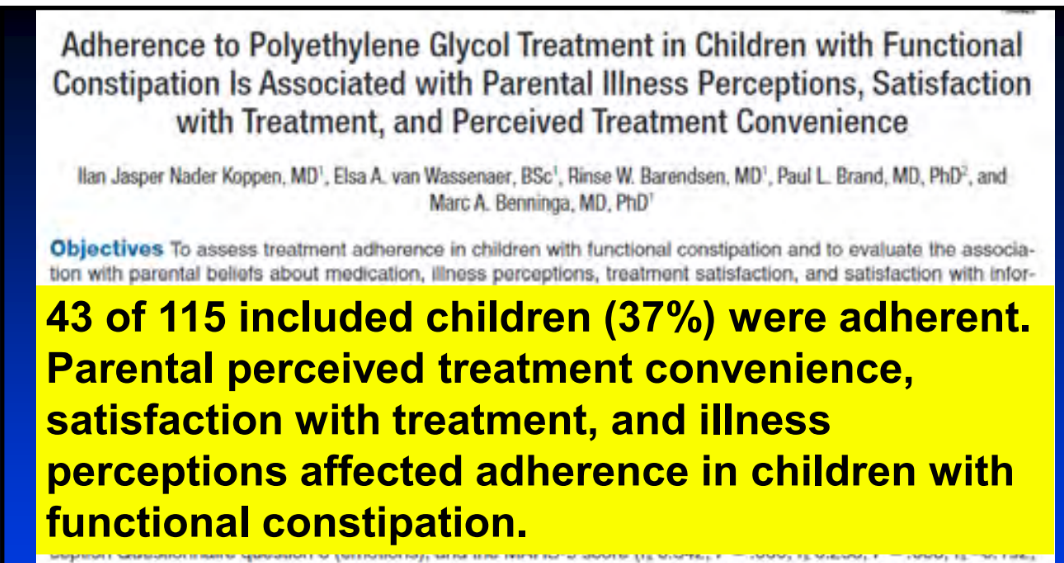
Is Reflux Really a Disease in Premature Infants?

From Atlanta Botanical Garden

Z Sultana et al. Gastro Hep Advances 2022; 1: 869-881: Open Access! Symptom Scores and pH-Impedance: Secondary Analysis of a Randomized Controlled Trial in Infants Treated for Gastroesophageal Reflux

In the introduction, the authors note: “Gastroesophageal reflux (GER) is a physiological process defined as the passage of gastric contents into the esophagus with or without regurgitation and vomiting, while GER disease (GERD) is pathophysiologic and occurs when GER is associated with troublesome symptoms and/or complications.”

“This distinction between GER and GERD remains enigmatic among survivors in the neonatal intensive care unit (NICU). Reflux-type symptoms (arching, irritability, acute life-threatening events, coughing, failure to thrive, and swallowing difficulties) in this high-risk infant population can be troublesome to the parent and provider, and empiric management using pharmacological and dietary changes are common albeit with consequences.”

Methods: “Infant Gastroesophageal Reflux Questionnaire Revised (I-GERQ-R) and 24-hour pH-impedance data were analyzed from 94 infants…[and] Longitudinal data from 40 infants that received randomized GER therapy (proton pump inhibitor [PPI] with or without feeding modifications) for 4 weeks followed by 1-week washout were analyzed. Relationships between I-GERQ-R and pH-impedance metrics (acid reflux index, acid and bolus GER events, distal baseline impedance, and symptoms) were examined and effects of treatments compared.”

Key findings:

  • Acid-suppressive therapy with feeding modifications had no effect on symptom scores or pH-impedance metrics. Clearance of refluxate worsened despite PPI therapy.
  • Correlations between I-GERQ-R and pH-impedance metrics were weak or non-existent, indicating that physicians cannot depend only on the questionnaire to diagnose and treat GERD in premature infants.

My take: This study shows that reflux symptoms are unreliable in establishing a diagnosis of reflux disease in infants. In addition, medical treatments were not beneficial in infants with abnormal pH-impedance metrics. Perhaps, it is time to acknowledge that we cannot even agree what reflux “disease” is in (premature) infants.

Related blog posts:

Terrain in Denali National Park, AK

Newsflash Articles: Untreated Eosinophilic Esophagitis Worsens and the Severely-Damaged Esophagus Does Not Work Well

NC Chang et al. Clin Gastroentol Hepatol 2022; 20: 1701-1708. Open Access! A Gap in Care Leads to Progression of Fibrosis in Eosinophilic Esophagitis Patients

In this retrospective review with 701 patients, 95 (14%) had a gap in care (mean time without care, 4.8 ± 2.3 years). Key findings:

  • Patients post-gap had higher endoscopic severity (2.4 vs 1.5; P < .001) and smaller esophageal diameters (11.0 vs 12.7 mm; P = .04).
  • Strictures were more prevalent with longer gap time (P < .05 for trend). Each additional year of gap time increased odds of stricture by 26%, even after accounting for pre-gap dilation. Additionally, of 67 patients without pre-gap fibrosis, 25 (37%) had at least one fibrotic feature (stricture, narrowing, or requiring dilation) post-gap.

DA Carlson et al. Clin Gastroenterol Hepatol 2022; 20: 1719-1728. Esophageal Dysmotility Is Associated With Disease Severity in Eosinophilic Esophagitis

Consecutive adult patients with EoE (n=199) completed a 16-cm functional luminal imaging probe (FLIP) during endoscopy were evaluated in a cross-sectional study. Key findings:

  • Mucosal eosinophil density was similar between abnormal contractile responses (CRs) and normal CRs (median 34 vs 25)
  • Abnormal CRs more frequently had reduced esophageal distensibility (distensibility plateau <17 mm in 56% vs 32%), with more severe ring scores, and a greater duration of symptoms (median, 10 y vs 7 y)

Thus, abnormal esophageal CRs were related to EoE disease severity, especially features of fibrostenosis. This study suggests that esophageal wall remodeling, rather than eosinophilic inflammatory intensity, was associated with esophageal dysmotility in EoE.

My take: Despite my satirical title, I think these articles are helpful by documenting that ongoing EoE results in worsening esophageal dysfunction/dysmotility (especially if not treated). In addition, they provide insight into the natural history/pathophysiology of EoE.

Related blog posts:

Near Seward, AK. Sea lions and birds flock to this island

IBD Updates: Built-in Infliximab Dosing, Pouchitis in kids, PIBD Symposium & Aspen Meeting

Heads up! Next year’s Aspen Pediatric GI Meeting will be July 10-14 -terrific learning experience and opportunity to mingle with some exceptional leaders in our field:

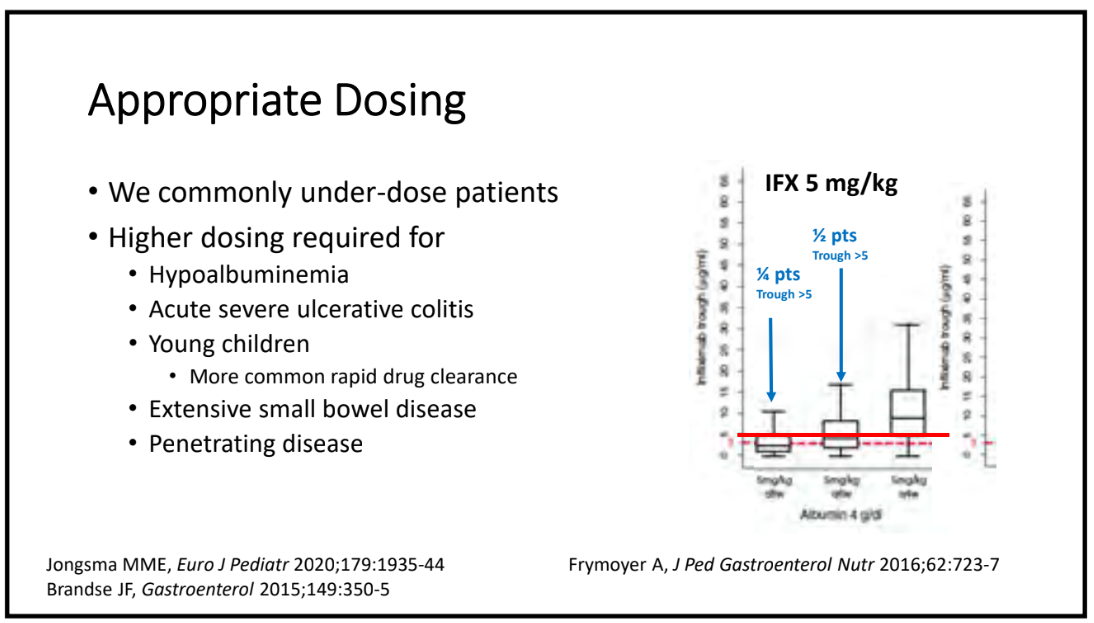
MC Dubinsky et al. Inflamm Bowel Dis 2022; 28: 1375-1385. Dashboard-Driven Accelerated Infliximab Induction Dosing Increases Infliximab Durability and Reduces Immunogenicity

In this prospective ‘real-world’ study (adults and children), “cumulative data from each infusion (INF), weight, albumin, C-reactive protein, IFX dose, IFX trough level, and antidrug antibody presence were used to inform subsequent INF dosing.” Key findings:

  • 69% of patients (n=180) required accelerated dosing by the 4th infusion dose. In addition, median dosing intervals were accelerated by ~2 weeks for the 3rd infusion and ~4 weeks for the 4th infusion
  • The authors report only 6% did not receive a 4th infusion. This early treatment failure rate is much lower than prior studies.
  • 123 of 180 remained on infliximab at week 52 (~32% failure rate); however, this rate is overestimated as there were 26 patients who were not considered failures but were changed to home infusions, moved or lost to followup.

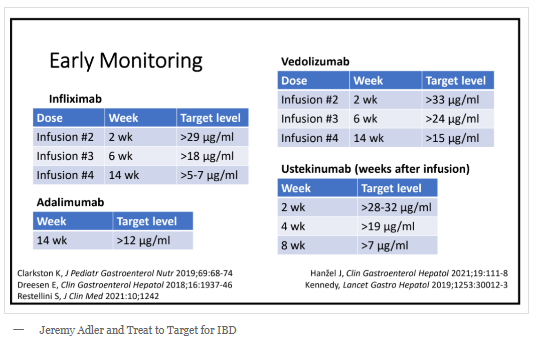
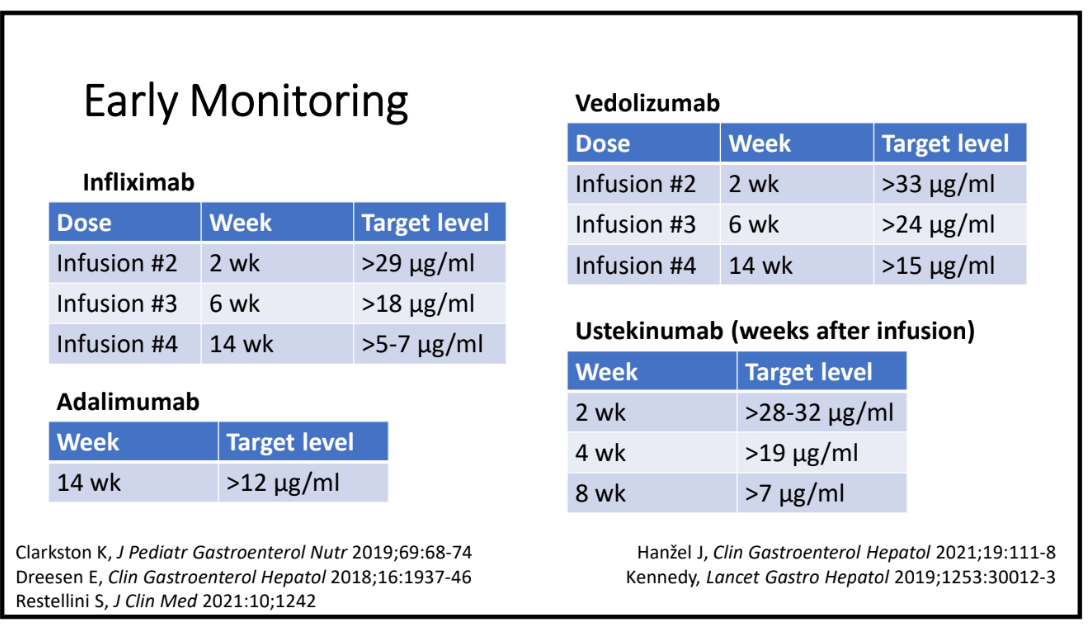
My take: The 8-week interval between induction dose (3rd) and maintenance dose (4th) is too long for many pediatric patients. For those using proactive therapeutic monitoring, checking a level prior to 3rd dose should be considered. Using an automated dosing system (like “iDose”) is likely to be helpful in optimizing response. Current target levels for TDM noted in recent post: Selected Slides from NASPGHAN 2022 Postgraduate Course (part 2) & copied below.

E Cowherd et al. Inflamm Bowel Dis 2022; 28: 1332-1337. The Cumulative Incidence of Pouchitis in Pediatric Patients With Ulcerative Colitis

Methods: Within the IQVIA Legacy PharMetrics Adjudicated Claims Database, the authors identified pediatric patients (n=68) with UC who underwent proctocolectomy with IPAA between January 1, 2007, and June 30, 2015. Key finding:  In the first 2 years following IPAA, the cumulative incidence of pouchitis was 54%. My take: Most patients continue to experience significant problems after “curative” surgery.

The 6th International Symposium on Peadiatric Inflammatory Bowel Disease (PIBD) was held on September 7-10, 2022, in Edinburgh, Scotland. Highlights of several featured presentations (including video presentation on exposome) regarding the latest updates on nutrition and diet are included at this link (courtesy of Nutritional Therapy for IBD website): PIBD Symposium 2022 Nutritional Highlights

Near Denali, AK

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
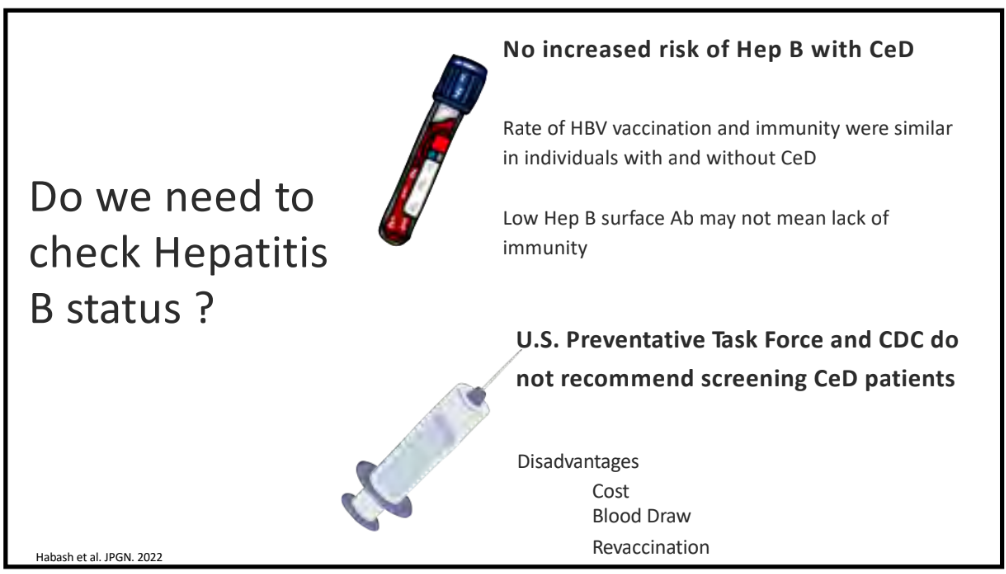
Selected Slides from NASPGHAN 2022 Postgraduate Course (Part 2)

See previous post for lecturers

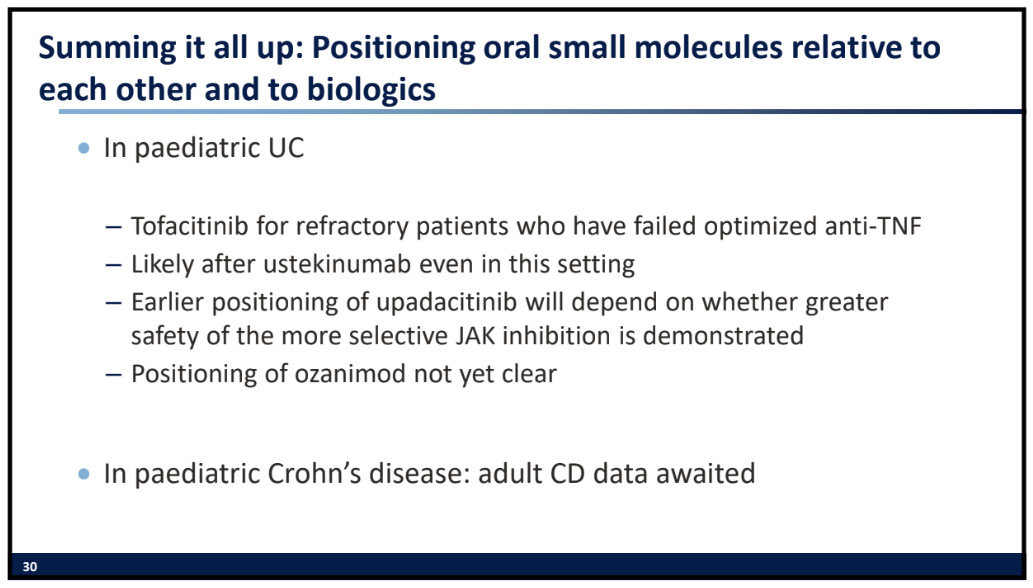
Oral small molecultes in IBD. Anne Griffiths, MD
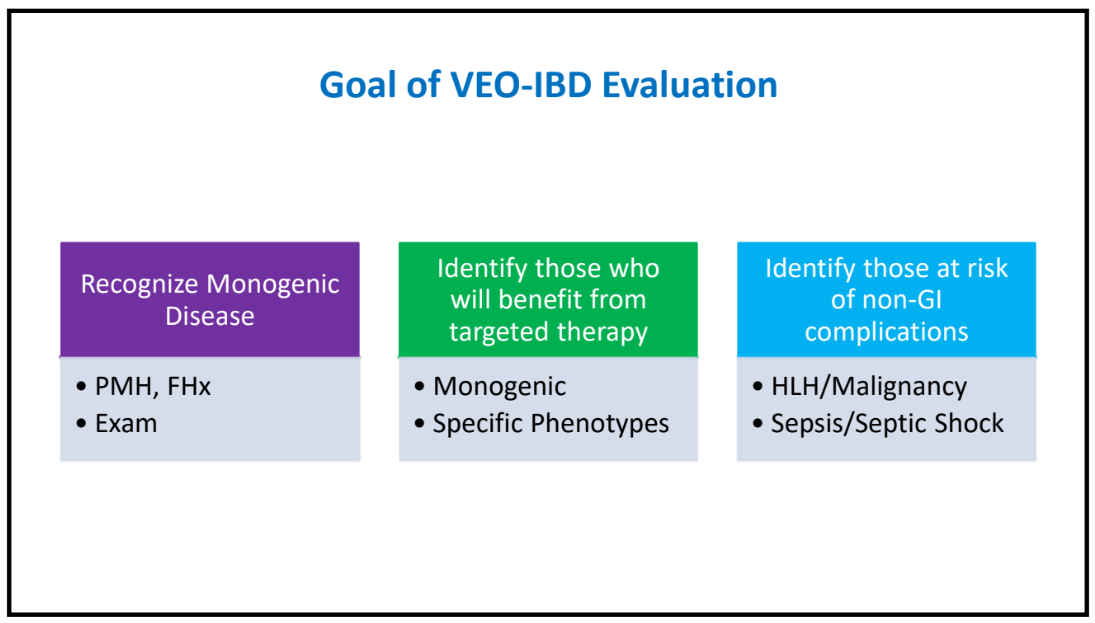
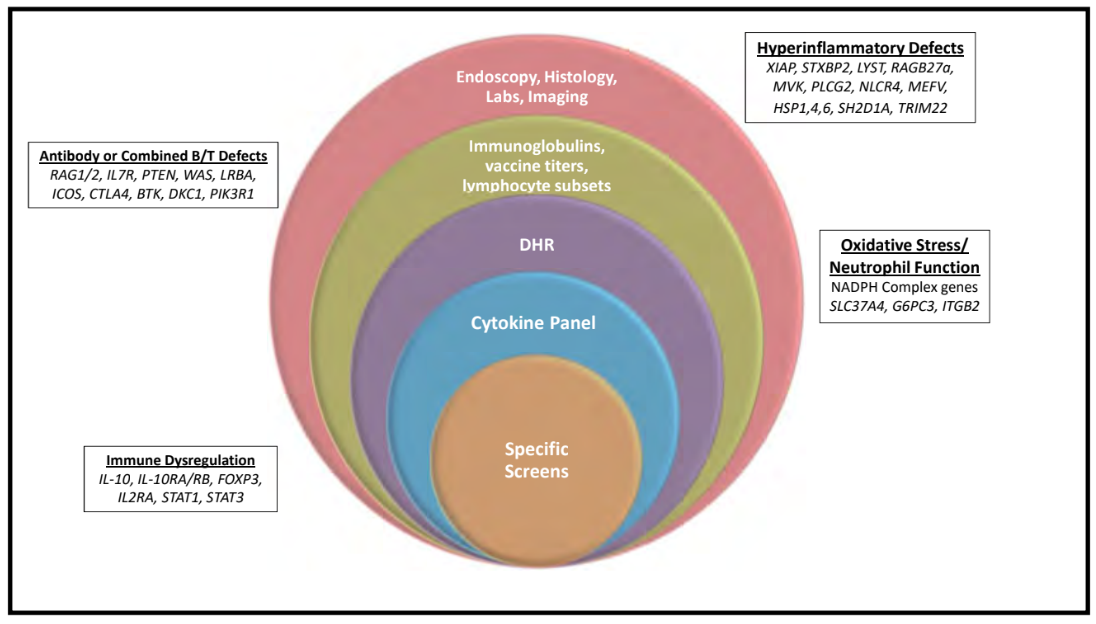
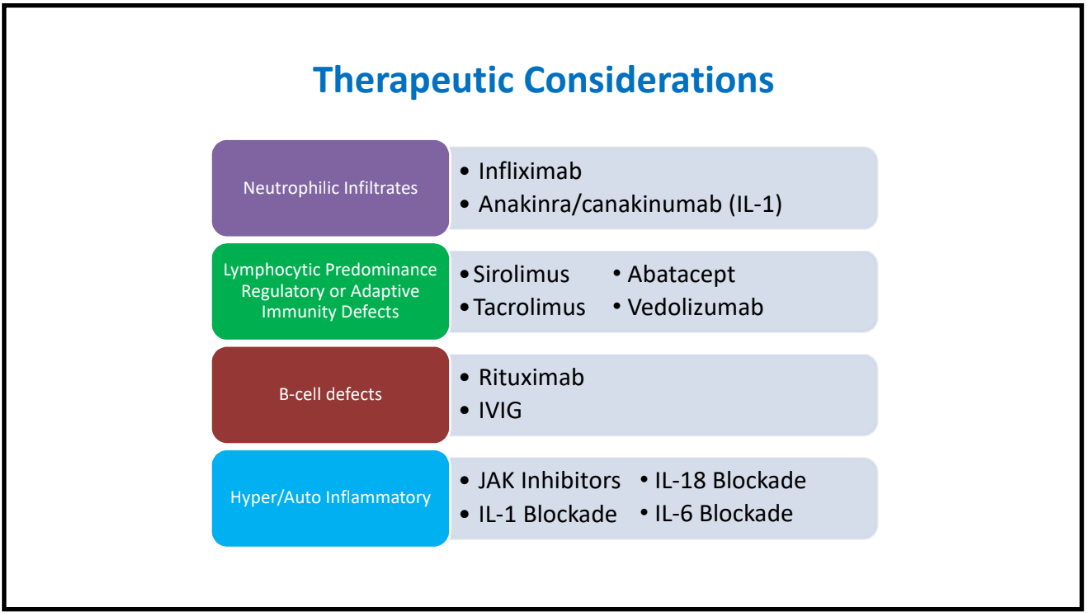
Judith Kelsen, Very early onset IBD
VEO Evaluation
VEO Treatments
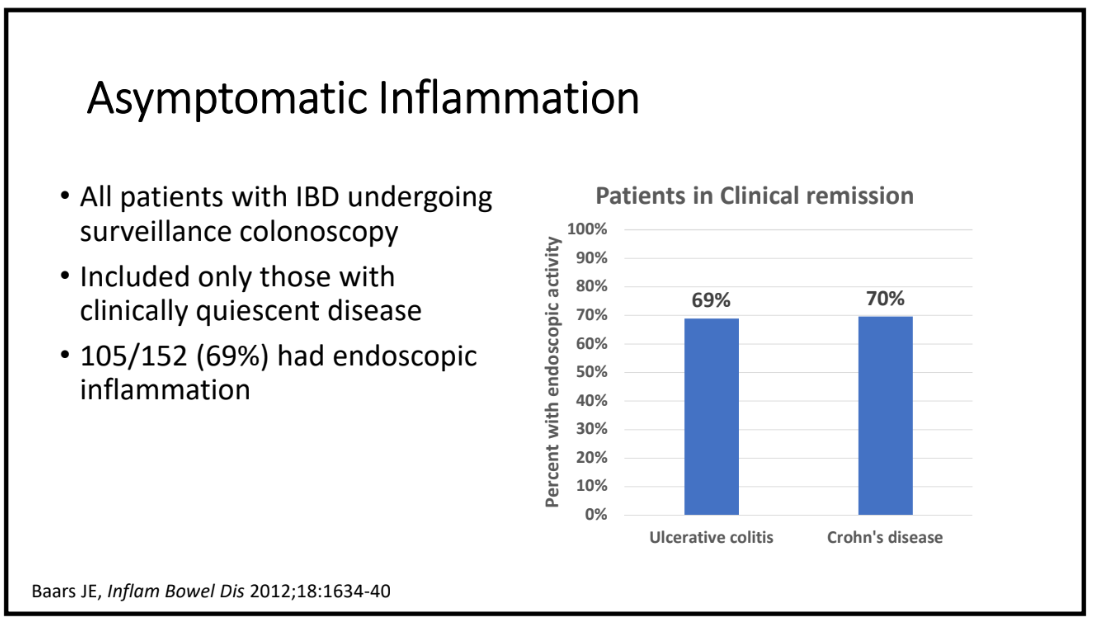
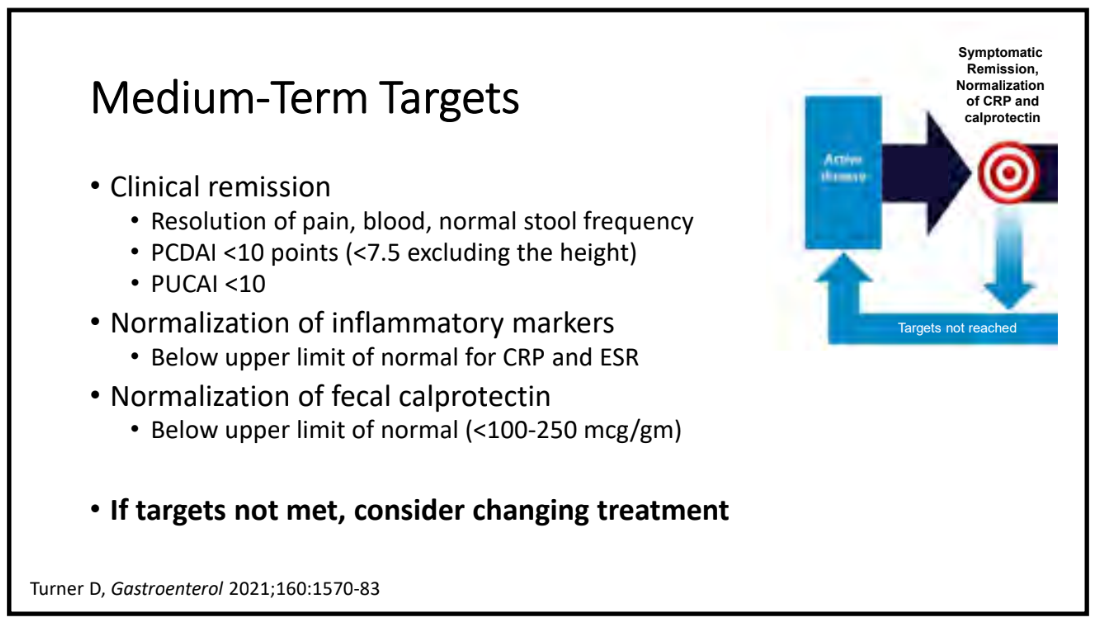
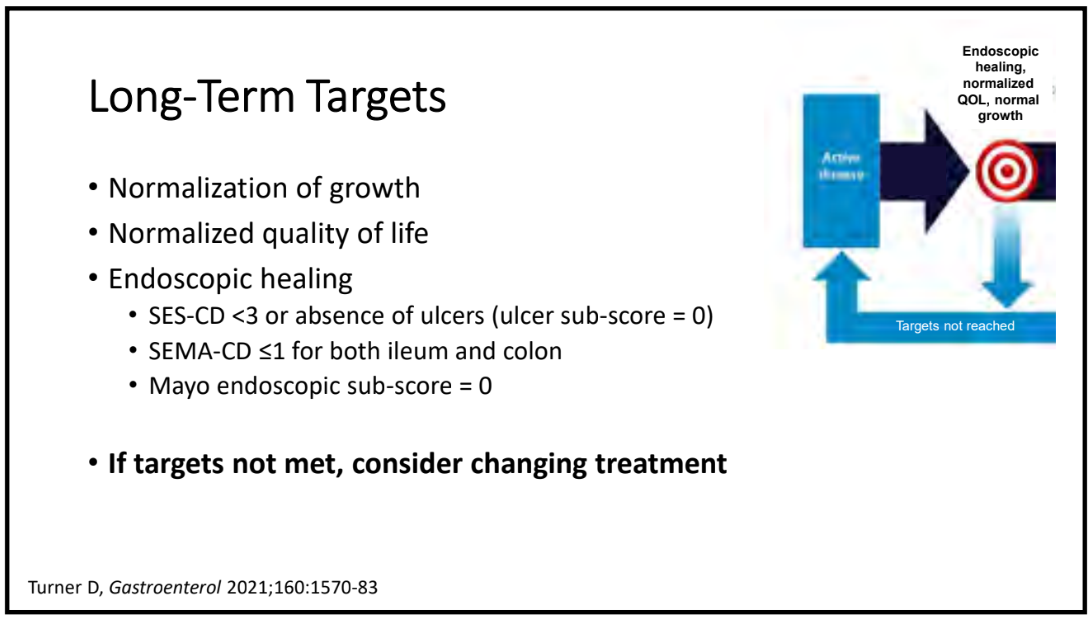
Jeremy Adler and Treat to Target for IBD
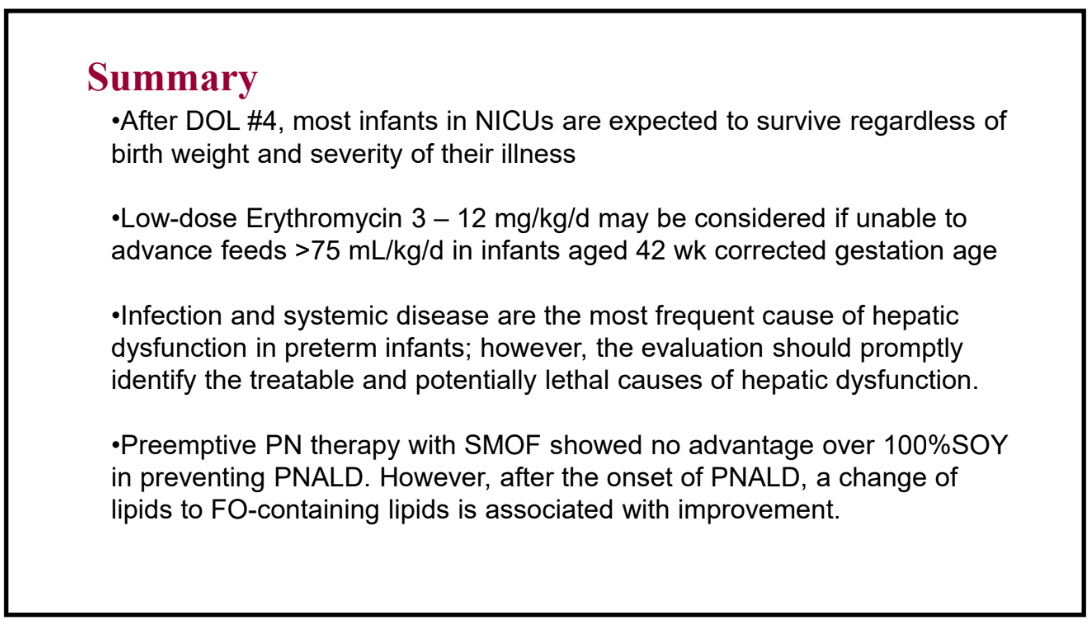
Timothy Sentongo and Growth and Nutrition Issues in the NICU
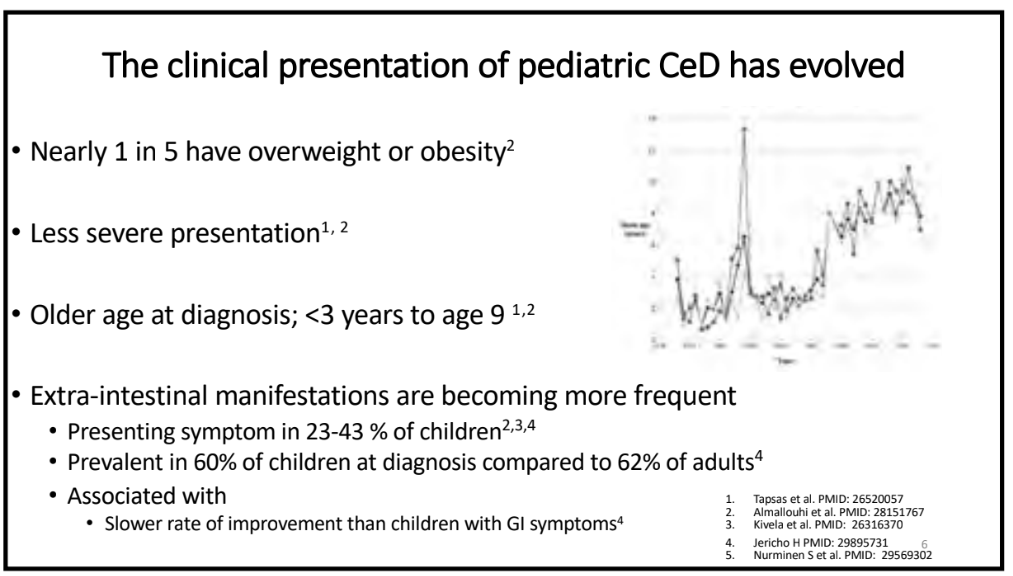
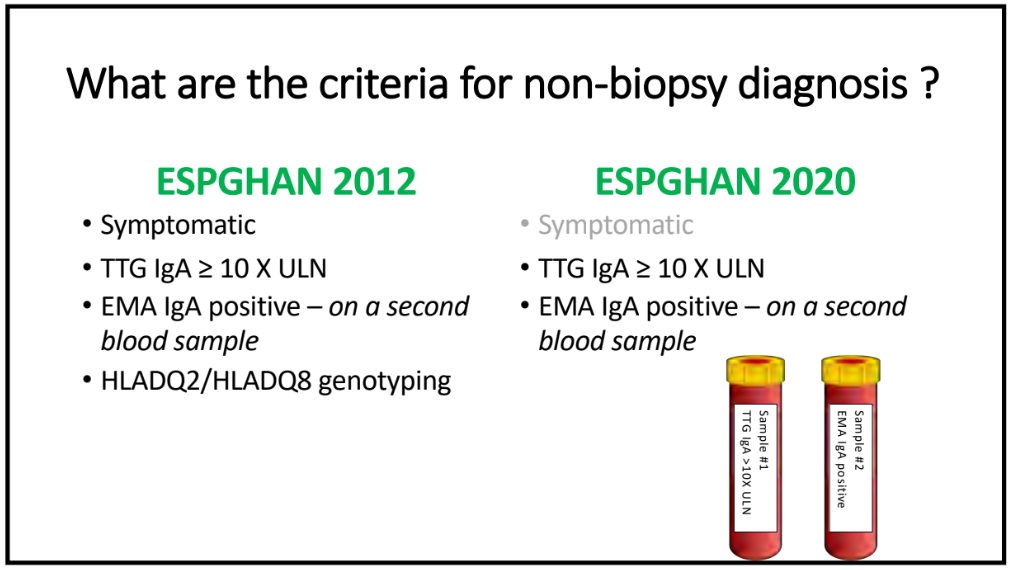
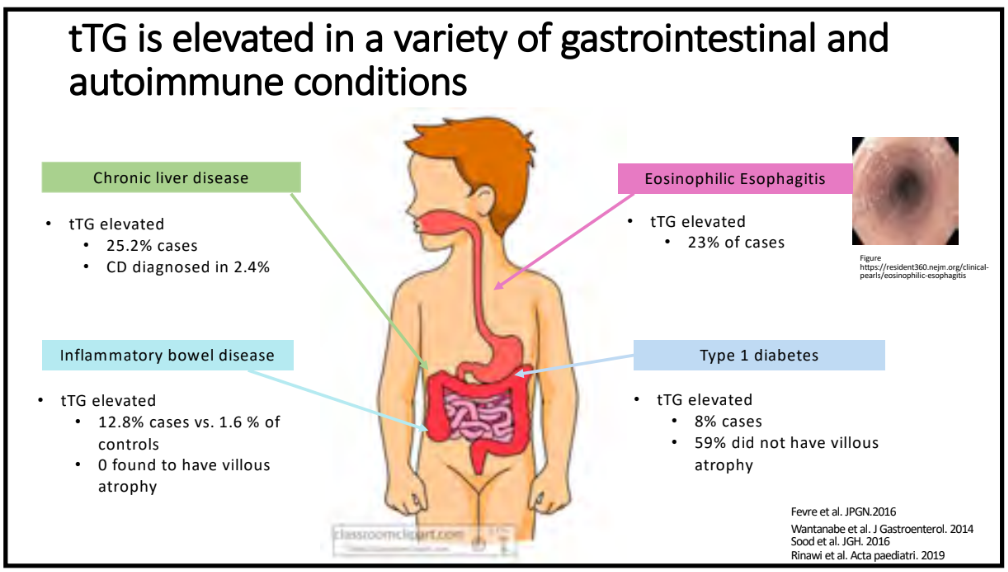
Maureen Leonard and Gluten-Related Disorders Update
Rachel Rosen and Esophageal Motor Disorders
Katja Kovacic and Functional Nausea
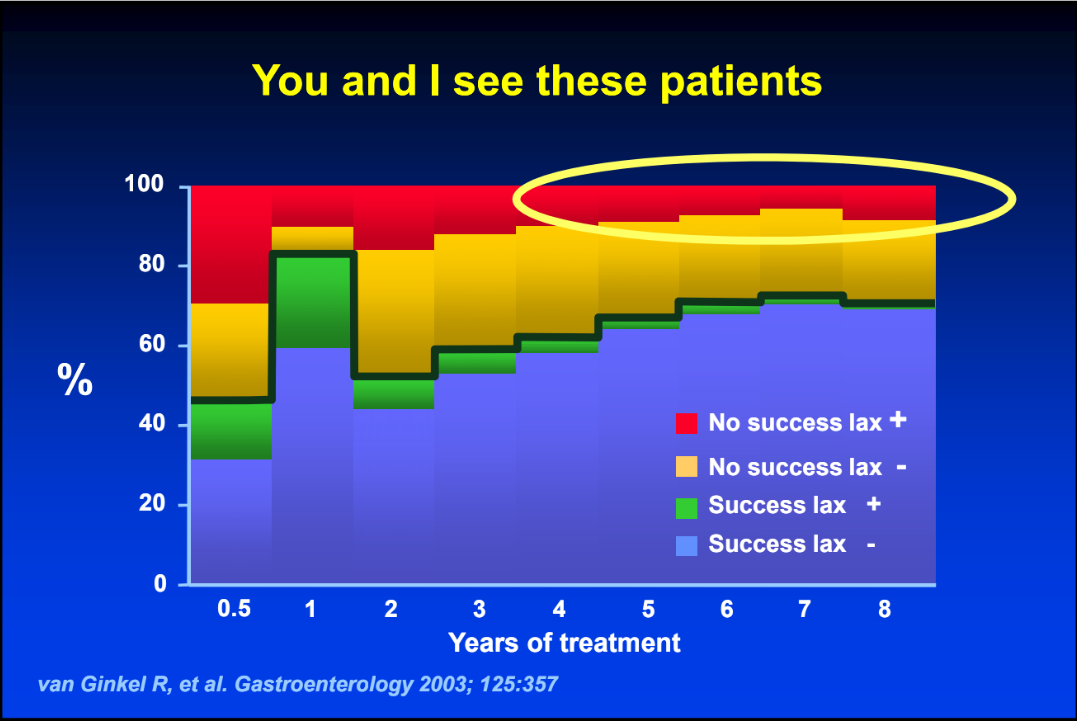
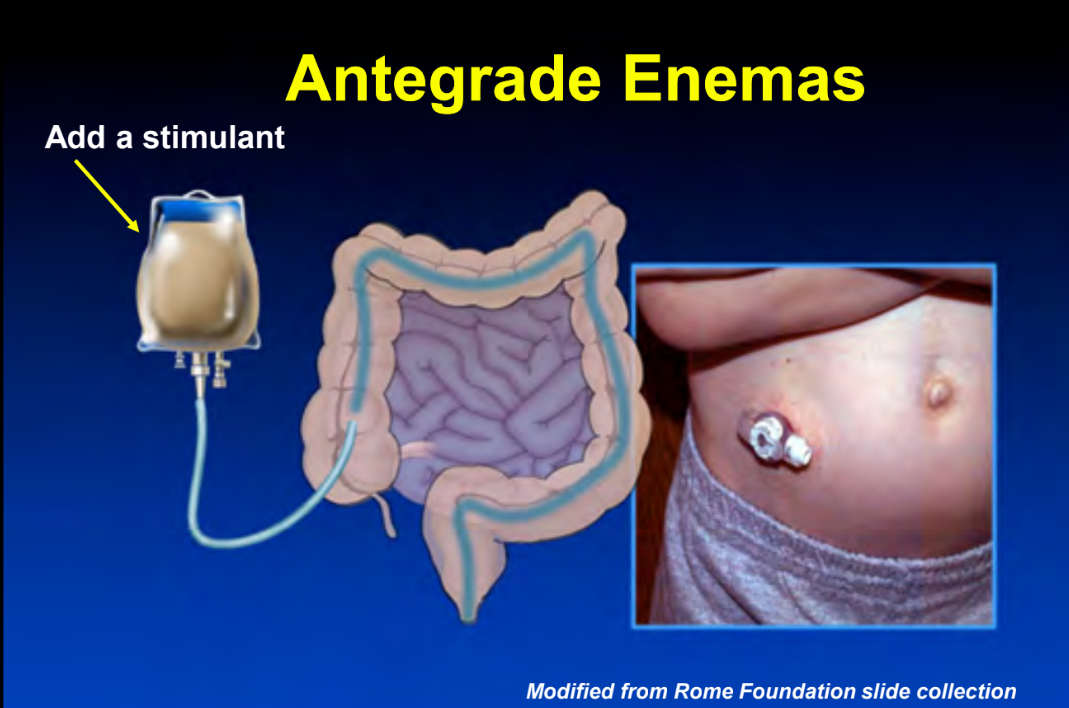
This study was 20 yrs ago -we can do better today

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
How Useful Are 3-site Esophageal Biopsies for Eosinophilic Esophagitis

JB Wechsler et al. Clin Gastroenterol Hepatol 2022; 20: 1971-1976. Defining the Patchy Landscape of Esophageal Eosinophilia in Children With Eosinophilic Esophagitis

Design: The authors prospectively obtained 3-site esophageal biopsies based on rigorous endoscopic measurements of the proximal, mid, and distal esophagus and gastroesophageal junction. Biopsies were reviewed by a pathologist, and those with at least 15 eosinophils per high-power field were considered active EoE.  

Key findings:

  • 304 endoscopies in 167 patients had active EoE. The entire cohort was 217 patients (n=596 endoscopies)
  • Among the 304 endoscopies with active EoE, 9 had focal eosinophilia restricted to the mid esophagus, and 8 were restricted to the proximal esophagus
  • Distal + proximal biopsies had the highest diagnostic sensitivity for a 2-site combination (~98% sensitivity)

Based on this study, the authors recommend “3-site biopsies for optimal disease assessment of active EoE in children.”

My take: I think recommendations to add more and more biopsies is premature until we have evidence that identifying “focal” inflammation in the mid-esophagus has some clinical usefulness/improves outcomes. To me, a 2% increase in sensitivity over 2-site biopsies is negligible & in all likelihood, a 4-site biopsy protocol would increase the yield even further.

Related blog posts:

Stream near Byron Glacier

Does Budesonide Work for Collagenous Gastritis?

Congratulations to NASPGHAN Elected Leaders and especially to Vicky Ng (who I met while completing my fellowship in Cincinnati).

Briefly noted:

RS Choung et al. Clin Gastroenterol Hepatol 2022; 20(9):1977-1985. Collagenous Gastritis: Characteristics and Response to Topical Budesonide

This was an open-label, retrospective study with 64 patients with collagenous gastritis (CG) (50 adults, 14 children). Budesonide was administered in 2 formulations: open-capsule budesonide or compounded immediate-release budesonide capsule.  Key finding: Of the patients treated with topically targeted budesonide (TTB), 89% had a clinical response (42% complete, 46% partial), and 88% had a histologic response (53% complete, 33% partial).

Related blog posts:

At the top of Crow’s Pass Trail, Girdwood AK

Will a SQUIRT Score Be Helpful?

A recent letter to the editor: J Rauh et al. Stool Quality for Intestinal Rehabilitation Therapy (SQUIRT) Score, JPS 2022. doi: https://doi.org/10.1016/j.jpedsurg.2022.08.025

The authors have devised a SQUIRT score for short bowel syndrome. The higher score indicates better enteral tolerance with a highest score of 13 and a lowest score is 3. It is a composite score based on composition, frequency and volume/blowouts. The authors define a blow-out to be a stool loose enough and large enough for the child to require a change of clothes.

How to Score:

Consistency (choose best stool of the day)
Playdough, Formed 5
Peanut Butter, Pasty 4
Pudding, Seedy 3
Pea Soup, Loose 2
Water 1

Occurrences (over 24 hours)
1 to 3 4
4 to 6 3
7 to 9 2
Greater Than 10 1
Ostomy Present 0

Volume
With Ostomy Without Ostomy
(mL/kg) (# of blowouts)

  • < 10 mL/kg 8 0 =4
  • 10 -14 mL/kg 7
    15-19 mL/kg 6 1 =3
  • 20-24 mL/kg 5 2 =2
    25-29 mL/kg 4
  • 30-34 mL/kg 3
  • 35 mL/kg 2
  • >35 mL/kg 1 >3 =1

The authors state that this scoring system has been used in their institution. “This tool can provide objective information to guide clinical decision making. Even patients with ostomies, for whom we can measure stool volume, benefit from SQUIRT scores because including the variable of stool consistency provides a more nuanced assessment than relying on volume.”

My take:This type of scoring system would be useful, primarily in patients in which the volume of stool is difficult to measure. It would benefit from trials to validate its utility.

Related blog posts for Short Bowel Syndrome:

American Windows by Marc Chagall, at the Art Institute of Chicage

Validated SEMA-CD Score For Crohn’s Disease

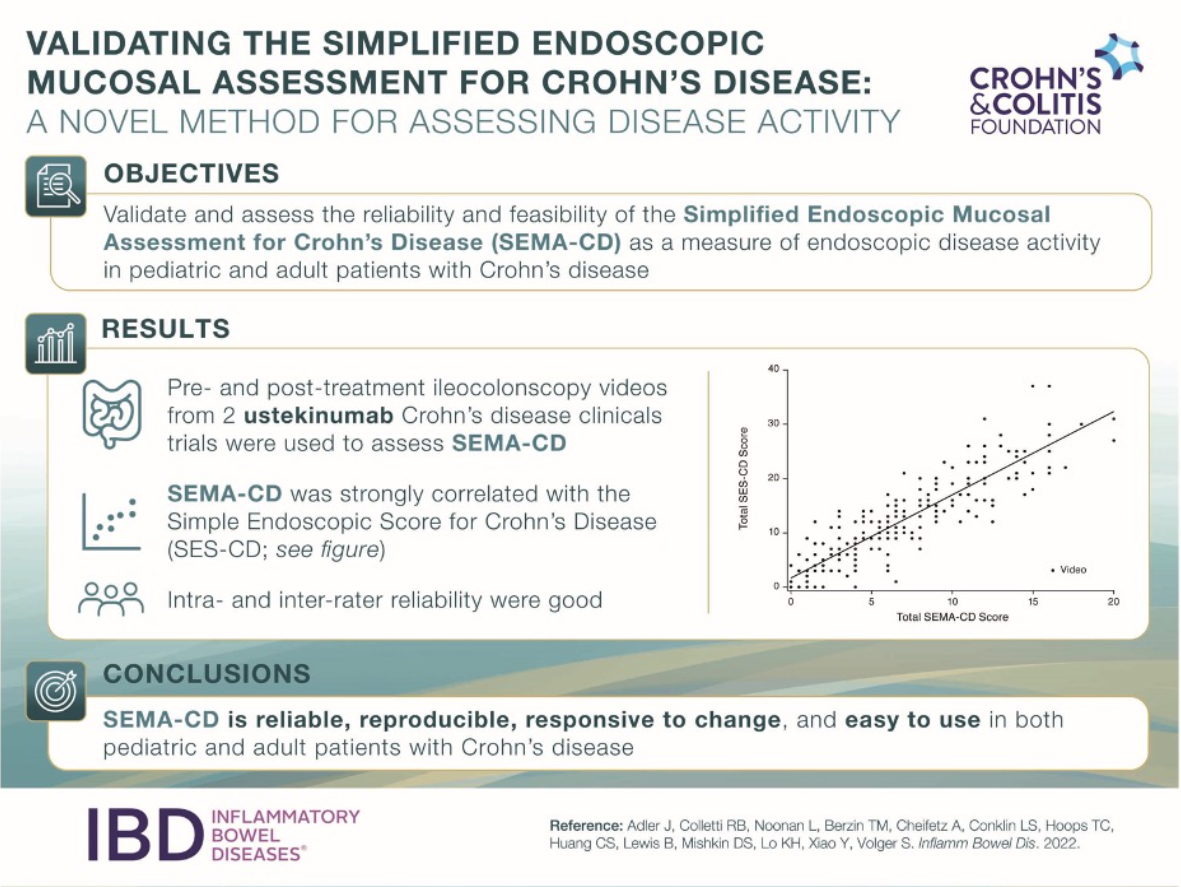
J Adler et al. Inflamm Bowel Dis 2022; Open Access! Validating the Simplified Endoscopic Mucosal Assessment for Crohn’s Disease: A Novel Method for Assessing Disease Activity

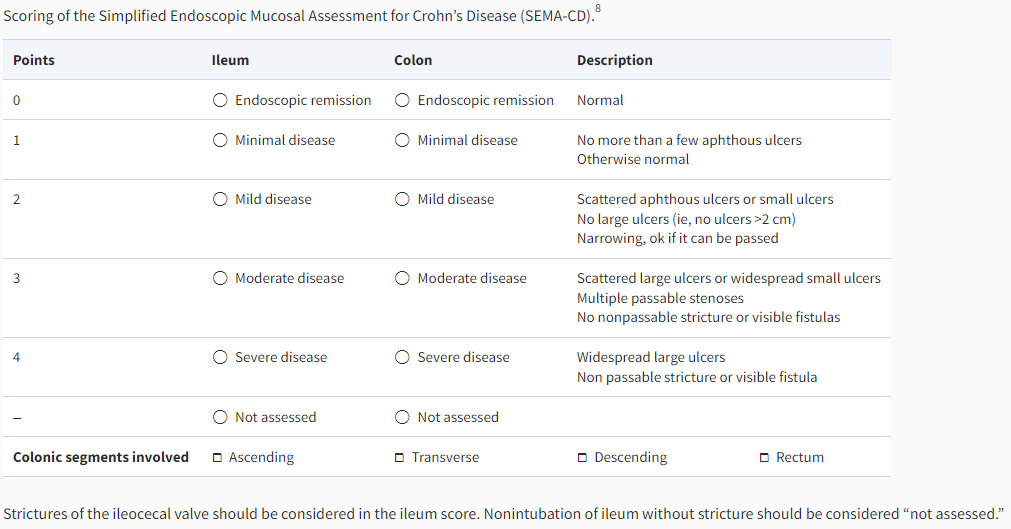
“The SEMA-CD is scored by assigning a numerical value ranging from 0 (endoscopic remission) to 4 (severe disease) for each bowel region (ileum and colon). The overall colon is scored as a whole based on the most severe colonic segment.  The number of colonic segments with any degree of active disease is recorded, regardless of the severity of individual segments. The overall colon score is then multiplied by the number of involved colonic segments, and the result is added to the ileum score.”

Related blog post: The Really Simplified Endoscopy Scoring

Understanding FDA Approval of Vonoprazan-Based Therapies for Helicobacter Pylori

Pharmacy Times (5/4/22): FDA Approves Pair of Vonoprazan Treatments for Helicobacter Pylori Infection

“The (FDA) has approved 2 vonoprazan-based medications for the treatment of Helicobacter pylori (H. pylori) infection.

Phathom Pharmaceuticals announced the approvals of both the Voquezna Triple Pak (vonoprazan, amoxicillin, clarithromycin) and Voquezna Dual Pak (vonoprazan, amoxicillin) based on positive safety and efficacy data from the phase 3 PHALCON-HP trial.”

WD Chey et al. Gastroenterol 2022; 163: 608-619. Open Access! Vonoprazan Triple and Dual Therapy for Helicobacter pylori Infection in the United States and Europe: Randomized Clinical Trial

Key findings from this randomized, controlled trial with treatment-naive 1046 adults:

  • In all patients, vonoprazan triple and dual therapy were superior to lansoprazole triple therapy (80.8% and 77.2%, respectively, vs 68.5% (both superior)
  • In patients with clarithromycin resistance, vonoprazan triple therapy was effective in 65.8%, dual therapy in 69.6%, vs lansoprazole triple therapy 31.9% (both superior)
  • Vonoprazan increases intragastric pH rapidly “and maintains it to a greater degree than PPI; this has been associated with higher H pylori eradication rates” (in prior studies as well)

The associated editorial: CA Fallone (Open Access!) The Current Role of Vonoprazan in Helicobacter pylori Treatment

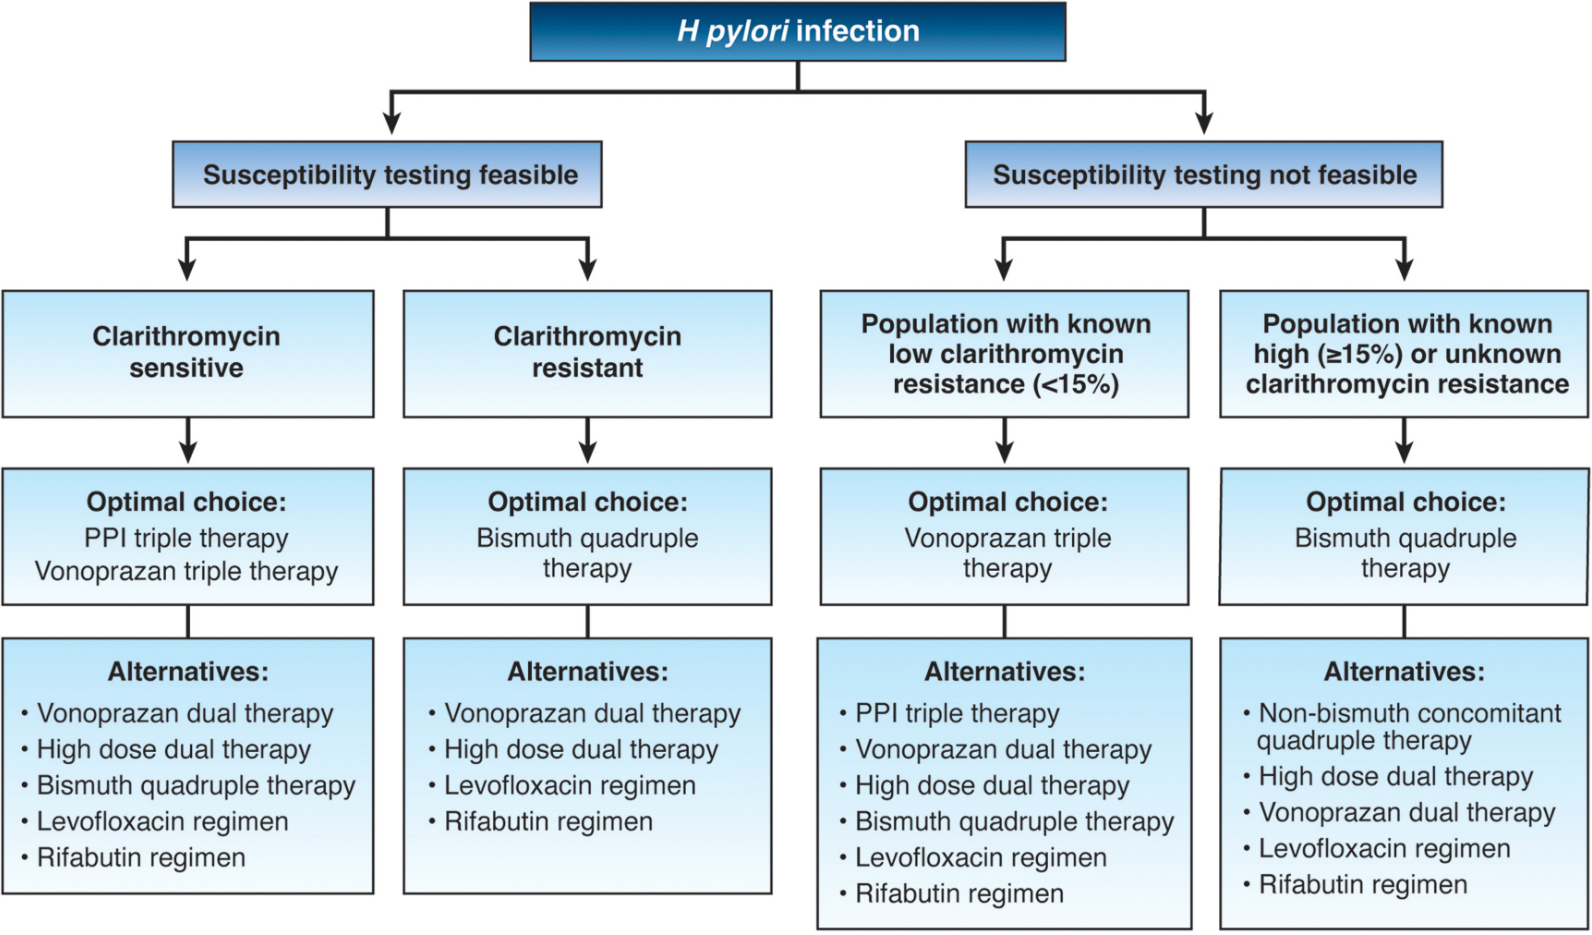
Based on this new information, the author proposes the treatment algorithm below and notes that “the role of increased acid suppression by PPI substitution with vonoprazan should be examined in other H pylori regimens.” The author favors bismuth quadruple therapy in those with clarithromycin resistance as non-bismuth quadruple therapy utilizes an unnecessary antibiotic (clarithromycin).

Other points:

  • Metronidazole resistance is fairly common, but bismuth quadruple therapy can overcome much of the metronidazole resistance
  • Levofloxacin resistance is quite high in certain regions and should only be used with caution, given recent warnings from the US Food and Drug Administration of aortic rupture in susceptible individuals
  • Rifabutin can cause some bone marrow suppression

My take: With the more widespread availability of susceptiblity testing (beyond clarithromycin), I anticipate more targeted treatments. At the same time, vonoprazan-based treatments are likely to be important in increasing eradication rates.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.