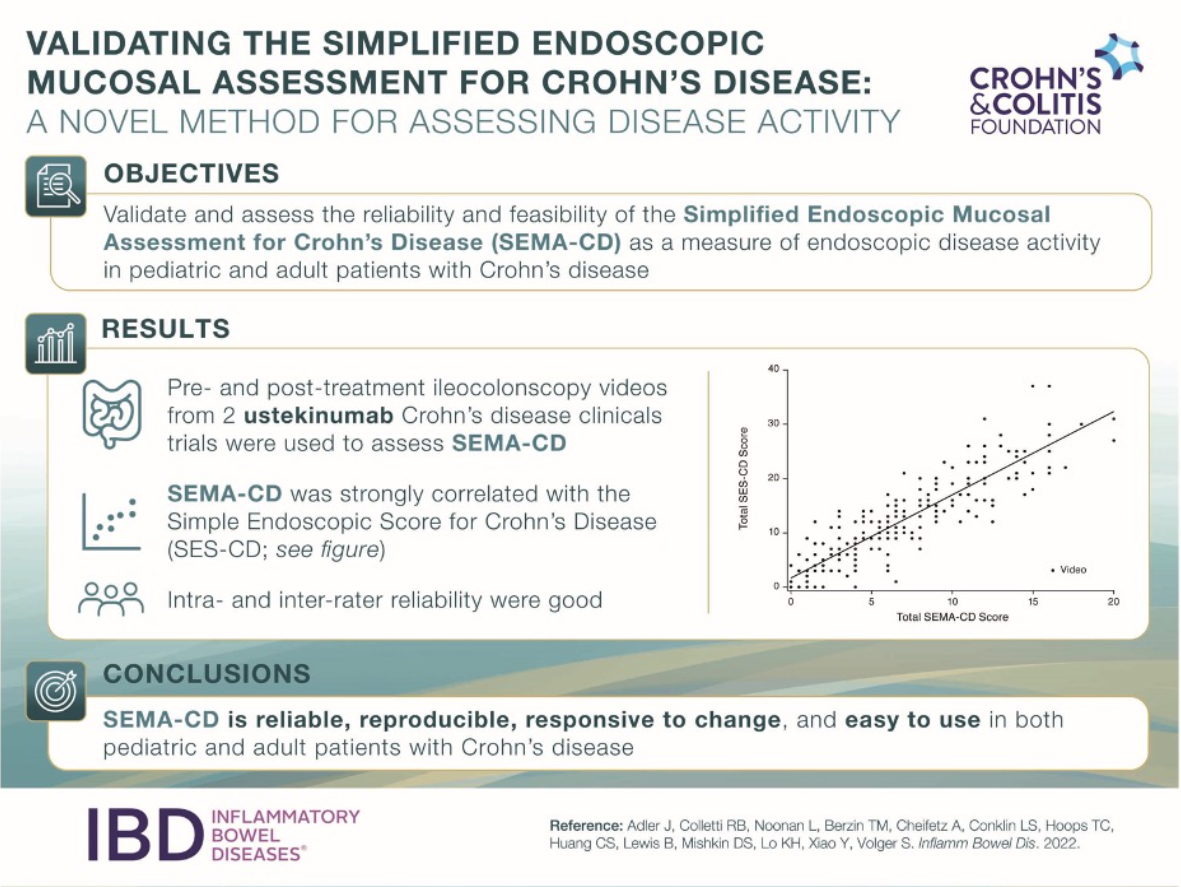
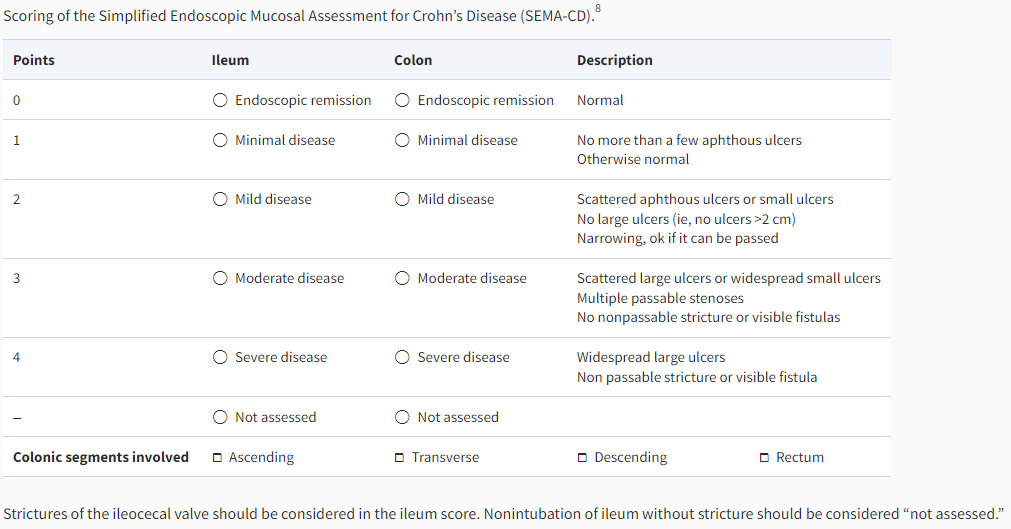
“The SEMA-CD is scored by assigning a numerical value ranging from 0 (endoscopic remission) to 4 (severe disease) for each bowel region (ileum and colon). The overall colon is scored as a whole based on the most severe colonic segment. The number of colonic segments with any degree of active disease is recorded, regardless of the severity of individual segments. The overall colon score is then multiplied by the number of involved colonic segments, and the result is added to the ileum score.”
In this retrospective study, “during a 20-month period until December 2021 using PPE and three different test approaches: no testing (n=4543), rapid antigen (RA) testing (n=682) and RT-PCR testing (n=10 465). In addition, 60 endoscopies were performed in patients with proven COVID-19. Not a single staff member became infected with SARS-CoV-2 during the 20 months analysed; vaccination rate of the team was 97%.”
The authors note that routine testing of clinical team was not performed; thus, they cannot exclude the possibility of asymptomatic infections.
My take (borrowed in part from authors): “PPE is highly effective for avoidance of SARS-CoV-2 transmission during upper or lower GI endoscopies.” Pre-op testing for COVID has many downsides: increased costs, delays in care, potential exacerbation of health disparities, and detrimental effects to endoscopy efficiency (especially with inconclusive results)
“The (FDA) has approved 2 vonoprazan-based medications for the treatment of Helicobacter pylori (H. pylori) infection.
Phathom Pharmaceuticals announced the approvals of both the Voquezna Triple Pak (vonoprazan, amoxicillin, clarithromycin) and Voquezna Dual Pak (vonoprazan, amoxicillin) based on positive safety and efficacy data from the phase 3 PHALCON-HP trial.”
Key findings from this randomized, controlled trial with treatment-naive 1046 adults:
In all patients, vonoprazan triple and dual therapy were superior to lansoprazole triple therapy (80.8% and 77.2%, respectively, vs 68.5% (both superior)
In patients with clarithromycin resistance, vonoprazan triple therapy was effective in 65.8%, dual therapy in 69.6%, vs lansoprazole triple therapy 31.9% (both superior)
Vonoprazan increases intragastric pH rapidly “and maintains it to a greater degree than PPI; this has been associated with higher H pylori eradication rates” (in prior studies as well)
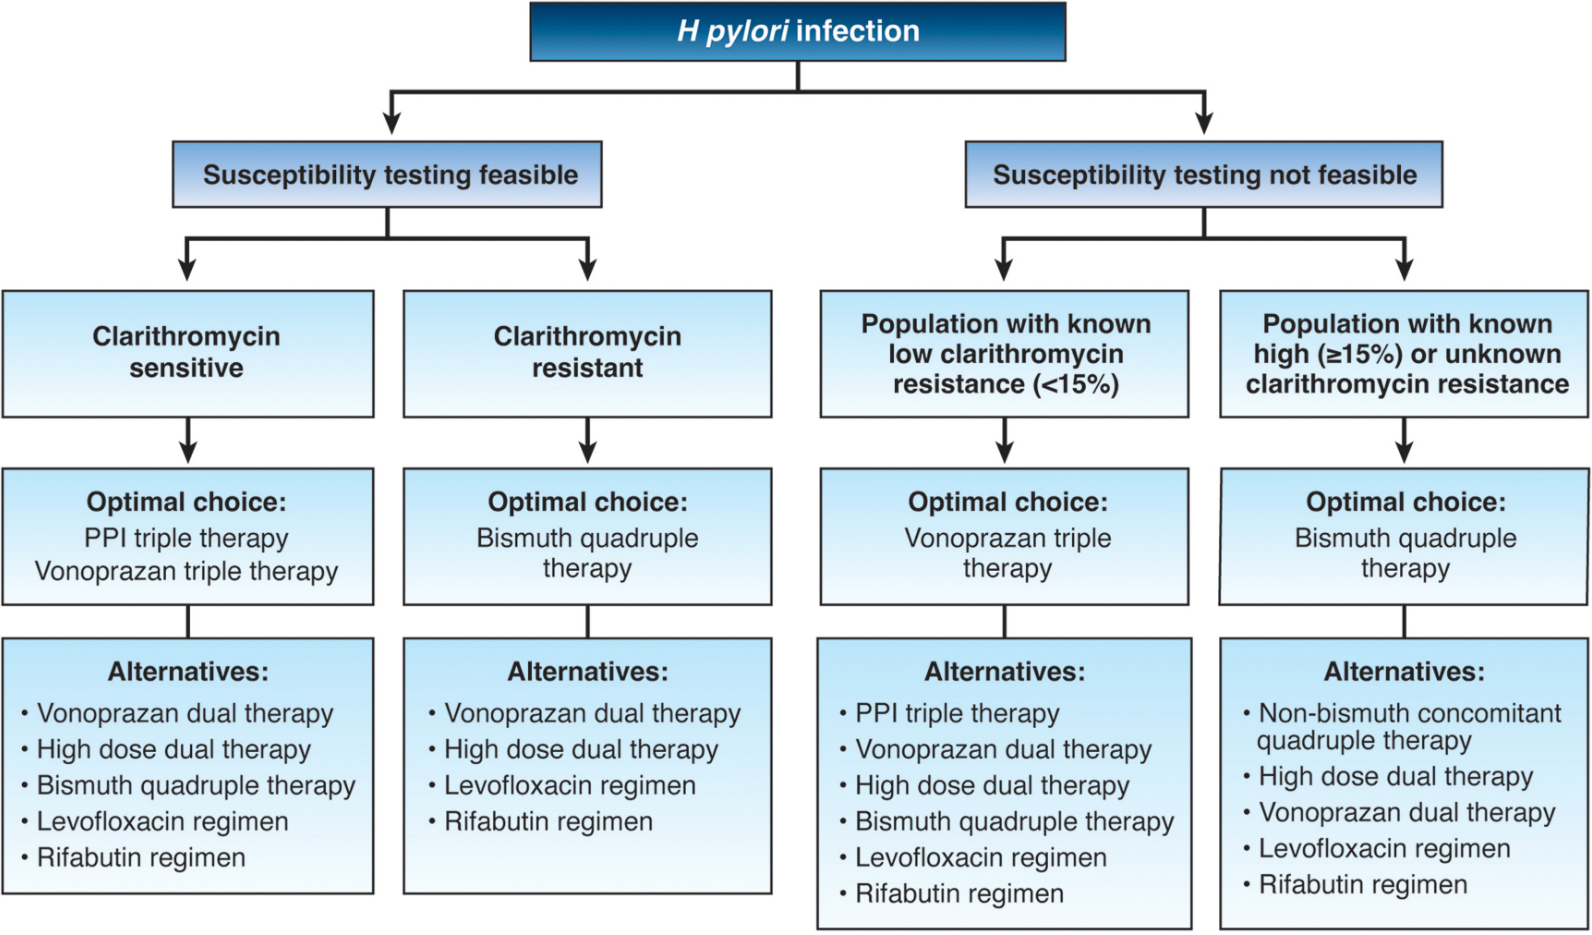
Based on this new information, the author proposes the treatment algorithm below and notes that “the role of increased acid suppression by PPI substitution with vonoprazan should be examined in other H pylori regimens.” The author favors bismuth quadruple therapy in those with clarithromycin resistance as non-bismuth quadruple therapy utilizes an unnecessary antibiotic (clarithromycin).
Other points:
Metronidazole resistance is fairly common, but bismuth quadruple therapy can overcome much of the metronidazole resistance
Levofloxacin resistance is quite high in certain regions and should only be used with caution, given recent warnings from the US Food and Drug Administration of aortic rupture in susceptible individuals
Rifabutin can cause some bone marrow suppression
My take: With the more widespread availability of susceptiblity testing (beyond clarithromycin), I anticipate more targeted treatments. At the same time, vonoprazan-based treatments are likely to be important in increasing eradication rates.
Related blog posts:
How To Achieve Helicobacter Pylori Cure Rates of >95% This post lists some of the codes from several commercial companies that perform susceptibility testing. The Quest code has been updated. Our Quest representative indicated code: 36994 (H. pylori culture with reflex to susceptibility). Preferred Specimen: 3 mm Gastric/Antral or Duodenal biopsy collected in Brucella broth or Trypticase Soy Broth (TSB) with 10-20% glycerol
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
In 2018, Belcher pharmaceuticals managed to get the FDA to designate Ethanol as an orphan drug with a subsequent increase in cost to ~$10,000 for a 10-vial pack (10-day supply) (Related post: FDA ‘Safety Initiative’ Now Means an Ounce of Ethanol Costs $30,000). As such, many (?most) children with intestinal failure (IF) no longer have access to this therapy which prevents life-threatening infections to their central lines.
A recent retrospective study (R Josyabhata et al. JPGN 2022; 75: 304-307. Sodium Bicarbonate Locks May Be a Safe and Effective Alternative in Pediatric Intestinal Failure: A Pilot Study) examined the use of sodium bicarbonate lock therapy (SBLT) as an alternative to ethanol in four children. This study was prompted by a clinical trial in hemodialysis patients which demonstrated a reduction in catheter-related bloodstream infections (CRBSI). None of the four patients had a CRBSI.
My take: A much larger multi-center study will be needed to determine if SBLT is worthwhile.
K Culbreath et al. JPGN 2022; 75: 345-350. Antibiotic Therapy for Culture-Proven Bacterial Overgrowth in Children With Intestinal Failure Results in Improved Symptoms and Growth This article describes outcomes of 104 children with intestinal failure who underwent endoscopy and had duodenal cultures sent to identify bacterial overgrowth/susceptibility/targeted antibiotics. This information was associated with fewer symptoms and better growth. The methods section provides detailed information on collection and handling of specimens (which could be helpful for those trying to implement this strategy). However, there is not a standardized protocol for duodenal cultures to detect bacterial overgrowth.
This is a terrific review of POEM; it explains the procedure technique (with pictures), outcomes, indications and adverse events. The paper indicates that more than 300 children (as young as 11 months) have had POEM in published studies with good outcomes.
Interestingly, the authors state that 20-40 procedures “should be performed for competency and that 60 are required to achieve mastery.” Also, long-term data are lacking.
My take: POEM has good data supporting its use, especially in adults. Still, it will be quite difficult for pediatric gastroenterologists to acquire sufficient expertise to do this procedure.
“Exit Glacier” in Kenai Fjords National Park. This picture shows how much the glacier has retreated since 2005 due to global warming (the ice used to extend to this sign).
Firearm-related deaths are now the leading cause of death in U.S. children. The push to make guns more available is resulting in more tragic outcomes. In the U.S., putting too much mayonnaise on a sandwich can be a death sentence:
In Georgia, the law, signed by current governor Brian Kemp, allows Georgians to carry concealed handguns without first getting a license from the state. This law along with a previous “Guns Everywhere Law” has been associated with increased gun sales and increased gun violence and deaths.
After Uvalde, Amanda Gorman published the following poem
Everything hurts, Our hearts shadowed and strange, Minds made muddied and mute. We carry tragedy, terrifying and true. And yet none of it is new; We knew it as home, As horror, As heritage. Even our children Cannot be children, Cannot be.
Everything hurts. It’s a hard time to be alive, And even harder to stay that way. We’re burdened to live out these days, While at the same time, blessed to outlive them.
This alarm is how we know We must be altered — That we must differ or die, That we must triumph or try. Thus while hate cannot be terminated, It can be transformed Into a love that lets us live.
May we not just grieve, but give: May we not just ache, but act; May our signed right to bear arms Never blind our sight from shared harm; May we choose our children over chaos. May another innocent never be lost.
Maybe everything hurts, Our hearts shadowed & strange. But only when everything hurts May everything change.
No Exaggeration: Too Many Children Are Dying in the U.S. “The sad fact is that a child or adolescent in the United States is 57% more likely to die by the age of 19 years than those in other wealthy nations.” This is due mainly to more deaths from MVAs and from gun violence.
In a nationwide Swedish cohort of 18,815 incident patients with a minimum 5 years of follow-up, 652 (3.5%) underwent formation of a stoma. The 5-year cumulative incidence of stoma formation was 2.5%, with no differences between calendar periods (2003–2006, 2007–2010, and 2011–2014).
This study captured data from 1317 patients (including 927 patients stopping infliximab and 390 patients stopping adalimumab) to develop risk prediction models. “The authors confirm many of the high risk, albeit rather intuitive, factors that are associated with the risk of relapse, including younger age, younger age at diagnosis, smoking, upper gastrointestinal tract involvement, longer disease duration, absence of concomitant immunosuppressant use, previous anti-TNF failure, and absence of clinical remission.”
The editorial notes that even in the lowest risk group, more than 20% had risk of relapse within 1 year; in addition, stopping therapy increases risk of not recapturing remission with restart of treatment. “Stopping anti-TNF therapy is a highly personalized treatment decision and is one that carries considerable risks…therapeutic discontinuation of TNF antagonists should be reserved for the very small minority of patients who are in deep remission, have a strong desire to stop treatment, have no (or very few) characteristics of high-risk CD, can tolerate a substantial disease flare, and are fully informed of the risks of therapeutic withdrawal.”
Graphical abstract below shows that 52.2% of patients who did not achieve clinical response to 8 weeks’ treatment with tofacitinib 10 mg BID in the induction studies achieved a clinical response following extended induction (delayed responders). At Month 12 of OCTAVE Open, 70.3%, 56.8%, and 44.6% of delayed responders maintained clinical response and achieved endoscopic improvement and remission, respectively. Corresponding values at Month 36 were 56.1%, 52.0%, and 44.6%.
My take: By extending the treatment induction to 16 weeks to determine response (rather than 8 weeks), the authors showed that 75% of patients with ulcerative colitis in the initial cohort respond to tofacitinib.
Design: A prospective observational single-center study in 41 children with EoE treated with the 1-food elimination diet (1FED). Upper endoscopy with biopsies was performed after 8 to 12 weeks of treatment. The primary end point was histologic remission, defined as fewer than 15 eosinophils per high-power field.
Key findings:
Histologic remission occurred in 21 (51%) children, with a decrease in peak eosinophils per high-power field from a median of 50
Endoscopic abnormalities improved in 24 (59%) patients, while symptoms improved in 25 (61%). Improved symptoms included chest pain, dysphagia, and pocketing/spitting out food
Interestingly, in terms of all symptom resolution, this was higher in the group of nonresponders 8 (40%) than in the responders 4 (19%)
Younger patients (mean 7 yrs vs 12 yrs) and patients with IgE-mediated food allergies tended to be more likely to fail dairy elimination in this study
One key caveat is that most patients continued PPI during study; thus it is unknown if stopping a PPI before starting dairy elimination would have changed treatment response. 90% of patients were receiving PPIs at enrollment
My take: This study should prompt more widespread use of dairy elimination as a first line treatment prior to consideration of medications for long-term treatment. This study also reinforces the concept that symptom improvement remains an inadequate indicator of response. Perhaps, Chick-Fil-A marketing needs to be used for our EoE patients to shun cows (cow’s milk in this case).