SERENE Study: Does a Higher Induction Dose of Adalimumab Help for Crohn’s Disease?

GR D’Haens et al. Gastroenterol 2022; DOI:https://doi.org/10.1053/j.gastro.2022.01.044. Open Access: Higher vs Standard Adalimumab Induction Dosing Regimens and Two Maintenance Strategies: Randomized SERENE CD Trial Results

Methods: In this phase 3, randomized, double-blind, multicenter trial, eligible adults were randomized to higher induction regimen (adalimumab 160 mg at weeks 0, 1, 2, and 3; n = 308) or standard induction regimen (adalimumab 160 mg at week 0 and 80 mg at week 2; n = 206) followed by 40 mg every other week from week 4 onward. Endoscopic results were interpreted by a central reviewer.

Key Findings:

  • Similar proportions of patients receiving higher induction regimen and standard induction regimen achieved clinical remission at week 4 (44% in both; P = .939) and endoscopic response at week 12 (43% vs 39%, respectively, P = .462).
  • There was a high proportion of patients (>70%) who achieved corticosteroid-free clinical remission after an early corticosteroid taper beginning at week 4
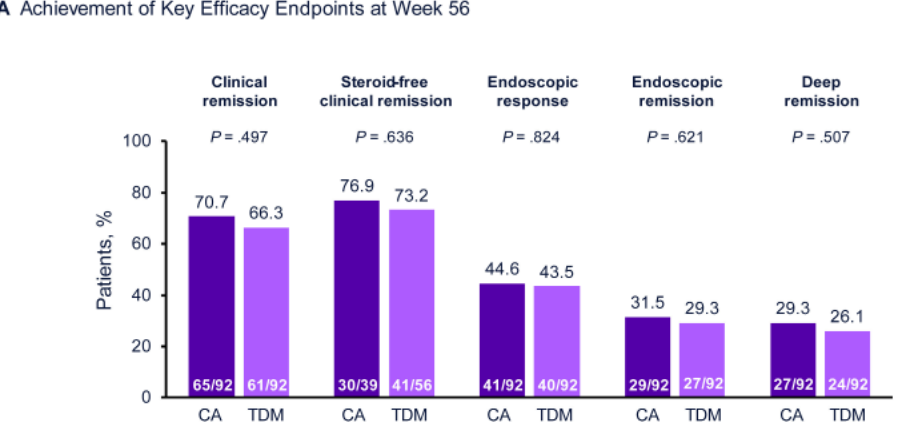
  • Week 56 efficacy was similar between clinically-adjusted (CA) and therapeutic drug monitoring (TDM).  28% of patients in the CA group and 39% of TDM had their dose escalated.
  • Safety profiles were comparable between dosing regimens.

In the discussion, the authors wade into the topic of TDM for adalimumab:

“Results from the exploratory SERENE CD study suggesting there is no clinical benefit of a proactive TDM strategy over a CA strategy for optimizing adalimumab maintenance dosing align with the results from previous studies evaluating TDM of anti–tumor necrosis factor therapies in adult patients with inflammatory bowel disease. In the TAXIT study, proactive TDM was not superior to CA dose optimization for achieving remission at 1 year in patients with CD or ulcerative colitis.24 Similarly, in the TAILORIX study of patients with CD, proactive TDM failed to improve clinical and endoscopic remission rates over a CA approach.25 In contrast, proactive TDM led to a higher clinical remission rate than did reactive TDM among pediatric patients with CD in the PAILOT trial, but this trial was nonblinded and lacked endoscopic assessments.26“

My take: This study shows that standard induction performed as well as higher dose induction in adults with Crohn’s disease. Also, this study found that TDM did not improve response at 56 weeks in adults. Due to differences in body size and metabolism, the exact role for TDM in pediatric patients needs further study.

Related blog posts:

HIR =high dose induction regimen, SIR =standard induction regimen

FLUTE Study: Fluticasone ODT for EoE -Phase 2b Study Shows Efficacy

ES Dellon et al. Clin Gastroenterol Hepatol 2022; https://doi.org/10.1016/j.cgh.2022.02.013 (Ahead of print) Open Access: Fluticasone Propionate Orally Disintegrating Tablet (APT-1011) for Eosinophilic Esophagitis: Randomized Controlled Trial

Methods: In this randomized, double-blind, placebo-controlled, dose-finding, phase 2b trial, 106 adults with EoE received 1 of 4 APT-1011  (fluticasone propionate oral disintegrating tablet) doses or placebo for a 12-week induction period and 40 weeks of maintenance. 

Key findings:

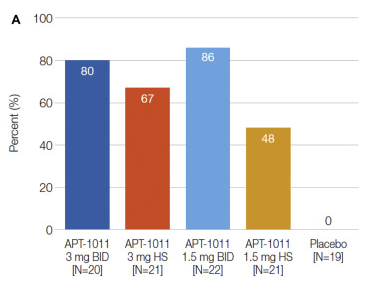
  • Histologic response (≤6 eosinophils per high-power field at Week 12) rates were 0% for placebo, 80% for APT-1011 3 mg twice daily (BID), 67% for 3 mg at bedtime (HS), 86% for 1.5 mg BID, 48% for 1.5 mg HS (P < .001 for all groups vs placebo). 
  • There was also improvement in treatment group in dysphagia and EoE Endoscopic Reference Score (EREFS); the EREFS improved from 4.5 to 2.3 for 3 mg BID, 5.3 to 2.1 for 3 mg HS, 4.6 to 1.7 for 1.5 mg BID, 5.3 to 2.9 for 1.5 mg HS vs 5.2 to 4.5 for placebo. See Figure 2 for 52 week trend in EREFS.
  • Candidiasis: For the 3-mg BID group, oral and esophageal candidiasis was 40% in Part 1 and 32% in Part 2, 18% and 16% for 1.5 mg BID, and 5% and 7% for 3 mg HS (same subject)
  • Low morning cortisol noted 3 times in part 1 and 5 times in part 2. “All cortisol test abnormalities resolved upon retesting, with no dose adjustment or interruption of treatment.” Adrenal suppression is expected to be low because “FP undergoes extensive first-pass metabolism to inactive metabolites, with bioavailability demonstrated as <1%”

My take: A fluticasone ODT would represent a big improvement compared to current situation of asking families to either spray a pulmonary inhaler down their throat or to create a budesonide slurry using either honey or splenda. How much would this cost?

Histologic responders at Weeks 12. Interestingly, the 1.5 mg BID had a modestly higher response rate at 12 weeks, 26 weeks, and 52 weeks than the the 3 mg BID and the 3 mg qhs dosing groups.

Related blog posts:

Sugary Beverage and Liver Stiffness in Healthy Adults

CW Leung, EB Tapper. Clin Gastroenterol Hepatol 2022; 20; 959-961. Sugar-sweetened Beverages Are Associated With Increased Liver Stiffness and Steatosis Among Apparently Healthy Adults in the United States

In this representative sample (2706 adults, median 37.9 years) from 2017-2018 NHANES, subjects without any known chronic disease had tow 24-hr dietary recalls collected and had liver stiffness measurements (LSM) and controlled attenuation parameters (CAP); LSM <7 kPa (using vibration-controlled transient elastography) was considered low risk for advanced fibrosis and CAP >248 dB/m were at risk for heaptosteatosis. Key findings:

  • 11% (n=305) had LSM >7.0 kPa and 46% (n=1254) had CAP >248 dB/m
  • Sugar-sweetened beverage (SSB) >2/day was associated with greater LSM (OR 2.30)
  • In mutlivariate analysis, consuming >1-2 sugar-sweetened servings per day was associated with elevated CAP (OR 1.51 compared to adults with SSB consumption
  • Limitations: this cross-sectional study cannot prove causality

My take: Even in healthy adults, SSB consumption is associated with detrimental changes in the liver.

Related blog posts:

How Esophageal Dilatation Affects Symptoms and Inflammation in Eosinophilic Esophagitis

E Safroneeva et al. Clin Gastroenterol Hepatol 2022; 20: 766-775. Long-Lasting Dissociation of Esophageal Eosinophilia and Symptoms After Dilation in Adults With Eosinophilic Esophagitis

100 adults enrolled in a multisite prospective observational study in which 55 underwent dilatation. Key findings:

  • In nondilated patients, the association between eos/hpf and symptoms was moderate (ρ = 0.49; P < .001) based on the symptom-based EoE activity index (EEsAI); for a 10-eos/hpf increase, the predicted EEsAI increased by 2.69 (P = .002)
  • In patients dilated 1 or less and more than 1 year before index endoscopy, this association was abolished (ρ = -0.38; P = .157 for ≤1 y and ρ = 0.02; P = .883 >1 y)

Limitations: sample size (only 25% subset of total cohort due to missing data), cross-sectional study design

My take: This finding is a double-edge sword. The good part is that dilatation improves dysphagia despite ongoing inflammation which may be refractory to current medical treatments. The bad part is this dissociation in symptoms makes it less likely for patients to be adherent to therapy.

Pic from relative -Artic Circle

Good Study, Bad Practice: Placebo for IBS and Functional Abdominal Pain

Have a great day (Mt Yonah, Cleveland GA)

S Nurko et al. JAMA Pediatr. 2022;176(4):349-356. doi:10.1001/jamapediatrics.2021.5750. Adolescents With Functional Abdominal Pain or Irritable Bowel Syndrome

Design: Patients completed 1 week of observation prior to randomization to 1 of 2 counterbalanced groups: OLP for 3 weeks followed by a 3-week control period or control period for 3 weeks followed by OLP for 3 weeks. During the OLP period, participants took 1.5 mL of an inert liquid placebo twice a day.

Key findings:

  • The mean (SD) pain scores were significantly lower during open label placebo (OLP) treatment compared with the control period (39.9 [18.9] vs 45.0 [14.7]; difference, 5.2; 95% CI, 0.2-10.1; P = .03)
  • Patients took nearly twice as many hyoscyamine pills during the control period compared with during the OLP period (mean [SD] number, 3.8 [5.1] pills vs 2.0 [3.0] pills; difference, 1.8 pills; 95% CI, 0.5-3.1 pills)

My take: It is a mistake to consider placebo as a treatment for functional abdominal pain. In many children, pain fluctuates and may improve with reassurance, distraction, healthier diets, and physical activity. However, we also need more effective therapies including pain psychology, dietary approaches and medications. The idea that placebo helps is misleading and undermines the fact that patients with functional disorders need effective treatment.

Related blog posts:

Why Ten Years of Choosing Wisely is a Disappointment

EJ Rourke. NEJM 2022; 386: 1293-1295. Open Access: Ten Years of Choosing Wisely to Reduce Low-Value Care

Key points from this commentary:

  • “Let me say at the outset that in my primary care clinic I practice low-value care. Not every day, but often enough. Probably every week”
  • “Choosing Wisely was an immediate public relations win for the medical profession in 2012, demonstrating that doctors were stepping up to address low value and high costs in medicine. Ten years later, however, it’s clear that making lists and publicizing them are not sufficient to reduce low-value care.1 “
  • “In the years since Choosing Wisely lists were first released, researchers have noted that specialty societies rarely select income-generating treatments provided by their members for inclusion on the lists.4“
  • “In short, Choosing Wisely has allowed doctors (and medical societies) to look like they are addressing low-value care without actually being forced to make any substantive changes.”
  • “My experience mirrors the findings of a 2015 study that used surveys, interviews, and focus groups to assess how patients understood low-value care. The study found ‘quite powerfully” that patients favored “replacing excessive tests with time for clinicians to talk, listen and personalize'”
  • “If Choosing Wisely is to continue, the specialty societies that have participated in it should celebrate its 10th anniversary by coming together to rethink and reinvent it.”

My take: While there are many factors that make it hard to eliminate low-value care, much is related to Upton Sinclair’s maxim: “It is difficult to get a man to understand something when his salary depends on his not understanding it.”

Related blog posts:

Omicron More Severe for Unvaccinated Children

NY Times: Omicron Was More Severe for Unvaccinated Children in 5-to-11 Age Group, Study Shows

  • “The C.D.C. study covered the period from mid-December to late February, during which about 400 children were hospitalized with Covid at the select hospitals participating in the study.”
  • “Among the children who tested positive for the virus before or during their hospitalization, three-quarters of them were admitted primarily for Covid, rather than other illnesses, the C.D.C. said.”

CDC MMWR (4/19/22): Hospitalizations of Children Aged 5–11 Years with Laboratory-Confirmed COVID-19 — COVID-NET, 14 States, March 2020–February 2022

Related blog post: COVID-19 Hospitalization Data from CDC on UnVax, Vax, and Vax + Boosted

Crepitus After G-tube Placement

Case: A 4 yo developed abdominal distention and crepitus after gastrostomy tube (GT) placement. An AXR (see below) showed subcutaneous emphysema (especially in left abdomen). There was no pneumoperitoneum or extravasation of contrast with fluoroscopy. Due to persistent distention, a CT scan was obtained three days after tube placement. The CT scan confirmed appropriate intragastric location of GT and nonspecific dilatation of bowel loops without pneumoperitoneum; the dilated bowel was attributed to an ileus and improved over the next few days. Thanks to colleague for sharing information.

My take: Isolated subcutaneous emphysema is rarely identified after GT placement and requires careful evaluation to assure appropriate insertion site (1,2).

  1. S Bernstein et al. AJR 2001;177:693–694 0361–803X/01/1773–693. Open Access: Subcutaneous Emphysema in a Pediatric Patient After Radiologic Placement of a Percutaneous Gastrostomy Tube
  2. MM Wojtowycz, JA Arata . AJR 1988; 151:311–312. Subcutaneous emphysema after percutaneous gastrostomy.

IBD Shorts: Ustekinumab in Kids, Subcutaenous Infliximab, Nutrition Highlights

MT Dolinger et al. J Crohns Colitis 2022.  doi: 10.1093/ecco-jcc/jjac055. Online ahead of print. Outcomes of Children With Inflammatory Bowel Disease Who Develop Anti-Tumor Necrosis Factor Induced Skin Reactions

In this retrospective study, among those who developed skin reactions to anti-TNF agents, 71 (64%) continued anti-TNF and 40 (36%) switched to ustekinumab (UST). Key findings:

  • Switching to UST had a higher rate and odds of resolution of skin findings (29/40 (73%) vs. 24/71 (34%); p <0.0001) and combined remission (21 (52%) vs. 22 (31%); p=0.03) vs. continuing anti-TNF at 6 months

PJ Smith et al. J Crohns Colitis, jjac053, https://doi.org/10.1093/ecco-jcc/jjac053 Open Access: Efficacy and Safety of Elective Switching From Intravenous to Subcutaneous Infliximab (Ct-P13): A Multi-Centre Cohort Study

Patients (n=181) on established maintenance IV infliximab who switched to SC CT-P13 were included in this retrospective multi-centre cohort study. Key findings:

  • Treatment persistence rate was high (N=167, 92.3%) and only 14 patients (7.7%) stopped treatment during the follow-up period. There were low rates of immunogenicity with no change in clinical disease activity indices or biomarkers

Link: Crohn’s and Colitis Congress 2022 Nutritional Highlights (Nutritional Therapy for IBD Website). This website has a summaries, and links to extensive information (videos/posters) from recent IBD meeting.

Sunrise in Sandy Springs (4/9/22) -no filter

Lessons Learned from Children In the Hepatitis B Virus Research Network

SJ Schwarzenberg et al. JPGN 2022. 74: 431-433. Lessons Learned from Children Enrolled into the Hepatitis B Virus Research Network Multi-Center Prospective Study

This NIDDK-funded Hepatitis B Research Network (HBRN) was established in 2009 and enrolled 362 patients. 97% of participants were born in countries where HBV is endemic or in North America to mothers born from these countries.

Key points:

  • Due to revised criteria for ALT values, most pediatric patients have elevated ALT and do not meet the definition of immune-tolerant
  • Spontaneous flares (ALT >400 in males and >350 in females) in untreated children…did not lead to hepatic decompensation
  • Hepatocellular carcinoma was not identified in this cohort, though HBRN centers reported historical experiences. Only one patient developed cirrhosis over 4 years of followup.

Clinical Recommendations from Authors:

  • Screen for HBV in children with unexplained serum aminotransferases regardless of immunization history
  • Screen for HBV in children with normal aminotransferases if they or their parents are from an area where HBV is endemic or other risk factors
  • In those with HBV, monitor aminotransferases and HBV levels every 6 months
  • Obtain genotype in children with HBV
  • Consider treatment if ALT >2 x ULN over 3-6 mo. Treatment should follow AASLD guideline
  • Recommend AGAINST treatment at the start of a flare
  • Recommend counseling to promote healthy weight and avoidance of at-risk alcohol use

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.