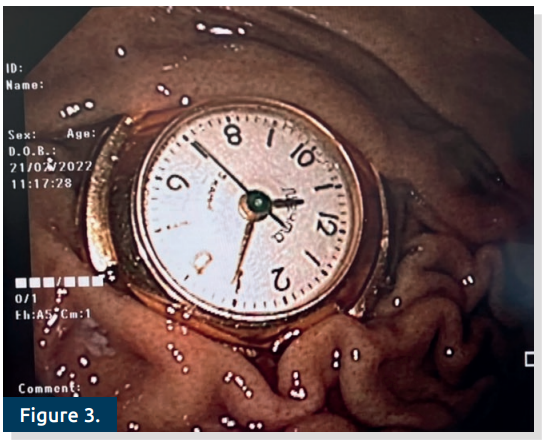
Case: A 4 yo developed abdominal distention and crepitus after gastrostomy tube (GT) placement. An AXR (see below) showed subcutaneous emphysema (especially in left abdomen). There was no pneumoperitoneum or extravasation of contrast with fluoroscopy. Due to persistent distention, a CT scan was obtained three days after tube placement. The CT scan confirmed appropriate intragastric location of GT and nonspecific dilatation of bowel loops without pneumoperitoneum; the dilated bowel was attributed to an ileus and improved over the next few days. Thanks to colleague for sharing information.
My take: Isolated subcutaneous emphysema is rarely identified after GT placement and requires careful evaluation to assure appropriate insertion site (1,2).
In this retrospective study, among those who developed skin reactions to anti-TNF agents, 71 (64%) continued anti-TNF and 40 (36%) switched to ustekinumab (UST). Key findings:
Switching to UST had a higher rate and odds of resolution of skin findings (29/40 (73%) vs. 24/71 (34%); p <0.0001) and combined remission (21 (52%) vs. 22 (31%); p=0.03) vs. continuing anti-TNF at 6 months
Patients (n=181) on established maintenance IV infliximab who switched to SC CT-P13 were included in this retrospective multi-centre cohort study. Key findings:
Treatment persistence rate was high (N=167, 92.3%) and only 14 patients (7.7%) stopped treatment during the follow-up period. There were low rates of immunogenicity with no change in clinical disease activity indices or biomarkers
This prospective study (n=80) expands on previous observations regarding the use of a transanal irrigation device for neurogenic bowel management.
Key points:
The neurogenic bowel dysfunction (NBD) score improved at both time points (<6 months, >6 months) by 14 and 13 points respectively. 94% and 98% had improved NBD score at time 1 and time 2 respectively
Patient satisfaction was high, though 8 patients discontinued device early on due to either discomfort or poor results
NBD score can used to monitor treatment effectiveness
This article describes a retrospective review of seven patients with a dual diagnosis of inflammatory bowel disease (IBD) and chronic recurrent multifocal osteomyelitis (CRMO). In their cohort 4 of 6 were receiving anti-TNF therapy at the time of CRMO diagnosis. Misleading statements from this article:
The triad of IBD, CRMO and psoriasis has not been reported previously to their knowledge
“It seems unlikely that anti-TNF-alpha therapy would promote its [CRMO] development”
In JPGN Reports (not available on pubmed), Cordesse et al (JPGN Reports; November 2020 – Volume 1 – Issue 2 – p e007) identified the association of IBD, CRMO and psoriasis; in addition, they identified a paradoxical reaction to anti-TNF-alpha therapy; in this case series of three patients, anti-TNF-alpha therapy triggered CRMO and stopping anti-TNF-alpha therapy led to resolution of CRMO in two of the cases.
In a response to a letter to the editor (Hochman JA. JPGN 2022; DOI: 10.1097/MPG.0000000000003407. Faulty Information Regarding CRMO and IBD), Dushnicky et al (DOI: 10.1097/MPG.0000000000003433) note that JPGN Reports is not available on Pubmed; however, the articles that have described this association are near the top of a google search if one looks for “IBD, CRMO and Psoriasis.” Interestingly, in their response to the letter to the editor, the authors did not amend their claim that anti-TNF therapy is unlikely to promote CRMO despite being furnished with information showing that it can. In my view, the situation with CRMO is similar to psoriasis which can be treated with anti-TNF therapy and can paradoxically be caused by anti-TNF agents as well.
My take:
CRMO is important to recognize due to its association with IBD and to realize that antibiotics are not an effective treatment.
Anti-TNF-alpha agents can cause CRMO in some patients.
In 2022, a web browser search (eg Google), in addition to Pubmed, is probably worthwhile when claiming that this is the first case of xyz ‘to our knowledge.’
In this pilot study, 12 individuals completed a web-based curriculum for VCE proficiency.
Key finding:
Participants showed significant improvement in knowledge (P = 0.041) and photo recognition posttests (P = 0.015). All participants who completed the curriculum found it helpful and reported that they would recommend it to their colleagues
The discussion notes that “Studies have demonstrated that competence with VCE develops in an endoscopist after reading 10–15 VCE studies (6,10). There are some newer guidelines that suggest that this number may be higher…[and] it requires continuous practice. Pediatric gastroenterologists may feel their skills are not adequate when VCEs are not performed on a consistent basis at their institution”
Previous studies have shown an association between the early use of antibiotics and an increased risk of inflammatory bowel disease. A recent study examined all the children born in Denmark from 1995-2009 and followed them up to 2013 via a prospectively maintained database.
During a median 9.5 years (9.3 million total person-years), CD was diagnosed in 208 of 979,039 children.
Key findings:
Antibiotic use in the first year of life was associated with a higher risk of CD (adjusted hazard ratio, 1.4)…with the highest risk with ≥6 courses of antibiotics (adjusted hazard ratio, 4.1)
The cumulative risk of CD at the 11th birthday for children exposed to antibiotics in their first year of life was 0.16% compared to 0.11% for children unexposed to antibiotics in their first year of life.
My take: This study indicates that antibiotics (and/or serious infections) are associated with an increased the risk of pediatric Crohn’s disease but the absolute risk is very low. We still have a lot to learn about how environmental exposures, including diet, infections, antibiotics, and pollution, contribute to the increasing prevalence of inflammatory bowel disease.
It is well-recognized that genetic mutations that persist often confer some advantages. For example, sickle cell trait (but not disease) provides protection against malaria.
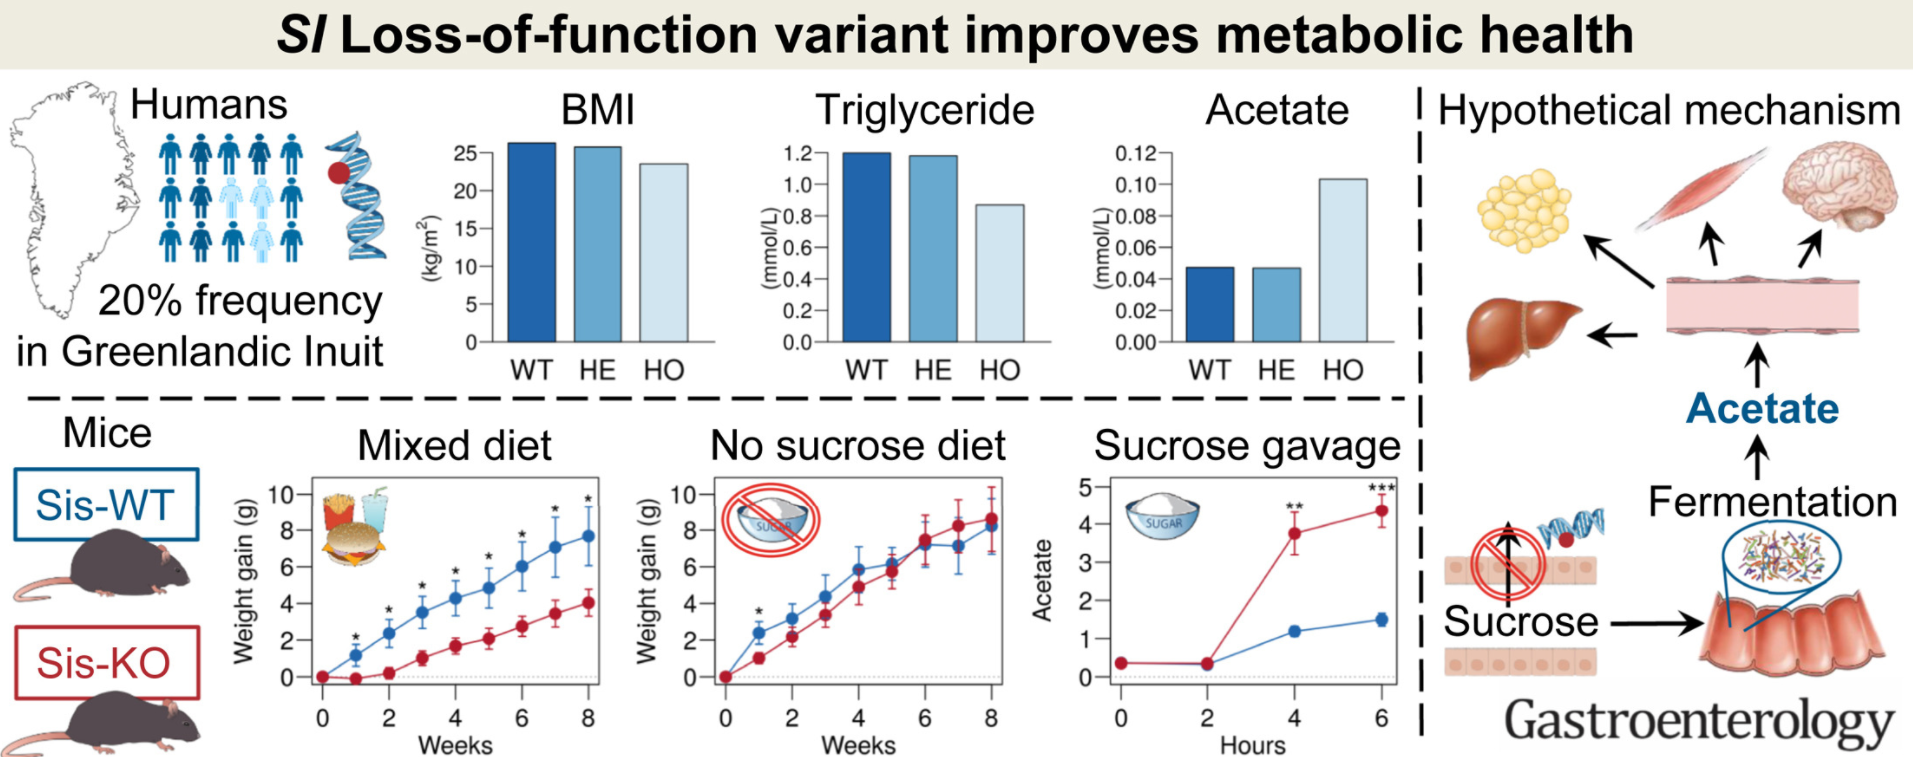
Methods: “The association between c.273_274delAG and phenotypes related to metabolic health was assessed in 2 cohorts of Greenlandic adults (n = 4922 and n = 1629). A sucrase-isomaltase knockout (Sis-KO) mouse model was used to further elucidate the findings”
Key findings:
Homozygous carriers of the variant had a markedly healthier metabolic profile than the remaining population, including lower body mass index ( –2.0 kg/m2; P = 3.1 × 10⁻⁵), body weight (–4.8 kg; P = 5.1 × 10⁻⁴), fat percentage (–3.3%; P = 3.7 × 10⁻⁴), fasting triglyceride (–0.27 mmol/L; P = 2.3 × 10⁻⁶), and remnant cholesterol (–0.11 mmol/L; P = 4.2 × 10⁻⁵).
The metabolic profile “was likely mediated partly by higher circulating levels of acetate observed in homozygous carriers” (0.056 mmol/L; P = 2.1 × 10⁻²⁶), and partly by reduced sucrose uptake, but not lower caloric intake.
“These findings were verified in Sis-KO mice, which, compared with wild-type mice, were leaner on a sucrose-containing diet, despite similar caloric intake, had significantly higher plasma acetate levels in response to a sucrose gavage, and had lower plasma glucose level in response to a sucrose-tolerance test.”
My take: It should not be surprising that a genetic condition that results in limited sucrose intake would have health benefits. Perhaps correcting this condition will result in unexpected health issues similar to health issues that can develop in those with celiac disease after institution of a gluten-free diet (Gastroenterol 2013; 144: 912-17).
Background: “Proton pump inhibitors (PPIs) are among the most commonly used medications in the United States, if not the world. Observational studies have demonstrated that PPI use has increased over time and that 7%–15% of patients use these medications at any time, with the prevalence increasing to 40% for patients 70 years or older…In a large observational study examining ambulatory visits of PPI users, nearly two-thirds had no clear indication for PPI use.”
Some of the best practice advice:
Best Practice Advice 2 All patients taking a PPI should have a regular review of the ongoing indications for use and documentation of that indication. This review should be the responsibility of the patient’s primary care provider.
Best Practice Advice 3 Most patients with an indication for chronic PPI use who take twice-daily dosing should be considered for step down to once-daily PPI.
Best Practice Advice 4 Patients with complicated gastroesophageal reflux disease, such as those with a history of severe erosive esophagitis, esophageal ulcer, or peptic stricture, should generally not be considered for PPI discontinuation.
Best Practice Advice 5 Patients with known Barrett’s esophagus, eosinophilic esophagitis, or idiopathic pulmonary fibrosis should generally not be considered for a trial of de-prescribing.
Best Practice Advice 7 Patients at high risk for upper gastrointestinal bleeding should not be considered for PPI de-prescribing.
Best Practice Advice 10 The decision to discontinue PPIs should be based solely on the lack of an indication for PPI use, and not because of concern for PAAEs (PPI-associated adverse events).
My take: There are a lot of individuals who could benefit from de-prescribing PPIs.
When I first saw this title, I mistakenly thought the title indicated that celiac disease (CD) occurred less often in those with inflammatory bowel disease (IBD). This would have been surprising given previous studies have found the opposite. In fact, this study confirms the bidirectional associated risk between patients with CD and in patients with IBD but with a twist. Most IBD treatments were associated with a lower risk of developing CD than those who were not treated.
Database study: Of the 72,965,940 individuals in the database (1999-2020), 133,400 had celiac disease (CD) (0.18%), 191,570 (0.26%) had ulcerative colitis (UC), and 230,670 (0.32%) had Crohn disease.
Key findings:
Patients with IBD were more likely to have a diagnosis of celiac disease (odds ratio [OR], 13.680), with a greater association with Crohn disease (OR 24.473).
Treated patients with IBD with UC and with Crohn disease, respectively, had a lower risk association with CD compared to those not undergoing IBD treatment, specifically corticosteroids (OR, 0.407 and 0.585), 5-aminosalicylates (OR, 0.124 and 0.127), immunomodulators (OR, 0.385 and 0.425), and anti-tumor necrosis factor drugs (OR, 0.215 and 0.242)
A new diagnosis of CD after 1 year of IBD diagnosis, was 1.59% for Crohn disease and 0.90% for UC compared to 0.16% in patients without IBD (P<0.0001)
A new diagnosis of IBD, Crohn disease and UC respectively, in patients with celiac disease was 2.75% and 1.11% compared to 0.29% and 0.25% in the non-celiac population (P<0.0001)
A new diagnosis of IBD and celiac disease among patients with microscopic colitis was 10.5% and 2.6% respectively; a new diagnosis of microscopic colitis among patients with celiac disease was 0.01%
My take: This study confirms the bidirectional associated risk between IBD and celiac disease. The risk of developing celiac disease in those with IBD may be lower in those receiving some treatments; however, this assertion is limited by the nature of a database study.