Comparative Efficacy: Infliximab vs. Ustekinumab

ECL Wong et al. Inflamm Bowel Dis 2023; 29: 1015-1023. Open Access! Comparative Efficacy of Infliximab vs Ustekinumab for Maintenance of Clinical Response in Biologic Naïve Crohn’s Disease

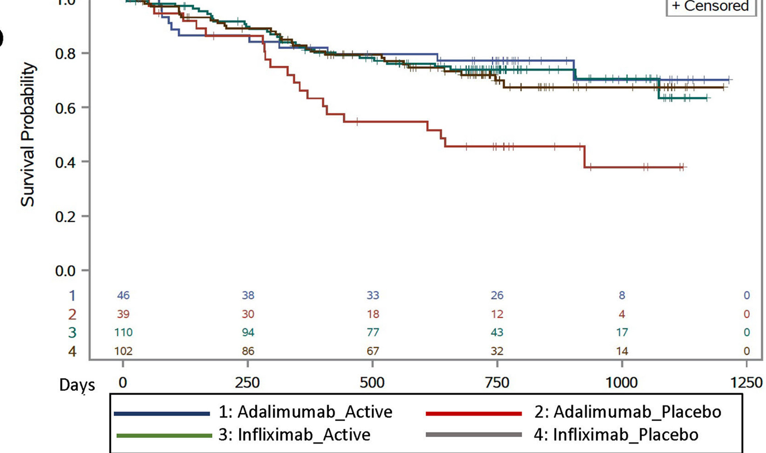
This post hoc analysis included data from separate trials examined the response of 220 biologic-naïve CD participants to either inflximab biosimilar or ustekinumab.

Key findings:

  • Clinical remission: One-year clinical remission (CR) and corticosteroid-free CR rates were similar between infliximab-treated and ustekinumab-treated patients (CR, 66 of 110 [60.0%] vs 63 of 110 [57.3%]; adjusted odds ratio [aOR], 1.15), corticosteroid-free CR, 11 of 28 (39.3%) vs 27 of 51 [52.9%]; aOR, 0.58)
  • Endoscopic response/remission:  infliximab-treated participants were more likely to achieve 1-year endoscopic response (43 of 92 [46.7%] vs 6 of 30 [20.0%], aOR, 3.59) and endoscopic remission (31 of 92 [33.7%] vs 4 of 30 [13.3%]; aOR, 3.35)

In the discussion, the authors note only 1 head-to-head study in CD with ustekinumab. “The SEAVUE trial (NCT03464136) compared adalimumab and ustekinumab among biologic-naïve CD patients. Ustekinumab demonstrated similar efficacy for the achievement of clinical and endoscopic outcomes compared with adalimumab.23 Similar rates of CR at 1 year were reported in SEAVUE (64.9% ustekinumab vs 61% adalimumab) as in our analysis (57.3% ustekinumab vs 60% infliximab)…ustekinumab demonstrated longer retention and lower immunogenicity and has practical advantages over adalimumab, including less frequent dosing intervals (every 8 weeks for ustekinumab vs every 2 weeks for adalimumab) while providing similar efficacy.”

My take: This study suggests that infliximab may be a little better than ustekimumab in biologic-naive patients due to the higher endoscopic response; however, the study was unpowered to provide a definitive answer. A prior study suggested similar endoscopic healing rates (P Riviere et al. Inflamm Bowel Dis 2023; 29: 923-931).

Related blog posts:

Waters off the Cap d’Ail Trail (near Eze, France)

More Data: Upadacitinib “is Effective and Safe” Plus 2 in Kids

S Friedberg et al. Clin Gastroenterol Hepatol 2023; 21: 1913-1923. Open Access! Upadacitinib Is Effective and Safe in Both Ulcerative Colitis and Crohn’s Disease: Prospective Real-World Experience

Methods: “We performed a prospective analysis of clinical outcomes on upadacitinib in patients with UC and CD using predetermined intervals at weeks 0, 2, 4, and 8 as part of a formalized treatment protocol.” 84 met inclusion criteria  (44 UC patients, 40 CD patients) -though complete data was available for only a fraction of these. All of the patients had received prior anti-TNF therapy and 89% had received 2 or more advanced therapies. 

Key findings:

  • Ulcerative colitis: At 4 and 8 weeks of treatment, 19 of 25 (76.0%) and 23 of 27 (85.2%) achieved clinical response and 18 of 26 (69.2%) and 22 of 27 (81.5%) achieved clinical remission, respectively. Of those who previously were tofacitinib-exposed, 7 of 9 (77.8%) achieved clinical remission by 8 weeks.
  • Crohn’s disease: In CD, 13 of 17 (76.5.%) achieved clinical response and 12 of 17 (70.6%) achieved clinical remission by 8 weeks. Of those with increased fecal calprotectin and C-reactive protein levels, 62% and 64% normalized by week 8, respectively. 
  • Results were seen as early as week 2 in both UC and CD, with clinical remission rates of 36% and 56.3.%,
  • Acne was the most commonly reported adverse event, occurring in 24 of 105 patients (22.9%) (Table 4). Six patients stopped upadacitinib due to adverse effects.

My take: “In this large real-world experience in medically resistant patients with UC or CD, we report that upadacitinib is rapidly effective and safe, including in those who had prior tofacitinib exposure.” In pediatrics, the effectiveness of this upadacitinib is a logical target for ImproveCareNow. More pediatric data will be needed to garner FDA approval.

Related articles:

LV Collen. Inflamm Bowel Dis 2023; 29: 1175-1176. Rapid Clinical Remission With Upadacitinib in a Pediatric Patient With Refractory Crohn’s Disease A pediatric patient with Crohn’s disease refractory to anti-tumor necrosis factor therapy, vedolizumab, ustekinumab, and 6-mercaptopurine achieved rapid clinical remission with upadacitinib.

A Bousvaros, BAR Schmidt, M Kurtz. Gastroenterology & Hepatology 2023; 19: 401-403. Open Access! “Treatment of Genital Crohn’s Disease with Upadacitinib in a Male Child: A Case Report”. This report describes the rapid response to upadacitinib in a 12 yo with refractory Crohn’s ileocolitis (x 5 yrs) with associated “granulomatous lymphangitis” affecting the penis and scrotum. It notes that “anti-TNF therapy was described as the most effective treatment, with either improvement or resolution of scrotal swelling in most patients. However, intermittent penile swelling persisted in a subset of the patients.18“…”Although data on the use of JAK inhibitors to treat pediatric IBD are limited, the fact that these are small molecules with wide systemic effects suggests that JAK inhibitors may be useful in the treatment of extraintestinal manifestations of IBD….[and]  that JAK inhibitors such as upadacitinib may play an important role in the treatment of such refractory patients.”

Related blog posts:

On an adventurous day, we climbed the Nietzsche trail to get from the coast to the top of Eze, France.

The Expanding Adalimumab Options

S White, R Morrow, I Pan, EF de Zoeten. JPGN 2023; 76: 701-703.
Riding the Wave of Adalimumab Biosimilars: Considerations for Pediatric Gastroenterologists

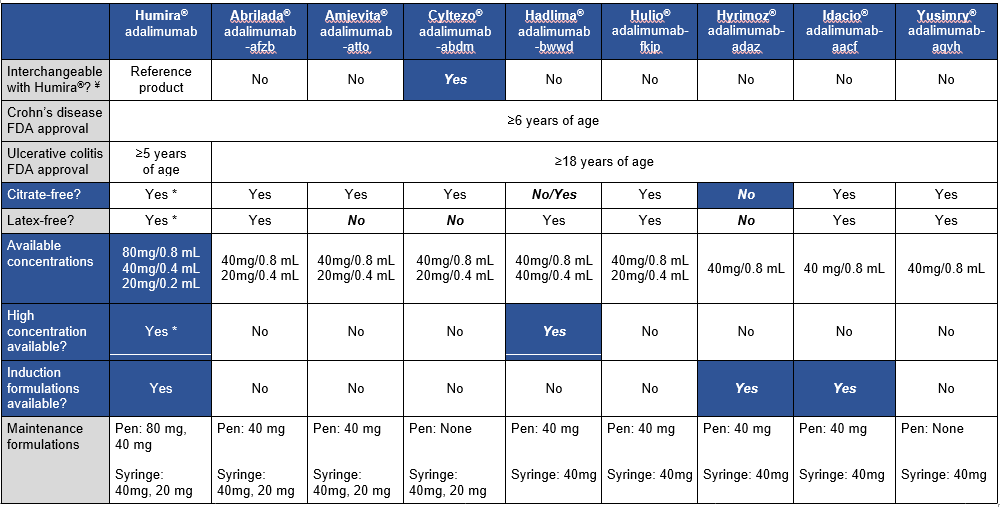
This article is a very handy update on approved adalimumab biosimilars, though even more biosimilars are expected to become available soon. The table below which is similar to a table in the article outlines the similarities and differences in these products compared to the reference product.

These biosimilars are FDA-approved for the treatment of adult and pediatric patients aged 6 and older with Crohn disease. “However, the biosimilar products are only approved for treatment of adult patients” (18 and older) with ulcerative colitis. “This may be due to the recent change in pediatric ulcerative colitis Humira FDA-approved dosing.”

My take (borrowed in part from authors): Insurance coverage decisions are likely to overlook some of these factors which are very important for pediatric patients. “The adalimumab biosimilars will likely provide a clinically effective, cost saving option for our patients, but consideration of a number of factors will be key when selecting between” them.

Related posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Which is a More Effective First-Line for Crohn’s Disease: Ustekinumab or anti-TNF agents?

P Riviere et al. Inflamm Bowel Dis 2023; 29: 923-931. Comparative Effectiveness of Ustekinumab and Anti-TNF Agent as First-Line Biological Therapy in Luminal Crohn’s Disease: A Retrospective Study From 2 Referral Centers

A previous study (SEAVUE) has suggested similar efficacy of ustekinumab and adalimumab in biologic-naive patients (post: SEAVUE: Head-to-Head Ustekimumab vs. Adalimumab) with ~60-65% clinical response at 52 weeks and ~30% endoscopic remission.

This current retrospective study sought to obtain ‘real-world’ data comparing anti-TNF agents (95 adalimumab, 61 infliximab) to ustekinumab (n=50). In the anti-TNF group, 44% (n=68) received concomitant immunomodulator therapy. Key findings:

  •  At 3 months, clinical response rates were 86% in anti-TNF groups and 64% in the ustekinumab.
  • At 12 months, in adjusted multivariate analysis, clinical remission (based on Harvey-Bradshaw Index) was independently associated with the biological therapy received (odds ratio, 2.6 for anti-TNF agent vs ustekinumab; P = .02).
  • “In our sensitivity analysis, a significant difference in terms of efficacy was only found between infliximab and ustekinumab.”
  • In those with ileocolonoscopy, endoscopic healing was similar (between 6-18 months): 58% of anti-TNF group and 61% of ustekinumab group.
  • 2% of patients in the anti-TNF group had severe adverse events compared to none in the ustekinumab group; among patients receiving adalimumab, 1 patient had cerebral aspergillosis, 1 had a postinfectious macrophage activation syndrome, and 1 had severe folliculitis needing abscess drainage.
  • Drug persistence at 12 months was 87% in anti-TNF group and 88% in ustekinumab group.

The discussion notes that ‘real-world’ data is important as only ~30% of patients in a regular practice would fulfill the criteria to be included in clinical trials. However, in this retrospective (non-randomized) study, there were differences in the patient population that could affect response to treatment, including a higher rate of smokers in the anti-TNF group (29% compared to 12% in the ustekinumab group).

My take: While anti-TNF therapy, particularly infliximab, may be a little better based on clinical remission, the most objective marker of efficacy, endoscopic healing, was similar. Thus, it is not clear if anti-TNF therapy is more effective than ustekinumab. To achieve optimal results, many in the anti-TNF group received immunomodulator cotherapy and dose escalation.

Related blog posts:

Joel Andres, Chef & Philanthropist, World Central Kitchen

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Early Postoperative Anti-TNF Therapy

JE Axelrad et al. Inflamm Bowel Dis 2023; 29: 888-897. Early Initiation of Antitumor Necrosis Factor Therapy Reduces Postoperative Recurrence of Crohn’s Disease Following Ileocecal Resection

This retrospective cohort study identified 1037 patients with Crohn’s disease who underwent ileocecal resection (ICR). Only 5.4% were younger than 18 yrs at the time of surgery. In this cohort, 278 (26%) received a biologic agent as prophylaxis to prevent recurrence with 80% receiving an anti-TNF agent. In those receiving an anti-TNF agent, 35% were started on therapy within 4 weeks of surgery and 65% were started between 4 and 12 weeks. Recurrence was defined by endoscopy (≥ i2b Rutgeerts score) or radiography (active inflammation in neoterminal ileum). Key findings:

  • After adjusting for factors associated with postoperative recurrence (POR), compared with no biologic prophylaxis, the initiation of an anti-TNF agent (n=223) within 4 weeks following an ICR was associated with a reduction in POR (adjusted hazard ratio, 0.61).
  • Prophylaxis after 4 weeks following an ICR or with vedolizumab or ustekinumab was not associated with a reduction in POR compared with those who did not receive prophylaxis –though sample size with vedolizumab (n=27) and ustekinumab (n=28) was very limited
  • Most patients receiving biologic prophylaxis had prior anti-TNF exposure including 73% of the anti-TNF group, 96% of the vedolizumab group, and 93% of the ustekinumab group.

In their discussion, the authors note that their findings reinforce previous studies which showed beneficial effects of anti-TNF therapy for POR, including the PREVENT trial. This randomized controlled trial with infliximab initiation within 45 days postoperatively in high risk individuals reduced endoscopic recurrence at 18 months (22.4% compared with 51% in placebo group).

My take: Anti-TNF therapy, even in those with prior exposure, likely improves outcomes in patients with Crohn’s disease following ileocecal resection. This study indicates that starting therapy within the first 4 weeks is more beneficial.

Related blog posts:

Watersound, FL

Why Do Children Taking Adalimumab Benefit from Methotrexate Dual Therapy?

MD Kappelman et al. Gastroenterology. 2023: 165: 149-161. Open Access! Comparative Effectiveness of Anti-TNF in Combination With Low-Dose Methotrexate vs Anti-TNF Monotherapy in Pediatric Crohn’s Disease: A Pragmatic Randomized Trial

This study enrolled 297 children with Crohn’s disease starting anti-TNF therapy.  Patients initiating infliximab or adalimumab were randomized in 1:1 allocation to methotrexate or placebo and followed for 12–36 months. 

Methotrexate dosing: For those in the active arm, oral methotrexate was administered with a weekly dose of 15 mg for children ≥40 kg, 12.5 mg for children 30 to <40 kg, and 10 mg for children 20 to <30 kg. All participants received pretreatment with ondansetron 4 mg (or placebo) to prevent nausea and folic acid (1 mg/d).

Key findings:

  • For treatment failure: among infliximab initiators, there were no differences between combination and monotherapy (hazard ratio, 0.93; 95% CI, 0.55–1.56)
  • For treatment failure: among adalimumab initiators, combination therapy was associated with longer time to treatment failure (hazard ratio, 0.40; 95% CI, 0.19–0.81).
  • A trend toward lower anti-drug antibody development in the combination therapy arm was not significant (infliximab: odds ratio, 0.72; 95% CI, 0.49–1.07; adalimumab: odds ratio, 0.71; 95% CI, 0.24–2.07).
  • In our study, only 38% of participants underwent colonoscopy during follow-up (41% had calprotectin measurement). 

My thoughts on this study:

My take: Given the increased difficulty monitoring the kids on adalimumab, they are probably better off on dual therapy.  My suspicion, though, is that if they had optimized levels, the benefit of dual therapy is probably small and would mirror the findings with IFX.

Do We Know How To Dilate Strictures Associated With Pediatric Crohn’s Disease?

O Ledder et al. JPGN 2023; 76: 799-806. Approach to Endoscopic Balloon Dilatation in Pediatric Stricturing Crohn Disease: A Position Paper of the Endoscopy Special Interest Group of ESPGHAN

This position paper regarding dilatation of strictures in Crohn’s disease provides mostly vague advice.

Here are a few examples:

  • Imaging: “The need for fluoroscopy is dependent on the stricture phenotype and the treating team…The advantage of live imaging is obvious: it provides greater certainty of balloon position and dilatation success; however, it is difficult and impractical in some centers…In simple strictures, where balloon passage and deployment can be performed with reasonable confidence under direct vision,…it is reasonable to dispense with imaging.”
  • Dilatation Size: “In the recent pediatric case series…a median of 15 mm was used” as a target dilatation….”It is wise to set reasonable goals for dilatation…Inherited wisdom recommended limiting esophageal dilatation to no more than 3 mm per session. However,…subsequently challenged in several studies demonstrating safe dilatation up to 5 mm per session…As an informal rule, the authors limit dilatation to 2 balloon sizes per session which roughly translates to 5-6 mm. An alternative approach…is to dilate to a maximum of three times the initial stricture diameter; however, neither of these approaches are based on any robust data.”

The main clear cut recommendations are to obtain careful consent, expecting a complication rate of ~4% (eg. bleeding, sepsis, perforation), and to have surgical backup.

My take: This “position paper” offers very few positions on management advice and gives little clear guidance in terms of dilating strictures in Crohn’s disease.

Related blog posts:

Infliximab Home Infusions

SR Gupta et al. JPGN 2023; 76: 776-781. Outcomes for Standardized Home and Hospital-Based Infusions of Infliximab for Children With Inflammatory Bowel Disease

In this retrospective study with 102 children, key findings:

  • There were similar outcomes among carefully-selected children receiving home infusions (HI), “drug durability, AOs [adverse outcomes], and laboratory values were similar between HI and hospital-based infusions.” 30% of eligible patients received HI.
  • Within 2 years, only 19% remained on 5 mg/kg every 8 week dosing and the remainder required increased dosing or decreased interval.  (Further supporting data showing that 5 mg/kg every 8 week dosing is inadequate in ~80%)

The authors note that HI were arranged with a single home health company with pediatric PALS-trained nurses. In addition, there was “direct communication between the home health nurse and IBD nurse after each infusion.”

Prior studies of HI have shown increased AOs in patients receiving HI including stopping therapy, ER visits, and hospitalizations (Clin Gastroenterol Hepatol 2020; 18: 257-258, Am J Gastroenterol 2020; 115: 1698-1706, JAMA New Open 2021; 4: e2110268).

My take: If set up properly, home infusions could be a reasonable alternative to hospital-based or office-based infusions.

In this article, from May 31, 2023: Sick Workers Tied to 40% of Food Poisoning Outbreaks, C.D.C. Says

“Each year, 48 million people become sick from a food-borne illness, according to C.D.C. estimates. Of those, 128,000 are hospitalized and 3,000 die.”

IBD Updates: Treat-to-Target Uptake, Long-Term Data on Ustekinumab Intensification, and Low Rates of C diff with Tofacitinib (& Clinical Pearl)

JL Yang et al. Inflamm Bowel Dis 2023; 29: 735-743. Utilization of Colonoscopy Following Treatment Initiation in U.S. Commercially Insured Patients With Inflammatory Bowel Disease, 2013-2019

In this study with 39,734 commercially-insured initiators of IBD medications (18-64 year old), 34% had a colonoscopy by 12 months and 42% at 15 months. The authors state that “it is evident that patients without any colonoscopy during this interval are not being followed under an optimal long-term T2T (treat-to-target) paradigm.”

RS Dalal et al. Inflamm Bowel Dis 2023; 29: 830-833. Long-Term Outcomes After Ustekinumab Dose Intensification for Inflammatory Bowel Diseases

This retrospective study examined 123 patients with Crohn’s disease and 40 with ulcerative colitis who had dose intensification with ustekinumab (to either every 4 weeks, n=91, or every 6 weeks, n=72). Dose escalation was effective in both achieving and maintaining corticosteroid-free clinical remission for 61% of patients with Crohn’s disease and 40% with ulcerative colitis at 24 months; endoscopic remission was noted in 43% with Crohn’s disease and 55% with ulcerative colitis.

EV Loftus et al. Inflamm Bowel Dis 2023; 29: 744-751. Open Access! Clostridium difficile Infection in Patients with Ulcerative Colitis Treated with Tofacitinib in the Ulcerative Colitis Program 

Using data from multiple studies with 1157 patients, only 9 tofacitinib patients developed Clostridioides difficile infection (CDI) which was lower than the placebo group. CDI were all mild–moderate in severity and resolved with treatment in 8 patients. Six of 9 patients continued tofacitinib treatment without interruption. The low rate of infection was likely in part due to screening for CDI prior to treatment. In addition, “it is possible than the lower rates of CDI …may be due to better-controlled disease…, thus reducing susceptibility to infection.”

One clinical pearl in the discussion: “When considering treatment [for CDI], initial therapy with oral vancomycin should be considered instead of metronidazole, and treating for at least 21 days should also be considered [in patients with IBD due to]…lower rates of CDI recurrence.”

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Lego Art at Tucson Botanical Gardens

How Long to Hold Biologics and Small Molecule Drugs Perioperatively

BL Cohen et al. Clin Gastroenterol Hepatol l2023; 21: 1148-1151. How to Manage Targeted Immune Suppressants (Biologics and Oral Small-molecule Drugs) Perioperatively for Inflammatory Bowel Disease and non-Inflammatory Bowel Disease surgery

This article makes pragmatic recommendations with regard to surgery timing in individuals taking medications that target the immune system.

Key points:

  • Several recent large studies have “observed no association between biologic exposure and postoperative infectious outcomes.”
  • The primary risk factor for infectious complications has been corticosteroid/glucocorticoid use.
  • For IBD Surgery: “If patients are deriving therapeutic benefit, including reducing the need for steroids, we propose continuing treatment until surgery…It may be practical to perform the surgery mid to late dosing interaval in the case of biologics with longer half-lives…Our expert opinion is that therapy may be resumed 14 days postoperatively or when recovered from infectious complications.”
  • For Non-IBD surgery: “Expert opinion suggests medications may be re-dosed by 14 days postoperatively if there have been no complications. Consideration should be given to resuming oral small molecules earlier given their short half-lives.”
  • Emergency or urgent surgeries “should be performed promptly regardless of targeted immune suppressant use.”
David Yetman Trail (Tucson)

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.